




The last chapter
My new deadline: 20 years to give away virtually all my wealth
During the first 25 years of the Gates Foundation, we gave away more than $100 billion. Over the next two decades, we will double our giving.

When I first began thinking about how to give away my wealth, I did what I always do when I start a new project: I read a lot of books. I read books about great philanthropists and their foundations to inform my decisions about how exactly to give back. And I read books about global health to help me better understand the problems I wanted to solve.
One of the best things I read was an 1889 essay by Andrew Carnegie called The Gospel of Wealth. It makes the case that the wealthy have a responsibility to return their resources to society, a radical idea at the time that laid the groundwork for philanthropy as we know it today.
In the essay’s most famous line, Carnegie argues that “the man who dies thus rich dies disgraced.” I have spent a lot of time thinking about that quote lately. People will say a lot of things about me when I die, but I am determined that "he died rich" will not be one of them. There are too many urgent problems to solve for me to hold onto resources that could be used to help people.
That is why I have decided to give my money back to society much faster than I had originally planned. I will give away virtually all my wealth through the Gates Foundation over the next 20 years to the cause of saving and improving lives around the world. And on December 31, 2045, the foundation will close its doors permanently.
This is a change from our original plans. When Melinda and I started the Gates Foundation in 2000, we included a clause in the foundation’s very first charter: The organization would sunset several decades after our deaths. A few years ago, I began to rethink that approach. More recently, with the input from our board, I now believe we can achieve the foundation’s goals on a shorter timeline, especially if we double down on key investments and provide more certainty to our partners.
During the first 25 years of the Gates Foundation—powered in part by the generosity of Warren Buffett—we gave away more than $100 billion. Over the next two decades, we will double our giving. The exact amount will depend on the markets and inflation, but I expect the foundation will spend more than $200 billion between now and 2045. This figure includes the balance of the endowment and my future contributions.
This decision comes at a moment of reflection for me. In addition to celebrating the foundation’s 25th anniversary, this year also marks several other milestones: It would have been the year my dad, who helped me start the foundation, turned 100; Microsoft is turning 50; and I turn 70 in October.
This means that I have officially reached an age when many people are retired. While I respect anyone’s decision to spend their days playing pickleball, that life isn’t quite for me—at least not full time. I’m lucky to wake up every day energized to go to work. And I look forward to filling my days with strategy reviews, meetings with partners, and learning trips for as long as I can.
The Gates Foundation’s mission remains rooted in the idea that where you are born should not determine your opportunities. I am excited to see how our next chapter continues to move the world closer to a future where everyone everywhere has the chance to live a healthy and productive life.
Planning for the next 20 years
I am deeply proud of what we have accomplished in our first 25 years.
We were central to the creation of Gavi and the Global Fund, both of which transformed the way the world procures and delivers lifesaving tools like vaccines and anti-retrovirals. Together, these two groups have saved more than 80 million lives so far. Along with Rotary International, we have been a key partner in reviving the effort to eradicate polio. We supported the creation of a new vaccine for rotavirus that has helped reduce the number of children who die from diarrhea each year by 75 percent. Every step of the way, we brought together other foundations, non-profits, governments, multilateral agencies, and the private sector as partners to solve big problems—as we will continue to do for the next twenty years.
Over the next twenty years, the Gates Foundation will aim to save and improve as many lives as possible. By accelerating our giving, my hope is we can put the world on a path to ending preventable deaths of moms and babies and lifting millions of people out of poverty. I believe we can leave the next generation better off and better prepared to fight the next set of challenges.
The work of making the world better is and always has been a group effort. I am proud of everything the foundation accomplished during its first 25 years, but I also know that none of it would have been possible without fantastic partners.
Progress depends on so many people around the globe: Brilliant scientists who discover new breakthroughs. Private companies that step up to develop life-saving tools and medicines. Other philanthropists whose generosity fuels progress. Healthcare workers who make sure innovations get to the people who need them. Governments, nonprofits, and multilateral organizations that build new systems to bring solutions to scale. Each part plays an essential role in driving the world forward, and it is an honor to support their efforts.
Of course, although the Gates Foundation is by far the most significant piece of my giving, it is not the only way I give back. I have invested considerable time and money into both energy innovation and Alzheimer’s R&D. Today’s announcement does not change my approach to those areas.
Expanding access to affordable energy is essential to building a future where every person can both survive and thrive. The bulk of my spending in this area is through Breakthrough Energy, which invests in companies with promising ideas to generate more energy while reducing emissions. I also started a company called TerraPower to bring safe, clean, next-generation nuclear technology to life. Both of these ventures will earn profits if successful, and I will reinvest any money I make through them back in the foundation, as I already do today.
I support a number of efforts to fight Alzheimer’s disease and other related dementias. Alzheimer’s is a growing crisis here in the United States, and as life expectancies go up, it threatens to become a massive burden to both families and healthcare systems around the world. Fortunately, scientists are currently making amazing progress to slow and even stop the progress of this disease. I expect to keep supporting their efforts as long as it’s necessary.
The success in both areas will determine exactly how much money is given to the foundation since any profits they earn will be part of my overall gift.
What the Gates Foundation hopes to accomplish
Over the next twenty years, the foundation will work together with our partners to make as much progress towards our vision of a more equitable world as possible.
The truth is, there have never been more opportunities to help people live healthier, more prosperous lives. Advances in technology are happening faster than ever, especially with artificial intelligence on the rise. Even with all the challenges that the world faces, I’m optimistic about our ability to make progress—because each breakthrough is yet another chance to make someone’s life better.
Over the next twenty years, the foundation’s funding will be guided by three key aspirations:
In 1990, 12 million children under the age of 5 died. By 2019, that number had fallen to 5 million. I believe the world possesses the knowledge to cut that figure in half again and get even closer to ending all preventable child deaths.
We now understand the essential role nutrition—and especially the gut microbiome—plays in not only helping kids survive but thrive. We’ve made huge advances in maternal health, making sure that new and expectant mothers have the support they need to deliver healthy babies. We have new, life-saving vaccines and medicines, and we know how to get them to the people who need them most thanks to organizations like Gavi and the Global Fund. The innovation is there, the ability to measure progress is stronger than ever, and the world has the tools it needs to put all children on a good path.
Today, the list of human diseases the world has eradicated has just one entry: smallpox. Within the next couple years, I expect to add polio and Guinea worm to the list. (When we eradicate the latter, it will be a testament to the late President Jimmy Carter’s leadership.) I’m optimistic that, by the time the foundation shuts down, we can also add malaria and measles. Malaria is particularly tricky, but we’ve got lots of new tools in the pipeline, including ways of reducing mosquito populations. That is probably the key tool that, as it gets perfected and approved and rolled out, gives us a chance to eradicate malaria.
In 2000, the year that we started the foundation, 1.8 million people died from HIV/AIDS. By 2023, advances in treatment and preventatives cut that number to 630,000. I believe that figure will be reduced dramatically in the decades ahead, thanks to incredible new innovations in the pipeline—including a single-shot gene therapy that could reduce the amount of virus in your body so much that it effectively cures you. This would be massively beneficial to anybody who has HIV, including in the rich world. The same technology is also being used to treat sickle cell disease, an excruciating and deadly illness.
We’re also making huge progress on tuberculosis, which still kills more people than malaria and HIV/AIDS combined. Last year, a historic phase 3 trial began that could be the first new TB vaccine in over 100 years.
The key to maximizing the impacts of these innovations will be lowering their costs to make them affordable everywhere, and I expect the Gates Foundation will play a big role in making that happen. Health inequities are the reason the Gates Foundation exists. And the true test of our success will be whether we can ensure these life-saving interventions reach the people who need them most—particularly in Africa, South Asia, and across the Global South.
To reach their full potential, people need access to opportunity. That’s why our foundation focuses on more than just health.
Education is key. Frustratingly, progress in education is less dramatic than in health—there is no vaccine to improve the school system—but improving education remains our foundation’s top priority in the United States. Our focus is on helping public schools ensure that all students can get ahead—especially those who typically face the greatest barriers, including Black and Latino students, and children from low-income backgrounds. At the K-12 level, that means boosting math instruction and ensuring teachers have the training and support they need—including access to new AI tools that allow them to focus on what matters most in the classroom. Given the importance of a post-secondary degree or credential for success nowadays, we’re funding initiatives to increase graduation rates, too.
As I mentioned, having access to a high-quality nutrition source is key to keeping kids’ development on track. Smallholder farmers form the backbones of local economies and food supplies, and they play a key role in making that happen. One of the main ways the foundation helps farmers is through the development of new, more resilient seeds that yield more crops even under difficult conditions. This work is even more important in a warming world, since no one suffers more from climate change than farmers who live near the equator. Despite that, I’m hopeful that we can help make smallholder farmers more productive than ever over the next two decades. Some of the crops our partners are developing even contain more nutrients—a win-win for both climate adaptation and preventing malnutrition.
We’ll also continue supporting digital public infrastructure, so more people have access to the financial and social services that foster inclusive economies and open, competitive markets. And we’ll continue supporting new uses of artificial intelligence, which can accelerate the quality and reach of services from health to education to agriculture.
Underpinning all our work—on health, agriculture, education, and beyond—is a focus on gender equality. Half the world’s smallholder farmers are women, and women stand to gain the most when they have access to education, health care, and financial services. Left to their own devices, systems often leave women behind. But done right, they can help women lift up their families and their communities.
The United States, United Kingdom, France, and other countries around the world are cutting their aid budgets by tens of billions of dollars. And no philanthropic organization—even one the size of the Gates Foundation—can make up the gulf in funding that’s emerging right now. The reality is, we will not eradicate polio without funding from the United States.
While it's been amazing to see African governments step up, it’s still not enough, especially at a moment when many African countries are spending so much money servicing their debts that they cannot invest in the health of their own people—a vicious cycle that makes economic growth impossible.
It's unclear whether the world’s richest countries will continue to stand up for its poorest people. But the one thing we can guarantee is that, in all of our work, the Gates Foundation will support efforts to help people and countries pull themselves out of poverty. There are just too many opportunities to lift people up for us not to take them.
The last chapter of my career
Next week, I will participate in the foundation’s annual employee meeting, which is always one of my favorite days of the year. Although it’s been many years since I left Microsoft, I am still a CEO at heart, and I don’t make any decisions about my money without considering the impact.
I feel confident putting the remainder of my wealth into the Gates Foundation, because I know how brilliant and dedicated the people responsible for using that money are—and I can’t wait to celebrate them.
I'm inspired by my colleagues at the foundation, many of whom have foregone more lucrative careers in the private sector to use their talents for the greater good. They possess what Andrew Carnegie called “precious generosity,” and the world is better off for it.
I am lucky to have been surrounded by many generous people throughout my life. As I wrote in my memoir Source Code, my parents were my first and biggest influences. My mom introduced me to the idea of giving back. She was a big believer in the idea of “to whom much is given much is expected,” and she taught me that I was just a steward of any wealth I gained.
Dad was a giant in every sense of the word, and he, more than anyone else, shaped the values of the foundation as its first leader. He was collaborative, judicious, and serious about learning—three qualities that shape our approach to everything we do. Every year, the most important internal recognition we hand out is called the Bill Sr. Award, which goes to the staff member who most exemplifies the values that he stood for. Everything we have accomplished—and will accomplish—is a testament to his vision of a better world.
As an adult, one of my biggest influences has been Warren Buffett, who remains the ultimate model of generosity. He was the first one who introduced me to the idea of giving everything away, and he’s been incredibly generous to the foundation over the decades. Chuck Feeney remains a big hero of mine, and his philosophy of “giving while living” has shaped how I think about philanthropy.
I hope other wealthy people consider how much they can accelerate progress for the world’s poorest if they increased the pace and scale of their giving, because it is such a profoundly impactful way to give back to society. I feel fulfilled every day I go to work at the foundation. It forces me to learn new things, and I get to work with incredible people out in the field who really understand how to maximize the impact of new tools.
Today’s announcement almost certainly marks the beginning of the last chapter of my career, and I’m okay with that. I have come a long way since I was just a kid starting a software company with my friend from middle school. As Microsoft turns 50 years old, it feels right that I celebrate the milestone by committing to give away the resources I earned through the company.
A lot can happen over the course of twenty years. I want to make sure the world moves forward during that time. The clock starts now—and I can’t wait to make the most of it.


Weather or not
Fighting climate change one text at a time
In Kenya, AI-powered weather forecasts are helping farmers adapt to a changing climate.
When I check the forecast for rain, I do it to answer fairly minor questions: Will I need an umbrella? Will my flight be delayed? Will my pickleball game get cancelled?
For smallholder farmers in Kenya, the stakes are much higher. If they plant their seeds too early, a dry spell might kill their crops before they have the chance to take root. If they plant too late, the crops might miss the rain entirely. When your family’s food and livelihood depend on getting the timing just right, a reliable weather forecast is incredibly valuable.
But in sub-Saharan Africa, it’s also been incredibly rare. That’s because global weather models are built from ground-station data, and Africa has fewer of these stations than any other inhabited continent. The result is forecasts that can accurately predict the rainfall in Missoula or Munich but are often far less accurate in Kenya’s Rift Valley, where 80 percent of the country’s staple maize crop is grown. As climate change makes weather patterns around the world increasingly erratic, today’s farmers are increasingly unable to rely on the seasonal patterns that guided generations before them.
Fortunately, AI offers us an affordable and fast solution. Over the past several years, a coalition of African institutions, researchers, and technology partners has been building a forecasting system with the technology at its center.
It starts with better information about the weather itself. On the ground, weather stations capture the basics like where it rained, when, and how much. But now, they’re supplemented by autonomous weather balloons up in the sky. For weeks at a time, these balloons float around and measure the temperature, humidity, and wind in places ground stations can’t reach and satellites can’t fully see either.
Then AI digests that information and puts it to work. While today’s AI models are far from perfect, they’re astoundingly good at squeezing immense insight out of limited data. In this case, they’re able to take the ground and sky observations, compare them to what was forecast, figure out the patterns behind the errors, and start correcting for them.
The more local data that comes in, the more the AI can finetune its models, and the better they get. As a result, a farmer in the Rift Valley can now get a weather forecast specific not just to her region but to her fields.
Of course, an accurate forecast only makes a difference if it reaches that farmer when she still has time to act on it. Even better if it’s delivered to her phone, in her own language, with advice she can use. That’s where a nonprofit called TomorrowNow comes in. I first saw their work on a trip to Kenya a few years ago and was impressed by how intuitive and impactful it is. Using AI, they translate the forecasts into easy-to-follow text message guidance like “plant this week,” “a dry spell is coming,” or “hold off on fertilizer.” Those text messages then reach farmers through organizations they already trust like One Acre Fund, which provides seeds and training to millions of them, and KALRO, Kenya's national agricultural research organization.
The results are undeniable. A rigorous two-year study of nearly 10,000 farmers found that those who got the text-message advisories grew 12 percent more food on average. That could be the difference between a family having to buy food and getting to sell their surplus. It's school tuition that gets paid and debts that are avoided. And the cost? Just 56 cents per farmer enrolled in the program. It’s hard to find a better bang for your buck than that in global health and development.
Today, Kenyan scientists at KALRO, working with TomorrowNow, are bringing AI-powered weather forecasts to more than five million farmers in Kenya; TomorrowNow’s goal is to reach 100 million across the rest of Africa and South Asia by 2030.
But even though international partners helped along the way, this system’s foundation—and the leadership deciding its future—is African. The observational backbone comes from institutions like the Trans-African Hydro-Meteorological Observatory, or TAHMO, which runs hundreds of weather stations across the continent. The forecasts draw on data from Kenya’s own meteorological authority. And the advisories are being built into the country’s permanent infrastructure rather than running alongside it as a donor project.
I've long argued that fighting climate change has to happen on two fronts: We have to cut emissions so the problem doesn’t get worse, and we have to help people who are most vulnerable to it adapt to the warming that's already occurred. The Gates Foundation invests a lot in this area, but the problem deserves much more attention and funding. And AI is making those investments go further than ever before.
When people ask me whether AI will exacerbate the gap between rich and poor, these are the innovations I talk about. Making sure AI's benefits reach everyone will take deliberate work, which the Gates Foundation committed over a billion dollars to at this year’s Goalkeepers event. The good news is: We already have proof that, when we’re intentional about it, this technology can be a great equalizer.
An epochal shift
The turbulent AI era is here. The choices we make now are critical.
We need a plan to ensure that the good outweighs the bad.
During my entire life I’ve only had two jobs. In the first one, I played a role in developing software to empower people through my work at Microsoft.
In my second one, which I started full time in 2008, I am giving back the wealth I made at Microsoft with the goal of making the world a healthier, better educated, and more equitable place. This is the job I will have for the rest of my life.
Both of these experiences inform my perspective on artificial intelligence. When I first learned about computers at age 13 I was fascinated by the idea of making them more intelligent and able to perform things that, at the time, only humans could do. Although the term “AI” was used from around the time I was born, the technology has only made significant progress in the last decade. It is now incredibly capable and it is continuing to improve at a mind-blowing rate. AI for the first time can replace and even exceed human cognition.
In terms of equity, AI will either be the greatest equalizer ever invented, or the worst source of injustice. The challenge is monumental. Even under the best circumstances, the transition to this new AI era will be one of the most turbulent times in human history. How will we use this technology to make the world a fairer place and keep it from widening the divide between rich and poor? How will we protect the people who are most vulnerable to the harms caused by artificial intelligence, including those who lose their livelihoods and the sense that they are in control of their future?
I believe that answering these questions and acting on the answers should be the world’s top priority. If the world takes the right steps AI will be a force for good and leave everyone better off.
Unfortunately, right now we are not preparing for it. I don’t see evidence that leaders, experts, and communities are confronting the challenges adequately. There is no plan to ease the entry into the AI era.
Part of the reason for this is that many commentators underestimate the extent of the impact AI will have. I think there are a few reasons why.
One is the fact that AI models still make mistakes. It is hard to envision any of them replacing human cognition when, not long ago, they couldn’t solve a simple Sudoku puzzle or figure out how many R’s are in the word strawberry.
But the reliability problem is being fixed quickly, as researchers create models that can check their own work and improve themselves. Soon they will be substantially better than humans at many tasks.
Another reason people underestimate AI is that analogies to the effects of past innovations are misleading. We have no experience with a technology that can be adopted quickly or that can think and move like a human. When the PC came along, it took twenty years to significantly change how we worked because the software had to be developed, the price had to come down, and people had to learn how to use the tools and incorporate them into their business processes. AI, on the other hand, runs on the devices we already have, and it uses natural language. We don’t have to adapt to it because it can adapt to us. It can watch the same training video that is used to train human workers and learn from existing data.
I want to acknowledge a potential bias. I have benefited enormously from the technology industry. Although I have diversified my portfolio quite a bit, I still have financial ties to it. I am working with Microsoft and other AI companies in my role as chairman of the Gates Foundation to try and ensure AI is deployed in ways that will truly benefit people around the world.
However, my views on AI are not motivated by the potential to make money for myself. Any profits generated by my investments, including those related to technology, will go to the Gates Foundation to tackle global inequity. Of course, readers will have to decide for themselves whether this clouds my view.
This time really is different.
For as long as I can remember, I’ve wished innovation could happen faster. With AI, my feelings are more complicated.
I wish the world could get the benefits rapidly and delay the problems it will cause as long as possible, but the benefits and problems are arriving at the same time. I believe we need time to prepare for the period of social, political, and economic upheaval we are about to enter. The people who need the most time are the ones who have the least—the accounting worker who’s replaced by a bot or the $20-an-hour worker who loses their job to a $10-an-hour robot.
Many observers say that this technology transition will be like previous ones. They give the example of how jobs in the United States shifted from agriculture to office work. However, that proceeded over several generations and created new jobs where human cognition was required. In this case, the technology can substitute for human cognition.
Because it can see, listen, speak, and reason and will eventually do physical work just as smoothly as any human, it will not just affect one sector. AI will take on work in law, customer service, medicine, software, and manufacturing. It will hit these industries rapidly, over the course of a decade rather than a few generations. There will be some new jobs, but without the right policies there will be far fewer than exist today.
If someone had a credible plan for slowing down AI advances globally, I would likely support it. However, I don’t think that’s going to happen. The geopolitical and economic incentives are pushing too hard to go full speed ahead.
To make sure we maximize the positive effects of this unprecedented technology and minimize the bad so we are better off overall, we need to understand both the benefits and the risks. I’ll start with the risks.
The transition to AI comes with three big risks.
I plan to write about each of these in more detail in the future, so I’ll touch briefly on them for now.
Many jobs will disappear forever.
In 1933, during the Great Depression, unemployment in the United States was roughly 25 percent. It remained in double digits for much of the following decade. It ultimately recovered as demand, investment, and growth returned.
AI may not reach this level, but its impact will not go away with an economic cycle. The jobs at most risk are entry- and mid-level, and the new jobs being created will mostly require skills that take many years to learn.
White-collar jobs are already being hit modestly. After the widespread adoption of generative AI, employment fell significantly among young workers in jobs that are especially vulnerable to replacement, but not among their older colleagues.
I think this trend will continue, but it will not be confined to a handful of industries or occupations. Jobs in sales and customer support (online and over the phone), software engineering, and paralegal work may be among the first affected, but the disruption will reach much further as AI takes on tasks that today still require trained workers: things like assessing loan applications, doing data analysis, and even triaging patients. A few areas like software engineering will generate new demand as the costs go down, so the net job loss in those areas will be less than in others as long as some tasks, such as design, are better done by humans.
Blue-collar jobs will be affected as well. Although robots are not as far along as AI, eventually their cost will be dramatically lower too. Many Americans I talk to don’t realize how fast dexterous robots are advancing because much of the advanced work is being done in other countries, primarily China. Or they may be confused by those videos of robots dancing badly that have been going viral lately. I think “smart” robots will begin to compete with people on some physical tasks—in the construction and hospitality industries, for example—by the end of the decade.
Robots and AI combined can create a vicious cycle. After one company adopts them and uses the savings to lower its prices, its competitors will feel immense pressure to do the same. If existing companies don’t adopt them, then start-ups will. Many people will shift to other jobs, but the turmoil of losing work, getting retrained, and finding other work will be significant. Market forces will make adoption go faster and faster and, unless we intervene, there will be fewer good jobs available and the benefits will accrue to a small group.
I’m especially worried about young people, who will enter a workforce with fewer entry-level openings. They understand the challenge because they are the most active users of AI and see both the capabilities and the rate of improvement. It’s no wonder that so many of them feel negatively about AI.
The biggest shift for workers will happen when AI provides nearly error-free work. At that point, it will be able to function on its own without a human checking in on it, and companies will have every economic incentive to let it.
This will lead to a fundamental change in how we think about work, income, and economic security. How will an economy that’s been built around employment operate if fewer people are working, or if many people are working fewer hours?
In a capitalist society, employment is the way most people get the money they need to pay for the basics of life as well as being a key source of dignity and social connection.
When a community has high unemployment, the ripple effects can be pervasive. Research suggests that in some parts of the United States, factory closures contribute to a rise in deaths from opioid overdoses. Now imagine similar pressures on both white-collar and blue-collar workers nationwide.
We have to think now about how to reduce job losses so that everyone can share in the prosperity that AI creates. Waiting until people are already displaced or underemployed will be too late. AI is a structural challenge to the way our economy is organized, and it requires thinking and action now.
AI will empower people (and perhaps AIs) to do more harm.
Long before AI entered the mainstream, there was information online about how to create weapons like bombs, bioweapons, even computer viruses. AI will make it much easier to not only get this information but act on it. Even criminals with very limited skills will be able to target victims at every scale: individuals, companies, and governments.
AI-enabled fraud, disinformation, deepfakes, and surveillance are the harms that many people will feel most keenly in their everyday lives.
AI capabilities are starting to be used for cyberattacks. The smartest cybersecurity experts I know are scared about the next few years, because the attackers are getting powerful new capabilities faster than the defenders can fix all the weaknesses. After all, the same AI model that can find a flaw in software so a company can fix it can also help a criminal exploit it. The resources needed to make an attack are going down significantly and we haven’t been able to separate those abilities from benign usage.
Think about the infrastructure that will be vulnerable: hospitals, financial institutions, water systems, power grids, systems for managing government benefits. When these institutions are attacked, it’s the patients, customers, and benefits recipients who stand to lose.
The same goes for bioterrorism. Although AI will lead to lifesaving advances in drugs and vaccines, it will also make it easier to design a deadly new disease. Again, the positive capabilities are hard to separate from the dangerous ones. This is a global problem.
The risks I’ve just mentioned are all about how AI will empower bad actors who have relatively little power now. The same tools will also concentrate power in places where it already exists. Autonomous weapons, for example, will make governments even more capable of using deadly force without a human being part of the decision. Monitoring and manipulating public opinion will be easier and cheaper, and more effective too.
Eventually, the power to use AI to harm people will not be limited to people or institutions. AI systems themselves already occasionally act in ways their designers didn’t intend. The technology is improving faster than anyone expected and in surprising ways, and as the models become more powerful, they could begin to act against our interests and we could lose control. I’ll have more to say about this in the future.
AI could stunt our kids’ development and replace human relationships.
When I was growing up in Seattle, I didn’t have that many friends aside from a few other boys who were like me. It took hard work and a lot of help from my mom to develop my social skills so I could relate to different kinds of people. I still draw on those lessons today at the age of 70.
I doubt I would have put in the same work if I had had an AI companion back then. They talk to you in ways you’re already comfortable with. They don’t push you outside your comfort zone. They are always available and never get mad at you. This gives them the potential to become highly addictive and to rob us of the lessons we learn from connecting with other people.
The body of evidence on this subject is still small and a bit mixed, but there are signs that we should be very concerned. For example, in one study of more than 1,100 people who use AI companions, researchers at Stanford and Carnegie Mellon found that those with smaller social networks were the most likely to turn to a chatbot for companionship. And the heavier and more emotionally personal that use became, the worse they felt.
Young people could be affected for their entire lives. In his book The Anxious Generation, Jonathan Haidt makes an observation about the effect of social media that is even more true for AI: “Like young trees exposed to wind, children who are routinely exposed to small risks grow up to become adults who can handle much larger risks without panicking. Conversely, children who are raised in a protected greenhouse sometimes become incapacitated by anxiety before they reach maturity.”
An AI companion designed to never upset you is a big, protected greenhouse.
We are only beginning to understand the dangers that the internet—especially social media—can pose to young people’s development. We’re seeing compulsive use, disrupted sleep, cyberbullying, and exposure to harmful content. AI could magnify many of these risks by making them more persuasive and difficult to escape, and we should not wait another generation to start taking them seriously. Countries including Australia, the United Kingdom, and Norway are adopting protections for children online. China has gone the furthest. Its rules restrict AI companion apps broadly, bar designs that foster emotional dependence, and ban virtual relatives and romantic partners for minors.
I’m also worried about AI’s impact on education. Ironically, the same tool that will allow people to learn more than ever could also lead to many people learning less. One preliminary survey suggested that heavier AI use was associated with less critical thinking. The effect was stronger for younger people.
This would be the worst possible time for humans to lose their critical thinking skills. In an era of deepfakes and misinformation that can be tailored to you individually, the ability to tell what is true from what is not becomes an essential life skill.
It’s unclear where to draw the line on these psychosocial problems. In some cases, AI may help people understand how to do better in their human relationships. It may be the only contact with the outside world for isolated elderly people and people with limited mobility, and it will be better than nothing. Wherever we end up drawing the line, it should be our decision, made intentionally.
The good things we do with AI could be very, very good.
It’s often said that we overestimate how much will change in the short term and underestimate how much will change in the long term.
With AI, I see something different going on. Some people see only the upside of AI and do not focus enough on the negatives. Others make the opposite mistake, which is to focus exclusively on the dangers—which are real—at the cost of missing the potential benefits.
We need both: deep concern about the AI harms we need to minimize, and grounded optimism about the positives if we maximize them for everyone.
Maximizing the benefits is just as important as minimizing the harms. If people see how AI makes their lives easier, it will help build the public trust that is necessary for managing the harder parts of the transition. If the first thing AI does in most people’s lives is take away their job, those who are already skeptical about it will outright reject it. This will make it harder to ever deliver on the benefits and it is another reason why governments, industries including the medical industry, and AI companies should be working together now.
With its ability to synthesize knowledge from every scientific field, AI can accelerate innovation in the world’s toughest technical challenges: providing reliable clean energy for everyone, combating climate change, growing enough food, eradicating diseases, and more. Researchers working on cancer treatments or nuclear energy can use AI to search through massive amounts of scientific literature. It can help them identify patterns that a human might miss and decide which experiments offer the most promise. When intelligence is no longer the limiting factor that it is today, smaller companies will be able to compete with organizations that have far larger research budgets. R&D and innovation will be supercharged.
Healthcare is one area where AI can help solve real-world problems. Many small American hospitals lack on-site specialists who can quickly diagnose a patient during a life-threatening emergency. In those places, AI could make sure a heart attack is caught in time and a family avoids the crushing expense of a medical emergency. Viz.ai is one example. It analyzes scans to detect strokes and other emergencies and helps medical teams coordinate their patients’ care. It is being used in nearly 2,000 U.S. hospitals.
AI will also help primary-care doctors make better diagnoses and keep in touch with their patients when they’re not in the clinic. It will help patients understand test results and complicated schedules for taking their medicine.
I surprise a lot of people when I tell them that a second area—agriculture—is where I see the fastest impact of AI in low-income countries. In most low-income countries, farmers don’t get reliable weather forecasts or advice on what seeds to plant, how to protect their crops and livestock from disease, or how to improve their soil. With population growth in these countries and the challenges of climate change, these farmers need more help than ever. Using AI, low-income farmers will soon be able to get better advice about all these things than even the richest farmers get today and increase their output substantially.
Government services are a third area where AI can make people’s lives easier. In the United States, I’ve met families who, understandably, were overwhelmed by the process of applying for health insurance, student aid, or food assistance. Faced with a huge stack of complicated bureaucratic forms, many felt like giving up. AI can streamline things dramatically so they get the help they need faster and the government can operate more efficiently. Governments can make the citizen’s experience far better, starting with those who need its safety net services the most.
Despite my concerns about its impact on our mental health, I think AI can also help a lot there. Most communities have too few counselors, psychiatrists, and addiction specialists. With the right privacy safeguards in place, AI tools could help people recognize warning signs. Then, if needed, they can offer evidence-based coping strategies and team up with a human to provide more responsive treatment.
AI can be a boon for education as well, despite the concerns I mentioned earlier. It can free teachers up to spend more time working with students one on one or in small groups and give them a clearer view of where the whole class is struggling. For students, an AI tool that preserves what researchers call “productive struggle”—the cognitive work that builds understanding—can strengthen learning. When a student first encounters a new idea, the AI gives substantive explanations and offers both questions and answers. Later, when it’s checking their comprehension, it holds the answer back and helps them arrive at it on their own.
Taken together, the advances in all these areas could make everyday life easier, more affordable, and less constrained by a person’s income or connections.
AI could give individuals and small businesses access to capabilities that today require expensive professional help or large staffs, while making products and services better and cheaper. It could help people with disabilities live more independently and enable workers and entrepreneurs with good ideas to accomplish far more than they can today.
Most importantly, it could give people back some of the time and attention now consumed by paperwork, bureaucracy, searching for reliable information, and tasks they cannot afford to pay someone else to handle. These benefits may seem modest, but multiplied across millions of lives, they would be profound: more people getting good advice when they need it and having greater freedom to focus on the lives they want to build.
In all these areas, the operative word is “can”—AI can improve life for people at every income level. But it won’t do that automatically. As with any new technology, we have to be deliberate about ensuring that it benefits everyone and not just a wealthy few. This will require governments and philanthropy to play a strong role so that less wealthy citizens and low-income countries are full beneficiaries.
The Gates Foundation has 19 years left of the 20 years in which it will spend its remaining $200 billion. AI will help it achieve its ambitious goals by both accelerating the discovery of vaccines and medicines for HIV, TB, malaria, and malnutrition and helping the healthcare workforce and patients know how to use those tools. The foundation’s goals include cutting the number of children who die every year in half again, as was done from 2000 to 2024. All of our work, not just health but also agriculture and education, will take full advantage of AI.
I will write much more about these efforts next month in the foundation’s annual Goalkeepers report—including our focus on making sure that AI models are available in the languages spoken by people in all the countries where we support work, and not just the ones that are common in rich and middle-income countries. Many of the leading AI companies, including OpenAI, Anthropic, Google, and Microsoft, are partnering with the foundation on all of these initiatives, which is making a big difference.
The world needs a plan.
It is great that some AI companies are proposing solutions to challenges raised by their own technology, but we should not expect them to lead the charge. Some of the issues are outside their area of expertise, and in a democratic society it’s not their role to decide these things.
Instead, solutions should be developed through a public democratic process that includes elected officials, policymakers, educators, health workers, local officials, and community leaders. Millions of people will have their lives disrupted, and we’ll need a stronger, more flexible social safety net to help them manage the transition. Local communities are already raising concerns about the energy and water needed for data centers. Without solutions, some groups will push for stopping AI development and deployment altogether.
The solutions should be shaped by our answers to the profound questions raised by AI, including how we preserve our humanity in a time when machines can out-think us. As people who spend their lives thinking about what it means to be human, religious leaders can play a key role in this. I was fascinated by Pope Leo XIV’s encyclical on AI, “On Safeguarding the Human Person in the Time of Artificial Intelligence.” It lays a strong foundation for the work that needs to be done.
In the coming months, I will share more ideas for making sure that AI’s benefits outweigh the harm it causes. Here are three to start, beginning with what I think is the most important one.
Build a new system for managing the transition.
The highest priority is a monumental task: creating a domestic and international framework for dealing with AI.
None of our current institutions were designed to handle a technology that spreads so fast and touches so many parts of our lives. So we’ll need to make new ones.
It’s hard to overstate what an enormous undertaking this will be. After the attacks of 9/11, the U.S. government went through its biggest reorganization since World War II for the purpose of improving just one function, national security.
AI will require much, much more. It will affect national security as well as employment, education, taxation, energy, elections, air and water, public health, the financial system, law enforcement, transportation, public lands, and IT systems.
These sectors overlap in ways our existing bureaucracy is not designed to manage. A labor department may understand workforce disruption but not security risk. A business regulator may understand market concentration but not AI’s effects on children and teenagers. Left to themselves, institutions will see only one part of the system, while the consequences of AI will ripple across the entire system.
At the national level, countries will need bodies that can set priorities across government agencies. The goal will be to make sure that every risk is accounted for. Otherwise, an AI-enabled attack might succeed because no one thought it was their job to stop it.
But even a country that gets its own house in order will still be exposed to risks that cross borders. This is why an international organization will need to be built in parallel.
It will be unlike any other institution we have ever created, though it can follow the model of some existing systems. There’s an inspections regime for nuclear weapons, regulations for international aviation, and agreements that protect the ozone layer. A new global organization for AI will need elements of all three and more.
It is fair to wonder whether the world’s institutions are up to the task of designing and implementing this new architecture. Government moves slowly when it moves at all, and polarization within and between countries makes it harder than ever to get things done. Some cooperation between the U.S. and China will be required.
We do not have the luxury of moving slowly. The place to start is with a process for building the right institutions before the disruption forces governments into crisis mode. National leaders should convene economists, technologists, labor experts, business leaders, and workers themselves regularly to identify where existing institutions are failing and what new authorities may be needed. Countries will need to learn from each other.
And the countries that host the leading AI developers and control critical parts of the supply chain should begin meeting now to set up shared norms, before competitive pressure makes it harder for them to cooperate.
Building the framework I’m talking about will take years, which is why we need to start now.
Set aside some jobs for humans.
My dad died of Alzheimer’s in 2020. In the later stages of his illness, he was cared for day and night by paid caregivers who understood him even when he struggled to express himself. He couldn’t always tell them when he was hungry, but they always knew.
My family and I will always be grateful to that amazing group of professionals. Something in the care they gave my dad was irreplaceably human. No robot could or should have done it.
I think about that team when the question of which jobs will disappear and which will remain comes up. I believe that as AI and robots improve, we’ll set aside certain things for only people to do. I’ve started calling this domain Human Reserved, and it’s an example of the kinds of ideas we’ll need to consider.
I like the phrase Human Reserved because it makes me think of nature reserves—places where we could put buildings and roads, but we choose not to because the loss would be too great.
We might set something aside as Human Reserved for economic reasons. For example, we may do it because allowing machines to take over a certain role will displace a large number of people who can’t easily change jobs. You can’t tell a 55-year-old who has worked in construction their whole career that they need to go work at an elder care facility and expect them to find it fulfilling.
Sometimes the decision to make something Human Reserved will be driven by other factors. In health, for example, imagine a robot giving you the awful news that you have an incurable disease. There’s no technical reason why it couldn’t. Yet it shouldn’t.
The Human Reserved domain will evolve over time—for example, we should consider setting aside some jobs now and phasing in AI slowly over years or decades with a commitment to preserve some jobs. Some areas, like education and mental health care, will be a mix, with a human in charge who’s using the technology to extend what they can do.
The lines will also vary from place to place. Some countries might insist on having humans take care of the elderly. But a country like Japan, which has a shrinking workforce and not enough young people to care for the old, may welcome a caregiving robot.
The idea of Human Reserved raises a host of questions I don’t have answers to. Who gets to decide what we reserve for humans? What criteria should we use? How do you keep companies from cheating and using robots anyway? What happens to international trade when one country lets robots make something and another country doesn’t? These will need to be worked out in public as part of the transition plan.
Rebalance how we tax labor and capital.
As workers are pushed into different jobs, they will need retraining and other support from the social safety net. But they will be working less, which means they will be paying less in income taxes, and government revenues will drop just when the demand for those services is greatest. The funds will have to come from somewhere at a time when budgets are stretched.
I believe we should tax AI tokens and robots. Right now, if you’re an employer and you hire someone, you pay payroll taxes on their earnings. But if you buy a robot, you can usually write it off right away as a business expense. The tax system nudges you toward replacing people with machines.
A tax would slow the rush away from human labor a little and raise money for retraining and a stronger safety net. It would need to be targeted so it does not slow down the purely beneficial uses of AI, like making medicine and education cheaper.
Critics of this idea point out that it’s not optimally efficient in an economic sense, but they’re not considering the broader value of work for individuals and society. And with all the accelerated innovation we will have, we’ll be able to afford a little inefficiency as the price for keeping people employed.
I proposed a robot tax years ago and most of the reaction was that it was a strange idea. I’m still a big proponent of it. Although it is not the whole solution to the threat of AI, it is part of a wise response.
However we raise money for more assistance, it needs to reach the people who need it most, including workers who lose their jobs to AI and robots, people whose hours or wages decline, and communities where the losses are concentrated. We need to start doing that work now so that the systems are ready when the need becomes acute.
What I’m doing.
I will use my voice and time to get AI and equity higher on the public agenda. I will raise the issue with lawmakers every time I visit Washington, D.C., and when I meet with leaders around the world. It will be front and center in my conversations with the people who are developing AI models. I will advocate for the national and international framework I described earlier. The Gates Foundation will help drive beneficial usage, including in Africa. Breakthrough Energy, a company I founded, will use AI to help companies develop cheap clean energy and help solve the climate problem. I will also be writing about AI on a regular basis.
My message to leaders is:
You have a chance to act now, before unemployment rises sharply, communities are hurting, and public trust has eroded. You can make sure that your government handles the problem holistically, rather than divvying it up into multiple bureaucratic fiefdoms. You can make sure AI benefits everyone. And you can work with other governments to meet this national and global challenge.
Finally, I will try to widen the circle of people shaping this debate. It should include workers, college students who are about to enter the workforce, community leaders, religious leaders and faith-based organizations, parents, educators, and others whose voices often aren’t heard but who have insight into how the transition will affect people’s lives.
How do we ensure that the benefits of AI reach people who do not already have wealth, influence, and access?
How do we strengthen the social safety net and help workers and communities thrive even when they’re displaced?
How should public institutions adapt?
And how do we preserve our humanity through all of this?
This unprecedented technology demands an unprecedented global response. If we get it right, the payoff for humanity will be phenomenal and the world will be a more equitable place.
I rarely stop thinking about AI—not because I have all the answers, but because the questions it raises are too consequential to leave to a small group of technologists. Leaders across academia, business, government, and civil society all have a role to play in shaping what comes next.
Buzz off
Small bugs, big breakthroughs
Science holds the key to stopping deadly pests like mosquitoes and screwworms.
What do humans and cows have in common? Among other things, we’re both victims of tiny insects.
For cows, the latest culprit is the New World screwworm. Despite the name, the screwworm is actually a type of fly that likes to lay its eggs on animals like cows, which creates an often-fatal wound on the animal’s hide. Screwworms once killed up to one million cattle a year here in the United States, and sixty years after we eliminated them in our country, they’re back.
For humans, one of our greatest nemesis is the mosquito. There are plenty of reasons to hate mosquitoes, but malaria is easily at the top of the list. The disease kills more than 600,000 people every year, most of them children, and it’s transmitted when a mosquito infected with a parasite called Plasmodium bites you.
Protecting people (or cattle) from an insect poses an interesting challenge. How do you stop something so small from hurting anyone? There are lots of different ways to approach the problem.
One approach is to keep insects out of the places where people are. There are already lots of tools that do this with mosquitoes, with more in the pipeline. The most widely used is the bed net, a gauzy sheet of fabric treated with an insecticide that kills any mosquito that tries to reach the person sleeping under it.
Bed nets are magical. In some places where malaria is endemic in Africa, they’ve reduced the number of children who die before the age of 5 by 20 percent. But there’s a problem: Mosquitoes can develop resistance to the insecticide used in bed nets, just like bacteria can evolve resistance to antibiotics.
Enter the dual active ingredient bed net. (You’ll often see them referred to as dual AI nets, even though they have nothing to do with artificial intelligence.) By treating bed nets with two different insecticides, scientists have been able to figure out how to negate a mosquito’s resistance and keep people safe. The catch is that dual AI nets are more expensive than regular bed nets, which is why the Global Fund and the Gates Foundation stepped in to make them affordable for the countries that needed them most. The results so far have exceeded my expectations. Dual AI nets now make up more than half of the bed nets used, just two years after they became available.
Bed nets have another flaw: They only protect you while you’re under them, even though mosquitoes are also active in the hours before you go to sleep and after you wake up. A new tool called a spatial emanator aims to bridge that gap. It basically works like a plug-in air freshener—but instead of releasing a nice fragrance, it slowly releases an insecticide at a low-enough dose that doesn’t harm people but drives away any mosquito that might enter your home.
When spatial emanators received the green light for use a year ago, they became the first new malaria-prevention tool the WHO has recommended in over a decade. I’m super excited about their ability to protect people from mosquitoes for more hours of the day.
Another approach to stopping insects is to target them at the population level. That’s how the world stopped screwworm the first time. In 1954, scientists figured out a way to use radiation to make the males sterile. They released the neutered insects into the target area, and since they couldn’t reproduce, the population died off. This approach worked sixty years ago, and it still works today (and scientists are working on even more effective methods).
What if we could use a similar approach to stop mosquitoes? Last year, I wrote about an incredible project in Tanzania called Transmission Zero. The idea behind it is simple: a mosquito that can’t give you malaria.
Tanzanian scientists have found a way to make Anopheles gambiae mosquitoes—the species responsible for most of the malaria in Africa—produce two types of molecules, naturally found in frogs and bees, that block the parasite from developing inside the insect. The mosquitoes would continue flying around, doing their mosquito business, but they wouldn’t be able to make anyone sick with malaria. Each time they mated with another mosquito, they would pass on the gene that protected them from the parasite. (I just published a new profile of Dr. Lina Finda from the Ifakara Health Institute in Tanzania, who is helping lead this work.)
These malaria-free mosquitoes could potentially help save tens of thousands of lives every year. And Tanzania isn’t the only country on the cutting edge of advancing this work. The Ugandan Virus Research Institute and the University of Sciences, Techniques and Technologies of Bamako in Mali are also doing pioneering work to move the field forward. Scientists are learning more every day about the role mosquitoes play in ecosystems, and research is now underway on two other species beyond Anopheles gambiae.
Dual AI bed nets, spatial emanators, and malaria-free mosquitoes are just the latest breakthroughs to come out of the robust malaria innovation pipeline. Treatments continue to get better, and vaccines are already proving to save lives, with even more effective next-gen vaccines to come. A lot of interesting work is underway with endectocides, a type of drug that could potentially make your blood toxic to mosquitoes. There’s even a fascinating trial that looks at whether targeting mosquito larvae in rice paddies could make a difference. The goal of this trial is to stop malaria, but early results from Nigeria and Rwanda indicate that larval control could boost rice yields as much as 50 percent, which would be incredible for farmers.
Unfortunately, while the R&D progress we’re making is remarkable, the same can’t be said for the fight against malaria overall. Donor governments are cutting health aid—including money for the Global Fund, which has saved more than 70 million lives to date by helping deliver lifesaving tools like bed nets. Last year, our partners across Africa pulled off a miracle to minimize the impact of the cuts. With support from our foundation, they found creative ways to distribute supplies that were already in warehouses across the continent.
This year, the picture looks different. While some funding has since been restored, cuts from multiple donor governments mean it's not yet enough to guarantee bed nets and other tools reach every family who needs them. Our foundation is doing everything we can to help close that gap. I continue to advocate for increased funding, because it is ridiculous to put the health of the world’s children at risk when we know how to save them.
I believe we can end malaria forever. We have some of the tools we need already, and I think we’ll have the rest soon. We can defeat mosquitoes, just like we stopped screwworm more than half a century ago and just like we’ll stop it again. The question is whether the world will choose to make it happen.
The choice is obvious to me. We have an opportunity to ensure that no child dies from malaria ever again. Let’s take it.
No fever dream
How the U.S. got rid of malaria
This is how a parasite helped build the CDC and changed public health forever.
I spend a lot of time thinking and worrying about malaria. After all, it’s one of the big focuses of my work at the Gates Foundation. But for most Americans, the disease is a distant concern—something that happens “there,” not here.
That’s true today. It wasn’t always.
It was especially rampant in the South, from the Carolinas and the Mississippi Delta down to Florida and all along the Gulf Coast.
Every summer, people braced for the start of “fever season.” In her Little House on the Prairie books, Laura Ingalls Wilder wrote about what she called “fever ‘n’ ague.” A laundry list of presidents—including George Washington, Andrew Jackson, Abraham Lincoln, and Ulysses S. Grant—battled the disease.
During the Civil War, Confederate General Robert E. Lee was even counting on malaria to weaken Union troops, confident that “the climate in June will force the enemy to retire.” (It ended up crippling his own army more.)
Without modern medicine, or any understanding of how the disease spread, people reached for whatever remedies they could find: drinking vinegar and whiskey, rubbing onions on their skin, and boiling bitter herbs into tea. Powdered quinine, a substance derived from cinchona bark, actually worked—but it was expensive and hard to obtain, so few people had access to it.
For most people, the fevers kept returning year after year and summer after summer.
The first breakthrough came at the turn of the 20th century. Scientists finally proved that malaria was transmitted by mosquitoes—not, as had been previously thought, by contaminated water or poor air quality. (Malaria means “bad air” in medieval Italian.) It was a crucial discovery. Finally, people knew what to target. Across the South, some communities began draining swamps to try to control their mosquito populations. But most of these efforts were basic and improvised. What was needed was the kind of massive, coordinated, well-funded approach that only the federal government could mount. Enter one of the most ambitious and impactful infrastructure projects in American history: the Tennessee Valley Authority.
Enter one of the most ambitious and impactful infrastructure projects in American history
the Tennessee Valley Authority.
The TVA wasn’t created to fight malaria. Launched in 1933 as part of the New Deal, its mission was mainly economic: to bring electricity and jobs to the rural South, where some of the country’s poorest people lived, during the Great Depression. But the region also had some of the nation’s highest malaria rates, with 30 percent of its population infected. TVA leaders quickly realized their work wouldn’t succeed unless public health improved too.
So they incorporated malaria prevention into their projects. As engineers built dams and power plants across the region, they also drained thousands of acres of swamps, reshaped rivers, regraded land, and upgraded housing—which all helped to destroy mosquito breeding grounds. At the same time, public health campaigns educated people on installing window screens and eliminating standing water around their homes after storms. Then came World War II.
Then Came
world war II
As military bases popped up across the South, malaria became a growing threat to soldiers and defense industry workers. So the U.S. responded by launching a new program in 1942: the Office of Malaria Control in War Areas, headquartered in Atlanta. It was the federal government’s first centralized program created explicitly to fight malaria—and it laid the groundwork for what would become the Centers for Disease Control and Prevention, or CDC, which officially took over the malaria effort in 1947.
The goal of the campaign, which began with wartime control before transitioning to peacetime eradication, was simple but ambitious: Stop mosquitoes from spreading malaria, and stop people from carrying it.
ON THE MOSQUITO FRONT
The campaign launched the largest insecticide operation in U.S. history and paired it with an aggressive effort to destroy mosquito breeding grounds. Teams of sprayers went door-to-door with tanks of DDT strapped to their backs, covering millions of homes in what was essentially a chemical shield against mosquitoes. In some areas, airplanes dusted entire counties with insecticide. Meanwhile, construction crews drained ditches by hand or with bulldozers. In Florida, they used dynamite to blast open drainage paths from mosquito-infested marshland.
ON THE HUMAN SIDE
Quinine and later chloroquine—its synthetic successor—were distributed widely, especially in rural areas with high infection rates. These drugs cleared the parasite from the bloodstream, which meant that even if someone was bitten by a mosquito, they wouldn’t pass the disease on. Mobile teams traveled from town to town, testing and treating entire communities. In the Mississippi Delta, they even set up roadside treatment stations where people could stop for a dose on the way to work or school.
Public health messaging played a huge role, too. One memorable cartoon featured a mosquito named Bloodthirsty Ann—yes, short for Anopheles—that taught troops how to reduce their risk of contracting malaria. Its creator was a young army captain named Theodor Geisel, who eventually became better known as Dr. Seuss.
Perhaps the most impressive part of the program was its scale and speed. In just a few years, tens of thousands of public health workers across fifteen states were hired and trained. Doctors, nurses, scientists, teachers, technicians, and trusted community figures knocked on doors, gathered data, treated patients, and made sure no outbreak went unchecked. In 1951, America declared victory over malaria.
In 1951
AMERICA DECLARED VICTORY OVER MALARIA
I think about this history a lot when I’m visiting Sub-Saharan Africa, where the parasite still kills 600,000 people a year. Because in many ways, the strategy hasn’t changed: Stop transmission, clear infections, and build public health systems that prevent malaria from roaring back.
Malarious area of the United States
But the U.S. had some key advantages that made elimination much easier. Compared to the species responsible for most malaria today, our mosquitoes weren’t as efficient at transmitting the parasite. Our climate also limited transmission to the summer months; in tropical regions, people get infected year-round. And by the 1940s, our country had relatively strong infrastructure, even in rural areas, that many malaria-endemic countries today still lack.
ON THE TREATMENT SIDE
So the challenge today is much bigger. Fortunately, today’s malaria-fighting toolbox is much bigger—and better—too.
Instead of blanket spraying DDT, which has since been banned, modern prevention relies on safer insecticide-treated bed nets and indoor spraying techniques that use smaller doses of more targeted chemicals. Sugar baits, which lure mosquitoes to ingest a lethal dose of insecticide, are already helping reduce their numbers. And gene drive technology could soon block the parasite inside the mosquito itself—so even if someone gets bitten, they won’t get infected.
Chloroquine has been replaced by artemisinin-based combination therapies, or ACTs, which are more effective and less prone to resistance. New drugs like tafenoquine are helping eliminate recurring strains. Seasonal chemoprevention protects children during peak transmission months. And the first malaria vaccine has been approved, with more on the way.
Malaria elimination is never easy. But unlike a century ago, it’s no longer a mystery. The world knows how to stop this disease. We’ve done it before. And with the right investments and innovations, we can do it again—this time, for everyone.

Bite back
Great news for mosquito haters
With some breakthrough tools, the end of malaria could be here soon.
I was scrolling Reddit recently when I saw a video of a mosquito trying and failing to suck someone’s blood. Some of the replies were pretty funny, but I noticed that most of them were just some form of “How do I get this person’s superpower?” It was a great reminder of how universally hated these bloodsuckers are.
But I have good news—for Reddit users and everyone else: Real progress has been made in the fight against mosquitoes and specifically against malaria, the deadliest disease they carry. And I believe we’ll soon have the transformational tools needed to end malaria entirely.
Eradication is a goal Melinda and I set back in 2007, when we stood before a group of global health leaders and called for something many considered impossible: wiping malaria out completely from every country. And until that happened, our goal was—and is—to save as many lives as possible by maximizing the impact of the tools we already have. Eradicating the disease wasn't a new idea; the World Health Organization had made a similar declaration back in 1955. But that earlier campaign, while successful in many wealthier parts of the world, had fallen short across Africa, Asia, the Middle East, Eastern Europe, Central and South America, the Caribbean, and Oceania. Despite half a century of effort, malaria was still infecting up to half a billion people—and claiming a million lives—annually.
Today, the landscape has changed dramatically. In 2022—the last year we have data on—there were 249 million cases worldwide and 608,000 deaths. Those are staggering numbers, but they’re also improvements from where the world was back in 2007. Since then, 17 additional countries have been declared malaria-free by the World Health Organization. Outside of Africa, deaths from the disease have mostly been eliminated.

Proof of progress
Bad news isn’t the only news
There are reasons to be hopeful about the future, if you know where to look.
Sometimes when I tell people I’m optimistic about the future, they look at me like I’m crazy. How could I say that when there’s so much violence in the world, the international order seems to be collapsing, and AI may end up doing more harm than good?
I see all these problems too, and I’m deeply concerned about them. (I am working on a long memo about the risks and benefits of AI that I plan to publish later this month.)
But through my work with the Gates Foundation and other organizations, I also get to see signs of progress that help me stay optimistic.
To me, being hopeful about the future doesn’t mean you ignore the bad news. It’s actually the opposite: You look directly at it and then search for people who are doing something about it. In most cases, you’ll find them. And then you will start to see the broader trend of progress they are contributing to.
Here are some of my favorite signs of progress.
IN THE PAST:
- We’ve cut the number of children who die every year by more than half, from more than 9 million in 2000 to fewer than 5 million now.
- For the first time, we have a blood test for Alzheimer’s and drugs that may slow its progress.
- Electric vehicles now make up about one in four new cars sold worldwide, with sales topping 20 million in 2025.
- There are 1.5 billion fewer people living in extreme poverty today than in 1990, even though the population has risen 50 percent since then.
- Nearly 95 million girls have been fully immunized with HPV vaccine, so they’re much less likely to develop cervical cancer later in life.
- More than 86 percent of the world’s adults can read and write, up from about 68 percent in 1979.
IN THE PIPELINE:
- The newest obesity drug in trials produces nearly 30 percent weight loss, almost as good as what surgery achieves. The same class of drugs is expanding fast into related conditions, including sleep apnea, fatty liver disease, and hopefully, osteoarthritis.
- Scientists are developing a single-shot cure for sickle cell disorders, which kill tens of thousands of people every year, and it could be available within five years. The underlying technology is also being used to develop a single-shot HIV cure.
- We’re close to eradicating polio, which is endemic in only two countries. We’re nearly done with Guinea worm disease as well, cutting it from 3.5 million cases in 1986 to just ten last year.
- The mRNA technology behind some COVID vaccines is now being used for cancer vaccines, with nearly 100 in clinical trials for melanoma, lung, pancreatic, and other cancers.
- A new tuberculosis vaccine is in final-stage trials. If it works, it will be the first new TB vaccine in more than a century and could prevent tens of millions of cases over the next 25 years.
I love telling these stories. Here’s a video where you can see the amazing impact of the Green Revolution.
I find that trying to keep a positive attitude is valuable in itself. It keeps me grounded so I don’t swing toward one political extreme or another. I think the world might be less polarized if more people had a sense of the positive things that are going on in addition to the problems we need to solve.
You can find more videos here about progress. If you see one that strikes a chord for you, I’d encourage you to share it.















Gone for good
“AIDS-free generation” is no empty promise
New tools mean we’ll be able to stop the pandemic forever.

Game changer
Grassroot Soccer scores a hat trick for African youth
This organization uses the beautiful game to reach millions of young people with lifesaving services.
I’ve never been much of a soccer fan. (Tennis and pickleball are my favorite sports.) Still, seeing the athleticism and passion on display during the World Cup, I understand why soccer has earned the nickname “the beautiful game.” What makes soccer even more beautiful is the positive impact it can have off the field.
There may be no better example of this than the work of a unique non-profit organization called Grassroot Soccer, which was featured at a health innovation event where I spoke earlier this week.
For the last two decades, Grassroot Soccer has used the incredible popularity of the game to help young people across Africa navigate some of their toughest health challenges.
Despite significant progress in health and development in Africa, including a dramatic decline in child mortality, HIV/AIDS continues to be a leading cause of death among youth in Africa. Sexual violence threatens the health and safety of girls. A lack of access to contraceptives contributes to high rates of teen pregnancy. And mental health services are often unavailable.
Solving these challenges is difficult—and especially important given that 60 percent of Africans are under the age of 25. So, how can soccer make a difference?
Because it’s so popular, soccer offers a hook to capture the attention of young people. Grassroot Soccer uses the game to involve them in activities that encourage them to live healthier, more productive lives.
Here’s one simple example. In an activity called “Risk Field,” players are asked to dribble a soccer ball through cones labeled with some of the risky behaviors that young people often encounter, such as unprotected sex, HIV, multiple partners, and alcohol.
The local youth who serve as Grassroot Soccer coaches are a critical component of the program. Trained in basic counseling skills, the coaches play an important role as trusted mentors to the young participants.
The coaches also accompany adolescents to clinics where they can get HIV testing, contraceptives, and other services. (In some countries, young people might be turned away because of their age or criticized by health staff for seeking contraceptives and testing. The coaches serve as advocates to support their right to health services.) Coaches also conduct home visits to talk with parents and guardians about their programs and health services.
Founded in 2002 by Dr. Tommy Clark, a pediatrician and former professional soccer player, Grassroot Soccer initially focused on stopping the spread of HIV. (The Gates Foundation was an early funder of its work.) Today the organization works in more than 60 countries and has reached more than 18 million young people.
Studies have shown that its participants had better access to sexual and reproductive health services, were more likely to stick with their HIV treatment, and were less likely to experience depression.
That kind of impact gives everyone, even casual soccer fans like me, something to cheer about.

Inspired by a farmer
These married scientists are leading the way on HIV
The Abdool Karims revolutionized the fight against AIDS. Now they’re helping the world tackle COVID-19 too.
Quarraisha and Salim Abdool Karim are two of the most respected HIV/AIDS researchers in the world. This year, the wife-and-husband team has also helped shape the world’s response to COVID-19. But it was a more humble setting that sparked their careers in epidemiology more than 30 years ago.
They had met in medical school in their native South Africa before moving to New York City for graduate school. In 1988, shortly after they were married, they took a trip to Mexico, where they met up in a tiny village in the Sierra Madre mountains with a friend, a physician who had written a seminal textbook on health care in remote rural settings.
Outside the village’s health clinic, they saw a man pedaling a bicycle that was mounted on a stand and connected to a power cable. It turned out that a local farmer also doubled as the village’s dentist—a pretty good one, apparently—and volunteers would pedal the bike to power his drill.
“We watched how this community took their destiny in their own hands,” says Salim, “and they had the most amazing dental care from this bicycle powering a drill. It imprinted on us how people can really change their own world.”
It was a powerful lesson about the need for scientists to understand and collaborate with the people they’re trying to help. The experience in that village would shape the rest of their careers, especially when they created a research center in South Africa designed to address two of the biggest problems in HIV/AIDS in Africa.
By the 1990s, the disease was devastating the Abdool Karims’ home country—and still is today. One out of every five people in the world with HIV lives in South Africa. The couple saw two issues that were rarely on the agenda of other HIV experts. One was that young women were bearing a disproportionate burden in the epidemic, and that there was no way to control the epidemic if their needs weren’t addressed. The other was that people living with HIV are at a high risk of contracting and dying from tuberculosis—a link that’s now known as HIV-TB coinfection.
“These were very much our problems in Africa that few others were working on,” says Quarraisha, “and if we waited for solutions from elsewhere, it wasn’t going to come. We had to take the lead.”
In 2001, they brought together a group of researchers they felt could make a bigger impact on HIV and named the group CAPRISA (for the Center for the AIDS Program of Research in South Africa). Today CAPRISA runs three clinics where they provide antiretrovirals to people living with HIV and study new approaches to treating and preventing the disease. It is regarded as one of the world’s most influential AIDS research programs.
CAPRISA is probably best known for a landmark study published in 2010 proving for the first time that a microbicide—a gel that a woman could use before and after sex—can offer some protection from the virus. Scientists had been trying to make effective microbicides for nearly two decades, but the Abdool Karims’ formulation—one that used tenofovir, a drug normally given to people who already had HIV—was the first to offer any protection. Although the field has now moved on from microbicides and is focused on a more effective daily pill instead, the concept is still based on CAPRISA’s microbicide findings.
CAPRISA is as admired for the way it works as for its results. Inspired by the farmer-dentist they met in Mexico, Salim and Quarraisha make it a priority to empower the people they’re trying to help. They work closely with community leaders to make sure their research efforts are informed by realities on the ground and embraced by their neighbors. Here’s the story of one remarkable CAPRISA staff member, Gethwana Mahlase, and the way she represents the program in her community of Vulindlela.
Over the next few years, Quarraisha and Salim hope to build on their study of tenofovir as an HIV preventative. Right now, the best option is a pill you have to take every day, a regimen that can be hard to keep up. So CAPRISA is working on a form of the drug that could protect a woman for as long as a year at a time.
They’re also working on a fascinating approach called “broadly neutralizing antibodies,” which dates back several years. In 2012, they discovered that an HIV-positive woman in one of CAPRISA’s studies had a trait that was, as far as they knew, unique. The antibodies made by her immune system could attack not only the strain of HIV that she had, but also—this was the impressive part—80 percent of the other known strains of HIV from around the world. If they could isolate the cells that made these antibodies, reproduce them, and use them to create antibodies for other people, it would be a game changer.
After years of painstaking work with a number of partners, they were able to create the broadly neutralizing antibodies in a lab and test them in monkeys, with very positive results. Now the antibodies are being studied in humans for safety and, eventually, efficacy. If this approach works, you would need to get an injection just twice a year in order to get protection—a dosage that is far more practical than a daily pill. Success would also point the way toward the ultimate goal of an HIV vaccine.
Unfortunately, much of the Abdool Karims’ attention has been elsewhere this year. Drawing on their experiences from HIV and TB, they are helping guide the COVID-19 response in South Africa and around the world. It is a shame that they haven’t been able to focus on HIV/AIDS, but on the other hand, it is a reminder of how fighting old diseases like HIV helps the world prepare for new ones like COVID-19. Investing long-term in programs like CAPRISA—or work on polio or malaria—not only prevents deaths and disability from specific diseases, it also strengthens the overall field of global health. So when a pandemic comes along, we have a network of experts like Quarraisha and Salim ready to pitch in.
What strikes me about this couple is how upbeat they are, even in the face of devastating diseases like the coronavirus and HIV. Their motto at CAPRISA is, “Each day that you come to work, you should be looking for how today is going to be better than yesterday.” That is a lesson we can all take to heart.
Heroes
Strength in numbers
The story of this amazing woman living with HIV in Mozambique fuels my optimism about our world.
Last year, at an event in New York, I learned about an impressive woman whose story I want to share with you. Her name is Cacilda Fumo, she lives in Mozambique, and every year she helps save hundreds of lives—by reminding them they are not alone.
Mozambique has one of the highest HIV infection rates in the world. More than 1.6 million people—10 percent of the adult population—are living with HIV.
Cacilda was diagnosed with HIV in 2002. “When I first learned about it, I thought I would die,” she recalls. “I used to wake up early morning and check if I am alive or not.”
But then she started meeting other people living with HIV, and as their numbers grew so did her strength and her belief she would live. Cacilda was one of the first in Maputo to be open about her status. She started wearing a t-shirt emblazoned with a logo that reads: “HIV POSITIVE.”
At times, people rejected her because of her status. Many more in her community, however, admired her for her courage, helping her create an even larger circle of friends and supporters. They met every week, praying together, cooking together, and sharing their stories. Eventually, the group had about one hundred people, many of them receiving life-saving anti-retroviral treatment. Cacilda emerged as their leader.
About the same time, Mozambique’s Ministry of Health was struggling to improve the delivery of anti-retroviral treatment. While the program was successful in putting thousands of patients on treatment for the first time, medical staff were overburdened with caseloads. People on HIV treatment often walked miles to reach their clinic and waited in long lines to get care. Every year, about 30 percent of HIV patients dropped off their life-saving treatment.
Working with Doctors Without Borders, the government of Mozambique decided to try a new approach to simplify care to help keep more people on treatment. They started organizing small peer support groups for people on HIV treatment. The idea was simple. Make treatment easier by putting more control into the hands of the patients. A representative from each patient group could pick up all the drugs for the group each month, saving the rest of the group the hassle of going to the clinic. Members of the groups, known as Community antiretroviral therapy (ART) Groups or CAGs, would also support one another to ensure they were all staying on their treatment.
When the program reached Maputo, Cacilda was ready to join. She helped organize dozens of support groups from her network. Then she went one step further. She kept track of the groups, checking whether members were attending their meetings and taking their treatment. If someone fell off treatment, she took upon herself to locate them and find out what was wrong.
“We help people feel strong knowing they are not alone,” she says.
Some patients who stop treatment are addicted to alcohol and forget to take their treatment, she says. Some don’t understand how the treatment works and the stop taking their medication as soon as they feel better. Others get busy with their jobs and drift away.
Whatever the reason, Cacilda warns them of the dangers of stopping treatment and encourages them to restart. Her efforts to bring back residents of Maputo to treatment has become nearly full-time work. Most days residents of Maputo see Cacilda traveling on foot—which is remarkable because due to a childhood injury she uses crutches—through the dirty alleyways and crowded markets in search of people who have stopped treatment. She doesn’t give up until she finds them.
Cacilda’s persistence pays off—in lives saved. Cacilda estimates that she tracks down about 500 people every year and encourages them to resume their treatment.
That’s a remarkable achievement—one that proves how much difference one life can make in the world.
World AIDS Day
The fight against AIDS is filled with heroes. Learn how you can be one too.
Thanks to many heroes, the world has made amazing progress against HIV/AIDS.
On December 1st, the global community will observe World AIDS Day. This year I would like to mark it by highlighting the work of two heroes who are making a difference in the fight against this deadly disease.
Chief Jonathan Eshiloni Mumena is chief of the Kaonde people, who live along Zambia’s border with the Democratic Republic of Congo. Risking his position as his people’s leader, Chief Mumena challenged long-held traditions to encourage Kaonde men to embrace voluntary medical male circumcision as a strategy to prevent HIV transmission. (Male circumcision can reduce a man’s risk of acquiring or transmitting HIV by up to 60 percent.) I had the privilege of meeting Chief Mumena in 2012. His story is an inspiring tale of courageous leadership and deep compassion for his people.
Guided by her belief that health care is a basic human right, Dr. Krisana Kraisintu, a pharmacist from Thailand, has worked tirelessly to make medicines affordable to even the poorest in the world. Her development of generic versions of the lifesaving HIV drugs dramatically reduced treatment costs, saving and improving countless lives. She has also dedicated her pharmaceutical skills to reduce treatment costs for malaria and other diseases.
Of course, Chief Mumena and Dr. Kraisintu are just two of the countless individuals—doctors, policymakers, researchers, activists, and political leaders—whose contributions have helped turn the tide against the disease. Today, 19.5 million people receive lifesaving antiretroviral therapy, giving them the opportunity to live full, productive lives. Improved access to treatment has also meant that millions of babies are now born HIV-free.
Much of this progress has been made possible by the world’s enormous investments in efforts to defeat the epidemic, including the Global Fund to Fight AIDS, Tuberculosis and Malaria, and the U.S. HIV/AIDS program known as PEPFAR, President’s Emergency Plan for AIDS Relief.
Still, many challenges lie ahead in the fight against the AIDS epidemic.
Funding for HIV control has been flat and there’s talk about cuts as the world turns to other priorities. Cuts in funding for HIV/AIDS would lead to sharp increases in deaths and new infections, reversing the gains that have been made the last decade. That’s why it’s more important than ever for the world to reaffirm its commitment to this fight. We need more AIDS heroes—from health care workers and advocates to global leaders. Together, we can bring an end to this public health threat.
If you want to be a hero this World AIDS Day, support the (RED) Shopathon. Our foundation is matching every dollar raised—up to $15 million—to fight HIV/AIDS in Africa.
Eye opener
What my favorite chart leaves out
Every year, 2 million babies are stillborn. A simple retinal scanner can change that.
If you’re anything like me, you have a favorite chart. Mine has been the same for years. It plots under-five mortality year over year—a figure that has dropped by half since the turn of the century, from over 10 million deaths in 2000 to fewer than 5 million in 2023.
In my view, this data is the strongest evidence we have that progress is possible, even in tough times, and that the investments the world has made in vaccines, oral rehydration, bed nets, and better nutrition are working.
But there's a rule in global health statistics that complicates the story: To count as a death, someone must have first been born alive. It sounds simple and obvious. But in practice, it isn't. That's because every year, about 2 million pregnancies end in stillbirth, which is when a baby is lost at 28 weeks or later. That's late enough that the mother has been feeling the fetus move for months. Many parents have already picked out a name. Often, the loss occurs in the final stretch of a pregnancy, or during labor itself, when everyone was expecting a healthy birth.
These tragedies should be central to how we measure child survival. Instead, they've fallen through the cracks—not quite a maternal health issue, not quite a child mortality issue. The UN didn't publish its first full global estimate of stillbirths until 2020, and stillbirth research is still badly underfunded in both rich and poor countries.
What gets measured gets managed, as the saying goes—and what doesn't, well, doesn't.
The data reflects this disparity. Stillbirths have fallen just 34 percent since 2000, compared to 50 percent for under-five mortality over the same period. In 81 countries—mostly low- and middle-income—the stillbirth rate hasn't meaningfully improved at all in 25 years. For every one stillbirth in Europe, there are roughly 40 in sub-Saharan Africa.
What's frustrating is that we know what causes, and therefore how to prevent, most stillbirths. One of the biggest drivers is pre-eclampsia—a dangerous spike in blood pressure during pregnancy—which is responsible for half a million fetal deaths every year, along with 70,000 maternal deaths. Beyond that, the bulk of stillbirths stem from a cluster of conditions we understand well: maternal infections, obstetric complications during labor, and chronic conditions like untreated diabetes.
If we could catch these problems earlier, we'd have a much better chance of intervening before it's too late. But that's hard to do in the rural clinics where most pregnant women receive care, which often have unreliable electricity, no specialists, and little in the way of lab equipment. By the time pre-eclampsia is obvious, or gestational diabetes has gone unmanaged through the third trimester, the harm is often irreversible. Even emergency intervention may not help.
But a few months ago, I got to hold a device that has the potential to make a huge impact: the Remidio fundus camera. You hold it up to a patient's eye to get a high-resolution image of their retina in seconds, no dilation required. A community health worker with a few hours of training can use it. The device itself is about the size of a handheld video camera, battery-powered, and portable enough to carry from village to village.
Why the retina? It's the only place in the body where you can see blood vessels from the outside.
Remidio is a medtech startup out of India, and its camera was originally built to screen for diabetic eye disease. With an AI system running on a phone the camera plugs into, it can pick up early signs of the disease that would otherwise require blood draws and specialist follow-up to catch. It's already been used that way for more than 15 million patients in 40 countries.
But that same hardware, with different software, can also flag the conditions that drive so many dangerous pregnancies. Gestational diabetes sharply increases the risk of pre-eclampsia, preterm birth, and fetal death, and in most of rural sub-Saharan Africa or South Asia, it usually isn't screened for at all, because the standard test requires a lab. A retinal scan offers a different way in. Remidio’s device is currently being used in India to screen pregnant women for conditions that drive stillbirth. And researchers are now adapting the same hardware to screen for anemia and hypertension, too.
A tool like Remidio’s won’t solve the problem of stillbirths alone. We also need more skilled birth attendants, better emergency obstetric care, and stronger health systems. But small, portable, affordable diagnostics in the hands of community health workers are exactly the kind of lever that can start to move a number that hasn't moved in a long time. That's a big part of why the foundation committed $2.5 billion to women's health research and development last year, our largest investment in this area ever.
In 25 years, I hope my favorite chart in the world will have two lines on it: one tracking under-five mortality, and one tracking stillbirths. With the right commitment, I believe both will have fallen dramatically, and both could be approaching zero.

Life and death
How to cut child mortality in half… again
We already know how to save millions of newborn lives.
When Paul Allen and I started Microsoft, we had an ambitious goal: to put a computer on every desk and in every home. A lot of people thought we were out of our minds. But we believed in the power and potential of these machines to change the world. So every day, we came to work determined to make it happen. Now, it’s hard to imagine the world any other way. In a few short decades, that goal became reality for billions.
In 1990, the possibility that the world would be able to cut child mortality in half over the next thirty years would have seemed just as remote. But that’s exactly what happened. And I believe the world can do it again by 2040—we can cut child mortality in half once more—and get even closer to ending all preventable child deaths.
My introduction to this issue came 27 years ago, when I read a piece in The New York Times about deadly drinking water in the world’s poorest countries that contained the following statistic: “Diarrhea kills some 3.1 million people annually, almost all of them children.” Learning that shocked me to my core. There’s no greater pain than the death of a child. The death of millions of them—from something easily treatable in much of the world—is tragedy after tragedy on an almost unfathomable scale.
Before long, I was learning everything I could about global health generally and child mortality specifically. And shortly after, the Gates Foundation, which was just getting off the ground, made it our mission to fight preventable health disparities like this around the world—with an emphasis on children whose lives were being cut short before they ever had a chance.
My look ahead
What it takes to take a breath
New tools can help millions more newborns—and their mothers—survive.
In a rural health clinic, a baby tries to take her first breath.
But her lungs aren’t ready. Because she was born too early, they haven’t developed the slick, soap-like substance that keeps her air sacs from collapsing. Without that substance—called lung surfactant—breathing becomes a desperate, exhausting act.
She’s suffering from respiratory distress syndrome, or RDS, a life-threatening condition that appears within hours of birth in premature babies. Unless she gets treatment, her oxygen levels will plummet and her organs will begin to shut down. In one study from India, every baby born with RDS outside of a hospital setting died. In Ethiopia and Nigeria, RDS is responsible for almost half of all neonatal deaths.
At hospitals in higher-income countries, there’s a way to save her: a liquid form of organically-derived surfactant delivered directly into the lungs. But the procedure requires a highly-trained specialist to guide a breathing tube down the newborn’s windpipe—avoiding the stomach and placing it just right—at a cost of up to $20,000. In many parts of the world, that kind of care simply doesn’t exist.
But what if any healthcare worker anywhere in the world could simply hold a small nebulizer to the baby's face and deliver surfactant as an easy-to-administer inhalant?
This breakthrough—a synthetic surfactant that’s stable enough to be delivered through a nebulizer—is still in development, drive in part by Gates Foundation-supported research at Virginia Commonwealth University, Seattle Children’s Research Institute, and The Lundquist Institute. But its promise is extraordinary: an RDS treatment that costs less to make, doesn’t require a specialist to administer, and eliminates the need for intubation.
In other words, a therapy currently limited to the most advanced hospitals could become accessible in rural clinics and community settings around the world. Even in places with top-tier care, it could make treatment gentler, faster, and easier to deliver. In the United States—where RDS still affects 24,000 newborns a year—it could reduce the risks that come with intubating babies who might weigh only two or three pounds.
It’s the kind of innovation that could help solve one of the most persistent problems in global health: delivering intensive care without an intensive care unit, and helping millions more babies survive their first, most fragile moments.
Since 1990, the mortality rate for children under five has been cut by more than half—an amazing mark of global progress. But another statistic hasn’t fallen as fast: the number of babies who die in their first month of life.
Each year, 2.3 million newborns don’t survive past their first 28 days. And the day a baby is born is the most dangerous day of their life. The single biggest cause of these deaths is prematurity. Nearly 900,000 babies a year die from complications related to being born too soon, including infection, underdeveloped organs, and RDS.
Lower cost, easier-to-deliver surfactant is one way to give newborns a fighting chance, but it’s not the only way. Around the world, simple, affordable interventions already exist to identify at-risk pregnancies earlier, prevent more preterm births, and ensure a healthy birthing experience for mothers. Not only are these tools designed to work in the hardest-to-reach places—many of them start working even before a baby takes that first breath.
One of these innovations is a new type of ultrasound that’s changing who can catch the risks of preterm birth—and where.
Around the world, two thirds of women never get an ultrasound screening during pregnancy. Traditional machines are bulky and expensive, with specialized training required to operate them and interpret their results. In places where medical resources are already stretched thin, these types of ultrasounds are rarely an option.
But now, we have ultrasound devices about the size of a phone that can be operated by a nurse or midwife—no on-site specialist required. They weigh less than a pound. They process scans instantly. Their AI interface automatically detects high-risk conditions, like a shortened cervix or signs of early labor, so patients are referred for further care. And they have built-in telehealth functions to share images with remote specialists when needed.
By finding and flagging risks early, these AI-enabled ultrasounds are giving healthcare workers more time to act. In some cases, that means transferring the mother to a higher-level facility. In others, it means providing her with antenatal steroids—an inexpensive, underused treatment that speeds up fetal lung development—and, when needed, medications that delay labor just long enough for those steroids to take effect.
Early warning is essential, but we can save even more lives by going further upstream, starting with the health of pregnant women themselves.
In many low-income countries, undernutrition isn’t an exception. It’s the norm. And the intense demands of pregnancy make nutritional deficiencies even worse—putting mothers at increased risk of complications or death in childbirth, and raising the odds of early labor, low birth weight, and developmental delays for their babies.
But there’s a surprisingly simple fix: a daily supplement called MMS, or multiple-micronutrient supplementation, developed by the United Nations. It contains 15 essential vitamins and minerals for pregnancy—like zinc to reduce the risk of early labor, folic acid to help prevent birth defects, iron and vitamin D for healthy birth weight, and iodine for brain development. For an entire pregnancy, it costs just $2.60.
If MMS became the standard prenatal supplement in every low- and middle-income country, it could save nearly half a million newborn lives each year—and prevent serious complications in 25 million births by 2040.
The innovations above focus on treating, detecting, and preventing premature birth, a huge threat to newborn survival. But one of the most powerful ways to protect babies, preterm or full-term, is by ensuring their mothers stay healthy through pregnancy and childbirth.
When a woman dies during delivery, her baby is 46 times more likely to die in that first month of life. That’s why any serious effort to tackle infant mortality must also address postpartum hemorrhage—which tragically kills 70,000 women a year and is the leading cause of maternal mortality. Fortunately, two innovations are already helping healthcare workers catch and treat it before it becomes fatal.
The first is a calibrated drape—a simple plastic sheet placed under a woman during delivery that collects blood and shows, through printed measurement lines, exactly how much she’s losing. It gives healthcare workers a fast, accurate way to spot dangerous bleeding before it becomes life-threatening. The second is a one-time, 15-minute iron infusion during pregnancy that treats severe anemia—so if a woman does hemorrhage during childbirth, she’s less likely to experience catastrophic blood loss and more likely to survive.
Neither of these tools is complicated or expensive. But in combination, they can make a life-or-death difference for mothers and the babies who depend on them.
Taken together, these innovations form a chain of survival. They help mothers stay healthy through pregnancy. They detect problems before they become emergencies. They give fragile newborns a fighting chance. And they make it possible for families to celebrate a baby’s birth rather than mourning a loss.
Some of these tools are already saving lives. Others are on the verge of doing so. But their impact will be limited unless we prioritize and fund their delivery, not just their development. The world needs to make sure these innovations don’t get stuck in labs or warehouses—so they can reach the mothers and babies who need them most.
My look back
The breakthrough that transformed the Gates Foundation
This is the story of how better data helped us cut child mortality in half.
We started the Gates Foundation 25 years ago to save and improve children’s lives. But no one can solve a problem they don’t fully understand. And back in 2000, the world’s understanding of childhood mortality was occasionally inaccurate, often imprecise, and almost always incomplete.
That’s why I believe the breakthrough that transformed our foundation in the two-and-a-half decades since wasn’t a single vaccine or treatment—it was a revolution in the world’s understanding of childhood mortality. Through advances in how researchers collect and analyze global health data, we now know much more about what kills children, where these deaths occur, and why some kids are more vulnerable than others. By putting those insights to work, we’ve been able to save lives.
The first challenge was knowing exactly what was killing children.
Reading the 1993 World Development Report opened my eyes to the scale of the problem: Around 12 million children under the age of five were dying every year, with a staggering disparity between rich and poor countries. But the available data was fragmented and inconsistent. That made it difficult to understand trends or allocate resources effectively.
So the foundation helped create the Institute for Health Metrics and Evaluation at the University of Washington, to give a permanent home to the Global Burden of Disease study—originally developed in the 1990s by researchers at Harvard University and the World Health Organization. We wanted to expand it from a static snapshot of the problem into a regularly updated tool that tracked how diseases impact people around the world. That gave us something the world never had before: a comprehensive—and current—picture of child mortality across every country.
Measuring symptom-based causes of children’s deaths was an important step. But broad disease categories like “diarrhea” or “respiratory infection” didn’t give us enough information to act on. We needed to know which specific pathogens were responsible for the most common and fatal cases. So the Gates Foundation funded two landmark studies to find out.
In 2013, the Global Enteric Multicenter Study, or GEMS, found that rotavirus was causing 20 percent of lethal diarrhea cases in kids. At the time, diarrhea was the second-leading infectious killer of children. While oral rehydration therapy had already helped bring down deaths over previous decades, GEMS helped fast-track the rollout of a more targeted tool—a new rotavirus vaccine—in the hardest-hit countries, in close partnership with Gavi, the Vaccine Alliance.
A year later, the Pneumonia Etiology Research for Child Health study, or PERCH, revealed that respiratory syncytial virus, or RSV, was a much more common cause of severe pneumonia—the leading infectious killer of kids around the world—than previously understood. (And not just in low- and middle-income countries, where 97 percent of RSV deaths occur, but in higher-income ones too, where the virus still fills pediatric hospital wards each winter.) That prompted us to expand our investments in RSV prevention, which led to the approval of the first maternal vaccines for RSV in 2023.
But understanding what causes childhood mortality wasn’t enough on its own, because deaths aren’t distributed evenly across countries—or even within them. That’s why our second challenge was to figure out where exactly children were dying.
At the time, most health data was collected at national or regional levels. That masked major differences in disease burden from one community to the next—and made it harder to target interventions effectively.
To solve this second challenge, the foundation invested in new approaches to health mapping that combined satellite imagery, GIS technology, GPS data, and local health surveys. These maps gave Ministries of Health and implementing partners unprecedented, anonymized detail about disease patterns and population distribution, down to individual neighborhoods, that transformed how and where public health resources are deployed—while still preserving the privacy of the individual children and families in these places.
In Pakistan—one of just two countries where wild polio remains endemic—advanced mapping tools have helped vaccination teams reach and protect kids in settlements that weren’t on any official maps. Across sub-Saharan Africa, better geographic data has transformed the fight against malaria by revealing that transmission often clusters in small, hyper-local pockets. Through the Malaria Atlas Project, countries like Nigeria can now track those patterns more precisely—and then get bed nets, testing, and treatment where they’ll have the greatest impact.
With better knowledge of what was killing children, and where, one more fundamental question remained: Why might one child die from a disease while another—who lives in the same place, faces the same risks, and gets the same treatment—survives? This was our third big challenge.
In theory, traditional autopsies would provide the answer. But in the places where most childhood deaths still occur, these invasive procedures are often impossible to perform—too costly, and sometimes opposed for religious, cultural, or personal reasons.
So in 2015, the foundation launched the Child Health and Mortality Prevention Surveillance network, or CHAMPS, which now operates in nine countries across Africa and South Asia. Working with in-country partners, CHAMPS pioneered a new autopsy alternative—using minimally invasive tissue sampling—that can determine causes of death quickly and accurately while respecting local customs and beliefs.
Through CHAMPS, we discovered that childhood deaths rarely have a single cause. Instead, kids often have multiple conditions at the same time, with malnutrition frequently leaving them much more vulnerable to a whole host of infections. (While it rarely shows up on death certificates, it’s an underlying cause of death in nearly half of all child mortality cases.) That finding helped solidify nutrition as a core focus of the foundation’s global health work—and the research, innovation, and product development we invest in. On the ground, we’re supporting partners as they integrate nutrition screening into routine care and train healthcare workers to manage multiple risks at once.
CHAMPS also demonstrated that inadequate prenatal care is responsible for a majority of stillbirths, newborn deaths, and maternal deaths, prompting us to further expand access to maternal health services—like prenatal vitamins and AI-enabled ultrasounds—in the communities where we work.
But the biggest takeaway from CHAMPS is also the most hopeful—and a reminder of why we started the Gates Foundation in the first place: So many childhood deaths could be prevented with existing interventions. We just need to ensure they reach the right children at the right time.
Twenty-five years in, our work on child mortality is far from complete. Still, the impact of what we have learned has been enormous
The Global Burden of Disease, GEMS, and PERCH studies helped shift global priorities by showing the world what was really killing kids—and where new vaccines and treatments could make the biggest difference. Better geospatial tools have empowered countries to pinpoint disease hotspots, find previously unmapped settlements, and distribute life-saving resources where they’re needed most. And CHAMPS is giving governments better data on why children are dying—data that’s now shaping policies, improving reporting, and guiding more effective care.
Most importantly, even as the number of children born every year has gone up, the number of overall childhood deaths has fallen by more than half—from 11.3 million in 1990 to 4.5 million in 2022. Playing a part in making that happen is the best job I’ve ever had, and the most meaningful work I’ve ever done.
At the Gates Foundation, we used to say we could cut child mortality in half again by 2040. The truth, though, is that goal feels further out of reach now—not because the science has stalled, but because support for global health has. The progress we’ve been part of was only possible because governments around the world, including here in the U.S., made long-term commitments to saving lives and followed through. That kind of leadership gave millions of children who would have died a chance at life—and made life better for millions more.
The last 25 years have shown us what’s possible. The next 25 will depend on whether the world keeps showing up for the children who need it most.
Life Line
A phone call that saves lives
m-mama uses mobile technology and community drivers to solve one of global health’s most persistent problems: Getting pregnant women to hospitals in time.
In the United States, when someone has a medical emergency, we take for granted that an ambulance will arrive. It will get to some places faster than others—a disparity driven by wealth and other factors. Still, by calling 911, we’re immediately connected to a vast fleet of emergency vehicles plugged into a system that’s designed to get people to hospitals in times of crisis.
But what about countries where ambulances aren’t readily accessible? What about places where even cars are scarce, where the nearest hospital with surgical capacity might be 100 miles away down an unpaved road, and where a family facing a medical crisis has no reliable way to get there or pay for the journey?
This is the reality for millions of pregnant women across sub-Saharan Africa.
Thanks to modern medicine, we now know how to prevent most maternal and newborn deaths. And maternal mortality has declined by 40 percent over the last two decades as a result. But hundreds of thousands of women and babies still die every year from complications during pregnancy and childbirth, because they can’t get to a place where someone can treat them in time.
In maternal health, this problem is called the “second delay.” It’s a terrible tragedy, one that the Gates Foundation has been trying to address for years.
Back in 2013, partners including Vodafone Foundation and local health organizations started tackling this problem by asking a simple question in rural Tanzania: What if you could create something like a 911 system that worked with whatever transportation was available in a community? They tested the idea in a few districts, and it worked well enough that they decided to scale it up. They called it m-mama.
m-mama works like this: When a community healthcare worker identifies an emergency—maybe it’s severe bleeding after delivery, or a premature baby who can’t breathe—they call a free hotline. A trained nurse dispatcher uses an app to figure out what kind of care is needed and where it’s available, then coordinates whatever transportation makes sense for that location (a community driver with a car where there are good roads, a motorcycle where there aren’t, a boat for island communities, even a horse for mountainous terrain.) The dispatcher stays on top of everything, tracking the journey, alerting the receiving facility, and handling payment at the end.
The numbers speak for themselves. Since 2013, m-mama has responded to more than 125,000 emergencies and saved an estimated 5,266 lives. And in regions where m-mama launched, maternal emergency transports more than doubled. That means there was a massive need that was going unmet for far too long. About 58% of the deliveries transported by m-mama end up requiring a C-section, compared to the 10-15% you would expect in the general population. These are genuinely high-risk cases that would have likely ended in tragedy without emergency transport.
What’s especially impressive about m-mama’s impact is that it hasn’t required building new hospitals or buying any expensive equipment. Instead, it makes existing health systems work better by coordinating resources that are already there—ambulances, facilities, healthcare workers—and filling gaps with options that cost a fraction of what traditional ambulances do.
And it is scaling. m-mama started as a pilot serving 750,000 people and now reaches 62 million in Tanzania. It’s gone nationwide in Lesotho. It just launched in Malawi and is scaling up in Kenya. There are plans for more countries across sub-Saharan Africa, supported in part by the Beginnings Fund—a partnership that includes our foundation, the Mohamed bin Zayed Foundation for Humanity, and other organizations working to improve maternal and newborn health across Africa.
The program is financially sustainable too. Once the program is up and running, the governments cover operating costs. m-mama has proven it can be owned and run locally, which is the only way something like this works long-term.
m-mama is a reminder that not all breakthroughs in global health are new drugs or sophisticated technology. Sometimes they’re just smart ways of getting the right care to the right person at the right time. When a mother or baby is in crisis, minutes can make the difference between life and death.
m-mama is making sure those minutes count.
The Year Ahead
Optimism with footnotes
As we start 2026, I am thinking about how the year ahead will set us up for the decades to come.
I have always been an optimist. When I founded Microsoft, I believed a digital revolution powered by great software would make the world a better place. When I started the Gates Foundation, I saw an opportunity to save and improve millions of lives because critical areas like children’s health were getting so little money.
In both cases, the results exceeded my expectations. We are far better off than when I was born 70 years ago. I believe the world will keep improving—but it is harder to see that today than it has been in a long time.
Friends and colleagues often ask me how I stay optimistic in an era with so many challenges and so much polarization. My answer is this: I am still an optimist because I see what innovation accelerated by artificial intelligence will bring. But these days, my optimism comes with footnotes.
The thing I am most upset about is the fact that the world went backwards last year on a key metric of progress: the number of deaths of children under 5 years old. Over the last 25 years, those deaths went down faster than at any other point in history. But in 2025, they went up for the first time this century, from 4.6 million in 2024 to 4.8 million in 2025—an increase driven by less support from rich countries to poor countries. This trend will continue unless we make progress in restoring aid budgets.
The next five years will be difficult as we try to get back on track and work to scale up new lifesaving tools. Yet I remain optimistic about the long-term future. As hard as last year was, I don’t believe we will slide back into the Dark Ages. I believe that, within the next decade, we will not only get the world back on track but enter a new era of unprecedented progress.
The key will be, as always, innovation. Consider this: An HIV diagnosis used to be a death sentence. Today, thanks to revolutionary treatments, a person with HIV can expect to live almost as long as someone without the virus. By the 2040s, new innovations could virtually eliminate deaths from HIV/AIDS.
Budget cuts limit how many people benefit from lifesaving tools, as we saw to devastating effect last year. But nothing can erase the fact that for decades we didn’t know how to save people from HIV, and now we do. Breakthroughs are a bell that cannot be unrung. They ensure that we will never go back to the world in 2000 where over 10 million children died from preventable causes every year—and they form the core of my optimism about where the world is headed.
But as I mentioned, there are footnotes to my optimism. Although the innovation pipeline sets us up for long-term success, the trajectory of progress hinges on how the world addresses three key questions.
1.
Will a world that is getting richer increase its generosity toward those in need?
The “golden rule” precept is more important now than ever with the record disparities in wealth. This idea of treating others as you wish to be treated does not just apply to rich countries giving aid. It must also include philanthropy from the wealthy to help those in need—both domestically and globally—which should grow rapidly in a world with a record number of billionaires and even centibillionaires.
Through the Giving Pledge, I get to work with a number of incredible philanthropists who set a great example by giving away substantial portions of their wealth in smart ways. However, more needs to be done to encourage higher levels of generosity from the rich and to show how fulfilling and impactful it can be.
Turning to aid budgets for poor countries, I am worried about one number: If funding for health decreases by 20 percent, 12 million more children could die by 2045. I know cuts won’t be reversed overnight, even though aid represented less than 1 percent of GDP even in the most generous countries. But it is critical that we restore some of the funding. The foundation’s Goalkeepers report lays out what is at risk and how the world can best spend the aid it gives.
I will spend much of my year working with partners to advocate for increased funding for the health of the world’s children. I plan to engage with a number of communities, including health care workers, religious groups, and members of diaspora communities to help make this case.
2.
Will the world prioritize scaling innovations that improve equality?
Some problems require doing far more than just letting market incentives take their course.
The first critical area is climate change. Without a large global carbon tax (which is, unfortunately, politically unachievable), market forces do not properly incentivize the creation of technologies to reduce climate-related emissions.
Yet only by replacing all emitting activities with cheaper alternatives will we stop the temperature increase. This is why I started Breakthrough Energy 10 years ago and why I will continue to put billions into innovation.
The world has made meaningful progress in the last decade, cutting projected emissions by more than 40 percent. But we still have a lot of innovation and scaling up to do in tough areas like industrial emissions and aviation. Government policies in rich countries are still critical because unless innovations reach scale, the costs won’t come down and we won’t achieve the impact we need.
If we don’t limit climate change, it will join poverty and infectious disease in causing enormous suffering, especially for the world’s poorest people. Since even in the best case the temperature will continue to go up, we also need to innovate to minimize the negative impacts.
This is called climate adaptation, and a critical example is helping farmers in poor countries with better seeds and better advice so they can grow more even in the face of climate change. Using AI, we will soon be able to provide poor farmers with better advice about weather, prices, crop diseases, and soil than even the richest farmers get today. The foundation has committed $1.4 billion to supporting farmers on the frontlines of extreme weather.
I will be investing and giving more than ever to climate work in the years ahead while also continuing to give more to children’s health, the foundation’s top priority. The need to ensure money is spent on the most important priorities was the topic of a memo I wrote in the fall.
A second critical area where the world must focus on innovation-driven equality is health care. Concerns about healthcare costs and quality are higher than ever in all countries.
In theory, people should feel optimistic about the state of health care with the incredible pipeline of innovations. For example, a recent breakthrough in diagnosing Alzheimer’s will revolutionize how we test for—and ultimately prevent—this disease, saving billions of dollars in costs. (Funding Alzheimer’s research is a particular focus for me.) There’s similar progress on obesity and cancer, as well as on problems in developing countries like malaria, TB, and malnutrition.
Despite so much progress, however, the cost and complexity of the system means very few people are satisfied with their care. I believe we can improve health care dramatically in all countries by using AI not only to accelerate the development of innovations but directly in the delivery of health care.
Like many of you, I already use AI to better understand my own health. Just imagine what will be possible as it improves and becomes available for every patient and provider. Always-available, high-quality medical advice will improve medicine by every measure.
We aren’t quite there yet—developers still have work to do on reliability and how we connect the AI to doctors and nurses so they are empowered to check and override the system. But I’m optimistic we will soon begin to scale access globally. I am following this work so the Gates Foundation and partners can make sure this capability is available in the countries that need it most—where there aren’t enough medical personnel—at the same time it is available elsewhere. We are already working on pilots and making sure that even relatively uncommon African languages are fully supported.
Governments will have to play a central role in leading the implementation of AI into their health systems. This is another case where the market alone won’t and can’t provide the solution.
A third and final area I will mention briefly is education. AI gives us a chance for the kind of personalized learning to keep students motivated that we have dreamed of in the past. This is now a focus of the Gates Foundation’s spending on education, and I am hopeful it will be empowering to both teachers and students. I’ve seen this firsthand in New Jersey, and it will be game changing as we scale it for the world.
All three of these areas—climate, health, and education—can improve rapidly with the right government focus. This year I will spend a lot of time meeting with pioneers all over the world to see which countries are doing the best work so we can spread best practices.
3.
Will we minimize negative disruptions caused by AI as it accelerates?
Of all the things humans have ever created, AI will change society the most. It will help solve many of our current problems while also bringing new challenges very different from past innovations.
When people in the AI space predict that AGI or fully humanoid robots will come soon and then those deadlines are missed, it creates the impression that these things will never happen. However, there is no upper limit on how intelligent AIs will get or on how good robots will get, and I believe the advances will not plateau before exceeding human levels.
The two big challenges in the next decade are use of AI by bad actors and disruption to the job market. Both are real risks that we need to do a better job managing. We’ll need to be deliberate about how this technology is developed, governed, and deployed.
In 2015, I gave a TED talk warning that the world was not ready to handle a pandemic. If we had prepared properly for the Covid pandemic, the amount of human suffering would have been dramatically less. Today, an even greater risk than a naturally caused pandemic is that a non-government group will use open source AI tools to design a bioterrorism weapon.
The second challenge is job market disruption. AI capabilities will allow us to make far more goods and services with less labor. In a mathematical sense, we should be able to allocate these new capabilities in ways that benefit everyone. As AI delivers on its potential, we could reduce the work week or even decide there are some areas we don’t want to use AI in.
The effects of this disruption are hard to model. Sometimes, when a game-changing technology improves rapidly, it drives more demand at lower cost and, by making the world richer, increases demand in other areas. For example, AI makes software developers at least twice as efficient, which makes coding cheaper while also creating demand elasticity for code. (Computing is a good historical example where lower costs actually caused the overall market to grow.)
Even with this complexity, the rate of improvement is already starting to be enough to disrupt job demand in areas like software development. Other areas like warehouse work or phone support are not quite there yet, but once the AIs become more capable, the job disruption will be more immediate.
We’re already starting to see the impact of AI on the job market, and I think this impact will grow over the next five years. Even if the transition takes longer than I expect, we should use 2026 to prepare ourselves for these changes—including which policies will best help spread the wealth and deal with the important role jobs play in our society. Different political parties will likely suggest different approaches.
By including these footnotes, particularly the last one, some readers may find my continued optimism even more surprising. But as we start 2026, I remain optimistic about the days ahead because of two core human capabilities.
The first is our ability to anticipate problems and prepare for them, and therefore ensure that our new discoveries make all of us better off. The second is our capacity to care about each other. Throughout history, you can always find stories of people tending not just to themselves or their clan or their country but to the greater good.
Those two qualities—foresight and care—are what give me hope as the year begins. As long as we keep exercising those abilities, I believe the years ahead can be ones of real progress.

Just the facts
Health aid saves lives. Don’t cut it.
Here’s the proof I’m showing Congress.
I’ve been working in global health for 25 years—that’s as long as I was the CEO of Microsoft. At this point, I know as much about improving health in poor countries as I do about software.
I’ve spent a quarter-century building teams of experts at the Gates Foundation and visiting low-income countries to see the work. I’ve funded studies about the effectiveness of health aid and pored over the results. I’ve met people who were on the brink of dying of AIDS until American-funded medicines brought them back. And I’ve met heroic health workers and government leaders who made the best possible use of this aid: They saved lives.
The more I’ve learned, the more committed I’ve become. I believe so strongly in the value of global health that I’m dedicating the rest of my life to it, as well as most of the $200 billion the foundation will give away over the next 20 years.
People in global health argue about a lot of things, but here’s one thing everyone agrees on: Health aid saves lives. It has helped cut the number of children who die each year by more than half since 2000. The number used to be more than 9 million a year; now it’s fewer than 5 million. That’s incontrovertible.
So when the United States and other governments suddenly cut their aid budgets the way they've been doing, I know for a fact that more children will die. We’re already seeing the tragic impact of reductions in aid, and we know the number of deaths will continue to rise.
A study in the Lancet looked at the cumulative impact of reductions in American aid. It found that, by 2040, 8 million more children will die before their fifth birthday. To give some context for 8 million: That's how many children live in California, Texas, Florida, New York, Pennsylvania, and Ohio combined.
I’ve submitted written testimony on this topic, which you can read below, for the Senate Appropriations Committee hearing occurring later today. In it, I discuss what’s already happened and what needs to happen next.
Testimony to the United States Senate Committee on Appropriations
June 25, 2025
Over the past 25 years—the same span of time I spent leading Microsoft—I have immersed myself in global health: building knowledge, deepening expertise, and working to save lives from deadly diseases and preventable causes. During that time, I have built teams of world-class scientists and public health experts at the Gates Foundation, studied health systems across continents, and worked in close partnership with national and local leaders to strengthen the delivery of lifesaving care. I have visited hundreds of clinics, listened to frontline health workers, and spoken with people who rely on these programs. Earlier this month, I traveled to Ethiopia and Nigeria, where I witnessed firsthand the impact that recent disruptions to U.S. global health funding are having on lives and communities.
Global health aid saves lives. And when that aid is withdrawn—abruptly and without a plan—lives are lost.
Yet, in recent months, some have questioned whether the foreign assistance pause has caused harm. Concerns about the human impact of these disruptions have been dismissed as overstated. Some people have even claimed that no one is dying as a result.
I wish that were true. But it is not.
It is important to note that while this hearing is about the Trump Administration’s $9 billion recission package, what is really at stake is tens of billions of dollars in critical aid and health research that has been frozen by DOGE with complete disregard for the Congress and its Constitutional power of the purse.
In the early weeks of implementing the foreign aid freeze, DOGE directives resulted in the dismissal of nearly all United States Agency for International Development (USAID) staff and many personnel at the Centers for Disease Control and Prevention (CDC). Some funding was later restored to allow for the continuation of what has been categorized as "lifesaving" programs. However, to date that designation has been applied narrowly and with limited transparency, in an inconsistent manner, often prioritizing emergency interventions when a patient is already in critical condition over essential preventative or supportive care.
For example, providing a child with a preventive antimalarial treatment, ensuring access to nutrition so that HIV/AIDS medications can be properly administered, testing pregnant women for HIV to see if they are eligible for treatment to prevent transmission to their children or identifying and treating tuberculosis cases early have not consistently qualified for exemption. As a result, many of the programs delivering these services have been suspended, delayed, or scaled back.
Recent reporting from the New York Times has shed light on the devastating human cost of the abrupt aid cuts. One especially tragic example is Peter Donde, a 10-year-old orphan in South Sudan, born with HIV, who died in February after losing his access to life-saving medication when USAID operations were suspended. His story is one of many.
During my recent visit to Nigeria, I met with leaders from local nonprofit organizations previously funded by the United States. One group shared the remarkable progress they had made in tuberculosis detection and treatment. In just a few years, case identification increased from 25 percent to 80 percent, a critical step toward breaking transmission and reducing the overall disease burden. That progress has now stalled. The grants that enabled this work were tied to USAID staff who have been dismissed, and with their departure, the funding ended, and the work stopped.
The broader effects of these sudden shifts are difficult to overstate. For example, funding for polio eradication has been preserved in the State Department budget but cut from the CDC—even though the two agencies collaborate closely on the program. This type of fragmented decision-making has left implementing organizations uncertain about staffing and operations. Many no longer feel confident that promised U.S. funds will materialize, even when awards have been announced. In some cases, staff continue to work without pay. Some organizations are approaching insolvency.
Meanwhile, in warehouses across the globe, food aid and medical supplies sourced from American producers are sitting idle—spoiling or approaching expiration—because the systems that once distributed them have been disrupted. Clinics are closing. Health workers are being laid off. HIV/AIDS patients are missing critical doses of medication. Malaria prevention campaigns, including bed net distributions and indoor spraying, have been delayed or canceled, leaving hundreds of millions of people unprotected at the peak of transmission season.
Efforts to track data that would illustrate the severity of this worsening crisis have also been severely compromised. Many of the people responsible for collecting and reporting health information—health workers, statisticians, and program managers—have been laid off or placed on leave. The systems that once monitored health outcomes are shutting down, and the offices where that data was once analyzed now sit empty. As a result, the true scope of the harm is becoming harder to measure, just as the need for information is most urgent.
The situation we face is not about political ideology, and it is not a debate over fiscal responsibility. U.S. government spending on global health accounts for just 0.2 percent of the federal budget. Shutting down USAID did nothing to reduce the deficit. In fact, the deficit has grown in the months since.
Furthermore, many of the allegations regarding waste, fraud, and abuse have proven to be unsubstantiated. For example, the widely circulated claim that USAID sent millions of dollars’ worth of condoms to the Gaza Strip is inaccurate. In fact, the Wall Street Journal reported that the program allocated approximately $27,000 for condoms as part of an HIV transmission prevention initiative—not in the Middle East, but in Gaza Province, Mozambique.
What we are witnessing because of the rapid dismantling of America’s global health infrastructure is a preventable, human-caused humanitarian crisis—one that is growing more severe by the day. DOGE made a deadly mistake by cutting health aid and laying off so many people. But it is not too late to undo some of the damage.
A Record of Progress—and What is at Risk
Since 2000, child mortality worldwide has been cut in half. Deaths from HIV/AIDS, tuberculosis, and malaria have declined significantly. And we are on the verge of eradicating only the second human disease in history: polio. These are not abstract statistics; they represent tens of millions of lives saved. None of this progress would have been possible without consistent, bipartisan U.S. leadership and investment.
Over the past several decades, the United States has built one of its most strategic global assets: a respected and robust public health presence. This leadership is not just a humanitarian achievement—it is a core pillar of American soft power and security. For example, a Stanford study analyzing 258 global surveys across 45 countries found that U.S. health aid is strongly linked to improved public opinion of the United States. In countries and years where U.S. health aid was highest, the probability of people having a very favorable view of the United States was 19 percentage points higher. Other forms of aid—like military or governance—did not have the same effect. Another example is the 2014 Ebola outbreak in West Africa. The rapid deployment of U.S. scientists, health workers, and CDC teams helped contain the virus before it could spread globally. Their presence allowed the U.S. to help shape the response strategy, speed up containment, and prevent a wider outbreak. Many African countries are facing the dual burden of rising debt and pressing health needs, forcing painful choices between repaying creditors, and protecting their citizens. Helping them navigate this challenge is not just the right thing to do—it is a strategic imperative. If the United States retreats, others will fill the gap, and not all of them will bring our values, our priorities, or our interests to the table. Preserving American global influence will require restoring the staff, systems, and resources that underpin it—before the damage becomes irreversible.
I understand the fiscal pressures facing Congress. I recognize the need to prioritize spending and to hold programs accountable for results. I also share the Trump Administration’s commitment to promoting efficiency and encouraging country-led solutions. But I believe those goals can—and must—be pursued while still protecting the programs that deliver the highest return on investment and the greatest impact on human lives.
The United States’ support for Gavi, the Vaccine Alliance; the Global Fund to Fight AIDS, Tuberculosis, and Malaria; the President’s Emergency Plan for AIDS Relief (PEPFAR); and the Global Polio Eradication Initiative (GPEI) represent some of the smartest, most effective investments our country has ever made. These initiatives are proven, strategically aligned with American interests, and cost-effective on a scale few other government programs can match.
Together, Gavi and the Global Fund have helped save more than 82 million lives. Gavi has helped halve childhood deaths in the world’s poorest countries and returns an estimated $54 for every $1 invested. The Global Fund has contributed to a 61% reduction in deaths from HIV/AIDS, TB, and malaria. PEPFAR has saved over 26 million lives and helped millions of children be born HIV-free. GPEI has brought us closer than ever to the eradication of polio. Pulling back now would not only jeopardize these historic gains—it would invite a resurgence of preventable disease, deepen global instability, and undermine decades of bipartisan American leadership.
This is not a forever funding stream for the U.S. Government. These programs set out clear pathways for countries to “graduate” from aid, which many have already done. For example, nineteen countries, including Viet Nam and Indonesia, have successfully graduated from Gavi support and now fully finance their own immunization programs. Others—from Bangladesh to Cote d'Ivoire—are on track to do the same. This is how U.S. development policy should work: catalytic, cost effective, and designed to help countries become self-reliant and drive their own progress. I agree that aid funding should have an end date, but not overnight. The most effective path to that end date is innovation. By investing in the development and delivery of new medical tools and treatments, we can drive down the cost of care, and in some cases, make diseases that were once a death sentence treatable, or even curable. Advances in therapies for chronic conditions like sickle cell disease, HIV, or certain types of cancers could transform lives and health systems. American innovation offers a sustainable exit strategy—one that reduces long-term costs, allows the United States to responsibly step back, and builds lasting trust and good will that far exceed the original investment.
Over the past 25 years, the Gates Foundation has invested nearly $16 billion in global health partnerships like Gavi, the Global Fund, and GPEI. We will continue to invest, through innovation, research, and close coordination with partners. But no private institution—or coalition of them—can replace the scale, reach, or authority of the U.S. government in delivering lifesaving impact at the global level.
The decisions made in the coming weeks will shape not only the lives saved in the near term—but the legacy of American leadership for generations to come.
Download a PDF of the testimony with appendices that include reflections from Gates Foundation staff in Africa on the impact of the U.S. aid cuts; analytical projections from respected organizations; and a selection of first-hand reporting from reputable news organizations and journalists.

No laughing matter
A gut-wrenching problem we can solve
Diarrhea used to be one of the biggest killers of kids—but now it’s one of the greatest global health success stories.
In 1997, I came across a New York Times column by Nick Kristof that stopped me in my tracks. The headline was “For Third World, Water Is Still a Deadly Drink,” and it included a statistic I almost didn’t believe: Diarrhea was killing 3.1 million people every year—most of them kids under the age of five.
I didn’t know much about the problem back then, except that it seemed so solvable. After all, in rich countries it felt like it already had been. My oldest daughter was a toddler at the time, and we never worried that an upset stomach would kill her. None of the other parents I knew worried about that either.
But in much of the world, kids without clean drinking water or basic sanitation were constantly being exposed to rotavirus, cholera, shigella, typhoid, and more—dangerous pathogens that spread easily when toilets are scarce and water is contaminated.
Nick’s column ended up changing my life. I sent it to my dad with a note: “Maybe we can do something about this.” He agreed. And after he traveled to Bangladesh to see the problem firsthand, we made a $40 million investment in vaccine research for diarrheal diseases. That grant helped shape what would become the Gates Foundation—and kickstarted decades of progress that’s now saved millions of lives.
Within a few years, I stepped away from Microsoft to focus on this work full-time. Once you’ve seen what’s possible in global health, it’s hard to do anything else.
When we first got involved, diarrhea was one of the biggest killers of kids worldwide. But over the past two and a half decades, these deaths have dropped by more than 70 percent.
The biggest breakthrough came from making vaccines for rotavirus, the leading cause of severe diarrhea and death in kids, affordable and accessible. When the vaccines first debuted in the early 2000s, they were priced at around $200 per dose—which meant they were completely out of reach for most families in most of the world. So the foundation partnered with vaccine manufacturers in India like Bharat Biotech and Serum Institute to develop high-quality, low-cost alternatives. Today, rotavirus protection costs about a dollar.
But getting the vaccines developed was only half the challenge. The other half was getting them to the kids who needed them most.
That’s where Gavi came in. The organization was set up a few years earlier to help low-income countries pay for lifesaving vaccines that had existed for decades but weren’t reaching the world’s poorest. But they were well-positioned to do the same with a new vaccine, and they did—purchasing the rotavirus vaccine for millions of children and supporting countries as they added it to their routine immunization programs. USAID played a huge role in this work, too, by helping local governments train community health workers and strengthen their vaccine delivery systems. Meanwhile, public health campaigns promoted treatments like oral rehydration salts and zinc supplements that can save a sick child's life for pennies. (Think of it as the medical-grade equivalent of Pedialyte.)
As all this was happening, countries quietly made enormous progress on clean water and sanitation too. Since 1990, 2.6 billion people around the world have gained access to safe drinking water—and the number of people who now have basic sanitation similarly has skyrocketed. These improvements help break a cycle where kids get sick, recover, and then get reinfected a few weeks later.
Despite the incredible progress, around 340,000 kids under five are still dying from diarrhea each year.
Part of the problem is that many kids still don't get vaccinated. Some live in places where health systems are weak or vaccines are hard to transport and store. Others are caught in conflict zones that make it dangerous for health workers to reach them.
And new challenges make the fight against diarrheal diseases even harder than it was 25 years ago. Shigella—one of the nastiest bacterial causes of diarrhea—is becoming more and more resistant to antibiotics, and we still don't have a vaccine. Climate change is making cholera and typhoid outbreaks more frequent, as floods contaminate water supplies and droughts force people to drink from unclean, unsafe sources.
For malnourished kids, everything is harder: They're more vulnerable to diarrheal diseases in the first place, and their damaged digestive tracts don't respond as well to oral vaccines or treatments. For families barely scraping by, diarrhea is both a medical crisis and an economic disaster. Parents miss work to care for sick kids. Kids miss school. Expenses pile up. It's one of the ways that disease keeps families trapped in poverty—and one of the reasons that a country’s public health is key to its development.
The encouraging news is that there’s a promising pipeline of innovations that builds on what we already know and could save even more lives.
At the foundation, we’re supporting scientists who are working on a vaccine for Shigella, which has become the leading bacterial cause of childhood diarrhea. We’re also funding efforts to combine different vaccines into a single shot, which would lower costs and make things easier for health workers and kids alike.
New delivery methods could make a big difference too. One example: vaccine patches for measles that don’t require needles, refrigeration, or trained staff to administer them. Just peel, stick, and protect.
We've already learned a lot about how chronic infections damage kids’ guts and make it harder for them to absorb nutrients or respond to vaccines. Now, scientists are researching how to repair that damage, which could help the sickest kids recover faster.
And outside the lab, environmental monitoring tools are being developed to detect early signs of outbreaks—by regularly testing sewage for typhoid, for instance. It’s like having an early warning system for epidemics.
We can’t afford to look away now
I’ve been talking about diarrhea for 25 years, even though it makes some people squeamish, because it’s a microcosm of global health. It’s proof that the world can come together to solve big problems. When we refuse to accept that some children won’t make it to their fifth birthday, we can save millions of lives.
But it’s also a warning of what can happen when we look away.
Right now, global health funding is being slashed around the world. According to one estimate, cuts to aid from the U.S. have already led to almost 60,000 additional childhood deaths from diarrhea. If nothing changes, by next January that number could rise to 126,000. These are projections, not final counts, but the reality is undeniable: When lifesaving programs are eliminated, kids pay the price.
Diarrhea is one of the most solvable problems in global health. We’ve come a long way, but we’re not done yet.
Lung Story Short
A book about tuberculosis, and everything else
Here’s how John Green turned a forgotten disease into a #1 NYT bestseller.
What do Adirondack chairs, Stetson hats, the city of Pasadena, and World War I have in common? According to John Green, all of their origin stories include tuberculosis.
In his new book, John argues that it’s impossible to separate the deadliest disease in history from, well, the rest of history. Adirondack chairs were designed by a man who vacationed in the New York mountains—a popular spot for TB patients seeking fresh air—and soon became staples of sanatorium porches across the country. John B. Stetson, who had TB himself, traveled west for dry mountain air and invented the cowboy hat to protect from sun, wind, and rain. Pasadena became a hub for TB treatment in the late 1800s, and TB “tourism” was a major driver of the city’s early economy, real estate, and identity. And the teenage assassins who killed Archduke Franz Ferdinand, which kicked off World War I? They were more willing to die for their cause since they were already dying of TB.
No wonder John calls this book Everything Is Tuberculosis. In so many ways, TB shaped the world we live in. Even though the disease is now both rare and treatable in rich countries, in poorer places it’s on the rise and still a death sentence for so many.
John is best known as the author of some of the best young adult novels of all time (at least according to my daughter Phoebe, whose encouragement led me to read The Fault in Our Stars and Turtles All the Way Down). So a lot of people were surprised when he announced that his next book would be about global health—about a disease most people in the western world think of in the past tense.
I wasn’t. After all, I first met John over a decade ago, when he joined me on a Gates Foundation trip to Ethiopia. While traveling, we talked about a lot of the big questions John wrestles with in Everything Is Tuberculosis—like why the place a person is born influences their odds of surviving childhood (or childbirth), and what people like us can do to increase those odds.
Since then, John has been an invaluable partner to the foundation, bringing his curiosity and clarity to our events and helping raise awareness of our work. But he’s also become a powerful advocate for global health in his own right. I don’t know anyone else who could turn a book about tuberculosis into a number one New York Times bestseller.
Everything Is Tuberculosis is poignant, smart, and at times infuriating. At its heart is the story of a boy named Henry, whom John met at a TB clinic in Sierra Leone. Henry was just six when he started showing classic signs of the disease: fatigue, weight loss, night sweats. But the first tests he got came back negative, so he was sent home from the hospital. By the time he was eventually diagnosed, Henry was already very sick.
He began treatment with the standard cocktail of decades-old antibiotics. It’s a brutal regimen that involves months of pills, painful injections, constant side effects—and, once the infection starts to subside, aching hunger from having an appetite again. The drugs only work if they’re taken consistently and on schedule, but that’s often unrealistic for patients. In much of the world, TB treatment means walking miles to a clinic, missing work or school, going into debt, and facing social stigma and isolation. Even though Henry’s mom did everything she could to support him, there were interruptions to his treatment, and eventually the TB became drug-resistant.
In the end, Henry got lucky. Even as he got sicker and ran out of options, his doctors wouldn’t give up on him. They fought to get him access to a personalized drug regimen—something that’s rarely available to kids in poor countries. That care ended up saving his life, and today Henry is thriving. After years stuck in the hospital, he’s caught up academically and now in university (and even has a YouTube channel where he shares his journey and advocates for other TB patients). John doesn’t romanticize Henry’s story as some kind of miracle. Instead, he uses it as proof: that TB is curable, that good care works, and that the real question isn’t whether we can save lives—but whether we’re willing to make that care available to everyone.
Even though John finished writing the book last year, he nails the urgency of this moment. He shows how a disease that most people in rich countries have forgotten is still killing over a million people a year, and how easily that number could keep climbing. That’s especially true now, as foreign aid cuts disrupt TB care across the globe. Henry might not be alive today if it weren’t for organizations like Partners In Health—funded in part by U.S. health aid—which fought to get him the treatment he needed. These aid cuts will be devastating for kids like him, who may lose access to treatment altogether. They’ll also lead to more interrupted care, more cases, more drug resistance, and more strains of an infectious disease that will be harder and more expensive for the entire world to contain.
This is a book about the central challenge of global health today: the reality that, in John’s words, “the cure is where the disease is not, and the disease is where the cure is not.”
A book about tuberculosis could be pretty boring, but John makes it super compelling by weaving in TB’s long and strange history, from the myth that it only afflicted white people, to the theory that it inspired creative genius, to its influence on Victorian beauty standards. (I didn’t know about those last two… or the Stetson hats.) If you’re familiar with John’s work, this approach won’t surprise you. He has a gift for getting people to care about things they might not think are “for me,” whether that’s poetry, astrophysics, or infectious disease.
John ends Everything Is Tuberculosis with a stirring call to action. He makes the case that saving lives from TB isn’t really a scientific challenge anymore; it’s a moral one. I largely agree. But I also think there are more reasons for hope than the book lets on.
While John is clear-eyed about the failures of the past and present—the slow pace of progress, the sky-high prices of new TB drugs, the inequality that determines who gets treated and who doesn’t—he doesn’t spend much time on what comes next. Having spent the last two-and-a-half decades investing in the science behind TB care through the Gates Foundation, I’ve seen a different side of the story. I know what’s in the pipeline, and I know what’s possible.
Today, we’re closer than ever to breakthroughs that could change everything about how we treat and even prevent TB: shorter drug regimens, better diagnostics, and even vaccines. These tools will only make a difference if they’re affordable enough to reach kids like Henry. But I think it’s important to recognize that the companies often criticized for pricing are also, ironically, the only ones that have been willing to invest in TB at all. We need to keep working with them as partners, keep the innovation coming, and keep bringing costs down.
If we do, we can make Henry’s story of survival the norm, not the exception—and make tuberculosis a disease of the past, not the future.
Such great heights
This heroic nurse climbs 1000-foot ladders to save lives
Agnes Nambozo goes to extraordinary lengths to vaccinate children in Uganda.
How do you get to work? Some people roll out of bed and move 10 feet to their desk. Others walk to the office or take public transit. I usually drive a car.
No matter how you get there, I guarantee that your commute isn’t as wild as Agnes Nambozo’s: She regularly climbs a rickety ladder that is nearly 1,000 feet tall—or 300 meters—before she can start work for the day.
Agnes is a nurse based in Buluganya, located in the shadow of Mount Elgon in eastern Uganda. Like many nurses in rural communities across sub-Saharan Africa, she wears a lot of different hats. She might spend one day delivering babies and treating wounds and the next as a health educator, promoting good nutrition and sanitation in her community. The days Agnes believes she makes the biggest difference, though, are the ones when she treks deep into the Ugandan countryside to vaccinate children.
Uganda has done an amazing job of reducing childhood mortality over the last 25 years. In 2000, about 145 children died per every thousand live births. By 2023, that figure had dropped to fewer than 40 deaths per 1,000 births. A lot of that progress can be attributed to vaccines and vaccinators like Agnes.
Eastern Uganda is a gorgeous place, but parts of it are incredibly difficult to cross. Many of the communities Agnes visits are high in the mountains. Some are only accessible by ladders, which act as links between communities. Older children can climb down them to go to school, but they are too steep for the little ones. Mothers can’t safely carry their babies down the ladders to the health clinic, so Agnes comes to them.
When Agnes was a little girl, she wanted to be a police officer—until her mom convinced her the job was too dangerous. Instead, she took a nursing course. She fell in love with the profession, even though it ended up being a much riskier job than her mom ever imagined. She travels to the villages to vaccinate kids in all kinds of weather. It’s often rainy in the mountains, and the ladders become slippery. “The ladders are risky because you might miss a step,” she says. “If you are lucky, you can get a fracture. If you’re not lucky, you can lose your life.”
On the days when she heads into the field to vaccinate children, Agnes leaves her house by 6:00 am. She takes a taxi from where she lives in Sironko to Buyaga, a town closer to where the health clinic is located. Cars can’t drive on the road to the clinic, so she takes a motorbike for the last stretch.
She arrives at the clinic around 8:00 am and starts packing for the day. Rural vaccinators like Agnes must carry their supplies on their backs, and there’s an art to making sure everything is loaded properly. The vaccines must be kept cold so she wears a heavy insulated backpack stuffed with ice packs.
Agnes then hops on another motorbike to a staging location before heading off on foot to the ladders. By the time she reaches the village and starts setting up to immunize the community, it’s usually around 10:30—more than four hours after she left her house for the day.
She comes in with a plan for how many people she’ll vaccinate, but Agnes always brings a couple extra doses just in case. A typical day usually means around 50 patients. Most are children under 5, who get vaccinated against deadly diseases like polio, measles, tetanus, and pneumonia. The latter is especially important in a region as rainy as this one, where the damp weather makes people more susceptible to respiratory diseases.
Agnes and her colleagues are often the only health workers who visit the most remote communities in the mountains, so they also provide general nursing care while they’re there. Agnes regularly gives kids deworming treatments and key supplements like vitamin A. She answers questions from the adults and offers them health guidance, including advice on planning a family.
After she wraps up for the day, Agnes makes the long trek back home. It’s exhausting, difficult work, but she is proud to help so many people. “Our motto for nurses in Uganda is ‘To love and serve,’” she says. “And to me, love is not just a word. It’s a verb.”
Unfortunately, Agnes’s job recently became a lot more difficult. Many of her colleagues at the health clinic in Buluganya were supported by USAID, and they lost their jobs when funding was cut. Some of the positions that were eliminated supported new and expectant mothers. Others worked on HIV and tuberculosis, distributing medication and testing high-risk individuals to prevent further spread.
Agnes and the others who are left are doing their best to ensure communities still receive care, but they can only do so much. “Our community is suffering a lot,” she says. She is worried about burnout if funding isn’t restored.
Still, Agnes won’t rest until she has helped as many people as she can. Thanks to the support of the Rotary Club of Kampala, she recently went back to school and is working towards a degree in nursing. She hopes to learn new skills that will save even more lives.
“My dream is to make people feel good, to make them happy, and to give my service to the people,” says Agnes. “When you have positivity, nothing is impossible.”

Everyday miracles
A perilous time for the world’s poorest children
My latest speech about why we need to keep funding vaccines.
I’ve been giving speeches about vaccines for 25 years. After so much time, it could have become routine for me. But it never has.
One reason is that the impact of vaccines—a single dose can protect a child from deadly diseases forever—is like a miracle to me, and who gets tired of talking about miracles?
The other reason is tied to this particular moment. There’s never been a point in the past 25 years when more lives hung in the balance. In all likelihood, 2025 will be the first year since the turn of the century when the number of children dying will go up instead of down.
Why? Governments are cutting health aid—including funds for Gavi, the vaccine organization that the Gates Foundation helped start. As a result, Gavi will likely not have all the money it needs to fund its next five years of work.
So when I spoke this week at a summit in Brussels where donors committed a new round of funding for Gavi, I focused on why it’s so important to keep the money flowing and maintain our momentum on vaccines. You can read my remarks below.
Remarks as delivered
June 25, 2025
Global Summit: Health & Prosperity through Immunisation
Brussels, Belgium
Good evening, and thank you to everyone joining us here tonight—and for all your support for one of the most transformative efforts in the world.
I want to particularly thank President von der Leyen and President Costa, and the European Union, for co-hosting this summit. President von der Leyen has long been an incredible champion for health and development, and the EU has been one of the Gavi's biggest supporters since the very beginning—support that's more crucial now than ever.
This chart is one that I think about a lot. It's really my most favorite chart. And I consider it almost kind of a report card for humanity. Because over the last 25 years, the reduction of under-five deaths has been far faster than any time in history. We've gone from over 9 million to now half as many deaths taking place by children. This is an unbelievable result.
And it doesn't fully state the benefit of these vaccines. The vaccines leave a lot of kids far more healthy, and so their ability to achieve their potential is increased.
Gavi prioritizes saving lives, and it's done with incredible scientific rigor. We're constantly improving vaccines. We're constantly looking at the safety, and I'm very proud of the work that's done to make sure that these vaccines are incredibly safe.
The founding of Gavi actually goes back to about the time the Gates Foundation was first started. And after 25 years, I can still say that it's at the top of the list of things that I'm very, very proud of. At that time, kids were not getting access to vaccines. They were too expensive. They hadn't been formulated properly. And I was stunned to learn that so many kids were dying from a disease like rotavirus because the vaccine wasn't getting out to all the children of the world.
So Gavi was created to not only help finance vaccines, but work with countries to adopt these new vaccines.
We've done an amazing job of getting these prices down. A good example is the pneumococcal vaccine, PCV. This vaccine became available in high-income countries the year that Gavi was founded. And it does a fantastic job of protecting kids against pneumonia, which was the single most deadly childhood infection. But it was very expensive.
And so Gavi and its partners incentivized vaccine manufacturers to develop a new, much cheaper PCV, which was introduced in 2017. Today, the manufacturers make PCV vaccines available to low-and middle-income countries for just $2 a dose.
And of course, we've seen similar reductions across all of the different vaccines, allowing us to add new vaccines to save even more children.
Since the founding of Gavi, the overall cost of fully vaccinating a child has been cut in more than half.
And we have a pipeline of new vaccines coming along, vaccines to address new diseases and that bring down costs even further.
A good example of this is the HPV vaccine. Cervical cancer, which HPV prevents, is the fourth most common cancer in women around the world. And this vaccine can prevent over 90% of these cases.
But countries were slow to adopt this vaccine, in part because it was hard to deliver: initially, it required three doses spread across six months.
Scientists believed that perhaps it could be done with fewer doses. And so the Gates Foundation funded a trial to see whether a single dose was essentially fully protective. And after seeing the incredible results, the WHO approved a single dose schedule in 2022.
Now, we have 75 countries around the world that have moved to this single dose approach.
And because the single dose is cheaper and easier to deliver, it's now getting to far more girls around the world. For example, after Nigeria introduced the single-dose vaccine, it was able to vaccinate more than 12 million girls in less than a year. That's really incredible.
Across Gavi countries, HPV vaccine coverage has increased dramatically. The year after this single-dose approval, we doubled the number of girls getting the vaccine. And [the next year] we doubled it again, and this year we'll double it again.
There's more than just making vaccines available. We have to work with our partner countries on helping improve their health systems. So the Gavi Alliance has spent a lot of its resources and a lot of its technical support in helping improve those primary health care systems, which are so vital. We've helped countries understand where they're missing kids and how to invest in raising those coverage levels.
As you've heard, over this 25-year period, that means over a billion children have been vaccinated—resulting in the saving of over 19 million lives.
Nineteen million is a big number. It's almost easier to understand if I just say: okay, here's a child whose life was saved. But you have to take your reaction to how valuable that is and multiply it by this absolutely gigantic number.
The total cost to save those lives was about $22 billion. And that means that Gavi saved children's lives for only about $1,000 per life saved.
And in addition, the kids who these vaccines have kept healthy not only go to school; they do well in school. They join the economy. They contribute to their country. And really, this is why improving health through vaccines is part of the formula for helping countries be self-sufficient.
Gavi's vaccination has generated $250 billion in economic benefits in the countries it supports. In fact, Gavi has had such an extraordinary economic benefit that over 19 countries that were Gavi recipients have now graduated, meaning they now fully fund their own immunization programs.
A great example is Indonesia. Since partnering with Gavi, it’s doubled the number of vaccines offered through its routine immunization program—and it’s seen childhood deaths fall to a quarter of what they were before. And now, Indonesia is not only transitioning to be fully self-supportive—it’s also become a Gavi donor.
Of course, this is a challenging time. All the progress we’ve made is at risk. Budgets are tight, and we all have to show our priorities when there’s tough trade-offs to be made.
There’s no denying: this is a global health crisis. Between the U.S. cuts and other funding cuts, in total, aid in total has gone down by 30 billion this year alone. It reinforces the incredible values being shown by the people who are showing up here today and being incredibly generous.
But with the cut in health resources, along with the financial situation a lot of these low-income countries are in, we are going to have a few years where things will go backwards.
As we think about this, think of a mother who will bring a baby wheezing for breath to a help center, and because the vaccines aren't available, that baby will not survive.
Think of a health worker trying to deal with a measles outbreak who, because there's less resources for that primary health care system or vaccines, that measles epidemic will continue.
This is agonizing. I mean, we have to put ourselves in the position of the parents who lose these children and how tough it must be for them to realize that the life could have been saved by a vaccine that costs just 30 cents.
So though our trend lines will briefly go into reverse, I believe that we can come back. I believe that we will resume that incredible progress that you saw.
I don't know if it'll be in two years or four years or six years, but I do know that as we bring these resources back, and we take advantage of an incredible pipeline of innovation, new drugs, new vaccines—lots of amazing things to help with these diseases—we will resume progress.
So everyone here, I'd say, is recommitting themselves, just like the Gates Foundation, to doubling down and staying committed.
You know, I'm not pessimistic. In fact, we have things like polio eradication that we are, as we say, this close to elimination. That'll be a mind-blowing thing. Likewise, malaria: we have tools, a variety of tools that brought together will give us a chance in the next 20 years to completely eradicate that as a disease, just like we're doing with polio.
This is all why the Gates Foundation is pledging $1. 6 billion to Gavi for this next five-year period. Thank you.
And it's why we'll invest billions in making sure that pipeline of new and lower-cost vaccines continues to make Gavi even more effective.
In closing, I think we can reflect on what Nelson Mandela once said: “There can be no keener revelation of a society's soul than the way it treats its children.”
In the last 25 years, Gavi has helped over a billion children live better, healthier lives—thanks to the extraordinary support of partners like you.
If we get this right, this trajectory of progress will continue for decades to come.
Thank you.
Field notes
The world needs more Nick Kristofs
I loved this journalist’s story of chasing hard problems and holding onto hope.
If you’re a big reader, you can probably point to a book or two that changed the course of your life. For me, it was a 1997 New York Times column by Nicholas Kristof about diarrhea, which was killing three million kids a year.
At the time, I had wealth—and knew I planned to give it away—but no clear mission. Nick’s article gave me one. I faxed it to my dad with a note: “Maybe we can do something about this.”
That ended up setting the direction for what became the Gates Foundation. It didn’t just give us a what—it gave us a how. Nick’s reporting showed us that the biggest challenge in global health isn’t always discovering new breakthroughs. Often, it’s making sure the tools we already have—vaccines, medicines, bed nets, or oral rehydration therapies for rotavirus—reach every child, no matter where they’re born.
Reading Nick’s new memoir, Chasing Hope, brought me back to that moment and showed me how it fit into the bigger story of his life. The book is a deeply personal account of a life spent documenting injustice and refusing to look away, whether it’s genocide in Darfur, refugee camps in Sudan, or the streets of his hometown in rural Oregon.
Nick’s impulse to go where the suffering is, and to make people care, has defined his career. He’s reported from more than 150 countries, covering war, poverty, health, and human rights. He and his longtime collaborator and wife, Sheryl WuDunn, won a Pulitzer Prize for their work. Together and individually, they’ve brought injustices around the world into view for millions of readers.
But Chasing Hope isn’t just a greatest-hits collection of his past reporting. It’s the story of how someone becomes Nick Kristof. He writes about growing up on a sheep and cherry farm in Oregon, driving tractors as a teenager, and nearly becoming a lawyer before deciding on journalism. He also reflects on the toll his career has taken on him, his family, and his capacity for hope.
I’ve known Nick for many years now, and I’ve admired his work since that 1997 rotavirus column. On paper, we don’t seem all that similar. He’s a journalist, I’m a technologist; he tells stories, I talk numbers. But reading Chasing Hope, I was struck by what we have in common: growing up in the Pacific Northwest, learning about the value of service from our parents, thinking globally.
We both attended Harvard and left early—me because I dropped out, him because he graduated in three years before heading to Oxford as a Rhodes Scholar. But neither of us ever stopped learning. I think we both believe the world’s pretty interesting if you remain a student.
Nick’s curiosity didn’t come out of nowhere, and neither did his sense of purpose. His mother was an art history professor and a civic leader who helped influence local politics. His father, a political science professor who fled both Nazism and communism, believed deeply in education and the responsibilities that come with freedom. That kind of upbringing left a mark on him and shaped the kind of journalist he became.
Over decades, he’s built a career reporting on crises that are often ignored because they happen in far-off places, far from centers of power. In Chasing Hope, he recounts his experiences chronicling river blindness in Ethiopia, maternal mortality in Cameroon, and malaria in Cambodia. Through the foundation, I mobilize science, data, and funding to address many of the same global challenges Nick reports on. Our approaches are different, but the underlying questions we ask (and try to answer) are the same: Why are some lives valued less than others? And how can we use the tools we have—information, resources, attention—to close that gap?
Nick has an admirable commitment to nuance, especially when it comes to hard subjects like China. Nick lived there for years, speaks Mandarin, and understands the country in a way most Western commentators don’t. I’ve always appreciated his ability to go beyond the headlines—and focus not just on what’s going wrong, but on what’s changing and why it matters.
Nick is also an optimist, which might sound strange given the kinds of suffering he writes about. But his work is grounded in a belief I share: The right data—or the right story—can move people to act. As Nick puts it, “A central job of a journalist is to get people to care about some problem that may seem remote.” People, when given the chance, want to make things better. Progress, while never guaranteed, is possible.
That optimism feels especially important, if increasingly difficult, right now. Isolationism is on the rise around the world, and governments are cutting back on foreign aid at the very moment when we should be doing more, not less. Millions of lives are at stake. Nick’s work reminds us what’s possible when we care about people beyond our own borders—and what happens when we don’t.
Chasing Hope made me think a lot about what kind of person chooses to run toward the hardest problems—and keep going back until they’re solved. It also made me think the world would be a much better place if there were more Nick Kristofs. In the meantime, we’re lucky to have this one.
Back for the future
I’m heading back to India
This trip will give me the chance to see what’s working, what’s changing, and what’s next—for India and the Gates Foundation.
In a few days, I’ll be traveling to India—my third visit in three years. India is a place where big challenges meet even bigger ambitions, and where innovation is transforming lives at an incredible scale. Every time I’m there, I see firsthand how much progress is being made in public health, agriculture, and technology. And I come away with new ideas, because India is full of smart, ambitious people tackling some of the world’s hardest problems in creative ways.
This visit will also be significant because—as we mark our 25th anniversary—the Gates Foundation’s Board of Trustees is meeting in the Global South for the first time. India is the right place for this milestone. The foundation has been working in the country for more than two decades, partnering with the government, researchers, and entrepreneurs to improve health and development. Today, India is home to some of the most impactful programs we’ve contributed to, from disease eradication and sanitation to women’s empowerment and digital financial services. This trip will give me a chance to see what’s working, what’s changing, and what’s next—for India and the foundation.
India’s track record in public health shows what’s possible. When I visited in 2011, it was one of the last places in the world still fighting polio. But that year, after relentless effort, India recorded its last case—and it’s remained polio-free ever since. Avahan, the HIV prevention program launched by the Gates Foundation two decades ago, is another success story. It pioneered a community-led approach to reduce infection rates that complemented the government’s efforts in high-prevalence states; eventually, management of the program transitioned to the Indian government, becoming part of the country’s broader health strategy.
That same model—leveraging local leadership, innovative solutions and data-driven insights—is now driving India’s fight against tuberculosis. The country has the world’s highest TB burden, but its investment in new diagnostics, AI-powered detection tools, and improved treatment strategies is accelerating progress toward elimination.
India’s success in childhood immunization is another reason I’m eager to return and learn more. Over the past several years, the country has scaled up routine vaccination programs, ensuring every major childhood vaccine is available. It has also used digital dashboards to track vaccine coverage, monitor cold storage, and improve maternal and child healthcare. These efforts have helped drive down mortality rates and create a stronger health system that can respond to new challenges.
India’s global health leadership is also transforming how the country approaches diagnostics and treatment for infectious diseases. As a result, it’s become a leader in low-cost vaccine manufacturing, ensuring that life-saving vaccines are available around the world. Indian companies are also tackling another critical challenge: making diagnostics more affordable. One effort I’m following closely is the push to make a saliva-based TB test for under $2, which could help millions of people in India and globally detect the disease earlier and get treatment faster.
Beyond health, India is also at the forefront of digital transformation. I’ve written before about how digital public infrastructure (DPI)—like Aadhaar and India’s digital payments system—has made it easier for millions of people to access banking, healthcare, and government services. Now, India is using AI-powered DPI tools to help rural health workers improve early disease detection, optimize pregnancy care, and manage patient data more effectively.
AI is also transforming agriculture across the country. When I was in Odisha last year, I saw farmers using AI-powered tools to predict weather patterns, choose crops, and reduce disease risks. I’m looking forward to seeing how much better those tools have gotten in the short time since.
What makes India’s progress so transformative, though, is that it doesn’t just benefit India. During India’s G20 Presidency in 2023, Prime Minister Modi declared his intent to make Indian innovations and know-how available to solve development problems globally. And that’s exactly what is happening. The solutions being developed there, from vaccine manufacturing to AI-powered diagnostics, are being shared with the world. Indian companies are making TB tests that could be game-changing across Africa. They’re developing AI models that could help farmers across Asia. And they’re proving that digital technology can make healthcare work better for everyone, especially the most vulnerable.
At the Gates Foundation, we tackle tough problems by working in close partnership with the people and governments most affected by them. India has been an incredible partner in this work because of the country’s deep expertise and willingness to develop and scale new ideas. The challenges remain: eliminating TB, improving nutrition, expanding access to AI-driven health and development services. But India has shown time and again that progress happens when innovation, local leadership, and investment come together.
That’s why I’m so excited for this trip. I’ll be meeting with government leaders, scientists, and philanthropists who are shaping the future of health and development in India. I’ll be visiting innovators who are working on solutions that could help people in India and around the world. And I’ll get to see how the foundation’s work fits into this bigger story—and how we can continue to support Indian-led efforts to improve lives.
I always leave India inspired. I know this trip will be no different.
The sky’s the limit
The Drone Didis are taking flight
Drones are helping rural women boost their income and India’s agricultural productivity.
I was excited to get a drone for my birthday last year. I couldn’t wait to get it into the air and see what my backyard looked like from the sky. But, as anyone who has used one can tell you, I quickly learned a harsh truth: Flying a drone isn’t easy. It takes a lot of practice and skill.
Maybe it’s time to pull the drone back out, because I was lucky to get a lesson from the experts last month in India. During my visit to Delhi, I met with Sangita Devi, Sumintra Devi, and Kajol Kumari—three Drone Didis from Bihar who are taking India’s agricultural productivity to new heights.
The women I met are part of the Indian government’s Namo Drone Didi program. (Didi is the Hindi word for “sister.”) It was launched in 2023 to help rural women boost their income and boost India’s agricultural productivity—and although the program is still in its early days, I’m already impressed by its results.
Right now, the Drone Didis primarily use their flying skills to fertilize crops. Applying fertilizer via drone has a lot of benefits over doing it by hand. Since you can spray farther away from the plant, the liquid fertilizer becomes more atomized—which means that it turns into finer droplets that cover more area. This benefits both farmers and the environment, because you need significantly less fertilizer and less water to help distribute it. Plus, it’s faster. One Drone Didi can cover as much as five acres in the same time it would take five people to cover half an acre.
I cannot wait to see how the program expands in the years ahead. The Indian government has plans to equip the drones with advanced sensors and imaging technology. This will allow Drone Didis to use real-time data to deliver targeted interventions to improve the quality and quantity of farmers’ crops. They will be able to detect diseases and pests, assess soil moisture levels, monitor crop growth, and more.
I’m equally excited to track how the Drone Didi program continues to empower women across India. Every Didi is affiliated with a self-help group, or SHG. The plan is to provide nearly 15,000 drones to SHGs across India by the end of next year.
In the United States, where I live, self-help groups are usually associated with mental health. In India, they’re a form of mutual aid. Each SHG is small—most are around 12 people, although some are as big as 25—and brings together women to support each other socially and financially. They pool their savings, access microloans at lower interest rates, and solve problems in areas like health and education.
The Didis I met with were longtime members of SHGs organized by JEEViKA, an organization in Bihar that works to lift people from rural areas out of poverty. During our time together in Delhi, Kajol told me about how JEEViKA helped her open her own shop three years ago, where she sells seeds and fertilizers. She loves being an entrepreneur, and when she was approached about becoming a Drone Didi, she knew it would do wonders for her business.
Each Didi attends a training program in Hyderabad or Noida, where they are taught how to pilot the drone and apply fertilizer effectively. (I was surprised to hear that learning to fly is apparently easier and takes less time than learning to fertilize!) Other women in their SHGs are trained as drone technicians, ready to repair the machines if any problems arise.
In the less than two years, the Drone Didi program is already transforming the lives of its pilots. Kajol is using the extra income she’s earned to expand her shop offerings and build a warehouse to store her stock. She also plans to send her children to a better school. Sangita’s family couldn’t afford a bicycle before she became a Drone Didi—today, she is the proud owner of an auto rickshaw.
Sumintra hopes that, when people see someone like her flying a huge drone, it changes their perception of what women are capable of. Like many women in her area, she married very young and was expected to stay home with her children. Today, her kids call her “Pilot Mummy” and dream about her flying airplanes one day.
I hope you think of the Didis the next time you hear the buzz of a drone above you at a wedding or a park. It’s remarkable how one piece of technology can reshape what is possible in a community. Kajol told me that people sometimes look at her and say, “She’s flying too high! What will she do next?”
Her response? “This is just the beginning. Wait and see what’s coming.”

Ancient gains
Could a grain older than the wheel be the future of food?
Lost crops like fonio could help us fight climate change and malnutrition.
What grain did your family grow up eating? I’m from the United States, where wheat and corn are king. But if I had been born in East Asia, I probably would’ve eaten a lot more rice as a kid.
If you grew up in West Africa, you might have eaten an ancient grain called fonio. Fonio has been feeding families in West Africa for more than 5,000 years, longer than any other cultivated grain on the continent. That makes it older than toilets, the wheel, and even writing. It’s a super small grain with a texture that reminds me a bit of couscous when cooked in hot water. Its nutty taste is delicious on its own but is also good when ground into flour.
Fonio is just one part of a much bigger family of remarkable ancient grains: the millets. Perhaps you’ve heard of finger millet. It’s a staple in Uganda and parts of Kenya and Tanzania, and it’s beloved in India where it is called ragi. Or maybe you’ve heard of teff, a longtime favorite in Ethiopia where it’s used to make injera.
Millets have been around for centuries, but they’re currently experiencing a resurgence—both for consumers who enjoy their taste and for farmers who appreciate how reliable they are to grow.
Fonio, in particular, is like farming on easy mode. You wait until a good rain comes, lightly till the soil to loosen it up, and then scatter the seeds on the ground. Two months later, you harvest the grain.

Farm work
On Africa’s farms, the forecast calls for adaptation and innovation
In Kenya, I visited with a smallholder farmer using new tools and practices to fight back against climate change.
I planted drought-tolerant seeds, fed and weighed chickens, and used a mobile phone to monitor weather forecasts and local crop prices.
These were a few of the chores I was given during my visit with Mary Mathuli, a smallholder farmer in rural Kenya.
I stopped at her home in Makueni County, south-east of Nairobi, during my recent trip to Kenya to better understand how farmers like Mary are faring in the face of climate change.
I arrived expecting to hear her talk about the record droughts and smaller harvests many farmers are experiencing throughout Africa.
Instead, to my surprise, she led me out to her fields to show off the innovations that are allowing her to continue to grow crops and earn an income to support her family, despite the drastic changes in rainfall and weather patterns.
A natural teacher, Mary encouraged me to learn by doing. She put me to work so I could understand how these new agricultural inputs and practices can make a big difference in their lives.
This experience taught me a couple important lessons.
First, my farming skills—like holding a chicken and swinging a hoe—need some work.
Second, and more importantly, I got a personal reminder of how resourceful and resilient African smallholder farmers like Mary are. Battered by years of drought and other extreme weather patterns, they are developing new skills and embracing new technologies to adapt to some of the toughest conditions for growing crops and raising livestock.
To be clear, African farmers face huge challenges due to climate change. Although sub-Saharan Africa accounts for only about four percent of the world’s carbon emissions, the continent is bearing the brunt of climate change impacts. Climate-related losses on many African farms are more than double those seen globally. In Makueni County, where Mary farms, yields of maize have been falling since 1994, largely due to changes in the weather.
While more innovation is needed to help Africa’s smallholder farmers keep pace with the threats posed by climate change, Mary and other farmers in Kenya are adopting some incredible new tools and practices that can limit crop losses and help their farms thrive even in extreme weather:
As farms go, Mary’s farm is quite small. Just about 4 acres, which is typical for farms in Africa. Still, she packs a lot of activities in this space, growing commercial and subsistence food crops and rearing poultry and livestock. In sub-Saharan Africa, more than half of the population works in agriculture. Together, they produce about 80 percent of the continent’s food supply. And most of the people doing the backbreaking farm work—like the chores I performed—are women.
I was impressed by Mary’s entrepreneurial spirit and her optimism. She appeared to seize every opportunity to try out new technologies and agricultural practices. It’s one of the reasons why she was trained as a model farmer and Village Based Advisor by the Cereal Growers Association, an organization that works with smallholder farmers to help improve their productivity. In this role, Mary provides guidance to several hundred farmers in her community, showing them how to use drought-tolerant seeds, raise chickens, and adopt other climate adaptation agricultural strategies.
She is clearly doing a good job in this role because more than 90 percent of farmers in her area have embraced one of the new adaptation practices.
I look forward to hearing how the seeds I planted with Mary are doing, despite the disappointing rains in recent months. I can’t imagine them in better hands than hers.
Thanks so much for the visit, Mary!
Food for thought
What it will really take to feed the world
In his latest book, one of my favorite authors argues that solving hunger requires more than producing more food.
In the introduction to his latest book, How to Feed the World, Vaclav Smil writes that “numbers are the antidote to wishful thinking.” That one line captures why I’ve been such a devoted reader of this curmudgeonly Canada-based Czech academic for so many years. Across his decades of research and writing, Vaclav has tackled some of the biggest questions in energy, agriculture, and public health—not by making grand predictions, but by breaking down complex problems into measurable data.
Now, in How to Feed the World, Vaclav applies that same approach to one of the most pressing issues of our time: ensuring that everyone has enough nutritious food to eat. Many discussions about feeding the world focus on increasing agricultural productivity through improved seeds, healthier soils, better farming practices, and more productive livestock (all priorities for the Gates Foundation). Vaclav, however, insists we already produce more than enough food to feed the world. The real challenge, he says, is what happens after the food is grown.
This kind of argument is classic Vaclav—questioning assumptions, forcing us to rethink the way we frame problems, and turning conventional wisdom on its head. His analysis is never about the best- or worst-case scenarios; it’s about what the numbers actually tell us.
And the numbers tell a striking story: Some of the world’s biggest food producers have the highest rates of undernourishment. Globally, we produce around 3,000 calories per person per day—more than enough to feed everyone—but a staggering one-third of all food is wasted. (In some rich countries, that figure climbs to 45 percent.) Distribution systems fail, economic policies backfire, and food doesn’t always go where it’s needed.
I’ve seen this firsthand through the Gates Foundation’s work in sub-Saharan Africa, where food insecurity is driven by low agricultural productivity and weak infrastructure. Yields in the region remain far lower than in Asia or Latin America, in part because farmers rely on rain-fed agriculture rather than irrigation and have limited access to fertilizers, quality seeds, and digital farming tools. But even when food is grown, getting it to market is another challenge. Poor roads drive up transport costs, inadequate storage leads to food going bad, and weak trade networks make nutritious food unaffordable for many families.
And access is only part of the problem. Even when people get enough calories, they’re often missing the right nutrients. Malnutrition remains one of the most critical challenges the foundation works on—and it’s more complex than eating enough food. While severe hunger has declined globally, micronutrient deficiencies remain stubbornly common, even in wealthy countries. One of the most effective solutions has been around for nearly a century: food fortification. In the U.S., flour has been fortified with iron and vitamin B since the 1940s. This simple step has helped prevent conditions like anemia and neural tube defects and improve public health at scale—close to vaccines in terms of lives improved per dollar spent.
One of the most interesting parts of the book is Vaclav’s exploration of how human diets evolved. Across civilizations, people independently discovered that pairing grains with legumes created complete protein profiles—whether it was rice and soybeans in Asia, wheat and lentils in India, or corn and beans in the Americas. These solutions emerged from practical experience long before modern science could explain why they worked so well.
But just as past generations adapted their diets to available resources, we’re now facing new challenges that require us to adapt in different ways. Technology and innovation can help. They’ve already transformed the way we produce food, and they’ll continue to play a role. Take aquaculture: Once a tiny industry, it’s grown over the past 40 years to supply more seafood for the world than traditional fishing—a scalable way to meet global protein demands. The Green Revolution is another example. Beginning in the 1960s, innovations in higher-yielding crops, more effective fertilizers, and modern irrigation prevented widespread famine in India and Mexico. These changes were once seen as unlikely, too.
New breakthroughs could drive even more progress. CRISPR gene editing, for instance, could help develop crops that are more resilient to drought, disease, and pests—critical for farmers facing the pressures of climate change. Vaclav warns that we can’t count on technological miracles alone, and I agree. But I also believe that breakthroughs like CRISPR could be game-changing, just as the Green Revolution once was. The key is balancing long-term innovation with practical solutions we can implement immediately.
And some of these solutions aren’t about producing more food at all—they’re about wasting less of what we already have. Better storage and packaging, smarter supply chains, and flexible pricing models could significantly reduce spoilage and excess inventory. In a conversation we had about the book, Vaclav pointed out that Costco (which might seem like the pinnacle of U.S. consumption) stocks fewer than 4,000 items, compared to 40,000-plus in a typical North American supermarket.
That kind of efficiency—focusing on fewer, high-turnover products—reduces waste, lowers costs, and ultimately eases pressure on global food supply, helping make food more affordable where it is needed most.
How to Feed the World had a lot to teach me—and I’m sure it will teach you a lot, too. Like all of Vaclav’s best books, it challenges readers to think differently about a problem we thought we understood. Growing more and better food remains crucial—especially in places like sub-Saharan Africa, where there simply isn’t enough. But as the world’s population approaches 10 billion, increasing agricultural productivity alone won’t solve hunger and malnutrition. We also need to ensure that food is more accessible and affordable, less wasted, and just as nutritious as it is abundant.
After all, the goal isn’t to make more food for its own sake—it’s to feed more people.

Alphabet soup
You’ve probably never heard of CGIAR, but they are essential to feeding our future
No other institution has done as much to feed our world as CGIAR.
What’s for dinner?
It’s a question asked every day in homes around the world. No other organization has done as much to ensure families—especially the poorest—have an answer to that question as CGIAR, the world’s largest global agricultural research organization.
More than 50 years ago, CGIAR’s research into high-yielding, disease-resistant rice and wheat launched the Green Revolution, saving more than a billion people from starvation. In the years since then, their work on everything from livestock and potatoes to rice and maize has helped reduce poverty, increase food security, and improve nutrition.
Never heard of CGIAR? You’re not alone. It’s an organization that defies easy brand recognition. For starters, its name is often mistaken for “cigar,” suggesting a link to the tobacco industry. And it doesn’t help that CGIAR is not a single organization, but a network of 15 independent research centers, most referred to by their own confusing acronyms. The list includes CIFOR, ICARDA, CIAT, ICRISAT, IFPRI, IITA, ILRI, CIMMYT, CIP, IRRI, IWMI, and ICRAF, leaving the uninitiated feeling as if they’ve fallen into a bowl of alphabet soup.
It’s too bad that more people don’t know about CGIAR. Their work to feed our hungry planet is as important now as it’s ever been. By 2050, as the world’s population gets bigger and incomes increase (which causes dietary changes like eating more meat), global food demand is expected to increase by 60 percent. Meeting this challenge is made tougher by climate change, which is affecting food production in every corner of the globe. Farmers are under assault from shifting rainfall, more frequent and extreme droughts and floods, and severe pest and disease outbreaks among crops and livestock.
The people who are most affected by these changes today are the world’s smallholder farmers. About 500 million farming households, in South Asia and sub-Saharan Africa, earn their living by raising crops and livestock on small parcels of land. These families have the fewest resources to cope with the many impacts of a warming climate.
I’ve been writing a lot this year about why reducing emissions from all sectors of our economy, including agriculture and electricity generation, is critical in our fight against climate change. But it’s equally important for the world to stay focused on helping vulnerable populations, like smallholder farmers, prepare for the disruptive impacts of climate change. We owe it to them. The people who will suffer most from climate change, especially in sub-Saharan Africa, are the least responsible for emitting these greenhouse gases. According to an Africa Progress Panel report, an average Ethiopian would have to live for 240 years to equal the carbon footprint of the average American.
I’m now co-chairing the new Global Commission on Adaptation, which is playing a key role in building government and public support for efforts to reduce the impacts of climate change on communities most at risk. We will need CGIAR’s research to help supply farmers with a steady stream of climate-smart crop varieties.
A great example of a CGIAR innovation helping smallholder farmers adapt to climate change is its drought-tolerant maize program. More than 200 million households in sub-Saharan Africa depend on maize for their livelihoods. Maize productivity in Africa is already the lowest in the world. And as weather patterns have become more erratic, farmers are at greater risk of having smaller maize harvests, and sometimes no harvest at all.
In response to this challenge, CGIAR’s International Maize and Wheat Improvement Center or CIMMYT, with funding from our foundation, USAID and the Howard Buffett Foundation, developed more than 150 new maize varieties that could withstand drought conditions. Each variety is adapted to grow in specific regions of Africa. At first, many smallholder farmers were afraid of trying new crop varieties instead of more commonly planted ones. But as CIMMYT worked with local farmers and seed dealers to share the benefits of these new varieties, more and more farmers adopted drought tolerant maize. The results have been life changing for many farming families.
In Zimbabwe, for example, farmers in drought-stricken areas using drought-tolerant maize were able to harvest up to 600 kilograms more maize per hectare than farmers using conventional varieties. The additional harvest was enough to feed a family of six for 9 months. For farming families who chose to sell their harvests, it was worth $240 in extra income, giving them much-needed cash to send their children to school and meet other household needs.
CIMMYT, in partnership with another CGIAR center, the International Institute of Tropical Agriculture or IITA, has gone on to develop other maize varieties for farmers who are not only vulnerable to drought, but also poor soils, disease, pests, and weeds. These varieties are expected to give farmers up to 30 percent greater yields and help them fight malnutrition.
CGIAR’s team of more than 8,000 scientists and staff around the world are also developing other tools to help farmers adapt to unpredictable weather and diseases. They have created a smart phone app that allows farmers to use the camera on their phone to identify specific pests and disease attacking cassava, an important cash crop in Africa. There are also new programs to use drones and ground sensors to help wheat and sugarcane farmers determine how much water and fertilizer their crops need.
We will need many new ideas like these to help farmers be prepared to meet the challenges of our changing climate. If they are, we will all have an answer to the question “What’s for dinner?” for years to come.

Farm aid
A warmer world will hurt this group more than any other
We need to help the world’s poorest people adapt to climate change.
I’ve spent a lot of time over the last month talking about climate change. Whether it’s on my book tour, in media interviews, or just during conversations with colleagues, it’s been great to have so many thoughtful conversations with people about how we prevent the worst effects of climate change.
Most of the questions I’ve gotten are about how we get to zero greenhouse gas emissions. Mitigation is the biggest climate problem we need to solve, and it’s been great to see it get so much attention. But I’ve noticed there’s one key topic that people don’t ask about as much: how we can help the world adapt to climate change.
I understand why. I dedicated five chapters of the book to mitigation and only one to adaptation. (In retrospect, I wish I had written more about the subject.) But there’s a reason I named my book “How to Avoid a Climate Disaster” and not “How to Stop Climate Change:” Our climate is already changing.
You just need to look at last month’s freeze in Texas and last year’s wildfires in California to see that extreme weather events are becoming more common. The scary thing is that these events aren’t the only (or even the most devastating) way a warming world is making life more difficult for people. The biggest damage is happening too gradually to make headline news, mostly in places near the Equator—and no one is more at risk than the world’s poorest people.
About two-thirds of those living in poverty work in agriculture, often relying on the food they grow to feed their families. A warmer world will be problematic for relatively well-off farmers in America and Europe, but potentially deadly for low-income farmers in Africa and Asia.
The closer you live to the Equator, the worse the effects of climate change will be. Droughts and floods will become more frequent, wiping out harvests more often. Livestock will eat less and produce less meat and milk. The air and soil start to lose moisture, leaving less water available for plants; in South Asia and sub-Saharan Africa, tens of millions of acres of farmland will become substantially drier.
When you’re already living on the edge, any one of these changes could be disastrous. We’re likely going to see a situation for these farmers where, instead of your crop getting wiped out every ten years, it gets wiped out every four years. If you don’t have money saved up to buy imported food—which is the case for most smallholder farmers—your children will likely become malnourished and more susceptible to disease.
The worst impact of climate change in poor countries will be to make health worse—which is yet another reason why we need to help the poorest improve their health. This starts with raising the odds that malnourished children will survive by improving primary healthcare systems, doubling down on malaria prevention, and continuing to provide vaccines for conditions like diarrhea and pneumonia. We also need to ensure that fewer children are malnourished in the first place by helping poor farmers grow more food.
This is a problem we can help solve with innovation. We need better methods and tools to grow food, just like we need to find zero-carbon ways to move around and generate electricity. No other organization is in a better position to create the innovations that will help poor farmers adapt to climate change in the years ahead than CGIAR, a global partnership that helps make plants and animals more resilient and productive. (I’ve written about how amazing CGIAR is before.)
Our foundation first got involved with CGIAR more than a decade ago, when we supported their work to develop drought- and flood-tolerant varieties of staple crops like maize. We’re already seeing big improvements in places like Zimbabwe. Farmers in drought-stricken areas there who used drought-tolerant maize were able to harvest up to 500 more pounds per acre than farmers who used conventional varieties—producing enough to feed a family of six for nine months.
CGIAR and other organizations are also creating tools to help farmers adapt to unpredictable weather, like sensors that tell you when to plant seeds and phone apps that help identify pests. Poor farmers need more advances like these, but to provide them, we need to invest more money in agricultural R&D. Doubling CGIAR’s funding so it can reach more farmers is one of the main recommendations by the Global Commission on Adaptation, which I led along with former UN secretary-general Ban Ki-moon and former World Bank CEO Kristalina Georgieva. (Other recommendations include shoring up water infrastructure and building a stronger safety net to help farmers recover faster.)
If we don’t take steps now to help farmers adapt, we’re setting ourselves up for a humanitarian and geopolitical disaster. The U.S. military predicts that climate change will become a huge driver of global instability. When people can’t grow enough food to feed themselves, they often leave those areas for places that can better support their families. We’re going to see more “climate refugees” move to cooler regions as the world gets warmer. The Department of Defense is already thinking about where a warmer climate could cause conflicts that they would be asked to intervene in.
It’s deeply unfair that the people who contribute the least to climate change will suffer the worst from its effects. Extreme poverty has plummeted in the past quarter century, from 36 percent of the world’s population in 1990 to 10 percent in 2015 (although COVID-19 is a huge setback that is undoing a great deal of progress). Climate change could erase even more of these gains, increasing the number of people living in extreme poverty by 13 percent.
Rich and middle-income countries are causing the vast majority of climate change, and we need to be the ones to step up and invest more in adaptation. The world’s poorest deserve our help, and they need more of it than they’re getting.

Net gains
Planes, trains, and smartphones
The future of public infrastructure is digital, efficient, and for everyone.
Almost thirty years ago, I wrote a book called The Road Ahead, about the transformative potential of the internet and other new digital technologies. Back then, I envisioned a world where online payments and e-government would change how we interact with money, services, and each other. Today, much of that has become a reality, in part due to the development of digital public infrastructure. In my recent travels around the world, I’ve seen up close how DPI is revolutionizing the way entire nations serve their people, respond to crises, and grow their economies. And at the Gates Foundation, we see it as an important part of our efforts to help save lives and fight poverty in poor countries.
There are a few core components that constitute DPI: digital ID systems that securely prove who you are, payment systems that move money instantly and cheaply, and data exchange platforms that allow different services to work together seamlessly. These systems and platforms are to the digital world what roads, bridges, and power lines are to the physical one—an underlying structure that connects people, data, and money online. Strong DPI can propel a country forward by making it easier for people to access essential services, participate in the formal economy, and improve their lives. On the flip side, DPI that is poorly implemented (or simply non-existent) can slow a country’s development and perpetuate inefficiencies and inequities.
In the 21st century, digital public infrastructure is proving to be as important for progress as its brick-and-mortar predecessors—and the effects have been impressive around the world, wherever it’s been embraced.

Accounting for accounts
Digital tech is turning the unbanked into the banked
More people have accounts than ever. Here’s what we need to do next.
In the worst days of COVID-19, when people around the world were out of work and struggling to pay for food and housing, many national governments came to the same conclusion about the best way to offer immediate help: send people cash. More than 200 countries introduced emergency cash transfer programs or expanded existing ones; India, for example, transferred money to 300 million people, 200 million of whom were women, in the weeks after its first lockdown. Brazil reached 70 million people with emergency transfers.
Imagine the risk involved in making these payments with paper money during a pandemic. Government workers would have to physically deliver these payments, potentially exposing them and everyone they encountered to the virus. In addition, the whole process would be expensive and time-consuming at a time when people need help as quickly as possible.
Fortunately, most governments didn’t have to resort to in-person payment. They were able to deposit cash transfers directly into people’s accounts—allowing them to give crucial support without paper bills changing hands. And during the pandemic, even more users were brought into the digital fold. For example, after financial regulators in West Africa temporarily allowed people to open accounts by text or telephone, more than 8 million signed up for accounts while their countries were in lockdown.
Globally, transferring so much money without cash was possible thanks to more than a decade of painstaking work by governments, financial service providers, nonprofits, and other partners. Today, about three quarters of people worldwide have an account at a financial institution or through a mobile money provider. That’s a 50 percent increase in the past ten years, and the growth has not just been in higher-income countries. Developing countries have increased 71 percent in that time.
This growth is great news because it means that more low-income people—and especially low-income women—are being empowered to use products that let them make and receive payments, save and borrow money, and get insurance. Both research and experience show that this financial inclusion helps people exit and stay out of poverty. And using digital technology to do it is a low-cost way to build economic resilience and reduce extreme poverty, which is why it’s an essential part of the Gates Foundation’s strategy. We have granted several hundred million dollars to partners who are helping low- and middle-income countries build digital financial systems.
Whenever I talk to friends about this work, they’re surprised to learn that roughly 1.4 billion adults can’t or don’t use any type of formal financial account, and most of those unbanked people live in low- and middle-income countries. One reason is that analog banking requires buildings, piles of paperwork, security guards, and tellers, making the cost per transaction so high that it’s not economical for a company to serve people with low balances and small transactions. As a result, people create ingenious informal banking methods—doing things like pooling cash with family and neighbors or creating community savings groups. As creative as these solutions are, they don’t allow people to build assets or move money instantly. And they are often risky—cash stashed under a mattress can be stolen, for example.
Today, the proliferation of mobile phones means that you no longer need so much expensive infrastructure to provide modern financial services. With digital technology, costs are low enough that it makes economic sense for companies to serve more of the people whom the old system has ignored.
An early example was M-PESA in Kenya, which let people living in cities send money to their relatives in rural areas efficiently and inexpensively. As it caught on, it was eventually used to make payments in shops. Likewise, India’s Universal Payment Interface allows users to make instant digital payments to each other at extremely low cost; it now includes 323 financial service providers throughout the country and handles nearly 6 billion transactions each month. During the pandemic, more than 80 million adults in India made their first digital payment to a merchant.
Yet even the exemplar countries aren’t reaching everyone who needs digital banking. That’s why the World Bank (with support from the foundation) runs the Global Findex database, a comprehensive survey of how adults borrow, save, and send money and manage risks. The Findex has been updated periodically since 2011, and the latest version was just published earlier today. Using data gathered from 128,000 adults in 123 economies, it highlights steps that will expand formal banking to everyone in the world who wants it.
I eagerly read an early copy of the Findex report as soon as I had the chance, and I’m glad I did. I recommend the report to anyone, especially policymakers, who wants more people to benefit from financial inclusion. When the world knows more about where inclusion is growing and where it isn’t, we’re better equipped to make sure we’re reaching the people who are still left out.
One Findex finding that jumped out to me is the gender gap. Although the world has made progress in empowering women to use formal financial services as much as men do, there’s still work to do. In developing countries, the gap was 9 percent in 2017 and 6 percent in 2021. The world can do better. Leaders should focus even more directly on expanding account ownership and use among women.
Another section of the report looks at a crucial question: What prevents the people who are still unbanked from joining the formal system? Knowing the answer will make it easier to create services that will work for them.
To find out, the researchers behind the Findex did extensive surveys of the unbanked. Their top explanations: The accounts are still too expensive, a family member already has one, banks are too far away, or they don’t have enough money to use an account. So making the accounts even more affordable, accessible, and appealing needs to be a priority. Introducing digital payments via mobile phones is a great way to start: Between 2014 and 2021, the percentage of people in Ghana using formal banking services went up 28 points, and virtually all of the increase was driven by people signing up for mobile-enabled digital payments.
I’ve heard people argue that there’s a simple way to automatically expand financial inclusion: introduce digital currencies, and specifically cryptocurrencies. But that idea isn’t rooted in an understanding of what poor people require—the kind of understanding that the Findex provides.
In many areas where the unbanked live, many transactions are still done in cash, so even people with digital accounts need the ability to convert digital money into paper money quickly, and vice versa. But today, that’s extremely difficult to do with cryptocurrencies, particularly in rural areas. In addition, cryptocurrencies don’t solve the problem of identification; buyers and sellers would still need to be able to prove they are who they say they are.
When it comes to financial inclusion, the most important thing is to consider what poor people require. That means creating secure financial systems that identify who is making transactions, and that are interoperable, so that a person using one system can make transactions with someone on another system. It also means updating regulations so they protect consumers while encouraging innovation.
I’m excited about the great progress that’s documented in this year’s Findex. More people around the world, including more women and low-income people, have and use bank accounts than ever before. A lot of people are still excluded, but we have a roadmap that is feasible without billions of dollars of extra money to build systems that empower them. By following the roadmap, we can help them lift themselves out of poverty and make the world a fairer place.

Two countries, five days
Highlights of my trip to Nigeria and Ethiopia
A few photos from my latest visit to Africa.
I’ve just wrapped up a busy five-day trip to Ethiopia and Nigeria. It’s the kind of trip that’s both tiring and energizing at the same time. Even though I stay in touch with a lot of partners in both countries—the Gates Foundation has been funding work in them for more than 15 years—there’s nothing quite like visiting to see the work in action.
Whenever I get home from a trip like this, friends are curious to hear how it went. Here’s what I’m telling them. From 2000 to 2019 or so, Ethiopia and Nigeria led the way on dramatic improvements in health and poverty that rippled across Sub-Saharan Africa. Since then, the pandemic, extreme weather, and political and economic instability have set both countries back, along with much of the rest of the continent. But as I saw on this trip, there’s great work going on in both places that makes me optimistic about their future, and Africa’s.
I want to share a few photos from the week. Thanks to everyone who shared their time and insights with me, including Prime Minister Ahmed of Ethiopia, Nigerian health minister Muhammad Ali Pate, and a special guest who came along for the trip: the amazing musician Jon Batiste. The foundation will be working with African partners even more in the future, and based on what I saw this week, my next visit will be just as inspiring.

Production diary
Behind the scenes of my new Netflix series
I had a lot of fun filming What’s Next?, which you can watch now.
I've always thought of myself as a student trying to get to the bottom of things. A good day for me is one where I go to sleep with just a little bit more knowledge than I had when I woke up in the morning. So, when I am deciding how to spend my time these days, I usually ask myself three questions: Will I have fun? Will I make a difference? And will I learn something?
My new Netflix Series, What’s Next? The Future with Bill Gates, is out today. And when I think back on the process of working on it over the last two years, the answer to all three questions is a resounding “yes.”
I had an amazing time working with the super talented director, Morgan Neville. Morgan directed one my favorite documentaries, Best of Enemies, which is about Gore Vidal’s and William Buckley’s debates during the 1968 U.S. presidential election. Morgan also won an Oscar for his terrific film 20 Feet from Stardom.
As you might guess from the title, What’s Next? is a show about the future. I’m very fortunate to get to work on a number of interesting problems. Between fighting to reduce inequities through the Gates Foundation, leading Breakthrough Energy’s work on the climate crisis, and my continued engagement with Microsoft, I have a front seat to some of the biggest challenges facing us today.
I feel extremely grateful to have had the opportunity to work with and learn from some truly incredible people during the making of this show. (I’m hesitant to even use the word “work” because the process was so much fun!) My hope is that people watch What’s Next? and feel like they’re joining me on my learning journey.
Each episode focuses on a different challenge: artificial intelligence, climate change, misinformation, disease eradication, and income inequality. I sat down with some of the big thinkers and innovators who are pushing for progress. Some of them have different ideas than I do about how to tackle these challenges, and I loved getting to hear their perspectives. It was an eye-opening experience.
I got to have conversations on camera with familiar faces like Dr. Anthony Fauci, Open A.I. co-founder Greg Brockman, and the groundbreaking director James Cameron. And I made a lot of new friends as well—including an ingenious malaria researcher from Burkina Faso named Abdoulaye Diabaté, young climate activists who impressed me with their intelligence and passion, and an amazing group of people from across the Bay Area who overcame tremendous adversity in their path from poverty to stability.
There also were dozens of people who participated in the series with standalone interviews, like my friend Bono and the brilliant Mark Cuban—each of whom brings an inspiring and grounded view of the challenges we’re facing. My hope is that, together, we can combat the doomsday narratives that so often surround these issues.
It’s hard to pick which discussion I learned the most from. But three conversations will always stand out in my memory: the ones with Lady Gaga, Senator Bernie Sanders, and my younger daughter, Phoebe.
Going Gaga
I couldn’t help but feel a little nervous.
I was in Palm Desert, CA, preparing to have a filmed conversation with Lady Gaga for our episode about misinformation. Being around famous people doesn’t normally affect me. But I’m a big fan of A Star is Born—especially its music—and I was aware of her reputation as an outsized personality. I couldn’t wait to hear what she had to say.
Luckily, I had nothing to worry about. I was blown away by how thoughtful Gaga was. She made me laugh with the outrageous stories of how she’s been the subject of misinformation in the past—and inspired me with some of the ways she thinks about the topic.
In the early years of her career, one of the most persistent internet rumors about Gaga was that she was actually a man. It became so mainstream that reporters would ask about it during interviews. She refused to confirm or deny it. Instead, Gaga turned it back on the interviewer and asked, “Would it matter if I was?”
On the day of our Netflix conversation, I had been filming earlier with my two sisters, Kristi and Libby. So I asked them to come and watch the conversation between Lady Gaga and me.

Start spreading the news
Amazing stories I wish everyone knew
Meet some of the heroes who are fighting poverty and saving lives.
Have you ever heard a story that was so cool you couldn’t help telling everyone you met about it? Something you knew and wished that everyone else did too?
That’s how I feel about the people whose work I get to learn about through the Gates Foundation. Every day, around the world, they save lives and help people lift themselves out of poverty. Some are scientists. Others are educators, nurses, midwives, or advocates. Their work is so inspiring to me that I’ve committed virtually all of my wealth to supporting it.
When I see how much passion people like Josephine have for helping themselves and their neighbors, I’m inspired to help too. I hope these stories will be as inspiring for you as they are for me.

More than a job
For Eva Nangalo, saving mothers and babies is a calling
She’s a midwife, teacher, and advocate—and she’s changing childbirth in Uganda.
Officially, Uganda’s maternal mortality rate is double the global average. But because that number doesn’t count those who give birth at home—in a country where poverty, distance, stigma, and distrust are all barriers to medical care—Eva Nangalo believes the real one may be much higher.
That’s why, as a midwife determined to eliminate these deaths altogether, she’s spent the past 23 years working to make hospital deliveries both more safe and more common.
For Nangalo, this is more than a job. It’s her life’s work, and something she’s felt called to do for as long as she can remember. “I was created to be a midwife, born to be a midwife, trained to be a midwife,” she said. “It’s what is in my DNA. That’s what I am.”
Working the night shift at Nakaseke General Hospital in rural central Uganda and tending to her family’s farm while off the clock, Nangalo is known for sleeping maybe one or two hours, if that, a day. When the power goes out in the middle of a delivery—which happens often—she uses the flashlight on her cellphone to get the job done. She even keeps her hair short rather than style it the way she’d prefer.
In her own words: “I’ve wanted my hair to be like other women. But then I think of the one dollar saving a mother’s life.”
That isn’t theoretical. Nangalo regularly reaches into her own pockets to ensure that expecting mothers have the transportation they need to get to the hospital in the first place—and the food, milk, and medicine they and their babies need to survive not only childbirth but also what comes next. She once tore a piece of her own bedsheet to give to a mother who didn’t have one at home.
It’s no wonder she’s made a name for herself—literally—among the women she’s served, with many choosing to name their daughters after her.
Her advocacy efforts—and their effects—are broad and far-reaching. Understanding the fears and misconceptions that exist in Uganda around healthcare facilities, she uses the radio to reach skeptics and explain the merits of hospital deliveries and the higher risks of fatal infection and bleeding inherent to home births. She helped establish a newborn clinic in Nakaseke, improving the safety of childbirth at the hospital and increasing the number of families served. She even pushed the government to make good on its own policies and open a health facility in every sub-county.
It’s no exaggeration to say that Eva Nangalo is making childbirth in Uganda safer for everyone involved.
“The future looks bright,” one colleague said, “if we have more and more people like Eva.” Fortunately, she’s working to ensure that’s exactly what happens.

The worst tragedy
Why do children die?
The toughest question I’ve ever had to answer.
Twenty-five years ago, I encountered a question that I have thought about literally every day since: Why do children die?
Before I tell you what drew me to this mystery, I want to acknowledge that child mortality is not an easy subject to talk about. As a parent, I can’t imagine what it would be like to lose a child. It is shocking even to see the words “children” and “die” used in the same sentence.
But I think “why do children die?” is one of the most important questions ever. It is hard to think of a measure of how a society is doing that reveals more than whether it is protecting its children, and especially its most vulnerable children. And the better we understand why children die, the more we can do to save them.
The very good news is that the world has made phenomenal progress in this area over the past several decades. Since 1990, the number of children who die every year has fallen by more than half! If progress on child mortality is a good measure of the state of the world, then—despite the huge global setbacks of the past few years, including COVID-19—the state of the world has improved dramatically. And based on what I know about innovations that are still to come, we can look forward to even more progress in the years ahead.
My introduction to the subject came 25 years ago, when I read a New York Times article about the health problems caused by unsafe drinking water in low- and middle-income countries. I was shocked to learn that every year, 3.1 million people—nearly all of them children—died of diarrhea, often because they had drunk contaminated water. Diarrhea kills 3.1 million children?, I thought. That can’t be true, can it? But it was.
I had to know more. What other major inequities did I not know about?
I read everything about global health that I could find, and I spoke to as many experts as I could. I learned that researchers define child mortality as the death of anyone under the age of 5. They use that age because the first five years are the riskiest time of childhood, when kids are the most vulnerable.
Learning about the history of child mortality helped me put the statistics in context. In 1950, some 20 million children died. In 1990, it was down to 12 million children, even though more babies were being born. By 2000, the number had dropped to fewer than 10 million. By 2019, it was below 5 million. Virtually all of these deaths occur in low- and middle-income countries.
So the next question was, why were so many children dying?
Around 18 percent of the deaths were caused by non-communicable conditions, such as cancer and cardiovascular problems. The large majority—82 percent—of the deaths were caused by communicable diseases, such as diarrhea and malaria, and health problems that their mothers experienced—and exacerbated by risk factors including malnutrition. (This 18:82 ratio still holds true today.)
On one hand, this was heartbreaking. The worst killers were all things that people in rich countries considered just an unpleasant episode (such as diarrhea) or never experienced at all anymore (such as malaria). In other words, although it was obviously true that children were dying because of deadly diseases, that was only part of the explanation. They were also dying because of where they were born.
On the other hand, it was encouraging to learn that such a large share of the deaths was preventable. When I saw the breakdown of diseases, I thought: Here is our road map. This is what the Gates Foundation should be working on. With the right team, partners, and funding, we could help the world move through the list, systematically going after the worst killers. The solutions that already existed could be made more affordable and delivered to people in low-income countries. The ones that didn’t exist could be invented.
Here is the chart as it looks today:
As you can see, pneumonia is the top preventable cause, but the story here is one of real progress. In 2000, it took the lives of more than 1.5 million children, but by 2019, the number was around 670,000—still an awful number, but a reduction of more than 55 percent. The innovation related to pneumonia that’s going on today is so exciting that I made a separate post and video about it.
Diarrhea is another example of progress. In two decades, its death toll has dropped 58 percent. A key reason is the use of low-tech interventions like oral rehydration solution (sugar water, essentially), which replaces lost electrolytes. Governments also ran large-scale sanitation programs to cut down on the spread of bacteria. And scientists developed an affordable rotavirus vaccine, and the world came together to deliver it. Between 2010 and 2020, this vaccine prevented more than 200,000 deaths. By 2030, it will have prevented more than half a million deaths.
Even though the overall number of deaths has gone down by half, the relative positions of the top three killers have not changed. They are the same today as in 1990: neonatal disorders, pneumonia, and diarrheal diseases. As you can see in this graphic, the fourth slot is where there has been a huge shift. In 1990, it was occupied by measles, responsible for half a million deaths. Today, it’s malaria that is in the fourth slot—not because malaria deaths went up (they actually went down), but because measles deaths fell by a whopping 87 percent.
Why? Vaccines. Since 2000, Gavi, the Vaccine Alliance has provided measles vaccines to more than 500 million children—half a billion!—through routine immunization and special vaccination campaigns. (This is just one example of the magic of vaccines—although unfortunately vaccination rates have dropped because of the pandemic and other factors.) And malaria may not be #4 on that list for long, thanks to innovations like malaria vaccines, improved insecticide-treated bed nets, and sugar baits.
Many groups deserve credit for the decades of progress I’ve described in this post. Countries with high disease burdens have launched massive vaccination campaigns, strengthened their health systems, and shared best practices with each other. Wealthy countries generously give aid that supports these efforts. Pharmaceutical companies have contributed technical expertise and made products affordable for low- and middle-income countries. Foundations including the Gates Foundation have stepped up with additional funding for innovative ideas. (At the foundation, we have staff and partners dedicated to each slice of the pie you see above.)
Although it’s still true that too many children do not live to see their fifth birthday, the world is moving in the right direction. If everyone keeps doing their part, we can move even faster and save even more lives. Because of COVID and other setbacks, the United Nations’ goal to cut childhood deaths in half again to below 3 million by 2030 will be missed, but it can still be achieved the following decade.
At a time when war and pandemic are in the news every day, it is important to look for reasons to be hopeful. The world’s opportunity—and ability—to save children’s lives is surely one of those reasons.

Bad air
A big threat to malaria eradication
Climate change could stall the world’s amazing progress on health.
It’s mind-blowing how much health has improved for the world’s poorest people over the past two decades. Malaria deaths, for example, have dropped by more than a third. Eradicating the disease has become a realistic goal.
Unfortunately, climate change threatens to slow or even reverse this progress. As temperatures go up and extreme weather events become more common, it will get harder to do things like provide bed nets, get rid of malaria-carrying mosquitoes, and offer basic health care in the world’s most vulnerable communities.
I’m optimistic that the world can avoid a climate disaster. But that effort can’t come at the expense of continuing progress on health care including malaria efforts.
If we fight only climate change and stop working on health, then we might reduce carbon emissions but allow malaria to make a comeback. Eradication would become even harder. No one will be better off in a world with fewer carbon emissions but more illness and death.
In this video, I talk more about the connection between climate change and malaria and explain why I’m optimistic that we can solve both problems.

The life of Neandersquito
This scientist uses old insects to help fight malaria
Mara Lawniczak has an ingenious approach to studying mosquito evolution.
Of all the things I thought would help fight malaria, 100-year-old mosquitoes would not have been high on the list. Then I learned about the work of Dr. Mara Lawniczak.
An evolutionary geneticist at the Wellcome Sanger Institute in the United Kingdom, Mara has spent much of her career trying to understand how the genomes of various mosquito species have changed in response to humans’ attempts to kill them. When, where, and how fast has it happened? What does that say about how they might evolve in the future?
In recent years, genetics has become an increasingly important tool for fighting malaria. Because mosquitoes breed so fast (a female can lay thousands of eggs in her lifespan of a couple of weeks), they evolve rapidly, at least compared to humans. By studying their genes, researchers are able to understand things like how they develop resistance to insecticides, crucial information that helps humans stay one step ahead.
After a few years of studying mosquitoes’ genomes, Mara had grown frustrated by the fact that the only insects available for study were ones that had been captured recently. Without DNA from their ancestors, there was no way to know how their genomes had responded to decades of human attacks. “We were often saying, ‘If only we could look into the past,’” Mara says. “And then it suddenly struck me: I'm sure there are historical collections of mosquitoes around.”
She was right. The Natural History Museum in London has a collection of 34 million insects from all over the world, carefully collected and preserved. Among the collection is a large sample of mosquitoes dating from 1936, when a British entomologist named H.S. Leeson spent a year in East Africa capturing and cataloguing the insects in the hope of learning more about malaria. Leeson didn’t know it at the time—DNA wouldn’t be discovered until the 1950s—but his collection of mosquitoes would become a vast source of genetic material that someone like Mara could study.
Mara reached out to the museum’s curators. They wanted to help, but there was a problem: Extracting DNA from the insects would require Mara to grind them up. Since the museum’s mission is to preserve its collection for future generations, they couldn’t let her do that.
So Mara and her colleagues invented a way around the problem. Working with the museum’s team, they developed a novel way to extract DNA from mosquitoes without damaging the specimen.
They affectionately call this work Project Neandersquito. It’s not because the mosquitoes date from the time of Neanderthals, some 40,000 years ago—this isn’t Jurassic Park, where they extract dinosaur DNA from a prehistoric mosquito trapped in amber. It’s because the mosquitoes they’re studying are 1,000 or 2,000 generations removed from modern ones, just as Neanderthals are more than 1,000 generations removed from modern humans.
Mara’s team has made some surprising finds. For example, because mosquitoes started developing resistance to the insecticide DDT in the 1950s, they expected to see genetic mutations for resistance appearing around the same time. But they didn’t. “We still don't see them even as late as the 1980s,” she says. “So the mosquitoes were somehow making themselves resistant to DDT in ways that we still don't really understand.”
They also hope to get insight into what's coming. “How fast can mosquitoes evolve? And as we throw new control initiatives at them, how quickly are they going to get around them?” Other labs are now using the process devised by the Lawniczak Group to do their own research.
Project Neandersquito is just one of the ways Mara and her team are using genomics to advance the fight against malaria. A different project, the Malaria Cell Atlas, is providing new genetic data that could inform the effort to make better malaria drugs and vaccines. Another project is designed to make it easier and cheaper to identify a mosquito’s species using its DNA—it’s surprisingly hard to do just by looking—as well as whether it’s carrying the parasite that causes malaria, and even which species of the parasite it has. Ultimately, the project’s goal is to help governments get data that will help them get the most out of their anti-malaria efforts.
Mara would be the first to say that these are just a few examples of the tools the world needs to eradicate malaria. It’s going to take global cooperation from governments, the private sector, and academia. And now we can add natural history museums to the list.

Guest post
The malaria geneticist cultivating the next generation of African scientists
Why Dr. Charles Wondji moved from a prestigious UK university to open a lab in Cameroon.

Each year, I love sharing stories from around the world about the incredible work being done to fight malaria. Sometimes, though, those stories are best told firsthand. That’s why I invited Professor Charles Wondji—a malaria researcher, mosquito geneticist, and executive director of the Centre for Research in Infectious Diseases in Cameroon—to share his.
Dr. Magellan Tchouakui, Cameroon, Medical Entomology and Vector Control
Dr. Tchouakui is an expert in assessing the impacts of insecticides on major African malaria vectors’ abilities to survive and reproduce. He’s passionate about putting that research to use, and leads the testing of many companies’ novel insecticide formulations to improve bed nets and indoor-residual sprays.
Dr. Mersimine Kouamo, Cameroon, Functional Genomics
Dr. Kouamo employs tools such as transgenesis to “knock down” certain genes in mosquitoes, allowing her to study the genes’ functions and understand which ones enable the mosquitoes to withstand insecticide exposure. She is also a role model to younger female scientists.
Dr. Leon Mugenzi, Rwanda, Molecular Genetics of Vectors
Dr. Mugenzi’s interest is in providing and improving the tools used to control the spread of malaria. During his PhD work at CRID, he designed the first DNA-based diagnostic tool to detect metabolic resistance in mosquitoes to insecticides, which helps prolong the effectiveness of bed nets.

Target acquired
The newest weapon against mosquitoes: computer vision
The tech behind self-driving cars is also helping fight malaria.
Can computers see? The answer is complicated. I've been following the field of computer vision for decades—ever since Paul Allen and I started dreaming about what you could do with a personal computer—and we're only now reaching the point where they can really understand visual inputs. We still have a long way to go, but the ability of computers to see things is already revolutionizing many parts of our lives. It makes autonomous vehicles possible. It’s used to read x-rays quickly and accurately, and it’s what allows a mobile phone to translate street signs from one language to another.
Lately I’ve been especially enthused about a different application (and one my teenage self never would’ve imagined caring about): scanning pictures of mosquitoes.
Mosquitoes are responsible for spreading malaria, which kills more than 600,000 people every year and is a major focus of the Gates Foundation’s health work. Although scientists have learned a lot about them in the past few decades, one challenge has been especially stubborn: telling one mosquito from another. There are around 3,500 different species of them, and many look alike. Even a highly trained entomologist has to examine one for several minutes under a microscope to identify it accurately.
Why do we care about mosquito species? Most importantly, because different species can carry different diseases, and some don’t carry any diseases at all. (The ones that carry malaria belong to the genus Anopheles.) There are other differences too: Some bite people indoors, while others feed outdoors. Some dine at dusk while others take their meals during the day. And only females bite—the blood gives them the energy needed to lay eggs.
All this variation means we need different tools for different mosquitoes. For example, indoor insecticides and bednets work well against species that primarily bite indoors. But for the ones that mainly live and feed outside, you’ll need to take other steps too, such as eliminating the outdoor spaces where they breed.
Fortunately, some novel uses of computer vision are supercharging the process of identification. They’re not only helping us know our opponent, they’re helping us target its weak spots, save more lives, and move even closer to eradicating malaria.
One of the most exciting innovations is called VectorCam—an app that lets someone with minimal training identify mosquito species in a matter of seconds.
VectorCam was developed by Dr. Soumya Acharya and his team of bioengineers at Johns Hopkins University, with support from Uganda’s malaria control program, Makerere University, and the Gates Foundation. Using a smartphone, the VectorCam app, and an inexpensive lens attached to the phone, you simply take a picture of a mosquito and get it identified right away. The app can distinguish among the different species that transmit malaria. It can also determine the sex of the mosquito and, if the insect is a female, whether it has recently fed on blood or developed eggs. And with further refinement, VectorCam could identify species that carry other diseases, like dengue and Zika.

Urban invader
The world’s newest weapon against malaria? Mosquitoes
A city-dwelling mosquito threatening Africa sparks innovation in the fight against malaria.
About 10 years ago, the African country of Djibouti had nearly succeeded in wiping out malaria. The country’s leaders hoped that getting rid of the disease would help them attract new investment, development, and tourism.
Then suddenly the disease roared back. Cases surged from just 27 in 2012, to more than 73,000 in 2020—a huge number for this East African nation of just one million people.
The cause?
A highly invasive mosquito that had migrated from South Asia and the Arabian Peninsula into Africa.
This pest—the Anopheles stephensi mosquito—has now emerged as one of the biggest threats to malaria elimination in sub-Saharan Africa. Since establishing a beachhead in Djibouti, An. stephensi mosquitoes have been detected in Ethiopia, Sudan, Somalia, Kenya and as far away as Nigeria and Ghana, in West Africa. According to one study, if this mosquito is left unchecked an additional 126 million people on the continent will be at risk of malaria.
What makes An. stephensi particularly dangerous is where it has chosen to reside. Unlike other malaria-carrying mosquitoes in Africa that primarily breed in rural areas, An. stephensi thrives in urban environments. Cities are already home to 40 percent of the population in sub-Saharan Africa and continue to experience rapid growth, creating a fertile habitat for this mosquito. Making matters worse, An. stephensi has been found to be resistant to many of the insecticides used to control mosquito populations. And they bite in the evening before bedtime—not in the middle of the night like other mosquitoes—making bed nets less effective as protection.
But this story doesn’t end here.
In 2018, the government of Djibouti, in search for a new approach to combat these urban invaders, heard about a biotechnology company called Oxitec that has a potentially game-changing solution to mosquito control.
The fight against mosquitoes and the diseases they carry has always been a game of cat and mouse. Humans develop new interventions—like bed nets, insecticides, and treatments—to protect themselves from mosquitoes. Mosquitoes, meanwhile, have an incredible capacity to adapt, allowing them to eventually dodge or develop resistance to the latest control methods. Then humans respond with more innovations to outsmart the mosquitoes. And so on.
Oxitec, however, aims to change this game from cat versus mouse to mouse versus mouse. Or in this case, mosquito versus mosquito. Oxitec specializes in using mosquitoes to fight other mosquitoes. With its genetic technology, Oxitec has already developed mosquitoes to effectively combat the dengue fever–carrying mosquito, Aedes aegypti, in Brazil. Now Oxitec plans to use the same technology to help African governments control An. stephensi and reduce the spread of malaria.
Here’s how Oxitec’s technology would work against An. stephensi mosquitoes: Oxitec male mosquitoes carry a special gene to prevent their female offspring from surviving into adulthood. (Only female mosquitoes bite and spread malaria.) Released into the wild, the male Oxitec mosquitoes mate with wild female mosquitoes. All the female offspring die. All the male progeny, which don’t bite, will survive and go on to mate with other wild females. With sustained releases of male Oxitec mosquitoes, more females die off, dramatically reducing the mosquito population and the spread of malaria. After the mosquito releases stop, however, because half of the gene’s carriers (the females) cannot survive, the gene steadily declines and disappears from the mosquito population within a few generations.
Genetic technology like Oxitec’s understandably raises many questions. Is it safe? What are the lasting environmental impacts? Here’s what’s important to know:
Because it’s passed through mating, the gene the Oxitec male mosquitoes carry only targets the An. stephensi mosquitoes. It doesn’t have any impact on other insects and cannot be established in the local ecosystem. After evaluating the potential risk of genetically modified mosquitoes, the U.S. Food and Drug Administration in 2016 and the EPA in 2022 have confirmed that the Oxitec mosquitoes do not pose a threat to humans or the environment. More than one billion Oxitec mosquitoes have been released worldwide, with no negative impacts. In Brazil, the Oxitec Aedes aegypti mosquitoes have been so successful in reducing the spread of dengue fever that they are in demand by communities, governments, and businesses in Brazil. Homeowners can even buy a kit to raise the mosquitoes in their own backyards. (If you want to learn more about this technology, I encourage you to visit the Oxitec website and the Centers for Disease Control and Prevention.)
Last year, the government of Djibouti formed a partnership with Oxitec, Association Mutualis (a non-profit public health organization in Djibouti), and the Djibouti National Malaria Control Programme to use this new technology to defeat An. stephensi.
No Oxitec mosquitoes have been released in Djibouti during the current pilot phase of the project. But the government of Djibouti expects to move forward with the first releases of Oxitec mosquitoes next year in Djibouti’s capital city, where 70 percent of the population live.
This solution is being pursued with the support of the people of Djibouti. The government of Djibouti, Oxitec, and its local partners have been working together to educate and engage the public about this technology, going door to door to listen to their concerns, and ensuring all the communities’ questions have been addressed before moving forward with the release of the mosquitoes. Local support has been outstanding to date.
To end malaria, we need many new tools and innovations to reduce the burden of this disease and move the world closer to eradication. I’m excited about the potential of Oxitec’s technology to help Djibouti and the rest of Africa achieve this goal.

Welcome to Mosquito City
It’s always buzzing in Mosquito City
A city where researchers study how to repel, attract, and kill the world’s deadliest animal.
When’s the best time to kill mosquitoes?
While they’re making love—at sunset.
No kidding.
This is just one of many fascinating discoveries being made at a place called Mosquito City. Located in the swamplands of central Tanzania, the “city” is home to the world’s largest captive colony of mosquitoes used for researching ways to combat malaria and other mosquito-borne diseases. Day and night scientists work to better understand mosquito behavior (like when and where they enjoy having sex) as well as cutting-edge approaches to trap, repel, and most importantly, kill them.
I first learned about Mosquito City during a trip to Africa several years ago when I met scientists from Ifakara Health Institute, a Tanzanian health research organization which runs the site. While I haven’t had the opportunity to visit, Fredros Okumu, Ifakara’s chief scientist, offered a behind-the-scenes look at some of the research underway there in this video. If you’re wondering how they get enough blood to feed all the mosquitoes, watch for the moment when Fredros puts his arm in a cage containing more than 500 very hungry mosquitoes for a feed! (For larger mosquito colonies, too big for one human to feed, a cow is on the mosquitoes’ dinner menu.)
Mosquito City is located in a region of Tanzania that’s hot, humid, and swampy. In other words—perfect conditions for its primary residents. Malaria has been so widespread in this part of the country—once infecting 80 percent of the population—that one meaning of the name of the local town, Ifakara, is, “the place people go to die.”
Fortunately, malaria deaths are on the decline in recent years. One reason is the use of insecticide-treated bed nets, which remain one of the most effective means to control the disease. (New bed net distribution efforts like the one that just launched in Benin are helping to ensure every person at risk of malaria is protected by one.)
Still, much more needs to be done to fight the disease, especially as mosquitoes become resistant to some of the pesticides used to control them. That’s why scientists at Mosquito City are working to better understand mosquito behaviors and find ways to outsmart them.
“It's kind of a love- hate relationship. If you can't beat them, you join them for now, but then you can kill them from the inside. And that's what we try to do here at the Mosquito City,” Fredros says.
Fredros and his team are studying one of the deadliest mosquito species, Anopheles funestus. In southeastern Tanzania, it is responsible for nearly 9 out of every 10 cases of malaria even though other species of mosquito are far more common. And yet, it is one of the least understood species of mosquitoes because it is difficult to raise in a lab environment. Our foundation is supporting the Ifakara Health Institute’s research into its behavior so they can mount a targeted campaign against them.
One promising approach may be killing them while they are mating. Ifakara scientists learned that mosquitoes, including Anopheles funestus, have favorite locations—like rice fields, trash heaps, and banana trees—to mate. The male mosquitoes appear at their favorite mating spots at sunset to begin a ritualistic flight dance, drawing in the females. Because these mating events occur at predictable times and locations, researchers are experimenting with regularly targeting these swarms with pesticides, dramatically reducing the mosquito populations and malaria transmission.
As the researchers dig deeper into the unique characteristics of different mosquito species, it’s become more important to be able to quickly identify them. Once they understand which species is posing the greatest threat, they can choose the best methods to eliminate them. But identifying mosquito species and other indicators, like age, can be a laborious process. At Mosquito City, scientists are working on some alternative identification approaches that would accelerate their research. One is to use their buzzing sound to identify them. Another option uses infrared spectroscopy. Mosquitoes have a unique electromagnetic signal. By crushing the abdomens of mosquitoes and analyzing them under a spectrometer, researchers can identify the species and age of the mosquito.
Many of the innovations coming out of Mosquito City are designed to meet the immediate needs of the local community, who work in small farming villages and spend most of their day outdoors. Researchers have developed a variety of mosquito traps, some mimicking the odor of sweaty feet, a smell that mosquitoes find irresistible. They’ve created a range of mosquito repellents too, including furniture treated with repellent that allows people to sit outside in the evening and stay protected. They’ve even developed a line of sandals which will keep mosquitoes at bay from the sweatiest feet, protecting their owner from bites.
What will the team at Mosquito City think of next? I can’t wait to find out.

Know your enemy
The U.S. military versus the mosquito
Finding ways to protect soldiers from mosquitoes is a top priority at the Walter Reed Army Institute of Research.
The most dangerous foe U.S. soldiers may have ever encountered is the mosquito, which has caused more casualties than bombs or bullets during the nation’s conflicts.
One of the first military expenditures by the Continental Congress was $300 for quinine to protect General George Washington’s troops from malaria. During the Civil War, there were over a million cases of malaria in Union troops alone. In World War II, there were nearly 700,000 cases of malaria. In Vietnam, 50,000 cases. And more recently, of all the American soldiers deployed in Afghanistan, one out of every 20 of them battled malaria.
Finding ways to protect soldiers from the mosquito—the world’s deadliest animal—is a top priority at the U.S. Department of Defense’s Walter Reed Army Institute of Research (WRAIR).
I expect most people have never heard about WRAIR—or, if they have, they may be confusing it with the more familiar but separate institution, the Walter Reed National Military Medical Center, where U.S. presidents visit wounded troops and go for medical treatment.
It’s too bad more people don’t know about the work being done at WRAIR. Since its founding in 1893, WRAIR has been a global research leader into new malaria drugs, mosquito control, and more recently, vaccines, to protect people from mosquito-borne diseases. This research benefits the lives of not only American soldiers, but also billions of people living in areas where mosquito-borne diseases are a threat. That’s why our foundation collaborates with WRAIR on a range of research projects in malaria and other diseases that endanger the lives of people living in some of the world’s poorest areas.
Here’s one of many incredible facts that speak to WRAIR prominence in malaria research: WRAIR has contributed to the discovery and development of all FDA-approved malaria drugs, including primaquine, mefloquine, atovaquone/proguanil (Malarone), tafenoquine, and doxycycline. If you’ve ever traveled to an area where malaria is prevalent you’ve probably been prescribed one of these drugs for protection. And because of the spread of malaria drug resistance, WRAIR continues to explore new drugs to stay one step ahead of this threat.
WRAIR, in partnership with the Smithsonian Institute, also manages the world’s largest mosquito collection, which currently has more than 1.7 million specimens. Some of the oldest were collected by Walter Reed, the Army major who helped discover that yellow fever is transmitted by mosquitoes. WRAIR is named in his honor.
This large mosquito collection allows WRAIR researchers to “know their enemy,” by giving them a deep understanding of the huge variety of mosquito species that populate the globe so they can mount the most effective defenses against them.
The first line of defense for soldiers is their clothing and WRAIR has developed uniforms treated with insecticides to protect them. Then, there are mosquito nets and various repellents, including ones that double as camouflage paint.
Highly effective vaccines against malaria and other mosquito-borne disease are also a priority at WRAIR. WRAIR developed the first-ever malaria vaccine in conjunction with GlaxoSmithKline. Researchers at WRAIR also led the development of a Zika vaccine.
One of the most surprising and important areas of research at WRAIR are the human malaria infection challenge trials. As part of this program, WRAIR recruits volunteers who agree to be bitten by malaria-infected mosquitoes, exposing themselves to a curable form of the disease to test the effectiveness of various interventions. This might sound scary, but the trials are extremely safe. The volunteers are carefully monitored and are quickly cured before they become too ill. In the last 30 years, WRAIR has performed over 100 trials on over 2,200 volunteers. Thanks to this research, WRAIR has greatly accelerated the development of experimental vaccines and malaria drugs.
What’s most exciting at WRAIR is the research that will help us all prepare for the threats of the future, including climate change, which will increase the spread of mosquito-borne diseases.
As Col. Brian Evans, WRAIR’s chief entomologist, says, “The challenge is always evolving and the role of WRAIR is to keep up with that, to stay ahead of the game.”
Thanks to their incredible work for more than 125 years, WRAIR has done just that.
Releasing Hope
This factory breeds 30 million mosquitoes per week. Here’s why.
These mosquitoes are allies in the fight against dengue and other deadly viruses.
Inside a two-story brick building in Medellín, Colombia, scientists work long hours in muggy labs breeding millions and millions of mosquitoes. They tend to the insects’ every need as they grow from larvae to pupae to adults, keeping the temperature just right and feeding them generous helpings of fishmeal, sugar, and, of course, blood.
Then, they release them across the country to breed with wild mosquitoes that can carry dengue and other viruses threatening to sicken and kill the population of Colombia.
This might sound the beginnings of a Hollywood writer’s horror film plot.
But it’s not.
This factory is real.
And the mosquitoes being released don’t terrorize the local population. Far from it. They’re actually helping to save and improve millions of lives.
Here’s how they do it: The mosquitoes being produced in this factory carry bacteria called Wolbachia that block them from transmitting dengue and other viruses, such as Zika, chikungunya and yellow fever, to humans. By releasing them to reproduce with wild mosquitoes, they spread the bacteria, reducing virus transmission and protecting millions of people from illnesses.
I’ve written before about these amazing Wolbachia mosquitoes, including last year when a new study showed how effective they could be in preventing diseases. The randomized controlled trial conducted in Yogyakarta, Indonesia, found that Wolbachia-carrying mosquitoes reduced the number of dengue cases in the city by 77 percent and dengue hospitalizations by 86 percent. In a new study in Medellín, dengue cases have declined by 89 percent since Wolbachia mosquitoes started being released in 2015.
These results are a huge breakthrough, offering proof that this new technology will protect entire cities and countries against the threat of mosquito-borne diseases. The World Mosquito Program, which is leading the Wolbachia effort, is now releasing these mosquitoes in 11 countries: Brazil, Colombia, Mexico, Indonesia, Sri Lanka, Vietnam, Australia, Fiji, Kiribati, New Caledonia, and Vanuatu.
And what’s remarkable about the Wolbachia mosquitoes is that once enough of them are released to offer disease protection, it’s a solution that’s self-sustaining. Over time, families will be spared the heartbreak of losing loved ones and communities won’t need to spend money on prevention and treatment for these mosquito-borne diseases, freeing up funds for other health priorities.
The World Mosquito Program aims to spread Wolbachia among Aedes aegypti mosquitoes, a tropical mosquito that is a host for dengue, yellow fever, and other viruses. (Malaria is spread through a parasite carried by the Anopheles mosquito and is not a focus of the Wolbachia effort.) With climate change, there is an urgency to the World Mosquito Program’s work. As global temperatures rise, Aedes aegypti mosquitoes, are finding more regions of the world habitable, increasing the spread of these diseases. The biggest risk is posed by dengue, which infects more than 400 million people each year and kills 20,000.
The demand for these lifesaving mosquitoes continues to grow and that means the World Mosquito Program needs to produce hundreds of millions of Wolbachia mosquitoes. That brings us back to the factory in Medellín, which is currently the world’s largest mosquito breeding facility in the world, producing more than 30 million mosquitoes per week. Other World Mosquito Program sites around the world are also breeding Wolbachia mosquitoes, but Colombia’s is currently the largest.
Until now, killing or repelling mosquitoes with insecticides, bed nets, and traps has been the priority, not mass producing them. As difficult as it is to kill mosquitoes, raising them by the millions may be even harder. Mosquitoes must be bred, fed, and housed under ideal conditions for them to grow and reproduce. The factory in Medellín has been perfecting the process and improving its efficiency so they can breed and release Wolbachia mosquitoes on a large scale.
The centerpiece of the mosquito factory is a colony of Wolbachia mosquitoes, called the brood stock, from which all future populations of Wolbachia mosquito offspring are bred. The brood stock offspring are then raised to create millions of eggs, which hatch when put in water and become larvae. Fed with fish meal, the larvae grow to become pupae, which then become adults. To thrive, adults need sugar (check out this story about how researchers in Zambia are exploiting mosquito’s craving for sugar to create a new bait that will control the spread of malaria) and blood, which the team sources from expired stocks at blood banks.
Once the factory has bred millions of eggs and adult mosquitoes, they are ready to be released. The eggs are packaged in small gelatin capsules, each containing 300 eggs, which are given to residents to drop in water to hatch. The advantage of egg releases like this is that the eggs can easily be transported long distances and they can be hatched as needed. The factory also releases adult mosquitoes by the thousands from the back of motorcycles roving the city. The World Mosquito team is also experimenting with releases from drones. The adult releases allow the Wolbachia mosquitoes to immediately begin mating with the wild mosquito population and spreading the virus-blocking bacteria.
It’s exciting to see how far the World Mosquito Program has come. Years ago, the idea of releasing mosquitoes as an ally in the fight against diseases struck many people as crazy. But support for this innovative solution has caught on in communities around the world. These amazing mosquitoes are taking flight and saving lives.

The nose knows
Could perfume be our secret weapon in the war on mosquitoes?
Mosquitoes use their sense of smell to find new victims. A Swiss fragrance company is hoping to thwart them.
Are you a mosquito magnet? If you don’t seem to get your unfair share of mosquito bites every summer, chances are you know someone who does. Some people are just more attractive to the pests than others.
The reason why is probably how you smell. Mosquitoes rely on their sense of smell to find their targets, and they’re drawn to certain odors naturally produced by the human body. Although some people may be a little more attractive, the unfortunate truth is that we all smell like a delicious meal to mosquitoes. You can hide yourself for a while using a bug spray like DEET or treating your clothes with permethrin. But if you want sustained protection, you have to add another step to your routine, which not everyone has the time to do or can afford.
There’s good news on the horizon, though: A company called dsm-firmenich is working to make repelling mosquitoes as easy as washing up in the morning.
I actually visited dsm-firmenich’s lab in Geneva back in 2016, when I checked out their innovative work to improve sanitation for the world’s poorest by reducing toilet odors. The nutrition, beauty, and health company is one of the world’s largest manufacturers of flavors and fragrances. Most of their products are used to make our food taste better and our household products smell more appealing, but they also have a history of using their scent expertise to fight disease transmission. Their latest efforts are focused on stopping mosquitoes, because the diseases they carry kill hundreds of thousands of people each year, most of whom are children in low-income countries.
The team’s goal is simple: Incorporate scents that repel mosquitoes into everyday products. After doing extensive research into the household products used most frequently in places where mosquito-borne diseases are common, they decided to focus mostly on bar soap and powdered laundry detergent. (They’re also thinking about other things like body lotion and body cream.) These products are already scented with a fragrance—what if that fragrance also helped keep mosquitoes away?
The idea is that you gain an added halo of protection without having to add any new steps to your daily routine or buy any new products. No one at dsm-firmenich thinks this kind of protection will be a silver bullet, but their hope is that, when combined with other proven tools like bed nets, people can significantly and sustainably lower their risk of catching deadly diseases like malaria and dengue.
Making a bar soap that gives you all-day protection against mosquitoes is a lot more complex than just infusing it with citronella. The scientists in Geneva started by identifying a wide array of scent ingredients that keep the pests away and are commonly used to create perfumes. Some of these ingredients are true repellants, giving off a smell that causes mosquitoes to fly in the opposite direction. Others block receptors in the mosquito’s brain that usually perceive and draw them to humans.
As they were combining the ingredients to create new fragrances, the team knew they had to keep a human-centered design approach in mind. The best candidates wouldn’t necessarily be the most effective—they also had to smell clean and fresh. I love the smell of cheeseburgers, but I don’t think I’d want my laundry to smell like them every day even if they protected me from mosquitoes!
To test the most promising odors, researchers used a tool I know all too well: The arm-in-cage test, where a human puts their arm—which has been coated in the fragrance being studied—into an enclosed area filled with hundreds of mosquitoes. Sensors track how the mosquitoes respond and whether they’re biting the arm. The team considered any test with two mosquito bites a failure.
Behavioral tests like those being done in collaboration with the Swiss Tropical and Public Health Institute are still ongoing, but they’ve already revealed some surprising results. One of the most effective fragrances so far smells like lily-of-the-valley, a light floral scent that is commonly used in perfumery. It’s exactly the kind of fresh scent that people like in their soaps and laundry detergents. The team’s early results indicate that some lily-of-the-valley odors could be as effective as DEET when used at certain doses.
The next step is the most difficult, and it remains to be seen whether it will succeed. The mosquito experts at dsm-firmenich have handed off the best scent candidates to the company’s product formulation experts and perfumers, who are now looking for ways to make them last all day in consumer products.
It’s a tall order. Scent ingredients are fragile, and activities like scrubbing your hands or washing your clothes cause them to vanish quickly. (Think about how quickly that freshly laundered smell can fade from your clothes.) A perfume that protects you from mosquitoes all day will likely end up being the result of a whole lot of innovation and a complex combination of different scents, rather than one single ingredient. And, of course, the final result has to smell good enough that people are willing to use it every day.
Still, I’m optimistic the scent wizards in Geneva will find a way. The Gates Foundation is supporting their research with the hope that, one day, people in high-risk areas will gain more mosquito protection without having to do any extra work or spend any extra money. When the world gives children and families more tools to protect themselves, we save lives—and take the bite out of the world’s deadliest animal.

Trip photos
I found inspiration in India
Here are a few pictures from my latest visit to this amazing country.
Around this time last year, I wrote a Gates Notes post that began: “I just returned from my visit to India, and I can’t wait to go back again.”
Last week, I got my wish and returned to India—and now that I’m home, I can’t wait to go back for another visit.
My goal was to get an update on some of the world-changing ideas and inventions that are coming out of India, and that’s exactly what I got. I spent four days there, meeting with political leaders, government officials, scientists, philanthropists, women who are lifting their communities out of poverty, and many others. The Gates Foundation funds more work in India than in any other country (other than the United States), and it’s always uplifting and educational to be there in person and see the impact of the efforts we’re supporting. Here are a few photos from my visit.

Ancient country, new ideas
India’s innovations are still changing the world
I’m excited to see the latest breakthroughs during my visit this week.
I’ve been visiting India since the 1990s, and I’m on my way to visit again this week. Over the years, I’ve learned about its rich history and visited some of its stunning monuments, including the Taj Mahal.
But when I think about India’s most important contributions to the world, these are not the first things that come to mind. India’s greatest gift is its ability to innovate.
This country has a long history of important breakthroughs. (Mathematicians in ancient India are widely credited with introducing the decimal system for numbers.) More recently, India has made advances that are saving and improving millions of lives in India and around the world. The Gates Foundation has been a partner in some of these efforts, and I’m visiting this week to learn about how we can continue working with India to help its ideas and inventions reach everyone who needs them, no matter where they live. This will be a main topic when I meet with Prime Minister Modi this week.
Health is one area where India is making a big difference. This country is the world's largest producer of vaccines—it supplies more than 60 percent of all vaccines distributed by Gavi, the organization that has helped vaccinate more than 1 billion children in lower-income countries. Indian companies pioneered the creation of high-quality, low-cost vaccines and drugs, leading the world in making affordable treatments for diseases like HIV/AIDS as well as vaccines for rotavirus, pneumococcal pneumonia, and COVID. The government has helped deliver huge supplies of vaccines to its own people and to other low- and middle-income countries, and now it’s looking to do the same for medical devices and diagnostics.
Thanks in large part to India, developing countries now get new medicines and vaccines much faster than they used to. I rank these efforts as one of the most important health achievements ever. (We’ve made progress, but we’re not done. The world should still do more to shrink the gap between when a drug or vaccine becomes available in rich countries and when it reaches lower-income ones.)
Another area where I admire India’s innovative spirit is what’s known as digital public infrastructure, or DPI. In short, DPI refers to the digital platforms and tools that help deliver various services. India’s biometric identity program, Aadhaar, covers more than 1.4 billion people, allowing them to take advantage of all kinds of government services without needing a photo ID. UPI, a digital payment system that ensures that the person you’re doing business with is who they say they are, processes more than 12 billion transactions a month.
During my trip I’ll get to see India’s DPI in action. I’ll visit an agricultural monitoring center in the state of Odisha where government officials use DPI to give farmers real-time guidance. Thanks to Aadhaar, this center is able to maintain a registry of 7.5 million farmers—even if they don’t own land—and their crops, so officials can keep track of who is growing what (and, therefore, what kind of farming advice they need). It has also developed a chatbot that makes it easy for farmers to get the latest information about their crops, using AI to tailor content to their particular needs and in their local language.
This service’s pest-management program now reaches more than 4 million farmers, and since it began in 2018, the volume of crops that participating farmers lose to pests every year has dropped by 90 percent. Now others—including other states in India as well as Ethiopia, Sri Lanka, and the World Bank—are looking to learn from Odisha’s experience with this service as well as its biometric ID and digital payments systems.
I'm also looking forward to learning more about how India is addressing urban poverty, especially among women. It has one of the fastest-growing urban populations in the world, and more than 100 million people there live in slums, where it’s hard and often impossible to get even basic services like health, education, and clean water. Women are particularly vulnerable because they face discrimination and violence.
This week, I’ll visit a low-income community in Odisha where a government program is helping women get the skills to fulfill government construction contracts. Since 2018, this program has helped 22,000 groups of women deliver on more than 52,000 projects including building roads, drains, and toilets.
This program could be a model for other countries that are facing similar challenges. The women who participate in it are partners in creating the projects: They get training in engineering, accounting, negotiating contracts, and other skills, and they’re involved in planning the project, making a budget, doing the construction, and doing maintenance on whatever they build. I'm looking forward to meeting a few women who are part of this program so I can hear about the challenges they face and the successes they’ve had.
India’s capacity to innovate will also become increasingly important to stopping climate change. Indians are already being affected by higher temperatures and less-predictable weather, and eliminating the greenhouse gases that are causing the problem is a huge scientific challenge. So it’s great that India is ramping up its ability to invent, manufacture, and deploy climate breakthroughs. The government is investing in research to raise the productivity of crops and livestock even in a warmer climate, and it’s expanding its plans for clean energy.
These are just a few of the ways in which India's innovations are changing the world. I could list many more, and I’m sure I’ll learn about a few new ones during my visit. I’m looking forward to speaking with government leaders, CEOs, and students who will drive innovation in India. This country has a lot to offer, and I'm optimistic that it will continue to lead the way in creating a more equitable world.


Exemplary
Lessons in lifesaving from Brazil
What the biggest country in South America can teach the world about healthcare.
I’ve been a big fan of Brazil for a while. I first visited back in 1995 when Microsoft was building out our operations there, including working with one of the national banks to launch home banking. And some of my favorite family trips have been to the Amazon, whose river, basin, and rainforest come up often during conversations on climate change. But it wasn’t until I began working in public health that I started appreciating just how impressive the country’s track record in this area is—and how much the rest of the world could learn from it.
In roughly three decades, Brazil has cut maternal mortality by nearly 60 percent, slashed under-five child mortality by 75 percent—far outpacing global trends—and increased life expectancy by almost a decade. None of these achievements was accidental. Instead, they’re the result of long-term, laser-focused investments Brazil has made in its primary healthcare system that other countries can learn from and emulate.
The story starts in the late 1980s. Two decades under military dictatorship had turned Brazil into one of the least equitable countries in the world. In 1985, the country became a democracy; a few years later, it created a universal health system.
In the decade that followed, deaths from non-communicable diseases and maternal, neonatal, and nutritional causes all started to decline, and life expectancy rose. With an increase in primary healthcare services, even hospitalizations dropped.
But it’s one thing to guarantee healthcare. It’s another thing to fund it—and another thing entirely to make sure it reaches the people who need it most. While Brazil had been making progress, there was much more to do. So at the turn of the century, the government accelerated its efforts and took steps to close the gaps in its healthcare system, including a dramatic increase in healthcare spending. One of the most important steps was massively expanding the size and scope of its community health worker (CHW) program.
Community health workers are trained public health professionals who work within communities, especially in remote or underserved areas. While their roles vary around the world based on local needs, they generally include things like disease tracking, vaccine drives, and basic health screenings.
In Brazil, CHWs had already shown they could improve public health access and outcomes during a pilot program in the Ceara state. As federal funding for primary healthcare increased, almost fivefold in fifteen years, the ratio of CHWs tripled.
Today, Brazil has over 286,000 CHWs who serve almost two thirds of the population—almost 160 million people. Each one visits about 100-150 households a month, offering guidance on health and hygiene, advocating for preventive care, following up after medical appointments, collecting socioeconomic data, and helping people navigate other government services.
In Brazil, CHWs act as the front door to the world’s largest universal free public healthcare system, and their impact has been transformative. They’re credited with further cutting child mortality and pushing immunization coverage to near-universal levels. (Unfortunately, the pandemic impacted vaccination rates, but there are efforts underway to bring them back up.)
The country’s Bolsa Familia program—which provides cash transfers to poor families if they meet certain conditions, including vaccination for children and prenatal care—deserves credit too. Expanded in tandem with primary healthcare, Bolsa Familia is just one of the many social programs Brazil has built out over the past few decades that have helped lift almost a fifth of the country’s population out of poverty. But it’s also helped broaden healthcare access and usage by giving people an incentive to enter the healthcare system—which is how Bolsa Familia has contributed to reductions in child mortality as well.
I’ve been able to learn about these initiatives through the Gates Foundation's partnership with Brazil's Ministry of Health—which has focused on combatting malaria, improving vaccine production, leveraging local brainpower to address global health issues, and documenting the impact of social and health programs through data sciences. And I’ve been really impressed.
Of course, despite all the progress that’s been made in recent decades, Brazil still faces challenges. Financial crises and austerity budgets have led to cuts in healthcare spending, for example, and there are still districts where poorer residents have no access to CHWs.
But Brazil’s healthcare system doesn’t have to be perfect to serve as proof of what happens when a country invests strategically in care for its most vulnerable: The returns are often far-reaching and life-changing.
That is why Brazil is highlighted by the Exemplars in Global Health program, which I helped launch in 2020. The program's mission is to identify countries that have made remarkable progress on health problems, understand the keys to their success, and share those insights globally so others can make similar progress. By that standard, Brazil has a lot to teach.
That’s not to say any country can or should replicate Brazil’s approach exactly, since no two countries are alike. But with the right mix of investment and innovation, Brazil has made great strides in becoming a healthier place for its people. If the country continues on that path and keeps doing what it’s done well already, and if other countries follow—or simply forge their own paths with Brazil in mind—we’ll have a healthier world, too.

Rise to the challenge
5 of the coolest innovations I saw in Senegal
I got to meet with amazing scientists working on the next big breakthrough while I was in Dakar.
I had an amazing trip to Senegal last month. I always love getting the chance to travel and see the remarkable work the foundation’s partners are doing firsthand. These visits leave me more energized than ever to go to work every day—and my time in Senegal was no exception.
Senegal is a particularly interesting country to visit, because it has made exemplary progress improving the health of its people thanks to a focus on community-led care and many years of smart policymaking. Some of the statistics are mind-blowing: Since 1992, the country has cut its stunting rate in half. Since 2000, the number of Senegalese children who die before their 5th birthday has dropped by 70 percent. And since 2005, the number of women giving birth in health facilities has increased from 62 percent to 80 percent. It’s the perfect place to talk about progress.
One of the highlights of my visit was a trip to the Institut Pasteur de Dakar, or IPD—a research center that has been pushing the frontiers of global health for nearly a century. The facility does it all: IPD plays a key role in monitoring for disease outbreaks in the region; produces millions of diagnostics every year; serves as an educational hub for the next generation of health workers and biomanufacturing workers; and will soon resume manufacturing vaccines.
It was inspiring to meet with brilliant Senegalese scientists who are doing remarkable work to keep their country healthy. Senegal’s health transformation is, in large part, a testament to their dedication and deep understanding of their communities, and I loved talking to them about how they’re constantly evolving to meet the needs of the moment. For example, when COVID hit in 2020, IPD quickly built up a test manufacturing facility. They’re now in the process of expanding that capacity so they can produce other essential tests, like one for measles and rubella.
I was also excited to attend the annual meeting of the Grand Challenges initiative in Dakar last month. The Gates Foundation launched Grand Challenges 20 years ago with a single goal in mind: to identify the biggest problems in health and give grants to the researchers who might solve them. Our hope was to inspire more brilliant scientists to think more ambitiously about transforming health in low-income countries. We hoped to create a scientific community that had support to sustain R&D for the benefit of billions of people whose health needs had been neglected.
In 2003, we put forth 14 Grand Challenges. The initial list included developing a vaccine that didn’t require refrigeration, creating a TB treatment for latent infection, and inventing a needle-free drug delivery system. In the years since, we’ve issued more than 200 challenges—and we even launched our first AI-specific call-to-action earlier this year.
I was lucky to spend a lot of time in Senegal with amazing scientists working on the next big breakthrough. Here are 5 of the coolest innovations I saw:
- An AI trainer that teaches health workers in India how to treat high-risk pregnancies. Here’s a devastating statistic: One woman dies in childbirth every 2 minutes. Amrita Mahale and the team at ARMMAN are using artificial intelligence to improve the odds for new mothers in India. Their large language model will one day teach health workers how to treat high-risk pregnancies. The training chatbot can be used in both English and Telugu, and the coolest part is that it automatically adjusts to the experience level of the person using it. Whether you’re a brand-new nurse or a midwife with decades of experience, ARMMAN’s trainer can arm you with the knowledge needed to save lives.
- A low-cost mRNA vaccine platform that puts manufacturing where it’s needed most. mRNA vaccines helped prevent millions of deaths during the height of the COVID pandemic. A company called Quantoom developed a new platform that will make it cheaper and easier to build and run factories that can be adapted to make different mRNA vaccines. I was proud to announce that the foundation is investing $40 million to scale up local mRNA vaccine manufacturing in low- and middle-income countries—which includes funding for IPD to use Quantoom’s platform. This will increase supply, lower costs, guard against the possibility of vaccine hoarding in emergencies, and provide a path for local scientists to discover and develop their own vaccines.
- A new way of tracking mosquitoes on the molecular level to stop malaria. Cases of mosquito-borne diseases like malaria are increasing for the first time in decades. Although climate change is a big contributor, other reasons include conflicts and drug resistance. Fortunately, Isabella Oyier at the Kenya Medical Research Institute is fighting back against mosquito evolution. She uses molecular epidemiology to track mosquitoes who have the genes that cause drug resistance and integrate it into national malaria surveillance and monitoring efforts. This will give stakeholders more insight into where resistance is spreading—and how to stop it.
- A novel approach to treating a common microbiome disorder. Our bodies are home to more microbial cells than human cells, and the good bacteria in our microbiome play an essential role keeping bad bacteria in check. When that balance is off, you get diseases like bacterial vaginosis—a common disorder that, among other problems, can make women more susceptible to HIV infection or more likely to give birth preterm. Today’s treatments are not very effective, so I was excited to talk to Meilin Zhu and her team about a new approach they’re exploring. It uses oleic acids to inhibit the growth of a “gateway” bacteria that can lead to more bad microbes, as well as promote the growth of the good bacteria. This research is still in its early stages, but it’s promising.
- A new drug development platform that will make us better prepared for the next pandemic. Although the world made remarkable progress on vaccines when COVID struck, the same can’t be said for therapeutics. The team at Decoy Therapeutics is working to speed up the process of developing drugs with their promising new biologic platform. The idea is that lipopeptide molecules could be used to inhibit a virus’ fusion machinery and prevent it from infecting cells. If Decoy’s research pans out, scientists could one day use the platform to design therapies for novel viruses within days or even hours.
My time in Senegal reaffirmed my belief in the power of science and innovation. There is no question that our world faces some difficult problems. But when brilliant scientists dedicate their talents to taking on the world’s biggest challenges, progress becomes possible, and we move closer to a future when all people lead healthy lives.
The big picture
On the road in Nigeria and Niger
These were some of my favorite moments from the last week in West Africa.
Have you ever visited a place you haven’t been in a while, and it somehow manages to feel both new and familiar? That’s how I feel every time I go back to Nigeria.
It was amazing to return to Lagos and Abuja this week. I’ve been fortunate to spend a lot of time in Nigeria over the last two-plus decades, but it’s been nearly five years since my last visit due to the pandemic. Nigeria—and especially Lagos—is one of the most dynamic, vibrant places in the world, and I am always blown away by how much it's changed. At the same time, I loved getting to catch up with old friends and reconnect in person with longtime partners. (Remote meetings are great, but it’s nice to meet face-to-face on occasion.)
This week also marked my first-ever trip to Niger. Our foundation has been working with talented Nigeriens for years to help ensure children's health and prevent the spread of polio, and it was exciting to see the country for myself and talk about the future of that work.
It was a great week. These were some of my favorite moments:

Photo Album
My trip to India in pictures
Why my travels in India made me optimistic about the future.
I just returned from my visit to India, and I can’t wait to go back again.
I love visiting India because every trip is an incredible opportunity to learn.
During my travels last week in Mumbai, Delhi, and Bangalore, I met some amazing people, including political leaders, bureaucrats, philanthropists, and scientists, who taught me how they are using the power of innovation, science, and collaboration to find solutions to the world’s health, climate, and development challenges.
Along the way, I met a teen bridge champion, had fun conversations with two of India’s most popular YouTubers, and I even drove an electric rickshaw!
But instead of telling you about it, let me show you. Here are some photos from my trip and some of the stories behind them:

Multitasking
My message in India: To fight climate change, improve global health
Climate change and global health are inextricably linked. We need to make progress on both problems at the same time.
I’m headed back to India next week. Although I’ve spent a lot of time there over the years—doing everything from checking out toilets to visiting a village that’s home to the one poorest, most underserved castes in India—I haven’t been back since before the pandemic. I can’t wait to see how much progress has been made in that time.
This essay originally ran in the Times of India and Dainik Jagaran. You can read it here:
More than two decades ago, I set out to give the vast majority of my resources back to society. My goal from the beginning was to help reduce the awful inequities I saw around the world.
When I started this work, my biggest focus was global health, because it’s the worst inequity in the world and it’s a solvable problem. That’s still the case today. But as time went on—and as the disastrous consequences of a warming world became more evident—it became clear that you can’t improve life for the world’s poorest without also tackling climate change.
Climate change and global health are inextricably linked. Hotter temperatures will make poverty reduction harder by increasing food insecurity and the prevalence of infectious diseases and diverting resources away from those who need them the most. It’s a vicious cycle. The poorer a community is, the more vulnerable it is to climate change. And the more impacted a community is by extreme weather events, the more entrenched in poverty it becomes. To break the cycle, we need to make progress on both problems at the same time.
When I talk to people about this, I often hear the same response: “There isn’t enough time or money to solve both at the same time.” But this idea that we can only tackle one thing at a time is just wrong. I’m stubborn in my belief that with the right innovations and delivery channels to get them to the vulnerable, we’re capable of making progress on lots of big problems at once—even at a time when the world faces multiple crises. There is no better proof than the remarkable progress that India has accomplished.
Consider the field of next-generation chickpea plants currently growing at the Indian Agricultural Research Institute, or IARI, in Pusa. Chickpeas are a staple crop in India. They provide an important source of income for many smallholder farmers, and families across the country rely on them for nutrition. But the chickpea harvest is threatened by climate change. Higher temperatures could reduce yields by as much as 70 percent, putting lives and livelihoods at risk.
So, the Gates Foundation joined hands with India’s public sector and CGIAR institutions to support the work of researchers at IARI. They found a new solution: chickpea varieties that have more than 10% higher yields and are more drought-resistant. One variety is already available to farmers, and others are currently in development at the institute. As a result, India is better prepared to keep feeding its people and supporting its farmers even in a warming world. It’s no exaggeration to say that India’s agricultural future is growing right now in a field in Pusa.
One of the reasons why challenges like climate, hunger, and health seem insurmountable is that we don’t yet have all the tools to solve them. But I’m optimistic that one day soon we will, thanks in part to innovators like researchers at IARI.
India as a whole gives me hope for the future. It’s about to become the world’s most populous country—which means you can’t solve most problems there without solving them at scale. And yet, India has proven it can tackle big challenges. The country eradicated polio, lowered HIV transmission, reduced poverty, cut infant mortality, and increased access to sanitation and financial services.
How did they do it? India has developed a world-leading approach to innovation that ensures solutions reach those who need them. When the rotavirus vaccine—which prevents the virus that causes many fatal cases of diarrhea—was too expensive to reach every child, India decided to make the vaccine themselves. They worked with experts and funders (including the Gates Foundation) to build factories and create large-scale delivery channels to distribute the vaccines. By 2021, 83 percent of 1-year-olds had been inoculated against rotavirus—and these low-cost vaccines are now being used in other countries around the world.
There is no question today’s challenges will test the limits of that ingenuity and cooperation. India is on the frontlines of climate change. But the progress it has made on health will make its people more resilient and provide helpful insights for how to tackle other major challenges. And the pace of its development, its skill in rolling out large-scale programs, and its people’s innovative expertise mean that India can be a key part of making progress on today’s biggest challenges.
I’m going to India next week to see firsthand the work being done by innovators and entrepreneurs. Some are working on breakthroughs that will help us mitigate the effects of climate change, like the work being done by Breakthrough Energy Fellow Vidyut Mohan and his team to turn waste into biofuels and fertilizers in remote agricultural communities. Others are finding new ways to help people adapt to a warmer world, such as IARI’s efforts to create more drought-tolerant crops. I’m looking forward to seeing the progress that’s already underway by both the Gates Foundation’s and Breakthrough Energy’s amazing partners.
Like every other country on the planet, India has limited resources. But it has shown us how the world can still make progress in spite of that constraint. By collaborating and trying novel approaches, the public, private, and philanthropic sectors can turn limited resources into big pools of funding and knowledge that lead to progress. If we work together, I believe we can fight climate change and improve global health at the same time.

Back in China
I’m visiting the country after four years away
I’m seeing first-hand some of the innovations that could contribute to global progress.
I want to share a few impressions from my time in China. I just had a meeting with President Xi, in which we discussed the importance of addressing global health and development challenges, like health inequity and climate change, and how China can play a role in achieving progress for people everywhere.
As part of my work with the Gates Foundation, I’ve tried to visit China, India, countries in Africa and Europe, and Washington D.C. each year. On these trips, I’d talk to researchers, government leaders, advocates, and other experts who are working on inequities in health and development. I’d always learn a lot, returning inspired by what I saw and heard.
It’s great to be able to resume these regular visits. This was my first trip to China in four years, and immediately after this trip, I’m headed to West Africa for the first time in five years. And I went to India in March.
On each trip this year, I have a key message: Over the past two decades, the world made significant strides in reducing poverty and improving health outcomes, but COVID was a big setback and even reversed progress on some global goals like reducing poverty and fighting TB and malaria. Many African countries, for example, are particularly impacted by overlapping challenges, including the effects of climate change, high food prices, escalating poverty rates, surging infectious diseases, and significant debt pressures.
Even though the challenges facing many African countries are complex, I’m optimistic that innovation in health, agriculture, digital finance, and energy will help improve lives there. I’m looking forward to meeting leaders and young people helping to accelerate progress when I visit West Africa.
Solving these problems requires innovation—both new tools and new ways of doing things. China has eliminated diseases, including polio and malaria, within its borders, developed drugs like artemisinin that have saved millions of lives around the world from malaria, made great strides in poverty reduction, and has made significant investments in clean energy and climate adaptation. So I was looking forward to seeing what’s changed since my last visit four years ago.
One highlight was my visit to the Global Health Drug Discovery Institute, an organization our foundation helped establish six years ago in partnership with the Beijing Municipal Government and Tsinghua University. GHDDI represents a productive way for public and private partners to work together on discovering new medicines for diseases that disproportionately impact the world’s most vulnerable populations but have applications for the world. I spoke about the institute’s work on TB and malaria yesterday, and we also extended our partnership over the next five years.
I also got to visit the National Crop Genebank of China. This facility is a prominent crop research center and also serves as a long-term preservation storage space for seeds so that scientists around the world have access to important genetic data. During my visit, I met with agricultural scientists who are working with their counterparts worldwide, particularly in Africa, on new rice varieties that help farmers increase their productivity and minimize the need for fertilizers, pesticides, and irrigation.
The benefits of their work have reached millions of farming households across Asia and Africa. The continued investment in technology and innovation within the agricultural sector has played a significant role in the increase in agricultural productivity throughout China. What excites me even more is China’s commitment to share their expertise and innovative practices with low-income countries. By assisting farmers in adapting to climate change, increasing their income, and combating food crises, they are making a substantial contribution to global food security.
The genebank and GHDDI are just two examples of the promising work the foundation has seen in China in the more than 15 years we’ve been partnering here. And there will be more opportunities for China and others to step up later this year, including a summit on development financing in Paris, a meeting of the G20 in New Delhi, and the COP28 climate conference in Dubai.
I’m convinced that if the world works together to address climate change, health inequity, and food security we can make extraordinary progress. And I’m looking forward to exploring new opportunities for collaboration and innovation that will make a better future for everyone.

Across the finish line
Makoy Samuel Yibi won’t stop until the world eradicates its next disease
Guinea worm once infected 3.5 million people every year. Thanks to heroes like Makoy, that number dropped to 13 last year.
When you see someone suffering from a terrible disease, it’s hard not to imagine a world where no one has to feel this way ever again. But the problem with eradication is that it’s really, really hard. The fewer cases remain, the more difficult it is to find them. That’s why, in all of human history, we’ve only eradicated two diseases: smallpox and the cattle disease rinderpest.
That might change soon.
The world is close to eradicating Guinea worm disease, a debilitating and painful condition that once devastated an estimated 3.5 million people in Africa and South Asia every year. Thanks to heroes like Makoy Samuel Yibi, that number dropped to 13 people in 2023.
As the national director of the South Sudan Ministry of Health’s Guinea Worm Eradication Program, Makoy helped reduce the number of cases in his country last year to just two. That’s a remarkable accomplishment by any standard, but it’s truly impressive when you consider the circumstances he and his team have faced: civil wars, the COVID-19 pandemic, the political changes brought by South Sudan’s decision to become an independent country in 2011, and the fact that the nation was once home to 90 percent of the world’s Guinea worm cases.
I recently caught up with Makoy at the COP climate conference in Dubai, where we both participated in an event focused on ending neglected tropical diseases, or NTDs, like Guinea worm. When you meet him in person, it’s hard to imagine a better person for the job. Makoy is passionate, brilliant, and laser-focused on making life better for the people of South Sudan. So I was surprised to learn that, as a young man, he never imagined a career in health.
Makoy was born in Terekeka County, a rural area located on the shores of the West Nile in southern Sudan. When he was a young man, Makoy had one primary focus: avoiding military service, which could be extremely dangerous. A chance meeting with a general from Terekeka resulted in a position with the national health department. A measles outbreak was ravaging parts of Sudan at the time, and Makoy’s first assignment was to travel from village to village providing care.
“What struck me,” he recalls, “was that, in every household we went to, we found at least half of the household was down with Guinea worm.”
The Guinea worm is a particularly nasty parasite. It’s unlikely to kill you, but the disease it causes—which is also called dracunculiasis, or “afflicted with little dragons”—can incapacitate you for months at a time and leave you permanently disabled. That can have devastating consequences if your family counts on you to grow the food you eat and sell it to make a living, as many people in South Sudan do.
The way the disease works is horrifying. If a person drinks water contaminated with Guinea worm larvae, the larvae enter the digestive system and mate. The impregnated female worm grows, undetected by the body’s immune system. Around a year later, the infected person will start to feel an itch somewhere on their body (usually the lower leg or foot). After a couple days, a painful blister appears and eventually bursts. The worm—which is now about one meter long—slowly starts to emerge from the wound.
This can take weeks or even months, and the pain it causes is excruciating. The wound can get infected, which could result in permanent disfigurement or even require amputation. And people often endure multiple worms emerging at the same time. Makoy has seen patients with as many as 40 worms.
And here’s the most insidious part: One of the few ways to relieve the pain of the blister is by soaking it in cold water, like a pond or a puddle. But that’s exactly what the worm wants. As soon as it touches water, it releases its larvae, starting the cycle anew. The Guinea worm is scarier and more efficient than any monster in a horror movie.
Makoy has seen countless times how devastating Guinea worm can be. “This is a situation where you see serious disruption of the livelihood of the community,” he says. “You see people going through a cycle of hunger because they don’t have enough. They have lost the window of cultivation. They’re not able to tend to their cattle, and there’s nothing they can do.”
There is no cure or treatment for Guinea worm, and yet, the world is on the doorstep of eradicating it. How? Through a series of highly effective interventions and a network of incredibly dedicated health workers.
Makoy’s team has built a network of volunteers in virtually every village in the country, who report rumors of Guinea worm cases. They spend every day searching for cases, getting the word out, and building trust in a country where more than 60 languages are spoken.
Makoy and his colleagues investigate every single rumor, no matter how remote. During the rainy season when the majority of cases happen, he often spends days hiking through the Sudd or up a mountain with all of his supplies on his back just to reach his destination. Last year, in a country the size of France with less than 100 miles of paved road, the team responded to nearly all of the 50,000 rumors they received within 24 hours.
Once the team finds a confirmed case, they make the patient as comfortable as possible and do what is called “controlled immersion.” This means soaking the affected area in a bucket of water and encouraging the worm to come out.
Makoy also spends a lot of time preventing people from getting Guinea worm in the first place. His team distributes free water filters and educates communities about safe water practices. The system they’ve built to support this work has strengthened health systems across the country, providing a platform for delivering other health services like childhood vaccination.
Makoy’s team has had a tremendous partner in all of this work: former U.S. President Jimmy Carter and the Carter Center. In 1995, when Makoy was first starting his public health journey, President Carter negotiated what remains the longest humanitarian ceasefire in history when he helped convince both sides of the Second Sudanese Civil War to lay down their arms and allow health workers access to treat Guinea worm and other diseases, like polio and river blindness. Today, the Carter Center continues to lead the global eradication campaign’s march to zero. The Gates Foundation is proud to support the Carter Center as part of our overall efforts to tackle NTDs. (You can learn more about Makoy’s partnership with the Carter Center in a new film called The President and the Dragon that is coming out later this year.)
Eradication is now within sight, although it won’t be easy to eliminate the last few cases. South Sudan previously reported no Guinea worm in 2018, but cases were subsequently discovered after a peace agreement was reached in the South Sudanese Civil War. And Guinea worm has recently been detected in dogs and other animals, mainly in Chad. Eradication will require stopping all transmission, both human and animal.
But Makoy Samuel Yibi is optimistic we can get there—and so am I. His determination to root out every last case makes me hopeful that we will someday soon celebrate the end of Guinea worm disease.
“In the places where Guinea worm has been eliminated,” he says, “you can actually see how communities have been energized. They are more active, and they are productive. The communities are now empowered to be more self-sufficient, because they don’t have to worry about Guinea worm.”

Ick!
What’s gross and better to see on an empty stomach? This museum in Tokyo
Welcome to the bizarre, creepy, and endlessly fascinating exhibits at the world’s foremost parasite museum.
You may want to skip lunch—and probably avoid sushi for dinner—when visiting the world’s foremost museum of parasites in Tokyo.
At the quirky and endlessly fascinating Meguro Parasitological Museum, which I toured during my trip to Japan in August, you’ll find hundreds of stomach-turning displays featuring creepy parasite specimens.
Some of the strangest-looking ones have resided inside the bodies of fish, turtles, pigs, and other animals. But by far the most horrific specimens are the parasites that have chosen humans as their hosts.
What steals the show is the world’s longest tapeworm. In 1986, this garden-hose length parasite was discovered living in the small intestine of a Japanese man. He had dined on a piece of raw salmon that was infected with a tapeworm egg smaller than a grain of rice. Over the next three months it grew and grew until it reached 29 feet long! (If you’re a follower on my Instagram account, you may have gotten a glimpse of this impressive specimen.)
The man who recovered the tapeworm from this unfortunate patient was Dr. Satoru Kamegai, the founder of Meguro Parasitological Museum. A physician, Dr. Kamegai started practicing medicine after World War II. At the time the country’s water and sanitation systems were in ruins and many people throughout Japan suffered from parasitic diseases. Dr. Kamegai became fascinated by the strange world of parasites and started collecting them from his patients. In 1953, he opened a small museum to display his findings and raise awareness of these creatures. Dr. Kamegai passed away in 2002, but the museum has continued to operate as a private research and educational facility.
Today, the museum has a collection of 60,000 different parasites, about 300 of which are on display in the two-story collection. Entrance to the museum is free and it draws a steady stream of visitors. It even has a gift shop with parasite-themed t-shirts, pens, and jewelry. (I picked up a t-shirt with the famous tapeworm on it.)
While I had a busy trip to Japan, I took time to stop at this museum because of our foundation’s efforts to reduce the burden of so-called neglected tropical diseases, many of them caused by parasites. More than 1 billion people suffer from these overlooked diseases with often difficult to pronounce names, including dracunculiasis (Guinea worm disease), human African trypanosomiasis (sleeping sickness), visceral leishmaniasis (black fever), onchocerciasis (river blindness), and schistosomiasis (snail fever).
These diseases can cause anemia and blindness, stunt children’s growth, lead to cognitive impairments, complicate pregnancies, and result in thousands of deaths each year. And it’s not uncommon for people living in extreme poverty to suffer from more than one of these diseases at the same time, affecting their ability to go to school or make a living.
Our foundation works with partners on the treatment and control of these diseases. One of the most successful efforts has been mass drug administration, which seeks to treat everyone against a disease—even if they are not actually infected or show any symptoms. I observed this incredible work in Tanzania, where I joined a group of health workers going from house to house to distribute medicine to wipe out lymphatic filariasis, one of the world’s most painful and debilitating diseases.
The good news is that there’s been a lot of progress in reducing parasitic diseases around the world. But there’s still more work to be done. That makes this museum a great place for people to learn about where these diseases still exist and the incredible work that’s going on to wipe them out.
If you happen to be in Tokyo, I encourage you to visit.
Neglected no more
A massive success
How to stop disease by treating everyone—even healthy people.
Health workers have an unusual tool for fighting disease that turns our old thinking about treatment on its head. I saw it at work recently in a remote hilltop village in Tanzania, where I joined a group of health workers going from house to house to distribute medicine to wipe out lymphatic filariasis, one of the world’s most painful and debilitating diseases.
At each home, one health worker told the family about the swollen limbs, disfigurements, and other symptoms of the parasitic disease. Another carried a tall stick to measure the height of each family member to determine the correct dosage. Then, if they were willing to be treated, the parents and children took their pills and washed them down with a cup of water before our team moved on to the next house.
What was surprising about this effort is that none of the people who took the medicine were sick.
The village I visited was participating in what’s known as a mass drug administration campaign, which seeks to treat everyone against a disease—even if they are not actually infected or show any symptoms. Typically, of course, the sick are the ones who get treated, not the people who are healthy. But when it comes to combating some diseases, like lymphatic filariasis, it’s critical for health workers to try to treat the entire at-risk population to break the cycle of transmission. If not, the disease could continue to be spread by those who are not aware they are infected.
Ten countries have successfully eliminated lymphatic filariasis in this way, including Togo, which this year became the first country in sub-Saharan Africa to wipe out the disease. Still, more than 800 million people in 52 countries worldwide remain threatened by lymphatic filariasis.
Mass drug administration is not only effective against lymphatic filariasis, but also other neglected tropical diseases, including schistosomiasis, onchocerciasis, trachoma, and soil-transmitted helminths. These diseases go by names that are largely unknown and often difficult to pronounce. But it should be easy to understand why we should all care about them. They afflict people living in the poorest countries and cause untold suffering.
Lymphatic filariasis is one of the worst of these diseases. It’s caused by a parasite that’s spread by mosquitoes, and in the severest cases people may develop swollen limbs, a thickening of the skin known as elephantiasis, or other severe disfigurements. Beyond the pain and disabilities they experience, people affected by the disease are often ostracized by their communities and are unable to work, sinking them deeper into poverty.
To combat lymphatic filariasis, health officials could test everyone and then treat only those people who are infected. But testing the population for these diseases would be expensive and slow. The medicines used for treatment (ivermectin and albendazole), however, are inexpensive and have no side effects, making mass treatment a more effective approach to protect people from the disease. (And thanks to the generosity of the many pharmaceutical companies, billions of doses of these and other medicines combating neglected tropical diseases are being donated for free.)
Like many countries running mass drug administration programs, Tanzania’s biggest challenge is treating enough of its population at risk of the disease. To break the cycle of transmission, health workers must treat at least 65 percent of the population every year for 5 to 10 years. As you might imagine, meeting this target year after year is not easy.
Health officials must have strong public awareness campaigns, thousands of trained health workers, a well-organized supply chain to distribute medicines to the remotest corners of the country, and regular disease surveying to track their progress. At the same time, the program provides treatment and care for people who are suffering from the debilitating symptoms of the diseases.
Walking from door to door in the village with the health workers, I was struck that perhaps the most important element of the program is trust. Taking the medicine is strictly voluntary, making it important that the health workers distributing it earn the confidence of the community. The health workers I met certainly had. They were knowledgeable, passionate about their work, and clearly cared about the community they were serving. At each home, they took the time to explain the goal of the program and address any of the villagers’ questions or concerns. Thanks to their hard work the latest survey of lymphatic filariasis in their district showed that the cycle of transmission had been broken. For the first time, the village was not at risk of the disease.
By 2020, Tanzania hopes to eliminate lymphatic filariasis entirely within its borders. Based on what I saw in this village, I’m optimistic they will.
24:00:00
Record-breaking generosity
On January 30, 2017, a group combatting neglected diseases did something extraordinary. Guinness World Records took notice.
Page through the Guinness Book of World Records and you’ll learn that a lot can happen in 24 hours.
On February 14, 2004, Dan Meyer of Davis, California, set the record for the longest paperclip chain by an individual in 24 hours. Length: 5,340 feet. Total number of paper clips: 54,030.
On June 4, 2011, Nabi Salehi, a barber in London, set the record for giving the most consecutive haircuts in 24 hours. Total haircuts: 526.
And on January 30, 2017, another achievement—one that will improve millions of lives—was added to the Guinness World Record list. A group fighting neglected tropical diseases—including Guinea worm, river blindness, and elephantiasis—set the record for most drugs donated in a 24-hour period. Total number of drugs: 207,169,292!
This week in Geneva, I was excited to participate in the ceremony to celebrate the group that achieved this incredible feat, Uniting to Combat Neglected Tropical Diseases, a coalition of drug companies, governments, health organizations, charities, and other partners who work to reduce the burden of tropical diseases that impact the world’s poorest.
On January 30th, they organized drug manufacturers, warehouse workers, delivery drivers, government officials, and health workers to deliver this historic number of donated drugs on four continents for distribution to people living in the remotest parts of the world.
What’s truly amazing is that the 207 million drugs donated on January 30th represent just a small amount of this group’s generosity. Since 2012, when United to Combat Neglected Tropical Diseases signed a declaration to control or eliminate 10 of the worst neglected diseases, they have donated 7 billion treatments. I’m grateful to the pharmaceutical companies that have been making these donations year after year: Bayer, Eisai, Gilead, GSK, Johnson & Johnson, MSD, Merck KGaA, Novartis, Pfizer, and Sanofi.
Thanks to the efforts of these drug companies and their partners millions of people are receiving the medicines they need to cure and protect them from these diseases. These diseases are in retreat and the world is moving closer to the day when they will be eliminated altogether.
Of course, all world records get challenged. And I for one will be thrilled for the day when this record for drug donations gets broken. So will the millions of families around the world who need them.
Warning!
Neglected no more
These diseases may be difficult to pronounce, but it should be easy to see why everyone should care about them.
Warning: you may find what I’m about to write disturbing.
Imagine a fly infected with parasites bites you. First you get a fever, then headaches, joint pains, and itching. Eventually, when the parasites cross the blood-brain barrier, you lose your mind, you can’t control your muscles, and then you lose your life.
Now, imagine you drink a glass of water. The water contains tiny fleas containing even tinier larvae. The larvae mate and grow in your body. One year later, a painful blister forms on your foot. The head of a worm pokes out. It’s 3-feet-long and takes weeks to remove.
Finally, imagine a mosquito bites you. It’s infected with tiny larvae. They set up camp in one of your lymph nodes, where they mate and nest, causing your leg to eventually swell to 10 times its size.
Sound horrific? Well, I haven’t told you the most disturbing part. I’m not making up these diseases (Human African trypanosomiasis, Dracunculiasis, and Lymphatic filariasis). They are just three of more than a dozen tropical diseases that afflict some of the poorest people in the world. As I write this, more than a billion people suffer from at least one of them.
These diseases go by names that are largely unknown and often difficult to pronounce.
Still, it should be easy to understand why we should all care about them. Spread by worms and insects, they disfigure and disable people living in the remotest areas of the world, keeping children out of school and parents from being able to work. In the worst cases, they kill. And all of them can be prevented—if the world continues to work together to end them.
I am in Geneva, Switzerland this week for a meeting to raise awareness and continue support for the fight against these overlooked diseases. Collectively, they’ve been dubbed “Neglected Tropical Diseases,” but lately they’ve been getting some of the attention they deserve.
Five years ago, Uniting to Combat Neglected Tropical Diseases, a group of pharmaceutical companies, governments, health organizations, charities, and other partners, came together to treat and prevent these diseases. They set a goal to control or eliminate at least 10 of them by 2020. Today, there’s a lot of progress to celebrate. Fewer people are suffering from them, and many countries are on their way to eliminating them altogether.
Here are some examples of the progress that’s been made.
Dracunculiasis (also known as Guinea worm), the parasitic disease I described above in which a large worm grows inside its victims, is nearing its end. In 1985, the disease afflicted an estimated 3.5 million people in 21 countries in Africa and Asia. Last year, thanks to the work of Uniting to Combat NTDs, The Carter Center, and other partners the number of Guinea worm cases has been reduced by more than 99 percent to 25 cases.
Lymphatic filariasis, also known as elephantiasis, is thepainful, disfiguring disease spread by mosquitoes. Five years ago, 1.5 billion people needed preventive drug treatment to protect them from the disease. Since then, it has been eliminated in six countries and reduced in 18 others.
Human African trypanosomiasis (HAT), commonly known as sleeping sickness, is also in retreat. Cases have declined by more than 90 percent, from 26,000 cases in 2000 to 2,733 in 2015.
What’s driving this progress? It’s been the result of drug donations by pharmaceutical companies and generous commitments by donors and governments. More than one billion people were reached with NTD treatments in 2015 alone—across nearly 150 countries.
New innovations for testing and treatment have also made a big difference. For example, the diagnostic test for sleeping sickness used to require electricity, bulky equipment, and refrigeration, making it difficult to deliver to remotest areas of the world. Now, a simple finger-prick blood test allows health workers to test for the diseases. And new smartphone-based mapping tools could make it easier to map these diseases so health workers can target their treatment efforts in real time down to the household level.
Still, there’s a lot of work to be done. We need continued support from donor governments to finish the job. We need more research on improved drugs and tests to help make it easier to treat people quickly. And we must support the frontline health workers who have the tough job of delivering the drugs in the hardest to reach regions of the world.
If the world keeps up the fight against these diseases, we can improve the lives of millions of the poorest families. They won’t be neglected anymore.
Take Action
Help us eliminate these debilitating diseases that afflict the world’s poorest by supporting The END Fund. The END Fund is a GiveWell Top Charity.

Wrapping up 2018
What I learned at work this year
Thoughts on Alzheimer’s, climate change, polio, and more.
Every Christmas when I was a kid, my parents would send out a card with an update on what the family was up to. Dad’s law firm is growing, Mom’s volunteer work is going strong, the girls are doing well in school, Bill is a handful.
Some people think it is corny, but I like the tradition. These days, at the end of each year, I still enjoy taking stock of my work and personal life. What was I excited about? What could I have done better?
I thought I would share a few of these thoughts as 2018 concludes.
One thing that occurs to me is that the questions I am asking myself at age 63 are very different from the ones I would have asked when I was in my 20s.
Back then, an end-of-year assessment would amount to just one question: Is Microsoft software making the personal-computing dream come true?
Today of course I still assess the quality of my work. But I also ask myself a whole other set of questions about my life. Did I devote enough time to my family? Did I learn enough new things? Did I develop new friendships and deepen old ones? These would have been laughable to me when I was 25, but as I get older, they are much more meaningful.
Melinda has helped broaden my thinking on this point. So has Warren Buffett, who says his measure of success is, “Do the people you care about love you back?” I think that is about as good a metric as you will find.
It may sound grand, but I think the world is slowly going through a similar transition to a broader understanding of well-being. For most of human history, we have been focused on living longer by fighting disease and trying to grow enough food for everyone. As a result, life spans have gone up dramatically. Technology has played a key role in that through vaccines, medicines, and improved sanitation.
We still need a lot of innovation to solve problems like malaria or obesity, but we are also going to be focusing more on improving the quality of life. I think this will be the thrust of many big breakthroughs of the future. For example, software will be able to notice when you’re feeling down, connect you with your friends, give you personalized tips for sleeping and eating better, and help you use your time more efficiently.
There are not the same clear measures of these things as there are for diseases, and there may never be. But there is nascent work in this field and I think it is going to accelerate.
As I look back on the year, I am also thinking about the specific areas I work on. Some of this is done through our foundation but a lot of it (such as my work on energy and Alzheimer’s work) is not. What connects it all is my belief that innovation can save lives and improve everyone’s well-being. A lot of people underestimate just how much innovation will make life better.
Here are a few updates on what’s going well and what isn’t with innovation in some areas where I work.
Alzheimer’s disease
I saw two positive trends in Alzheimer’s research in 2018.
One is that researchers focused on a new set of ideas about how to stop Alzheimer’s.
The first generation of theories, which dominated the field for years, emphasized two proteins called amyloid and tau. These proteins cause plaques and tangles in the brain, clogging up and killing brain cells. The idea was to stop the plaques and tangles from forming. I hope these approaches pay off, but we have not seen much evidence that they will.
In the past year, researchers have doubled down on a second generation of hypotheses. One theory is that a patient’s brain cells break down because their energy producers (called mitochondria) wear out. Another is that brain cells break down because part of the immune system gets overactivated and attacks them.
This is a great example of how improving our understanding of biology will reduce both medical costs and human suffering.
The other trend this year is that the Alzheimer’s community focused on getting more and better access to data. We’re working with researchers to make it easier for them to share information from their studies broadly so that we can better understand questions like how the disease progresses.
Over the past few years, the U.S. government has dramatically stepped up funding for Alzheimer’s research, from $400 million a year to over $2 billion a year. There is also a big push to create better diagnostics.
The only problem where I don’t yet see a clear path forward yet is how to develop more efficient ways to recruit patients for clinical trials. Without a simple and reliable diagnostic for Alzheimer’s, it’s hard to find eligible people early enough in the disease’s progression who can participate in trials. It can take years to enroll enough patients. If we could find a way to pre-screen participants, we could start new trials more quickly.
But there is so much momentum in other areas—scientific tools, better diagnostics, improved access to data—that as long as we can solve the recruitment problem, I am confident that we will make substantial progress in the next decade or two.
Polio
I thought we would be closer to eradicating polio today than we are. Unfortunately, there were more cases in 2018 than in 2017 (29 versus 22).
I underestimated how hard it would be to vaccinate children in places where there’s political violence and war. Families move around to escape fighting, which makes it hard to keep track of children and make sure they get all the doses of the vaccine. Or sewage systems get destroyed, allowing the virus to spread as children come into contact with an infected person’s excrement.
This is a key reason why Afghanistan and Pakistan have never been free of polio—in fact they are the only two countries that have never been free of polio.
I spend a lot of time on polio, part of it talking to the funders to make sure they continue their commitment even though eradication is taking longer than any of us would like. I remind them of the huge benefits of success, and the risk that the disease will return in a big way if we don’t finish the job.
I also remind them what a difference innovation is making. We’re now able to test sewage samples to track the virus and find the source before an outbreak starts. And the global health community is finding creative ways to work in war zones, having stopped outbreaks in Syria and Somalia in recent years.
Finally, I am hopeful about a new oral vaccine being tested in Belgium and Panama. The results should be out in 2019, and if this one proves effective, it would overcome some of the problems with previous oral vaccines when they’re used in places where few children are immunized. The new vaccine could be in use as soon as 2020.
Despite all the challenges, I am still optimistic that we can eradicate polio soon.
Energy
Global emissions of greenhouse gases went up in 2018. For me, that just reinforces the fact that the only way to prevent the worst climate-change scenarios is to get some breakthroughs in clean energy.
Some people think we have all the tools we need, and that driving down the cost of renewables like solar and wind solves the problem. I am glad to see solar and wind getting cheaper and we should be deploying them wherever it makes sense.
But solar and wind are intermittent sources of energy, and we are unlikely to have super-cheap batteries anytime soon that would allow us to store sufficient energy for when the sun isn’t shining or the wind isn’t blowing. Besides, electricity accounts for only 25% of all emissions. We need to solve the other 75% too.
This year Breakthrough Energy Ventures, the clean-energy investment fund I’m involved with, announced the first companies we’re putting money into. You can see the list at http://www.b-t.energy/ventures/our-investment-portfolio/. We are looking at all the major drivers of climate change. The companies we chose are run by brilliant people and show a lot of promise for taking innovative clean-energy ideas out of the lab and getting them to market.
Next year I will speak out more about how the U.S. needs to regain its leading role in nuclear power research. (This is unrelated to my work with the foundation.)
Nuclear is ideal for dealing with climate change, because it is the only carbon-free, scalable energy source that’s available 24 hours a day. The problems with today’s reactors, such as the risk of accidents, can be solved through innovation.
The United States is uniquely suited to create these advances with its world-class scientists, entrepreneurs, and investment capital.
Unfortunately, America is no longer the global leader on nuclear energy that it was 50 years ago. To regain this position, it will need to commit new funding, update regulations, and show investors that it’s serious.
There are several promising ideas in advanced nuclear that should be explored if we get over these obstacles. TerraPower, the company I started 10 years ago, uses an approach called a traveling wave reactor that is safe, prevents proliferation, and produces very little waste. We had hoped to build a pilot project in China, but recent policy changes here in the U.S. have made that unlikely. We may be able to build it in the United States if the funding and regulatory changes that I mentioned earlier happen.
The world needs to be working on lots of solutions to stop climate change. Advanced nuclear is one, and I hope to persuade U.S. leaders to get into the game.
The next epidemic
In 1918, the Spanish flu killed 50 million people worldwide. It still ranks as one of the deadliest natural disasters ever.
I had hoped that hitting the 100th anniversary of this epidemic would spark a lot of discussion about whether we’re ready for the next global epidemic. Unfortunately, it didn’t, and we still are not ready.
People rightly worry about dangers like terrorism and climate change (and, more remotely, an asteroid hitting the Earth). But if anything is going to kill tens of millions of people in a short time, it will probably be a global epidemic. And the disease would most likely be a form of the flu, because the flu virus spreads easily through the air. Today a flu as contagious and lethal as the 1918 one would kill nearly 33 million people in just six months.
I have been studying this for several years. To be prepared, we need a plan for national governments to work together. We need to think through how to handle quarantines, make sure supply chains will reach affected areas, decide how to involve the military, and so on. There was not much progress on these questions in 2018.
The good news is that there has been progress toward a vaccine that would protect you from every strain of the flu. This year I visited the U.S. National Institutes of Health in Maryland and got an update from some of the people leading this work.
The challenges of making a universal flu vaccine are fascinating. All strains of the virus have certain structures in common. If you’ve never been exposed to the flu, it’s possible to make a vaccine that teaches your immune system to look for those structures and attack them. But once you’ve had the flu, your body obsesses over the strain that got you sick. That makes it really hard to get your immune system to look for the common structures.
So it is clear how we could make a universal vaccine that would protect anyone (such as the very young) who has never been exposed to the flu before. But for anyone who has already had the virus, it is a lot harder. The problem is a long way from being solved, but new research money is coming in and more scientists are working on it.
To make the most of these scientific efforts (some of which our foundation is funding), the world needs to develop a global system for monitoring and responding to epidemics. That is a political matter that requires international cooperation among government leaders. This issue deserves a lot more focus.
Gene editing
Gene editing made the news in November when a Chinese scientist announced that he had altered the genes of two baby girls when they were embryos. What is unprecedented about his work is that he edited their germline cells, meaning the changes will be passed down to their children. (The other, less controversial type of gene editing involves somatic cells, which aren’t inherited by future generations.)
I agree with those who say this scientist went too far. But something good can come from his work if it encourages more people to learn and talk about gene editing. This might be the most important public debate we haven’t been having widely enough.
The ethical questions are enormous. Gene editing is generating a ton of optimism for treating and curing diseases, including some that our foundation works on (though we fund work on altering crops and insects, not humans). But the technology could make inequity worse, especially if it is available only for wealthy people.
I am surprised that these issues haven’t generated more attention from the general public. Today, artificial intelligence is the subject of vigorous debate. Gene editing deserves at least as much of the spotlight as AI.
I encourage you to read up on it whenever you have a chance. Keep an eye out for articles in your news feed. If you are willing to read a whole book, The Gene by Siddhartha Mukherjee is very well done. This story is one to follow, because big breakthroughs—some good, some worrisome—are coming.
Looking ahead
I am making a resolution for 2019.
Although I have never been one for New Year’s resolutions, I have always been committed to setting clear goals and making plans to achieve them. As I get older, these two things look more and more like the same exercise. So I am making a resolution for 2019. I am committing to learn and think about two key areas where technology has the potential to make an enormous impact on the quality of our lives, but also raises complex ethical and social considerations.
One is the balance between privacy and innovation. How can we use data to gain insights into education (like which schools do the best job of teaching low-income students) or health (like which doctors provide the best care for a reasonable price) while protecting people’s privacy?
The other is the use of technology in education. How much can software improve students’ learning? For years we have been hearing overheated claims about the huge impact that technology would have on education. People have been right to be skeptical. But I think things are finally coming together in a way that will deliver on the promises.
I will be posting updates on these and other issues on the Gates Notes.
In the meantime, Melinda and I are working on our next Annual Letter. The theme is a surprise, though it is safe to say we’ll be sharing some positive trends that make us optimistic about the future. We’ll send the letter out in February.
I hope you have a happy and healthy start to 2019.
A true data farm
Can the Wi-Fi chip in your phone help feed the world?
I recently visited an amazing farm near Seattle that uses data to grow better harvests.
I recently visited a remarkable farm in Carnation, Washington, just 25 miles from downtown Seattle.
At first glance, Dancing Crow Farm looks like any other farm. There are rows of crops and, at least when I was there, the field was dusty. There were farm implements and freshly picked peppers piled up under a lean-to. But if you talk to Sean Stratman—the man responsible for this plot—it quickly becomes clear what makes his farm so special: Sean knows more about his land than almost any other farmer on earth.
Dancing Crow Farm is the pilot site for FarmBeats, an amazing new project that hopes to make farmers more productive by arming them with data. When most people think of groundbreaking digital technology, they don’t picture soil sensors. But a farmer who knows the temperature, pH, and moisture level of his soil can make all sorts of informed decisions that save money and boost yield.
For example, fertilizer works better when it’s applied to moist soil. But how do you know when to fertilize? Soil that feels dry is often still damp below the surface. You’ll end up fertilizing more often than necessary if you go by touch alone. But if you know exactly how much moisture is in your soil at any given moment, you can fertilize only when you need to. You use less and save money.
The problem is that most existing digital platforms that provide this kind of information are expensive. Sensors can cost hundreds of dollars each, and each one only covers 10 meters. The cost is so prohibitive that only the very richest farmers can afford them.
A team of researchers at Microsoft—led by researcher Ranveer Chandra, who I talk to in the video above—wants to change that. In FarmBeats, they’ve developed a series of innovations that might one day put data in the hands of even the poorest farmers.
The main innovation is in how FarmBeats sensors transmit data. Most farms have poor or no access to the Internet. In the United States, 20 percent of people living in rural areas don’t have access to even the slowest broadband speeds. Most farm data systems require expensive transmitters to connect, but FarmBeats relies on a clever workaround: it uses TV white space.
White spaces are unused TV broadcast spectrum. If you’ve ever watched an old TV, you’ve seen white spaces before. They’re the “snow” you’ll sometimes see while flipping through channels. These gaps in spectrum are plentiful in the remote areas where most farms are located, so data can be sent over them the same way that data gets transmitted via broadband.
Here’s how FarmBeats works: The whole system is powered by solar panels. You place a small number of sensors—one every couple hundred meters, instead of 10 meters—in the ground. You then attach your smart phone with the camera facing down to either a drone (if you have money to spare) or a helium balloon (if you don’t).

You walk around the fields with the camera, creating an aerial map of the farm. Data from both the sensors and the phone are transmitted via TV white space to your computer, where an edge device stitches everything together into a data map.
The data generated by FarmBeats has been a game changer for Sean and Dancing Crow Farm. He can use up to 30 percent less water for irrigation and 44 percent less lime to control soil pH. Information on soil temperature and moisture levels has helped him better time the planting of seeds, so he gets a more productive harvest. Because Dancing Crow Farm is located next to a river, flooding is a problem. FarmBeats’ aerial imaging capabilities precisely document flooding patterns, so he’s able to better plan what he plants where. The system even helped Sean identify parts of the farms where inadequate drainage was affecting the quality of beans.
It’ll be at least a year before every component of FarmBeats is available to the public—and even longer before the cost comes down enough for broad adoption (the current version is much cheaper than other farm data systems but still too expensive for poor farmers to afford). But I’m hopeful that one day this technology could be available to every farmer everywhere, including the most remote parts of Africa.
Even as they continue working on the current version, the FarmBeats team is already working on the next generation of their technology. They just released a paper demonstrating for the first time that Wi-Fi signals can be used to collect soil data. Using only their smart phones and super cheap RFID tags buried in the ground, any farmer could get important information about their land—no special, high tech equipment required.
The Wi-Fi technology is still theoretical, but I’m glad brilliant minds are thinking about how we can help the poorest farmers gather data and increase yield. Even small gains in productivity could mean the difference between affording to send your kids to school or not. And for farmers who rely on the food they grow to feed their family—where the size of your harvest is a matter of life or death—FarmBeats could be a literal lifesaver.
More than three-quarters of the world’s poor rely on agriculture to earn a living. If we’re going to win the fight against poverty, we must help farmers—and I believe that FarmBeats could be a powerful tool.
Just the facts, Max
Memorizing these three statistics will help you understand the world
Why we should be optimistic but not complacent.
One of my favorite websites is OurWorldInData.org. Based at the University of Oxford, it uses statistics—on everything from health and population growth to war, the environment, and energy—to give you phenomenal insight into how living conditions are changing around the world. I asked its founder, Oxford economist Max Roser, to share three facts from the site that everyone should know. Here’s what Max had to say. – Bill Gates
In the past few years, it has become easy to find many of the important statistics on global development with a quick online search. And since it is now so easy to find the information you need, many argue that it doesn’t make sense to actually remember these statistics. ‘Just look them up when you need them!’ they say.
I disagree with this. Yes, for some details, it makes sense to just search for them when you need them. But for the large global developments, it is important to know some basic statistics that describe living conditions currently and the direction of change that we have seen over the past few decades. Knowing the facts on global changes gives you the context for the daily news and allows you to make sense of new information that you learn. And it must be the basis for political debate, so that we can discuss what we should and shouldn’t do as a society.
And so I compiled a short list of three facts about global living conditions that I want to remember. Each of them describes the current situation and the direction of change.
Fact #1: Since 1960, child deaths have plummeted from 20 million a year to 6 million a year.
Imagine how awful it must be to see your child die.
Then consider that every minute this happens to about 11 parents. This is the number of children, younger than five years of age, who die—on average—every single minute. Eleven deaths every minute for 24 hours add up to 15,500 deaths per day, or 5.6 million deaths per year.
Do we just have to accept that? Is that just how the world is?
Clearly no. We are very much able to drive positive change. Look at the chart below. The same UN data that shows us that 5.6 million are dying today also shows us that in the 1950s and 60s the world saw around 20 million children dying every year.
One key reason why we struggle to see progress in the world today is that we do not know how very bad the past was.
Both are true at the same time: The world is much better than in the past and it is still awful.
To bring this to mind I need to know both statistics: When someone says we can sit back and relax because the world is in a much better place, I point out that 11 children are still dying every minute. We cannot accept the world as it is today. And when I feel hopeless in the face of this tragedy, I remember that we reduced annual child deaths from 20 million to 5.6 million in the last fifty years.
So I am remembering the current extent of child mortality and the direction of change that we have seen: The number of child deaths is falling; there were 3.5-times as many child deaths 50 years ago. But child deaths are still extremely common; 11 children are dying every minute.
Fact #2: Since 1960, the fertility rate has fallen by half.
The chart below shows the key statistic to understand about world population growth: the global fertility rate—the average number of children per woman in the world. When the fertility rate is close to 2 children per woman, so that every couple is on average replaced by about two children, population growth is slow. But until the late 1960s, each woman had on average more than 5 children, and at such high fertility rates, population growth is fast. At that time the world population increased by 2 percent every year.
The availability of contraceptives allows parents to have only as many children as they want. And that number changes as people’s income goes up. From decades of demographic research, we know that women decide to have fewer children as they get access to better education and better opportunities in the job market. We also know that when child mortality falls, so that families do not need to fear that their children will die, they consequently decide to have fewer children in the first place.
Improvements in conditions for women and the health of children have driven a rapid reduction in fertility rates across the world. In fact, the global fertility rate has halved in the last 50 years, from more than 5 children per woman to fewer than 2.5 children. The world population growth rate has also halved in the last 50 years and is just above 1 percent.
The statistic that I remember on population growth is the one that tells me that rapid population growth is coming to an end in this century. In the last 50 years the global fertility rate has fallen from 5 children per woman to less than 2.5 children per woman. In fifty years the fertility rate has halved.
Fact #3: 137,000 people escaped extreme poverty every day between 1990 and 2015.
Living in poverty means that many of the most essential things in life are out of reach. People in poverty tend to lack decent shelter and basic healthcare, and they often struggle to afford adequate food supplies.
People are considered to live in ‘extreme poverty’ if they have to get by on less than 1.90 international-dollars per day, which is a currency that corrects for price differences between countries and inflation.
In this definition of poverty, the term extreme poverty is clearly appropriate: this is a very low poverty line.
When you ask people whether the world is making progress against extreme poverty, the majority of us believe things are getting worse—that the number of people in extreme poverty in the world is rising.
The opposite is true. Both the number and the share of people in extreme poverty is falling:
In 1990, 1.86 billion people were living on less than 1.90 international-$ per day—more than every third person in the world. Twenty-five years later, the number of people living in extreme poverty has more than halved to 706 million, every tenth person.
This is a very large transformation. It means that, on average, every day for the past 25 years 137,000 fewer people were living in extreme poverty than the day before. On every day in the last 25 years there could have been a newspaper headline reading, “The number of people in extreme poverty fell by 137,000 since yesterday.”
This is the statistic I remember: Today every 10th person is living in extreme poverty—706 million people. An unacceptably large number of people. But we should also know that the trend is moving in the right direction. The number of people in extreme poverty is falling. It is possible to end extreme poverty.
Remembering these facts about the world brings to mind why I think it is important to get engaged in global development. The statistics on the current state of the world make clear that we cannot be complacent about the world as it is today. Especially because progress is uneven, and in sub-Saharan Africa progress has been slower, but is not absent. The statistics on global change over time tell us that it is possible to work for a better world. The number of child deaths is dropping. The challenges of rapid population growth will not continue indefinitely. And the number of people in extreme poverty is falling.
Let’s continue in this direction. Our past successes should encourage us to work for more progress.
Lifesavers
What kangaroos can teach us about saving lives
A simple, low-cost intervention can have a huge impact on newborn health.
I write a lot about new inventions that are improving people’s health and saving lives around the world. But some breakthrough ideas don’t involve any new technology at all. Let me tell you about one of my favorite examples—a solution that is readily available, requires no special equipment, and is so cheap any government can support it.
It’s called kangaroo mother care—continuous skin-to-skin contact between mothers and low-birth weight or premature babies. Combined with exclusive breastfeeding, this practice prevents neonatal deaths by regulating the baby’s temperature, accelerating weight gain, and reducing the risk of infections. What’s more, it encourages mother-infant bonding at a critical time of the child’s development.
Two Colombian pediatricians, Edgar Rey and Hector Martinez, developed kangaroo mother care in the 1970s. The doctors were struggling to care for preterm infants in Bogota, where few incubators were available. Looking for a solution, they drew inspiration from how kangaroos care for their young. Baby kangaroos, born the size of a lima bean, develop inside the pouch on their mother’s belly where they can feed and stay warm.
Years later, study after study has proven the benefits of skin-to-skin contact between mothers and their newborns. For preterm babies, it’s even better than warming them in an incubator. And even as new lifesaving technologies are introduced to facilities to support newborns, kangaroo mother care is an opportunity to keep mothers at the center of their baby’s care.
When kangaroo care has been adopted on a national scale, the impact is truly remarkable. Rwanda, for example, cut its newborn mortality rate by 30 percent between 2008 and 2015, largely due to the spread of kangaroo mother care along with encouraging exclusive breastfeeding and cutting the umbilical cord in a hygienic way.
Surprisingly, despite its clear benefits, kangaroo mother care is not practiced widely. But it should be. Every year, about 2.7 million newborns die during their first month of life. The majority of newborn deaths occur in parts of the world where there are no hospitals or clinics nearby, and no access to skilled birth attendants.
Many of these lives could be saved with simple, affordable health interventions like kangaroo mother care. Our foundation, along with many other organizations, have been working to spread the word about kangaroo mother care with policymakers and health officials so more parents can be trained to use this lifesaving practice.
If you need another reason to be convinced of the power of kangaroo mother care: A recent study found that this practice is a gift that keeps on giving. Kangaroo mother care had “significant, long-lasting social and behavioral protective effects” on children as they entered young adulthood. Parents who practiced kangaroo mother care were more protective and nurturing, and their children were less likely to miss school and less likely to be aggressive or hyperactive. These positive effects were still present in the children 20 years later! Now that’s a smart investment in our children’s future.
Business boost
Giving foreign aid helps America’s economy
Investing in the health of the world’s poor is good for U.S. companies
I’m a big fan of America’s investments in the health and well-being of the world’s poor. Unfortunately, not everyone feels the same way. In fact, some in Washington D.C. have proposed dramatic cuts in foreign assistance.
That would be a terrible mistake. Last month I wrote about how foreign aid helps keep Americans safe. In this post, I want to show how smart health and development programs promote America’s economy, and how cutting back on these investments could backfire on American workers.
(As I said in my previous post, these security and economic arguments aren’t what inspired Melinda and me to get involved in global health. What inspired us was the chance to save children from dying of preventable diseases. But over the years I’ve come to see the connection to America’s security and economy as well.)
I start from the simple premise that everyone is better off when there are more middle-income countries in the world. As a country climbs up the economic ladder, you see concrete improvements in the lives of its people. Richer countries are less likely to go to war and more capable of preventing global epidemics. And they can afford to buy more products from other countries, including the United States.
Here’s one example from my experience with Microsoft. From our earliest days, we intended to expand into markets beyond the United States. In 1986, we chose Tokyo for the site of our first foreign office. That bet paid off phenomenally well. For a time, we sold more software in Japan than anywhere else.
You may be thinking, “Of course an ambitious software company would want a foothold in Japan.” But it wasn’t always so obvious. Just a few decades before we opened our Tokyo office, Japan had been devastated by World War II. Its economy and infrastructure lay in ruins. How did they recover? Among other things, through smart aid programs from the United States and others. By the 1980s Japan’s economy was booming, and the country presented a great opportunity for companies like us. To this day, sales there are a key part of Microsoft’s success and these sales have produced many jobs in Japan and America alike.
Microsoft’s experience in Japan is part of a larger trend that’s still going on today, as more countries join the ranks of the middle class. Countless U.S. companies are doing business in places that used to get American aid but have become self-sufficient, including South Korea, Brazil, Mexico, Vietnam, and Thailand.
Here’s another way that U.S. investments abroad help American businesses: by connecting them directly with new customers and suppliers. America’s chief aid agency, USAID, uses its expertise to encourage private companies to collaborate on projects. For example, they have worked with Cargill and Land O’Lakes to help dairy farmers in East Africa raise their productivity, increasing the value of the companies’ exports to places like Kenya and Uganda. As the companies’ CEOs wrote, “This benefits not only the farmers in Africa, but food producers and their workers in the United States and it promotes goodwill in a part of the world that can be a market for more American goods in the future.” USAID has also worked with Walmart to train thousands of women farmers in sub-Saharan Africa, and with Starbucks, Keurig, and others to help coffee farmers in Latin America improve their crops so they can join the global market.
These and other efforts are part of America’s global economic leadership. Pulling back now would mean retreating from the world stage at a time when other countries are doubling down on their investments. It would deprive American companies of potential new markets and make them less competitive, while also harming the health and productivity of some of the poorest people in the world. It wouldn’t be robbing Peter to pay Paul; it would be robbing Peter and then robbing Paul too.
So it’s good for the American economy when other countries join the middle class. But how much credit does aid deserve for making that happen?
It’s a hard question to answer; growth has many causes. My own conclusion, based on years of looking at the evidence and discussing it with experts, is that although aid may not directly cause growth, there is a strong indirect connection between the two. Moving to the middle class requires a strong education system and good infrastructure, nutrition, and healthcare—and smart, targeted aid can promote those things pretty effectively.
Fighting AIDS, for example, saves lives, and it increases productivity because societies are stronger when they have healthy teachers, police officers, and entrepreneurs. Countries that worked with PEPFAR—America’s phenomenally successful effort to slow the AIDS epidemic—improved three times more on one measure of economic development than their non-PEPFAR counterparts.
Their per-capita income also grew quickly. Between 2005 and 2015, for example, Tanzania’s per-person income went up more than 37 percent. Zambia’s went up 55 percent. Ethiopia’s rose 107 percent. And as these countries grew, so did their appetite for American goods. In the same time frame, U.S. exports to Tanzania rose by more than 77 percent, U.S. exports to Zambia went up 189 percent, and to Ethiopia, 241 percent.
Many other countries are making similar gains. The point is not that aid directly makes poor people richer. It’s that aid helps create a foundation for growth. Along with many other factors, it helps remove some of the barriers that keep people from making the most of their talents. And when people in one place do better, the rest of us do better too.
We can build on this progress if the United States helps maintain the momentum. Investments in aid—which account for less than 1 percent of the federal budget—are an essential part of the solution. We need to keep making them on behalf of Americans and people around the world.

Endgame
Let’s make this the last pandemic
My new book is all about how we eliminate the pandemic as a threat to humanity.
The great epidemiologist Larry Brilliant once said that “outbreaks are inevitable, but pandemics are optional.” I thought about this quote and what it reveals about the COVID-19 pandemic often while I was working on my new book.
On the one hand, it’s disheartening to imagine how much loss and suffering could’ve been avoided if we’d only made better choices. We are now more than two years into the pandemic. The world did not prioritize global health until it was too late, and the result has been catastrophic. Countries failed to prepare for pandemics, rich countries reduced funding for R&D, and most governments failed to strengthen their health systems. Although we’re finally reaching the light at the end of the tunnel, COVID still kills several thousand people every day.
On the other hand, Dr. Brilliant’s quote makes me feel hopeful. No one wants to live through this again—and we don’t have to. Outbreaks are inevitable, but pandemics are optional. The world doesn’t need to live in fear of the next pandemic. If we make key investments that benefit everyone, COVID-19 could be the last pandemic ever.
This idea is what my book, How to Prevent the Next Pandemic , is all about. I’ve been part of the effort to stop COVID since the early days of the outbreak, working together with experts from inside and out of the Gates Foundation who have been fighting infectious diseases for decades. I’m excited to share what I've learned along the way, because our experience with COVID gives us a clear pathway for how to be ready next time.
So, how do we do it? In my book, I explain the steps we need to take to get ready. Together, they add up to a plan for eliminating the pandemic as a threat to humanity. These steps—alongside the remarkable progress we’ve already made over the last two years in creating new tools and understanding infectious diseases—will reduce the chance that anyone has to live through another COVID.
Imagine a scenario like this: A concerning outbreak is rapidly identified by local public health agencies, which function effectively in even the world’s poorest countries. Anything out of the ordinary is shared with scientists for study, and the information is uploaded to a global database monitored by a dedicated team.
If a threat is detected, governments sound the alarm and initiate public recommendations for travel, social distancing, and emergency planning. They start using the blunt tools that are already on hand, such as quarantines, antivirals that protect against almost any strain, and tests that can be performed anywhere.
If this isn’t sufficient, then the world’s innovators immediately get to work developing new tests, treatments, and vaccines. Diagnostics in particular ramp up extremely fast so that large numbers of people can be tested in a short time. New drugs and vaccines are approved quickly, because we’ve agreed ahead of time on how to run trials safely and share the results. Once they’re ready to go into production, manufacturing gears up right away because factories are already in place and approved.
No one gets left behind, because we’ve already worked out how to rapidly make enough vaccines for everyone. Everything gets where it’s supposed to, when it’s supposed to, because we’ve set up systems to get products delivered all the way to the patient. Communications about the situation are clear and avoid panic.
And this all happens quickly. The goal is to contain outbreaks within the first 100 days before they ever have the chance to spread around the world. If we had stopped the COVID pandemic before 100 days, we could’ve saved over 98 percent of the lives lost.
I hope people who read the book come away with a sense that ending the threat of pandemics forever is a realistic, achievable, and essential goal. I believe this is something that everyone—whether you’re an epidemiologist, a policymaker, or just someone who’s exhausted from the last two years–should care about.
The best part is we have an opportunity to not just stop things from getting worse but to make them better. Even when we’re not facing an active outbreak, the steps we can take to prevent the next pandemic will also make people healthier, save lives, and shrink the health gap between the rich and the poor. The tools that stop an outbreak can also help us find and treat more HIV cases. They can protect more children from deadly diseases like malaria, and they can give more people around the world access to high quality care.
Shrinking the health gap was the life’s work of my friend Paul Farmer, who tragically died in his sleep in February. That’s why I’m dedicating my proceeds from this book to his organization Partners in Health, which provides amazing health care to people in some of the poorest countries in the world. I will miss Paul deeply, but I am comforted by the knowledge that his influence will be felt for decades to come.
If there’s one thing the world has learned over the last two years, it’s that we can’t keep living with the threat of another variant—or another pathogen—hanging over our heads. This is a pivotal moment. There is more momentum than ever before to stop pandemics forever. No one who lived through COVID will ever forget it. Just like a war can change the way a generation looks at the world, COVID has changed the way we see the world.
Although it may not always feel like it, we have made tremendous progress over the last two years. New tools will let us respond faster next time, and new capabilities have made us better prepared to fight deadly pathogens. The world wasn’t ready for COVID, but we can choose to be ready next time.
Everyone, everywhere
Vaccinate the world in six months
To prevent pandemics, we need to be able to do it. Here’s how.
The greatest medical breakthrough of this pandemic—and surely one of the most important in decades—is the creation of COVID-19 vaccines. One study found that in their first year, they saved more than 1 million lives and prevented 10 million hospitalizations in the U.S. alone. The number of deaths averted around the world is of course far higher. It’s horrifying to think what COVID-19 would be doing to humanity if it weren’t for vaccines.
The world has a lot to be proud of in the creation and delivery of these vaccines. Scientists have never developed one nearly as quickly as they did in 2020, and the governments of the world have never run immunization campaigns that were as fast and as far-reaching as the ones that took place in 2021.
But there are also serious problems that we need to solve before the next potential pandemic comes along. One is the huge inequity in who has been vaccinated and who has not. It is both unjust and unwise to give a third shot to a healthy 25-year-old in a rich country before a 75-year-old cancer survivor in a poor country gets her first shot.
Another concern is that the speed with which vaccines were created was only partly a matter of skill and diligence. It was also a matter of luck.
Because coronaviruses had already caused two previous outbreaks (SARS and MERS), scientists had learned quite a lot about the structure of the virus. In particular, they had identified its characteristic spike protein—the tips on the crownlike virus you’ve seen a dozen pictures of—as a potential target for vaccines. When it came time to create new vaccines, they had a sense of what part of the virus was most vulnerable to attack.
In the next outbreak, we may not be so lucky. It could be caused by a virus that scientists haven’t studied as closely, or by one they’ve never seen at all.
This is why the world needs to adopt a serious plan for developing, manufacturing, and distributing new vaccines to prevent another pandemic. The manufacturing alone is a huge challenge: To prevent the inequities we’ve seen in COVID-19, the world needs to be ready to produce enough vaccines for everyone on the planet within six months of discovering a new pathogen. That’s 8 billion doses for a single-dose vaccine, and 16 billion for a two-dose version. In a typical year, around 5 billion or 6 billion doses are produced—that’s all vaccines combined.
The plan needs to cover four steps, starting with accelerating the invention of new vaccines.
During the pandemic, the process of creating a new vaccine got a huge boost (no pun intended). Typically, the process involves a lot of trial and error: Scientists spend years identifying weak spots in the virus and trying to identify vaccine candidates that would teach the immune system to attack them.
The creation of the first mRNA vaccines during the COVID-19 pandemic was a big step forward. They work by delivering genetic code to your body that instructs it to make shapes that look like the weak part of the virus. Your immune system notices that those shapes are foreign and sets out to attack them. Once it does, it remembers what the shapes looked like and will attack them the next time they show up. That’s what makes you immune.
One reason mRNA vaccines were so revolutionary is that they’re easily adapted for different pathogens. Once the weak spot of a virus has been identified—a process made much easier by recent advances in mapping viral genomes—it’s simply a matter of changing the genetic code in the vaccine so that it tells your body to make a new shape. This can be done in a matter of days.
As a result, the development of new vaccines will be exponentially faster—as long as researchers have the same deep understanding of future pathogens as they did of coronaviruses. So it is imperative to invest in basic research on a wider array of known viruses and other pathogens, so we understand as much as possible before the next outbreak.
Once a vaccine has been invented, the second step is to test it and get it approved for use in humans. Typically, it takes years to run all the trials necessary to prove that a vaccine is safe and effective—including time spent recruiting tens of thousands of volunteers. Assuming the vaccine proves out, it can take another year to get it authorized by the WHO and the relevant government agencies.
But when an outbreak is threatening to go global, we won’t have years. So we need ways to speed up the process without sacrificing the safety and effectiveness that people have come to expect from vaccines.
The world should build on models like the RECOVERY trial in the U.K. It set up protocols for running drug trials in advance and built infrastructure that made it much easier to get started once COVID hit. In addition, the agencies that regulate vaccines need to agree ahead of time on how volunteers will be enrolled in trials and on the software tools that will enable people around the world to sign up as soon as the disease strikes. And by connecting diagnostic tests to the trial system, we can automatically suggest to doctors that their patients should join a trial if they’re eligible.
The third step, once a vaccine has been approved for use in humans, is to make enough of it fast enough to stop the outbreak. Ending a relatively small outbreak might require hundreds of thousands of doses of a new vaccine, which is not hard to make. (The world already produces more than 5 billion doses of vaccines every year.) But countries need to be prepared for the worst—another big outbreak in which everyone needs to be vaccinated—so we must be ready to produce as many as 8 billion or even 16 billion, roughly triple the amount manufactured in a typical year.
During COVID-19, the closest thing to a breakthrough in manufacturing vaccines was the proliferation of second-source deals. These are agreements in which a company that invented a vaccine agrees to let other companies use their factories to make it. (Picture Honda Accords rolling off the line of a Ford facility.)
It’s hard to overstate the impact of second-source deals during COVID-19. In less than two years, a single manufacturer, AstraZeneca, signed second-source deals involving 25 factories in 15 countries. (AZ also agreed to forgo its profits on the COVID vaccine.) Novavax also signed one with Serum Institute of India—leading to a COVID-19 vaccine now being used in many countries—and Johnson & Johnson signed one with the Indian company Biological E. Limited and the South African firm Aspen Pharmacare. All told, second-source deals led to the production of billions of additional COVID vaccine doses.
In the future, such deals could be done even faster if companies that have them now can maintain their relationships with one another so they can hit the ground running during the next outbreak.
mRNA vaccines could also help speed up manufacturing. Many of the conventional ways to make vaccines are quite complex, so it can take a lot of time to transfer the technology and know-how from one company to another. But because the basic approach to mRNA is pretty much the same—you just swap out your old mRNA for the new one and make sure the lipid is made the right way—it should be easier to transfer between companies. There are also some new modular technologies in the pipeline that, if they prove out, will make it cheaper and easier to build and run factories that can be adapted to make different vaccines.
Finally, the fourth step in the world’s plan should be to make sure that new vaccines reach everyone who needs them—including people who live in low-income countries. In 2021, only 8 percent of people in those countries received at least one dose of a COVID-19 vaccine, while more than half of the world’s population did.
So how can the world make sure that doesn’t happen in future outbreaks?
One key is to take on the problem of vaccine hesitancy. Check out this video about how, by dealing with rumors and myths, one community in India increased its COVID-19 vaccination rate by a factor of five and created a model that other communities are now taking up:
Another key is to make sure it’s possible to manufacture enough vaccines that supply is not a limiting factor, as it was during much of 2021. Another is to make sure that vaccines are affordable for every country. Organizations like COVAX have helped with that during COVID-19. It also helps to work with manufacturers in developing countries to design new vaccines that are much cheaper to produce than existing ones. This is how the price of the pentavalent vaccine, which protects against five debilitating and deadly diseases, dropped from $3.50 per dose to less than $1 a dose—which in turn allowed the number of children who get it every year to increase by more than 16 times since 2005.
There are also a lot of innovations that make it easier to deliver vaccines. For example, auto-disable syringes have a built-in safety mechanism so health workers can’t accidentally poke themselves or use them more than once. New coolers can keep vaccines at the right temperature for longer. Advanced methods for delivering vaccines, such as replacing the needle and syringe with a small patch containing micro-needles—picture something that looks superficially like the nicotine patches that people use to stop smoking—will also help.
With these advances, it will be possible to achieve something amazing beyond preventing pandemics: eradicating entire families of pathogens. The world could rid itself of all coronaviruses, for example, or even all influenza viruses. A future without pandemics—and without the flu—is worth investing in.

A plan for the world
3 things we can do right now
If we’re going to make COVID-19 the last pandemic, the world needs to get to work right away on these key areas.
When I sat down to write my new book, my goal was to create a concrete list of steps the world could take to prevent the next pandemic. There’s a lot we can and should learn from COVID-19. But I knew that I wanted to focus more on the future instead of the past.
For decades, people told the world to get ready for a pandemic, but hardly anyone made it a priority. Then COVID struck, and stopping it became the most important thing on the global agenda. Governments need to take action now to get ready for the next pathogen, while all of us still remember how awful COVID was (and still is) and feel the urgency of never allowing another one to happen.
If we’re going to make COVID-19 the last pandemic, the world needs to get to work right away on three key areas:
1.
Make and deliver better tools.
The story of Katalin Kariko and mRNA vaccines proves that ideas for new tools must often be nurtured and researched, sometimes for decades, before they produce anything of practical value. That’s why step one in any pandemic-prevention plan should be to keep investing in better vaccines, therapeutics, and diagnostics.
You can read more about how new vaccines can be developed and delivered faster here. This includes improving our ability to test and approve new products, as well as scaling up manufacturing capacity and creating better way of delivering vaccines (like microneedle patches) so we can get out lots of doses fast.
On the therapeutics front, it took nearly two years to find effective treatments for COVID. The trajectory of the pandemic would’ve looked a lot different if we had found them sooner. We need to build out the systems that will allow us to make new treatments much faster in the future.
One key step is to create a library of antiviral compounds that are designed to attack common respiratory viruses, so that we can more easily find out if an existing drug will work in the event of an outbreak. We can also take advantage of advances in artificial intelligence and other computational methods. A computer could quickly scan a 3D model of a pathogen to figure out which drugs might be effective against it. It would be able to tell you which drugs look promising, figure out how to improve them, and, if necessary, even design new ones from scratch.
We should also expand incentives for generics manufacturers to create low-cost versions of new drugs. This can be achieved through advance orders on behalf of low- and middle-income countries, which get generic drugmakers to start manufacturing a new drug through advance orders and agreements that allow one company to manufacture a drug invented by another company even while it’s still going through regulatory approvals.
Another area where we need to spark more innovation is in diagnostics. Researchers should keep working on—and funders should keep supporting—high-throughput PCR tests, which have all the benefits of a PCR but are significantly faster at returning results, much cheaper to run, and easier to adapt to a new pathogen. We also need to support work on new types of tests that make it easier to collect samples and turn around results quickly, like better versions of the rapid antigen tests that many of us now take at home for COVID or even handheld devices that health workers can use to easily test people in their community. And testing should be tied to treatment, so if you test positive, you get the medication you need right away.
2.
Improve disease monitoring.
Creating the GERM—Global Epidemic Response and Mobilization—team is one of the most important steps we can take to stop the next pandemic. GERM will play a crucial role in virtually every aspect of pandemic prevention, but improving monitoring will be the most significant part of their mandate.
GERM is only one piece of the puzzle, though. Another crucial step is to improve civil registration and vital statistics in the developing world. At a minimum, many low- and middle-income countries need stronger registries of births and deaths, so that GERM can work with local organizations to more easily spot if there’s an unusual pattern worth investigating. Then, building on that foundation, countries should expand into autopsies that use minimally invasive tissue samplings, wastewater surveillance, and other practices.
The world’s disparate disease monitoring systems also need to be integrated so that public health officials can rapidly detect pathogens. Data must be made available in real time, with test results integrated into the public health system so that officials can watch for outbreaks. And in countries like the United States, where testing can be extremely expensive, governments need to make diagnostics cheaper and more accessible to everyone.
Finally, we need to expand our capacity to sequence the genomes of pathogens in order to track new variants. We should double down on investments in projects like the Africa Pathogen Genomics Initiative, a network of labs across the continent that share genomic data with each other, and in new tools that will let us sequence more genomes in more places.
3.
Strengthen health systems.
Good health care starts with good health systems. That’s true for basic care, and it’s especially true for pandemic prevention. When a new or deadly pathogen emerges, you need somewhere for sick people to reliably seek treatment. You need health workers who can identify potential threats and the infrastructure to report anything out of the ordinary. And, once a pathogen starts to spread, you need trained professionals who can administer higher level tests, treatments, vaccines, and more.
The pandemic devastated health systems around the world, but the need in low-income countries is especially acute. The fundamental challenge is that they don’t have the funding, expert capacity, or institutions they need to offer basic health services to all their people, let alone manage a major outbreak. And during the pandemic, the problem got worse, as many rich governments cut foreign aid or took money from work on other diseases and redirected it to COVID.
We need to reverse this trend. A major part of the Gates Foundation’s work has been to help improve health systems—investments that both save lives, end preventable infectious diseases, and pave the way for economic growth. But philanthropy alone cannot close the gap between rich and poor countries. The models for wealthy countries are still Sweden and Norway, who each give at least 0.7 of their GDP in aid. If we’re going to be serious about preventing the next pandemic, we need to not just go back to pre-COVID aid levels but increase investments in strengthening health systems (which will also help shrink the overall health gap between the rich and the poor).
For their part, low- and middle-income countries should focus on health spending that achieves many things at once. For example, hiring more health workers gives you more people who can manage malaria cases, offer HIV testing and treatment, and give public officials unprecedented insight into what’s causing illness and death in their country.
But as COVID made clear, low- and middle-income countries aren’t the only ones that need to strengthen their health systems. There are steps that countries at every income level should consider, like improving primary health care and deciding in advance of a crisis who will oversee what. Governments and donors also need a global forum where they can coordinate action with poor countries.
All of these efforts—new tools, better disease surveillance, and improved health systems—won’t be cheap, but they will save lives and money in the long run. I estimate that, over the next decade, governments combined need to spend $15 to $20 billion per year to develop the tools we need. Strengthening health system will cost the world an extra $30 billion a year, on top of the money we should already be spending to improve health in low income countries.
That sounds like a lot of money until you learn that the International Monetary Fund estimates this pandemic will cost $12.5 trillion over just five years. Think of it like insurance. This is the billions we need to spend in order to save millions of lives and trillions of dollars.
And here’s the best news: Even when we’re not facing an active outbreak, these investments will make people healthier, save lives, and shrink the health gap between the rich and the poor. This is an opportunity to not just stop things from getting worse but to make them better.
We don’t need to surrender to living in perpetual fear of another global catastrophe. But we do need to remain aware of the possibility and be willing to do something about it. I hope the world seizes this moment and invests in the steps needed to make COVID-19 the last pandemic.

The outbreak squad
Meet the GERM team
Creating the GERM team is one of the most important things we can do to prevent the next pandemic.
At the beginning of the movie Outbreak, there’s a scene where three government virologists arrive by helicopter at a remote village. Most of the village has recently died from Ebola-like symptoms. Wearing protective moon suits while triumphant music plays in the background, our heroes immediately get to work trying to contain the threat before it hurts anyone else. It’s an inspiring scene.
Unfortunately, it’s pure Hollywood fiction.
A full-time team like this doesn’t exist in real life—yet. I’m hoping this changes soon, because it is one of the most important things we can do to prevent the next pandemic.
Today, there are many organizations that work hard to respond to a major epidemic, but their efforts are largely dependent on volunteers. The best known is the Global Outbreak Alert and Response Network, or GOARN, which does heroic work but doesn’t have the staffing, funding, or global mandate to tackle every threat.
We need a permanent organization of experts who are fully paid and prepared to mount a coordinated response to a dangerous outbreak at any time. In my book, I propose that we call this group the GERM—Global Epidemic Response and Mobilization—team.
The GERM team would be made up of people from all over the world who have a wide range of expertise: epidemiology, genetics, data systems, diplomacy, rapid response, logistics, computer modeling, communications, and more. When they aren’t actively working in the field, most of them would call individual countries’ public health agencies home base, though some would sit in the WHO’s regional offices and at its headquarters in Geneva. (I talked about GERM at length in my TED talk last month.)
It's important that GERM have a diverse workforce. The team is going to serve the entire world—it only makes sense that its members reflect the experiences and backgrounds of the people they’re going to work with. Ideally, GERM would have a high number of local experts from countries at a higher risk of outbreak, and outsiders would only show up when necessary and when the in-country team requests help.
Here’s how a GERM response would work: The team’s disease monitoring experts would look for potential outbreaks. Once it spots one, GERM should have the ability to declare an outbreak and work with national governments and the World Bank to raise money for the response very quickly. Product-development experts would advise governments and companies on the highest-priority drugs and vaccines. People who understand computer modeling would coordinate the work of modelers around the world. And the team would help create and coordinate responses, such as how and when to implement border closures and recommend mask use.
But GERM’s response to an active outbreak is only one part of their work.
The team’s most important job is helping to run outbreak response exercises that test whether the world is ready for the next major outbreak. Militaries regularly run war games to evaluate their readiness—we should do the same with disease threats. In most countries, these exercises can be run by local public health and military leaders, with GERM acting as an advisor and reviewer. For some low-income countries, the world should invest in building this capacity and lend resources as needed.
You can learn more about what these germ games would look like by reading chapter 7 of How to Prevent the Next Pandemic, which is available as a free download for all Gates Notes Insiders.
The GERM team would also be responsible for developing a checklist for pandemic preparedness, similar to the ones that airplane pilots follow before every takeoff and many surgeons now use during an operation. A checklist sounds like such an obvious tool, but very few places had a plan like this in place when COVID hit. A GERM-developed checklist could be used anywhere and help make sure that governments are ready with an efficient and effective response.
But GERM’s impact won’t be limited to stopping pandemics. The group will improve overall health around the world, especially in the poorest countries.
Emerging diseases will always be their top priority, but when there isn’t an active pandemic threat, the team will keep their skills sharp by helping out with deadly diseases like polio and malaria. For example, they could work alongside public health workers in Nigeria to help distribute millions of doses of the oral polio vaccine every year to keep the country polio-free. This would both save a lot of kids from needless suffering and help the GERM team build relationships with communities they will need if an outbreak strikes. Now that’s what I call getting your money’s worth!
Running GERM will cost the world around $1 billion a year to cover salaries for the force of 3,000 people we’d need, plus equipment, travel, and other expenses—money that would come from governments. The work would be coordinated by the WHO, the only group that can give it global credibility, and it needs to be accountable to the public.
When Hollywood gets something wrong, the result is usually pretty silly and unrealistic. But movies like Outbreak nailed it when they imagined a global disease-fighting team who is ready to respond to a crisis on a moment’s notice. If we’re going to make sure that COVID-19 is the last pandemic, we need the GERM team.

Pathogen prevention
In Africa, detecting disease outbreaks before they become a global threat
Using genomic sequencing technologies, this hero is working to prevent the next pandemic.
While promoting my new pandemic book the last month, I’ve been telling audiences and interviewers that if we want to make COVID-19 the last pandemic, we need to combat infectious diseases the same way we fight fires.
Just like we have a robust system of fire alarms, firefighters, and fire hydrants to help detect and extinguish fires, we need to create an equally effective system to identify and respond to new disease outbreaks.
This firefighting comparison is also a useful way to understand the amazing work of Sofonias Tessema.
Officially, Sofonias is the program lead for the Africa Pathogen Genomics Initiative at the Africa Centers for Disease Control and Prevention or Africa CDC. But in firefighting terms you might think of him as a fire safety officer who is building a network of fire watchtowers and smoke detectors across Africa.
Instead of looking out for the first signs of a fire before it can spread, however, Sofonias is focused on quickly detecting deadly pathogens before they can grow into a global threat. And instead of using watchtowers and smoke detectors, he relies on powerful genomic sequencing technologies to spot disease outbreaks.
Genomic sequencing allows scientists to read the DNA and RNA of pathogens and understand what they are, how they spread from one person to another, and develop counter measures like vaccines. During COVID-19, this technology has been an invaluable tool for identifying new variants, tracking the evolution and spread of the virus, and guiding public health responses.
Advances in this technology have made it easier, faster, and cheaper to do genomic surveillance. Over the last two decades, the price of sequencing a full human genome has fallen dramatically. And one company, Oxford-Nanopore, has even developed a portable gene sequencer that can be operated with a laptop and no need for a lab, allowing health officials to conduct genetic testing in remote areas where outbreaks may occur.
As powerful as genomic sequencing technologies have become, many countries have not taken full advantage of them. Building genomic disease surveillance capacity presents challenges because it requires investments in labs, expensive equipment, and specially trained personnel. While the COVID-19 pandemic has sparked new interest in using genomic sequencing to improve disease surveillance, many parts of the world are still working to strengthen their capacity to use this critical technology.
In 2019, Sofonias joined the Africa CDC to establish a continent-wide genomic disease surveillance network. One of Sofonias’s first projects was to conduct an assessment to understand how many African nations were prepared to use this technology.
The results, Sofonias said, were shocking.
Of the African Union’s 55 member states, just seven had public health institutions with trained personnel and equipment to do genetic sequencing.
Given the scale of the job before them, Sofonias and his team had planned for a phased approach to help African nations build genomic surveillance capabilities. They had to acquire the technology, hire and train the technicians to operate them, and create the data systems so governments can analyze and share the genetic information and use it to inform public health decisions. Building this system would take time.
But the Africa CDC soon learned that time was a luxury they didn’t have. Within weeks of Sofonias joining the Africa CDC, the first cases of COVID-19 were detected in China. And two months later, the first cases were identified in African countries.
It’s hard to overstate the challenge before Sofonias and the Africa CDC. While genomic surveillance had been used during Ebola, Lassa fever, and cholera outbreaks, bringing this technology to scale posed many challenges in Africa, where many countries did not have the infrastructure or trained personnel to run these labs.
But this was just the kind of challenge Sofonias had always been eager to take on.
Born in Ethiopia, Sofonias grew up in a rural town where malaria was always a major threat. Seeing people die and suffer from the mosquito-borne disease got him interested in a career in public health. He earned a PhD in malaria genomics, an emerging field of research that uses genetic data of the malaria parasite to advance malaria eradication efforts. After graduate school, he was working as postdoctoral fellow at the University of California in San Francisco, where he was focused on how genomic data combined with mobile phone data could help researchers understand how malaria spreads from one country to another.
In 2019, when a call came from the Africa CDC asking if he would use his knowledge of genomic surveillance technologies to help Africa, he jumped at the opportunity. Sofonias saw the untapped potential of this new technology to make more informed public health decisions in Africa. And after years living abroad, he was also excited to return home to Ethiopia, where the Africa CDC is based.
Sofonias and his team scrambled to quickly build up Africa’s capacity to do genomic disease surveillance. The Africa CDC focused first on scaling up COVID-19 testing capabilities. At the beginning of the pandemic, only two African nations had the ability to perform PCR COVID tests, highly accurate tests that detect genetic material from the virus.
At the same time, his team worked to acquire next-generation sequencing technologies (NGS) for Africa. NGS technologies offer a more efficient, accurate, and cheaper way for researchers to track the slightest genetic changes in pathogens which may cause disease outbreaks. This effort received support from a group of public, private, and non-profit partners including the African Union, Illumina and Oxford Nanopore, which produce next-generation sequencing machines, the US Centers for Disease Control and our foundation.
Thanks to Sofonias and the rest of the Africa Pathogen Genomics Initiative team, 31 African nations now have the capability to do genetic sequencing for surveillance of COVID, malaria, cholera, Ebola, and other diseases.
Despite this progress, much remains to be done. Sofonias’s team faces challenges in bringing this technology to all African nations. Access to the equipment needed in the labs has been delayed because of global supply chain disruptions. Training enough lab technicians and data scientists to process and analyze the samples has been difficult. Finally, more coordination is needed between countries to share their genetic data and use it to inform collective health responses.
But every month, Sofonias’s team continues to strengthen and expand the system across the continent. The goal is to create a seamless, integrated network that includes laboratories at the community level, which can spot the first signs of an outbreak, perform genomic testing of pathogens, and analyze the results to guide a public health response.
“Our vision is bold. Our vision is optimistic. We always push forward and continue to work with the countries to show that this is actually feasible,” he said. “It really makes me hopeful that this technology can improve outbreak detection and response in Africa.”
Sofonias shared the progress and challenges of building a genomic disease surveillance network with a group of graduate students who participated in a recent Gates Notes Deep Dive on pandemic prevention.

Heroic acts
Meet the heroes in Africa fighting back against this pandemic—and working to prevent the next one
As Africa faces many challenges during the pandemic, these heroes are making a difference.
In Africa, the latest statistics on COVID-19 are discouraging. Just 6 percent—about 78 millionof the continent’s 1.3 billion people have been fully vaccinated. Worldwide, by comparison, 43 percent are fully vaccinated, and boosters are now widely available in many countries.
Without enough vaccines available in Africa, COVID-19 marches on infecting millions of people. Even assessing the true scale of the pandemic on the continent is difficult. A recent World Health Organization assessment estimated that only one in seven cases of COVID in Africa are being detected because of a limited amount of testing.
And while many Western and Asian countries are recovering economically from the pandemic and returning to some version of normalcy, most countries in Africa continue to struggle. Disruptions to schooling, health care, and livelihoods have sunk many families deeper into poverty, leaving them without enough food and basic services.
We should all be upset about this inequity. (I’ve written recently about this divide and the steps the world needs to take to get the virus under control.) It’s critical that more be done to get vaccines into the arms of the people at high risk for COVID, including the elderly and immunocompromised, who are living in low-income countries. And the recent detection of the Omicron variant serves as a reminder of how important increasing vaccination rates is to deter new mutations of the virus from emerging.
But even during this difficult time, I think it’s important to highlight the many Africans who are fighting back against this pandemic. They are stepping up to alleviate suffering, to combat misinformation, and to develop the tools needed to prevent future pandemics.
There are thousands of examples of heroic work being done in Africa during this pandemic. Here are three stories of organizations and individuals who are working to save lives and bring hope to their communities.
1. South Africa: The Truck
As COVID-19 swept across South Africa, one of the most pressing needs was access to public health information. People needed to know about the virus and how to stay safe. And as South Africa started rolling out COVID vaccines this year, health officials were also tasked with counteracting the spread of misinformation about the virus and vaccines. This was especially challenging in hard-to-reach communities in South Africa, where people don’t have access to television and other media. But UNICEF, in partnership with the national government, had an answer to this challenge: A truck. Not just any truck but a multi-media messenger on wheels. The truck has LED screens, which allows the truck’s organizer to broadcast videos telling local stories about COVID-19. They also organize presentations in communities to raise awareness of the virus, teach people how to prevent its spread, and promote COVID testing and vaccinations. The truck has logged more than 40,000 miles and delivered messages to hundreds of thousands of people.
2. Lesotho: Mamello Makhele
Mamello Makhele is a nurse-midwife working to improve health care for women in rural Lesotho, where there are high rates of maternal mortality. During the pandemic lockdowns many health facilities closed, leaving women living in these remote communities without access to family planning services. On foot and by donkey, Mamello travels high into the mountain to offer health care, deliver babies, and distribute contraceptives. Mamello has also worked nationwide to empower young women, encouraging them to take control of their health and prevent unwanted pregnancies. Thanks to her incredible work, many women are healthier today in Lesotho.
3. Tanzania: Afyadata
Even as the world seeks to end the current COVID-19 pandemic, we need to also be thinking about how to prevent future pandemics. That’s just what a mobile app called Afyadata is helping health officials do in Tanzania. Designed by the Southern African Center for Infectious Disease Surveillance (SACIDS), Afyadata is a digital surveillance tool that allows health workers and even ordinary people to serve as disease detectives. Users can report unusual health occurrences not only in humans, but also animals. Monitoring animals is critical because most new pathogens start in animals before they spread and sicken humans. With the app, farmers can easily report any suspicious illness among their livestock to health officials, who can then quickly follow up with further investigation, if necessary. While this app is still being piloted in several districts of Tanzania and other parts of Africa, it has already been effective in the detection and identification of several small disease outbreaks. I look forward to learning more about Afyadata’s progress.
Inspiring acts
7 unsung heroes of the pandemic
Incredible people caring for those in need during COVID-19.
When I was a kid, my image of a hero was largely inspired by my dad’s collection of early Superman comics. I read them all. A “hero” was somebody who had supernatural powers like flying, laser vision, or the strength to bend steel.
As humans, of course, we’re all pretty limited in our physical powers. We don’t fly. We can’t see through walls. But what’s unbounded in us is our ability to see injustices and to take them on—often at great risk to ourselves.
My work in global health and development has introduced me to many extraordinary heroes with this kind of superpower. And I’ve had the honor of highlighting many of them on this blog: An epidemiologist who helped eradicate smallpox. A doctor working to end sexual violence in Africa. A researcher working to end hunger with improved crops. Just to name a few.
Why do we need heroes?
Because they represent the best of who we can be. Their efforts to solve the world’s challenges demonstrate our values as a society and they serve as powerful examples of how to make a positive difference in the world. And if enough people hear about their actions, they can inspire others to do something heroic too.
If there’s ever been a time that we need heroes, it’s now. The COVID-19 pandemic has created unprecedented health and economic challenges, especially for the most vulnerable among us. The good news is that many people from all walks of life are doing their part to help them. Health care workers. Scientists. Firefighters. Grocery store workers. Aid workers. Vaccine trial participants. And ordinary citizens caring for their neighbors.
Here are portraits of a few individuals from around the world working to alleviate suffering during this pandemic. I hope their stories inspire you just as much as they have me.
To these heroes and heroes everywhere, thank you for the work you do!

Abundant air
Breathing new hope into Africa’s fight against COVID-19
In Africa’s battle against COVID-19, a Kenyan doctor is making sure every breath counts.
As the COVID-19 pandemic spreads across Africa, hospitals across the continent face shortages of essential medical supplies needed to treat the respiratory disease and keep patients alive.
Not just masks and ventilators, but oxygen.
For people living in wealthy countries, medical oxygen is often taken for granted. In many low-income countries, however, oxygen is often in short supply or not available at all. And globally, a lack of oxygen –needed to treat pneumonia, malaria, and other diseases—leads to hundreds of thousands of deaths each year.
Addressing this often overlooked challenge is the life’s work of Bernard Olayo, a Kenyan doctor who founded Hewatele, an innovative organization working to ensure all patients—even in remote areas of the country—have access to oxygen.
Now, he is playing a critical role in Kenya’s preparations to tackle COVID-19 by scaling up oxygen supplies that will be needed to keep the most critically ill patients alive.
While the number of COVID-19 cases in Africa remains low compared to other parts of the world, the continent is bracing for a surge of infections. According to the World Health Organization, up to 190,000 people could die of COVID-19 in Africa if the disease is not controlled. A widespread outbreak would flood many of Africa’s fragile health systems.
A lot of attention has been focused on the lack of ventilators in Africa. Ventilators are the mechanical devices that help patients breathe, pushing air in and out of their lungs, when they can’t on their own. And the shortage of them is a real problem. But the lack of oxygen itself is equally worrying. The coronavirus attacks the respiratory tract, inflaming the lungs and making it difficult for patients to breathe. Oxygen, delivered through a mask or nasal tube, is an essential and effective first line of treatment that’s less invasive than being on a ventilator. Oxygen is also needed to run a ventilator. If COVID-19 patients have access to oxygen as an initial treatment, however, it may prevent many of them from becoming so critically ill that they would require one of the limited number of ventilators to breathe.
What Bernard is hoping to avoid during this pandemic are the painful choices he faced as a young doctor because of a lack of oxygen. After medical school he was posted to a rural hospital, where many of the patients were children battling pneumonia who needed oxygen for treatment. But Bernard soon learned that there was never enough oxygen available. He and the other hospital staff often had to share a single cylinder of oxygen between patients. When there were too many patients and not enough oxygen, he and other doctors would be forced to decide which children would receive oxygen and live, and which would go without it and sometimes die—a choice that broke his heart, he says.
That experience inspired Bernard to investigate the source of Kenya’s oxygen supply shortages. He discovered that one of the biggest challenges is that oxygen is expensive in Africa. In Kenya, oxygen costs about 13 times more than what it does in the United States. The high cost was driven, in part, by a lack of competition. In many countries, including Kenya, there was just a single oxygen supplier for the entire country. And with many health facilities located hundreds of miles away from the oxygen plants, transportation costs drove up prices even higher. The long distances and poor roads also meant that deliveries were unreliable. Hospitals and clinics would regularly run out of oxygen supplies.
In 2014, Bernard founded a public-private partnership to try a new approach that would make access to medical oxygen more affordable and reliable. He named the organization Hewatele (Swahili for “abundant air”). Given the delivery challenges in Kenya, Bernard decided to build oxygen plants at several of the busiest hospitals in the country, where demand is highest and reliable electricity for production is available. The oxygen is then sent out for delivery using a milkman model, with oxygen cylinders regularly dropped off at remote hospitals and clinics and the empty cylinders returned to be refilled. This system ensures that there is always more than enough oxygen available at each facility. Using this new approach, Hewatele has cut the market price for oxygen in Kenya by 50 percent. Now, Bernard is working to expand the number of oxygen plants in Kenya and bring Hewatele’s business model to other parts of Africa.
While the COVID-19 pandemic has brought much needed attention to the oxygen gap in Africa, more needs to be done to ensure that everyone has access to this simple medical intervention. Thanks to Bernard’s efforts, progress is being made. His work has already helped save the lives of thousands of children and adults and will save many more in the future—one breath at a time.

High hopes
This organization is working to create a world without pandemics
The Coalition for Epidemic Preparedness is working to make sure we never again experience the hardship of a pandemic.
Here’s a fact that’s hard to believe: At this time two months ago, the world did not yet know about the omicron variant.
It’s both remarkable and horrifying how quickly omicron has become the dominant cause of COVID-19 in many countries. In just seven weeks, it has led to record-high case numbers and hospitalizations around the world. I’m still optimistic that the pandemic can come to an end sometime in 2022, but first we have to contend with a virus that’s spreading faster than any other in history. (I recently had a good discussion about this with global health Professor Devi Sridhar.)
The omicron surge has been an unfortunate reminder that the only way to eliminate the threat of COVID-19 somewhere is to eliminate it everywhere. As long as the virus continues to circulate at a high level in some parts of the world, we’ll always be at risk for another devastating variant. Game-changing innovations—including vaccines and new antivirals—will save lives but won’t truly accelerate the end of the pandemic until they’re accessible to everyone.
That’s why the Gates Foundation is renewing its investment in the Coalition for Epidemic Preparedness Innovations, or CEPI. I’m excited to announce a new $150 million commitment to its future work on COVID and beyond.
Our foundation helped create CEPI in 2017 to accelerate work on vaccines against new infectious diseases and make sure those vaccines reach people in the poorest countries. The organization has played an invaluable role in the COVID-19 pandemic as one of the leaders of COVAX, the global effort to get vaccines out to low- and middle-income countries.
As with malaria, polio, and many other diseases that our foundation works on, the key to pandemic prevention and preparedness is to keep on innovating. This pandemic’s most significant innovation is mRNA vaccines, which were available less than a year after the virus that causes COVID was identified. CEPI began funding efforts to develop mRNA vaccines for COVID just days after the virus was detected outside of mainland China. (One of the candidates CEPI backed in January 2020 was Moderna.)
But CEPI’s support for research on mRNA vaccines predates COVID-19—which is one of the reasons the approach was successful. The groundwork had been laid years before by investments from governments, pharmaceutical companies, and (more recently) CEPI. And the progress they’ve supported will continue to pay dividends long after the COVID pandemic ends. The mRNA platform is already being used to test new vaccines for TB and malaria diseases. Scientists are hard at work formulating next-generation vaccines that don’t require as many doses and don’t need to be kept frozen.
Altogether, CEPI has invested in 14 COVID vaccine candidates and it continues to work on variants of concern and develop next-generation vaccines that could protect against all coronaviruses. It is also focusing on six other diseases of epidemic potential.
But creating new vaccines isn’t enough. We also have to make sure that everyone who can benefit from vaccines has access to them, and that’s where the world has collectively failed in its response to COVID. While at least 9 billion doses were distributed in the past year, less than one percent went to people in low-income countries. It doesn’t make sense that so many people at lower risk of infection in wealthier countries got vaccinated before we reached the most vulnerable people, including the elderly, those with underlying medical conditions, and healthcare workers.
We need to do better the next time the world faces a pathogen that has the potential to spark a pandemic. (I’m currently writing a book about what the world needs to do to prevent the next pandemic, which will come out later this year.) I believe that the world can and should be ready to develop a new vaccine and make enough for everyone in the world within six months of detecting a potential pandemic—and CEPI will play a crucial role in achieving that. It is one example of how we need to be making investments now to support innovations that will prevent disasters in the future. For example, the organization is supporting efforts to increase manufacturing capacity and recently released a study that provides valuable insights into how we can improve the world’s production capabilities. This is the type of investment we need to make now to prevent disasters in the future.
And because CEPI is a global institution rather than a national one, it can focus on providing access for everyone, alongside other effective global institutions that have saved millions of lives like WHO, Gavi, and the Global Fund to Fight AIDS, TB and Malaria. These groups will help make sure that vaccines don’t just go to the highest bidders.
Imagine how different the last two years would’ve been if everyone in the world had had access to safe, effective COVID vaccines within six months. I know it’s hard to think about the next pandemic as the omicron variant surges around the world, but we have an opportunity to make sure the world never experiences this hardship again. Investing in organizations like CEPI is an important step that moves us closer to a world without pandemics.

COVID coverage
Next time, we can close the vaccine gap much faster
How to use vaccines more fairly and effectively.
Today, 46 percent of the world’s population has received at least one dose of a COVID-19 vaccine. It’s hard to overstate what a remarkable achievement this is. Humanity has never made and distributed a vaccine for a disease faster than it did for COVID-19. It accomplished in 18 months something that used to take a decade or more.
But within this amazing success there is a startling disparity: Just over 2 percent of people in low-income countries have received any COVID-19 vaccines. And the gap will be harder to close as rich-world governments buy up extra doses to serve as booster shots.
People are right to be upset about the inequity here. Vaccines make COVID-19 a largely preventable disease—and a survivable one in all but the rarest cases—and it is heartbreaking to know that people are dying of a disease not because it can’t be stopped but because they live in a low-income country.
Sadly, this inequity is not new. It is not even the worst gap in global health. There were shocking disparities in health long before any of us had heard of COVID-19.
Every year, more than 5 million children die before their fifth birthday, mostly from infectious diseases, and almost entirely in low- and middle-income countries. A child in northern Nigeria is 20 times more likely to die before the age of 5 than a child in a rich country. That is simply unjust, and reducing this inequity has been the Gates Foundation’s top priority for more than 20 years.
If you step back and look at the trends, though, there is good news. Since 1960 the childhood death rate has been cut by more than 80 percent, thanks in large part to the invention and distribution of vaccines for children around the world.
The fact that routine childhood vaccines are reaching so many people is reason to believe COVID-19 vaccines can too. Providing them to everyone who needs them is one of three crucial steps in controlling this pandemic, along with containing the virus so it doesn’t come roaring back and coordinating the global response. At the same time, we can learn from the inequities that were so clear during this pandemic so we can do a better job of closing the gap during the next one. (Assuming there is a next pandemic. I think it is possible to prevent them altogether. But that’s a subject for another time.)
How could we achieve vaccine equity in a future pandemic? I see two ways.
1. Change how the world allocates doses.
What would the optimal allocation look like? It’s not simply a matter of proportional representation, where if your county has X percent of the world’s population, you get X percent of the vaccines. There are two different benefits to consider, and both are important.
One benefit is to the individual who’s immunized; they get protection from the virus. The more likely you are to get infected—and the more likely you are to become seriously ill or die if you do get infected—the more benefit you get from a vaccine. A COVID-19 patient in their seventies is 90 times more likely to die of the disease than a patient in their twenties. From a global perspective, it is neither fair nor wise to protect that young person before the old one.
Second, when an individual is vaccinated, society gets the benefit of lowering the risk that the person will spread the disease to others. This is the core of the argument in favor of vaccinating health workers and people who work in elderly care facilities, since even when a lockdown is in place, they can transmit the virus to people at high risk.
When a virus is spreading, we should maximize both benefits—saving lives and stopping transmission. This means that, when supplies are short, we should prioritize vaccinating people who both have a high risk of death and live in the places where the virus is spreading fastest.
Those will not necessarily be low-income countries. When COVID-19 vaccines first became available, many of the most severe epidemics were in rich- and middle-income countries.
The gravest inequity, even more than vaccinating rich people before poor ones, is vaccinating young people in rich countries before older people in middle-income countries with bad epidemics, such as South Africa and most of South America.
To their credit, rich countries have pledged to share more than a billion doses with poorer countries during COVID-19. But they haven’t yet delivered fully on those pledges, and even if they had, the gap would still be enormous.
Although sharing doses needs to be part of the solution, it will never be sufficient to solve the problem. For one thing, the number of doses won’t be high enough. And will future politicians always be willing to tell young voters they can’t be vaccinated because the doses are going to another country, at a time when schools are still closed and people—including a few young people—are still dying?
That’s why it’s so important to find ways to produce more doses in less time. The world should have the goal of being able to make and deliver enough vaccines for everyone on the planet within six months of detecting a potential pandemic. If we could do that, then the supply of doses would not be a limiting factor, and the way they were allocated would no longer be a matter of life and death.
2. Make more doses.
As limited as the supply of COVID-19 vaccines has been, the situation could have been even worse.
We are fortunate that mRNA vaccines work so well, since this is the first disease for which the mRNA technology has been used. If they hadn’t, we would have been far worse off.
It is also great that some vaccine companies entered into second-source deals, which allowed huge volumes of their vaccines to be manufactured by other firms. This was a crucial and remarkable step. (It’s as if Ford let Honda use its factories to build Accords.) Just one example: In less than two years, a single manufacturer, AstraZeneca, signed second source deals involving 25 factories in 15 countries.
You may have heard the argument that waiving intellectual property (or IP) restrictions would have made a difference. Unfortunately, that’s not true in this case. IP waivers and licensing are a complicated issue, so I want to take some time to untangle it.
There are cases in which IP licensing is a great way to make something cheaper and better. For example, in 2017, the Gates Foundation and a number of partners were involved in an agreement to make a new, more effective version of an HIV drug cocktail that would be more affordable for the world’s poorest countries.
In the deal, a pharmaceutical company gave the recipe for the key ingredient in this cocktail to firms that specialize in producing generic drugs. These firms were able to reduce the cost so much that today nearly 80 percent of people who get HIV treatment in low- or middle-income countries are receiving the improved cocktail.
Unfortunately, IP licensing doesn’t work as well with vaccines. Here’s why.
Many drugs are made using chemical processes that are well defined and measurable. If you mix the same ingredients in the right proportion and so on, you’ll get the same product every time, and you can check your work by looking at the chemical structure after the drug is made. Company A can give a recipe to company B, and company B will be able to make precisely the same drug consistently.
But many vaccines don’t work that way. Manufacturing them often involves living organisms—anything from bacteria to chicken eggs. Living things don’t necessarily act exactly the same way every time, which means that even if you follow the same process twice, you might not get the same product both times. Even an experienced vaccine maker might not be able to simply take another’s recipe and replicate it reliably.
This is why broadly waiving IP protections would not meaningfully increase the supply of vaccines. (In the case of COVID-19, though, a narrow waiver that applied to specific easily transferred technologies during the pandemic made sense.) Supply has been limited not because of IP rules, but because there aren’t enough factories capable of handling the more complicated process of making vaccines.
Licensing IP—or having the rights to it waived—only guarantees that company A can’t sue company B. Second-source deals are far superior because they involve sharing not only the recipe but also knowledge about how to use it, as well as personnel, data, and biological samples. It was a second-source deal with AstraZeneca—not an IP waiver—that allowed Serum Institute of India to produce 100 million doses at a very low cost and in record time.
So how can the world make more doses faster next time?
First, decision makers should get serious about expanding the world’s vaccine-making capacity. In particular, governments and industry should make sure there’s enough capacity to quickly make huge volumes of mRNA vaccines; now that we know the mRNA platform works, it will allow new vaccines to be developed faster than any other approach. And if companies that have second-source deals now maintain their relationships with each other, they won’t have to start from square one in the next outbreak.
Another step is to develop prototype vaccines against the diseases that are most likely to cause future outbreaks, and to develop universal vaccines for flu and coronaviruses, which would protect people against any form of the two pathogens. The NIH and Coalition for Epidemic Preparedness Innovations are doing excellent work on both, but even more research is needed.
One longer-term step is for more countries to build the capacity to develop, manufacture, and approve vaccines themselves.
Historically, the companies that invent new vaccines have been based in higher-income countries. Because it costs so much to develop a new product, they try to recoup their costs as quickly as possible by selling doses at the higher prices that rich countries can afford. They have no financial incentive to try to lower their costs (by optimizing the production process, for example) so that the price can be cheap enough for lower-income countries.
The pentavalent vaccine—which protects against five diseases—is a great example. It was invented in the early 2000s, but there was only one manufacturer, and at more than $3.50 per dose, it was far too expensive for low- or middle-income countries. Our foundation and other partners worked with two vaccine companies in India—Biological E Limited and Serum Institute of India—to develop a pentavalent vaccine that would be affordable everywhere. Today that vaccine costs about $1, and it is given to 80 million children a year. That’s a 16-fold increase since 2005.
We need more examples like this. Pentavalent took years to pull off. If there were more high-volume vaccine manufacturers whose primary goal was to produce low-cost vaccines, then affordable doses would be available much faster. Middle-income countries are a natural home for these companies, and some have set ambitious goals for themselves. For example, a group of African leaders has set a target of manufacturing 60 percent of the continent’s vaccines by 2040.
Helping middle-income countries build their vaccine-making capacity is something the Gates Foundation has been working on for two decades. We’ve helped bring 17 vaccines to market, and we’re supporting the African efforts to build theirs out by 2040.
What we’ve learned is that creating an entire vaccine-making ecosystem is a tough challenge. But the obstacles can be overcome.
One issue is the need for regulatory approvals. Vaccine factories are required to be approved by what’s known as a “gold-standard” regulator. India is the only developing country with a gold-standard regulator; factories in any other developing country have to be approved by their own government first, and then by the WHO. It’s time-consuming.
Regional agencies in Africa are working with the WHO and the European Union to create gold-standard regulation on the continent. Governments are also collaborating on regional standards for vaccines, so manufacturers don’t have to meet different safety and efficacy requirements in each country.
Another challenge: If vaccine manufacturers don’t have other products to make between outbreaks, they’ll go out of business. Unfortunately, making existing vaccines isn’t a viable option, at least right now, because the market is already saturated with existing vaccines, and it would be hard for new entrants to compete on price with established low-cost / high-volume companies.
But new products are coming that would be ideal products for them. As vaccines become available for diseases like malaria, tuberculosis, and HIV, they’ll create opportunities for producers in middle-income countries. In the meantime, countries can take on the fill and finish process—putting vaccines made elsewhere into vials and distributing them.
To anyone who has lost a loved one to COVID-19, or had to choose between paying the rent or buying food, it is no comfort to suggest that anything has gone well in this pandemic. But as my friend the late Hans Rosling used to say, “The world can be both bad and better.” The situation today is bad, and also better than it would have been if COVID-19 had come along ten years ago. If the world makes the right investments and decisions now, we can make things better next time. And maybe even make sure there is no next time at all.
This post originally appeared on CNN.com.

Pandemic plan
How to end the COVID crisis
Three steps to getting the virus under control.
This week global leaders are coming together at the UN General Assembly, which presents an opportunity to refocus energy and commitment on ending the crisis phase of this pandemic and to make sure we’re better prepared for the next one. In this piece I talk about how we can apply what we have learned since early 2020 and embrace a set of global actions that chart an equitable course out of the pandemic—vaccinate now, contain the disease, and coordinate the global response.
We’ve reached the 18th month of the COVID-19 pandemic, a somber milestone marked by yet another surge of cases and deaths fueled by the Delta variant. This global crisis has been a health, economic and moral disaster playing out in waves in every geography, sparing none. While the pandemic has been a shared experience, the experience has not been the same everywhere.
In the past year-and-a-half, we have witnessed scientific breakthroughs with multiple safe and effective vaccines developed in record time, incredible multilateral cooperation resulting in billions of dollars raised for the response, and heroic efforts by healthcare and frontline workers in communities worldwide. But at the same time, we have also seen widening gaps in equity that go against everything our foundation and its partners have worked for over the past 20 years. The advent of vaccines was an opportunity to bend the curve in the direction of a global recovery. It turned out that unequal distribution and a lack of funding and supply meant the recovery has been precarious and halting.
In last year’s Goalkeepers report, Melinda and I shared modeling that warned that globally deaths would be higher if doses went predominantly to high income countries. To date, less than 2% of people in low-income countries have received a dose of a COVID-19 vaccine, compared to more than 60% of people in the U.S. The pull of the inequity we’re seeing isn’t only on the here and now—the economic recovery of low-income countries that are slow to be vaccinated is stuck in the starting blocks. These countries can expect to experience between 2-4% GDP losses through 2025 (averaging 3% per year in sub-Saharan Africa).
After 18 months of surprises around every corner with variants fueling new waves of disease there’s a tendency to say one cannot predict what will happen next. To some extent that’s true—nature is wily, and the virus will continue to mutate if it can transmit unchecked. But it’s also defeatist and incorrect to suggest that the acute phase of the pandemic will spiral on from one variant to the next. Just as the virus can change, so can the world’s response to it. Whether the world can finally turn the corner, however, will be determined by what we do next and how it’s done.
Our path out of the pandemic has always required one thing—a commitment to equity. A willingness to see that what happens in lower-income countries affects high-income countries. There is no nationalistic solution to this global problem. We’ve seen countries try and fail in that pursuit as variants emerge and threaten progression from the acute phase of the pandemic. There are three things that can be done in the coming months that can bring about the end of the acute phase of the pandemic and set the world on a different timeline in preparation for the next. I hope that leaders meeting virtually this week at the COVID Summit commit to actions that meet these needs:
1. Vaccinate Now
Governments and the private sector must work together to build a more transparent system to accelerate the global supply of vaccines. While a shortage of supply was a major issue in the first half of the year, recently 41 million doses per day have been distributed globally. It’s progress, but there’s a long way to go. The WHO/Gavi-led COVAX AMC, Africa CDC-led African Vaccine Acquisition Task Team (AVATT) and other channels can move vaccines, but they need more doses, visibility to supply, and sufficient money to acquire and deliver them. This is quickly turning into a logistics and financing challenge, and we know how to solve those types of problems. A consolidated global dashboard that provides real-time vaccine production and availability data will enable countries and global institutions to collaborate on filling access gaps. While donations to COVAX were slow to arrive, current funding can support delivery to about 30% of the population in lower- and middle-income countries. It’s a good start, and funding for 70% coverage in the lowest income countries needs to be made available by mid-2022 along with enhanced delivery capacity at the country level.
2. Contain the Disease
In addition to getting vaccines out to close the global equity gap we also must contain outbreaks as they happen. This can help keep countries out of the cycle of lockdowns that has left schools and businesses in constant flux. To reduce the risk of variants jumping from border to border, the world must invest in readily available rapid testing, a system for sharing genetic sequences, and a mechanism to deliver expertise and commodities (like oxygen, PPE, and life-saving drugs) quickly where they are needed. We’ve seen this done successfully with diseases like polio and malaria—using data to inform actions that bring outbreaks under control. We need to have expert support and response materials like oxygen, PPE, and life-saving drugs ready to deploy in the event of major outbreaks. The private sector has a role to play, using its expertise in logistics to reduce lead times and fill supply gaps.
3. Coordinate the Global Response
The establishment of the Access to COVID-19 Tools Accelerator (ACT-A) in early 2020 was a milestone: governments, international organizations and the private sector came together in response to the crisis. We now need all governments to appoint a COVID-19 global lead, reporting to the head of state, and for these leads to regularly convene through 2022. With the support of independent monitoring this globally coordinated, time-limited task force can complement ACT-A and take us from aspiration to ending the pandemic through collective action and provide a model for the long-term coordination needed to prevent future pandemics.
For people involved in global health, what happened during the pandemic is disappointing, but not a surprise. The system whereby lower-income countries rely on the generosity of high-income country donors broke down when those donor countries were experiencing the same struggles. The next 18 months do not have to look like the past 18 months. But we cannot turn the page on this pandemic until we’ve addressed the fundamental inequity that stands in our way.
I’m optimistic about the potential of this moment. Health is not a zero-sum game—we can meet everyone’s needs through planning, investment, collaboration, and applying lessons learned. The cost of this pandemic has already been unacceptably high. Ending it cannot come at the cost of progress on other global health and development priorities. Reducing poverty, advancing gender equality, and finishing the job of eradicating polio are all possible through the same collective action that is needed to end this pandemic.
For those that want to go deeper, Gargee Ghosh who heads up the policy and advocacy division at the Gates Foundation has shared a white paper with more details on actions the world could take to end the COVID crisis.

Changes
5 things you should know about variants
The virus that causes COVID-19 is evolving, and it’s complicating our efforts to end the pandemic.
I’ve spent a lot of time over the last year meeting with colleagues at our foundation and around the world about ways to test for, treat, and prevent COVID-19. In recent months, the experts in those meetings are increasingly asking the same question: How will new variants impact our efforts to end the pandemic?
The world has come a long way in the fight against COVID-19, but new variants of the virus could threaten progress we’ve made over the past year. Here are five things you should know if you want to understand how variants are (and aren’t) complicating the pandemic.
1. If you’ve ever gotten a flu shot, you’ve already dealt with a virus variant.
Viruses evolve all the time. Unless you work on infectious diseases, the idea of a “variant” might seem new and scary—but there’s nothing particularly unusual about them. Influenza’s ability to mutate quickly (I’ll talk more about this in the next section) is why we get a new flu shot every year. We need to update the vaccine annually to keep up with constantly shifting flu virus strains.
To understand why the virus that causes COVID-19 is changing, you need to understand how it works (or spreads) in your body. The coronavirus—like all viruses—has only one goal: to replicate itself. Every time the virus invades your cells, it tricks the cell into following the instructions encoded in its RNA to make more copies of the virus.
When the cell is making a new virus, it has to copy those instructions. If you’ve ever had to take a typing class in school, you know how hard it is to retype something without making a mistake. The code for the virus that causes COVID-19 is around 30,000 letters long. That’s a lot of opportunities to mess up—which the coronavirus often does.
Most mistakes lead to a virus that either is functionally identical or can’t replicate. But every once in a while, there’s a change that makes it easier for the virus to infect people or evade the immune system. When that change starts to spread through a population, a new variant emerges.
2. We’re seeing the same mutations pop up again and again. That may be good news.
All viruses evolve, but not all viruses evolve at the same rate and in the same way. Some, like the flu, change rapidly. Others mutate slowly. Fortunately for us, SARS-CoV-2 is in the latter camp. It mutates about half as fast as the influenza virus.
I know it feels like new variants are popping up all the time right now. That’s because there is so much virus circulating around the world, giving it more opportunities to change. Once case numbers go down, I suspect we’ll see new variants emerge much less often.
Compared to influenza viruses—which are made up of eight genetic segments that can be rearranged in lots of different ways—the coronavirus is a much simpler virus. The most notable mutations we’ve seen so far have happened in the same spot: the spike protein that sticks out of the surface of the virus.
That spike protein is the key to COVID’s spread. Its shape is what enables the virus to grab onto human cells. If the spike protein changes just a little, it might bind with cells more effectively (which makes the virus more transmissible) or become harder for the immune system to target (which makes people more susceptible to it). But if it changes too much, the virus can no longer gain the entry that’s key to its lifecycle.
That limited capacity for change may explain why we keep seeing the same mutations appear in different places rather than lots of distinct variations. Both B.1.1.7 (which was originally detected in the UK) and B.1.351 (which was first found in South Africa) evolved independently, yet they share a number of the same mutations. There’s clearly something about these specific mutations that makes them more likely to succeed than other changes.
Some experts think we may have already seen the most concerning mutations that this virus is capable of. But COVID-19 has surprised us before, of course, and it could surprise us again.
3. The virus is changing, but the path to ending the pandemic remains the same.
For the last year, public health experts have been repeating some form of the same message: we need to contain COVID-19 as best we can until the vaccine is ready and available for everyone.
The good news is that many of the vaccines being used today appear to prevent severe disease, even from the new variants. This is a tribute to how effective the vaccines are in general. We still need a lot more data about how effective every vaccine is against the different variants, but many of the early numbers are reassuring (especially out of Israel, where many people are already vaccinated and the B.1.1.7 strain is dominant).
The big question now is whether we need to update the vaccines to target the variants. Regulators and drug companies are working on a modified vaccine that could be out in a couple months if it’s deemed necessary. Here in the United States—where the majority of people will likely be vaccinated by the end of the summer—some people may end up getting a booster shot that protects against additional strains.
For now, the key is to keep following best practices. The best way to prevent new variants from emerging is by stopping transmission of the virus altogether. If we remain vigilant about social distancing, wearing a mask, and getting vaccinated, we will bring the pandemic to an end much sooner.
4. Variants make it even more important that vaccines are made available everywhere.
COVID-19 anywhere is a threat to health everywhere. That’s true with the original virus, and it’s true when it comes to variants.
The more the virus that causes COVID-19 is out there in the world, the more opportunities it has to evolve—and to develop new ways of fighting our defenses against it. If we don’t get the vaccine out to every corner of the planet, we’ll have to live with the possibility that a much worse strain of the virus will emerge. We could even see a new variant emerge that evades existing vaccines altogether.
No one wants that to happen. The best way to make sure it doesn’t is by getting the vaccine out to everyone who needs it, no matter where they live. That’s why our foundation is working with governments, vaccine manufacturers, organizations like CEPI and Gavi, the Vaccine Alliance, and others to deliver COVID-19 vaccines to low-income countries through an initiative called COVAX.
COVAX recently announced that it’ll be able to deliver 300 million doses by mid-2021. That’s great news, but the world is going to need a lot more if we’re going to truly stamp out the threat of COVID-19. I hope rich world countries continue to support COVAX’s work, even as life starts to get back to normal in some parts of the world over the summer.
5. We can do better next time.
Virus variants are inevitable. If we ever find ourselves in a pandemic scenario again where a pathogen is spreading around the globe, we should expect to see it adapt to survive our attempts to stop it—just as we saw with COVID-19. I hope the difference next time is that we’re better prepared to spot these variants earlier.
The key will be genetic sequencing in combination with better disease surveillance. Right now, if you test positive for COVID-19, there’s a possibility that your test sample gets selected to be sequenced. This lets researchers see the exact 30,000 letter code that makes up the virus’ RNA instructions. That code gets uploaded to a database, where a computer compares the virus in your sample to all the other strains in circulation. . If you have a new strain that’s starting to pop up over and over in your area, scientists can compare the sequence data to transmission, death, and hospitalization rates to see if there’s need for concern.
Researchers need to take a systematic approach to catch variants early. Some experts think we need to sequence at least 5 percent of all test samples to get an accurate picture of how a pathogen is mutating—although sequencing a large number of samples alone isn’t enough. The UK has analyzed nearly 8 percent of its tests and linked that data with their surveillance capabilities, which helped them see that B.1.1.7 was spreading much faster and was more lethal. South Africa was able to quickly see how vaccines worked on B.1.351 by comparing results from clinical trials there to sequenced data.
The tools we’re putting in place to monitor variants in this pandemic will prove invaluable long after the worst of COVID-19 is behind us. Widespread sequencing should be part of any plan to prepare for the next pandemic. If you’re doing enough sequencing and comparing that data with other measures, you can see concerning variants when they first emerge. The earlier you identify a change, the more time you have to study it and, if needed, to tune vaccines and therapeutics to address any changes that have taken place.
There’s no doubt that variants complicate our efforts to bring an end to this pandemic. Even once the worst is behind us, we’ll need to remain vigilant. Fortunately, we know what we need to do to stop them from emerging. For now, the best thing you can do to protect yourself is to follow public health guidelines and get vaccinated as soon as you’re eligible.
Polio
Iron will
I can’t think of a more important moment than right now in the fight against polio.
Most people today probably don’t know what this is.
And that’s a good thing because it shows how much progress the world has made against polio, a terrible and now largely forgotten disease.
This metal tank is an iron lung, a mechanical respirator that saved the lives of thousands of polio victims.
Polio attacks the body’s nervous system, crippling patients. In the worst cases, the disease paralyzes their respiratory muscles and makes it difficult for them to breathe, sometimes resulting in death.
Using changes in air pressure, the iron lung pulls air in and out of a patient’s lungs, allowing them to breathe and stay alive.
During the height of the polio epidemic in the U.S. in the 1940s and 1950s, rows of iron lungs filled hospital wards to treat thousands of polio patients, most of them children.
Polio
Meeting the Musahar
A trip to a remote corner of India taught me a powerful lesson about what it will take to wipe out polio.
Whenever someone asks me why I believe it’s possible to eradicate polio, I tell them about my 2010 trip to India to visit one of the country’s lowest castes—the Musahar.
Today, India is polio free. But less than a decade ago, more than half the world’s cases of polio could be found in India. At the time, many health experts said that India would be the last place on Earth to stop polio because its high birth rate, poor sanitation, and population density allowed the disease to flourish.
So how did they wipe out the disease?
The answer can be found in the remote marshlands of the Kosi River in the Indian state of Bihar. The region is home to one of the poorest, most underserved castes in India, the Musahar. In 2010, vaccinating the Musahar and other people living in remote, high-risk areas was one of the biggest obstacles India faced in its long campaign to end the paralyzing disease. Thousands of children were being missed during the national immunization drives, allowing the disease to continue to spread.
In response, the Indian government launched an all-out effort to reach every child, employing a new communication campaign to mobilize support for polio immunization and better maps to ensure that no family was missed. They deployed more than 2 million vaccinators who covered every speck of the country, including the Musahar village I visited, which was often inaccessible because of flooding from the Kosi River. (One of the most inspiring photographs of that time was an image of polio workers wading waste deep in water to reach remote villages with the polio vaccine.)
By 2014, India achieved its goal of being polio free, proving that the paralyzing disease could be defeated in the most complicated circumstances. With new ties to even the remotest communities, health workers are providing children with much more than the polio vaccine. They continue to work with local communities to improve the delivery of other critical health services, including maternal and newborn care, as well as vaccinations for measles and other preventable diseases.
India’s experience continues to be an inspiration for the world’s final push to wipe out polio in the three countries where it endures: Afghanistan, Pakistan, and Nigeria. Based on the latest figures, in 2017, there were just 21 identified cases of wild poliovirus in the world—the lowest number ever—down from 350,000 cases per year when the global polio eradication effort launched in 1988.
That’s an incredible achievement. But now is no time for complacency. If polio is a threat anywhere in the world, it is a threat to us all. That’s why it’s more important than ever for the world to continue to support the millions of vaccinators who are working tirelessly to finish the job. Their dream, as is mine, is to see the day that polio is defeated.
Exemplars
We’re finally learning why countries excel at saving lives
A new program is spreading the word about the most successful approaches to health.
Ever since I was a teenager, I’ve tackled every big new problem the same way: by starting off with two questions. I used this technique at Microsoft, and I still use it today. I ask these questions literally every week about COVID-19.
Here they are: Who has dealt with this problem well? And what can we learn from them?
They seem like obvious questions, but sometimes it's surprisingly hard to find the answers—especially when it comes to global health. There are low- and middle-income countries that have made huge leaps in, for example, delivering vaccines or ending malnutrition. But anyone who wants to identify those countries, find out how they did it, and apply the lessons in their own country would have their work cut out for them.
In sports, every coach is able to study the most successful teams and figure out what they’re doing well. There’s no reason that things should be any different when the goal is preventing childhood deaths instead of scoring touchdowns.
That’s why I was eager to be part of a global effort to fill the gap. Over the past three years, health experts and organizations from countries at every income level (including the Gates Foundation) have come together to find out who has made the most progress on certain health problems, identify what made them so successful, and help others put these lessons into action.
The result of all this effort—the Exemplars in Global Health program—launched earlier this year. If you want to know which countries have made the most progress with limited resources, Exemplars is a great place to start.
For now, Exemplars focuses on five areas: under-five mortality; vaccine delivery; the role of community health workers; epidemic preparedness and response; and childhood stunting (the reduction in physical and mental development caused by poor nutrition). The team will be adding other areas, including newborn and maternal mortality, family planning, maternal anemia, and primary health care systems.
The Exemplars team has scoured the world for the best performers and worked with experts in those countries to find out what worked so well. For example, they identified seven countries that have excelled at reducing the number of children who die before their fifth birthday: Bangladesh, Cambodia, Ethiopia, Nepal, Peru, Rwanda, and Senegal. The Exemplars website has a profile of each country, detailing insights from its work that other countries could learn from.
Bangladesh—whose childhood mortality rate dropped 56 percent between 2000 and 2015—used data, research, and testing especially well, and empowered women to make decisions about their children’s health. Peru, which achieved roughly the same decline as Bangladesh, conducted local studies to identify interventions that might suit specific communities. All seven countries built up strong community health systems and made specific efforts to close the equity gap by reaching the poorest people.
Of course, not all lessons can be applied in the same way everywhere. What works in one country may not work exactly the same way in another. And it is not always obvious how to implement big changes in national health systems, which are very complex and require a lot of coordination among the government, the private sector, and non-profits.
Recognizing these challenges, the Exemplars program is much more than a website. There is also a community of global and in-country experts ready to help countries make the case for investing in the most effective programs and figure out how to adapt the lessons to their particular needs. We’re not interested in simply getting the information out there—we want to help drive change.
Our hope is to connect with decisionmakers: people who work in the governments of low- and middle-income countries, at development agencies like America’s USAID and the World Bank, and at organizations that implement health programs. Exemplars is all about figuring out how to improve health care based on evidence of what works. It will help governments use time and money more efficiently—and with the COVID-19 pandemic, there has never been a greater need to get the most impact out of every dollar spent.
I’m grateful to all the people in governments, academia, and non-profits who made the Exemplars program possible. We all started out with one goal in mind: to accelerate the progress in improving health, so that the poorest countries don't have 20 times the childhood death rate of the richest ones. I think Exemplars is a great resource that will spread success stories so even countries with very little money can benefit. And that will, ultimately, save lives.

Handling coronavirus
How to respond to COVID-19
And prepare for the next epidemic, too.
In any crisis, leaders have two equally important responsibilities: solve the immediate problem and keep it from happening again. The COVID-19 pandemic is an excellent case in point. The world needs to save lives now while also improving the way we respond to outbreaks in general. The first point is more pressing, but the second has crucial long-term consequences.
The long-term challenge—improving our ability to respond to outbreaks—isn’t new. Global health experts have been saying for years that another pandemic rivalling the speed and severity of the 1918 influenza epidemic wasn’t a matter of if but when. The Bill & Melinda Gates Foundation has committed significant resources in recent years to helping the world prepare for such a scenario.
Now, in addition to the perennial challenge, we face an immediate crisis. In the past week, COVID-19 has started to behave a lot like the once-in-a-century pathogen we’ve been worried about. I hope it’s not that bad, but we should assume that it will be until we know otherwise.
There are two reasons that COVID-19 is such a threat. First, it can kill healthy adults in addition to elderly people with existing health problems. The data so far suggests that the virus has a case fatality risk around 1%; this rate would make it several times more severe than typical seasonal influenza and would put it somewhere between the 1957 influenza pandemic (0.6%) and the 1918 influenza pandemic (2%).
Second, COVID-19 is transmitted quite efficiently. The average infected person spreads the disease to two or three others. That’s an exponential rate of increase. There is also strong evidence that it can be transmitted by people who are just mildly ill or not even showing symptoms yet. This means COVID-19 will be much harder to contain than Middle East Respiratory Syndrome or Severe Acute Respiratory Syndrome (SARS), which were only spread by those showing symptoms and were much less efficiently transmitted. In fact, COVID-19 has already caused 10 times as many cases as SARS in just a quarter of the time.
The good news is that national, state, and local governments and public health agencies can take steps over the next few weeks to slow the spread of COVID-19.
For example, in addition to helping their own citizens respond, donor governments should help low- and middle-income countries prepare for this pandemic. The health systems in many of these countries are already stretched thin, and a pathogen like coronavirus can quickly overwhelm them. And poorer countries have little political or economic leverage, given wealthier countries’ natural desire to put their own people first.
By helping countries in Africa and South Asia get ready now, we can save lives and also slow the global circulation of the virus. (A significant portion of the commitment Melinda and I recently made to help kickstart the global response to COVID-19—which could total up to $100 million—is focused particularly on developing countries.)
The world also needs to accelerate work on treatments and vaccines for COVID-19. Scientists were able to sequence the genome of the virus and develop several promising vaccine candidates in a matter of days, and the Coalition for Epidemic Preparedness Innovations is already preparing up to eight promising vaccine candidates for clinical trials. If one or more of these vaccines proves safe and effective in animal models, they could be ready for larger-scale trials as early as June. Drug discovery can also be accelerated by drawing on libraries of compounds that have already been tested for safety and by applying new screening techniques, including machine learning, to identify antivirals that could be ready for large-scale clinical trials within weeks.
All these steps would help address the current crisis. But we also need to make larger systemic changes so we can respond more efficiently and effectively when the next epidemic arrives.
It’s essential to help low- and middle-income countries strengthen their primary health care systems. When you build a health clinic, you’re also creating part of the infrastructure for fighting epidemics. Trained health care workers not only deliver vaccines; they can also monitor disease patterns, serving as part of the early warning systems that will alert the world to potential outbreaks.
The world also needs to invest in disease surveillance, including a case database that is instantly accessible to the relevant organizations and rules that require countries to share their information. Governments should have access to lists of trained personnel, from local leaders to global experts, who are prepared to deal with an epidemic immediately, as well as lists of supplies to be stockpiled or redirected in an emergency.
In addition, we need to build a system that can develop safe and effective vaccines and antivirals, get them approved, and deliver billions of doses within a few months of the discovery of a fast-moving pathogen. That’s a tough challenge that presents technical, diplomatic, and budgetary obstacles, as well as demanding partnership between the public and private sectors. But all these obstacles can be overcome.
One of the main technical challenges for vaccines is to improve on the old ways of manufacturing proteins, which are just too slow for responding to an epidemic. We need to develop platforms that are predictably safe, so regulatory reviews can happen quickly, and that make it easy for manufacturers to produce doses at a low cost and a massive scale. For antivirals, there will need to be an organized system to screen existing treatments and candidate molecules in a swift and standardized manner.
Another technical challenge involves constructs based on nucleic acids. These constructs can be produced within hours after a virus’s genome has been sequenced; now we need to find ways to produce them at scale.
In addition to these technical solutions, we’ll need diplomatic efforts to drive international collaboration and data sharing. Developing antivirals and vaccines involves massive clinical trials and licensing agreements that would cross national borders. We should make the most of global forums that can help achieve consensus on research priorities and trial protocols so that promising vaccine and antiviral candidates can move quickly through this process. These platforms include the World Health Organization R&D Blueprint, the International Severe Acute Respiratory and Emerging Infection Consortium trial network, and the Global Research Collaboration for Infectious Disease Preparedness. The goal of this work should be to get conclusive clinical trial results and regulatory approval in three months or less, without compromising patients’ safety.
Then there is the question of funding. Budgets for these efforts need to be expanded several times over. Billions more dollars are needed to complete Phase III trials and secure regulatory approval for coronavirus vaccines, and still more funding will be needed to improve disease surveillance and response.
Why does this require government funding—can’t the private sector solve this on its own? Pandemic products are extraordinarily high-risk investments, and pharmaceutical companies will need public funding to de-risk their work and get them to jump in with both feet. In addition, governments and other donors will need to fund—as a global public good—manufacturing facilities that can generate a vaccine supply in a matter of weeks. These facilities can make vaccines for routine immunization programs in normal times and be quickly refitted for production during a pandemic. Finally, governments will need to finance the procurement and distribution of vaccines to the populations that need them.
Obviously, billions of dollars for anti-pandemic efforts is a lot of money. But that’s the scale of investment required to solve the problem. And given the economic pain that an epidemic can impose—just look at the way COVID-19 is disrupting supply chains and stock markets, not to mention people’s lives—it will be a bargain.
Finally, governments and industry will need to come to an agreement: During a pandemic, vaccines and antivirals won’t simply be sold to the highest bidder. They’ll be available and affordable for people who are at the heart of the outbreak and in greatest need. Not only is this the right thing to do, it’s also the right strategy for short-circuiting transmission and preventing future pandemics.
These are the actions that leaders should be taking now. There is no time to waste.
This post originally appeared on the website of the New England Journal of Medicine. I wrote there about the need for a global pandemic response system in 2015, and about the threat posed by a novel respiratory virus in 2018.

Talking dirt
Why I ♥ fertilizer
I visited a warehouse in Tanzania that was filled with a magical innovation that can lift millions out of poverty.
I’ve never been shy about my passion for fertilizer. It’s a magical innovation that’s responsible for saving millions of lives from hunger and lifting millions more out of poverty by boosting agricultural productivity.
So, you can imagine my delight when I recently stepped into a warehouse in Tanzania and got a glimpse of thousands of tons of fertilizer piled as high as snow drifts. The warehouse in Dar es Salaam is part of a new fertilizer distribution center, the largest of its kind in East Africa. Watching workers fill bags with the tiny white pellets containing nitrogen, phosphorous, and other plant nutrients was a powerful reminder of how every ounce of fertilizer has the potential to transform lives in Africa.
But that potential is only realized when it reaches the hands of the world’s poorest farmers—a challenge that’s proven difficult in Africa, where fertilizer use is very low, and, as a result, agricultural productivity is too. (Farmers’ yields in many parts of Africa are just a fifth of those of U.S. farmers.)
The warehouse I visited is one critical piece of the solution for improving both the supply and demand for fertilizer in Africa.
There are many reasons fertilizer use has not caught on in Africa. Cost is one of the biggest problems. Poor roads and other weak infrastructure make transporting fertilizer expensive, driving up its price for many African farmers by about 25 percent compared to their counterparts in other parts of the world. Then, there’s the issue of supply, which is not always dependable because of weak distribution systems in many parts of the continent. Limited access to credit prevents farmers from purchasing fertilizer even if it is available. And a lack of agricultural training means that farmers may not see the value of investing in it or understand how to use it properly.
So how can a warehouse solve these challenges? Let’s start with the warehouse itself. With room for 350,000 metric tons of fertilizer—in 2016, Tanzania used a total of 277,000 metric tons—the warehouse built by Yara, a Norwegian agricultural company, can hold an ample supply to prevent shortages.
At the same time, Yara is working with the government of Tanzania and dozens of other businesses and nonprofit organizations to stimulate demand for fertilizer by providing training to smallholder farmers on how to use it to boost crop yields.
Around 80 percent of Tanzania’s workforce is engaged in farming and related industries. Growing more food through greater fertilizer use would have a huge impact on the country’s prosperity.
What I saw at work in Tanzania is part of a broader effort underway in Africa to use agricultural as an engine to power economic growth across the continent. New innovations in farming—from better fertilizer and crops that are more productive, nutritious and drought and disease resistant—will make it possible for African farmers to increase their yields in the years ahead. With greater productivity, farming families will be able to sell their surpluses to supplement their family's diet with vegetables, eggs, milk, and meat.
We’ve seen the impact of helping farmers grow more food before with the “Green Revolution,” a historic transformation of agriculture in Latin America and South and Southeast Asia during the 1960s, which doubled food production and staved off widespread famine. The increase in agriculture production was made possible by improved seeds and fertilizer use.
As Africa experiences its own agricultural revolution, however, the world must be sure to learn from the past. One of the consequences of the Green Revolution was excessive fertilizer use, leading to water pollution and other environmental impacts. That’s why our foundation continues to work with partners to help train farmers how to apply fertilizer in the proper amounts that will increase yields while also promoting environmental sustainability. We’re also working on digital soil mapping and soil testing to provide farmers with valuable insights into how to improve the health of their soil so they can remain productive for generations to come.
My visit to the warehouse was a highlight of my trip to Tanzania. Just before wrapping up my tour, I paused briefly to watch workers stack bags of fertilizer onto flatbed trucks for their long journey to farms hundreds of miles away. It was exciting to think about the farmers who would use them and the positive impact the fertilizer would have on their next harvests and their country’s future.
Captain Kirk vs. malaria
The world’s deadliest shapeshifter
The malaria parasite is good at fooling your immune system. Now scientists are fighting back.
It’s Mosquito Week again on the Gates Notes. In this post I write about how the malaria parasite changes shape to foil your immune system. I’ve also written about ingenious new genetic techniques for fighting mosquitoes and maps that could help us defeat malaria.
I remember an old episode of the original Star Trek where the bad guy is a shapeshifter who turns himself into a second Captain Kirk. There’s a great scene at the end where Spock has to figure out which one is the impostor.
Shapeshifters are not just the stuff of science fiction, though. We have them right here on earth. Some are innocuous, like a caterpillar turning into a butterfly. But there’s another shapeshifter that’s responsible for more than 400,000 deaths every year. I’m talking about the group of microscopic parasites that cause malaria.
Malaria is one of the most fascinating and frustrating diseases our foundation works on, and its ability to change shape is one of the main reasons why. These parasites have figured out ingenious ways to fool your immune system. They have also (mostly) evaded our best efforts to make a malaria vaccine.
To understand how, it helps to know a bit about how your immune system works.
Your system is very good at detecting unusual objects in your body. It looks at the proteins on the surface of an invader and says, “I’ve never seen the funny shape on the outside of this thing. I’m going to attack it.” After the invader is defeated, your body remembers what it looked like and will go after it if it ever shows up again. Vaccines work by taking advantage of this process. When you get a measles shot, it contains a little bit of the virus; it won’t make you sick, but your body learns how to defend itself against future infections.
Unfortunately, malaria is a lot more complex than viruses or bacteria. For one thing, it is caused by parasites. Parasites don’t look as weird to your body as viruses or bacteria do. In fact, they more closely resemble your own cells, so your immune system has a harder time fighting them off.
Another problem is that the malaria parasite goes through three different stages in your body. It looks radically different in each stage, and as the infection goes on, you have all three going on at once.
Stage 1 begins when an infected mosquito bites you and injects a little saliva under your skin. This dose of saliva might contain only 100 parasites (called sporozoites in this stage). They are small and don’t cause any inflammation in your body, so your immune system doesn’t bother to look for them. You’re not feeling any symptoms yet.
Within an hour or two, the sporozoites make their way to your liver for stage 2. Coming out of your liver, they take a new form (called merozoites) and start invading your red blood cells. This invasion causes the symptoms—fever, chills, and so on—that make malaria such a miserable and deadly disease.
Now your body knows it’s sick and your immune system kicks in. But this is where the parasite’s shapeshifting comes into play.
Remember how the measles vaccine helps your immune system learn to identify the virus by looking for certain proteins on its surface? That works because those proteins look the same on each clone of the measles virus in your body. With malaria, each one can present up to 60 different proteins—and thanks to a mechanism that tells the parasite to alter its surface periodically, they shuffle these proteins around in different combinations every few days.
As a result, by the time your immune system has figured out how to attack one shape, the parasite has transformed, and your body’s defenses are useless. Your immune system adjusts, but not before the parasite has shifted again. It’s as if there’s a door on the surface of the parasite, but it keeps changing the locks so your body never has the right key.
Finally, in stage 3, a few of the merozoites develop into male and female cells. These hang out in your bloodstream, waiting for the next mosquito to come bite you. Once they’re in the mosquito’s stomach, they form new sporozoites, which make their way to the bug’s saliva glands and get injected into the next human, where the cycle starts all over again.
So that is the life cycle of malaria. What does all this mean for the effort to control and eventually eradicate this disease?
You might think we could create a vaccine that simply recognizes all the different shapes of the parasite. Unfortunately, that’s not practical. The only vaccine we have ever done that with is for a type of pneumonia. It is very expensive to manufacture and covers only a dozen shapes or so, versus the 60 shapes in one malaria infection and the many hundreds across all malaria parasites worldwide.
The malaria community (including our foundation) has been working for years on a vaccine to protect you in stage 1, before the infection takes hold. This vaccine, called RTS,S, teaches your immune system to hunt for a bit of protein that is always on the surface of the parasite. Unfortunately, the protection provided by RTS,S is not strong enough for long enough to help us make real headway toward eradication. And there are other forms of protection (such as bednets and insecticides) that are more cost-effective for saving lives.
People often ask me if it’s frustrating to fund work that takes so long to come to fruition. My answer is: not at all. Of course, I’m disappointed that we don’t have a long-lasting vaccine yet. But this is hard work. Parasites are such complex organisms that there are no effective vaccines for any of the human diseases that they cause. Besides, the research on RTS,S has given scientists a lot of insight into how malaria works and new clues about how to stop it. In fact, much of what we know about how your body responds (or fails to respond) to this type of parasite came from research on RTS,S.
The malaria community is now building on this knowledge. For example, scientists are working on new approaches that we hope will trigger the immune system to create long-lived, antibody-generating cells. Another promising idea is to create synthetic antibodies rather than trying to get your immune system to make natural ones. These monoclonal antibodies have revolutionized the treatment of cancer and inflammatory disease, and they could do the same for infectious diseases like malaria.
Knowing how complex malaria is helps me appreciate how much progress the world has made in fighting it. Deaths from malaria have dropped 42 percent since 2000, thanks to investments in bednets that prevent it and medicines that cure it. When I see how far we have come and how much we have learned, I am as optimistic as ever that we can beat this clever shapeshifter.

Disease atlas
These maps could point the way to stopping malaria
We’re using them to maximize scarce resources.
It’s Mosquito Week again on the Gates Notes. This year I’m exploring some of the science behind malaria and other mosquito-borne diseases. You can read below about how maps are revolutionizing the fight against malaria. I’ve also written about how the malaria parasite is a clever shapeshifter and how genetically editing mosquitoes could help us defeat the disease.
Imagine calling the fire department and telling them: “There’s a house burning somewhere in the city!” They ask you for the address or at least some nearby streets, but you’re not sure. Without more specifics, it’s just about impossible for them to help.
For decades, the malaria community has faced a similar problem, but on a national scale. In many of the countries with a lot of malaria, we have had a national estimate of how prevalent it is, but very little reliable information about the breakdown within the country. That means health officials have to distribute bednets across an entire region, hoping to get everyone who might be at risk while also covering people who aren’t.
This problem is especially urgent now. After more than 15 years of steady progress against the disease, the improvement is slowing down. Funding for malaria has also flatlined. If we simply stick with the same tools and the same strategies, progress will stall, and the disease might make a comeback. We need to do more with what we have.
I am happy to report that things are changing, thanks to better data. A combination of new technology and improved systems is helping us target lifesaving interventions in the places where there’s the greatest risk of malaria—making sure that each dollar spent has the biggest possible impact.
I admit that data isn’t as sexy as shapeshifters or the X-shredder. Yet the topic is super-important. It is a big focus for our foundation’s malaria strategy, one of the key things we bring to the table given our interest in technology and innovation. This post will get more in-the-weeds than I usually do on TGN, but if you are as obsessed with malaria as I am, I hope you’ll find it interesting.
Health experts estimate the burden of disease in two ways. One is to use anonymous information collected by health workers. But this information has a lot of gaps and gets aggregated as it moves up the chain from the clinic to the district to the province. This would be roughly equivalent to adding up the cases in every hospital in a U.S. state and only reporting the total. It obscures a ton of local variation, and by the time all the data is processed, the report may be a year out of date.
The other source is surveys. Health workers go out to a community and test a few volunteers for malaria, then repeat this at sites across the country. But this process is expensive and time-consuming, which limits the number of samples a country can take and how often it can take them.
The malaria community is tackling the problem in two ways. A nonprofit called the Malaria Atlas Project (funded by our foundation) started by gathering all the data they could find from every endemic country. They discovered something surprising: Although there were big gaps on the map where we had very little information, overall there was a lot more data than anyone expected.
Using the information they had, along with data on local conditions that affect the spread of malaria (such as the temperature, humidity, and the location of health clinics), MAP started building computer models that give us a much clearer picture of what’s going on.
The results are remarkable. We now have data-rich maps with pixels that are just 5 km square. Instead of blanketing entire regions with bednets and other anti-malaria measures, health officials can target efforts where they will do the most good.
Now comes the next step: getting even better data so we make maps with an even higher resolution. To accomplish this, our foundation and other partners are helping countries strengthen their systems for monitoring disease. In the poorest places, this might mean disaggregating their data and making sure it is accurate and timely. For others, it means equipping health workers with mobile phones or tablets so they can enter the information digitally. More than 60 countries already use the same software to report health data, vastly simplifying the process of collecting and analyzing information.
Below you can see a dramatic example of what the future of mapping looks like. Both are maps of Haiti. The one on the left uses the 5x5 km resolution, built with aggregated data. (Remember, this was already a huge leap forward from national estimates.) The one on the right uses data from individual health facilities to create pixels that are just 1x1 km square. See how much more detailed it is? When you need to maximize scarce resources, this kind of information is invaluable.
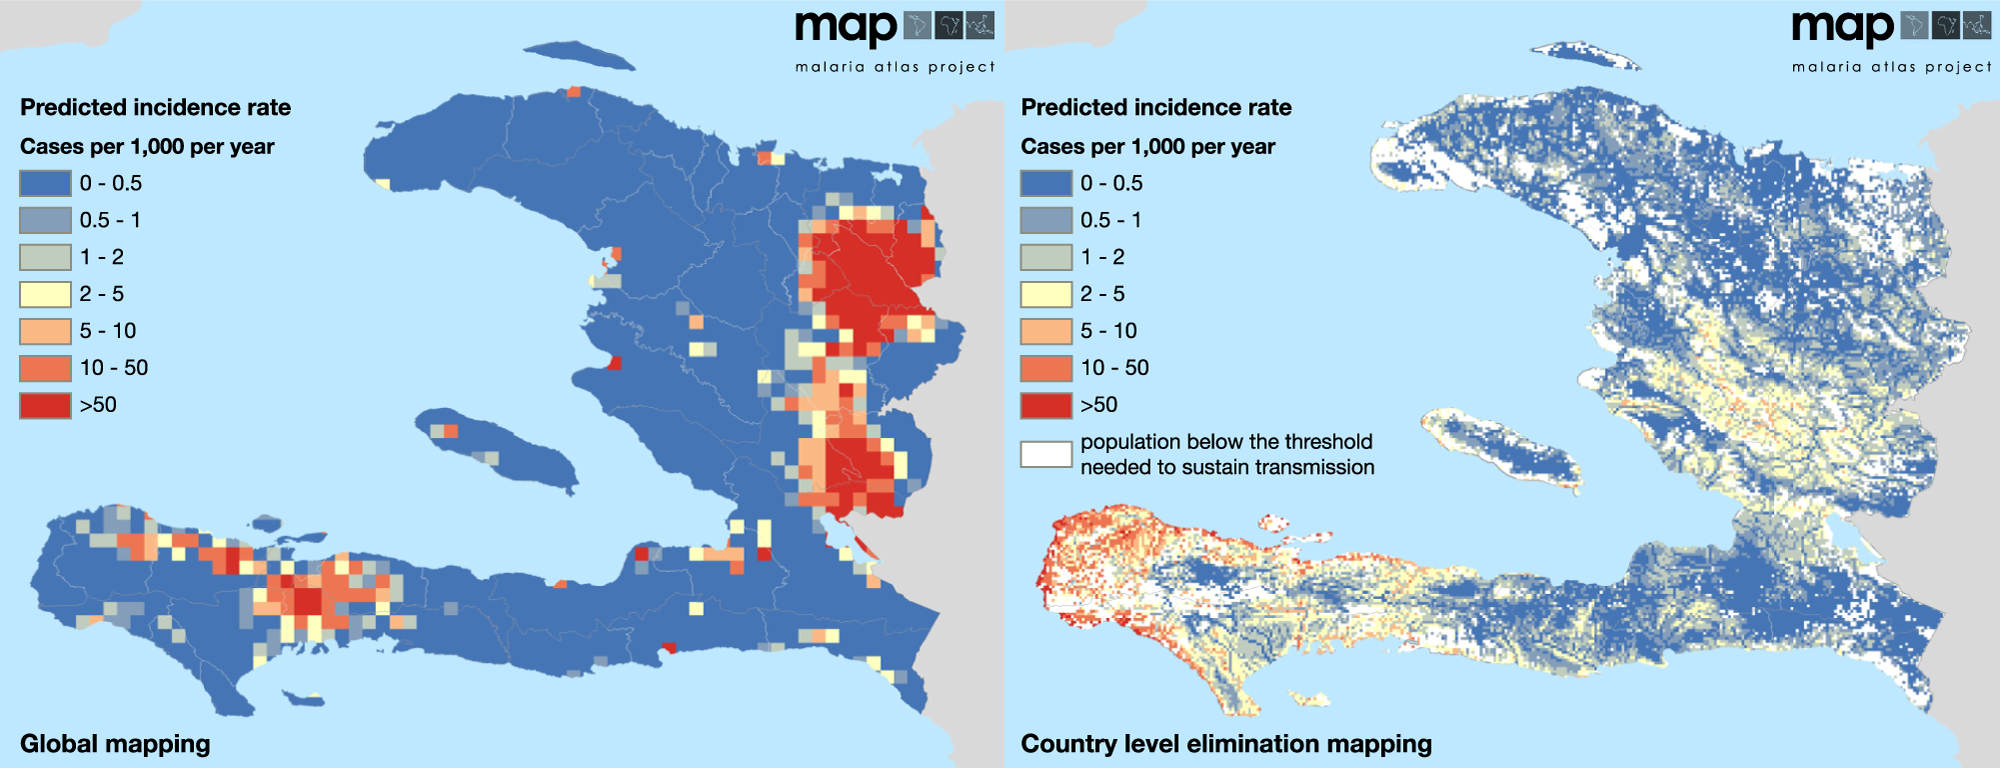
There is more to come. One promising approach uses genetic analysis of the malaria parasite to make the maps even more robust, for example revealing how the disease is transmitted from place to place.
Genetic data is also helping us identify insecticide-resistant mosquitoes and drug-resistant forms of the disease. In Vietnam, health officials recently noticed an alarming spike of cases in one region of the country. Then genetic analysis of the parasite in that region revealed that they were fighting a drug-resistant strain of malaria. They quickly switched to a more effective drug and expect to see the number of cases drop soon.
This kind of work is best done at the local level. So we’re funding programs that help scientists in developing countries do more of this analysis themselves, rather than sending samples off to a lab in the U.S. or Europe. Increasingly, scientists in Senegal, Thailand, and other countries are doing their own analysis, which both speeds up the process and puts local experts in the leading role where they belong.
There is a lot of innovation in the malaria field right now, including work on vaccines and other parasite-killers and a way to fight the disease using test-tube mosquitoes. Better data and malaria maps will help us put all these breakthroughs to their best use, and bring us closer to the day when this disease is gone forever.

Quality of life
What the plow and lab-grown meat tell us about innovation
I was honored to guest curate MIT Technology Review’s 2019 breakthrough technology issue.
I’m a big fan of the MIT Technology Review’s annual list of ten breakthrough technologies—so when they asked me to choose this year’s list, I jumped at the chance. It’s been a lot of fun working on the issue and picking which innovations to include. I think all ten entries will have a significant impact in the years to come, and I’m excited for you to learn more about them.
Here’s the opening essay I wrote for the issue. You can see the full list of breakthrough technologies here.
I was honored when MIT Technology Review invited me to be the first guest curator of its 10 Breakthrough Technologies. Narrowing down the list was difficult. I wanted to choose things that will not only create headlines in 2019 but captured this moment in technological history—which got me thinking how innovation has evolved over time.
My mind went to—of all things—the plow. The plow is an excellent embodiment of the history of innovation. Humans have been using them since 4000 BCE when Mesopotamian farmers used sharpened sticks to aerate soil. We’ve been slowly tinkering with and improving them ever since, and today’s plows are technological marvels.
But what exactly is the purpose of a plow? It’s a tool that creates more: more seeds planted, more crops harvested, more food to go around. In places where nutrition is hard to come by, it’s no exaggeration to say that a plow gives more years of life to people. The plow—like many technologies, both ancient and modern—is about creating more of something and doing it more efficiently, so that more people can benefit.
Contrast that with lab-grown meat, one of the innovations I picked for this year’s TR10 list. Growing animal protein in a lab isn’t about feeding more people. There’s enough livestock to feed the world already, even as demand for meat goes up. Next-generation protein isn’t about creating more—it’s about making meat better. It lets us provide for a growing and wealthier world without contributing to deforestation or emitting methane. It also allows us to enjoy hamburgers without killing any animals.
Put another way, the plow improves our quantity of life, and lab-grown meat improves our quality of life. For most of human history, we’ve put most of our innovative capacity into the former. And our efforts have paid off: worldwide life expectancy jumped from 34 years in 1913, to 60 in 1973, and has reached 71 today.
Because we’re living longer, our focus is starting to shift toward well-being. This transformation is happening slowly. If you divide scientific breakthroughs into these two categories—things that improve quantity of life versus quality of life—the TR10 list from 2009 looks not so different from this year’s. Like most forms of progress, the change is so gradual that it’s hard to perceive. It’s a matter of decades, not years—and I believe we’re only at the midpoint of the transition.
To be clear, I don’t think humanity will stop trying to extend lifespans anytime soon. We’re still far from a world where everyone everywhere lives to old age in perfect health, and it’s going to take a lot of innovation to get us there. Plus, “quantity of life” and “quality of life” are not mutually exclusive ideas. A malaria vaccine would both save lives and make life better for children who might have otherwise been left with developmental delays from the disease.
We’ve reached a point where we’re tackling both ideas at once, and that’s what makes this moment in history so interesting. If I had to predict what the TR10 will look like a few years from now, I bet technologies that alleviate chronic disease will be a big theme. This won’t just include new drugs (although I would love to see new treatments for diseases like Alzheimer’s on the list). These innovations might look like a mechanical glove that helps a person with arthritis maintain flexibility or an app that connects someone experiencing a major depressive episode with the help they need.
If we could look even further out—let’s say the TR10 list 20 years from now—I would hope to see technologies that center almost entirely on well-being. I think the brilliant minds of the future will focus on more metaphysical questions: How do we make people happier? How do we create meaningful connections? How do we help everyone live a fulfilling life?
I would love to see these questions shape the 2039 list, because it would mean that we’ve successfully fought back disease (and dealt with climate change). I can’t imagine a greater sign of progress than that. For now, though, the innovations driving change are a mix of things that extend life and things that make it better. My picks reflect both. Each one gives me a different reason to be optimistic for the future, and I hope they inspire you, too.
My selections include amazing new tools that will one day save lives, from simple blood tests that diagnose cancer to toilets that destroy deadly pathogens. I’m equally excited by how other technologies on the list will improve our lives. Wearable health monitors like the wrist-based EKG will warn heart patients of impending problems, while others let diabetics not only track glucose levels but manage their disease. Advanced nuclear reactors could provide carbon-free, safe, and secure energy to the world.
One of my choices even offers us a peek at a future where society’s primary goal is personal fulfillment. Among many other applications, AI-driven personal agents might one day make your email inbox more manageable—something that sounds trivial until you consider what possibilities open up when you have more free time.
The thirty minutes you used to spend reading emails could be spent doing other things. I know some people would use that time to get more work done—but I hope most would use it for more fulfilling pursuits, like connecting with a friend over coffee, helping your child with her homework, or even volunteering in your community.
That, I think, is a future worth working toward.
The Youngest Continent
Giving the Mandela Lecture
Africa could change faster in the next generation than any continent ever has.
I was 9 years old when Nelson Mandela was sent to prison on Robben Island. As a boy, I learned about him in school, and I remember seeing reports about the anti-Apartheid movement on the evening news. Decades later, I got to meet him and work with him. In person he was even more inspiring than I had imagined. His humility and courage left an impression that I will never forget.
So it was a special honor to be invited to give the Nelson Mandela Lecture in Pretoria, South Africa. I eagerly accepted the invitation and quickly began working on my remarks.
I decided to share my optimism about Africa’s future—to explain why I think the continent has the potential to change faster in the next generation than any continent ever has.
It’s because Africa is the world’s youngest continent, and youth can go hand in hand with a special dynamism. I was 20 years old when Paul Allen and I started Microsoft. The entrepreneurs driving startup booms in Johannesburg, Lagos, and Nairobi are just as young, and the thousands of businesses they’re creating are already changing lives across the continent. The potential will only grow as the digital revolution brings more advances in artificial intelligence and robotics.
But positive change across Africa won’t happen automatically. The real returns will come only if Africans can unleash this talent for innovation in all of the continent’s growing population. That depends on whether all of its young people are given the opportunity to thrive.
It is still an open question, and it is the crux of my speech, which I gave today at the University of Pretoria. It was an honor to give this lecture, and I’m grateful to the Nelson Mandela Foundation and the university for inviting me. You can read my full speech below the video.
Remarks as delivered
Nelson Mandela Annual Lecture
University of Pretoria, South Africa
July 17, 2016
BILL GATES:
Well, thank you. Good evening, ladies and gentlemen. Graça Machel, Professor Ndebele, Vice Chancellor de la Rey, members of the Mamelodi families, friends and dignitaries.
I can’t think of a greater honor than giving a lecture named after Nelson Mandela.
I’m also thrilled that the theme of this lecture this year is “living together.”
It’s truly fitting because in many ways, “living together” was also the theme of Nelson Mandela’s life.
The system he fought against was based on the opposite idea—that people should be kept apart, that our superficial differences are more important than our common humanity.
Today, South Africans are still striving to “live together” in the fullest sense. But you are so much closer to that ideal because Nelson Mandela and so many others believed in the promise of one South Africa.
I was only nine years old when Nelson Mandela was sent to Robben Island. As a boy, I learned about him in school. I remembered seeing reports about the anti-Apartheid movements regularly on the evening news.
The first time I got to speak to him was in 1994 when he called me to help fund South Africa’s election.
I was running Microsoft, and largely focused on software most of the time, but I admired him so much, and I knew the election was historic. So I did what I could to help.
My first trip to Africa had been just the year before that in 1993 when my wife Melinda and I had traveled to East Africa.
The landscape was beautiful, the people were friendly, but the poverty there, which we were seeing for the first time, disturbed us. It also energized us.
Obviously, we knew parts of Africa were poor, but being on the continent turned what had been an abstraction into an injustice we couldn’t ignore.
Melinda and I had always known that we’d give our wealth to philanthropy eventually. But when we were confronted with such glaring inequity, we started thinking about how to take action sooner.
This sense of urgency was further spurred on by another trip in 1997 when I came to Johannesburg for the first time as a representative of Microsoft.
I spent most of the time in the richer part of the city in business meetings, but I also went to the community center in Soweto where Microsoft was donating computers.
My visit to Soweto, which was quite different then than it is now, taught me how much I had to learn about the world outside the comfortable bubble I’d lived in all my life.
As I walked into the community center, I noticed there weren’t any electrical connections. To keep the computer on, the one I was donating, they had rigged up an extension cord connected to a diesel generator outside. I realized the minute I left, the generator would get moved to something more important.
So as I read my remarks about the importance of the technology gap, I knew that it was only a small part of the story. Computers could help people do very important things, and in fact, they are part of how life on the continent can be revolutionized. But computers alone can’t feed disease or cure children. And if they can’t be turned on, they can’t do much at all.
So after that, Melinda and I moved to start our foundation because the cost of waiting had become clear.
Our work is based on the simple idea that every person, no matter where they live, should have the opportunity to lead a healthy and productive life.
We’ve spent the past 15 years learning about the issues and looking for the leverage points where we can do the most to help people seize their opportunity.
It was when I started coming to Africa regularly for the foundation that I got to know Nelson Mandela personally. AIDS was one of the first issues our foundation worked on, and Nelson Mandela was both an advisor and an inspiration.
One thing we talked about was the stigma around AIDS. So I remember 2005 very clearly when his own son died of AIDS. Rather than stay silent about the cause of his son’s death, Nelson Mandela announced it publicly because he knew that stopping the disease required breaking down the walls of fear and shame that surrounded it.
It is important to recall Nelson Mandela’s legacy, and I’m grateful for the opportunity to do so.
But Nelson Mandela was concerned about the future. He believed people could make the future better than the past. And so that’s what I want to focus on for the remainder of my talk.
What can South Africa become? What can Africa become? What can the world become? And what must we do to make it that way?
The Millennium Development Goals adopted by the United Nations in 2000 laid a foundation that enabled the world, including Africa, to achieve extraordinary progress over the last 15 years.
And the Sustainable Development Goals that recently replaced them set even more ambitious targets for creating the better world we all want.
When I talk about progress, I always start with child survival because whether children are living or dying is such a basic indicator of a society’s values.
Since 1990, child mortality in sub-Saharan Africa has been reduced by 54 percent. That means one million fewer children dying each year compared to 25 years ago.
Ten African countries achieved the very ambitious MDG target of reducing child mortality by over two-thirds.
At the same time, the incidence of poverty and malnutrition is down. And though economic growth has slowed in the past few years, it’s been very robust in many African countries for more than a decade.
This is real progress, but the Africa Rising narrative doesn’t tell the whole story about the life on the continent.
First, the progress have been uneven. You know this very well here in South Africa.
In last year’s Nelson Mandela Annual Lecture, the French economist, Thomas Piketty, pointed out that income inequality in South Africa is, quote, “higher than pretty much anywhere else in the world.”
In general, African countries tend to have higher rates of inequality than countries on other continents.And despite healthy average GDP growth in the region, many countries have not yet shared in it. Inequalities exist within countries and between countries.
So until progress belongs to all people everywhere, the real promise of living together will remain elusive.
Second, even with the great progress Africa has made, it still lags behind the rest of the world in most indicators. In sub-Saharan Africa, one in 12 children still die before they turn five. Now, that’s a vast improvement compared to 25 years ago, but African children are still 12 times more likely to die than the average child in the world.
And because rates of poverty and malnutrition aren’t shrinking as fast as the population is growing, the number of people who are poor or malnourished has actually gone up since 1990.
Finally, the progress is fragile. The continent’s two largest economies, here in South Africa and in Nigeria, are facing serious economic challenges. And new threats require attention. The Ebola crisis pointed out weaknesses in many national health systems. The effects of climate change are already being felt among farmers in many countries.
In short, to meet the ambitious goals of the Sustainable Development Goals, Africa needs to do more, do it faster, and make sure everybody benefits. It won’t be easy, but I believe it can be done.
The successes and failures of the past 15 years have generated examples and lessons we can follow. Phenomenal advances in science and technology are expanding the range of solutions available to solve development challenges. And then there is the ingenuity of the African people.
One topic that Nelson Mandela came back to over and over again was the power of youth. He knew what he was talking about because he started his career as a member of the African National Congress Youth League when he was still in his 20s.
Later on, he understood that highlighting the oppression of young people was a powerful way to explain why things must change. There is a universal appeal to the conviction that youth deserve a chance.
I agree with Mandela about young people, and that is one reason I am optimistic about the future of this continent. Demographically, Africa is the world’s youngest continent. And its youth can be the source of a special dynamism.
In the next 35 years, two billion babies will be born in Africa. By 2050, 40 percent of the entire world’s children will live on this continent.
Economists talk about a demographic dividend. When you have more people of working age and fewer dependents for them to take care of, you can generate phenomenal economic growth. Rapid economic growth in East Asia in the 1970s and 1980s was partly driven by the large number of young people moving into their workforce.
But, for me, the most important thing about young people is the way their minds work. Young people are better than old people at driving innovation because they’re not locked in by the limits of the past.
When I started Microsoft at the age of 19, computer science was a young field. We didn’t feel beholden to old notions about what computers could or should do. We dreamed about the next big thing and we scoured the world around us for the ideas and tools that would help us create it.
But it wasn’t just Microsoft. Steve Jobs was 21 when he started Apple. Mark Zuckerberg was only 19 when he started Facebook.
The African entrepreneurs driving startup booms in the Silicon Savannahs from Johannesburg and Cape Town to Lagos and Nairobi are just as young in chronological age, but also in their outlook. The thousands of businesses they’re creating are already changing daily life across the continent.
In a few days, I’ll be meeting with some of these young innovators. People like the 21-year-old who founded Kenya’s first software coding school to provide other young people with computer programming skills. And like the 23-year-old social entrepreneur here in South Africa who manufactures school bags from recycled plastic shopping bags. Besides being highly visible to protect children as they’re walking to school, these school bags sport a small solar panel that charges a lantern during the journey to and from school, providing illumination so students can study at home.
The full returns will come if we can multiply this talent for innovation by the whole of Africa’s growing youth population. That depends on whether Africa’s young people—all of Africa’s young people—are given the opportunity to thrive.
Nelson Mandela said, “Poverty is not natural, it is man made and it can be overcome and eradicated by the actions of human beings.”
We are the human beings that must take action. And we have to decide now because this unique moment won’t last. We must clear away the obstacles that are standing in young people’s way so that they can seize all of their potential.
If young people are sick and malnourished, their bodies and brains will never fully develop. If they are not educated well, their minds will lie dormant. If they do not have access to economic opportunities, they will not be able to achieve their goals.
But if we invest in the right things, if we make sure the basic needs of Africa’s young people are taken care of, then they will have the physical, cognitive, and emotional resources they need to change the future. Life on this continent will improve faster than it ever has. And the inequities that have kept people apart will be erased by broad-based progress that is the very meaning of the words “living together.”
When Melinda and I started our foundation 15 years ago, we asked ourselves: What are the areas of greatest impact? It was clear to us that investing in health was high on the list. When people aren’t healthy, they can’t turn their attention to other priorities. But when health improves, life improves by every measure.
Over the last 15 years, our foundation has invested more than $9 billion in Africa. And we are committed to keep on investing to help Africa.
In the next five years, we will invest another $5 billion.
Some of this money has gone into discovering and developing new and better vaccines and drugs to help prevent infectious disease. We’ve also invested in global partnerships that work closely with countries across the continent to get these solutions to the people who need them most.
We’ve been fortunate to work with amazing partners, and together we’ve seen incredible progress.
For example, the entire continent of Africa has been polio free for two years, which puts us within reach of wiping polio out from the face of the earth forever.
The newest vaccines that protect children from two of the most devastating diseases—pneumonia and diarrhea—are reaching children across Africa at the same time they’re available for children in wealthier countries.
Countries that invest in strong, community-based primary healthcare systems—including Malawi, Ethiopia, and Rwanda—are making great progress reducing child mortality.
Malaria infections and deaths are down significantly thanks to better treatment and prevention tools.
And efforts like the Ouagadougou Partnership in West Africa are helping millions of women get access to contraceptives, which make it easier for them to care for their families.
HIV/AIDS is another area where there’s been good progress. Though it’s a complicated story, and there are still big challenges ahead.
In a few days, I’ll be speaking at the International AIDS Conference in Durban. When the global AIDS community last met there in 2000, only a few thousand Africans were receiving antiretroviral drugs. Today, more than 12 million Africans are on treatment, more than a quarter of them living here in South Africa.
So this is a huge achievement, and millions of lives have been saved. But the rate of new infections remains high. In sub-Saharan Africa, more than 2,000 young people under the age of 24 are infected every single day. The number of young people dying from HIV has increased fourfold since 1990.
We need to get people to get diagnosed, we need people to seek treatment, and people who are on treatment need to be fully adherent.
Along with HIV, we have high rates of tuberculosis, including here in South Africa where TB/HIV co-infection continues to wage a devastating toll.
So we need more creative ways to make testing and treatment accessible and easier to use.
We need to get much more out of existing prevention methods like condoms, voluntary medical male circumcision, and oral anti-HIV medicine.
And we’re going to have to invent new and better preventative solutions like medicines you only have to take once a month or an effective vaccine.
If we don’t act both on today’s treatment and create these tools, the hard-earned gains made against HIV in sub-Saharan Africa over the last 15 years could actually be reversed. Because of the population growth, just doing what we are today is not enough. We need to do more.
Nutrition is another critical area of focus for Africa. Nearly one-third of the continent’s children suffer from malnutrition that stunts their growth and robs them of their physical and cognitive potential. Millions more suffer from micronutrient deficiencies. These are impacts that last a lifetime and impact whole generations of African youth.
African Development Bank President Akin Adesina put it best when he said recently that the greatest contributor to Africa’s economic growth is not physical infrastructure, but gray matter infrastructure, people’s brainpower. The best way to build that infrastructure includes proper nutrition.
Without eliminating malnutrition, we won’t get the great potential that’s there.
We know that when mothers and infants get good nutrition, that breast feeding is a key part of that. We know that certain vitamins and minerals are essential for children.
We have a number of ways to intervene to help nutrition, things like fortified cooking oil, sugar fortified with vitamin A, and sugar and flour enriched with iron, zinc, and vitamin B.
One of the most exciting advances is the breeding of crops so they are naturally more nutritious. For example, when adolescents eat high-iron pearl millet, their likelihood of iron deficiency is reduced six-fold. And just half a cup of biofortified orange sweet potato is all it takes to meet a child’s daily vitamin A needs.
The toll of micronutrient deficiency is huge, but the costs of fighting it are not.
Recent estimates done in Nigeria and Uganda indicate that every dollar invested to reduce stunting returns $17 in greater earning capacity in the workplace.
When children’s bodies and brains are healthy, the next step is an education that helps them develop the knowledge and skills to become productive contributors to society.
Improving education is hard work. I’ve learned this first hand through our foundation’s efforts to create better learning outcomes for primary, secondary, and university students in the United States.
But this hard work is incredibly important. A good education is the best lever we have for giving every young person a chance to make the most of their lives.
In Africa, as in the United States, we need new thinking and new educational tools to make sure that a high-quality education is available to every child.
In Uganda, young innovators at the NGO called Educate! are helping high schools prepare young people for the workplace by teaching students how to start their own business.
And with the high level of mobile phone penetration in Africa, technology using mobile phones to connect to the Internet have the potential to help students build foundational skills while giving teachers better feedback and support.
Globally, the educational technology sector is innovating and growing rapidly and it’s exciting to see new models and tools emerging to meet the needs of educators and students who are not connected to current systems.
At the university level, we need not only to broaden access, we have to also ensure that we have high-quality public universities that will launch the next generation of scientists, entrepreneurs, educators, and government leaders.
South Africa is blessed with some of the best universities in Africa, like the one we’re at today.
For our foundation, we partner with these universities to do our work in health and agricultural research. Maintaining the quality of this country’s higher-education system, while expanding access to more students will not be easy, but it is critical to South Africa’s future.
Other countries in the region will do well to follow South Africa’s example and provide the highest-level university education to the largest number of qualified students.
Healthy, educated young people are eager to make their way in the world. But Africa’s youth must have economic opportunity to channel their energy into progress.
Some of those youths will work in agriculture, where still over half of the workforce toils today.
We need advances to make agriculture far more productive. Today, the seeds that are used are unproductive, the soils are not very good, and so many farmers grow just enough to feed their family.
With climate change leading to more severe weather, doing more of the same will not be good enough.
The key to this is a series of innovation at every step along the way from farm to market.
First, farmers need better tools to avoid disasters and grow surplus. Things like seeds that can tolerate drought, floods, pests, and disease; affordable fertilizers that have the right mix of nutrients to replenish the soil; and easy-to-administer livestock vaccines that can help prevent flocks and herds from being wiped out.
Next, farmers need to be connected to a market where they can buy these inputs at a good price, and sell their surplus, and earn a profit that they can invest not only in their family’s basic needs, but also back into the farm.
This, in turn, will provide employment opportunities both on and off the farm as more prosperous farmers begin to support a range of agribusinesses like seed dealers, trucking companies, and processing plants.
I recently met with a group of young crop breeders, one from Ethiopia, one from Kenya, one from Nigeria, one from Uganda. I really love talking about the science of plant productivity. And in this case, I was amazed at the expertise all of these scientists brought to their work on cassava, a staple crop that provides more than one-third of the calories in many African diets.
Some had ways of improving the nutritional content of cassava. Others were breeding a variety that can resist both of the devastating diseases that are threatening to wipe out the cassava crop.
Our foundation is also working with a young computer scientist from Makerere University who designed a mobile phone app that lets farmers upload a picture of their cassava plants to find out whether it’s infected or not.
These are examples of the kind of innovators who can drive an agricultural transformation across the continent if they have the support they need. For many decades, agriculture has suffered from dramatic underinvestment. Many governments didn’t see the link between their farmers and economic growth.
Now, however, this misconception is gone. And through the Comprehensive African Agricultural Development Program, countries have a framework for transforming agriculture. The investment needs to follow so that young Africans have the means to create the thriving agriculture they envision.
With Africa’s farms as a base, the next step in economic growth is to promote job creation in other sectors. Doing this will require investment in infrastructure including energy.
Seven in 10 Africans lack access to power, which makes it harder to do everything. Harder to get healthcare in a dark clinic. Harder to learn in school when it’s boiling hot. Harder to be productive when you can’t use labor-saving machinery.
Ultimately, a shortage of power, like many African countries—including South Africa—have experienced, is also a drag on economic growth.
Businesses will not invest fully in places where they can’t operate efficiently.
A recent report projected that 500 million Africans won’t have electricity even in 2040. We need to change that.
What Africa needs is what the whole world needs: An energy advance that provides cheap, clean energy for everyone.
I’ve spent a lot of my time in the last two years working on this issue because it’s such an important advance. I’m involved with a group of business people who are collaborating with governments to not only increase energy R&D, but also to vastly increase the private investment in this area.
I get angry when I see that Africa is suffering the worst effects of climate change, although Africans had almost nothing to do with causing this.
The rich countries need to follow through on their commitment to double their energy R&D budgets so that we get the breakthroughs that are applicable globally, and we need to do that urgently.
Africa needs power now. And so there are many pragmatic steps we need to take even in advance of these new inventions.
In parts of Africa, there’s hydro and geothermal sources which are both reliable and renewable that can be exploited. There’s been a lot of work on small-scale grids and the use if micro solar. This approach can provide individuals with electricity for basic purposes, but we also need large-scale power including well-managed electrical grids.
It means organizing the power system so that it’s economic, so that the electronic bills are paid for, and so that the network is reliable 100 percent of the time.
Once we get economic viability for these utilities, then it bootstraps the economy. It allows investments that are job creating.
So there are many challenges that I’ve laid out here: Challenges in health, education, agricultural productivity, energy, and creating enough job opportunities.
These advances only happen in the context of governments that function well enough to enable them. I applaud initiatives like Mo Ibrahim’s Annual Index of African Governments, which looks objectively at multiple measures of government performance in each country on the continent.
Citizens in other regions would be well served by this kind of comprehensive effort to spotlight and spread effective governance.
A lot can be accomplished by focusing on fiscal governance and accountability. Here in South Africa, the government gets strong marks for the budget information it provides to the public.
The International Budget Partnership, an independent monitoring organization, also ranks South Africa highly for its oversight of government spending.
In some countries, individual citizens are leading the way. In Nigeria, 30-year-old Oluseun Onigbinde gave up a career in banking years ago to devote himself full time to pulling back the curtain on the Nigerian federal expenditure.
With savvy use of data and social media, he founded BudgetIT Nigeria, which provides facts and figures the average Nigerian can understand. No doubt, he’s a thorn in the side of some of Nigeria’s elite, but to me he’s an example of what one person can do to make a difference.
Governments have an opportunity not only to learn from what’s been done in the past, but to do things in new ways. One of the exciting prospects is the role they can play in accelerating use of digital technology to leapfrog traditional models and costly infrastructure associated with banking and delivery of government services.
By using mobile phones, tens of millions of people are already storing money digitally and using their phones to make purchases as if they were debit cards.
A good example of this is M-PESA in Kenya. These services don’t just give people a better way to move money around, they give people a place to save cash to fund a startup of a micro enterprise or pay a child’s school fee. They create informal insurance networks of friends and families who can help with unexpected shocks. And they increase the profitability of small businesses by lowering transaction costs, making it easy to order products and supplies, and having greater security of financial assets.
A digital financial connection can also help governments deliver services more efficiently. Studies from India show the government able to save tens of billions a year by connecting households to a digital payment system and automating all government payments.
The early evidence suggests that similar programs in Africa can also yield substantial benefits. For example, recent research in Uganda showed that providing people with digital cash transfers rather than direct food subsidies not only saved the cost of delivery, it also improved nutrition because recipients used the money to purchase a greater diversity of foods and to space out meals as needed.
Governments can accelerate this digital transformation by implementing policies that encourage commercial investment, innovation, and healthy competition.
Countries like Kenya, Tanzania, and Nigeria are already investing in the building blocks of this new digital financial platform. And I believe they’ll see substantial positive returns.
If there’s one thing I’m sure of, it’s this: Africa can achieve the future it aspires to.
That future depends on the people of Africa working together across economic and social strata and across national borders to lay a foundation so that Africa’s young people have the opportunities they deserve.
Recently, I had a meeting with students at Addis Ababa University. I started asking them the kinds of questions you would ask college students in the United States like, “What do you want to do after you graduate? What fields are you thinking of going into?”
They looked at me like I was kind of crazy for asking those questions. Each of them had a plan for their future. They felt their parents had sacrificed for decades so they could go to this university. They weren’t weighing their options, they had come to the university to get specific training, and they were eager to take that training and use it to make their country more prosperous.
They saw themselves as part of a large community with great needs.And they were going to dedicate themselves to serving that community by meeting those needs.
I see that sense of purpose when I come to Africa, and especially when I talk to young Africans. I think it’s a unique asset that people see the need to change and that they want to give back.
The students here believe not only in themselves, they also believe in their countries and the future of the continent. Our priority is to make sure they have the opportunity to turn those beliefs into action because young people with this sense of purpose can make the difference between stagnation and faster progress.
Nelson Mandela said, “Young people are capable, when aroused, of bringing down the towers of oppression and raising the banners of freedom.” But our duty is not merely to arouse, our duty is to invest in these young people, to put in place the basic building blocks so they can build the future.
And our duty is to do it now because the innovations of tomorrow depend on the opportunities available to children today.
I’m sure it’s clear to everyone that these are big and complicated challenges. But it’s just as clear that people with bravery, energy, intellect, passion, and stamina can face big, complicated challenges and overcome them.
There is so much more work to be done to create a future in which we can all live together, but there are also so many people who are eager to get to work.
Let’s do everything within our power right now to help build the future that Nelson Mandela dreamed of and the future that we will achieve together.
Thank you.
Ring the alarm
The next epidemic is coming. Here’s how we can make sure we’re ready.
I was honored to be asked to give this year’s Shattuck Lecture.
Four years ago, the world was stunned by the Ebola outbreak in West Africa. Panic broke out all over the globe. Governments scrambled to contain the infection. By the time the last patient tested negative for the disease, the outbreak claimed thousands of lives and caused billions of dollars in economic losses.
The 2014 Ebola outbreak was a stark reminder of how vulnerable our society is to epidemics of infectious diseases. We weren’t ready then, and we’re still not ready now—but we can be. We don’t know when the next epidemic will strike, but I believe we can protect ourselves if we invest in better tools, a more effective early detection system, and a more robust global response system.
When the Massachusetts Medical Society asked me to deliver this year’s Shattuck Lecture, I knew I wanted to talk about epidemic preparedness. I was honored to address their annual meeting earlier today. Here is the full text of my prepared remarks:
BILL GATES:
Thank you, Dr. Drazen, for that kind introduction. It’s an honor to be invited to deliver the Shattuck Lecture.
Most of the speeches I give on global health are about the incredible progress and exciting new tools that are helping the world reduce child mortality and tackle infectious diseases. Thanks to better immunization and other interventions, child mortality has been reduced by more than 50 percent since 1990. We are on the verge of eradicating polio. HIV is no longer a certain death sentence. And half the world is now malaria-free.
So usually, I’m the super-optimist, pointing out that life keeps getting better for most people in the world.
There is one area, though, where the world isn’t making much progress, and that’s pandemic preparedness. This should concern us all, because if history has taught us anything, it’s that there will be another deadly global pandemic.
We can’t predict when. But given the continual emergence of new pathogens, the increasing risk of a bioterror attack, and how connected our world is through air travel, there is a significant probability of a large and lethal, modern-day pandemic occurring in our lifetimes.
Watching Hollywood thrillers, you’d think the world was pretty good at protecting the public from deadly microorganisms. We like to believe that somewhere out there, there is a team ready to spring into action – equipped with the latest and best technologies.
Government agents like Jack Bauer in 24. Harvard professors like Robert Langdon in Inferno. And WHO epidemiologists like Dr. Leonora Orantes in Contagion – who even risked getting kidnapped as she pursued “Patient Zero.”
In the real world, though, the health infrastructure we have for normal times breaks down very rapidly during major infectious disease outbreaks. This is especially true in poor countries. But even in the U.S., our response to a pandemic or widespread bioterror attack would be insufficient.
Several things in the last decade have made me pay closer attention to the risk of future pandemics. One was the outbreak of Swine Flu in 2009. While H1N1 wasn’t as lethal as people initially feared, it showed our inability to track the spread of disease and develop new tools for public health emergencies.
The Ebola epidemic in West Africa four years ago was another wake-up call. As confirmed cases climbed, the death toll mounted, and local health systems collapsed. Again, the world was much too slow to respond.
And, as biological weapons of mass destruction become easier to create in the lab, there is an increasing risk of a bioterror attack.
What the world needs – and what our safety, if not survival, demands – is a coordinated global approach. Specifically, we need better tools, an early detection system, and a global response system.
Today, I’d like to speak with you about some of the advances in tools – vaccines, drugs, and diagnostics – that make me optimistic we can get a leg up on the next pandemic. And I’ll talk about some of the gaps we must address in preparedness and response.
Interestingly, the first Shattuck Lecture – given back in 1890 – focused on a pandemic . . . the Russian flu that struck Massachusetts the previous year. The Russian flu was not especially deadly. But it was the first flu pandemic to spread across continents connected by rail travel – and between continents connected by fast ocean liners. The virus circled the globe in just four months.
But the world was soon in for much worse. Less than 30 years later, the Boston area was one of the first places in the U.S. to feel the deadly effects of the 1918 flu. Military personnel getting off and on ships at the Commonwealth Pier – near where we are meeting today – helped carry the pathogen across the U.S. and back to the battlefields of World War I.
This animation shows how quickly the virus spread across the United States. It took five weeks and killed 675,000 people.
The death toll was so great that average life expectancy in the U.S. for that period dropped by 12 years.
Worldwide, the 1918 flu killed an estimated 50 million people, perhaps more.
We have better tools today than we did a century ago. We have a seasonal flu vaccine, although it’s not always effective, you have to get one every year, and most people in the world never get the shot. We also have antibiotics for secondary infections of bacterial pneumonia.
Despite these advances, this animated simulation by the Institute for Disease Modeling shows what would happen if a highly contagious and lethal airborne pathogen – like the 1918 flu – were to occur today.
Nearly 33 million people worldwide would die in just six months.
That’s the sobering news. The good news is that scientific advances and growing interest on the federal level, in the private sector, and among philanthropic funders makes development of a universal flu vaccine more feasible now than 10 or 20 years ago.
Our foundation is involved in a variety of research partnerships, including a collaboration between the Icahn School of Medicine at Mount Sinai, GlaxoSmithKline, and PATH.
Their work focuses on several vaccine candidates that did well in animal trials and which are now in human trials.
We are also supporting efforts by others, including the National Institute of Allergy and Infectious Diseases, whose vaccine candidate is expected to advance to human safety trials in about a year.
To broaden efforts even further, today we are launching a $12 million Grand Challenge in partnership with the Page family to accelerate the development of a universal flu vaccine. The goal is to encourage bold thinking by the world’s best scientists across disciplines, including those new to the field.
Lucy and Larry Page are also supporting efforts by the Sabin Vaccine Institute to encourage innovative approaches that eliminate the threat of a deadly flu pandemic.
However, the next threat may not be a flu at all. More than likely, it will be an unknown pathogen that we see for the first time during an outbreak, as was the case with SARS, MERS, and other recently-discovered infectious diseases.
The world took an important step last year to begin addressing this risk with the launch of a public-private partnership called the Coalition for Epidemic Preparedness Innovations (CEPI).
With funding commitments of more than $630 million, CEPI’s first order of business is advancing the development of vaccines for three of the priority diseases on the WHO list for public health R&D: Lassa fever, Nipah virus, and Middle East Respiratory Syndrome.
CEPI is also working on rapid-response platforms to produce safe, effective vaccines for a range of infectious diseases – almost as quickly as new threats emerge. Later this year, CEPI will announce grants to several companies working with a variety of technologies – including nucleic acid vaccines, viral vectors, and other innovative approaches. The goal is to be able to develop, test, and release new vaccines in a matter of weeks or months, rather than years.
I’m a big fan of vaccines, but they may not be the answer when we have to respond immediately to rapidly spreading infectious disease pandemics. Not only do vaccines take time to develop and deploy; they also take at least a couple of weeks after the vaccination to generate protective immunity. So, we need to invest in other approaches like antiviral drugs and antibody therapies that can be stockpiled or rapidly manufactured to stop the spread of pandemic diseases or treat people who have been exposed.
Earlier this year, the Shionogi pharmaceutical company received approval in Japan for a new influenza anti-viral, Xofluza This single-dose drug stops flu in its tracks by inhibiting an enzyme that the virus needs to multiply.
And PrEP Biopharm, a development stage biopharmaceutical company, has demonstrated in human challenge studies that pre-activating the innate immune response through intranasal delivery of a double-stranded viral RNA “mimic” can prevent both influenza and rhinovirus.
Since the host’s innate immune response is non-virus specific, such an approach has the potential to offer protection against other types of respiratory viruses as well.
Monoclonal antibody therapies have also made incredible advances in the last couple of decades, leading to several products for cancer and autoimmune diseases. During the Ebola outbreak in West Africa several years ago, researchers were able to identify and test a promising combination of monoclonal antibodies to treat infected patients.
And a growing pipeline of broadly neutralizing antibodies are being discovered in some individuals exposed to infectious diseases. For example, a small percentage of people infected with HIV develop antibodies with high potency and breadth of coverage sufficient to protect against many strains of the virus. The same is true for some people infected with the flu.
Different sets or cocktails of these exceptional antibodies may protect against a pandemic strain of a virus even if it has genetically evolved. It is conceivable that we could create libraries of these antibodies, produce manufacturable seed stocks, and have them ready for immediate use in an outbreak—or ready to scale up manufacturing if a pandemic ensues. If we can learn how to use RNA or DNA gene delivery effectively, we may not need to make the antibodies at all.
Rapid diagnosis is also critical, especially at the beginning of an outbreak when quarantine, treatment, and other public health measures are most effective. To that end, researchers at the Broad Institute and at UC-Berkeley have developed a highly-sensitive point-of-care diagnostic test that harnesses the powerful genetic engineering technology known as CRISPR.
But instead of using CRISPR to edit DNA, they have programmed an associated protein called Cas13 to hunt for specific pieces of RNA. When Cas13 locates the relevant genetic sequence, it releases a signal molecule that indicates the presence or absence of the target.
In a paper published yesterday in the journal, Science, the Broad researchers highlighted the field-use potential of this new diagnostic. Using paper strips similar to a pregnancy test – and with minimal sample processing – the diagnostic can check a patient’s blood, saliva, or urine for evidence of a pathogen.
What’s more, it can test for multiple pathogens at once. It could, for example, identify if someone is infected with Zika or dengue virus, which have similar symptoms.
There are also some interesting advances that leverage the power of computing to help predict where pandemics are likely to emerge and model different approaches to preventing or containing them.
Over the last few years, researchers at the Institute for Health Metrics and Evaluation at the University of Washington have developed a sophisticated computer model that combines data from dozens of sources with geospatial mapping to predict the pandemic risk of infectious diseases.
They recently looked at the pandemic potential of four viral hemorrhagic fevers in Africa – including Ebola. Their analysis confirmed that Guéckédouprefecture in Guinea – where the West African Ebola outbreak originated – was indeed one of the most likely places where an individual Ebola case could lead to a widespread epidemic.
The research also pinpointed dozens of other African communities that are at high risk of outbreaks of hemorrhagic fevers.
Meanwhile, researchers at the Institute for Disease Modeling are pushing the boundaries of computational epidemiology to provide a deeper understanding of both the spread of infectious diseases and the effectiveness of different control and eradication strategies.
In the effort to eliminate malaria, for example, IDM is combining surveillance data with computational modeling to tailor antimalarial efforts to unique local conditions. They are also using quantitative analysis and modeling to evaluate various control strategies for HIV, TB, and to eradicate polio. This kind of research could provide valuable information to help predict disease transmission and identify prevention measures and intervention tactics for epidemics and pandemics.
At the Munich Security Conference last year, I asked world leaders to imagine that somewhere in the world, there is a weapon that exists – or that could emerge – that is capable of killing millions of people, bringing economies to a standstill, and casting nations into chaos.
If this were a military threat, the response – of course – would be that we should do everything possible to develop countermeasures. In the case of biological threats, that sense of urgency is lacking.
The world needs to prepare for pandemics the way the military prepares for war. This includes simulations and other preparedness exercises so we can better understand how diseases will spread and how to deal with things like quarantine and communications to minimize panic.
We need better coordination with military forces to ensure we can draw on their mobilization capacity to transport people, equipment, and supplies on a mass scale.
We need a reserve corps of trained personnel and volunteers, ready to go at a moment’s notice. And we need manufacturing and indemnification agreements in place with pharmaceutical companies –with expedited review processes for government approval of new treatments.
Last month, Congress directed the administration to come up with a comprehensive plan to strengthen global health security – here and abroad. This could be an important first step if the White House and Congress use the opportunity to articulate and embrace a leadership role for the U.S. in global health security.
No other country has the depth of scientific or technical expertise that we do – drawing on the resources of institutions like the NIH, the CDC, and advanced research organizations like DARPA and BARDA.
Our biopharmaceutical industry is the global leader in biomedical innovation. And, on the world stage, the U.S. is an influential member of international forums like the UN, the WHO, the G7, and the G20.
The point is that the U.S. can and should play a leadership role in creating the kind of pandemic preparedness and response system the world needs.
As I said at the start, I’m fundamentally an optimist, and that gives me hope that we can get prepared for the next big pandemic.
The global community eradicated smallpox, a disease that killed an estimated 300 million people in the 20th century alone.
We are on the verge of eradicating polio, a disease that 30 years ago was endemic in 125 countries and that paralyzed or killed 350,000 people a year.
And today, nearly 21 million people are receiving life-saving HIV treatment, thanks primarily to the support of the world community.
America’s global HIV initiative, PEPFAR, was the catalyst for world action on the AIDS crisis. It’s an example of the kind of leadership we need from the U.S. on a broader effort to make the world safer from other infectious disease threats. With strong bipartisan support, PEPFAR has saved millions of lives and shown that national governments can work together to address pandemics.
Somewhere in the history of these collective efforts is a roadmap to create a comprehensive pandemic preparedness and response system.
We must find it and follow it because lives – in numbers too great to comprehend – depend on it.
Thank you for the opportunity to address you today.
Buzz Kill
Could this be the first country in sub-Saharan Africa to defeat malaria?
Swaziland’s success fighting malaria can teach the world valuable lessons.
In the tiny African kingdom of Swaziland*, one of the most effective tools in the fight against malaria is a telephone number: 977.
When someone tests positive for the mosquito-borne disease at a Swazi clinic, a nurse immediately dials those three digits to report the case to the country’s national emergency response center. The call triggers a text message to the national malaria program team, which dispatches investigators—armed with computer tablets that have built-in satellite maps and GPS software—to interview the patient and test all people living within a one-kilometer radius of their home. A separate team is called in to reapply insecticide to the walls of homes in the community to help protect other families from infection.
Such vigilance is one of the reasons why Swaziland may become the first malaria-free country in sub-Saharan Africa, where most malaria deaths occur.
Swaziland’s well-coordinated malaria program—including a robust surveillance and control system—has helped reduce the number of cases in the country by more than 90 percent since 2002. Now, Swaziland aims to eliminate malaria entirely within its borders by 2020.
Swaziland’s bold goal is evidence of the incredible progress the world has made against malaria. Between 2000 and 2015, the combination of increased donor investment, strengthened political commitment, and new tools (including artemisinin combination therapies, rapid diagnostic tests, indoor residual spraying, and insecticide-treated bed nets), led to a 60 percent decline in malaria deaths.
At the same time, the difficulties Swaziland has experienced trying to become malaria free are a sobering reminder of the challenges the world faces to reach its goal of eradicating the disease. While the number of malaria cases in Swaziland has fallen to just a few hundred cases each year, tackling those final cases is more difficult than anyone imagined. Swaziland thought it would eliminate the disease by the end of 2015, and again by the end of 2017, but each time fell short of its goal. Last year, Swaziland saw its number of malaria cases rise sharply.
Globally, progress in the malaria fight has stalled. Further progress is in peril given the plateauing funding levels which make it impossible to fill remaining gaps in prevention and treatment of malaria and address the challenges of drug and insecticide resistance. After years of dramatic declines in malaria cases and deaths, the world is starting to lose ground. In 2017, the World Malaria Report showed that for the first time in years the number of malaria cases went up.
These setbacks should not lead to despair. They should serve as a wake-up call. As I told health officials at the Malaria Summit in London last week, the world needs a new strategy to meet the challenges ahead. That means developing innovations that will keep driving down malaria cases and malaria deaths, while tailoring interventions to address the specific needs of a country or region.
Swaziland is a good example of how countries can adapt their malaria control strategies to meet their unique circumstances. One of Swaziland’s biggest challenges is the cross-border movement of people infected with the disease from outside the country. Mozambique, Swaziland’s next-door neighbor, has one of the highest malaria burdens in the world. Workers from Mozambique may come into Swaziland with malaria. And when Swazis go to Mozambique, they sometimes return with the disease, which can then be passed on to their neighbors. Unpredictable weather also poses a challenge. The sudden spike of new cases last year was driven by heavier rainfall in the region, resulting in more mosquito breeding.
Swaziland and Mozambique are part of the Elimination 8 regional malaria elimination effort, which aims to wipe out malaria from eight countries in southern Africa. Last year, as part of that effort, Swaziland and Mozambique set up malaria posts along their border. As people go back and forth between the two countries, they are offered malaria tests and treatment to help prevent the importation of new cases. Since the posts were set up last year, thousands of people have been tested and treated and the national malaria program is optimistic that the number of cases will fall this year as a result.
At the same time, Swaziland remains committed to the painstaking work of investigating every new malaria case and responding swiftly to reduce the chance the disease will spread. The country also organized intensive media campaigns to warn residents and travelers of the danger of malaria and teach them how to protect themselves. Malaria diagnosis and treatment are free to everyone in private and public clinics.
I look forward to hearing more about Swaziland’s progress in the months ahead. If successful eliminating malaria within its borders, Swaziland can achieve a major milestone toward a goal once thought impossible—making Africa malaria free. I hope to see many more countries follow its lead.
* Just before I posted this, King Mswati III of Swaziland announced that the name of the country was changing to the Kingdom of eSwatini. In order to avoid confusion, I’ve used Swaziland in this post.
Out for blood
This animal kills more people in a day than sharks do in a century
I’m bringing back Mosquito Week on the Gates Notes.
Mosquitoes keep me up at night.
If you ask someone about what things scare people the most, there’s a list of usual suspects: shark attacks, heights, enclosed spaces, etc. Mosquitoes usually don’t make the cut—but they frighten me more than almost anything else.
This fear might be a bit irrational in Seattle, where I live. Our climate is too mild for the types of mosquitoes that harbor serious diseases. In other parts of the world, however, families have good reason to be afraid. Mosquitoes and the diseases they carry kill more than half a million people every year. Consider this mind-blowing statistic:
Of all the illnesses mosquitoes spread, malaria is the worst by far. More than 200 million people suffer from it every year, and a child dies from malaria every other minute of every day. If you survive, it can leave you vulnerable to other debilitating diseases and chronic anemia. It’s an awful, painful disease (I wrote about what it feels like to have malaria a couple years ago).
Melinda and I encounter a lot of suffering through our work, but one of the worst things I’ve ever seen is a child having seizures from cerebral malaria in Tanzania. I will never forget watching his small body twist in agony, as his parents waited to find out if he would survive. I wouldn’t wish that experience on anyone.
So why exactly are people more afraid of sharks than mosquitoes? The late Hans Rosling would argue that humans are hardwired to fear things that cause us physical harm. This instinct is practical if you live in poverty (on level 1 or 2), where an animal attack is more likely to kill you. But if you can afford life-saving healthcare, it can distort your perception of how significant a threat really is.
Even if you know that you’re 50,000 times more likely to get killed by a mosquito than a shark, human instinct wins out. A photo of a shark attack victim on the evening news evokes a visceral reaction, because the threat is obvious. A picture of a malaria victim in a hospital ward doesn’t trigger our fear instinct in the same way.
Despite this, I’m determined to spread the word about mosquitoes—which is why I’m bringing back Mosquito Week here on Gates Notes.
Everything I’m posting this week is dedicated to my least favorite pest. You can read some good news about a country that hopes to eliminate malaria by 2020. You can see how the bed nets the Mozambique Ministry of Health and World Vision distributed last year on behalf of the Gates Notes Insider community are making a difference. I’m going to be talking about mosquitoes on my social channels all week, and I hope you’ll join the conversation.
As long as Hollywood keeps making blockbusters about sharks, I’ll keep talking about why everyone should be more scared of a tiny bug than a 3,000-pound carnivore. Jaws is nothing compared with the flying terror that is a mosquito.
Covered
Net impact
Learn how a new, long-lasting mosquito net is helping save lives in the southern African country of Mozambique.
The world is making incredible progress against malaria. New innovations—including more effective drugs for treatment, rapid diagnostic tests, and better insecticides—have helped prevent more than 600 million cases of malaria and saved 6.8 million lives between 2000 and 2015. One new tool that helps protect families in Africa is a long-lasting type of bed net. Learn more about the impact these bed nets are having in the southern African country of Mozambique.
Fourteen-month-old Judite Luis battles malaria (and complications from malnutrition) at Chicuque Rural Hospital in Inhambane, Mozambique with her mother, Adozinda Augusta, at her side. Malaria is the leading cause of death among children under 5 in Mozambique. Judite died the day after this photo was taken.
A boy points out the holes in an old mosquito net used in his home. While the older generation of bed nets helped protect families from malaria in Mozambique, they had some downsides. They needed to be soaked in insecticide every six months and didn’t stand up to repeated washings when they got dirty, leading to tears that mosquitoes could fly through.

In November, thousands of families in Inhambane, Mozambique lined up to receive long-lasting insecticidal mosquito nets from the Mozambique Ministry of Health’s National Malaria Control Program and World Vision partnership. The nets protect people from mosquitoes for three years and can even be washed when they get dirty. (The bed net donation was made possible, in part, by the participation of Gates Notes readers in a bed net giveaway campaign last year. Thanks for your help!)

Clayton Pedro Albert, age 6, and his 11-month-old sister, Sharmila, go to bed under one of the long-lasting insecticidal nets. “There is no malaria in this house this year. Last year, it was so many times,” said Carolina Alberto, their mother. Across Mozambique, World Vision, in partnership with the Ministry of Health, has distributed more than 21 million bed nets. Ensuring families use their new bed nets is critical for controlling malaria. World Vision follows up with households to show families how to hang and care for their nets and remind them of the importance of sleeping under them every night.

Silvina Jorge Mahoche and her daughter, Celineza Mahoche, share their new insecticidal net. The Mahoche family has had malaria more times than they can remember. What they don’t forget are the painful symptoms: “A fever, chills, joint pain, headaches, and vomiting,” Silvina said. Since receiving the net last year, no one in the family has been sick from malaria.

Villagers return home after receiving new mosquito nets. Ensuring communities have universal coverage of nets and follow up to ensure appropriate use is critical to achieving malaria control and elimination. Some mosquitoes are now developing resistance to the pyrethroid insecticides used in bed nets—so researchers are working on next generation nets that use combinations of insecticides and appear effective against all mosquitoes, including insecticide-resistant ones. Much more work needs to be done to eliminate malaria in Africa, but continued innovation in bed nets and other tools will ensure that the world will continue to make progress against this deadly disease.

Safety first
Foreign aid keeps Americans safe
The strategic case for fighting disease and poverty abroad.
You may have seen in the news that elected officials in Washington, D.C., are working on next year’s federal budget. One of the ideas that has been floated is to make deep cuts in foreign aid—the investments that America makes to help other countries fight poverty and disease.
That would be a big mistake.
For one thing, these programs amount to less than 1 percent of the federal budget. For anyone worried about the budget deficit, cutting 1 percent will not make a dent.
More importantly, these programs give American taxpayers a phenomenal return on investment, one of the best anywhere in government. They do this in three ways:
- Making Americans safer and the world more stable
- Creating jobs at home and promote trading partners that will buy American goods
- Saving lives and building up health systems so other countries can take better care of their people
Together these three points make what you might call the strategic case for aid—the argument that aid helps the countries that give it as well as those that receive it.
To be honest, the strategic case is not what prompted Melinda and me to get involved in this work more than 17 years ago. We were moved by what you could call the moral case: the idea that it is terribly unjust that people in poor countries—especially children—die of diseases that can be prevented. That is still the main thing that drives us today. But over the years we have come to see the compelling strategic case too. And we have found that people often support aid who aren’t convinced by the moral argument but are by the strategic one.
In this post I want to focus on point #1 above. I’ll come back to #2 and #3 in subsequent posts.
Let’s look at how promoting health and development keeps Americans safe.
Preparing for the next epidemicYou may remember the Ebola epidemic of 2014–16. It killed more than 11,000 people in three West African countries. Each of those deaths was a tragedy, but the epidemic could have been far worse. If it had spread to neighboring Nigeria, home to more than 180 million people and a busy international travel hub with daily flights to the world’s capitals, it would have been very hard to contain. It could have easily jumped the Atlantic and infected Americans, and spread throughout Europe or Asia.
Why didn’t that happen? One key reason is that a number of health workers were stationed in Nigeria as part of the global campaign to stamp out polio. As the Ebola epidemic took hold, they were quickly reassigned from polio to Ebola. They already had a system in place for identifying possible cases, tracking them, and reporting the data to people organizing the response. They helped contain the disease and keep it from spreading farther than it did.
The polio eradication program helped stop Ebola and saved countless people, including Americans. Its biggest public funder? The United States government.
In addition, Ebola may have been only a preview of what is to come. The next epidemic—say, a virulent flu as bad as the Spanish Flu of 1918—could be far worse. Epidemiologists estimate it could kill 30 million people, more than three times the population of New York City.
Funding from the U.S. government helps keep that from happening. It helps other countries strengthen their health systems so they can identify dangerous diseases and contain them before they get out of control.
It is no accident that the Ebola epidemic hit hardest in three countries—Guinea, Sierra Leone, and Liberia—with especially weak health systems. Helping them improve makes it more likely that we can prevent a worldwide epidemic that destabilizes entire regions of the world and kills tens of millions of people.
Stabilizing vulnerable countriesPreventing pandemics is one specific way that U.S. funding makes Americans safer. There is also a broader point here: by fighting poverty and disease, we make the world a more stable place.
For example, both evidence and common sense tell us that when people don’t have reliable food supplies, they will pick up and move someplace else—becoming migrants or refugees—and that leads to more instability. Look at the countries with the least reliable food supplies in the world: Sudan, South Sudan, Eritrea, Burundi. Each of them is either at war or recently emerged from conflict.
Syria is another tragic example. In 2007, the country suffered the worst drought in its history. More than 1 million people fled rural areas for the cities, where they hoped to find food. This migration stoked political tensions and created the foundation for the horrific civil war that continues today. Of course that war has many causes, and not every drought-stricken country will become another Syria. But it is clear that the world is not a safer place when more people are going hungry—and that when we strengthen food and farming systems, we tackle some of the root causes of migration and instability.
Improving health is another way to make countries more secure. One of my favorite all-time examples is PEPFAR, the program America launched in 2003 to stop the spread of AIDS. Today it provides life-saving medicine for more than 11 million people living with HIV in some of the world’s poorest countries. Those 11 million people are teachers, health-care workers, and police officers—people who build strong, self-sufficient societies. So it should not be surprising that in countries where PEPFAR has a presence, political instability fell by 40 percent between 2004 and 2013. In non-PEPFAR countries, it dropped only 3 percent. And the PEPFAR countries grew three times faster.
Shoring up national securityAmerican military leaders understand that fighting poverty and disease is part of a smart national-security strategy. It was true after World War II, when the United States invented modern development assistance to combat instability in Europe and prevent a third World War, and it’s true today. The more stable poor countries are, the lower the odds that America will need to intervene in them.
More than 120 retired generals and admirals recently wrote a letter to Congress arguing that U.S. aid programs “are critical to preventing conflict and reducing the need to put our men and women in uniform in harm’s way.” While he was the head of U.S. Central Command, overseeing American operations in Syria, Pakistan, Afghanistan, and elsewhere, Secretary of Defense James Mattis said: “If you don’t fully fund the State Department”—which houses many aid programs—“then I need to buy more ammunition.”
Aid is an important part of our broad diplomatic and security relationships. Out of 135 countries that receive some health or development aid from the United States, we have bilateral defense agreements with 131 of them.
These are some of the arguments I have been making in Washington on behalf of American aid. In future posts I will explain how aid not only keeps Americans safe, but also creates jobs in the United States and helps other countries become more self-sufficient. All reasons why I believe this money is well-spent and ought to be maintained.
360⁰ of Connection
South Africa: Virtually There
Travel with me to South Africa to see how the country is hoping to win the fight against AIDS.
If you could shuffle all of the homes in the world like a deck of cards so that people in wealthy countries lived side by side with people from poor countries, it would transform the world’s fight against poverty, hunger, and disease. It would be impossible for people to look away, impossible for them not to help.
I was naïve about the deep poverty in the world until I took my first trip to Africa with Melinda in 1993. Seeing the disparities with our own eyes made all the difference and inspired us to start our foundation.
Since then, I’ve continued to travel regularly to Africa, India, and other parts of the developing world. I always return from my trips humbled and inspired. My one disappointment is that I wish everyone could have seen what I did. I have no doubt it would help more people become aware of the challenges the world’s poorest people face. It would also leave them as optimistic as I am about the incredible progress the world is making in health and development.
During my trip to South Africa in July, I tried something new that I hope will allow people to experience what I have. I had highlights of my visit recorded in virtual reality. It’s still an emerging technology but what excites me about it is that it allows viewers to immerse themselves in another world. You can look up and down. Turn right or left. Listen to sounds all around you. I used to think there was no substitute to being there and seeing things for yourself. But virtual reality is a close second. It fulfills my dream of allowing people to see what I’m seeing and, perhaps, feel what I’m feeling, too.
In this video, you will hear the stories of young women living with HIV. Sit beside me as I drive from the leafy suburbs of Johannesburg to the dusty township of Soweto. Feel what it’s like to be in the center of a stomping gumboot dancing troupe. And be inspired by the power of South Africa’s youth, who will drive the next generation of innovations to create a future free of AIDS.
If you want to know more about my trip to South Africa, you can read about my visit here and here. I also encourage you to learn more about The Global Fund, which has helped provide lifesaving treatment to millions of people living with HIV.
Thanks for watching and look out for more virtual reality videos in the months ahead.
John Green in Ethiopia
“It was invigorating and encouraging. And sad.”
The bestselling author reflects on our visit to Ethiopia.
I was playing bocce with a close friend recently when he told me, “I can’t bring myself to watch any of your videos about Ethiopia.”
Now, I don’t care if my friends watch my videos or read my books; I don’t know much about their jobs and don’t expect them to know much about mine. But the specificity of the comment surprised me, so I asked him why, and he said, “Well, it’s all just so SAD.”
I understand it: It’s difficult to look directly at suffering. And the challenges of our own lives can be so overwhelming that at times it feels like there’s no room left to consider the vast and tangled challenges of absolute poverty. We have to look away. “It’s too much,” my friend said.
But my visit to Ethiopia wasn’t sad—at least not merely so. It was invigorating and encouraging. And sad. And by being unable to look away—at least for a short time—I had the opportunity to listen to extraordinary people who’d brought tremendous positive change to Ethiopia.
The successes of the past twenty years are truly unprecedented in human history: Child mortality in Ethiopia has dropped by two thirds. Agricultural yields are improving. More kids are in school, and more of those kids go on to attend college.
Those are all very encouraging developments, but for narratively oriented people like me, it can be hard to internalize statistics until you see what this change looks like for individuals and families. At the rural health care outposts I visited, women told me about how radically the health care options for their children had improved. It was easier to get vaccines and antibiotics and rehydration solutions. Fewer of their kids were dying of malaria and pneumonia. Better family planning options allowed them to make choices about when to have kids. And while every mother I spoke to had been born at home, almost all of their kids had been born in a health care facility.
Maternal death is still far too common in Ethiopia, and infant mortality is still far too high. Ethiopia is a nation of 90 million people with just seven neonatologists. There are no CT scanners or MRI machines. Most of the people I met walked for miles twice a week to get water. And people die, every day, of easily preventable and treatable illnesses. But Ethiopia is also a nation with a growing middle class and an increasingly educated population (the University of Addis Ababa now has more than 40,000 students).
When we assume that stories about developing world countries will be merely sad, we do ourselves a great disservice, because the truth—as Oscar Wilde put it—is rarely pure and never simple. I emerged from my time in Ethiopia feeling not discouraged but energized. I was energized by people like Bill Gates and Sue Desmond-Hellmann, whose focus and commitment were inspiring. But mostly, I was energized by the parents and students and health workers I met in Ethiopia, who have helped bring radical improvement to their communities. There is, of course, so much still to do. But we shouldn’t look away or feel discouraged. We should get to work.
Africa’s Table
Why does hunger still exist in Africa?
Not starving, but still hungry in Africa.
When I first started traveling to Africa, I would often meet children in the villages I was visiting and try to guess their ages. I was shocked to find out how often I guessed wrong. Kids I thought were 7 or 8 years old based on how tall they were—would tell me that they were actually 12 or 13 years old.
What I was witnessing was the terrible impact of malnutrition in Africa. These children were suffering from a condition known as stunting. They were not starving, but they were not getting enough to eat, leaving them years behind in their development—and it was hard to see how they could ever catch up.

Stunting not only affects a child’s height. It also has an impact on brain development. Stunted children are more likely to fall behind at school, miss key milestones in reading and math, and go on to live in poverty. When stunted children don’t reach their potential, neither do their countries. Malnutrition saps a country’s strength, lowering productivity and keeping the entire nation trapped in poverty.
Worldwide, one in four children is stunted. Three-quarters of them live in South Asia and sub-Saharan Africa. However, while stunting has declined by more than a third in South Asia since 1990, in sub-Saharan Africa, the number of stunted children is still on the rise, up 12 million since 1990 to 56 million. Forty percent of all children in sub-Saharan Africa are stunted.
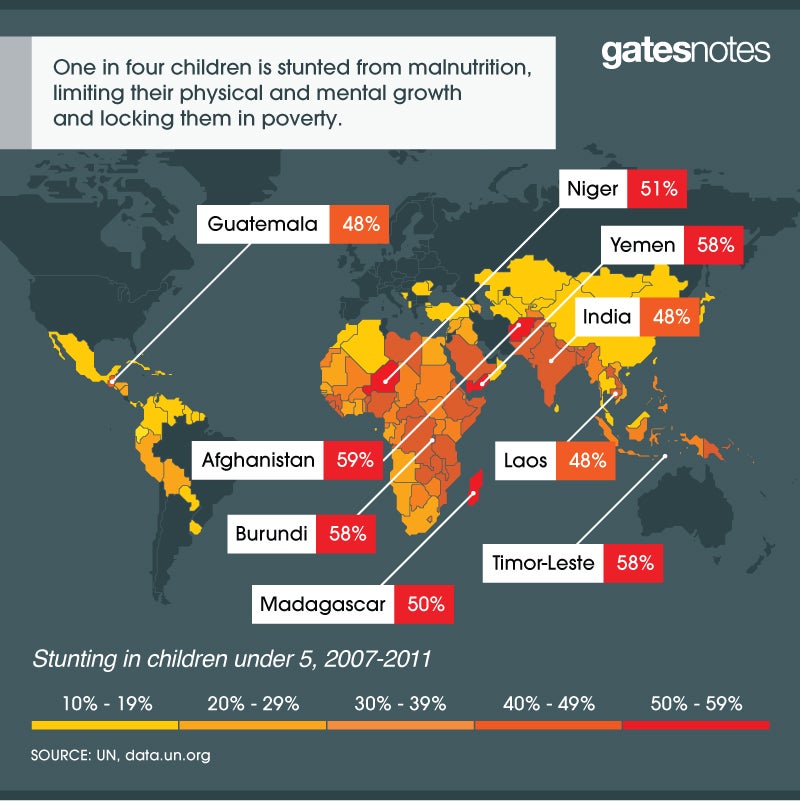
I run into a lot of people from rich countries who still think of Africa as a continent of starvation. The fact is, that’s an outdated picture (to the extent that it was ever accurate at all). Thanks to economic growth and smart policies, the extreme hunger and starvation that once defined the continent are now rare. As I saw when I was back in Africa last month with best-selling author John Green, today the issue isn’t quantity of food as much as it is quality—whether kids are getting enough protein and other nutrients to fully develop.
As Melinda and I have grown aware of the scale of this challenge, we’ve made improving nutrition a bigger priority for our foundation. One thing we’ve quickly come to appreciate is the problem’s complexity. There’s no vaccine to prevent stunting. Proper nutrition involves eating enough food, and the right kinds, every day of your life. While the global health community is still working to understand all of the causes and solutions to malnutrition, we do know a lot about how to ensure children get the nutrition they need for a healthy start to life.
We know that getting children the right nutrition in the first 1000 days—from the start of a woman’s pregnancy until her child’s 2nd birthday – is the best down payment on their future, giving them the opportunity to grow and develop physically and mentally. We also know that exclusive breastfeeding in the first six months of a child’s life is the single most effective intervention to help the brain develop and protect against life-threatening diseases. That’s why we continue to research the best ways to address cultural beliefs and other barriers that have kept almost half of all women from using optimal breastfeeding practices.
We know kids have a hard time getting the nutrients they need when fruits, meats, and vegetables are in short supply—so fortifying staple foods like cooking oil, flour, and salt with essential vitamins and minerals can fill the gap. We’re also beginning to develop new crops that are more-nutritious--including a sweet potato that’s enriched with vitamin A—and also produce a higher yield. Not only does this help smallholder farmers earn more income that can be used to diversify their family’s diet, it also puts more nutritious food directly on their table.
Providing better health care can make a difference too. Children who receive the rotavirus vaccine, for example, have fewer bouts of diarrhea, which can drain kids of vital nutrients and make them more susceptible to infection. Likewise, clean water and sanitation play a role in improving nutrition by reducing illness and disease.
We have many great interventions on our side, but with so many factors at play it can be difficult to measure which interventions have the most impact on improving nutrition and why. If I could have one wish, I would want the world to have a better understanding of malnutrition and how to solve it.
We have much more research to do in this area and we will continue to make progress. But what’s not in doubt is the importance of giving all children the nutrition they need for a healthy start to life. Their future depends on it. So does Africa’s.
Africa’s Table
Increasing awesome in Africa with John Green
John Green quizzes me on philanthropy, Ethiopia, and helicopters in Africa.
I didn’t know much about YouTube star John Green until a few months ago when my kids told me about his best-selling novel The Fault in Our Stars. It’s a deeply moving and, at times, surprisingly funny story about two teenagers with cancer who fall in love.
Later, I watched some of John’s video blogs and Crash Courses and was really impressed. People my age may not be John’s target audience, but I could quickly understand why millions of teens flock to his books and videos. One night I sat down to look at one of his online courses and then suddenly realized more than an hour had gone by as I watched John tackle complex ideas in history, biology and other subjects.
What impresses me most about John is his courage to ask tough questions—about cancer, the conflict in the Central African Republic, even how giraffes have sex—and then answer them in a way that is entertaining while at the same time super informative.
I asked John to come on part of my recent trip to Africa and found he was a terrific traveling companion. In Ethiopia, we visited health posts helping to vaccinate kids living in remote areas of the country; discussed the challenges of agriculture in Africa with a group of small farmers; and had an amazing conversation about growing up in Ethiopia with students at Addis Ababa University.
We also helped John conquer his fear of flying in a helicopter (though I’m not sure telling him how much safer it is than riding a motorcycle really convinced him).
As you can see in these videos, John’s endless curiosity was one of the highlights of our travels together. At every stop, he asked thoughtful questions about tackling poverty, getting young people involved in philanthropy, and tapping the power of storytelling to change the world.
So John, thanks for the great conversations and the company. I never thought of fighting poverty and disease as decreasing world suck and increasing awesome, but you convinced me that it’s as good a description as any other.
A Generous Turnout
Behind the scenes at the Vaccine Summit
We reached a critical milestone in the race to eradicate polio.
As I mentioned in an earlier post, last week I attended the first-ever Global Vaccine Summit in Abu Dhabi. In the months leading up to the conference, we weren’t at all sure how successful it would be. Budgets are tight. How much would governments and donors be willing to contribute?
In the video above, I talk about how things turned out.
I want to especially thank these seven private donors, who came together at the Summit to contribute $335 million to help eradicate polio.
- His Royal Highness Alwaleed Bin Talal (Alwaleed Foundation)
- Michael Bloomberg (Bloomberg Foundation)
- Ray Dalio (Dalio Family Foundation)
- Carl C. Icahn (Foundation for a Greater Opportunity)
- Carlos Slim (Fundación Carlos Slim Helú)
- Dato Tahir (Tahir Foundation)
- Albert L. Ueltschi Foundation
With these and other commitments, including $1.8 billion from the Gates Foundation, we raised $4 billion, which is enough to vaccinate more than 1 billion children against polio and other diseases over the next five years. That’s phenomenal—it’s more than 70 percent of the funding we’ll need for the plan we rolled out at the Summit to free the world of polio by 2018. Now we need to finish the job by raising that final 30 percent. When we eradicate polio—and I’m confident that we will—it will be a critical milestone in the Decade of Vaccines, a vision to reach all children with the vaccines they need by 2020.
Off to a Great Start
Global Vaccine Summit: We Changed History
The Summit was a big success.
I want to share with you my excitement over the outcomes of the Global Vaccine Summit in Abu Dhabi to celebrate the huge progress we’ve made toward ending polio and protecting all children with life-saving vaccines. The Summit was a big success.
World leaders including health and political ministers from Afghanistan, Nigeria and Pakistan, EU President Jose Manuel Barroso and former UNSG Kofi Annan appeared alongside polio survivors and vaccine heroes like Ade Adepitan, a British Paralympic medalist who contracted polio as a child in Nigeria, and Sikha Patra and Salim Shekh, two kids from India who organize polio immunizations for their community in Calcutta.
We had an amazing cross-section of participants, including community leaders like the Sultan of Sokoto from Nigeria and Rotarian Deepak Kapur from India, industry representatives, and leaders from our organizing partners UNICEF, GAVI, WHO and GPEI. Although he couldn’t attend, Archbishop Desmond Tutu, a polio survivor, also added his voice to the gathering.
We were also in Abu Dhabi to have some frank discussions on what still needs to be done to reach our ambitious goals.
And I’m proud to say that collectively, we changed history. The Global Polio Eradication Initiative rolled out a new strategy to achieve a polio-free world by 2018. Global leaders demonstrated their confidence in the six-year plan by pledging their financial and political commitments to help ensure its success.
In all, we raised a total of $4 billion dollars. That’s close to three-quarters of the plan’s projected $5.5 billion cost over six years, and enough to protect more than one billion children from polio forever.
Countries like Norway, Canada, Germany, Ireland, and the UK made generous pledges, as did His Royal Highness the Crown Prince of Abu Dhabi. The $4 billion also includes $335 million from private philanthropists such as Carlos Slim, His Royal Highness Alwaleed Bin Talal, and Mayor Michael Bloomberg. The foundation stepped in with $1.8 billion, a third of what’s needed for the polio campaign.
The Summit pledges are a huge step towards a fully funded plan, and I hope that financing won’t be the thing that stands in the way of achieving the miracle of polio eradication.
Collectively, we sent a powerful message that the world remains committed to fulfilling the vision of the Decade of Vaccines to end polio and reach all children, no matter where they live, with the vaccines they need.
Waste Management
Why we’re talking to scientists about toilets
Melinda and I encouraged scientists to innovate to help the poor.
Melinda and I spoke earlier today at the National Academy of Sciences, a non-profit group that has advised the nation on important scientific matters for 150 years. The NAS has roughly 2,200 members, all scientists at the top of their respective fields. About 200 of them have Nobel prizes.
Naturally, I took the opportunity to talk about toilets. Of course I also mentioned vaccines and other life-saving scientific advances. Melinda talked about the benefits of contraception and agriculture. But I put special emphasis on our Reinvent the Toilet Challenge, because it’s a great example of one of our biggest priorities: encouraging scientists to focus on the problems of the poor.
Scientific advances like the microprocessor and new medicines have been key in lifting millions of people around the world out of poverty. In my lifetime, extreme poverty has been cut in half. So have the number of people who don’t have safe drinking water, and the number of mothers who die during childbirth.
But we can do even better. There are many life-saving discoveries that don’t reach the developing world. Or they aren’t tailored to meet the needs of the poor to begin with. The toilet for example has been essentially the same technology for 200 years, and it requires infrastructure like sewage systems that are out of reach for much of the world. That leads to open defecation and other problems—and 1.5 million children who die each year from contaminated food and water. So Melinda and I made the case for finding more ways to make sure the poor are among the first, rather than the last, to benefit from scientific progress.
Why the National Academy of Sciences? Because it’s a group that represents one of the greatest resources we have in fighting poverty and disease: brainpower. Material scientists can make big advances on the next-generation toilet. Geneticists can develop new seeds that help farmers grow more nutritious food and raise their incomes. Energy researchers can create cheaper, cleaner forms of energy to meet the growing demand for it in the developing world.
Here are some specific ways we’re trying to use the power of science to benefit the poor:
Reinventing the Toilet
Many of us in the rich world take toilets for granted. But today 40 percent of the world’s population doesn’t have access to them. Instead they resort to open defecation, which contaminates water and food supplies, killing 1.5 million children a year. Unfortunately, today’s toilets require complex sewer infrastructure that won’t work in many of these settings. So we need to design affordable toilets that work in these communities.
Last year eight universities participated in a Reinvent the Toilet Challenge. We held a fair to celebrate the winner, and I got to award prizes to the top three winners. It probably says something about me that I really had fun handing out prizes for toilet designs.
SCUBA Rice
In her speech, Melinda talked about the importance of providing farmers with new seeds. One example of this is the effort to develop new varieties of rice that can thrive in areas of Asia and Africa, where rice yields are historically much lower than other parts of the world because of flooding, drought and poor soils. Partners from around the world are working to create rice that can “hold its breath” underwater.
Grand Challenges
In 1900, the German mathematician David Hilbert sparked a century of innovation in mathematics by identifying the 23 problems in that field that most needed solving. That’s the model for the Grand Challenges in Global Health. A panel of scientists has identified 16 challenges that, if solved, could lead to breakthrough advances for the developing world. They include everything from making vaccines that don’t have to be refrigerated to preventing mosquitos from transmitting malaria.
Midwife Calling
Ghana: Mobile technology for global health
Mobile phones keep midwives and patients connected.
In Ghana, the Grameen Foundation is using mobile applications to improve the quality of maternal health and childcare. With the MOTECH Mobile Midwife program, pregnant women can register and receive voice messages that provide reliable advice for a health pregnancy. Smartphones are also used to record health services delivered.
Texting Immunity
Mozambique: Mobile Technology for Global Health
Text messaging has increased immunization rates in Mozambique.
In Mozambique, Margarida Mathshinhe and VillageReach use text messaging to improve routine immunization. VillageReach deployed the Dedicated Logistics System (DLS) to increase the scale and efficiency of vaccine delivery to children living in rural areas.
First, Celebrate
Not Your Typical Vaccine Conference
This week I'm going to Abu Dhabi to attend the Global Vaccine Summit to celebrate the tremendous progress the world has made in ending polio and immunizing children.

This week I’m going to Abu Dhabi to attend the Global Vaccine Summit to celebrate the tremendous progress the world has made in ending polio and immunizing children.
This isn’t going to be typical conference. We aren’t going to have breakout sessions or canvas bags crammed with printed reports to take home. We’ll be there to do just two things: first, celebrate the progress we’ve made in the Decade of Vaccines to reach all kids, everywhere, with the vaccines they need; and second, to share best practices and have some frank discussions on what still needs to be done. As part of that, the Global Polio Eradication Initiative will roll out a new strategy to end polio once and for all. Global leaders will discuss their confidence in the plan and pledge political and financial commitments to help ensure its success.
Why Abu Dhabi? His Highness General Sheikh Mohamed bin Zayed bin Sultan Al Nahyan, Crown Prince of Abu Dhabi, is joining UN Secretary-General Ban Ki-moon and me to host the Summit, the first of its kind. The Crown Prince, an important partner of the foundation across several issues, represents to me the inspirational leadership we are seeing from the Middle Eastern and Islamic communities to improve child health worldwide.
In my talk, I’m going to share some of the numbers that impress me, such as the measurement systems that have allowed Ghana to build a strong immunization system. And I’ll share numbers that make me angry. For example, a child born in a low-income country is 18 times more likely to die before reaching the age of five compared to a child in a high-income country—largely due to preventable causes. That inequity is simply unacceptable and completely fixable.
I’m excited to meet some pretty amazing heroes while I’m there, too. World leaders like Jose Manuel Barroso and Kofi Annan will appear alongside Ade Adepitan, a British Paralympic medalist who contracted polio as a child in Nigeria, and Sikha Patra and Salim Shekh, two kids from India who organize polio immunizations for their community in Calcutta. I get to meet the two winners of my annual Gates Vaccine Innovation Award, too. Archie Panjabi will be our emcee. She appears on the American series The Good Wife and is using her celebrity to be a strong advocate for ending polio.
Thousands of people—scientists, investors, health experts, community leaders—share involved in the process of immunizing a child. We need to have the right vaccines, developed and manufactured at affordable prices, delivered to the hardest-to-reach children. It is crucial to build up strong routine immunization systems to protect our gains against polio and provide a platform for primary care. When the world comes together, we can set ambitious goals, we can measure our progress, and we can achieve even more. I’m counting on the Global Vaccine Summit to do just that.
No "One Size Fits All"
Putting HIV Patients at the Center
The lessons I drew from my visit to a clinic in South Africa.

Experts have long recognized that there is no “one-size-fits-all” approach to HIV services. The features of the global HIV epidemic vary by country, often by community and patient, and it’s important to understand these distinctions so that we can design programs to meet people’s needs and strengthen their access to treatment and prevention.
A few months ago, I had the opportunity to meet Craig Househam, who heads the Department of Health in the Western Cape, one of South Africa’s nine provinces. We talked about how his department is delivering health care to the thousands of people living with HIV in the townships and rural areas surrounding the city of Cape Town. I was really impressed with the approach that Professor Househam and his team have created in the Western Cape, and I want to share some of the lessons that I think can be drawn from it.
One thing that the system does well is to tailor the support provided to each HIV patient by offering different tiers of engagement with the health system.
In many countries, all HIV patients are expected to have the same level of engagement with the health system, regardless of their needs. That generally means monthly medical appointments with a doctor or high-level nurse at a central hospital. For many people living far from facilities, these trips often take an entire day due to lengthy travel and significant wait times. For the majority of patients who are generally healthy and responding well to their medications, this level of engagement with the healthcare system may be burdensome and actually discourage patients from remaining in care. For others with more complicated cases, this standardized level of care may be insufficient.
In the system in the Western Cape, healthy patients who are adhering to their anti-retroviral (ARV) treatment can pick up their medicine every two months from local service organizations rather than from a central hospital or clinic. Qualified pharmacists sort and package the medications, and then they are delivered to patients by mid-level healthcare workers rather than doctors or nurses. This lets people access quality services in their own neighborhood, reducing the burden on them and on the health system overall. To ensure that people are staying healthy and not developing resistance to their treatment, the Western Cape schedules everyone for an annual clinical exam with a highly qualified nurse. If there are problems, patients are immediately referred to a doctor for further examination.
I was also impressed by how the Western Cape collects the data required to understand which level of engagement is appropriate for the individual patient. They are phasing out their paper-based records and adopting an electronic health record that creates individual e-files for patients and links their lab results, hospital records, and other information under one file that can be accessed wherever an individual seeks care.
Why am I so excited about this approach?
First, this system takes into account the specific needs of the individual receiving care. By providing patients only the level of care they need, it leaves them more time to devote to their jobs, their families, and their communities.
Second, it enhances the impact of scarce healthcare resources—financial, human, and technical. By reducing the cost and effort while still keeping thousands of people healthy, it frees up resources that can be directed toward more specialized care for those who need it—or toward expanding access to treatment for those who don’t have it.
Third, the Western Cape’s approach uses smart IT solutions to meet patients’ clinical needs and providers’ logistical needs. It is preparing the way for an even more efficient, patient-focused health records system that can facilitate a better managed HIV treatment system at a lower cost to the public. This is especially important in countries like South Africa, where many patients might be on the move; electronic records can follow a patient much more easily than paper ledgers.
Approaches like these remain critical in our efforts to turn the tide on HIV. We have made huge progress against HIV in the past decade, thanks in no small part to programs like PEPFAR and the Global Fund for AIDS, Tuberculosis, and Malaria. The cost of ARV medicines has fallen by more than 99 percent, and more than eight million people now have access to lifesaving treatment. But we still face a situation where only half of all people who could benefit from HIV treatment are actually receiving it. And that means we have a moral obligation to be smarter about how we organize treatment programs so that people in treatment are able to live longer and so that fewer people die for lack of access to treatment.
Tracking Immunization
Seeing Ghana’s Health Care System in Action
I saw a healthcare system tracking and using data to great effect.

I got to spend two days in Ghana this week. It was my first visit there, and the time was really productive and inspiring. I got to watch an effective health system in action – from the decision makers at the national level to nurses who live and work in the villages.

I had heard that Ghana’s health system thrived on tracking information but I didn’t realize until I got there that it has an entire culture of data. Every immunization is carefully documented in the mother’s green booklet that tracks the health care of each child, as well as recorded in large registry books. That data moves up the chain to the sub-district and district levels. This kind of rigor may sound obvious, but in many places I’ve traveled, recordkeeping is so erratic that health workers don’t know how many babies live in their area of service, much less whether they’ve had all of their shots.

I met Patricia Antwi, district director of health services in Awutu Senya, about an hour’s drive north of Accra. Every month she gathers all of the sub-district heads to validate and pressure test their data with each other. Then every quarter all of the district leaders in her region meet and do the same. They track their work and adjust their planning and decision making based on such data as patient visits, products delivered and used, and immunization coverage rates. They openly debate what they have measured to help each other improve. They admit when it doesn’t go as well as it should.

Many of us are looking at potential digital strategies for record-keeping, but paper is pretty good.
The energy and commitment of the well-trained nurses was obvious. Alice Grant Yamoah runs the community health compound in the village of Ahentia. She lives in the heart of the community with three colleagues. A couple of days a week they go out in to the villages to treat or immunize children when their mothers don’t bring them in. Alice showed me how to give six-week-old Fredrick his rotavirus vaccine. Luckily for Fredrick these are drops that are fairly easy to administer. Still, both Fredrick and his mother were patient with someone doing it who clearly was less experienced than Alice and her colleagues.

There is a lot to learn from Ghana’s successes – but the most important in my mind is that countries need to have a really strong primary health care system that includes immunization as well as maternal and child health, malaria treatment and prevention, and other things that protect children and their families. It was a strong reminder to me that health is the magic lever. If you make progress there, it will help with all other things.
I’m a huge believer in the Millennium Development Goals, and I was also struck in Ghana over how important they are in helping drive focus and progress in the right places and in the right ways.
After visiting the clinics, I had the opportunity to meet with President John Dramani Mahama, who came into office in January. I was impressed by his strong focus on the MDGs. President Mahama and his ministers have a clear sense for where there has been great progress and where they still need to drive improvement.
The MDGs have really helped Ghana’s leaders focus their efforts, develop effective plans and measure their progress. Mahama was very clear about the good strides they have made in hunger and poverty as well as child mortality and education. He was equally candid about where they must redouble efforts to hit their targets in the areas of maternal health and sanitation. They still have a ways to go, but what’s exciting is that they have a strong direction and a solid plan to accelerate progress.
Going for GMOs
Farmers deserve options
Farmers have started hearing about GMO seeds, and they all want them.
This article by Sam Dryden, Director of Agricultural Development, Bill & Melinda Gates Foundation, was first printed on March 6, 2013, on the Impatient Optimists blog.
It is an exciting time to be working in agricultural science: we are seeing developments in crop research that are transforming farmers’ lives: tools that allow farmers to adapt and survive environmental challenges, and innovations that mean farmers can grow and eat more food so they are healthier and more productive.
Throughout my career developments in science have come hand in hand with criticisms and sometimes rejections of new research or scientific breakthroughs. While critical dialogue is important, the debate is only constructive when based on evidence instead of dogma.
Unfortunately, in one area of agricultural science, GMOs, many of the arguments have often steered towards dogma. So, it was refreshing when at the beginning of the year, a once outspoken anti-GMO activist, Mark Lynas, apologized for the myths he had helped create about biotechnology. He apologized for the scare tactics he and his peers had used to fill tabloid headlines and the trespassing and destroying of crop research he had led. He admitted—in a compelling speech to the Oxford Farming Union—that his previous views were “anti-science”. Once he had devoured the peer-reviewed articles and scientific data, he acknowledged the inconsistency between his position on climate change and his rhetoric around GMOs.
Most important of all, he apologized for contributing to depriving poor farmers of valuable, potentially lifesaving technology used successfully by most of the rich world.
It is this point that I feel most passionately about. What is so often missed in the debate about GMOs is choice: the choice for a poor farmer to consider planting a maize crop which could cope with droughts that are becoming ever more frequent; the choice to grow rice that provides the nutrition her child needs to prevent blindness; or put simply, a choice that we in the west take for granted.
Whether the tool being developed is produced by the latest technology or a more traditional approach, giving farmers access to solutions that deliver more productive or more nutritious crops, should be a decision based on scientific debate and research.
As in medicine, the development of new products should undergo rigorous safety reviews, guided by national regulatory bodies. Instead of arguing about the role of biotechnology in agriculture (interestingly, genetic engineering has produced insulin for diabetics without any alarm or calls for a complete ban), we should concentrate on ensuring that products—whether they are new seeds or new vaccines—are safe and effective.
Once proven (and so far, GMOs have been proven safe and effective), the use of these tools must be a choice for farmers to make. And farmers are choosing GMOs in their millions: GMO crops are the fastest growing technology (in the US, in Brazil, in India, Argentina) – because when farmers have access to more productive, less resource intensive crops, they seize the opportunity.
Since Bt Cotton (insect resistant) was introduced to Indian farmers in 2002, this GM cotton has grown to now account for approximately 90% of all cotton grown. During this past cropping season in India, roughly 6 million small holder farmers planted over 8 million hectors of insect resistant cotton.
The environmental impact, in the US alone, has been huge—cotton farmers have been able to cut back from 10 to 12 sprays per season to one. That’s less spraying of chemicals, less toxic agents impacting on the wildlife, marine life and on the children walking through fields. The same is possible throughout the developing world.
It is not just GM technology that is delivering positive results, innovations in conventional breeding are also benefitting small holder farmers. Our partners at the International Rice Research Institute in Bihar, India developed Stress Tolerant Rice for Africa and South Asia (STRASA). This new rice can survive up to 20 days underwater so when rains flood their fields, farmers are now getting twice the yield compared to the old rice variety. The impact on farmers’ lives is enormous—in a flood year, they have seen their incomes double.
STRASA has reached 3 million rice farmers in South Asia. But that’s just the beginning. Farmers have started hearing about these seeds, and they all want them. In the next six years, we expect 20 million farmers to plant these new varieties.
By adopting new technologies (whether it is genetic modification, conventional breeding or any other approach) farmers are making a loud statement about the importance of choice to them. However, their voices are rarely heard in this debate.
Hopefully soon it won’t be old hats like myself or Vandana Shiva arguing anymore, but the young scientists and farmers themselves who are seeing the benefits of all the tools in the box.
It is time to share their stories with the rest of the world. I urge you all to step forward and make your voices heard.
CIMMYT
Mexico will lead innovation in agricultural development for the world
Mexico is at the forefront of advances in agricultural development to help poor countries become food self-sufficient.
Building on its success a half-century ago pioneering new varieties of wheat and maize that saved a billion people from starvation, Mexico is again at the forefront of advances in agricultural development to help poor countries become food self-sufficient.
Combining the latest breakthroughs in agricultural science and farming practices with digital technology, Mexico’s innovative efforts will enable even the poorest farmers to grow and sell more crops.
Against the dramatic realities of climate change, a growing global population, rising food prices, and a shrinking agricultural land base, Mexico’s leadership in agricultural innovation is critically important—especially to the countries of Sub-Saharan Africa where hundreds of millions of people face severe hunger and poverty.
At the center of these efforts is Centro Internacional de Mejoramiento de Maíz y Trigo (CIMMYT), where Mexican and international researchers have worked for decades to develop higher-yielding, more resilient seeds for maize and wheat, and to introduce better agricultural practices that help farmers be more productive. One of CIMMYT’s greatest strength is its partnership approach. In addition to bringing together the world’s leading scientists and agricultural experts, CIMMYT has also involved farmer associations, the private sector, governments, international organizations, and NGOs in developing effective solutions to meet the needs of poor farmers worldwide.
This week, CIMMYT will be celebrating the completion of new agricultural research and training facilities made possible through the financial support of Fundación Carlos Slim. These state-of-the-art labs and greenhouses will ensure CIMMYT’s continued leadership developing high-yielding maize and wheat varieties equipped to tolerate the stresses of climate change. Expanded training facilities will enhance CIMMYT’s ability to develop and deliver resource-conserving farming practices and advance digital technologies that enable poor farming families to increase their productivity and income.
Helping poor farming families increase production in a sustainable way, and sell more crops, is the most effective way to reduce hunger and poverty over the long term. This has been proven in Mexico, India, Pakistan, Brazil, China, and many other countries over the last half century.
The unique partnership between CIMMYT, the government, and our foundations ensures that Mexico will continue to lead in agricultural development—first in Mexico and then the rest of the world.
The new infrastructure funded through Fundación Carlos Slim will enable CIMMYT to carry out cutting-edge agricultural science using the latest digital innovations, and to accelerate the use of mobile technology to provide farmers everywhere with vital information about weather, prices, and new techniques to improve their productivity. The Mexican government’s MasAgro initiative is helping farmers adopt more sustainable and profitable farming practices to increase food production. As these agricultural advances achieve scale in Mexico, the Gates Foundation will ensure that they reach maize and wheat farmers in Africa and South Asia, along with the resources needed to improve productivity.
Fifty years ago, Mexico’s leadership in agricultural innovation helped lift hundreds of millions of people in Latin America and Asia from hunger and poverty. More recently the UN’s Millennium Development Goals have reduced the number of people living in extreme poverty by half, since 1990.
The world is counting on Mexico to continue leading the way in agricultural research and sustainable farming practices to ensure global food security. Meanwhile, the global community must do its part by aligning around a new set of goals—including an agricultural productivity target—and achieving measurable outcomes that improve the lives of the world’s poorest people.
Gene Banks for Crops
Mexico, Carlos Slim, and me
Mexico and philanthropists like Carlos Slim are helping lead the global fight against hunger and poverty through agricultural development.
This week I’m excited to be in Mexico for a series of events with Carlos Slim, probably Mexico’s best-known business leader, whom I’ve enjoyed getting to know for his business insights—but also because of some of the innovative approaches he’s taking to philanthropy.

We’ve been invited by the International Maize and Wheat Improvement Center (known by its acronym in Spanish, CIMMYT) to help launch new facilities at its headquarters near Mexico City. With a staff of 1,100 in Mexico and 13 regional offices around the world, CIMMYT is helping reduce hunger and raise living standards in many poor countries through programs focused on increasing maize and wheat productivity. Our foundation has invested in CIMMYT, and Carlos Slim has been a big supporter.
Carlos is a very interesting guy. His father immigrated to Mexico from Lebanon. Carlos started several businesses when he was quite young and was already very successful by his mid-20s. His interests in construction, real estate and mining eventually branched out into many other businesses, including Mexico’s largest telecommunications company. He reminds me a little of Warren Buffett in his ability to find undervalued investment opportunities. I’ve enjoyed the time I’ve spent with him, getting to hear his thoughts on business trends and the future of Latin America.
Among many other great projects, the Slim Foundation has funded the new CIMMYT facilities that we’re helping open this week. Carlos’ foundation and ours have collaborated before in helping launch the Salud Mesoamérica 2015 initiative to support health projects in Chiapas, Mexico and across Central America.
This week we’ll get a chance to tour the new CIMMYT facilities including the gene bank, which holds the genetic diversity of 130,000 wheat and 28,000 maize varieties worldwide. This information is being uploaded onto databases that will be available to plant breeders everywhere. We’ll also get into the field with farmers who’ve been helped by the MasAgro project, sponsored by the Mexican government to help strengthen food security through R&D, capacity building and technology transfer.
One reason why I always enjoy going to Mexico is because of the country’s incredible progress, which has been really encouraging for me to get to see as I’ve spent time there over the years first for Microsoft and lately for our foundation. Despite the many challenges Mexico still faces, Mexico’s extreme poverty rate (those living on less than $1.25 per day) went from 13.6 percent in 1996 to 4.03 percent in 2010 (as per latest World Bank figures). A major driver in reducing poverty has been agricultural development, especially innovations that have helped improve crop yields for smallholder farmers, whose lives have improved a lot as a result.
Part of what makes this week’s visit particularly exciting for me is that the expansion of CIMMYT represents a very important and positive global trend: newly industrialized countries such as Mexico, China, India and Brazil are becoming leaders in efforts to help less developed countries. Mexico is in a great position to work closely with poor countries both because of its progress and because of its quite advanced technical capabilities in agricultural development. CIMMYT is a prime example of that.
Poor countries, donors and rapidly growing countries are increasingly working together in partnerships that I believe are a model for how to deploy the world’s combined resources. These sorts of partnerships, combined with rigorous goal-setting and measurement, can produce enormous benefits for the poorest around the world.
“Developing Countries”?
The River of Myths by Hans Rosling
Hans Rosling shows how countries are making progress in saving lives.
Hans Rosling shows how measurement reveals incredible progress in saving the lives of children in what were once labeled "developing countries." If the few countries that still have high child mortality rates can follow the path of Ethiopia, preventable child deaths may be history by 2030. We must continue to closely measure this progress.
Video created in partnership between The Gates Notes and Gapminder. #BillsLetter. License: Creative Commons 3.0.
Closing in on 1%
Turning the Corner on Polio in 2012
The Global Polio Eradication Initiative is making important changes.
Working to support the effort to rid the world of polio has taken me to some exotic places. But earlier this month, it took me to Washington, DC (I suppose you could argue this is also quite an unusual spot) to talk with policy makers about the historic opportunity we have to end polio forever.
My conversations with lawmakers gave me a chance to discuss some of the doubts people have expressed about whether we can really do this. But it also provided the opportunity to bring lawmakers up-to-speed on the results of important changes in the Global Polio Eradication Initiative’s (GPEI) approach—including cool new technology being used and the increased engagement on the part of governments in the countries where polio transmission continues.
In my opinion, the changes and progress in 2012 have made for the most convincing case yet that ending polio is possible—and is one of the most concrete accomplishments possible for global health.
For more than 10 years, we have been 99 percent of the way toward ridding the world of polio. Since then, every few years the global community would vow that year would be the year when polio transmission would stop.
However, 2012 is notably different from the earlier stagnation in progress. And while the global program hasn’t stopped transmission of the wild polio virus everywhere as some had predicted, it did close a big gap in that last one percent when India became polio-free early in the year after a long and hard battle to protect more than 172 million children under the age of five from polio. This was incredible tough terrain in which to run thousands, if not tens of thousands of vaccination campaigns. So, the lessons learned from India’s success are serving as a great guide for what’s needed in the remaining three countries where polio transmission persists—Nigeria, Pakistan and Afghanistan.
There’s no doubt that these countries aren’t easy places to get rid of the disease. There are a number of factors that need to be in place including improved campaign quality, meeting the program’s global funding needs, and anticipating political challenges.
I heard from U.S. lawmakers that the news regularly coming out of Afghanistan and Pakistan has led to reasonable concerns about the role insecurity plays in being able to reach children with vaccines. But in the last 11 months, incredible efforts are being made in these two countries by government officials, religious and community leaders and non-government organizations to negotiate access to children in hard-to-reach places.
And those efforts are paying off.
The polio program has been partnering with a number of NGOs to conduct negotiations to secure access to children, leading to breakthroughs in the past few months. In Afghanistan, the average number of inaccessible children in thirteen of the highest risk districts of the country has been reduced by more than half, from nine percent in June 2012 to 3.4 percent this November. And in the Terah Valley in Pakistan, where children hadn’t received vaccines in three years, approximately 30,000 children were reached with the polio and other critical vaccines during a vaccination campaign earlier this fall.
On the other front, in Nigeria, while cases have actually gone up this year, there is a full-scale effort to revamp the program, with many changes based on what vaccinators in India implemented to great success. Included in these changes are decreases in the size of vaccination teams and the addition of female vaccinators, tracking of nomadic populations, rigorous microplanning and scaling up of additional staff to help with all of these activities.
Another major innovation that is leading to early reports of impressive progress is the work on GIS mapping and GPS tracking to improve polio campaign planning and performance. (It’s a really ingenious use of the technology that you can learn more about here.) GPEI’s focus on using the polio program to increase routine immunization is ensuring that the polio program has an even broader long-term impact on the population.
The Independent Monitoring Board of the GPEI also notes the positive changes in a report released last week and their conclusion that the GPEI “has never been in a stronger position” reflects what I’m seeing too. Their assessment about what comes next for the history books is telling: “The time is momentous for public health history. A final concerted effort could indeed mean writing the story of polio’s last stand.”
I couldn’t agree more.
In Europe with Bono
Europe with Bono, defending aid
Shoring up support for international development assistance programs.
I spent Wednesday in Paris, talking about the importance and effectiveness of foreign aid. My partner in many of those meetings was Bono, who has used his voice so effectively to advocate for development aid and the needs of the poorest people on earth.
By any estimation, my few days in Europe were off to a good start.
We spent the better part of the day meeting with senior French officials, including France’s new president, Francois Hollande, his finance minister, Pierre Moscovici, the Minister of Foreign Affairs, Laurent Fabius, and their new Development Minister, Pascal Canfin.
France plays a critical role in encouraging the European Union to keep its commitments to overseas development assistance programs, particularly in the face of Europe’s economic difficulties. Its own commitment to foreign aid is a tremendous example to other donor countries. That was the context for our meetings.
President Hollande was clear that he remains committed to aid, and that he is an advocate for both the effectiveness of foreign aid when it is carefully done, and the responsibility developed countries have in working with the developing world. France has a remarkable history of support for Africa and for its assistance efforts around the world, with organizations like Médecins sans Frontières. The President also spoke about how aid can benefit both the recipient and donor countries.
France’s finance minister Pierre Moscovici made this point last month when he noted that Europe’s growth over the next 20 years will depend heavily on Africa’s growth and development. Ensuring that all Africans have a chance for a better future is not only the right thing to do, but also the smart thing to do from an economic standpoint.
We had a good exchange about getting the most out of every Euro of aid. I’m a big advocate for the incredible impact that investments in vaccines can achieve, and was very happy to hear the President specifically call out France’s commitment to staying involved with the Global Fund, which provides funding for programs to fight AIDS, TB, and malaria. France should be particularly proud in their leadership with the Global Fund. Their help is making a real difference in millions of lives around the world.
Support from leaders like President Hollande is critical to preserving those life-saving investments in aid and explaining why staying true to the EU goal of devoting .7% of national budgets to foreign aid is the right course.
Bono was very persuasive about the impact foreign aid is having, as well as the devastating consequences withdrawing it could have on poor countries, particularly in Africa.

I was really pleased with our meetings. They took place in spectacular surroundings (the Élysée Palace is a stunning example of French style and decoration). But the focus was on the poor, on both sides of the table. And that made for a very good first day in Europe.
Vaccines and Mangoes
India: day two
My second full-day in India started with a meeting with a high-level delegation from Pakistan of people working on eradicating polio in their country. It was tremendously kind of them to come to Delhi to see me. We had a lot to discuss.
The delegation was led by Shannaz Wazir Ali, who is Prime Minister Syed Yousaf Raza Gillani’s Special Assistant for polio eradication. I’d met her early last year in Dubai, to talk about ridding Pakistan of this terrible disease, and so it was good to catch up on progress made in the intervening months.Accompanying her were a group of public health officials and, most importantly, leaders from many of the provincial governments who are on the ground working toward this tough but important goal.
That this meeting happened in India is significant for several reasons. But the fact that India has been without a case of polio for over a year now is a terrific achievement. Besides meeting with me, the group will also spend time with Indian public health officials, sharing best practices and learning from one another. The conditions in Pakistan are really difficult, but you could not hope to find a more committed group of people than the delegation I met with. Many of the public health workers fighting to end polio in Pakistan risk their lives doing so. These are true heroes who face incredible obstacles -- misperceptions about the vaccines, remote and migrant communities, the need to go into villages that are dangerous because of violence and political instability.
But if India could beat polio (at least so far) in places like Uttar Pradesh and Bihar, I know Pakistan can do the same for its people. There are 16 cases reported in Pakistan so far this year. While that’s not a big number, it represents a huge vaccination challenge. I don’t wish to underplay the challenge, but seeing the Pakistani delegation’s resolve and desire to make polio eradication a national priority encouraged me.
Later in the day I visited the Serum Institute of India. This is an amazing company, and its facilities would be considered state of the art anywhere in the world. Serum produces low-cost, high-quality vaccines used in 140 countries around the world. It started out in 1966 to manufacture low-cost vaccines for Indian use. But over the years, Serum’s low-cost vaccines have literally transformed the world of health. By lowering the cost, you expand the reach of these miracle drugs. So I was really honored to be welcomed by Dr. Cyrus Poonawalla, who started Serum with his brother, and whose commitment to low-cost access has made a huge difference to millions of people around the world. This year, Serum will ship a billion doses of vaccines worldwide.
I was able to meet with a number of Serum’s top scientists and got to look at their impressive manufacturing line. I was particularly happy to see their work on the Pentavalent vaccines. This is a 5-in-1 vaccine given to children to protect them from life-threatening haemophilus influenza type B, diphtheria, pertussis, tetanus and hepatitis B. Serum’s work has dramatically lowered the cost of these vaccines (and a great many others) and is a true contribution by India to the well-being of the world.
A couple of commenters have asked about the weather, and I’ll admit – as a guy from Seattle – that the temperatures have been a challenge (44 Celsius – 112 Fahrenheit today). The upside is that it’s the height of the mango season right now, and I’ve been lucky enough to get them at just about every meal. They’re spectacular.
I finish up in Bangalore on Friday where I’ll once again be spending time with two distant ends of the spectrum. In the morning, a meeting with sex workers involved in an HIV prevention program called Avahan and I’ll end the day listening to some of India’s wealthiest families about their thoughts on philanthropy.
Keeping the Pests Out
A simple advance in crop storage aids poor farmers in Africa
Reducing spoilage from weevils helps farmers store and sell more crops.
On a recent trip to Africa, I saw the incredible impact that simple innovations can have on the world’s poor. For years, farmers trying to eke out a living growing cowpeas—a protein-rich staple—would lose as much as half their crop to weevils. As I showed students during a recent talk at Stanford, a simple, inexpensive triple-layer bag invented by researchers at Purdue University enables farmers to protect their entire crop. This allows farmers to charge more for their crops and has increased their incomes by as much as 30 percent.
In Africa
Visiting Tanzania: A Battleground in the Fight Against Malaria
On my most recent trip to Tanzania, Melinda and I spent time looking into how the foundation’s partnerships to reduce malaria are progressing.
On a recent trip to Tanzania with Melinda, we spent time focused on the foundation's efforts to reduce malaria. We were particularly interested in learning about the progress of research into a malaria vaccine.
Bagamoyo District Hospital
These children were waiting to see a doctor at the Bagamoyo District Hospital in Tanzania. They are among several thousand children participating in field trials of the vaccine, known as RTS,S. Just this week, interim results from the clinical trials were reported, and they prove that it’s possible to create a vaccine that’s effective against malaria. It was exciting to visit this clinic because it is so well run, they're offering lots of good health services, and people are coming from far away to participate in the vaccine trial.
Meeting with Health Officials
We met with health officials from the Bagamoyo District Hospital and the Ifakara Health Institute. There were a lot of visiting scientists from the Swiss Tropical and Public Health Institute, which has a close relationship with the IHI. We saw scientists who are working on ways of repelling mosquitoes so people don’t just have to rely on bed nets, which are only partly successful protection against malaria. It's great that the foundation’s support is helping with the vaccine, and that it is also helping train young scientists and building up a research infrastructure, which will have a lot of long-term benefits.

Ifakara Health Institute
Scientists at the Ifakara Health Institute were great at educating us about their work, including techniques for capturing mosquitos to help prevent malaria, what species of mosquito they were focused on, how they get the vaccine out into the field, and how they saw if the vaccine worked.

Meeting with Hospital Staff
We also met with staff at the local hospital to discuss progress treating and preventing malaria.

Mapinga Village Dispensary
We visited the Mapinga Village Dispensary, which is an example of how healthcare is delivered in Africa. These dispensaries are the first place people go for care in or near their villages. We saw how the dispensaries keep their vaccines, and we talked to people like Neema Malachi Najwale, the nurse in charge of the Mapinga Dispensary, about how they get mothers to come in for the vaccines. We also talked about how they can now use cell phones to send regular status reports on their inventory.

Meeting with Parents
We talked with some of the parents of children participating in the vaccine trials. Although Tanzania is quite poor and hasn't developed a very extensive infrastructure of roads and electricity, in the health area they've done pretty well. They have good vaccine coverage and are on track to meet a lot of the Millennium Development Goals. It’s a great example of the progress taking place in Africa.

Defeating Malaria
At the Mapinga Village Dispensary, we talked with the head nurse about a number of diseases they have to deal with besides malaria. But by far the biggest killer of children and adults in that area of Tanzania is malaria. So the enthusiasm among health officials for the new malaria work there is very high. I’m an optimist when it comes to defeating malaria. There is good progress with the vaccine, drugs to prevent and treat malaria, and other preventive measures. Eradicating malaria won’t happen overnight, but it’s a moral and economic imperative for Africa, and for the entire world.

A Childhood Terror
The history of polio in the U.S.
David Oshinsky remembers growing up in an America terrified by polio—a plague that put every child at risk until a vaccine was finally developed in the mid-1950s.
David Oshinsky, the author of Polio: An American Story reflects on the history of polio and the final push needed for eradication.
Be Prepared
Annual Letter: A health emergency
I’m willing to be seen as a troublemaker by people who are happy with the status quo on global health.
Malaria: Progress on Multiple Fronts
The fight against malaria is making very good progress. The death toll, overwhelmingly of young children in Africa, went down from 985,000 in 2000 to 781,000 in 2009. Of the 99 countries with malaria, 43 have decreased cases of the disease by more than 50 percent. Turkmenistan and Morocco were recently declared malaria-free. For these communities the reduction in both death and sickness makes a huge difference. And it is possible only because of increased donor spending, which reached $1.5 billion in 2009.
The Roll Back Malaria group, with strong support from the WHO and our foundation, has set an aggressive goal to provide bed nets to almost every household that needs them in the next few years. As coverage goes up from its current level of 42 percent, it will have a dramatic impact. In Senegal, where 80 percent of households own a bed net, the number of malaria cases went down 41 percent in a single year. Many amazing grassroots groups are helping with the delivery of bed nets. The Nothing But Nets campaign, for example, has gotten hundreds of thousands of individual citizens and organizations like the United Methodist Church and the National Basketball Association involved in the fight against malaria.
We are also working on lowering the cost of the anti-malaria drugs containing artemisinin, which are expensive enough that people are still using less effective drugs instead. The approaches range from breeding the plant that provides artemisinin to have a higher yield, to using very advanced synthetic chemistry that can make artemisinin starting with simple sugars.
As is the case with all infectious diseases, the ultimate tool against malaria would be a low cost, highly effective vaccine. The RTS,S vaccine, developed in partnership with the pharmaceutical manufacturer GSK, is in its final phase-3 trial stage. Interim data will be available later this year, and we should have final results by 2015. A number of other vaccine candidates that might be even more effective or might be combined with RTS,S are also making progress, and several will start human trials this year.
Saving the Youngest Children
Of the 8.1 million deaths per year of children under the age of 5, over 40 percent happen in the first 28 days of life, or the neonatal period. The good news is that we are headed in the right direction. In 1995 there were an estimated 5.6 million neonatal deaths. The most recent estimates show the number down to around 3.6 million.
Unlike the deaths that take place after a child is 28 days old, almost all of which can be prevented by inventing and delivering vaccines, reducing these early deaths requires a range of approaches. Some require new tools such as an ointment for the baby’s skin that prevents infection and an antibiotic solution for cleaning the cut umbilical cord. However, many of the key interventions involve social and behavioral change. You can have a huge impact (on both newborn and maternal health) by increasing the number of births done by a skilled provider in a clinic. It’s also important to teach mothers to wash their hands before handling a baby, to have frequent skin-to-skin contact with their babies, and to breastfeed exclusively for the baby’s first six months. (Mother’s milk contains not only key nutrition but also antibodies that block infection until the baby’s immune system is ready to operate on its own.) Where all of these elements come together, neonatal deaths can be reduced by 50 percent or more, so it’s critical that we learn more about how to teach and motivate mothers effectively, especially at a large scale.
Melinda has been a strong leader on maternal and child health issues. She gave an especially powerful speech last year to the Women Deliver conference. The plight of mothers and their babies is something she feels deeply, and it’s something we talk about a lot.
When she came home from a trip to Malawi she shared the experience of seeing two babies in a hospital in the town of Lilongwe, lying side-by-side in the same incubator. They were born within hours of each other. Each had suffered the same condition—they were unable to breathe at birth. Sadly, it was clear that only one would survive. That baby’s mother had made it to the donor-funded hospital in time for her delivery and was able to get the care she needed. Her baby was immediately resuscitated, which saved his life. The other was not so fortunate. He was born on the way to the clinic, on the side of road, and was not resuscitated soon enough. I wish everyone had a chance to experience what Melinda did, so they could see how things are improving but also understand the urgent need to do more.
HIV/AIDS and the Need for Leadership
Progress continues in fighting the AIDS epidemic, but the pace is slow. The rate of HIV infection has been reduced by almost 20 percent over the last 10 years, to fewer than 2.7 million infections per year. The number of people dying from AIDS has gone down by more than 20 percent in the last five years, to fewer than 2 million annually. Given all the lives that are at stake, I am impatient enough about this that I am willing to be viewed as a troublemaker by people who are happy with the status quo.
The war against AIDS is being waged on two fronts—treating those who are already infected and preventing new infections. Treatment continues to be scaled up, with more than 5 million people receiving HIV drugs. This is a great success story. Rich country generosity has been crucial and the execution in poor countries has been strong. However, there will not be enough money to treat everyone who will become infected if we don’t halt the progress of HIV. Because we don’t have a cure for AIDS, treatment has to continue for a patient’s entire life. That means costs continue to increase as you put more and more people on treatment.
Even without including people who will become infected in the future, the cost of treating the 33 million people living with AIDS today would be over $40 billion per year at current costs—over four times as much as is provided in aid today. To minimize the funding gap we need to reduce per patient costs of treatment. Drug costs have already been reduced to less than 20 percent of treatment costs. Most of the future savings will have to come from treatment models that reduce personnel, laboratory, and overhead costs. The difficulty of funding treatment makes it clear how important it is to prevent new cases. The sooner we make progress the better. There needs to be a sense of urgency that doesn’t exist yet.
Prevention breaks down into several different areas. The easiest should be preventing mother-to-child transmission since it simply involves giving a mother drugs to prevent transmission to her child. There is a lot of focus on getting from the current number of over 300,000 infections per year to zero. Another prevention approach is counseling people to change their behavior, including avoiding risky acts and using condoms. Then we have prevention approaches that rely on new tools. We now have three tools that have shown significant impact. The first is male circumcision, which I discussed last year. Amazingly, teenagers in communities with high HIV incidence show a high willingness to be circumcised. Kenya is leading the way with over 200,000 circumcisions performed. However, there are over 10 million men in high-risk settings in Africa who would benefit from male circumcision, and we should be scaling up 10 times faster than we are.
Another new tool is a vaginal microbicide gel that a woman can use to protect herself. A recent trial showed a gel containing tenofovir protected women against infection. Now the question is how long it will take before the gel is rolled out on a large scale. As someone outside the field, I am surprised at the number of steps it takes. First the product has to be licensed, which requires approvals from regulatory groups in both the country where the product will be used and donor countries. Many of these approval steps happen serially rather than in parallel, and it is only when the entire approval process is complete that the product can be rolled out. Even then the process isn’t complete because a whole system for delivering the product needs to be put together, and again a lot of these steps proceed in a slow serial fashion.
Another new prevention tool, PrEP (Pre-Exposure Prophylaxis), involves someone without HIV taking an anti-HIV drug on a regular basis to block infection. A PrEP trial showed a strong prevention benefit for the participants who consistently used the drugs and a weaker impact when all the participants were included. With both microbicides and PrEP I think countries with large epidemics should figure out how to do large community trials as soon as possible. This would shorten the time before all patients have these lifesaving tools by many years.
If the United States had an epidemic where almost half the girls in large neighborhoods contracted a terrible disease, we would find a way to cut through all the complexity. With HIV it is more difficult since there are many countries involved. But we need to work creatively to shorten these delays.
The best tool would be a vaccine for HIV. The scientific progress on this has gone well. The positive results of the trial in Thailand were a turning point for the field, and blood samples from the volunteers are being studied in depth for lessons about why that vaccine worked but only to a limited degree.
There has also been an explosion in the discovery of antibodies that block HIV infection. Scientists don’t yet know how to make a vaccine that will cause patients to generate lots of these antibodies, but there are several approaches that look promising and will be ready to go to trials in the next few years.
In order to get a fully effective HIV vaccine we will almost certainly need several rounds of trials where we learn and improve the candidate vaccines. So to get a vaccine as soon as possible we need to minimize the length of the trials and the time between trials. So far each cycle has taken over five years. The field needs to look into how to shorten this so that progress matches the urgency of the problem.
Building Dreams
In China, speeding toward the future
In September 2010, I traveled through China to visit with vaccine makers, computer scientists, energy technology companies and car manufacturers.
I travelled to China for the first time in 1990 on Microsoft business and have been back many times since. One very memorable trip was in 1995 with Melinda, my father and Warren Buffett. We rode the trains and traveled around as tourists for several weeks—it was an incredible trip and a lot of fun.
My recent trip was unique and especially exciting, as I had the opportunity to do work that spans my various interests. I met with our team at Microsoft Research Asia, where I saw some incredible innovations in search and related technologies. I also met with a number of vaccine companies that are working with our foundation. For the last part of the trip, I joined Warren Buffett, Charlie Munger and other Berkshire Hathaway board members. Our main focus was a visit to BYD, an incredible company in which Berkshire owns a 10 percent stake. BYD fully lives up to its name, which stands for Build Your Dreams. It manufactures batteries, electric and hybrid cars and buses, and many highly innovative green products.
The meetings with vaccine manufacturers were about the potential for expanding development of new vaccines in China for use worldwide. Historically, most important vaccines have originated in Europe and the United States. Now, countries like Brazil, India and China are providing lower-cost versions of some of them. Ideally, they’ll also get involved in inventing new vaccines. Because these countries suffer from many of the infectious diseases that we need new vaccines for, local development could help speed vaccine dissemination. Also, because countries like China have experience in making low-cost vaccines, they could be better at designing new ones in ways that make them low in cost from the very beginning. That would be wonderful.
And so the foundation is reaching out to new vaccine companies, seeing how we can help them and what holds them back. This was my first visit with some of the companies in China. I was impressed at how quickly the industry is moving ahead. They really understand low-cost manufacturing, and they’re getting their quality up to world standards. Over the next five to ten years, they have the potential to create many breakthrough vaccines, as well as to help get current vaccines to the world’s poorest people, for whom price can be a significant obstacle.
Specifically, the foundation is trying to make sure that every child in the world gets three vaccines: pentavalent (against diphtheria, tetanus, whooping cough, hepatitis B and influenza B), rotavirus (against severe acute gastroenteritis) and pneumococcal (against pneumonia). Together, these three could reduce child deaths by almost one million per year. If we can get their cost down, then we’ll be able to get all three to even the poorest children in the world. It looks like China could help out on low-cost rotavirus and pneumococcal. So we have possibilities there, as we do in India and Brazil.
Gearing up to manufacture vaccines that meet international standards is a costly and complex process. In China we saw a flu vaccine manufacturing line that is unique in that it involves growing flu virus in chicken eggs. The plant has to buy a huge number of eggs and make sure they're all sterile. It’s quite a process, and people worry that, in the event of a big epidemic, they might not be able to buy enough eggs and grow the virus quickly enough. But in our visit to Sinovac Biotech, headquartered in the Beijing University Biological Industry Park, we saw that it has really distinguished itself by rapidly building up its flu vaccine capability. That was quite impressive.
I love any excuse for spending time with Warren Buffett, whether we’re playing golf (which neither of us is very good at) or playing bridge, which we're kind of just okay at.
Our visit to BYD was amazing. The company was started back in 1995 by a battery expert. It grew to be very strong in phone batteries and car batteries, and then, in 2003, BYD decided to make its own cars. It has about six percent of the domestic car market and plans to expand its product line and volume quite dramatically. It’s an innovative company, pushing forward on battery technology, doing electric taxis, electronic buses and electric storage systems.
BYD has created an entirely electronic bus using special batteries and a special electronic motor. The company has innovated to bring the battery cost down and the battery life up. If it works as well as planned, the operator saves enough on fuel to be able to pay quite a premium for the bus. We rode around on a prototype and participated in a ceremony where a local city committed to buy a thousand of these buses. They will be a huge help in reducing the smog in Chinese cities and could even help start to reduce CO2 emissions.
BYD headquarters is in Shenzhen, in the southeast part of China next to Hong Kong. Shenzhen is where the Chinese economic miracle started; it was a special economic zone. So I wasn’t surprised to see a lot of modern buildings and a pretty impressive car factory. But I was blown away when I heard how quickly they put up the buildings. In the U.S., you just can’t build nearly as fast.
What was even more amazing was to go to a city in the middle of China, Changsha, which has six million people, and see a new factory that will turn out 400,000 cars a year. It was built in less than two years from start to completion. Around the city, new high-rise buildings are going up where only cornfields stood just a few years ago. You hear about China’s 10-percent annual economic growth, but to fully understand you really have to see it in person. China is moving at incredible speed.
Travels in India
Seeing self-help in action in India
I was on the road again in May 2010 on a visit to northern India. I came back excited by the progress I saw in villages that have suffered from dire poverty and the persistence of polio.
India is always a fascinating place to visit. I’ve now been there more than a dozen times. I went in July 2009 to look at the government’s efforts to improve health care in poor communities. I returned in May 2010 to see how things are going with projects that are trying to help eliminate polio and other infectious diseases, and help improve things for people in some of the poorest areas, specifically the states of Uttar Pradesh and Bihar in the north of the country.
I traveled to Uttar Pradesh with Rahul Gandhi, a member of Parliament. He has been a real innovator in organizing women’s self-help groups, and one of our first stops was a meeting of self-help group leaders. It was incredible to listen in on their discussions and hear them encouraging one another with songs and chants about vaccinations, sanitation and safe birthing practices. You could hear in their voices how they had gained optimism and confidence from their experiences working together.
These women go out to other villages and in the past three years they’ve helped form over 20,000 new self-help groups. The groups enable women to get microloans at lower rates than the moneylenders charge and work to improve services, like health and education, in their villages. I really can't express how uplifting it was to listen to these women talk about how they organized. If one woman couldn't get something to be done, then ten would show up. If that didn't work, 100 would show up. Rahul was making the point that self-help groups are a key enabler, not super expensive, with all sorts of additional benefits that contribute to our health and education goals.
I also went to Bihar, the poorest state in India, but one that’s making lots of progress. Polio is still a significant problem there, and the campaign against it is very intense. As in Utter Pradesh, self-help groups play an important role in Bihar, particularly groups organized by PRADAN, a nonprofit group of professionals who provide development assistance to India’s remotest villages whom we support through the Bill & Melinda Gates Foundation.
Among other things, PRADAN helps farmers improve their agricultural practices so they can increase their crop yields and even find new sources of income, such as by developing arjuna tree plantations for rearing silkworms and weaving silk. It was amazing to see how self-help groups aided by PRADAN expertise had completely transformed the villages we visited, keeping kids in school, encouraging girls to marry later and to take control of their family size, all things that improve the well being of their families and the village as a whole.
While in Bihar, I also met with the Chief Minister of the state. Under his leadership, Bihar has made significant progress, improving health outcomes and increasing vaccination rates. It’s really encouraging to see progress being made in one of the poorest places in India. You realize if it can happen here, it can happen almost anywhere.
My last few days were spent in India’s capital, New Delhi. I met with innovators from some of the Indian companies that make inexpensive vaccines, which are helping make vaccination more affordable for kids around the world. I also met with government officials including Prime Minister Manmohan Singh and Health Minister Ghulam Azad, whose energy and commitment were also very impressive.
So it was an uplifting trip. India has a good chance of eliminating polio in the next few years, which would be a huge achievement. And the progress being made toward many development goals is truly inspiring.
Making Medicines Available
Eliminating killer diseases with new medicines
For people suffering from serious but treatable diseases like pneumonia and tuberculosis, access to drugs can mean the difference between life and death. A new report and two recent announcements are signs of progress in efforts to expand access.
In the developed world, we sometimes take life-saving medicines for granted. But as I’ve traveled in the developing world, I’ve seen first-hand the huge difference they can make. A new report and two recent announcements are reminders of the important role of the pharmaceutical industry, especially in helping save the lives of people in poor countries.
The new report is the Access to Medicine Index 2010 from the Access to Medicine Foundation, based in the Netherlands. The index ranks 20 of the world's largest pharmaceutical companies on their efforts to make sure that medicines are made for and reach people in developing countries. The latest index found that companies are being more transparent about their efforts to expand access. They’ve also taken steps to make drug pricing more equitable and to increase R&D on diseases affecting poor countries. But in the words of the Index’s founder Wim Leereveld, “the industry as a whole still has a long way to go.”
One example of progress on access is the announcement by GlaxoSmithKline and Pfizer Inc. that they will accelerate production and distribution of new vaccines against pneumococcal disease, which kills 1.6 million people a year—mostly in developing countries, and half of them children under the age of five.
Glaxo and Pfizer will supply 30 million doses a year, for 10 years, at a price that is more affordable for developing countries. Estimates are that the vaccines could save 900,000 lives by 2015, and up to 7 million lives by 2030. Key to this effort was an innovative financing mechanism, known as an Advance Market Commitment, piloted by the GAVI Alliance. I am pleased that our foundation was able to support this effort in partnership with GAVI, the World Bank, the World Health Organization, UNICEF and the national governments of Italy, Canada, Norway, Russia, and the United Kingdom.
In another important effort supported by the foundation, the non-profit Critical Path Institute (C-Path) and the Global Alliance for TB Drug Development (TB Alliance) will coordinate testing of promising combinations of tuberculosis drug candidates from at least 11 different pharmaceutical companies early in the development pipeline.
If you used the historical approach to testing and getting regulatory approval for new TB drugs—individually and then in combination with other drugs—it could take 24 years. This new approach, which the foundation created in partnership with C-Path and the TB Alliance, hopes to develop effective new combination TB treatments in just six years. Importantly, the U.S. Food and Drug Administration and regulatory authorities in Europe have indicated strong support for accelerating approvals of safe, effective new treatments.
Although many people think of TB as a disease that was conquered long ago, it still kills 1.8 million people a year, mainly in the poorest countries on earth. The current four-drug course of treatment for TB is now 50 years old and requires patients to take numerous pills for six months or longer, which many find difficult, especially given the often-unpleasant side effects. When patients don't complete their course of treatment, the disease can become resistant to the initial drugs. In 2007, there were more than 500,000 cases of drug-resistant TB. New and easier ways to treat TB would be a great step forward.
I believe that these kinds of innovative collaborations between pharmaceutical companies, governments and the non-profit sector are critical to accelerating the delivery of medicines, which is critical to saving lives.


