




Be Prepared
Annual Letter: A health emergency
I’m willing to be seen as a troublemaker by people who are happy with the status quo on global health.




Malaria: Progress on Multiple Fronts
The fight against malaria is making very good progress. The death toll, overwhelmingly of young children in Africa, went down from 985,000 in 2000 to 781,000 in 2009. Of the 99 countries with malaria, 43 have decreased cases of the disease by more than 50 percent. Turkmenistan and Morocco were recently declared malaria-free. For these communities the reduction in both death and sickness makes a huge difference. And it is possible only because of increased donor spending, which reached $1.5 billion in 2009.
The Roll Back Malaria group, with strong support from the WHO and our foundation, has set an aggressive goal to provide bed nets to almost every household that needs them in the next few years. As coverage goes up from its current level of 42 percent, it will have a dramatic impact. In Senegal, where 80 percent of households own a bed net, the number of malaria cases went down 41 percent in a single year. Many amazing grassroots groups are helping with the delivery of bed nets. The Nothing But Nets campaign, for example, has gotten hundreds of thousands of individual citizens and organizations like the United Methodist Church and the National Basketball Association involved in the fight against malaria.
We are also working on lowering the cost of the anti-malaria drugs containing artemisinin, which are expensive enough that people are still using less effective drugs instead. The approaches range from breeding the plant that provides artemisinin to have a higher yield, to using very advanced synthetic chemistry that can make artemisinin starting with simple sugars.
As is the case with all infectious diseases, the ultimate tool against malaria would be a low cost, highly effective vaccine. The RTS,S vaccine, developed in partnership with the pharmaceutical manufacturer GSK, is in its final phase-3 trial stage. Interim data will be available later this year, and we should have final results by 2015. A number of other vaccine candidates that might be even more effective or might be combined with RTS,S are also making progress, and several will start human trials this year.
Saving the Youngest Children
Of the 8.1 million deaths per year of children under the age of 5, over 40 percent happen in the first 28 days of life, or the neonatal period. The good news is that we are headed in the right direction. In 1995 there were an estimated 5.6 million neonatal deaths. The most recent estimates show the number down to around 3.6 million.
Unlike the deaths that take place after a child is 28 days old, almost all of which can be prevented by inventing and delivering vaccines, reducing these early deaths requires a range of approaches. Some require new tools such as an ointment for the baby’s skin that prevents infection and an antibiotic solution for cleaning the cut umbilical cord. However, many of the key interventions involve social and behavioral change. You can have a huge impact (on both newborn and maternal health) by increasing the number of births done by a skilled provider in a clinic. It’s also important to teach mothers to wash their hands before handling a baby, to have frequent skin-to-skin contact with their babies, and to breastfeed exclusively for the baby’s first six months. (Mother’s milk contains not only key nutrition but also antibodies that block infection until the baby’s immune system is ready to operate on its own.) Where all of these elements come together, neonatal deaths can be reduced by 50 percent or more, so it’s critical that we learn more about how to teach and motivate mothers effectively, especially at a large scale.
Melinda has been a strong leader on maternal and child health issues. She gave an especially powerful speech last year to the Women Deliver conference. The plight of mothers and their babies is something she feels deeply, and it’s something we talk about a lot.
When she came home from a trip to Malawi she shared the experience of seeing two babies in a hospital in the town of Lilongwe, lying side-by-side in the same incubator. They were born within hours of each other. Each had suffered the same condition—they were unable to breathe at birth. Sadly, it was clear that only one would survive. That baby’s mother had made it to the donor-funded hospital in time for her delivery and was able to get the care she needed. Her baby was immediately resuscitated, which saved his life. The other was not so fortunate. He was born on the way to the clinic, on the side of road, and was not resuscitated soon enough. I wish everyone had a chance to experience what Melinda did, so they could see how things are improving but also understand the urgent need to do more.
HIV/AIDS and the Need for Leadership
Progress continues in fighting the AIDS epidemic, but the pace is slow. The rate of HIV infection has been reduced by almost 20 percent over the last 10 years, to fewer than 2.7 million infections per year. The number of people dying from AIDS has gone down by more than 20 percent in the last five years, to fewer than 2 million annually. Given all the lives that are at stake, I am impatient enough about this that I am willing to be viewed as a troublemaker by people who are happy with the status quo.
The war against AIDS is being waged on two fronts—treating those who are already infected and preventing new infections. Treatment continues to be scaled up, with more than 5 million people receiving HIV drugs. This is a great success story. Rich country generosity has been crucial and the execution in poor countries has been strong. However, there will not be enough money to treat everyone who will become infected if we don’t halt the progress of HIV. Because we don’t have a cure for AIDS, treatment has to continue for a patient’s entire life. That means costs continue to increase as you put more and more people on treatment.
Even without including people who will become infected in the future, the cost of treating the 33 million people living with AIDS today would be over $40 billion per year at current costs—over four times as much as is provided in aid today. To minimize the funding gap we need to reduce per patient costs of treatment. Drug costs have already been reduced to less than 20 percent of treatment costs. Most of the future savings will have to come from treatment models that reduce personnel, laboratory, and overhead costs. The difficulty of funding treatment makes it clear how important it is to prevent new cases. The sooner we make progress the better. There needs to be a sense of urgency that doesn’t exist yet.
Prevention breaks down into several different areas. The easiest should be preventing mother-to-child transmission since it simply involves giving a mother drugs to prevent transmission to her child. There is a lot of focus on getting from the current number of over 300,000 infections per year to zero. Another prevention approach is counseling people to change their behavior, including avoiding risky acts and using condoms. Then we have prevention approaches that rely on new tools. We now have three tools that have shown significant impact. The first is male circumcision, which I discussed last year. Amazingly, teenagers in communities with high HIV incidence show a high willingness to be circumcised. Kenya is leading the way with over 200,000 circumcisions performed. However, there are over 10 million men in high-risk settings in Africa who would benefit from male circumcision, and we should be scaling up 10 times faster than we are.
Another new tool is a vaginal microbicide gel that a woman can use to protect herself. A recent trial showed a gel containing tenofovir protected women against infection. Now the question is how long it will take before the gel is rolled out on a large scale. As someone outside the field, I am surprised at the number of steps it takes. First the product has to be licensed, which requires approvals from regulatory groups in both the country where the product will be used and donor countries. Many of these approval steps happen serially rather than in parallel, and it is only when the entire approval process is complete that the product can be rolled out. Even then the process isn’t complete because a whole system for delivering the product needs to be put together, and again a lot of these steps proceed in a slow serial fashion.
Another new prevention tool, PrEP (Pre-Exposure Prophylaxis), involves someone without HIV taking an anti-HIV drug on a regular basis to block infection. A PrEP trial showed a strong prevention benefit for the participants who consistently used the drugs and a weaker impact when all the participants were included. With both microbicides and PrEP I think countries with large epidemics should figure out how to do large community trials as soon as possible. This would shorten the time before all patients have these lifesaving tools by many years.
If the United States had an epidemic where almost half the girls in large neighborhoods contracted a terrible disease, we would find a way to cut through all the complexity. With HIV it is more difficult since there are many countries involved. But we need to work creatively to shorten these delays.
The best tool would be a vaccine for HIV. The scientific progress on this has gone well. The positive results of the trial in Thailand were a turning point for the field, and blood samples from the volunteers are being studied in depth for lessons about why that vaccine worked but only to a limited degree.
There has also been an explosion in the discovery of antibodies that block HIV infection. Scientists don’t yet know how to make a vaccine that will cause patients to generate lots of these antibodies, but there are several approaches that look promising and will be ready to go to trials in the next few years.
In order to get a fully effective HIV vaccine we will almost certainly need several rounds of trials where we learn and improve the candidate vaccines. So to get a vaccine as soon as possible we need to minimize the length of the trials and the time between trials. So far each cycle has taken over five years. The field needs to look into how to shorten this so that progress matches the urgency of the problem.


Weather or not
Fighting climate change one text at a time
In Kenya, AI-powered weather forecasts are helping farmers adapt to a changing climate.
When I check the forecast for rain, I do it to answer fairly minor questions: Will I need an umbrella? Will my flight be delayed? Will my pickleball game get cancelled?
For smallholder farmers in Kenya, the stakes are much higher. If they plant their seeds too early, a dry spell might kill their crops before they have the chance to take root. If they plant too late, the crops might miss the rain entirely. When your family’s food and livelihood depend on getting the timing just right, a reliable weather forecast is incredibly valuable.
But in sub-Saharan Africa, it’s also been incredibly rare. That’s because global weather models are built from ground-station data, and Africa has fewer of these stations than any other inhabited continent. The result is forecasts that can accurately predict the rainfall in Missoula or Munich but are often far less accurate in Kenya’s Rift Valley, where 80 percent of the country’s staple maize crop is grown. As climate change makes weather patterns around the world increasingly erratic, today’s farmers are increasingly unable to rely on the seasonal patterns that guided generations before them.
Fortunately, AI offers us an affordable and fast solution. Over the past several years, a coalition of African institutions, researchers, and technology partners has been building a forecasting system with the technology at its center.
It starts with better information about the weather itself. On the ground, weather stations capture the basics like where it rained, when, and how much. But now, they’re supplemented by autonomous weather balloons up in the sky. For weeks at a time, these balloons float around and measure the temperature, humidity, and wind in places ground stations can’t reach and satellites can’t fully see either.
Then AI digests that information and puts it to work. While today’s AI models are far from perfect, they’re astoundingly good at squeezing immense insight out of limited data. In this case, they’re able to take the ground and sky observations, compare them to what was forecast, figure out the patterns behind the errors, and start correcting for them.
The more local data that comes in, the more the AI can finetune its models, and the better they get. As a result, a farmer in the Rift Valley can now get a weather forecast specific not just to her region but to her fields.
Of course, an accurate forecast only makes a difference if it reaches that farmer when she still has time to act on it. Even better if it’s delivered to her phone, in her own language, with advice she can use. That’s where a nonprofit called TomorrowNow comes in. I first saw their work on a trip to Kenya a few years ago and was impressed by how intuitive and impactful it is. Using AI, they translate the forecasts into easy-to-follow text message guidance like “plant this week,” “a dry spell is coming,” or “hold off on fertilizer.” Those text messages then reach farmers through organizations they already trust like One Acre Fund, which provides seeds and training to millions of them, and KALRO, Kenya's national agricultural research organization.
The results are undeniable. A rigorous two-year study of nearly 10,000 farmers found that those who got the text-message advisories grew 12 percent more food on average. That could be the difference between a family having to buy food and getting to sell their surplus. It's school tuition that gets paid and debts that are avoided. And the cost? Just 56 cents per farmer enrolled in the program. It’s hard to find a better bang for your buck than that in global health and development.
Today, Kenyan scientists at KALRO, working with TomorrowNow, are bringing AI-powered weather forecasts to more than five million farmers in Kenya; TomorrowNow’s goal is to reach 100 million across the rest of Africa and South Asia by 2030.
But even though international partners helped along the way, this system’s foundation—and the leadership deciding its future—is African. The observational backbone comes from institutions like the Trans-African Hydro-Meteorological Observatory, or TAHMO, which runs hundreds of weather stations across the continent. The forecasts draw on data from Kenya’s own meteorological authority. And the advisories are being built into the country’s permanent infrastructure rather than running alongside it as a donor project.
I've long argued that fighting climate change has to happen on two fronts: We have to cut emissions so the problem doesn’t get worse, and we have to help people who are most vulnerable to it adapt to the warming that's already occurred. The Gates Foundation invests a lot in this area, but the problem deserves much more attention and funding. And AI is making those investments go further than ever before.
When people ask me whether AI will exacerbate the gap between rich and poor, these are the innovations I talk about. Making sure AI's benefits reach everyone will take deliberate work, which the Gates Foundation committed over a billion dollars to at this year’s Goalkeepers event. The good news is: We already have proof that, when we’re intentional about it, this technology can be a great equalizer.
Body of evidence
Ramesh Ferris wants you to look at his legs
A powerful reminder of why polio eradication matters.
When Ramesh Ferris speaks in public, which he does a lot, he has an unusual way of getting to the stage. He crawls across the floor.
Ramesh was paralyzed by polio when he was six months old. Today, at age 46, he can walk with crutches and leg braces, but as an advocate for polio eradication, sometimes he chooses not to. He wants his audience to see what the disease does to the human body.
“I’m the voice of the polio survivors that I’ve met crawling in the streets of their communities,” he says. “Showing my legs is the most powerful tool I can use to educate people about the reality of what happens when kids don’t receive the polio vaccine.”
Ramesh contracted polio in 1980, when he was six months old. The first polio vaccine had been invented 25 years earlier, and millions of children had received it, but it still hadn’t reached low-income communities like the one in the state of Tamil Nadu, India, where he was born.
His birth mother had never heard of the disease, much less a vaccine for it. She just knew that her boy kept getting sick, and she couldn’t afford medical care for him, so she made what must have been an agonizing decision. She put him in the care of an orphanage in her community.
A year later, Ramesh was adopted by a Canadian couple who raised him and five other adopted children in the Yukon. Life was hard at times—kids at school mocked and bullied him—but he got expert medical care. Through three surgeries, doctors straightened his legs, and after intensive physical therapy, he learned to walk with crutches and braces.
When Ramesh was 22, he took a trip that changed his life. He went to India to meet his birth mother for the first time, so he could tell her how grateful he was that she had sacrificed so much so he could get the care he needed.
On the same trip, he had another powerful emotional moment. “I saw a fellow human being that had polio because he didn’t receive the polio vaccine as a child,” Ramesh says. “He was crawling around the streets as a beggar.” The person he was traveling with told him: “You’re looking at your life if you weren’t adopted.”
Since that time, Ramesh has been traveling around the world as a volunteer with Rotary International to spread the word about how much progress the world has made and the work that still remains. He’s raised awareness and funds with eye-catching campaigns including a 7,140 km trip across Canada… by hand bike.
We’re close to eradicating the disease—there were 52 cases of wild poliovirus in 2025, down from 350,000 in 1988—but finishing the job is a tough challenge that takes continued funding and effort.
People like Ramesh remind us not only how we can do it, but why we should.
An epochal shift
The turbulent AI era is here. The choices we make now are critical.
We need a plan to ensure that the good outweighs the bad.
During my entire life I’ve only had two jobs. In the first one, I played a role in developing software to empower people through my work at Microsoft.
In my second one, which I started full time in 2008, I am giving back the wealth I made at Microsoft with the goal of making the world a healthier, better educated, and more equitable place. This is the job I will have for the rest of my life.
Both of these experiences inform my perspective on artificial intelligence. When I first learned about computers at age 13 I was fascinated by the idea of making them more intelligent and able to perform things that, at the time, only humans could do. Although the term “AI” was used from around the time I was born, the technology has only made significant progress in the last decade. It is now incredibly capable and it is continuing to improve at a mind-blowing rate. AI for the first time can replace and even exceed human cognition.
In terms of equity, AI will either be the greatest equalizer ever invented, or the worst source of injustice. The challenge is monumental. Even under the best circumstances, the transition to this new AI era will be one of the most turbulent times in human history. How will we use this technology to make the world a fairer place and keep it from widening the divide between rich and poor? How will we protect the people who are most vulnerable to the harms caused by artificial intelligence, including those who lose their livelihoods and the sense that they are in control of their future?
I believe that answering these questions and acting on the answers should be the world’s top priority. If the world takes the right steps AI will be a force for good and leave everyone better off.
Unfortunately, right now we are not preparing for it. I don’t see evidence that leaders, experts, and communities are confronting the challenges adequately. There is no plan to ease the entry into the AI era.
Part of the reason for this is that many commentators underestimate the extent of the impact AI will have. I think there are a few reasons why.
One is the fact that AI models still make mistakes. It is hard to envision any of them replacing human cognition when, not long ago, they couldn’t solve a simple Sudoku puzzle or figure out how many R’s are in the word strawberry.
But the reliability problem is being fixed quickly, as researchers create models that can check their own work and improve themselves. Soon they will be substantially better than humans at many tasks.
Another reason people underestimate AI is that analogies to the effects of past innovations are misleading. We have no experience with a technology that can be adopted quickly or that can think and move like a human. When the PC came along, it took twenty years to significantly change how we worked because the software had to be developed, the price had to come down, and people had to learn how to use the tools and incorporate them into their business processes. AI, on the other hand, runs on the devices we already have, and it uses natural language. We don’t have to adapt to it because it can adapt to us. It can watch the same training video that is used to train human workers and learn from existing data.
I want to acknowledge a potential bias. I have benefited enormously from the technology industry. Although I have diversified my portfolio quite a bit, I still have financial ties to it. I am working with Microsoft and other AI companies in my role as chairman of the Gates Foundation to try and ensure AI is deployed in ways that will truly benefit people around the world.
However, my views on AI are not motivated by the potential to make money for myself. Any profits generated by my investments, including those related to technology, will go to the Gates Foundation to tackle global inequity. Of course, readers will have to decide for themselves whether this clouds my view.
This time really is different.
For as long as I can remember, I’ve wished innovation could happen faster. With AI, my feelings are more complicated.
I wish the world could get the benefits rapidly and delay the problems it will cause as long as possible, but the benefits and problems are arriving at the same time. I believe we need time to prepare for the period of social, political, and economic upheaval we are about to enter. The people who need the most time are the ones who have the least—the accounting worker who’s replaced by a bot or the $20-an-hour worker who loses their job to a $10-an-hour robot.
Many observers say that this technology transition will be like previous ones. They give the example of how jobs in the United States shifted from agriculture to office work. However, that proceeded over several generations and created new jobs where human cognition was required. In this case, the technology can substitute for human cognition.
Because it can see, listen, speak, and reason and will eventually do physical work just as smoothly as any human, it will not just affect one sector. AI will take on work in law, customer service, medicine, software, and manufacturing. It will hit these industries rapidly, over the course of a decade rather than a few generations. There will be some new jobs, but without the right policies there will be far fewer than exist today.
If someone had a credible plan for slowing down AI advances globally, I would likely support it. However, I don’t think that’s going to happen. The geopolitical and economic incentives are pushing too hard to go full speed ahead.
To make sure we maximize the positive effects of this unprecedented technology and minimize the bad so we are better off overall, we need to understand both the benefits and the risks. I’ll start with the risks.
The transition to AI comes with three big risks.
I plan to write about each of these in more detail in the future, so I’ll touch briefly on them for now.
Many jobs will disappear forever.
In 1933, during the Great Depression, unemployment in the United States was roughly 25 percent. It remained in double digits for much of the following decade. It ultimately recovered as demand, investment, and growth returned.
AI may not reach this level, but its impact will not go away with an economic cycle. The jobs at most risk are entry- and mid-level, and the new jobs being created will mostly require skills that take many years to learn.
White-collar jobs are already being hit modestly. After the widespread adoption of generative AI, employment fell significantly among young workers in jobs that are especially vulnerable to replacement, but not among their older colleagues.
I think this trend will continue, but it will not be confined to a handful of industries or occupations. Jobs in sales and customer support (online and over the phone), software engineering, and paralegal work may be among the first affected, but the disruption will reach much further as AI takes on tasks that today still require trained workers: things like assessing loan applications, doing data analysis, and even triaging patients. A few areas like software engineering will generate new demand as the costs go down, so the net job loss in those areas will be less than in others as long as some tasks, such as design, are better done by humans.
Blue-collar jobs will be affected as well. Although robots are not as far along as AI, eventually their cost will be dramatically lower too. Many Americans I talk to don’t realize how fast dexterous robots are advancing because much of the advanced work is being done in other countries, primarily China. Or they may be confused by those videos of robots dancing badly that have been going viral lately. I think “smart” robots will begin to compete with people on some physical tasks—in the construction and hospitality industries, for example—by the end of the decade.
Robots and AI combined can create a vicious cycle. After one company adopts them and uses the savings to lower its prices, its competitors will feel immense pressure to do the same. If existing companies don’t adopt them, then start-ups will. Many people will shift to other jobs, but the turmoil of losing work, getting retrained, and finding other work will be significant. Market forces will make adoption go faster and faster and, unless we intervene, there will be fewer good jobs available and the benefits will accrue to a small group.
I’m especially worried about young people, who will enter a workforce with fewer entry-level openings. They understand the challenge because they are the most active users of AI and see both the capabilities and the rate of improvement. It’s no wonder that so many of them feel negatively about AI.
The biggest shift for workers will happen when AI provides nearly error-free work. At that point, it will be able to function on its own without a human checking in on it, and companies will have every economic incentive to let it.
This will lead to a fundamental change in how we think about work, income, and economic security. How will an economy that’s been built around employment operate if fewer people are working, or if many people are working fewer hours?
In a capitalist society, employment is the way most people get the money they need to pay for the basics of life as well as being a key source of dignity and social connection.
When a community has high unemployment, the ripple effects can be pervasive. Research suggests that in some parts of the United States, factory closures contribute to a rise in deaths from opioid overdoses. Now imagine similar pressures on both white-collar and blue-collar workers nationwide.
We have to think now about how to reduce job losses so that everyone can share in the prosperity that AI creates. Waiting until people are already displaced or underemployed will be too late. AI is a structural challenge to the way our economy is organized, and it requires thinking and action now.
AI will empower people (and perhaps AIs) to do more harm.
Long before AI entered the mainstream, there was information online about how to create weapons like bombs, bioweapons, even computer viruses. AI will make it much easier to not only get this information but act on it. Even criminals with very limited skills will be able to target victims at every scale: individuals, companies, and governments.
AI-enabled fraud, disinformation, deepfakes, and surveillance are the harms that many people will feel most keenly in their everyday lives.
AI capabilities are starting to be used for cyberattacks. The smartest cybersecurity experts I know are scared about the next few years, because the attackers are getting powerful new capabilities faster than the defenders can fix all the weaknesses. After all, the same AI model that can find a flaw in software so a company can fix it can also help a criminal exploit it. The resources needed to make an attack are going down significantly and we haven’t been able to separate those abilities from benign usage.
Think about the infrastructure that will be vulnerable: hospitals, financial institutions, water systems, power grids, systems for managing government benefits. When these institutions are attacked, it’s the patients, customers, and benefits recipients who stand to lose.
The same goes for bioterrorism. Although AI will lead to lifesaving advances in drugs and vaccines, it will also make it easier to design a deadly new disease. Again, the positive capabilities are hard to separate from the dangerous ones. This is a global problem.
The risks I’ve just mentioned are all about how AI will empower bad actors who have relatively little power now. The same tools will also concentrate power in places where it already exists. Autonomous weapons, for example, will make governments even more capable of using deadly force without a human being part of the decision. Monitoring and manipulating public opinion will be easier and cheaper, and more effective too.
Eventually, the power to use AI to harm people will not be limited to people or institutions. AI systems themselves already occasionally act in ways their designers didn’t intend. The technology is improving faster than anyone expected and in surprising ways, and as the models become more powerful, they could begin to act against our interests and we could lose control. I’ll have more to say about this in the future.
AI could stunt our kids’ development and replace human relationships.
When I was growing up in Seattle, I didn’t have that many friends aside from a few other boys who were like me. It took hard work and a lot of help from my mom to develop my social skills so I could relate to different kinds of people. I still draw on those lessons today at the age of 70.
I doubt I would have put in the same work if I had had an AI companion back then. They talk to you in ways you’re already comfortable with. They don’t push you outside your comfort zone. They are always available and never get mad at you. This gives them the potential to become highly addictive and to rob us of the lessons we learn from connecting with other people.
The body of evidence on this subject is still small and a bit mixed, but there are signs that we should be very concerned. For example, in one study of more than 1,100 people who use AI companions, researchers at Stanford and Carnegie Mellon found that those with smaller social networks were the most likely to turn to a chatbot for companionship. And the heavier and more emotionally personal that use became, the worse they felt.
Young people could be affected for their entire lives. In his book The Anxious Generation, Jonathan Haidt makes an observation about the effect of social media that is even more true for AI: “Like young trees exposed to wind, children who are routinely exposed to small risks grow up to become adults who can handle much larger risks without panicking. Conversely, children who are raised in a protected greenhouse sometimes become incapacitated by anxiety before they reach maturity.”
An AI companion designed to never upset you is a big, protected greenhouse.
We are only beginning to understand the dangers that the internet—especially social media—can pose to young people’s development. We’re seeing compulsive use, disrupted sleep, cyberbullying, and exposure to harmful content. AI could magnify many of these risks by making them more persuasive and difficult to escape, and we should not wait another generation to start taking them seriously. Countries including Australia, the United Kingdom, and Norway are adopting protections for children online. China has gone the furthest. Its rules restrict AI companion apps broadly, bar designs that foster emotional dependence, and ban virtual relatives and romantic partners for minors.
I’m also worried about AI’s impact on education. Ironically, the same tool that will allow people to learn more than ever could also lead to many people learning less. One preliminary survey suggested that heavier AI use was associated with less critical thinking. The effect was stronger for younger people.
This would be the worst possible time for humans to lose their critical thinking skills. In an era of deepfakes and misinformation that can be tailored to you individually, the ability to tell what is true from what is not becomes an essential life skill.
It’s unclear where to draw the line on these psychosocial problems. In some cases, AI may help people understand how to do better in their human relationships. It may be the only contact with the outside world for isolated elderly people and people with limited mobility, and it will be better than nothing. Wherever we end up drawing the line, it should be our decision, made intentionally.
The good things we do with AI could be very, very good.
It’s often said that we overestimate how much will change in the short term and underestimate how much will change in the long term.
With AI, I see something different going on. Some people see only the upside of AI and do not focus enough on the negatives. Others make the opposite mistake, which is to focus exclusively on the dangers—which are real—at the cost of missing the potential benefits.
We need both: deep concern about the AI harms we need to minimize, and grounded optimism about the positives if we maximize them for everyone.
Maximizing the benefits is just as important as minimizing the harms. If people see how AI makes their lives easier, it will help build the public trust that is necessary for managing the harder parts of the transition. If the first thing AI does in most people’s lives is take away their job, those who are already skeptical about it will outright reject it. This will make it harder to ever deliver on the benefits and it is another reason why governments, industries including the medical industry, and AI companies should be working together now.
With its ability to synthesize knowledge from every scientific field, AI can accelerate innovation in the world’s toughest technical challenges: providing reliable clean energy for everyone, combating climate change, growing enough food, eradicating diseases, and more. Researchers working on cancer treatments or nuclear energy can use AI to search through massive amounts of scientific literature. It can help them identify patterns that a human might miss and decide which experiments offer the most promise. When intelligence is no longer the limiting factor that it is today, smaller companies will be able to compete with organizations that have far larger research budgets. R&D and innovation will be supercharged.
Healthcare is one area where AI can help solve real-world problems. Many small American hospitals lack on-site specialists who can quickly diagnose a patient during a life-threatening emergency. In those places, AI could make sure a heart attack is caught in time and a family avoids the crushing expense of a medical emergency. Viz.ai is one example. It analyzes scans to detect strokes and other emergencies and helps medical teams coordinate their patients’ care. It is being used in nearly 2,000 U.S. hospitals.
AI will also help primary-care doctors make better diagnoses and keep in touch with their patients when they’re not in the clinic. It will help patients understand test results and complicated schedules for taking their medicine.
I surprise a lot of people when I tell them that a second area—agriculture—is where I see the fastest impact of AI in low-income countries. In most low-income countries, farmers don’t get reliable weather forecasts or advice on what seeds to plant, how to protect their crops and livestock from disease, or how to improve their soil. With population growth in these countries and the challenges of climate change, these farmers need more help than ever. Using AI, low-income farmers will soon be able to get better advice about all these things than even the richest farmers get today and increase their output substantially.
Government services are a third area where AI can make people’s lives easier. In the United States, I’ve met families who, understandably, were overwhelmed by the process of applying for health insurance, student aid, or food assistance. Faced with a huge stack of complicated bureaucratic forms, many felt like giving up. AI can streamline things dramatically so they get the help they need faster and the government can operate more efficiently. Governments can make the citizen’s experience far better, starting with those who need its safety net services the most.
Despite my concerns about its impact on our mental health, I think AI can also help a lot there. Most communities have too few counselors, psychiatrists, and addiction specialists. With the right privacy safeguards in place, AI tools could help people recognize warning signs. Then, if needed, they can offer evidence-based coping strategies and team up with a human to provide more responsive treatment.
AI can be a boon for education as well, despite the concerns I mentioned earlier. It can free teachers up to spend more time working with students one on one or in small groups and give them a clearer view of where the whole class is struggling. For students, an AI tool that preserves what researchers call “productive struggle”—the cognitive work that builds understanding—can strengthen learning. When a student first encounters a new idea, the AI gives substantive explanations and offers both questions and answers. Later, when it’s checking their comprehension, it holds the answer back and helps them arrive at it on their own.
Taken together, the advances in all these areas could make everyday life easier, more affordable, and less constrained by a person’s income or connections.
AI could give individuals and small businesses access to capabilities that today require expensive professional help or large staffs, while making products and services better and cheaper. It could help people with disabilities live more independently and enable workers and entrepreneurs with good ideas to accomplish far more than they can today.
Most importantly, it could give people back some of the time and attention now consumed by paperwork, bureaucracy, searching for reliable information, and tasks they cannot afford to pay someone else to handle. These benefits may seem modest, but multiplied across millions of lives, they would be profound: more people getting good advice when they need it and having greater freedom to focus on the lives they want to build.
In all these areas, the operative word is “can”—AI can improve life for people at every income level. But it won’t do that automatically. As with any new technology, we have to be deliberate about ensuring that it benefits everyone and not just a wealthy few. This will require governments and philanthropy to play a strong role so that less wealthy citizens and low-income countries are full beneficiaries.
The Gates Foundation has 19 years left of the 20 years in which it will spend its remaining $200 billion. AI will help it achieve its ambitious goals by both accelerating the discovery of vaccines and medicines for HIV, TB, malaria, and malnutrition and helping the healthcare workforce and patients know how to use those tools. The foundation’s goals include cutting the number of children who die every year in half again, as was done from 2000 to 2024. All of our work, not just health but also agriculture and education, will take full advantage of AI.
I will write much more about these efforts next month in the foundation’s annual Goalkeepers report—including our focus on making sure that AI models are available in the languages spoken by people in all the countries where we support work, and not just the ones that are common in rich and middle-income countries. Many of the leading AI companies, including OpenAI, Anthropic, Google, and Microsoft, are partnering with the foundation on all of these initiatives, which is making a big difference.
The world needs a plan.
It is great that some AI companies are proposing solutions to challenges raised by their own technology, but we should not expect them to lead the charge. Some of the issues are outside their area of expertise, and in a democratic society it’s not their role to decide these things.
Instead, solutions should be developed through a public democratic process that includes elected officials, policymakers, educators, health workers, local officials, and community leaders. Millions of people will have their lives disrupted, and we’ll need a stronger, more flexible social safety net to help them manage the transition. Local communities are already raising concerns about the energy and water needed for data centers. Without solutions, some groups will push for stopping AI development and deployment altogether.
The solutions should be shaped by our answers to the profound questions raised by AI, including how we preserve our humanity in a time when machines can out-think us. As people who spend their lives thinking about what it means to be human, religious leaders can play a key role in this. I was fascinated by Pope Leo XIV’s encyclical on AI, “On Safeguarding the Human Person in the Time of Artificial Intelligence.” It lays a strong foundation for the work that needs to be done.
In the coming months, I will share more ideas for making sure that AI’s benefits outweigh the harm it causes. Here are three to start, beginning with what I think is the most important one.
Build a new system for managing the transition.
The highest priority is a monumental task: creating a domestic and international framework for dealing with AI.
None of our current institutions were designed to handle a technology that spreads so fast and touches so many parts of our lives. So we’ll need to make new ones.
It’s hard to overstate what an enormous undertaking this will be. After the attacks of 9/11, the U.S. government went through its biggest reorganization since World War II for the purpose of improving just one function, national security.
AI will require much, much more. It will affect national security as well as employment, education, taxation, energy, elections, air and water, public health, the financial system, law enforcement, transportation, public lands, and IT systems.
These sectors overlap in ways our existing bureaucracy is not designed to manage. A labor department may understand workforce disruption but not security risk. A business regulator may understand market concentration but not AI’s effects on children and teenagers. Left to themselves, institutions will see only one part of the system, while the consequences of AI will ripple across the entire system.
At the national level, countries will need bodies that can set priorities across government agencies. The goal will be to make sure that every risk is accounted for. Otherwise, an AI-enabled attack might succeed because no one thought it was their job to stop it.
But even a country that gets its own house in order will still be exposed to risks that cross borders. This is why an international organization will need to be built in parallel.
It will be unlike any other institution we have ever created, though it can follow the model of some existing systems. There’s an inspections regime for nuclear weapons, regulations for international aviation, and agreements that protect the ozone layer. A new global organization for AI will need elements of all three and more.
It is fair to wonder whether the world’s institutions are up to the task of designing and implementing this new architecture. Government moves slowly when it moves at all, and polarization within and between countries makes it harder than ever to get things done. Some cooperation between the U.S. and China will be required.
We do not have the luxury of moving slowly. The place to start is with a process for building the right institutions before the disruption forces governments into crisis mode. National leaders should convene economists, technologists, labor experts, business leaders, and workers themselves regularly to identify where existing institutions are failing and what new authorities may be needed. Countries will need to learn from each other.
And the countries that host the leading AI developers and control critical parts of the supply chain should begin meeting now to set up shared norms, before competitive pressure makes it harder for them to cooperate.
Building the framework I’m talking about will take years, which is why we need to start now.
Set aside some jobs for humans.
My dad died of Alzheimer’s in 2020. In the later stages of his illness, he was cared for day and night by paid caregivers who understood him even when he struggled to express himself. He couldn’t always tell them when he was hungry, but they always knew.
My family and I will always be grateful to that amazing group of professionals. Something in the care they gave my dad was irreplaceably human. No robot could or should have done it.
I think about that team when the question of which jobs will disappear and which will remain comes up. I believe that as AI and robots improve, we’ll set aside certain things for only people to do. I’ve started calling this domain Human Reserved, and it’s an example of the kinds of ideas we’ll need to consider.
I like the phrase Human Reserved because it makes me think of nature reserves—places where we could put buildings and roads, but we choose not to because the loss would be too great.
We might set something aside as Human Reserved for economic reasons. For example, we may do it because allowing machines to take over a certain role will displace a large number of people who can’t easily change jobs. You can’t tell a 55-year-old who has worked in construction their whole career that they need to go work at an elder care facility and expect them to find it fulfilling.
Sometimes the decision to make something Human Reserved will be driven by other factors. In health, for example, imagine a robot giving you the awful news that you have an incurable disease. There’s no technical reason why it couldn’t. Yet it shouldn’t.
The Human Reserved domain will evolve over time—for example, we should consider setting aside some jobs now and phasing in AI slowly over years or decades with a commitment to preserve some jobs. Some areas, like education and mental health care, will be a mix, with a human in charge who’s using the technology to extend what they can do.
The lines will also vary from place to place. Some countries might insist on having humans take care of the elderly. But a country like Japan, which has a shrinking workforce and not enough young people to care for the old, may welcome a caregiving robot.
The idea of Human Reserved raises a host of questions I don’t have answers to. Who gets to decide what we reserve for humans? What criteria should we use? How do you keep companies from cheating and using robots anyway? What happens to international trade when one country lets robots make something and another country doesn’t? These will need to be worked out in public as part of the transition plan.
Rebalance how we tax labor and capital.
As workers are pushed into different jobs, they will need retraining and other support from the social safety net. But they will be working less, which means they will be paying less in income taxes, and government revenues will drop just when the demand for those services is greatest. The funds will have to come from somewhere at a time when budgets are stretched.
I believe we should tax AI tokens and robots. Right now, if you’re an employer and you hire someone, you pay payroll taxes on their earnings. But if you buy a robot, you can usually write it off right away as a business expense. The tax system nudges you toward replacing people with machines.
A tax would slow the rush away from human labor a little and raise money for retraining and a stronger safety net. It would need to be targeted so it does not slow down the purely beneficial uses of AI, like making medicine and education cheaper.
Critics of this idea point out that it’s not optimally efficient in an economic sense, but they’re not considering the broader value of work for individuals and society. And with all the accelerated innovation we will have, we’ll be able to afford a little inefficiency as the price for keeping people employed.
I proposed a robot tax years ago and most of the reaction was that it was a strange idea. I’m still a big proponent of it. Although it is not the whole solution to the threat of AI, it is part of a wise response.
However we raise money for more assistance, it needs to reach the people who need it most, including workers who lose their jobs to AI and robots, people whose hours or wages decline, and communities where the losses are concentrated. We need to start doing that work now so that the systems are ready when the need becomes acute.
What I’m doing.
I will use my voice and time to get AI and equity higher on the public agenda. I will raise the issue with lawmakers every time I visit Washington, D.C., and when I meet with leaders around the world. It will be front and center in my conversations with the people who are developing AI models. I will advocate for the national and international framework I described earlier. The Gates Foundation will help drive beneficial usage, including in Africa. Breakthrough Energy, a company I founded, will use AI to help companies develop cheap clean energy and help solve the climate problem. I will also be writing about AI on a regular basis.
My message to leaders is:
You have a chance to act now, before unemployment rises sharply, communities are hurting, and public trust has eroded. You can make sure that your government handles the problem holistically, rather than divvying it up into multiple bureaucratic fiefdoms. You can make sure AI benefits everyone. And you can work with other governments to meet this national and global challenge.
Finally, I will try to widen the circle of people shaping this debate. It should include workers, college students who are about to enter the workforce, community leaders, religious leaders and faith-based organizations, parents, educators, and others whose voices often aren’t heard but who have insight into how the transition will affect people’s lives.
How do we ensure that the benefits of AI reach people who do not already have wealth, influence, and access?
How do we strengthen the social safety net and help workers and communities thrive even when they’re displaced?
How should public institutions adapt?
And how do we preserve our humanity through all of this?
This unprecedented technology demands an unprecedented global response. If we get it right, the payoff for humanity will be phenomenal and the world will be a more equitable place.
I rarely stop thinking about AI—not because I have all the answers, but because the questions it raises are too consequential to leave to a small group of technologists. Leaders across academia, business, government, and civil society all have a role to play in shaping what comes next.
Buzz off
Small bugs, big breakthroughs
Science holds the key to stopping deadly pests like mosquitoes and screwworms.
What do humans and cows have in common? Among other things, we’re both victims of tiny insects.
For cows, the latest culprit is the New World screwworm. Despite the name, the screwworm is actually a type of fly that likes to lay its eggs on animals like cows, which creates an often-fatal wound on the animal’s hide. Screwworms once killed up to one million cattle a year here in the United States, and sixty years after we eliminated them in our country, they’re back.
For humans, one of our greatest nemesis is the mosquito. There are plenty of reasons to hate mosquitoes, but malaria is easily at the top of the list. The disease kills more than 600,000 people every year, most of them children, and it’s transmitted when a mosquito infected with a parasite called Plasmodium bites you.
Protecting people (or cattle) from an insect poses an interesting challenge. How do you stop something so small from hurting anyone? There are lots of different ways to approach the problem.
One approach is to keep insects out of the places where people are. There are already lots of tools that do this with mosquitoes, with more in the pipeline. The most widely used is the bed net, a gauzy sheet of fabric treated with an insecticide that kills any mosquito that tries to reach the person sleeping under it.
Bed nets are magical. In some places where malaria is endemic in Africa, they’ve reduced the number of children who die before the age of 5 by 20 percent. But there’s a problem: Mosquitoes can develop resistance to the insecticide used in bed nets, just like bacteria can evolve resistance to antibiotics.
Enter the dual active ingredient bed net. (You’ll often see them referred to as dual AI nets, even though they have nothing to do with artificial intelligence.) By treating bed nets with two different insecticides, scientists have been able to figure out how to negate a mosquito’s resistance and keep people safe. The catch is that dual AI nets are more expensive than regular bed nets, which is why the Global Fund and the Gates Foundation stepped in to make them affordable for the countries that needed them most. The results so far have exceeded my expectations. Dual AI nets now make up more than half of the bed nets used, just two years after they became available.
Bed nets have another flaw: They only protect you while you’re under them, even though mosquitoes are also active in the hours before you go to sleep and after you wake up. A new tool called a spatial emanator aims to bridge that gap. It basically works like a plug-in air freshener—but instead of releasing a nice fragrance, it slowly releases an insecticide at a low-enough dose that doesn’t harm people but drives away any mosquito that might enter your home.
When spatial emanators received the green light for use a year ago, they became the first new malaria-prevention tool the WHO has recommended in over a decade. I’m super excited about their ability to protect people from mosquitoes for more hours of the day.
Another approach to stopping insects is to target them at the population level. That’s how the world stopped screwworm the first time. In 1954, scientists figured out a way to use radiation to make the males sterile. They released the neutered insects into the target area, and since they couldn’t reproduce, the population died off. This approach worked sixty years ago, and it still works today (and scientists are working on even more effective methods).
What if we could use a similar approach to stop mosquitoes? Last year, I wrote about an incredible project in Tanzania called Transmission Zero. The idea behind it is simple: a mosquito that can’t give you malaria.
Tanzanian scientists have found a way to make Anopheles gambiae mosquitoes—the species responsible for most of the malaria in Africa—produce two types of molecules, naturally found in frogs and bees, that block the parasite from developing inside the insect. The mosquitoes would continue flying around, doing their mosquito business, but they wouldn’t be able to make anyone sick with malaria. Each time they mated with another mosquito, they would pass on the gene that protected them from the parasite. (I just published a new profile of Dr. Lina Finda from the Ifakara Health Institute in Tanzania, who is helping lead this work.)
These malaria-free mosquitoes could potentially help save tens of thousands of lives every year. And Tanzania isn’t the only country on the cutting edge of advancing this work. The Ugandan Virus Research Institute and the University of Sciences, Techniques and Technologies of Bamako in Mali are also doing pioneering work to move the field forward. Scientists are learning more every day about the role mosquitoes play in ecosystems, and research is now underway on two other species beyond Anopheles gambiae.
Dual AI bed nets, spatial emanators, and malaria-free mosquitoes are just the latest breakthroughs to come out of the robust malaria innovation pipeline. Treatments continue to get better, and vaccines are already proving to save lives, with even more effective next-gen vaccines to come. A lot of interesting work is underway with endectocides, a type of drug that could potentially make your blood toxic to mosquitoes. There’s even a fascinating trial that looks at whether targeting mosquito larvae in rice paddies could make a difference. The goal of this trial is to stop malaria, but early results from Nigeria and Rwanda indicate that larval control could boost rice yields as much as 50 percent, which would be incredible for farmers.
Unfortunately, while the R&D progress we’re making is remarkable, the same can’t be said for the fight against malaria overall. Donor governments are cutting health aid—including money for the Global Fund, which has saved more than 70 million lives to date by helping deliver lifesaving tools like bed nets. Last year, our partners across Africa pulled off a miracle to minimize the impact of the cuts. With support from our foundation, they found creative ways to distribute supplies that were already in warehouses across the continent.
This year, the picture looks different. While some funding has since been restored, cuts from multiple donor governments mean it's not yet enough to guarantee bed nets and other tools reach every family who needs them. Our foundation is doing everything we can to help close that gap. I continue to advocate for increased funding, because it is ridiculous to put the health of the world’s children at risk when we know how to save them.
I believe we can end malaria forever. We have some of the tools we need already, and I think we’ll have the rest soon. We can defeat mosquitoes, just like we stopped screwworm more than half a century ago and just like we’ll stop it again. The question is whether the world will choose to make it happen.
The choice is obvious to me. We have an opportunity to ensure that no child dies from malaria ever again. Let’s take it.















Gone for good
“AIDS-free generation” is no empty promise
New tools mean we’ll be able to stop the pandemic forever.
PrEP talk
From once a day to twice a year
Long-acting preventatives will save more lives from HIV/AIDS.
I’ve been working in global health for two and a half decades now, and the transformation in how we fight HIV/AIDS is one of the most remarkable achievements I’ve witnessed. (It’s second only to how vaccines have saved millions of children's lives.)
At the dawn of the AIDS epidemic, an HIV diagnosis was often a death sentence. But in the years since, so much has changed. Today, not only do we have anti-retroviral medications that allow people with HIV to live full, healthy lives with undetectable viral loads—meaning they can’t transmit the virus to others. We also have powerful preventative medications known as PrEP, or pre-exposure prophylaxis, that can reduce a person’s risk of contracting the virus by up to 99 percent when taken as prescribed. It’s an incredible feat of science: a pill that virtually prevents HIV contraction.
In theory, if we could get these tools to everyone who needs them and make sure they’re used correctly, we could stop HIV in its tracks. Because when people with the virus receive proper treatment, they can’t transmit it to others. And when people at risk take PrEP, they can’t contract it. In practice, however, getting these tools to people—and making sure they’re used correctly—is the hard part. Especially for PrEP.
That’s because current preventatives require people to take medication every single day. Miss a dose, and protection drops. It’s like trying to remember to lock your front door 365 times a year—if you mess up once, you’re vulnerable. For many people, the barriers stack up quickly. Some have to walk hours to reach a clinic. Others struggle to store medication safely or discreetly at home. And many face judgment and stigma for taking PrEP, especially young women in conservative communities. The very act of protecting yourself can lead to being shamed or ostracized.
That’s why I’m so excited about a new wave of innovations in HIV prevention. Scientists are in the process of developing several longer-lasting PrEP breakthroughs, each with distinct advantages that could help more people protect themselves on their own terms.
Lenacapavir, which requires only two doses per year through injection, could open HIV prevention up to people who can’t make frequent clinic visits. Cabotegravir, another injectable option that works for two months at a time, offers a more flexible dosing schedule than daily PrEP pills, too. Meanwhile, a monthly oral medication called MK-8572, still in the trial stage, could provide an alternative for people who prefer pills to injections. The Gates Foundation is even exploring ways to maintain a person’s protection for six months or longer. And researchers are working on promising PrEP options that include contraception, which would be particularly valuable for women who need both types of protection.
To understand how these options work in real life, and not just in labs, our foundation has supported implementation studies in South Africa, Malawi, and elsewhere. Unlike traditional clinical trials that test safety and efficacy in highly controlled settings, these studies examine how medications fit into people’s lives and work in everyday circumstances—looking at ease of use, cultural acceptance, and other practical challenges. This real-world understanding is crucial for successful adoption.
Some people ask me if these new preventative tools mean the Gates Foundation has given up on finding an HIV vaccine. Not at all. In fact, these advances push us to aim even higher in our research for a vaccine that could prevent HIV for a lifetime—and not just a few months at a time. Our goal is to create multiple layers of protection, much like modern cars have seatbelts, airbags, and even collision-warning sensors. Different tools work better for different people in different ways, and we need every tool we can get.
But even the most brilliant innovations make no difference unless they reach the people who need them most. This is where partnerships become crucial. Through grants to research institutions around the world, the foundation is working to lower manufacturing costs for HIV drugs so they’re accessible to everyone, everywhere. Then there are organizations like the Global Fund and PEPFAR, which have been instrumental in turning scientific advances into real-world impact.
The Global Fund—which needs to raise significant new resources next year to continue its work—currently helps more than 24 million people access HIV prevention and treatment. And PEPFAR has saved 25 million lives since its inception in 2003—a powerful example of how American leadership can build tremendous goodwill while transforming the world. Motivated by the belief that no person should die of HIV/AIDS when lifesaving medications are available, President George W. Bush created PEPFAR with strong bipartisan backing and it continues to serve as a lifeline to millions of people.
We're at a pivotal moment in this fight. Twenty years ago, many believed it would be impossible to deliver HIV treatment at scale in Africa’s poorest regions. Since then, we’ve made fantastic progress. Science has shown us promising paths forward—for better prevention options, easier treatment regimens, and, maybe one day, an effective vaccine. Our task now? Ensuring the life-saving innovations we already have reach the people whose lives they can save.

Inspired by a farmer
These married scientists are leading the way on HIV
The Abdool Karims revolutionized the fight against AIDS. Now they’re helping the world tackle COVID-19 too.
Quarraisha and Salim Abdool Karim are two of the most respected HIV/AIDS researchers in the world. This year, the wife-and-husband team has also helped shape the world’s response to COVID-19. But it was a more humble setting that sparked their careers in epidemiology more than 30 years ago.
They had met in medical school in their native South Africa before moving to New York City for graduate school. In 1988, shortly after they were married, they took a trip to Mexico, where they met up in a tiny village in the Sierra Madre mountains with a friend, a physician who had written a seminal textbook on health care in remote rural settings.
Outside the village’s health clinic, they saw a man pedaling a bicycle that was mounted on a stand and connected to a power cable. It turned out that a local farmer also doubled as the village’s dentist—a pretty good one, apparently—and volunteers would pedal the bike to power his drill.
“We watched how this community took their destiny in their own hands,” says Salim, “and they had the most amazing dental care from this bicycle powering a drill. It imprinted on us how people can really change their own world.”
It was a powerful lesson about the need for scientists to understand and collaborate with the people they’re trying to help. The experience in that village would shape the rest of their careers, especially when they created a research center in South Africa designed to address two of the biggest problems in HIV/AIDS in Africa.
By the 1990s, the disease was devastating the Abdool Karims’ home country—and still is today. One out of every five people in the world with HIV lives in South Africa. The couple saw two issues that were rarely on the agenda of other HIV experts. One was that young women were bearing a disproportionate burden in the epidemic, and that there was no way to control the epidemic if their needs weren’t addressed. The other was that people living with HIV are at a high risk of contracting and dying from tuberculosis—a link that’s now known as HIV-TB coinfection.
“These were very much our problems in Africa that few others were working on,” says Quarraisha, “and if we waited for solutions from elsewhere, it wasn’t going to come. We had to take the lead.”
In 2001, they brought together a group of researchers they felt could make a bigger impact on HIV and named the group CAPRISA (for the Center for the AIDS Program of Research in South Africa). Today CAPRISA runs three clinics where they provide antiretrovirals to people living with HIV and study new approaches to treating and preventing the disease. It is regarded as one of the world’s most influential AIDS research programs.
CAPRISA is probably best known for a landmark study published in 2010 proving for the first time that a microbicide—a gel that a woman could use before and after sex—can offer some protection from the virus. Scientists had been trying to make effective microbicides for nearly two decades, but the Abdool Karims’ formulation—one that used tenofovir, a drug normally given to people who already had HIV—was the first to offer any protection. Although the field has now moved on from microbicides and is focused on a more effective daily pill instead, the concept is still based on CAPRISA’s microbicide findings.
CAPRISA is as admired for the way it works as for its results. Inspired by the farmer-dentist they met in Mexico, Salim and Quarraisha make it a priority to empower the people they’re trying to help. They work closely with community leaders to make sure their research efforts are informed by realities on the ground and embraced by their neighbors. Here’s the story of one remarkable CAPRISA staff member, Gethwana Mahlase, and the way she represents the program in her community of Vulindlela.
Over the next few years, Quarraisha and Salim hope to build on their study of tenofovir as an HIV preventative. Right now, the best option is a pill you have to take every day, a regimen that can be hard to keep up. So CAPRISA is working on a form of the drug that could protect a woman for as long as a year at a time.
They’re also working on a fascinating approach called “broadly neutralizing antibodies,” which dates back several years. In 2012, they discovered that an HIV-positive woman in one of CAPRISA’s studies had a trait that was, as far as they knew, unique. The antibodies made by her immune system could attack not only the strain of HIV that she had, but also—this was the impressive part—80 percent of the other known strains of HIV from around the world. If they could isolate the cells that made these antibodies, reproduce them, and use them to create antibodies for other people, it would be a game changer.
After years of painstaking work with a number of partners, they were able to create the broadly neutralizing antibodies in a lab and test them in monkeys, with very positive results. Now the antibodies are being studied in humans for safety and, eventually, efficacy. If this approach works, you would need to get an injection just twice a year in order to get protection—a dosage that is far more practical than a daily pill. Success would also point the way toward the ultimate goal of an HIV vaccine.
Unfortunately, much of the Abdool Karims’ attention has been elsewhere this year. Drawing on their experiences from HIV and TB, they are helping guide the COVID-19 response in South Africa and around the world. It is a shame that they haven’t been able to focus on HIV/AIDS, but on the other hand, it is a reminder of how fighting old diseases like HIV helps the world prepare for new ones like COVID-19. Investing long-term in programs like CAPRISA—or work on polio or malaria—not only prevents deaths and disability from specific diseases, it also strengthens the overall field of global health. So when a pandemic comes along, we have a network of experts like Quarraisha and Salim ready to pitch in.
What strikes me about this couple is how upbeat they are, even in the face of devastating diseases like the coronavirus and HIV. Their motto at CAPRISA is, “Each day that you come to work, you should be looking for how today is going to be better than yesterday.” That is a lesson we can all take to heart.
Heroes
Strength in numbers
The story of this amazing woman living with HIV in Mozambique fuels my optimism about our world.
Last year, at an event in New York, I learned about an impressive woman whose story I want to share with you. Her name is Cacilda Fumo, she lives in Mozambique, and every year she helps save hundreds of lives—by reminding them they are not alone.
Mozambique has one of the highest HIV infection rates in the world. More than 1.6 million people—10 percent of the adult population—are living with HIV.
Cacilda was diagnosed with HIV in 2002. “When I first learned about it, I thought I would die,” she recalls. “I used to wake up early morning and check if I am alive or not.”
But then she started meeting other people living with HIV, and as their numbers grew so did her strength and her belief she would live. Cacilda was one of the first in Maputo to be open about her status. She started wearing a t-shirt emblazoned with a logo that reads: “HIV POSITIVE.”
At times, people rejected her because of her status. Many more in her community, however, admired her for her courage, helping her create an even larger circle of friends and supporters. They met every week, praying together, cooking together, and sharing their stories. Eventually, the group had about one hundred people, many of them receiving life-saving anti-retroviral treatment. Cacilda emerged as their leader.
About the same time, Mozambique’s Ministry of Health was struggling to improve the delivery of anti-retroviral treatment. While the program was successful in putting thousands of patients on treatment for the first time, medical staff were overburdened with caseloads. People on HIV treatment often walked miles to reach their clinic and waited in long lines to get care. Every year, about 30 percent of HIV patients dropped off their life-saving treatment.
Working with Doctors Without Borders, the government of Mozambique decided to try a new approach to simplify care to help keep more people on treatment. They started organizing small peer support groups for people on HIV treatment. The idea was simple. Make treatment easier by putting more control into the hands of the patients. A representative from each patient group could pick up all the drugs for the group each month, saving the rest of the group the hassle of going to the clinic. Members of the groups, known as Community antiretroviral therapy (ART) Groups or CAGs, would also support one another to ensure they were all staying on their treatment.
When the program reached Maputo, Cacilda was ready to join. She helped organize dozens of support groups from her network. Then she went one step further. She kept track of the groups, checking whether members were attending their meetings and taking their treatment. If someone fell off treatment, she took upon herself to locate them and find out what was wrong.
“We help people feel strong knowing they are not alone,” she says.
Some patients who stop treatment are addicted to alcohol and forget to take their treatment, she says. Some don’t understand how the treatment works and the stop taking their medication as soon as they feel better. Others get busy with their jobs and drift away.
Whatever the reason, Cacilda warns them of the dangers of stopping treatment and encourages them to restart. Her efforts to bring back residents of Maputo to treatment has become nearly full-time work. Most days residents of Maputo see Cacilda traveling on foot—which is remarkable because due to a childhood injury she uses crutches—through the dirty alleyways and crowded markets in search of people who have stopped treatment. She doesn’t give up until she finds them.
Cacilda’s persistence pays off—in lives saved. Cacilda estimates that she tracks down about 500 people every year and encourages them to resume their treatment.
That’s a remarkable achievement—one that proves how much difference one life can make in the world.
Eye opener
What my favorite chart leaves out
Every year, 2 million babies are stillborn. A simple retinal scanner can change that.
If you’re anything like me, you have a favorite chart. Mine has been the same for years. It plots under-five mortality year over year—a figure that has dropped by half since the turn of the century, from over 10 million deaths in 2000 to fewer than 5 million in 2023.
In my view, this data is the strongest evidence we have that progress is possible, even in tough times, and that the investments the world has made in vaccines, oral rehydration, bed nets, and better nutrition are working.
But there's a rule in global health statistics that complicates the story: To count as a death, someone must have first been born alive. It sounds simple and obvious. But in practice, it isn't. That's because every year, about 2 million pregnancies end in stillbirth, which is when a baby is lost at 28 weeks or later. That's late enough that the mother has been feeling the fetus move for months. Many parents have already picked out a name. Often, the loss occurs in the final stretch of a pregnancy, or during labor itself, when everyone was expecting a healthy birth.
These tragedies should be central to how we measure child survival. Instead, they've fallen through the cracks—not quite a maternal health issue, not quite a child mortality issue. The UN didn't publish its first full global estimate of stillbirths until 2020, and stillbirth research is still badly underfunded in both rich and poor countries.
What gets measured gets managed, as the saying goes—and what doesn't, well, doesn't.
The data reflects this disparity. Stillbirths have fallen just 34 percent since 2000, compared to 50 percent for under-five mortality over the same period. In 81 countries—mostly low- and middle-income—the stillbirth rate hasn't meaningfully improved at all in 25 years. For every one stillbirth in Europe, there are roughly 40 in sub-Saharan Africa.
What's frustrating is that we know what causes, and therefore how to prevent, most stillbirths. One of the biggest drivers is pre-eclampsia—a dangerous spike in blood pressure during pregnancy—which is responsible for half a million fetal deaths every year, along with 70,000 maternal deaths. Beyond that, the bulk of stillbirths stem from a cluster of conditions we understand well: maternal infections, obstetric complications during labor, and chronic conditions like untreated diabetes.
If we could catch these problems earlier, we'd have a much better chance of intervening before it's too late. But that's hard to do in the rural clinics where most pregnant women receive care, which often have unreliable electricity, no specialists, and little in the way of lab equipment. By the time pre-eclampsia is obvious, or gestational diabetes has gone unmanaged through the third trimester, the harm is often irreversible. Even emergency intervention may not help.
But a few months ago, I got to hold a device that has the potential to make a huge impact: the Remidio fundus camera. You hold it up to a patient's eye to get a high-resolution image of their retina in seconds, no dilation required. A community health worker with a few hours of training can use it. The device itself is about the size of a handheld video camera, battery-powered, and portable enough to carry from village to village.
Why the retina? It's the only place in the body where you can see blood vessels from the outside.
Remidio is a medtech startup out of India, and its camera was originally built to screen for diabetic eye disease. With an AI system running on a phone the camera plugs into, it can pick up early signs of the disease that would otherwise require blood draws and specialist follow-up to catch. It's already been used that way for more than 15 million patients in 40 countries.
But that same hardware, with different software, can also flag the conditions that drive so many dangerous pregnancies. Gestational diabetes sharply increases the risk of pre-eclampsia, preterm birth, and fetal death, and in most of rural sub-Saharan Africa or South Asia, it usually isn't screened for at all, because the standard test requires a lab. A retinal scan offers a different way in. Remidio’s device is currently being used in India to screen pregnant women for conditions that drive stillbirth. And researchers are now adapting the same hardware to screen for anemia and hypertension, too.
A tool like Remidio’s won’t solve the problem of stillbirths alone. We also need more skilled birth attendants, better emergency obstetric care, and stronger health systems. But small, portable, affordable diagnostics in the hands of community health workers are exactly the kind of lever that can start to move a number that hasn't moved in a long time. That's a big part of why the foundation committed $2.5 billion to women's health research and development last year, our largest investment in this area ever.
In 25 years, I hope my favorite chart in the world will have two lines on it: one tracking under-five mortality, and one tracking stillbirths. With the right commitment, I believe both will have fallen dramatically, and both could be approaching zero.

Life and death
How to cut child mortality in half… again
We already know how to save millions of newborn lives.
When Paul Allen and I started Microsoft, we had an ambitious goal: to put a computer on every desk and in every home. A lot of people thought we were out of our minds. But we believed in the power and potential of these machines to change the world. So every day, we came to work determined to make it happen. Now, it’s hard to imagine the world any other way. In a few short decades, that goal became reality for billions.
In 1990, the possibility that the world would be able to cut child mortality in half over the next thirty years would have seemed just as remote. But that’s exactly what happened. And I believe the world can do it again by 2040—we can cut child mortality in half once more—and get even closer to ending all preventable child deaths.
My introduction to this issue came 27 years ago, when I read a piece in The New York Times about deadly drinking water in the world’s poorest countries that contained the following statistic: “Diarrhea kills some 3.1 million people annually, almost all of them children.” Learning that shocked me to my core. There’s no greater pain than the death of a child. The death of millions of them—from something easily treatable in much of the world—is tragedy after tragedy on an almost unfathomable scale.
Before long, I was learning everything I could about global health generally and child mortality specifically. And shortly after, the Gates Foundation, which was just getting off the ground, made it our mission to fight preventable health disparities like this around the world—with an emphasis on children whose lives were being cut short before they ever had a chance.
Life Line
A phone call that saves lives
m-mama uses mobile technology and community drivers to solve one of global health’s most persistent problems: Getting pregnant women to hospitals in time.
In the United States, when someone has a medical emergency, we take for granted that an ambulance will arrive. It will get to some places faster than others—a disparity driven by wealth and other factors. Still, by calling 911, we’re immediately connected to a vast fleet of emergency vehicles plugged into a system that’s designed to get people to hospitals in times of crisis.
But what about countries where ambulances aren’t readily accessible? What about places where even cars are scarce, where the nearest hospital with surgical capacity might be 100 miles away down an unpaved road, and where a family facing a medical crisis has no reliable way to get there or pay for the journey?
This is the reality for millions of pregnant women across sub-Saharan Africa.
Thanks to modern medicine, we now know how to prevent most maternal and newborn deaths. And maternal mortality has declined by 40 percent over the last two decades as a result. But hundreds of thousands of women and babies still die every year from complications during pregnancy and childbirth, because they can’t get to a place where someone can treat them in time.
In maternal health, this problem is called the “second delay.” It’s a terrible tragedy, one that the Gates Foundation has been trying to address for years.
Back in 2013, partners including Vodafone Foundation and local health organizations started tackling this problem by asking a simple question in rural Tanzania: What if you could create something like a 911 system that worked with whatever transportation was available in a community? They tested the idea in a few districts, and it worked well enough that they decided to scale it up. They called it m-mama.
m-mama works like this: When a community healthcare worker identifies an emergency—maybe it’s severe bleeding after delivery, or a premature baby who can’t breathe—they call a free hotline. A trained nurse dispatcher uses an app to figure out what kind of care is needed and where it’s available, then coordinates whatever transportation makes sense for that location (a community driver with a car where there are good roads, a motorcycle where there aren’t, a boat for island communities, even a horse for mountainous terrain.) The dispatcher stays on top of everything, tracking the journey, alerting the receiving facility, and handling payment at the end.
The numbers speak for themselves. Since 2013, m-mama has responded to more than 125,000 emergencies and saved an estimated 5,266 lives. And in regions where m-mama launched, maternal emergency transports more than doubled. That means there was a massive need that was going unmet for far too long. About 58% of the deliveries transported by m-mama end up requiring a C-section, compared to the 10-15% you would expect in the general population. These are genuinely high-risk cases that would have likely ended in tragedy without emergency transport.
What’s especially impressive about m-mama’s impact is that it hasn’t required building new hospitals or buying any expensive equipment. Instead, it makes existing health systems work better by coordinating resources that are already there—ambulances, facilities, healthcare workers—and filling gaps with options that cost a fraction of what traditional ambulances do.
And it is scaling. m-mama started as a pilot serving 750,000 people and now reaches 62 million in Tanzania. It’s gone nationwide in Lesotho. It just launched in Malawi and is scaling up in Kenya. There are plans for more countries across sub-Saharan Africa, supported in part by the Beginnings Fund—a partnership that includes our foundation, the Mohamed bin Zayed Foundation for Humanity, and other organizations working to improve maternal and newborn health across Africa.
The program is financially sustainable too. Once the program is up and running, the governments cover operating costs. m-mama has proven it can be owned and run locally, which is the only way something like this works long-term.
m-mama is a reminder that not all breakthroughs in global health are new drugs or sophisticated technology. Sometimes they’re just smart ways of getting the right care to the right person at the right time. When a mother or baby is in crisis, minutes can make the difference between life and death.
m-mama is making sure those minutes count.
The Year Ahead
Optimism with footnotes
As we start 2026, I am thinking about how the year ahead will set us up for the decades to come.
I have always been an optimist. When I founded Microsoft, I believed a digital revolution powered by great software would make the world a better place. When I started the Gates Foundation, I saw an opportunity to save and improve millions of lives because critical areas like children’s health were getting so little money.
In both cases, the results exceeded my expectations. We are far better off than when I was born 70 years ago. I believe the world will keep improving—but it is harder to see that today than it has been in a long time.
Friends and colleagues often ask me how I stay optimistic in an era with so many challenges and so much polarization. My answer is this: I am still an optimist because I see what innovation accelerated by artificial intelligence will bring. But these days, my optimism comes with footnotes.
The thing I am most upset about is the fact that the world went backwards last year on a key metric of progress: the number of deaths of children under 5 years old. Over the last 25 years, those deaths went down faster than at any other point in history. But in 2025, they went up for the first time this century, from 4.6 million in 2024 to 4.8 million in 2025—an increase driven by less support from rich countries to poor countries. This trend will continue unless we make progress in restoring aid budgets.
The next five years will be difficult as we try to get back on track and work to scale up new lifesaving tools. Yet I remain optimistic about the long-term future. As hard as last year was, I don’t believe we will slide back into the Dark Ages. I believe that, within the next decade, we will not only get the world back on track but enter a new era of unprecedented progress.
The key will be, as always, innovation. Consider this: An HIV diagnosis used to be a death sentence. Today, thanks to revolutionary treatments, a person with HIV can expect to live almost as long as someone without the virus. By the 2040s, new innovations could virtually eliminate deaths from HIV/AIDS.
Budget cuts limit how many people benefit from lifesaving tools, as we saw to devastating effect last year. But nothing can erase the fact that for decades we didn’t know how to save people from HIV, and now we do. Breakthroughs are a bell that cannot be unrung. They ensure that we will never go back to the world in 2000 where over 10 million children died from preventable causes every year—and they form the core of my optimism about where the world is headed.
But as I mentioned, there are footnotes to my optimism. Although the innovation pipeline sets us up for long-term success, the trajectory of progress hinges on how the world addresses three key questions.
1.
Will a world that is getting richer increase its generosity toward those in need?
The “golden rule” precept is more important now than ever with the record disparities in wealth. This idea of treating others as you wish to be treated does not just apply to rich countries giving aid. It must also include philanthropy from the wealthy to help those in need—both domestically and globally—which should grow rapidly in a world with a record number of billionaires and even centibillionaires.
Through the Giving Pledge, I get to work with a number of incredible philanthropists who set a great example by giving away substantial portions of their wealth in smart ways. However, more needs to be done to encourage higher levels of generosity from the rich and to show how fulfilling and impactful it can be.
Turning to aid budgets for poor countries, I am worried about one number: If funding for health decreases by 20 percent, 12 million more children could die by 2045. I know cuts won’t be reversed overnight, even though aid represented less than 1 percent of GDP even in the most generous countries. But it is critical that we restore some of the funding. The foundation’s Goalkeepers report lays out what is at risk and how the world can best spend the aid it gives.
I will spend much of my year working with partners to advocate for increased funding for the health of the world’s children. I plan to engage with a number of communities, including health care workers, religious groups, and members of diaspora communities to help make this case.
2.
Will the world prioritize scaling innovations that improve equality?
Some problems require doing far more than just letting market incentives take their course.
The first critical area is climate change. Without a large global carbon tax (which is, unfortunately, politically unachievable), market forces do not properly incentivize the creation of technologies to reduce climate-related emissions.
Yet only by replacing all emitting activities with cheaper alternatives will we stop the temperature increase. This is why I started Breakthrough Energy 10 years ago and why I will continue to put billions into innovation.
The world has made meaningful progress in the last decade, cutting projected emissions by more than 40 percent. But we still have a lot of innovation and scaling up to do in tough areas like industrial emissions and aviation. Government policies in rich countries are still critical because unless innovations reach scale, the costs won’t come down and we won’t achieve the impact we need.
If we don’t limit climate change, it will join poverty and infectious disease in causing enormous suffering, especially for the world’s poorest people. Since even in the best case the temperature will continue to go up, we also need to innovate to minimize the negative impacts.
This is called climate adaptation, and a critical example is helping farmers in poor countries with better seeds and better advice so they can grow more even in the face of climate change. Using AI, we will soon be able to provide poor farmers with better advice about weather, prices, crop diseases, and soil than even the richest farmers get today. The foundation has committed $1.4 billion to supporting farmers on the frontlines of extreme weather.
I will be investing and giving more than ever to climate work in the years ahead while also continuing to give more to children’s health, the foundation’s top priority. The need to ensure money is spent on the most important priorities was the topic of a memo I wrote in the fall.
A second critical area where the world must focus on innovation-driven equality is health care. Concerns about healthcare costs and quality are higher than ever in all countries.
In theory, people should feel optimistic about the state of health care with the incredible pipeline of innovations. For example, a recent breakthrough in diagnosing Alzheimer’s will revolutionize how we test for—and ultimately prevent—this disease, saving billions of dollars in costs. (Funding Alzheimer’s research is a particular focus for me.) There’s similar progress on obesity and cancer, as well as on problems in developing countries like malaria, TB, and malnutrition.
Despite so much progress, however, the cost and complexity of the system means very few people are satisfied with their care. I believe we can improve health care dramatically in all countries by using AI not only to accelerate the development of innovations but directly in the delivery of health care.
Like many of you, I already use AI to better understand my own health. Just imagine what will be possible as it improves and becomes available for every patient and provider. Always-available, high-quality medical advice will improve medicine by every measure.
We aren’t quite there yet—developers still have work to do on reliability and how we connect the AI to doctors and nurses so they are empowered to check and override the system. But I’m optimistic we will soon begin to scale access globally. I am following this work so the Gates Foundation and partners can make sure this capability is available in the countries that need it most—where there aren’t enough medical personnel—at the same time it is available elsewhere. We are already working on pilots and making sure that even relatively uncommon African languages are fully supported.
Governments will have to play a central role in leading the implementation of AI into their health systems. This is another case where the market alone won’t and can’t provide the solution.
A third and final area I will mention briefly is education. AI gives us a chance for the kind of personalized learning to keep students motivated that we have dreamed of in the past. This is now a focus of the Gates Foundation’s spending on education, and I am hopeful it will be empowering to both teachers and students. I’ve seen this firsthand in New Jersey, and it will be game changing as we scale it for the world.
All three of these areas—climate, health, and education—can improve rapidly with the right government focus. This year I will spend a lot of time meeting with pioneers all over the world to see which countries are doing the best work so we can spread best practices.
3.
Will we minimize negative disruptions caused by AI as it accelerates?
Of all the things humans have ever created, AI will change society the most. It will help solve many of our current problems while also bringing new challenges very different from past innovations.
When people in the AI space predict that AGI or fully humanoid robots will come soon and then those deadlines are missed, it creates the impression that these things will never happen. However, there is no upper limit on how intelligent AIs will get or on how good robots will get, and I believe the advances will not plateau before exceeding human levels.
The two big challenges in the next decade are use of AI by bad actors and disruption to the job market. Both are real risks that we need to do a better job managing. We’ll need to be deliberate about how this technology is developed, governed, and deployed.
In 2015, I gave a TED talk warning that the world was not ready to handle a pandemic. If we had prepared properly for the Covid pandemic, the amount of human suffering would have been dramatically less. Today, an even greater risk than a naturally caused pandemic is that a non-government group will use open source AI tools to design a bioterrorism weapon.
The second challenge is job market disruption. AI capabilities will allow us to make far more goods and services with less labor. In a mathematical sense, we should be able to allocate these new capabilities in ways that benefit everyone. As AI delivers on its potential, we could reduce the work week or even decide there are some areas we don’t want to use AI in.
The effects of this disruption are hard to model. Sometimes, when a game-changing technology improves rapidly, it drives more demand at lower cost and, by making the world richer, increases demand in other areas. For example, AI makes software developers at least twice as efficient, which makes coding cheaper while also creating demand elasticity for code. (Computing is a good historical example where lower costs actually caused the overall market to grow.)
Even with this complexity, the rate of improvement is already starting to be enough to disrupt job demand in areas like software development. Other areas like warehouse work or phone support are not quite there yet, but once the AIs become more capable, the job disruption will be more immediate.
We’re already starting to see the impact of AI on the job market, and I think this impact will grow over the next five years. Even if the transition takes longer than I expect, we should use 2026 to prepare ourselves for these changes—including which policies will best help spread the wealth and deal with the important role jobs play in our society. Different political parties will likely suggest different approaches.
By including these footnotes, particularly the last one, some readers may find my continued optimism even more surprising. But as we start 2026, I remain optimistic about the days ahead because of two core human capabilities.
The first is our ability to anticipate problems and prepare for them, and therefore ensure that our new discoveries make all of us better off. The second is our capacity to care about each other. Throughout history, you can always find stories of people tending not just to themselves or their clan or their country but to the greater good.
Those two qualities—foresight and care—are what give me hope as the year begins. As long as we keep exercising those abilities, I believe the years ahead can be ones of real progress.
Just the facts
Health aid saves lives. Don’t cut it.
Here’s the proof I’m showing Congress.
I’ve been working in global health for 25 years—that’s as long as I was the CEO of Microsoft. At this point, I know as much about improving health in poor countries as I do about software.
I’ve spent a quarter-century building teams of experts at the Gates Foundation and visiting low-income countries to see the work. I’ve funded studies about the effectiveness of health aid and pored over the results. I’ve met people who were on the brink of dying of AIDS until American-funded medicines brought them back. And I’ve met heroic health workers and government leaders who made the best possible use of this aid: They saved lives.
The more I’ve learned, the more committed I’ve become. I believe so strongly in the value of global health that I’m dedicating the rest of my life to it, as well as most of the $200 billion the foundation will give away over the next 20 years.
People in global health argue about a lot of things, but here’s one thing everyone agrees on: Health aid saves lives. It has helped cut the number of children who die each year by more than half since 2000. The number used to be more than 9 million a year; now it’s fewer than 5 million. That’s incontrovertible.
So when the United States and other governments suddenly cut their aid budgets the way they've been doing, I know for a fact that more children will die. We’re already seeing the tragic impact of reductions in aid, and we know the number of deaths will continue to rise.
A study in the Lancet looked at the cumulative impact of reductions in American aid. It found that, by 2040, 8 million more children will die before their fifth birthday. To give some context for 8 million: That's how many children live in California, Texas, Florida, New York, Pennsylvania, and Ohio combined.
I’ve submitted written testimony on this topic, which you can read below, for the Senate Appropriations Committee hearing occurring later today. In it, I discuss what’s already happened and what needs to happen next.
Testimony to the United States Senate Committee on Appropriations
June 25, 2025
Over the past 25 years—the same span of time I spent leading Microsoft—I have immersed myself in global health: building knowledge, deepening expertise, and working to save lives from deadly diseases and preventable causes. During that time, I have built teams of world-class scientists and public health experts at the Gates Foundation, studied health systems across continents, and worked in close partnership with national and local leaders to strengthen the delivery of lifesaving care. I have visited hundreds of clinics, listened to frontline health workers, and spoken with people who rely on these programs. Earlier this month, I traveled to Ethiopia and Nigeria, where I witnessed firsthand the impact that recent disruptions to U.S. global health funding are having on lives and communities.
Global health aid saves lives. And when that aid is withdrawn—abruptly and without a plan—lives are lost.
Yet, in recent months, some have questioned whether the foreign assistance pause has caused harm. Concerns about the human impact of these disruptions have been dismissed as overstated. Some people have even claimed that no one is dying as a result.
I wish that were true. But it is not.
It is important to note that while this hearing is about the Trump Administration’s $9 billion recission package, what is really at stake is tens of billions of dollars in critical aid and health research that has been frozen by DOGE with complete disregard for the Congress and its Constitutional power of the purse.
In the early weeks of implementing the foreign aid freeze, DOGE directives resulted in the dismissal of nearly all United States Agency for International Development (USAID) staff and many personnel at the Centers for Disease Control and Prevention (CDC). Some funding was later restored to allow for the continuation of what has been categorized as "lifesaving" programs. However, to date that designation has been applied narrowly and with limited transparency, in an inconsistent manner, often prioritizing emergency interventions when a patient is already in critical condition over essential preventative or supportive care.
For example, providing a child with a preventive antimalarial treatment, ensuring access to nutrition so that HIV/AIDS medications can be properly administered, testing pregnant women for HIV to see if they are eligible for treatment to prevent transmission to their children or identifying and treating tuberculosis cases early have not consistently qualified for exemption. As a result, many of the programs delivering these services have been suspended, delayed, or scaled back.
Recent reporting from the New York Times has shed light on the devastating human cost of the abrupt aid cuts. One especially tragic example is Peter Donde, a 10-year-old orphan in South Sudan, born with HIV, who died in February after losing his access to life-saving medication when USAID operations were suspended. His story is one of many.
During my recent visit to Nigeria, I met with leaders from local nonprofit organizations previously funded by the United States. One group shared the remarkable progress they had made in tuberculosis detection and treatment. In just a few years, case identification increased from 25 percent to 80 percent, a critical step toward breaking transmission and reducing the overall disease burden. That progress has now stalled. The grants that enabled this work were tied to USAID staff who have been dismissed, and with their departure, the funding ended, and the work stopped.
The broader effects of these sudden shifts are difficult to overstate. For example, funding for polio eradication has been preserved in the State Department budget but cut from the CDC—even though the two agencies collaborate closely on the program. This type of fragmented decision-making has left implementing organizations uncertain about staffing and operations. Many no longer feel confident that promised U.S. funds will materialize, even when awards have been announced. In some cases, staff continue to work without pay. Some organizations are approaching insolvency.
Meanwhile, in warehouses across the globe, food aid and medical supplies sourced from American producers are sitting idle—spoiling or approaching expiration—because the systems that once distributed them have been disrupted. Clinics are closing. Health workers are being laid off. HIV/AIDS patients are missing critical doses of medication. Malaria prevention campaigns, including bed net distributions and indoor spraying, have been delayed or canceled, leaving hundreds of millions of people unprotected at the peak of transmission season.
Efforts to track data that would illustrate the severity of this worsening crisis have also been severely compromised. Many of the people responsible for collecting and reporting health information—health workers, statisticians, and program managers—have been laid off or placed on leave. The systems that once monitored health outcomes are shutting down, and the offices where that data was once analyzed now sit empty. As a result, the true scope of the harm is becoming harder to measure, just as the need for information is most urgent.
The situation we face is not about political ideology, and it is not a debate over fiscal responsibility. U.S. government spending on global health accounts for just 0.2 percent of the federal budget. Shutting down USAID did nothing to reduce the deficit. In fact, the deficit has grown in the months since.
Furthermore, many of the allegations regarding waste, fraud, and abuse have proven to be unsubstantiated. For example, the widely circulated claim that USAID sent millions of dollars’ worth of condoms to the Gaza Strip is inaccurate. In fact, the Wall Street Journal reported that the program allocated approximately $27,000 for condoms as part of an HIV transmission prevention initiative—not in the Middle East, but in Gaza Province, Mozambique.
What we are witnessing because of the rapid dismantling of America’s global health infrastructure is a preventable, human-caused humanitarian crisis—one that is growing more severe by the day. DOGE made a deadly mistake by cutting health aid and laying off so many people. But it is not too late to undo some of the damage.
A Record of Progress—and What is at Risk
Since 2000, child mortality worldwide has been cut in half. Deaths from HIV/AIDS, tuberculosis, and malaria have declined significantly. And we are on the verge of eradicating only the second human disease in history: polio. These are not abstract statistics; they represent tens of millions of lives saved. None of this progress would have been possible without consistent, bipartisan U.S. leadership and investment.
Over the past several decades, the United States has built one of its most strategic global assets: a respected and robust public health presence. This leadership is not just a humanitarian achievement—it is a core pillar of American soft power and security. For example, a Stanford study analyzing 258 global surveys across 45 countries found that U.S. health aid is strongly linked to improved public opinion of the United States. In countries and years where U.S. health aid was highest, the probability of people having a very favorable view of the United States was 19 percentage points higher. Other forms of aid—like military or governance—did not have the same effect. Another example is the 2014 Ebola outbreak in West Africa. The rapid deployment of U.S. scientists, health workers, and CDC teams helped contain the virus before it could spread globally. Their presence allowed the U.S. to help shape the response strategy, speed up containment, and prevent a wider outbreak. Many African countries are facing the dual burden of rising debt and pressing health needs, forcing painful choices between repaying creditors, and protecting their citizens. Helping them navigate this challenge is not just the right thing to do—it is a strategic imperative. If the United States retreats, others will fill the gap, and not all of them will bring our values, our priorities, or our interests to the table. Preserving American global influence will require restoring the staff, systems, and resources that underpin it—before the damage becomes irreversible.
I understand the fiscal pressures facing Congress. I recognize the need to prioritize spending and to hold programs accountable for results. I also share the Trump Administration’s commitment to promoting efficiency and encouraging country-led solutions. But I believe those goals can—and must—be pursued while still protecting the programs that deliver the highest return on investment and the greatest impact on human lives.
The United States’ support for Gavi, the Vaccine Alliance; the Global Fund to Fight AIDS, Tuberculosis, and Malaria; the President’s Emergency Plan for AIDS Relief (PEPFAR); and the Global Polio Eradication Initiative (GPEI) represent some of the smartest, most effective investments our country has ever made. These initiatives are proven, strategically aligned with American interests, and cost-effective on a scale few other government programs can match.
Together, Gavi and the Global Fund have helped save more than 82 million lives. Gavi has helped halve childhood deaths in the world’s poorest countries and returns an estimated $54 for every $1 invested. The Global Fund has contributed to a 61% reduction in deaths from HIV/AIDS, TB, and malaria. PEPFAR has saved over 26 million lives and helped millions of children be born HIV-free. GPEI has brought us closer than ever to the eradication of polio. Pulling back now would not only jeopardize these historic gains—it would invite a resurgence of preventable disease, deepen global instability, and undermine decades of bipartisan American leadership.
This is not a forever funding stream for the U.S. Government. These programs set out clear pathways for countries to “graduate” from aid, which many have already done. For example, nineteen countries, including Viet Nam and Indonesia, have successfully graduated from Gavi support and now fully finance their own immunization programs. Others—from Bangladesh to Cote d'Ivoire—are on track to do the same. This is how U.S. development policy should work: catalytic, cost effective, and designed to help countries become self-reliant and drive their own progress. I agree that aid funding should have an end date, but not overnight. The most effective path to that end date is innovation. By investing in the development and delivery of new medical tools and treatments, we can drive down the cost of care, and in some cases, make diseases that were once a death sentence treatable, or even curable. Advances in therapies for chronic conditions like sickle cell disease, HIV, or certain types of cancers could transform lives and health systems. American innovation offers a sustainable exit strategy—one that reduces long-term costs, allows the United States to responsibly step back, and builds lasting trust and good will that far exceed the original investment.
Over the past 25 years, the Gates Foundation has invested nearly $16 billion in global health partnerships like Gavi, the Global Fund, and GPEI. We will continue to invest, through innovation, research, and close coordination with partners. But no private institution—or coalition of them—can replace the scale, reach, or authority of the U.S. government in delivering lifesaving impact at the global level.
The decisions made in the coming weeks will shape not only the lives saved in the near term—but the legacy of American leadership for generations to come.
Download a PDF of the testimony with appendices that include reflections from Gates Foundation staff in Africa on the impact of the U.S. aid cuts; analytical projections from respected organizations; and a selection of first-hand reporting from reputable news organizations and journalists.
Such great heights
This heroic nurse climbs 1000-foot ladders to save lives
Agnes Nambozo goes to extraordinary lengths to vaccinate children in Uganda.
How do you get to work? Some people roll out of bed and move 10 feet to their desk. Others walk to the office or take public transit. I usually drive a car.
No matter how you get there, I guarantee that your commute isn’t as wild as Agnes Nambozo’s: She regularly climbs a rickety ladder that is nearly 1,000 feet tall—or 300 meters—before she can start work for the day.
Agnes is a nurse based in Buluganya, located in the shadow of Mount Elgon in eastern Uganda. Like many nurses in rural communities across sub-Saharan Africa, she wears a lot of different hats. She might spend one day delivering babies and treating wounds and the next as a health educator, promoting good nutrition and sanitation in her community. The days Agnes believes she makes the biggest difference, though, are the ones when she treks deep into the Ugandan countryside to vaccinate children.
Uganda has done an amazing job of reducing childhood mortality over the last 25 years. In 2000, about 145 children died per every thousand live births. By 2023, that figure had dropped to fewer than 40 deaths per 1,000 births. A lot of that progress can be attributed to vaccines and vaccinators like Agnes.
Eastern Uganda is a gorgeous place, but parts of it are incredibly difficult to cross. Many of the communities Agnes visits are high in the mountains. Some are only accessible by ladders, which act as links between communities. Older children can climb down them to go to school, but they are too steep for the little ones. Mothers can’t safely carry their babies down the ladders to the health clinic, so Agnes comes to them.
When Agnes was a little girl, she wanted to be a police officer—until her mom convinced her the job was too dangerous. Instead, she took a nursing course. She fell in love with the profession, even though it ended up being a much riskier job than her mom ever imagined. She travels to the villages to vaccinate kids in all kinds of weather. It’s often rainy in the mountains, and the ladders become slippery. “The ladders are risky because you might miss a step,” she says. “If you are lucky, you can get a fracture. If you’re not lucky, you can lose your life.”
On the days when she heads into the field to vaccinate children, Agnes leaves her house by 6:00 am. She takes a taxi from where she lives in Sironko to Buyaga, a town closer to where the health clinic is located. Cars can’t drive on the road to the clinic, so she takes a motorbike for the last stretch.
She arrives at the clinic around 8:00 am and starts packing for the day. Rural vaccinators like Agnes must carry their supplies on their backs, and there’s an art to making sure everything is loaded properly. The vaccines must be kept cold so she wears a heavy insulated backpack stuffed with ice packs.
Agnes then hops on another motorbike to a staging location before heading off on foot to the ladders. By the time she reaches the village and starts setting up to immunize the community, it’s usually around 10:30—more than four hours after she left her house for the day.
She comes in with a plan for how many people she’ll vaccinate, but Agnes always brings a couple extra doses just in case. A typical day usually means around 50 patients. Most are children under 5, who get vaccinated against deadly diseases like polio, measles, tetanus, and pneumonia. The latter is especially important in a region as rainy as this one, where the damp weather makes people more susceptible to respiratory diseases.
Agnes and her colleagues are often the only health workers who visit the most remote communities in the mountains, so they also provide general nursing care while they’re there. Agnes regularly gives kids deworming treatments and key supplements like vitamin A. She answers questions from the adults and offers them health guidance, including advice on planning a family.
After she wraps up for the day, Agnes makes the long trek back home. It’s exhausting, difficult work, but she is proud to help so many people. “Our motto for nurses in Uganda is ‘To love and serve,’” she says. “And to me, love is not just a word. It’s a verb.”
Unfortunately, Agnes’s job recently became a lot more difficult. Many of her colleagues at the health clinic in Buluganya were supported by USAID, and they lost their jobs when funding was cut. Some of the positions that were eliminated supported new and expectant mothers. Others worked on HIV and tuberculosis, distributing medication and testing high-risk individuals to prevent further spread.
Agnes and the others who are left are doing their best to ensure communities still receive care, but they can only do so much. “Our community is suffering a lot,” she says. She is worried about burnout if funding isn’t restored.
Still, Agnes won’t rest until she has helped as many people as she can. Thanks to the support of the Rotary Club of Kampala, she recently went back to school and is working towards a degree in nursing. She hopes to learn new skills that will save even more lives.
“My dream is to make people feel good, to make them happy, and to give my service to the people,” says Agnes. “When you have positivity, nothing is impossible.”
The last chapter
My new deadline: 20 years to give away virtually all my wealth
During the first 25 years of the Gates Foundation, we gave away more than $100 billion. Over the next two decades, we will double our giving.
When I first began thinking about how to give away my wealth, I did what I always do when I start a new project: I read a lot of books. I read books about great philanthropists and their foundations to inform my decisions about how exactly to give back. And I read books about global health to help me better understand the problems I wanted to solve.
One of the best things I read was an 1889 essay by Andrew Carnegie called The Gospel of Wealth. It makes the case that the wealthy have a responsibility to return their resources to society, a radical idea at the time that laid the groundwork for philanthropy as we know it today.
In the essay’s most famous line, Carnegie argues that “the man who dies thus rich dies disgraced.” I have spent a lot of time thinking about that quote lately. People will say a lot of things about me when I die, but I am determined that "he died rich" will not be one of them. There are too many urgent problems to solve for me to hold onto resources that could be used to help people.
That is why I have decided to give my money back to society much faster than I had originally planned. I will give away virtually all my wealth through the Gates Foundation over the next 20 years to the cause of saving and improving lives around the world. And on December 31, 2045, the foundation will close its doors permanently.
This is a change from our original plans. When Melinda and I started the Gates Foundation in 2000, we included a clause in the foundation’s very first charter: The organization would sunset several decades after our deaths. A few years ago, I began to rethink that approach. More recently, with the input from our board, I now believe we can achieve the foundation’s goals on a shorter timeline, especially if we double down on key investments and provide more certainty to our partners.
During the first 25 years of the Gates Foundation—powered in part by the generosity of Warren Buffett—we gave away more than $100 billion. Over the next two decades, we will double our giving. The exact amount will depend on the markets and inflation, but I expect the foundation will spend more than $200 billion between now and 2045. This figure includes the balance of the endowment and my future contributions.
This decision comes at a moment of reflection for me. In addition to celebrating the foundation’s 25th anniversary, this year also marks several other milestones: It would have been the year my dad, who helped me start the foundation, turned 100; Microsoft is turning 50; and I turn 70 in October.
This means that I have officially reached an age when many people are retired. While I respect anyone’s decision to spend their days playing pickleball, that life isn’t quite for me—at least not full time. I’m lucky to wake up every day energized to go to work. And I look forward to filling my days with strategy reviews, meetings with partners, and learning trips for as long as I can.
The Gates Foundation’s mission remains rooted in the idea that where you are born should not determine your opportunities. I am excited to see how our next chapter continues to move the world closer to a future where everyone everywhere has the chance to live a healthy and productive life.
Planning for the next 20 years
I am deeply proud of what we have accomplished in our first 25 years.
We were central to the creation of Gavi and the Global Fund, both of which transformed the way the world procures and delivers lifesaving tools like vaccines and anti-retrovirals. Together, these two groups have saved more than 80 million lives so far. Along with Rotary International, we have been a key partner in reviving the effort to eradicate polio. We supported the creation of a new vaccine for rotavirus that has helped reduce the number of children who die from diarrhea each year by 75 percent. Every step of the way, we brought together other foundations, non-profits, governments, multilateral agencies, and the private sector as partners to solve big problems—as we will continue to do for the next twenty years.
Over the next twenty years, the Gates Foundation will aim to save and improve as many lives as possible. By accelerating our giving, my hope is we can put the world on a path to ending preventable deaths of moms and babies and lifting millions of people out of poverty. I believe we can leave the next generation better off and better prepared to fight the next set of challenges.
The work of making the world better is and always has been a group effort. I am proud of everything the foundation accomplished during its first 25 years, but I also know that none of it would have been possible without fantastic partners.
Progress depends on so many people around the globe: Brilliant scientists who discover new breakthroughs. Private companies that step up to develop life-saving tools and medicines. Other philanthropists whose generosity fuels progress. Healthcare workers who make sure innovations get to the people who need them. Governments, nonprofits, and multilateral organizations that build new systems to bring solutions to scale. Each part plays an essential role in driving the world forward, and it is an honor to support their efforts.
Of course, although the Gates Foundation is by far the most significant piece of my giving, it is not the only way I give back. I have invested considerable time and money into both energy innovation and Alzheimer’s R&D. Today’s announcement does not change my approach to those areas.
Expanding access to affordable energy is essential to building a future where every person can both survive and thrive. The bulk of my spending in this area is through Breakthrough Energy, which invests in companies with promising ideas to generate more energy while reducing emissions. I also started a company called TerraPower to bring safe, clean, next-generation nuclear technology to life. Both of these ventures will earn profits if successful, and I will reinvest any money I make through them back in the foundation, as I already do today.
I support a number of efforts to fight Alzheimer’s disease and other related dementias. Alzheimer’s is a growing crisis here in the United States, and as life expectancies go up, it threatens to become a massive burden to both families and healthcare systems around the world. Fortunately, scientists are currently making amazing progress to slow and even stop the progress of this disease. I expect to keep supporting their efforts as long as it’s necessary.
The success in both areas will determine exactly how much money is given to the foundation since any profits they earn will be part of my overall gift.
What the Gates Foundation hopes to accomplish
Over the next twenty years, the foundation will work together with our partners to make as much progress towards our vision of a more equitable world as possible.
The truth is, there have never been more opportunities to help people live healthier, more prosperous lives. Advances in technology are happening faster than ever, especially with artificial intelligence on the rise. Even with all the challenges that the world faces, I’m optimistic about our ability to make progress—because each breakthrough is yet another chance to make someone’s life better.
Over the next twenty years, the foundation’s funding will be guided by three key aspirations:
In 1990, 12 million children under the age of 5 died. By 2019, that number had fallen to 5 million. I believe the world possesses the knowledge to cut that figure in half again and get even closer to ending all preventable child deaths.
We now understand the essential role nutrition—and especially the gut microbiome—plays in not only helping kids survive but thrive. We’ve made huge advances in maternal health, making sure that new and expectant mothers have the support they need to deliver healthy babies. We have new, life-saving vaccines and medicines, and we know how to get them to the people who need them most thanks to organizations like Gavi and the Global Fund. The innovation is there, the ability to measure progress is stronger than ever, and the world has the tools it needs to put all children on a good path.
Today, the list of human diseases the world has eradicated has just one entry: smallpox. Within the next couple years, I expect to add polio and Guinea worm to the list. (When we eradicate the latter, it will be a testament to the late President Jimmy Carter’s leadership.) I’m optimistic that, by the time the foundation shuts down, we can also add malaria and measles. Malaria is particularly tricky, but we’ve got lots of new tools in the pipeline, including ways of reducing mosquito populations. That is probably the key tool that, as it gets perfected and approved and rolled out, gives us a chance to eradicate malaria.
In 2000, the year that we started the foundation, 1.8 million people died from HIV/AIDS. By 2023, advances in treatment and preventatives cut that number to 630,000. I believe that figure will be reduced dramatically in the decades ahead, thanks to incredible new innovations in the pipeline—including a single-shot gene therapy that could reduce the amount of virus in your body so much that it effectively cures you. This would be massively beneficial to anybody who has HIV, including in the rich world. The same technology is also being used to treat sickle cell disease, an excruciating and deadly illness.
We’re also making huge progress on tuberculosis, which still kills more people than malaria and HIV/AIDS combined. Last year, a historic phase 3 trial began that could be the first new TB vaccine in over 100 years.
The key to maximizing the impacts of these innovations will be lowering their costs to make them affordable everywhere, and I expect the Gates Foundation will play a big role in making that happen. Health inequities are the reason the Gates Foundation exists. And the true test of our success will be whether we can ensure these life-saving interventions reach the people who need them most—particularly in Africa, South Asia, and across the Global South.
To reach their full potential, people need access to opportunity. That’s why our foundation focuses on more than just health.
Education is key. Frustratingly, progress in education is less dramatic than in health—there is no vaccine to improve the school system—but improving education remains our foundation’s top priority in the United States. Our focus is on helping public schools ensure that all students can get ahead—especially those who typically face the greatest barriers, including Black and Latino students, and children from low-income backgrounds. At the K-12 level, that means boosting math instruction and ensuring teachers have the training and support they need—including access to new AI tools that allow them to focus on what matters most in the classroom. Given the importance of a post-secondary degree or credential for success nowadays, we’re funding initiatives to increase graduation rates, too.
As I mentioned, having access to a high-quality nutrition source is key to keeping kids’ development on track. Smallholder farmers form the backbones of local economies and food supplies, and they play a key role in making that happen. One of the main ways the foundation helps farmers is through the development of new, more resilient seeds that yield more crops even under difficult conditions. This work is even more important in a warming world, since no one suffers more from climate change than farmers who live near the equator. Despite that, I’m hopeful that we can help make smallholder farmers more productive than ever over the next two decades. Some of the crops our partners are developing even contain more nutrients—a win-win for both climate adaptation and preventing malnutrition.
We’ll also continue supporting digital public infrastructure, so more people have access to the financial and social services that foster inclusive economies and open, competitive markets. And we’ll continue supporting new uses of artificial intelligence, which can accelerate the quality and reach of services from health to education to agriculture.
Underpinning all our work—on health, agriculture, education, and beyond—is a focus on gender equality. Half the world’s smallholder farmers are women, and women stand to gain the most when they have access to education, health care, and financial services. Left to their own devices, systems often leave women behind. But done right, they can help women lift up their families and their communities.
The United States, United Kingdom, France, and other countries around the world are cutting their aid budgets by tens of billions of dollars. And no philanthropic organization—even one the size of the Gates Foundation—can make up the gulf in funding that’s emerging right now. The reality is, we will not eradicate polio without funding from the United States.
While it's been amazing to see African governments step up, it’s still not enough, especially at a moment when many African countries are spending so much money servicing their debts that they cannot invest in the health of their own people—a vicious cycle that makes economic growth impossible.
It's unclear whether the world’s richest countries will continue to stand up for its poorest people. But the one thing we can guarantee is that, in all of our work, the Gates Foundation will support efforts to help people and countries pull themselves out of poverty. There are just too many opportunities to lift people up for us not to take them.
The last chapter of my career
Next week, I will participate in the foundation’s annual employee meeting, which is always one of my favorite days of the year. Although it’s been many years since I left Microsoft, I am still a CEO at heart, and I don’t make any decisions about my money without considering the impact.
I feel confident putting the remainder of my wealth into the Gates Foundation, because I know how brilliant and dedicated the people responsible for using that money are—and I can’t wait to celebrate them.
I'm inspired by my colleagues at the foundation, many of whom have foregone more lucrative careers in the private sector to use their talents for the greater good. They possess what Andrew Carnegie called “precious generosity,” and the world is better off for it.
I am lucky to have been surrounded by many generous people throughout my life. As I wrote in my memoir Source Code, my parents were my first and biggest influences. My mom introduced me to the idea of giving back. She was a big believer in the idea of “to whom much is given much is expected,” and she taught me that I was just a steward of any wealth I gained.
Dad was a giant in every sense of the word, and he, more than anyone else, shaped the values of the foundation as its first leader. He was collaborative, judicious, and serious about learning—three qualities that shape our approach to everything we do. Every year, the most important internal recognition we hand out is called the Bill Sr. Award, which goes to the staff member who most exemplifies the values that he stood for. Everything we have accomplished—and will accomplish—is a testament to his vision of a better world.
As an adult, one of my biggest influences has been Warren Buffett, who remains the ultimate model of generosity. He was the first one who introduced me to the idea of giving everything away, and he’s been incredibly generous to the foundation over the decades. Chuck Feeney remains a big hero of mine, and his philosophy of “giving while living” has shaped how I think about philanthropy.
I hope other wealthy people consider how much they can accelerate progress for the world’s poorest if they increased the pace and scale of their giving, because it is such a profoundly impactful way to give back to society. I feel fulfilled every day I go to work at the foundation. It forces me to learn new things, and I get to work with incredible people out in the field who really understand how to maximize the impact of new tools.
Today’s announcement almost certainly marks the beginning of the last chapter of my career, and I’m okay with that. I have come a long way since I was just a kid starting a software company with my friend from middle school. As Microsoft turns 50 years old, it feels right that I celebrate the milestone by committing to give away the resources I earned through the company.
A lot can happen over the course of twenty years. I want to make sure the world moves forward during that time. The clock starts now—and I can’t wait to make the most of it.
The sky’s the limit
The Drone Didis are taking flight
Drones are helping rural women boost their income and India’s agricultural productivity.
I was excited to get a drone for my birthday last year. I couldn’t wait to get it into the air and see what my backyard looked like from the sky. But, as anyone who has used one can tell you, I quickly learned a harsh truth: Flying a drone isn’t easy. It takes a lot of practice and skill.
Maybe it’s time to pull the drone back out, because I was lucky to get a lesson from the experts last month in India. During my visit to Delhi, I met with Sangita Devi, Sumintra Devi, and Kajol Kumari—three Drone Didis from Bihar who are taking India’s agricultural productivity to new heights.
The women I met are part of the Indian government’s Namo Drone Didi program. (Didi is the Hindi word for “sister.”) It was launched in 2023 to help rural women boost their income and boost India’s agricultural productivity—and although the program is still in its early days, I’m already impressed by its results.
Right now, the Drone Didis primarily use their flying skills to fertilize crops. Applying fertilizer via drone has a lot of benefits over doing it by hand. Since you can spray farther away from the plant, the liquid fertilizer becomes more atomized—which means that it turns into finer droplets that cover more area. This benefits both farmers and the environment, because you need significantly less fertilizer and less water to help distribute it. Plus, it’s faster. One Drone Didi can cover as much as five acres in the same time it would take five people to cover half an acre.
I cannot wait to see how the program expands in the years ahead. The Indian government has plans to equip the drones with advanced sensors and imaging technology. This will allow Drone Didis to use real-time data to deliver targeted interventions to improve the quality and quantity of farmers’ crops. They will be able to detect diseases and pests, assess soil moisture levels, monitor crop growth, and more.
I’m equally excited to track how the Drone Didi program continues to empower women across India. Every Didi is affiliated with a self-help group, or SHG. The plan is to provide nearly 15,000 drones to SHGs across India by the end of next year.
In the United States, where I live, self-help groups are usually associated with mental health. In India, they’re a form of mutual aid. Each SHG is small—most are around 12 people, although some are as big as 25—and brings together women to support each other socially and financially. They pool their savings, access microloans at lower interest rates, and solve problems in areas like health and education.
The Didis I met with were longtime members of SHGs organized by JEEViKA, an organization in Bihar that works to lift people from rural areas out of poverty. During our time together in Delhi, Kajol told me about how JEEViKA helped her open her own shop three years ago, where she sells seeds and fertilizers. She loves being an entrepreneur, and when she was approached about becoming a Drone Didi, she knew it would do wonders for her business.
Each Didi attends a training program in Hyderabad or Noida, where they are taught how to pilot the drone and apply fertilizer effectively. (I was surprised to hear that learning to fly is apparently easier and takes less time than learning to fertilize!) Other women in their SHGs are trained as drone technicians, ready to repair the machines if any problems arise.
In the less than two years, the Drone Didi program is already transforming the lives of its pilots. Kajol is using the extra income she’s earned to expand her shop offerings and build a warehouse to store her stock. She also plans to send her children to a better school. Sangita’s family couldn’t afford a bicycle before she became a Drone Didi—today, she is the proud owner of an auto rickshaw.
Sumintra hopes that, when people see someone like her flying a huge drone, it changes their perception of what women are capable of. Like many women in her area, she married very young and was expected to stay home with her children. Today, her kids call her “Pilot Mummy” and dream about her flying airplanes one day.
I hope you think of the Didis the next time you hear the buzz of a drone above you at a wedding or a park. It’s remarkable how one piece of technology can reshape what is possible in a community. Kajol told me that people sometimes look at her and say, “She’s flying too high! What will she do next?”
Her response? “This is just the beginning. Wait and see what’s coming.”
Alphabet soup
You’ve probably never heard of CGIAR, but they are essential to feeding our future
No other institution has done as much to feed our world as CGIAR.
What’s for dinner?
It’s a question asked every day in homes around the world. No other organization has done as much to ensure families—especially the poorest—have an answer to that question as CGIAR, the world’s largest global agricultural research organization.
More than 50 years ago, CGIAR’s research into high-yielding, disease-resistant rice and wheat launched the Green Revolution, saving more than a billion people from starvation. In the years since then, their work on everything from livestock and potatoes to rice and maize has helped reduce poverty, increase food security, and improve nutrition.
Never heard of CGIAR? You’re not alone. It’s an organization that defies easy brand recognition. For starters, its name is often mistaken for “cigar,” suggesting a link to the tobacco industry. And it doesn’t help that CGIAR is not a single organization, but a network of 15 independent research centers, most referred to by their own confusing acronyms. The list includes CIFOR, ICARDA, CIAT, ICRISAT, IFPRI, IITA, ILRI, CIMMYT, CIP, IRRI, IWMI, and ICRAF, leaving the uninitiated feeling as if they’ve fallen into a bowl of alphabet soup.
It’s too bad that more people don’t know about CGIAR. Their work to feed our hungry planet is as important now as it’s ever been. By 2050, as the world’s population gets bigger and incomes increase (which causes dietary changes like eating more meat), global food demand is expected to increase by 60 percent. Meeting this challenge is made tougher by climate change, which is affecting food production in every corner of the globe. Farmers are under assault from shifting rainfall, more frequent and extreme droughts and floods, and severe pest and disease outbreaks among crops and livestock.
The people who are most affected by these changes today are the world’s smallholder farmers. About 500 million farming households, in South Asia and sub-Saharan Africa, earn their living by raising crops and livestock on small parcels of land. These families have the fewest resources to cope with the many impacts of a warming climate.
I’ve been writing a lot this year about why reducing emissions from all sectors of our economy, including agriculture and electricity generation, is critical in our fight against climate change. But it’s equally important for the world to stay focused on helping vulnerable populations, like smallholder farmers, prepare for the disruptive impacts of climate change. We owe it to them. The people who will suffer most from climate change, especially in sub-Saharan Africa, are the least responsible for emitting these greenhouse gases. According to an Africa Progress Panel report, an average Ethiopian would have to live for 240 years to equal the carbon footprint of the average American.
I’m now co-chairing the new Global Commission on Adaptation, which is playing a key role in building government and public support for efforts to reduce the impacts of climate change on communities most at risk. We will need CGIAR’s research to help supply farmers with a steady stream of climate-smart crop varieties.
A great example of a CGIAR innovation helping smallholder farmers adapt to climate change is its drought-tolerant maize program. More than 200 million households in sub-Saharan Africa depend on maize for their livelihoods. Maize productivity in Africa is already the lowest in the world. And as weather patterns have become more erratic, farmers are at greater risk of having smaller maize harvests, and sometimes no harvest at all.
In response to this challenge, CGIAR’s International Maize and Wheat Improvement Center or CIMMYT, with funding from our foundation, USAID and the Howard Buffett Foundation, developed more than 150 new maize varieties that could withstand drought conditions. Each variety is adapted to grow in specific regions of Africa. At first, many smallholder farmers were afraid of trying new crop varieties instead of more commonly planted ones. But as CIMMYT worked with local farmers and seed dealers to share the benefits of these new varieties, more and more farmers adopted drought tolerant maize. The results have been life changing for many farming families.
In Zimbabwe, for example, farmers in drought-stricken areas using drought-tolerant maize were able to harvest up to 600 kilograms more maize per hectare than farmers using conventional varieties. The additional harvest was enough to feed a family of six for 9 months. For farming families who chose to sell their harvests, it was worth $240 in extra income, giving them much-needed cash to send their children to school and meet other household needs.
CIMMYT, in partnership with another CGIAR center, the International Institute of Tropical Agriculture or IITA, has gone on to develop other maize varieties for farmers who are not only vulnerable to drought, but also poor soils, disease, pests, and weeds. These varieties are expected to give farmers up to 30 percent greater yields and help them fight malnutrition.
CGIAR’s team of more than 8,000 scientists and staff around the world are also developing other tools to help farmers adapt to unpredictable weather and diseases. They have created a smart phone app that allows farmers to use the camera on their phone to identify specific pests and disease attacking cassava, an important cash crop in Africa. There are also new programs to use drones and ground sensors to help wheat and sugarcane farmers determine how much water and fertilizer their crops need.
We will need many new ideas like these to help farmers be prepared to meet the challenges of our changing climate. If they are, we will all have an answer to the question “What’s for dinner?” for years to come.
Two countries, five days
Highlights of my trip to Nigeria and Ethiopia
A few photos from my latest visit to Africa.
I’ve just wrapped up a busy five-day trip to Ethiopia and Nigeria. It’s the kind of trip that’s both tiring and energizing at the same time. Even though I stay in touch with a lot of partners in both countries—the Gates Foundation has been funding work in them for more than 15 years—there’s nothing quite like visiting to see the work in action.
Whenever I get home from a trip like this, friends are curious to hear how it went. Here’s what I’m telling them. From 2000 to 2019 or so, Ethiopia and Nigeria led the way on dramatic improvements in health and poverty that rippled across Sub-Saharan Africa. Since then, the pandemic, extreme weather, and political and economic instability have set both countries back, along with much of the rest of the continent. But as I saw on this trip, there’s great work going on in both places that makes me optimistic about their future, and Africa’s.
I want to share a few photos from the week. Thanks to everyone who shared their time and insights with me, including Prime Minister Ahmed of Ethiopia, Nigerian health minister Muhammad Ali Pate, and a special guest who came along for the trip: the amazing musician Jon Batiste. The foundation will be working with African partners even more in the future, and based on what I saw this week, my next visit will be just as inspiring.

The worst tragedy
Why do children die?
The toughest question I’ve ever had to answer.
Twenty-five years ago, I encountered a question that I have thought about literally every day since: Why do children die?
Before I tell you what drew me to this mystery, I want to acknowledge that child mortality is not an easy subject to talk about. As a parent, I can’t imagine what it would be like to lose a child. It is shocking even to see the words “children” and “die” used in the same sentence.
But I think “why do children die?” is one of the most important questions ever. It is hard to think of a measure of how a society is doing that reveals more than whether it is protecting its children, and especially its most vulnerable children. And the better we understand why children die, the more we can do to save them.
The very good news is that the world has made phenomenal progress in this area over the past several decades. Since 1990, the number of children who die every year has fallen by more than half! If progress on child mortality is a good measure of the state of the world, then—despite the huge global setbacks of the past few years, including COVID-19—the state of the world has improved dramatically. And based on what I know about innovations that are still to come, we can look forward to even more progress in the years ahead.
My introduction to the subject came 25 years ago, when I read a New York Times article about the health problems caused by unsafe drinking water in low- and middle-income countries. I was shocked to learn that every year, 3.1 million people—nearly all of them children—died of diarrhea, often because they had drunk contaminated water. Diarrhea kills 3.1 million children?, I thought. That can’t be true, can it? But it was.
I had to know more. What other major inequities did I not know about?
I read everything about global health that I could find, and I spoke to as many experts as I could. I learned that researchers define child mortality as the death of anyone under the age of 5. They use that age because the first five years are the riskiest time of childhood, when kids are the most vulnerable.
Learning about the history of child mortality helped me put the statistics in context. In 1950, some 20 million children died. In 1990, it was down to 12 million children, even though more babies were being born. By 2000, the number had dropped to fewer than 10 million. By 2019, it was below 5 million. Virtually all of these deaths occur in low- and middle-income countries.
So the next question was, why were so many children dying?
Around 18 percent of the deaths were caused by non-communicable conditions, such as cancer and cardiovascular problems. The large majority—82 percent—of the deaths were caused by communicable diseases, such as diarrhea and malaria, and health problems that their mothers experienced—and exacerbated by risk factors including malnutrition. (This 18:82 ratio still holds true today.)
On one hand, this was heartbreaking. The worst killers were all things that people in rich countries considered just an unpleasant episode (such as diarrhea) or never experienced at all anymore (such as malaria). In other words, although it was obviously true that children were dying because of deadly diseases, that was only part of the explanation. They were also dying because of where they were born.
On the other hand, it was encouraging to learn that such a large share of the deaths was preventable. When I saw the breakdown of diseases, I thought: Here is our road map. This is what the Gates Foundation should be working on. With the right team, partners, and funding, we could help the world move through the list, systematically going after the worst killers. The solutions that already existed could be made more affordable and delivered to people in low-income countries. The ones that didn’t exist could be invented.
Here is the chart as it looks today:
As you can see, pneumonia is the top preventable cause, but the story here is one of real progress. In 2000, it took the lives of more than 1.5 million children, but by 2019, the number was around 670,000—still an awful number, but a reduction of more than 55 percent. The innovation related to pneumonia that’s going on today is so exciting that I made a separate post and video about it.
Diarrhea is another example of progress. In two decades, its death toll has dropped 58 percent. A key reason is the use of low-tech interventions like oral rehydration solution (sugar water, essentially), which replaces lost electrolytes. Governments also ran large-scale sanitation programs to cut down on the spread of bacteria. And scientists developed an affordable rotavirus vaccine, and the world came together to deliver it. Between 2010 and 2020, this vaccine prevented more than 200,000 deaths. By 2030, it will have prevented more than half a million deaths.
Even though the overall number of deaths has gone down by half, the relative positions of the top three killers have not changed. They are the same today as in 1990: neonatal disorders, pneumonia, and diarrheal diseases. As you can see in this graphic, the fourth slot is where there has been a huge shift. In 1990, it was occupied by measles, responsible for half a million deaths. Today, it’s malaria that is in the fourth slot—not because malaria deaths went up (they actually went down), but because measles deaths fell by a whopping 87 percent.
Why? Vaccines. Since 2000, Gavi, the Vaccine Alliance has provided measles vaccines to more than 500 million children—half a billion!—through routine immunization and special vaccination campaigns. (This is just one example of the magic of vaccines—although unfortunately vaccination rates have dropped because of the pandemic and other factors.) And malaria may not be #4 on that list for long, thanks to innovations like malaria vaccines, improved insecticide-treated bed nets, and sugar baits.
Many groups deserve credit for the decades of progress I’ve described in this post. Countries with high disease burdens have launched massive vaccination campaigns, strengthened their health systems, and shared best practices with each other. Wealthy countries generously give aid that supports these efforts. Pharmaceutical companies have contributed technical expertise and made products affordable for low- and middle-income countries. Foundations including the Gates Foundation have stepped up with additional funding for innovative ideas. (At the foundation, we have staff and partners dedicated to each slice of the pie you see above.)
Although it’s still true that too many children do not live to see their fifth birthday, the world is moving in the right direction. If everyone keeps doing their part, we can move even faster and save even more lives. Because of COVID and other setbacks, the United Nations’ goal to cut childhood deaths in half again to below 3 million by 2030 will be missed, but it can still be achieved the following decade.
At a time when war and pandemic are in the news every day, it is important to look for reasons to be hopeful. The world’s opportunity—and ability—to save children’s lives is surely one of those reasons.

Urban invader
The world’s newest weapon against malaria? Mosquitoes
A city-dwelling mosquito threatening Africa sparks innovation in the fight against malaria.
About 10 years ago, the African country of Djibouti had nearly succeeded in wiping out malaria. The country’s leaders hoped that getting rid of the disease would help them attract new investment, development, and tourism.
Then suddenly the disease roared back. Cases surged from just 27 in 2012, to more than 73,000 in 2020—a huge number for this East African nation of just one million people.
The cause?
A highly invasive mosquito that had migrated from South Asia and the Arabian Peninsula into Africa.
This pest—the Anopheles stephensi mosquito—has now emerged as one of the biggest threats to malaria elimination in sub-Saharan Africa. Since establishing a beachhead in Djibouti, An. stephensi mosquitoes have been detected in Ethiopia, Sudan, Somalia, Kenya and as far away as Nigeria and Ghana, in West Africa. According to one study, if this mosquito is left unchecked an additional 126 million people on the continent will be at risk of malaria.
What makes An. stephensi particularly dangerous is where it has chosen to reside. Unlike other malaria-carrying mosquitoes in Africa that primarily breed in rural areas, An. stephensi thrives in urban environments. Cities are already home to 40 percent of the population in sub-Saharan Africa and continue to experience rapid growth, creating a fertile habitat for this mosquito. Making matters worse, An. stephensi has been found to be resistant to many of the insecticides used to control mosquito populations. And they bite in the evening before bedtime—not in the middle of the night like other mosquitoes—making bed nets less effective as protection.
But this story doesn’t end here.
In 2018, the government of Djibouti, in search for a new approach to combat these urban invaders, heard about a biotechnology company called Oxitec that has a potentially game-changing solution to mosquito control.
The fight against mosquitoes and the diseases they carry has always been a game of cat and mouse. Humans develop new interventions—like bed nets, insecticides, and treatments—to protect themselves from mosquitoes. Mosquitoes, meanwhile, have an incredible capacity to adapt, allowing them to eventually dodge or develop resistance to the latest control methods. Then humans respond with more innovations to outsmart the mosquitoes. And so on.
Oxitec, however, aims to change this game from cat versus mouse to mouse versus mouse. Or in this case, mosquito versus mosquito. Oxitec specializes in using mosquitoes to fight other mosquitoes. With its genetic technology, Oxitec has already developed mosquitoes to effectively combat the dengue fever–carrying mosquito, Aedes aegypti, in Brazil. Now Oxitec plans to use the same technology to help African governments control An. stephensi and reduce the spread of malaria.
Here’s how Oxitec’s technology would work against An. stephensi mosquitoes: Oxitec male mosquitoes carry a special gene to prevent their female offspring from surviving into adulthood. (Only female mosquitoes bite and spread malaria.) Released into the wild, the male Oxitec mosquitoes mate with wild female mosquitoes. All the female offspring die. All the male progeny, which don’t bite, will survive and go on to mate with other wild females. With sustained releases of male Oxitec mosquitoes, more females die off, dramatically reducing the mosquito population and the spread of malaria. After the mosquito releases stop, however, because half of the gene’s carriers (the females) cannot survive, the gene steadily declines and disappears from the mosquito population within a few generations.
Genetic technology like Oxitec’s understandably raises many questions. Is it safe? What are the lasting environmental impacts? Here’s what’s important to know:
Because it’s passed through mating, the gene the Oxitec male mosquitoes carry only targets the An. stephensi mosquitoes. It doesn’t have any impact on other insects and cannot be established in the local ecosystem. After evaluating the potential risk of genetically modified mosquitoes, the U.S. Food and Drug Administration in 2016 and the EPA in 2022 have confirmed that the Oxitec mosquitoes do not pose a threat to humans or the environment. More than one billion Oxitec mosquitoes have been released worldwide, with no negative impacts. In Brazil, the Oxitec Aedes aegypti mosquitoes have been so successful in reducing the spread of dengue fever that they are in demand by communities, governments, and businesses in Brazil. Homeowners can even buy a kit to raise the mosquitoes in their own backyards. (If you want to learn more about this technology, I encourage you to visit the Oxitec website and the Centers for Disease Control and Prevention.)
Last year, the government of Djibouti formed a partnership with Oxitec, Association Mutualis (a non-profit public health organization in Djibouti), and the Djibouti National Malaria Control Programme to use this new technology to defeat An. stephensi.
No Oxitec mosquitoes have been released in Djibouti during the current pilot phase of the project. But the government of Djibouti expects to move forward with the first releases of Oxitec mosquitoes next year in Djibouti’s capital city, where 70 percent of the population live.
This solution is being pursued with the support of the people of Djibouti. The government of Djibouti, Oxitec, and its local partners have been working together to educate and engage the public about this technology, going door to door to listen to their concerns, and ensuring all the communities’ questions have been addressed before moving forward with the release of the mosquitoes. Local support has been outstanding to date.
To end malaria, we need many new tools and innovations to reduce the burden of this disease and move the world closer to eradication. I’m excited about the potential of Oxitec’s technology to help Djibouti and the rest of Africa achieve this goal.


The big picture
On the road in Nigeria and Niger
These were some of my favorite moments from the last week in West Africa.
Have you ever visited a place you haven’t been in a while, and it somehow manages to feel both new and familiar? That’s how I feel every time I go back to Nigeria.
It was amazing to return to Lagos and Abuja this week. I’ve been fortunate to spend a lot of time in Nigeria over the last two-plus decades, but it’s been nearly five years since my last visit due to the pandemic. Nigeria—and especially Lagos—is one of the most dynamic, vibrant places in the world, and I am always blown away by how much it's changed. At the same time, I loved getting to catch up with old friends and reconnect in person with longtime partners. (Remote meetings are great, but it’s nice to meet face-to-face on occasion.)
This week also marked my first-ever trip to Niger. Our foundation has been working with talented Nigeriens for years to help ensure children's health and prevent the spread of polio, and it was exciting to see the country for myself and talk about the future of that work.
It was a great week. These were some of my favorite moments:

Across the finish line
Makoy Samuel Yibi won’t stop until the world eradicates its next disease
Guinea worm once infected 3.5 million people every year. Thanks to heroes like Makoy, that number dropped to 13 last year.
When you see someone suffering from a terrible disease, it’s hard not to imagine a world where no one has to feel this way ever again. But the problem with eradication is that it’s really, really hard. The fewer cases remain, the more difficult it is to find them. That’s why, in all of human history, we’ve only eradicated two diseases: smallpox and the cattle disease rinderpest.
That might change soon.
The world is close to eradicating Guinea worm disease, a debilitating and painful condition that once devastated an estimated 3.5 million people in Africa and South Asia every year. Thanks to heroes like Makoy Samuel Yibi, that number dropped to 13 people in 2023.
As the national director of the South Sudan Ministry of Health’s Guinea Worm Eradication Program, Makoy helped reduce the number of cases in his country last year to just two. That’s a remarkable accomplishment by any standard, but it’s truly impressive when you consider the circumstances he and his team have faced: civil wars, the COVID-19 pandemic, the political changes brought by South Sudan’s decision to become an independent country in 2011, and the fact that the nation was once home to 90 percent of the world’s Guinea worm cases.
I recently caught up with Makoy at the COP climate conference in Dubai, where we both participated in an event focused on ending neglected tropical diseases, or NTDs, like Guinea worm. When you meet him in person, it’s hard to imagine a better person for the job. Makoy is passionate, brilliant, and laser-focused on making life better for the people of South Sudan. So I was surprised to learn that, as a young man, he never imagined a career in health.
Makoy was born in Terekeka County, a rural area located on the shores of the West Nile in southern Sudan. When he was a young man, Makoy had one primary focus: avoiding military service, which could be extremely dangerous. A chance meeting with a general from Terekeka resulted in a position with the national health department. A measles outbreak was ravaging parts of Sudan at the time, and Makoy’s first assignment was to travel from village to village providing care.
“What struck me,” he recalls, “was that, in every household we went to, we found at least half of the household was down with Guinea worm.”
The Guinea worm is a particularly nasty parasite. It’s unlikely to kill you, but the disease it causes—which is also called dracunculiasis, or “afflicted with little dragons”—can incapacitate you for months at a time and leave you permanently disabled. That can have devastating consequences if your family counts on you to grow the food you eat and sell it to make a living, as many people in South Sudan do.
The way the disease works is horrifying. If a person drinks water contaminated with Guinea worm larvae, the larvae enter the digestive system and mate. The impregnated female worm grows, undetected by the body’s immune system. Around a year later, the infected person will start to feel an itch somewhere on their body (usually the lower leg or foot). After a couple days, a painful blister appears and eventually bursts. The worm—which is now about one meter long—slowly starts to emerge from the wound.
This can take weeks or even months, and the pain it causes is excruciating. The wound can get infected, which could result in permanent disfigurement or even require amputation. And people often endure multiple worms emerging at the same time. Makoy has seen patients with as many as 40 worms.
And here’s the most insidious part: One of the few ways to relieve the pain of the blister is by soaking it in cold water, like a pond or a puddle. But that’s exactly what the worm wants. As soon as it touches water, it releases its larvae, starting the cycle anew. The Guinea worm is scarier and more efficient than any monster in a horror movie.
Makoy has seen countless times how devastating Guinea worm can be. “This is a situation where you see serious disruption of the livelihood of the community,” he says. “You see people going through a cycle of hunger because they don’t have enough. They have lost the window of cultivation. They’re not able to tend to their cattle, and there’s nothing they can do.”
There is no cure or treatment for Guinea worm, and yet, the world is on the doorstep of eradicating it. How? Through a series of highly effective interventions and a network of incredibly dedicated health workers.
Makoy’s team has built a network of volunteers in virtually every village in the country, who report rumors of Guinea worm cases. They spend every day searching for cases, getting the word out, and building trust in a country where more than 60 languages are spoken.
Makoy and his colleagues investigate every single rumor, no matter how remote. During the rainy season when the majority of cases happen, he often spends days hiking through the Sudd or up a mountain with all of his supplies on his back just to reach his destination. Last year, in a country the size of France with less than 100 miles of paved road, the team responded to nearly all of the 50,000 rumors they received within 24 hours.
Once the team finds a confirmed case, they make the patient as comfortable as possible and do what is called “controlled immersion.” This means soaking the affected area in a bucket of water and encouraging the worm to come out.
Makoy also spends a lot of time preventing people from getting Guinea worm in the first place. His team distributes free water filters and educates communities about safe water practices. The system they’ve built to support this work has strengthened health systems across the country, providing a platform for delivering other health services like childhood vaccination.
Makoy’s team has had a tremendous partner in all of this work: former U.S. President Jimmy Carter and the Carter Center. In 1995, when Makoy was first starting his public health journey, President Carter negotiated what remains the longest humanitarian ceasefire in history when he helped convince both sides of the Second Sudanese Civil War to lay down their arms and allow health workers access to treat Guinea worm and other diseases, like polio and river blindness. Today, the Carter Center continues to lead the global eradication campaign’s march to zero. The Gates Foundation is proud to support the Carter Center as part of our overall efforts to tackle NTDs. (You can learn more about Makoy’s partnership with the Carter Center in a new film called The President and the Dragon that is coming out later this year.)
Eradication is now within sight, although it won’t be easy to eliminate the last few cases. South Sudan previously reported no Guinea worm in 2018, but cases were subsequently discovered after a peace agreement was reached in the South Sudanese Civil War. And Guinea worm has recently been detected in dogs and other animals, mainly in Chad. Eradication will require stopping all transmission, both human and animal.
But Makoy Samuel Yibi is optimistic we can get there—and so am I. His determination to root out every last case makes me hopeful that we will someday soon celebrate the end of Guinea worm disease.
“In the places where Guinea worm has been eliminated,” he says, “you can actually see how communities have been energized. They are more active, and they are productive. The communities are now empowered to be more self-sufficient, because they don’t have to worry about Guinea worm.”

Ick!
What’s gross and better to see on an empty stomach? This museum in Tokyo
Welcome to the bizarre, creepy, and endlessly fascinating exhibits at the world’s foremost parasite museum.
You may want to skip lunch—and probably avoid sushi for dinner—when visiting the world’s foremost museum of parasites in Tokyo.
At the quirky and endlessly fascinating Meguro Parasitological Museum, which I toured during my trip to Japan in August, you’ll find hundreds of stomach-turning displays featuring creepy parasite specimens.
Some of the strangest-looking ones have resided inside the bodies of fish, turtles, pigs, and other animals. But by far the most horrific specimens are the parasites that have chosen humans as their hosts.
What steals the show is the world’s longest tapeworm. In 1986, this garden-hose length parasite was discovered living in the small intestine of a Japanese man. He had dined on a piece of raw salmon that was infected with a tapeworm egg smaller than a grain of rice. Over the next three months it grew and grew until it reached 29 feet long! (If you’re a follower on my Instagram account, you may have gotten a glimpse of this impressive specimen.)
The man who recovered the tapeworm from this unfortunate patient was Dr. Satoru Kamegai, the founder of Meguro Parasitological Museum. A physician, Dr. Kamegai started practicing medicine after World War II. At the time the country’s water and sanitation systems were in ruins and many people throughout Japan suffered from parasitic diseases. Dr. Kamegai became fascinated by the strange world of parasites and started collecting them from his patients. In 1953, he opened a small museum to display his findings and raise awareness of these creatures. Dr. Kamegai passed away in 2002, but the museum has continued to operate as a private research and educational facility.
Today, the museum has a collection of 60,000 different parasites, about 300 of which are on display in the two-story collection. Entrance to the museum is free and it draws a steady stream of visitors. It even has a gift shop with parasite-themed t-shirts, pens, and jewelry. (I picked up a t-shirt with the famous tapeworm on it.)
While I had a busy trip to Japan, I took time to stop at this museum because of our foundation’s efforts to reduce the burden of so-called neglected tropical diseases, many of them caused by parasites. More than 1 billion people suffer from these overlooked diseases with often difficult to pronounce names, including dracunculiasis (Guinea worm disease), human African trypanosomiasis (sleeping sickness), visceral leishmaniasis (black fever), onchocerciasis (river blindness), and schistosomiasis (snail fever).
These diseases can cause anemia and blindness, stunt children’s growth, lead to cognitive impairments, complicate pregnancies, and result in thousands of deaths each year. And it’s not uncommon for people living in extreme poverty to suffer from more than one of these diseases at the same time, affecting their ability to go to school or make a living.
Our foundation works with partners on the treatment and control of these diseases. One of the most successful efforts has been mass drug administration, which seeks to treat everyone against a disease—even if they are not actually infected or show any symptoms. I observed this incredible work in Tanzania, where I joined a group of health workers going from house to house to distribute medicine to wipe out lymphatic filariasis, one of the world’s most painful and debilitating diseases.
The good news is that there’s been a lot of progress in reducing parasitic diseases around the world. But there’s still more work to be done. That makes this museum a great place for people to learn about where these diseases still exist and the incredible work that’s going on to wipe them out.
If you happen to be in Tokyo, I encourage you to visit.
Neglected no more
A massive success
How to stop disease by treating everyone—even healthy people.
Health workers have an unusual tool for fighting disease that turns our old thinking about treatment on its head. I saw it at work recently in a remote hilltop village in Tanzania, where I joined a group of health workers going from house to house to distribute medicine to wipe out lymphatic filariasis, one of the world’s most painful and debilitating diseases.
At each home, one health worker told the family about the swollen limbs, disfigurements, and other symptoms of the parasitic disease. Another carried a tall stick to measure the height of each family member to determine the correct dosage. Then, if they were willing to be treated, the parents and children took their pills and washed them down with a cup of water before our team moved on to the next house.
What was surprising about this effort is that none of the people who took the medicine were sick.
The village I visited was participating in what’s known as a mass drug administration campaign, which seeks to treat everyone against a disease—even if they are not actually infected or show any symptoms. Typically, of course, the sick are the ones who get treated, not the people who are healthy. But when it comes to combating some diseases, like lymphatic filariasis, it’s critical for health workers to try to treat the entire at-risk population to break the cycle of transmission. If not, the disease could continue to be spread by those who are not aware they are infected.
Ten countries have successfully eliminated lymphatic filariasis in this way, including Togo, which this year became the first country in sub-Saharan Africa to wipe out the disease. Still, more than 800 million people in 52 countries worldwide remain threatened by lymphatic filariasis.
Mass drug administration is not only effective against lymphatic filariasis, but also other neglected tropical diseases, including schistosomiasis, onchocerciasis, trachoma, and soil-transmitted helminths. These diseases go by names that are largely unknown and often difficult to pronounce. But it should be easy to understand why we should all care about them. They afflict people living in the poorest countries and cause untold suffering.
Lymphatic filariasis is one of the worst of these diseases. It’s caused by a parasite that’s spread by mosquitoes, and in the severest cases people may develop swollen limbs, a thickening of the skin known as elephantiasis, or other severe disfigurements. Beyond the pain and disabilities they experience, people affected by the disease are often ostracized by their communities and are unable to work, sinking them deeper into poverty.
To combat lymphatic filariasis, health officials could test everyone and then treat only those people who are infected. But testing the population for these diseases would be expensive and slow. The medicines used for treatment (ivermectin and albendazole), however, are inexpensive and have no side effects, making mass treatment a more effective approach to protect people from the disease. (And thanks to the generosity of the many pharmaceutical companies, billions of doses of these and other medicines combating neglected tropical diseases are being donated for free.)
Like many countries running mass drug administration programs, Tanzania’s biggest challenge is treating enough of its population at risk of the disease. To break the cycle of transmission, health workers must treat at least 65 percent of the population every year for 5 to 10 years. As you might imagine, meeting this target year after year is not easy.
Health officials must have strong public awareness campaigns, thousands of trained health workers, a well-organized supply chain to distribute medicines to the remotest corners of the country, and regular disease surveying to track their progress. At the same time, the program provides treatment and care for people who are suffering from the debilitating symptoms of the diseases.
Walking from door to door in the village with the health workers, I was struck that perhaps the most important element of the program is trust. Taking the medicine is strictly voluntary, making it important that the health workers distributing it earn the confidence of the community. The health workers I met certainly had. They were knowledgeable, passionate about their work, and clearly cared about the community they were serving. At each home, they took the time to explain the goal of the program and address any of the villagers’ questions or concerns. Thanks to their hard work the latest survey of lymphatic filariasis in their district showed that the cycle of transmission had been broken. For the first time, the village was not at risk of the disease.
By 2020, Tanzania hopes to eliminate lymphatic filariasis entirely within its borders. Based on what I saw in this village, I’m optimistic they will.
24:00:00
Record-breaking generosity
On January 30, 2017, a group combatting neglected diseases did something extraordinary. Guinness World Records took notice.
Page through the Guinness Book of World Records and you’ll learn that a lot can happen in 24 hours.
On February 14, 2004, Dan Meyer of Davis, California, set the record for the longest paperclip chain by an individual in 24 hours. Length: 5,340 feet. Total number of paper clips: 54,030.
On June 4, 2011, Nabi Salehi, a barber in London, set the record for giving the most consecutive haircuts in 24 hours. Total haircuts: 526.
And on January 30, 2017, another achievement—one that will improve millions of lives—was added to the Guinness World Record list. A group fighting neglected tropical diseases—including Guinea worm, river blindness, and elephantiasis—set the record for most drugs donated in a 24-hour period. Total number of drugs: 207,169,292!
This week in Geneva, I was excited to participate in the ceremony to celebrate the group that achieved this incredible feat, Uniting to Combat Neglected Tropical Diseases, a coalition of drug companies, governments, health organizations, charities, and other partners who work to reduce the burden of tropical diseases that impact the world’s poorest.
On January 30th, they organized drug manufacturers, warehouse workers, delivery drivers, government officials, and health workers to deliver this historic number of donated drugs on four continents for distribution to people living in the remotest parts of the world.
What’s truly amazing is that the 207 million drugs donated on January 30th represent just a small amount of this group’s generosity. Since 2012, when United to Combat Neglected Tropical Diseases signed a declaration to control or eliminate 10 of the worst neglected diseases, they have donated 7 billion treatments. I’m grateful to the pharmaceutical companies that have been making these donations year after year: Bayer, Eisai, Gilead, GSK, Johnson & Johnson, MSD, Merck KGaA, Novartis, Pfizer, and Sanofi.
Thanks to the efforts of these drug companies and their partners millions of people are receiving the medicines they need to cure and protect them from these diseases. These diseases are in retreat and the world is moving closer to the day when they will be eliminated altogether.
Of course, all world records get challenged. And I for one will be thrilled for the day when this record for drug donations gets broken. So will the millions of families around the world who need them.
Warning!
Neglected no more
These diseases may be difficult to pronounce, but it should be easy to see why everyone should care about them.
Warning: you may find what I’m about to write disturbing.
Imagine a fly infected with parasites bites you. First you get a fever, then headaches, joint pains, and itching. Eventually, when the parasites cross the blood-brain barrier, you lose your mind, you can’t control your muscles, and then you lose your life.
Now, imagine you drink a glass of water. The water contains tiny fleas containing even tinier larvae. The larvae mate and grow in your body. One year later, a painful blister forms on your foot. The head of a worm pokes out. It’s 3-feet-long and takes weeks to remove.
Finally, imagine a mosquito bites you. It’s infected with tiny larvae. They set up camp in one of your lymph nodes, where they mate and nest, causing your leg to eventually swell to 10 times its size.
Sound horrific? Well, I haven’t told you the most disturbing part. I’m not making up these diseases (Human African trypanosomiasis, Dracunculiasis, and Lymphatic filariasis). They are just three of more than a dozen tropical diseases that afflict some of the poorest people in the world. As I write this, more than a billion people suffer from at least one of them.
These diseases go by names that are largely unknown and often difficult to pronounce.
Still, it should be easy to understand why we should all care about them. Spread by worms and insects, they disfigure and disable people living in the remotest areas of the world, keeping children out of school and parents from being able to work. In the worst cases, they kill. And all of them can be prevented—if the world continues to work together to end them.
I am in Geneva, Switzerland this week for a meeting to raise awareness and continue support for the fight against these overlooked diseases. Collectively, they’ve been dubbed “Neglected Tropical Diseases,” but lately they’ve been getting some of the attention they deserve.
Five years ago, Uniting to Combat Neglected Tropical Diseases, a group of pharmaceutical companies, governments, health organizations, charities, and other partners, came together to treat and prevent these diseases. They set a goal to control or eliminate at least 10 of them by 2020. Today, there’s a lot of progress to celebrate. Fewer people are suffering from them, and many countries are on their way to eliminating them altogether.
Here are some examples of the progress that’s been made.
Dracunculiasis (also known as Guinea worm), the parasitic disease I described above in which a large worm grows inside its victims, is nearing its end. In 1985, the disease afflicted an estimated 3.5 million people in 21 countries in Africa and Asia. Last year, thanks to the work of Uniting to Combat NTDs, The Carter Center, and other partners the number of Guinea worm cases has been reduced by more than 99 percent to 25 cases.
Lymphatic filariasis, also known as elephantiasis, is thepainful, disfiguring disease spread by mosquitoes. Five years ago, 1.5 billion people needed preventive drug treatment to protect them from the disease. Since then, it has been eliminated in six countries and reduced in 18 others.
Human African trypanosomiasis (HAT), commonly known as sleeping sickness, is also in retreat. Cases have declined by more than 90 percent, from 26,000 cases in 2000 to 2,733 in 2015.
What’s driving this progress? It’s been the result of drug donations by pharmaceutical companies and generous commitments by donors and governments. More than one billion people were reached with NTD treatments in 2015 alone—across nearly 150 countries.
New innovations for testing and treatment have also made a big difference. For example, the diagnostic test for sleeping sickness used to require electricity, bulky equipment, and refrigeration, making it difficult to deliver to remotest areas of the world. Now, a simple finger-prick blood test allows health workers to test for the diseases. And new smartphone-based mapping tools could make it easier to map these diseases so health workers can target their treatment efforts in real time down to the household level.
Still, there’s a lot of work to be done. We need continued support from donor governments to finish the job. We need more research on improved drugs and tests to help make it easier to treat people quickly. And we must support the frontline health workers who have the tough job of delivering the drugs in the hardest to reach regions of the world.
If the world keeps up the fight against these diseases, we can improve the lives of millions of the poorest families. They won’t be neglected anymore.
Take Action
Help us eliminate these debilitating diseases that afflict the world’s poorest by supporting The END Fund. The END Fund is a GiveWell Top Charity.

Wrapping up 2018
What I learned at work this year
Thoughts on Alzheimer’s, climate change, polio, and more.
Every Christmas when I was a kid, my parents would send out a card with an update on what the family was up to. Dad’s law firm is growing, Mom’s volunteer work is going strong, the girls are doing well in school, Bill is a handful.
Some people think it is corny, but I like the tradition. These days, at the end of each year, I still enjoy taking stock of my work and personal life. What was I excited about? What could I have done better?
I thought I would share a few of these thoughts as 2018 concludes.
One thing that occurs to me is that the questions I am asking myself at age 63 are very different from the ones I would have asked when I was in my 20s.
Back then, an end-of-year assessment would amount to just one question: Is Microsoft software making the personal-computing dream come true?
Today of course I still assess the quality of my work. But I also ask myself a whole other set of questions about my life. Did I devote enough time to my family? Did I learn enough new things? Did I develop new friendships and deepen old ones? These would have been laughable to me when I was 25, but as I get older, they are much more meaningful.
Melinda has helped broaden my thinking on this point. So has Warren Buffett, who says his measure of success is, “Do the people you care about love you back?” I think that is about as good a metric as you will find.
It may sound grand, but I think the world is slowly going through a similar transition to a broader understanding of well-being. For most of human history, we have been focused on living longer by fighting disease and trying to grow enough food for everyone. As a result, life spans have gone up dramatically. Technology has played a key role in that through vaccines, medicines, and improved sanitation.
We still need a lot of innovation to solve problems like malaria or obesity, but we are also going to be focusing more on improving the quality of life. I think this will be the thrust of many big breakthroughs of the future. For example, software will be able to notice when you’re feeling down, connect you with your friends, give you personalized tips for sleeping and eating better, and help you use your time more efficiently.
There are not the same clear measures of these things as there are for diseases, and there may never be. But there is nascent work in this field and I think it is going to accelerate.
As I look back on the year, I am also thinking about the specific areas I work on. Some of this is done through our foundation but a lot of it (such as my work on energy and Alzheimer’s work) is not. What connects it all is my belief that innovation can save lives and improve everyone’s well-being. A lot of people underestimate just how much innovation will make life better.
Here are a few updates on what’s going well and what isn’t with innovation in some areas where I work.
Alzheimer’s disease
I saw two positive trends in Alzheimer’s research in 2018.
One is that researchers focused on a new set of ideas about how to stop Alzheimer’s.
The first generation of theories, which dominated the field for years, emphasized two proteins called amyloid and tau. These proteins cause plaques and tangles in the brain, clogging up and killing brain cells. The idea was to stop the plaques and tangles from forming. I hope these approaches pay off, but we have not seen much evidence that they will.
In the past year, researchers have doubled down on a second generation of hypotheses. One theory is that a patient’s brain cells break down because their energy producers (called mitochondria) wear out. Another is that brain cells break down because part of the immune system gets overactivated and attacks them.
This is a great example of how improving our understanding of biology will reduce both medical costs and human suffering.
The other trend this year is that the Alzheimer’s community focused on getting more and better access to data. We’re working with researchers to make it easier for them to share information from their studies broadly so that we can better understand questions like how the disease progresses.
Over the past few years, the U.S. government has dramatically stepped up funding for Alzheimer’s research, from $400 million a year to over $2 billion a year. There is also a big push to create better diagnostics.
The only problem where I don’t yet see a clear path forward yet is how to develop more efficient ways to recruit patients for clinical trials. Without a simple and reliable diagnostic for Alzheimer’s, it’s hard to find eligible people early enough in the disease’s progression who can participate in trials. It can take years to enroll enough patients. If we could find a way to pre-screen participants, we could start new trials more quickly.
But there is so much momentum in other areas—scientific tools, better diagnostics, improved access to data—that as long as we can solve the recruitment problem, I am confident that we will make substantial progress in the next decade or two.
Polio
I thought we would be closer to eradicating polio today than we are. Unfortunately, there were more cases in 2018 than in 2017 (29 versus 22).
I underestimated how hard it would be to vaccinate children in places where there’s political violence and war. Families move around to escape fighting, which makes it hard to keep track of children and make sure they get all the doses of the vaccine. Or sewage systems get destroyed, allowing the virus to spread as children come into contact with an infected person’s excrement.
This is a key reason why Afghanistan and Pakistan have never been free of polio—in fact they are the only two countries that have never been free of polio.
I spend a lot of time on polio, part of it talking to the funders to make sure they continue their commitment even though eradication is taking longer than any of us would like. I remind them of the huge benefits of success, and the risk that the disease will return in a big way if we don’t finish the job.
I also remind them what a difference innovation is making. We’re now able to test sewage samples to track the virus and find the source before an outbreak starts. And the global health community is finding creative ways to work in war zones, having stopped outbreaks in Syria and Somalia in recent years.
Finally, I am hopeful about a new oral vaccine being tested in Belgium and Panama. The results should be out in 2019, and if this one proves effective, it would overcome some of the problems with previous oral vaccines when they’re used in places where few children are immunized. The new vaccine could be in use as soon as 2020.
Despite all the challenges, I am still optimistic that we can eradicate polio soon.
Energy
Global emissions of greenhouse gases went up in 2018. For me, that just reinforces the fact that the only way to prevent the worst climate-change scenarios is to get some breakthroughs in clean energy.
Some people think we have all the tools we need, and that driving down the cost of renewables like solar and wind solves the problem. I am glad to see solar and wind getting cheaper and we should be deploying them wherever it makes sense.
But solar and wind are intermittent sources of energy, and we are unlikely to have super-cheap batteries anytime soon that would allow us to store sufficient energy for when the sun isn’t shining or the wind isn’t blowing. Besides, electricity accounts for only 25% of all emissions. We need to solve the other 75% too.
This year Breakthrough Energy Ventures, the clean-energy investment fund I’m involved with, announced the first companies we’re putting money into. You can see the list at http://www.b-t.energy/ventures/our-investment-portfolio/. We are looking at all the major drivers of climate change. The companies we chose are run by brilliant people and show a lot of promise for taking innovative clean-energy ideas out of the lab and getting them to market.
Next year I will speak out more about how the U.S. needs to regain its leading role in nuclear power research. (This is unrelated to my work with the foundation.)
Nuclear is ideal for dealing with climate change, because it is the only carbon-free, scalable energy source that’s available 24 hours a day. The problems with today’s reactors, such as the risk of accidents, can be solved through innovation.
The United States is uniquely suited to create these advances with its world-class scientists, entrepreneurs, and investment capital.
Unfortunately, America is no longer the global leader on nuclear energy that it was 50 years ago. To regain this position, it will need to commit new funding, update regulations, and show investors that it’s serious.
There are several promising ideas in advanced nuclear that should be explored if we get over these obstacles. TerraPower, the company I started 10 years ago, uses an approach called a traveling wave reactor that is safe, prevents proliferation, and produces very little waste. We had hoped to build a pilot project in China, but recent policy changes here in the U.S. have made that unlikely. We may be able to build it in the United States if the funding and regulatory changes that I mentioned earlier happen.
The world needs to be working on lots of solutions to stop climate change. Advanced nuclear is one, and I hope to persuade U.S. leaders to get into the game.
The next epidemic
In 1918, the Spanish flu killed 50 million people worldwide. It still ranks as one of the deadliest natural disasters ever.
I had hoped that hitting the 100th anniversary of this epidemic would spark a lot of discussion about whether we’re ready for the next global epidemic. Unfortunately, it didn’t, and we still are not ready.
People rightly worry about dangers like terrorism and climate change (and, more remotely, an asteroid hitting the Earth). But if anything is going to kill tens of millions of people in a short time, it will probably be a global epidemic. And the disease would most likely be a form of the flu, because the flu virus spreads easily through the air. Today a flu as contagious and lethal as the 1918 one would kill nearly 33 million people in just six months.
I have been studying this for several years. To be prepared, we need a plan for national governments to work together. We need to think through how to handle quarantines, make sure supply chains will reach affected areas, decide how to involve the military, and so on. There was not much progress on these questions in 2018.
The good news is that there has been progress toward a vaccine that would protect you from every strain of the flu. This year I visited the U.S. National Institutes of Health in Maryland and got an update from some of the people leading this work.
The challenges of making a universal flu vaccine are fascinating. All strains of the virus have certain structures in common. If you’ve never been exposed to the flu, it’s possible to make a vaccine that teaches your immune system to look for those structures and attack them. But once you’ve had the flu, your body obsesses over the strain that got you sick. That makes it really hard to get your immune system to look for the common structures.
So it is clear how we could make a universal vaccine that would protect anyone (such as the very young) who has never been exposed to the flu before. But for anyone who has already had the virus, it is a lot harder. The problem is a long way from being solved, but new research money is coming in and more scientists are working on it.
To make the most of these scientific efforts (some of which our foundation is funding), the world needs to develop a global system for monitoring and responding to epidemics. That is a political matter that requires international cooperation among government leaders. This issue deserves a lot more focus.
Gene editing
Gene editing made the news in November when a Chinese scientist announced that he had altered the genes of two baby girls when they were embryos. What is unprecedented about his work is that he edited their germline cells, meaning the changes will be passed down to their children. (The other, less controversial type of gene editing involves somatic cells, which aren’t inherited by future generations.)
I agree with those who say this scientist went too far. But something good can come from his work if it encourages more people to learn and talk about gene editing. This might be the most important public debate we haven’t been having widely enough.
The ethical questions are enormous. Gene editing is generating a ton of optimism for treating and curing diseases, including some that our foundation works on (though we fund work on altering crops and insects, not humans). But the technology could make inequity worse, especially if it is available only for wealthy people.
I am surprised that these issues haven’t generated more attention from the general public. Today, artificial intelligence is the subject of vigorous debate. Gene editing deserves at least as much of the spotlight as AI.
I encourage you to read up on it whenever you have a chance. Keep an eye out for articles in your news feed. If you are willing to read a whole book, The Gene by Siddhartha Mukherjee is very well done. This story is one to follow, because big breakthroughs—some good, some worrisome—are coming.
Looking ahead
I am making a resolution for 2019.
Although I have never been one for New Year’s resolutions, I have always been committed to setting clear goals and making plans to achieve them. As I get older, these two things look more and more like the same exercise. So I am making a resolution for 2019. I am committing to learn and think about two key areas where technology has the potential to make an enormous impact on the quality of our lives, but also raises complex ethical and social considerations.
One is the balance between privacy and innovation. How can we use data to gain insights into education (like which schools do the best job of teaching low-income students) or health (like which doctors provide the best care for a reasonable price) while protecting people’s privacy?
The other is the use of technology in education. How much can software improve students’ learning? For years we have been hearing overheated claims about the huge impact that technology would have on education. People have been right to be skeptical. But I think things are finally coming together in a way that will deliver on the promises.
I will be posting updates on these and other issues on the Gates Notes.
In the meantime, Melinda and I are working on our next Annual Letter. The theme is a surprise, though it is safe to say we’ll be sharing some positive trends that make us optimistic about the future. We’ll send the letter out in February.
I hope you have a happy and healthy start to 2019.
A true data farm
Can the Wi-Fi chip in your phone help feed the world?
I recently visited an amazing farm near Seattle that uses data to grow better harvests.
I recently visited a remarkable farm in Carnation, Washington, just 25 miles from downtown Seattle.
At first glance, Dancing Crow Farm looks like any other farm. There are rows of crops and, at least when I was there, the field was dusty. There were farm implements and freshly picked peppers piled up under a lean-to. But if you talk to Sean Stratman—the man responsible for this plot—it quickly becomes clear what makes his farm so special: Sean knows more about his land than almost any other farmer on earth.
Dancing Crow Farm is the pilot site for FarmBeats, an amazing new project that hopes to make farmers more productive by arming them with data. When most people think of groundbreaking digital technology, they don’t picture soil sensors. But a farmer who knows the temperature, pH, and moisture level of his soil can make all sorts of informed decisions that save money and boost yield.
For example, fertilizer works better when it’s applied to moist soil. But how do you know when to fertilize? Soil that feels dry is often still damp below the surface. You’ll end up fertilizing more often than necessary if you go by touch alone. But if you know exactly how much moisture is in your soil at any given moment, you can fertilize only when you need to. You use less and save money.
The problem is that most existing digital platforms that provide this kind of information are expensive. Sensors can cost hundreds of dollars each, and each one only covers 10 meters. The cost is so prohibitive that only the very richest farmers can afford them.
A team of researchers at Microsoft—led by researcher Ranveer Chandra, who I talk to in the video above—wants to change that. In FarmBeats, they’ve developed a series of innovations that might one day put data in the hands of even the poorest farmers.
The main innovation is in how FarmBeats sensors transmit data. Most farms have poor or no access to the Internet. In the United States, 20 percent of people living in rural areas don’t have access to even the slowest broadband speeds. Most farm data systems require expensive transmitters to connect, but FarmBeats relies on a clever workaround: it uses TV white space.
White spaces are unused TV broadcast spectrum. If you’ve ever watched an old TV, you’ve seen white spaces before. They’re the “snow” you’ll sometimes see while flipping through channels. These gaps in spectrum are plentiful in the remote areas where most farms are located, so data can be sent over them the same way that data gets transmitted via broadband.
Here’s how FarmBeats works: The whole system is powered by solar panels. You place a small number of sensors—one every couple hundred meters, instead of 10 meters—in the ground. You then attach your smart phone with the camera facing down to either a drone (if you have money to spare) or a helium balloon (if you don’t).

You walk around the fields with the camera, creating an aerial map of the farm. Data from both the sensors and the phone are transmitted via TV white space to your computer, where an edge device stitches everything together into a data map.
The data generated by FarmBeats has been a game changer for Sean and Dancing Crow Farm. He can use up to 30 percent less water for irrigation and 44 percent less lime to control soil pH. Information on soil temperature and moisture levels has helped him better time the planting of seeds, so he gets a more productive harvest. Because Dancing Crow Farm is located next to a river, flooding is a problem. FarmBeats’ aerial imaging capabilities precisely document flooding patterns, so he’s able to better plan what he plants where. The system even helped Sean identify parts of the farms where inadequate drainage was affecting the quality of beans.
It’ll be at least a year before every component of FarmBeats is available to the public—and even longer before the cost comes down enough for broad adoption (the current version is much cheaper than other farm data systems but still too expensive for poor farmers to afford). But I’m hopeful that one day this technology could be available to every farmer everywhere, including the most remote parts of Africa.
Even as they continue working on the current version, the FarmBeats team is already working on the next generation of their technology. They just released a paper demonstrating for the first time that Wi-Fi signals can be used to collect soil data. Using only their smart phones and super cheap RFID tags buried in the ground, any farmer could get important information about their land—no special, high tech equipment required.
The Wi-Fi technology is still theoretical, but I’m glad brilliant minds are thinking about how we can help the poorest farmers gather data and increase yield. Even small gains in productivity could mean the difference between affording to send your kids to school or not. And for farmers who rely on the food they grow to feed their family—where the size of your harvest is a matter of life or death—FarmBeats could be a literal lifesaver.
More than three-quarters of the world’s poor rely on agriculture to earn a living. If we’re going to win the fight against poverty, we must help farmers—and I believe that FarmBeats could be a powerful tool.
Just the facts, Max
Memorizing these three statistics will help you understand the world
Why we should be optimistic but not complacent.

One of my favorite websites is OurWorldInData.org. Based at the University of Oxford, it uses statistics—on everything from health and population growth to war, the environment, and energy—to give you phenomenal insight into how living conditions are changing around the world. I asked its founder, Oxford economist Max Roser, to share three facts from the site that everyone should know. Here’s what Max had to say. – Bill Gates
In the past few years, it has become easy to find many of the important statistics on global development with a quick online search. And since it is now so easy to find the information you need, many argue that it doesn’t make sense to actually remember these statistics. ‘Just look them up when you need them!’ they say.
I disagree with this. Yes, for some details, it makes sense to just search for them when you need them. But for the large global developments, it is important to know some basic statistics that describe living conditions currently and the direction of change that we have seen over the past few decades. Knowing the facts on global changes gives you the context for the daily news and allows you to make sense of new information that you learn. And it must be the basis for political debate, so that we can discuss what we should and shouldn’t do as a society.
And so I compiled a short list of three facts about global living conditions that I want to remember. Each of them describes the current situation and the direction of change.
Fact #1: Since 1960, child deaths have plummeted from 20 million a year to 6 million a year.
Imagine how awful it must be to see your child die.
Then consider that every minute this happens to about 11 parents. This is the number of children, younger than five years of age, who die—on average—every single minute. Eleven deaths every minute for 24 hours add up to 15,500 deaths per day, or 5.6 million deaths per year.
Do we just have to accept that? Is that just how the world is?
Clearly no. We are very much able to drive positive change. Look at the chart below. The same UN data that shows us that 5.6 million are dying today also shows us that in the 1950s and 60s the world saw around 20 million children dying every year.
One key reason why we struggle to see progress in the world today is that we do not know how very bad the past was.
Both are true at the same time: The world is much better than in the past and it is still awful.
To bring this to mind I need to know both statistics: When someone says we can sit back and relax because the world is in a much better place, I point out that 11 children are still dying every minute. We cannot accept the world as it is today. And when I feel hopeless in the face of this tragedy, I remember that we reduced annual child deaths from 20 million to 5.6 million in the last fifty years.
So I am remembering the current extent of child mortality and the direction of change that we have seen: The number of child deaths is falling; there were 3.5-times as many child deaths 50 years ago. But child deaths are still extremely common; 11 children are dying every minute.
Fact #2: Since 1960, the fertility rate has fallen by half.
The chart below shows the key statistic to understand about world population growth: the global fertility rate—the average number of children per woman in the world. When the fertility rate is close to 2 children per woman, so that every couple is on average replaced by about two children, population growth is slow. But until the late 1960s, each woman had on average more than 5 children, and at such high fertility rates, population growth is fast. At that time the world population increased by 2 percent every year.
The availability of contraceptives allows parents to have only as many children as they want. And that number changes as people’s income goes up. From decades of demographic research, we know that women decide to have fewer children as they get access to better education and better opportunities in the job market. We also know that when child mortality falls, so that families do not need to fear that their children will die, they consequently decide to have fewer children in the first place.
Improvements in conditions for women and the health of children have driven a rapid reduction in fertility rates across the world. In fact, the global fertility rate has halved in the last 50 years, from more than 5 children per woman to fewer than 2.5 children. The world population growth rate has also halved in the last 50 years and is just above 1 percent.
The statistic that I remember on population growth is the one that tells me that rapid population growth is coming to an end in this century. In the last 50 years the global fertility rate has fallen from 5 children per woman to less than 2.5 children per woman. In fifty years the fertility rate has halved.
Fact #3: 137,000 people escaped extreme poverty every day between 1990 and 2015.
Living in poverty means that many of the most essential things in life are out of reach. People in poverty tend to lack decent shelter and basic healthcare, and they often struggle to afford adequate food supplies.
People are considered to live in ‘extreme poverty’ if they have to get by on less than 1.90 international-dollars per day, which is a currency that corrects for price differences between countries and inflation.
In this definition of poverty, the term extreme poverty is clearly appropriate: this is a very low poverty line.
When you ask people whether the world is making progress against extreme poverty, the majority of us believe things are getting worse—that the number of people in extreme poverty in the world is rising.
The opposite is true. Both the number and the share of people in extreme poverty is falling:
In 1990, 1.86 billion people were living on less than 1.90 international-$ per day—more than every third person in the world. Twenty-five years later, the number of people living in extreme poverty has more than halved to 706 million, every tenth person.
This is a very large transformation. It means that, on average, every day for the past 25 years 137,000 fewer people were living in extreme poverty than the day before. On every day in the last 25 years there could have been a newspaper headline reading, “The number of people in extreme poverty fell by 137,000 since yesterday.”
This is the statistic I remember: Today every 10th person is living in extreme poverty—706 million people. An unacceptably large number of people. But we should also know that the trend is moving in the right direction. The number of people in extreme poverty is falling. It is possible to end extreme poverty.
Remembering these facts about the world brings to mind why I think it is important to get engaged in global development. The statistics on the current state of the world make clear that we cannot be complacent about the world as it is today. Especially because progress is uneven, and in sub-Saharan Africa progress has been slower, but is not absent. The statistics on global change over time tell us that it is possible to work for a better world. The number of child deaths is dropping. The challenges of rapid population growth will not continue indefinitely. And the number of people in extreme poverty is falling.
Let’s continue in this direction. Our past successes should encourage us to work for more progress.
Endgame
Let’s make this the last pandemic
My new book is all about how we eliminate the pandemic as a threat to humanity.
The great epidemiologist Larry Brilliant once said that “outbreaks are inevitable, but pandemics are optional.” I thought about this quote and what it reveals about the COVID-19 pandemic often while I was working on my new book.
On the one hand, it’s disheartening to imagine how much loss and suffering could’ve been avoided if we’d only made better choices. We are now more than two years into the pandemic. The world did not prioritize global health until it was too late, and the result has been catastrophic. Countries failed to prepare for pandemics, rich countries reduced funding for R&D, and most governments failed to strengthen their health systems. Although we’re finally reaching the light at the end of the tunnel, COVID still kills several thousand people every day.
On the other hand, Dr. Brilliant’s quote makes me feel hopeful. No one wants to live through this again—and we don’t have to. Outbreaks are inevitable, but pandemics are optional. The world doesn’t need to live in fear of the next pandemic. If we make key investments that benefit everyone, COVID-19 could be the last pandemic ever.
This idea is what my book, How to Prevent the Next Pandemic , is all about. I’ve been part of the effort to stop COVID since the early days of the outbreak, working together with experts from inside and out of the Gates Foundation who have been fighting infectious diseases for decades. I’m excited to share what I've learned along the way, because our experience with COVID gives us a clear pathway for how to be ready next time.
So, how do we do it? In my book, I explain the steps we need to take to get ready. Together, they add up to a plan for eliminating the pandemic as a threat to humanity. These steps—alongside the remarkable progress we’ve already made over the last two years in creating new tools and understanding infectious diseases—will reduce the chance that anyone has to live through another COVID.
Imagine a scenario like this: A concerning outbreak is rapidly identified by local public health agencies, which function effectively in even the world’s poorest countries. Anything out of the ordinary is shared with scientists for study, and the information is uploaded to a global database monitored by a dedicated team.
If a threat is detected, governments sound the alarm and initiate public recommendations for travel, social distancing, and emergency planning. They start using the blunt tools that are already on hand, such as quarantines, antivirals that protect against almost any strain, and tests that can be performed anywhere.
If this isn’t sufficient, then the world’s innovators immediately get to work developing new tests, treatments, and vaccines. Diagnostics in particular ramp up extremely fast so that large numbers of people can be tested in a short time. New drugs and vaccines are approved quickly, because we’ve agreed ahead of time on how to run trials safely and share the results. Once they’re ready to go into production, manufacturing gears up right away because factories are already in place and approved.
No one gets left behind, because we’ve already worked out how to rapidly make enough vaccines for everyone. Everything gets where it’s supposed to, when it’s supposed to, because we’ve set up systems to get products delivered all the way to the patient. Communications about the situation are clear and avoid panic.
And this all happens quickly. The goal is to contain outbreaks within the first 100 days before they ever have the chance to spread around the world. If we had stopped the COVID pandemic before 100 days, we could’ve saved over 98 percent of the lives lost.
I hope people who read the book come away with a sense that ending the threat of pandemics forever is a realistic, achievable, and essential goal. I believe this is something that everyone—whether you’re an epidemiologist, a policymaker, or just someone who’s exhausted from the last two years–should care about.
The best part is we have an opportunity to not just stop things from getting worse but to make them better. Even when we’re not facing an active outbreak, the steps we can take to prevent the next pandemic will also make people healthier, save lives, and shrink the health gap between the rich and the poor. The tools that stop an outbreak can also help us find and treat more HIV cases. They can protect more children from deadly diseases like malaria, and they can give more people around the world access to high quality care.
Shrinking the health gap was the life’s work of my friend Paul Farmer, who tragically died in his sleep in February. That’s why I’m dedicating my proceeds from this book to his organization Partners in Health, which provides amazing health care to people in some of the poorest countries in the world. I will miss Paul deeply, but I am comforted by the knowledge that his influence will be felt for decades to come.
If there’s one thing the world has learned over the last two years, it’s that we can’t keep living with the threat of another variant—or another pathogen—hanging over our heads. This is a pivotal moment. There is more momentum than ever before to stop pandemics forever. No one who lived through COVID will ever forget it. Just like a war can change the way a generation looks at the world, COVID has changed the way we see the world.
Although it may not always feel like it, we have made tremendous progress over the last two years. New tools will let us respond faster next time, and new capabilities have made us better prepared to fight deadly pathogens. The world wasn’t ready for COVID, but we can choose to be ready next time.

The outbreak squad
Meet the GERM team
Creating the GERM team is one of the most important things we can do to prevent the next pandemic.
At the beginning of the movie Outbreak, there’s a scene where three government virologists arrive by helicopter at a remote village. Most of the village has recently died from Ebola-like symptoms. Wearing protective moon suits while triumphant music plays in the background, our heroes immediately get to work trying to contain the threat before it hurts anyone else. It’s an inspiring scene.
Unfortunately, it’s pure Hollywood fiction.
A full-time team like this doesn’t exist in real life—yet. I’m hoping this changes soon, because it is one of the most important things we can do to prevent the next pandemic.
Today, there are many organizations that work hard to respond to a major epidemic, but their efforts are largely dependent on volunteers. The best known is the Global Outbreak Alert and Response Network, or GOARN, which does heroic work but doesn’t have the staffing, funding, or global mandate to tackle every threat.
We need a permanent organization of experts who are fully paid and prepared to mount a coordinated response to a dangerous outbreak at any time. In my book, I propose that we call this group the GERM—Global Epidemic Response and Mobilization—team.
The GERM team would be made up of people from all over the world who have a wide range of expertise: epidemiology, genetics, data systems, diplomacy, rapid response, logistics, computer modeling, communications, and more. When they aren’t actively working in the field, most of them would call individual countries’ public health agencies home base, though some would sit in the WHO’s regional offices and at its headquarters in Geneva. (I talked about GERM at length in my TED talk last month.)
It's important that GERM have a diverse workforce. The team is going to serve the entire world—it only makes sense that its members reflect the experiences and backgrounds of the people they’re going to work with. Ideally, GERM would have a high number of local experts from countries at a higher risk of outbreak, and outsiders would only show up when necessary and when the in-country team requests help.
Here’s how a GERM response would work: The team’s disease monitoring experts would look for potential outbreaks. Once it spots one, GERM should have the ability to declare an outbreak and work with national governments and the World Bank to raise money for the response very quickly. Product-development experts would advise governments and companies on the highest-priority drugs and vaccines. People who understand computer modeling would coordinate the work of modelers around the world. And the team would help create and coordinate responses, such as how and when to implement border closures and recommend mask use.
But GERM’s response to an active outbreak is only one part of their work.
The team’s most important job is helping to run outbreak response exercises that test whether the world is ready for the next major outbreak. Militaries regularly run war games to evaluate their readiness—we should do the same with disease threats. In most countries, these exercises can be run by local public health and military leaders, with GERM acting as an advisor and reviewer. For some low-income countries, the world should invest in building this capacity and lend resources as needed.
You can learn more about what these germ games would look like by reading chapter 7 of How to Prevent the Next Pandemic, which is available as a free download for all Gates Notes Insiders.
The GERM team would also be responsible for developing a checklist for pandemic preparedness, similar to the ones that airplane pilots follow before every takeoff and many surgeons now use during an operation. A checklist sounds like such an obvious tool, but very few places had a plan like this in place when COVID hit. A GERM-developed checklist could be used anywhere and help make sure that governments are ready with an efficient and effective response.
But GERM’s impact won’t be limited to stopping pandemics. The group will improve overall health around the world, especially in the poorest countries.
Emerging diseases will always be their top priority, but when there isn’t an active pandemic threat, the team will keep their skills sharp by helping out with deadly diseases like polio and malaria. For example, they could work alongside public health workers in Nigeria to help distribute millions of doses of the oral polio vaccine every year to keep the country polio-free. This would both save a lot of kids from needless suffering and help the GERM team build relationships with communities they will need if an outbreak strikes. Now that’s what I call getting your money’s worth!
Running GERM will cost the world around $1 billion a year to cover salaries for the force of 3,000 people we’d need, plus equipment, travel, and other expenses—money that would come from governments. The work would be coordinated by the WHO, the only group that can give it global credibility, and it needs to be accountable to the public.
When Hollywood gets something wrong, the result is usually pretty silly and unrealistic. But movies like Outbreak nailed it when they imagined a global disease-fighting team who is ready to respond to a crisis on a moment’s notice. If we’re going to make sure that COVID-19 is the last pandemic, we need the GERM team.

Live from Vancouver
Talking about the last pandemic at TED
A lot has changed since the last time I spoke on the TED stage.
Last week, I went to the TED conference in Vancouver. It was my first time back at TED since 2015, when I gave a speech about how the world wasn’t ready for the next epidemic.
A lot of people watched that talk, but almost all of the views came after the start of the COVID-19 pandemic. This time, I spoke about the same subject, but a lot had changed. No one in the audience needed to be convinced that a deadly virus could kill millions of people around the world and upend our lives.
My talk was all about how we can make COVID-19 the last pandemic. I believe we can eliminate the threat of pandemics completely if we approach infectious diseases like we approach fires. We need a well-oiled system in place, complete with full-time professional personnel and innovative tools ready to be deployed at a moment’s notice.
You can watch my full talk here:
Giving a TED talk is always a memorable (and nerve-wracking!) experience. I started thinking about what I wanted to say a couple months ago. I decided to focus on what I call the GERM—Global Epidemic Response and Mobilization—team, a new full-time, paid group whose entire job is to prepare for the next outbreak. I talk a lot about GERM in my upcoming book, but this was the first time I was going to speak about GERM publicly at length.
One of the coolest things about TED is how visual all the talks are. I had the opportunity to make sure the graphics for mine looked okay during a rehearsal. I also got to practice bringing the Roman fire brigade bucket I was using as a prop onto the stage. (It’s a lot heavier than it looks!)
Learning from Munich & Islamabad
The innovations and investments that do double duty
Health systems developed to fight longstanding infectious diseases have been critical for COVID—and vice versa.
Last week, I traveled to Germany to attend the 58th Munich Security Conference, a gathering of leading experts on global security, health, development, and international relations. After learning from and working with so many of them virtually for two years, I was eager to hear from heads of state and global health leaders—in person at last!—about the ongoing impact of COVID-19 on their countries, the infectious disease and inequity challenges they’re still contending with, and what we need to be doing now to prevent future pandemics.
Health security was already a big priority at the MSC in pre-COVID times, but this year’s conference underlined how much global health is now rightfully seen as a serious national and global security issue. It’s clearer than ever that investing in health R&D, disease surveillance, and strong health systems is critical to keeping people safe, wherever they live in the world.
In Munich, I took part in a panel discussion that included the foreign ministers of Canada and Sweden, the CEO of the Crisis Group, and remarks from Tedros Adhanom Ghebreyesus, the director-general of World Health Organization. These leaders hit on the same themes I heard from many others I talked with on this trip—themes I’ve given a lot of thought to while writing a book about how to prevent the next pandemic. For one, when it comes to COVID, we’re not out of the woods yet, because the virus is still mutating. At the same time, the pandemic is evolving, with vaccines plus the rapid spread of Omicron appearing to offer many more people some protection against severe disease. Meanwhile, COVID continues to exacerbate existing inequities—something we’ll feel the effects of for years to come.
In all countries, especially the poorest, the pandemic is still hindering the prevention and treatment of other diseases. The world’s response must continue prioritizing equity and protecting the most vulnerable. We need an integrated approach that manages COVID for the long haul alongside other infectious diseases such as HIV, TB, and malaria, which continue to kill millions. This will enable countries to take limited resources and apply them where they are needed most, whether by mitigating COVID risks, supplying insecticide-treated nets against rising malaria cases, or making up for lost ground with other life-saving vaccinations.
Another theme that came up in Munich is the need for stronger health systems and tools to prevent, detect, and respond quickly to emerging and existing infectious diseases. We discussed how this can prevent future pandemics and what role multilateral cooperation must play. For example, the effects of COVID would have been much worse without investments made to fight other infectious diseases like HIV, TB, malaria, and polio. For decades, countries like Pakistan, Kenya, and South Africa have strengthened their health systems by training community health workers, building surveillance and lab capacity, creating efficient supply chains, and accelerating innovation.
The world’s response to COVID was far from perfect, but these advances helped put some countries in a better position to pivot and defend against the virus. And they helped mitigate the pandemic’s impact on these countries’ ability to fight other diseases.
Take the Global Polio Eradication Initiative. Thanks to investments made by governments, the private sector, and philanthropy, wild polio cases are at a historic low, and the disease is endemic in just two countries: Pakistan and Afghanistan. Last week I also went to Pakistan, where I visited two of the country’s innovative command centers for fighting diseases, the National Emergency Operations Center for polio eradication and the National Command and Operation Centre for COVID. The NEOC uses state-of-the-art informational tools developed by GPEI to track polio so that no child is ever paralyzed by it again. The NCOC has applied resources and lessons learned from the polio program—including data analysis, vaccine campaign planning, and community engagement—to coordinate Pakistan’s response to COVID. Both centers blew me away.
At the NEOC, we pored over a wall of screens that displayed an up-to-the-minute summary of immunization rates and areas where children have not been reached with the vaccine. The health officials I talked to in Pakistan told me that the polio program’s infrastructure was invaluable once COVID hit. By setting its priorities based on the needs at the time, Pakistan was able to expand and redirect health infrastructure that had been supported by the global community—the national help line call center, communication systems, and networks of religious leaders and community influencers—to help protect people during the pandemic.
It’s easier to ramp up testing and deliver vaccines and protective gear during a pandemic when you already have a community health workforce, labs, surveillance capacity, and supply chains in place. Another organization that has proven invaluable over the last two years is the Global Fund, which funds more than half of all global programs working to end AIDS, tuberculosis, and malaria. The Global Fund’s partnerships with countries enabled community health workers who go door to door to detect, diagnose, and report fevers as malaria or COVID. Along the same lines, organizations like the Coalition for Epidemic Preparedness Innovations, which accelerates work on vaccines for infectious diseases, and Gavi, which has immunized nearly 1 billion children since 2000, have been key partners in developing and distributing COVID vaccines.
Unfortunately, this isn’t a simple success story. We’ve also seen increases in cases and deaths from malaria, HIV, and tuberculosis for the first time in 20 years because of COVID. But the backsliding was not nearly as bad as it could have been.
I’m optimistic about the future. We have learned so much from COVID, and the innovations have been tremendous. Talking to public health leaders in Munich and Islamabad, it’s clear that long-term funding for global health—including investments in proven initiatives like GPEI, Global Fund, and CEPI —helped save millions of lives during this pandemic. Just think: It took less than a year after the virus emerged to develop a vaccine against it. I believe we’ll do even better next time and can deliver them to everyone within six months of an outbreak if we build enough global capacity.
As the pandemic continues to evolve and the world adapts strategies and investments to match, we can apply these lessons and make choices that help prevent future pandemics. We need a full-time global team dedicated to responding to new disease outbreaks and working to end other infectious diseases. We should, above all, approach this work with a greater focus on improving inequities by understanding that investments in global health and pandemic prevention are critical security issues. And they’re mutually reinforcing.
Now is the time to build on these lessons, increase our funding for the basic building blocks of public health, and support countries in meeting their needs. If we make the right choices and investments now, we can end other devastating diseases and make COVID-19 the last pandemic.

Pathogen prevention
In Africa, detecting disease outbreaks before they become a global threat
Using genomic sequencing technologies, this hero is working to prevent the next pandemic.
While promoting my new pandemic book the last month, I’ve been telling audiences and interviewers that if we want to make COVID-19 the last pandemic, we need to combat infectious diseases the same way we fight fires.
Just like we have a robust system of fire alarms, firefighters, and fire hydrants to help detect and extinguish fires, we need to create an equally effective system to identify and respond to new disease outbreaks.
This firefighting comparison is also a useful way to understand the amazing work of Sofonias Tessema.
Officially, Sofonias is the program lead for the Africa Pathogen Genomics Initiative at the Africa Centers for Disease Control and Prevention or Africa CDC. But in firefighting terms you might think of him as a fire safety officer who is building a network of fire watchtowers and smoke detectors across Africa.
Instead of looking out for the first signs of a fire before it can spread, however, Sofonias is focused on quickly detecting deadly pathogens before they can grow into a global threat. And instead of using watchtowers and smoke detectors, he relies on powerful genomic sequencing technologies to spot disease outbreaks.
Genomic sequencing allows scientists to read the DNA and RNA of pathogens and understand what they are, how they spread from one person to another, and develop counter measures like vaccines. During COVID-19, this technology has been an invaluable tool for identifying new variants, tracking the evolution and spread of the virus, and guiding public health responses.
Advances in this technology have made it easier, faster, and cheaper to do genomic surveillance. Over the last two decades, the price of sequencing a full human genome has fallen dramatically. And one company, Oxford-Nanopore, has even developed a portable gene sequencer that can be operated with a laptop and no need for a lab, allowing health officials to conduct genetic testing in remote areas where outbreaks may occur.
As powerful as genomic sequencing technologies have become, many countries have not taken full advantage of them. Building genomic disease surveillance capacity presents challenges because it requires investments in labs, expensive equipment, and specially trained personnel. While the COVID-19 pandemic has sparked new interest in using genomic sequencing to improve disease surveillance, many parts of the world are still working to strengthen their capacity to use this critical technology.
In 2019, Sofonias joined the Africa CDC to establish a continent-wide genomic disease surveillance network. One of Sofonias’s first projects was to conduct an assessment to understand how many African nations were prepared to use this technology.
The results, Sofonias said, were shocking.
Of the African Union’s 55 member states, just seven had public health institutions with trained personnel and equipment to do genetic sequencing.
Given the scale of the job before them, Sofonias and his team had planned for a phased approach to help African nations build genomic surveillance capabilities. They had to acquire the technology, hire and train the technicians to operate them, and create the data systems so governments can analyze and share the genetic information and use it to inform public health decisions. Building this system would take time.
But the Africa CDC soon learned that time was a luxury they didn’t have. Within weeks of Sofonias joining the Africa CDC, the first cases of COVID-19 were detected in China. And two months later, the first cases were identified in African countries.
It’s hard to overstate the challenge before Sofonias and the Africa CDC. While genomic surveillance had been used during Ebola, Lassa fever, and cholera outbreaks, bringing this technology to scale posed many challenges in Africa, where many countries did not have the infrastructure or trained personnel to run these labs.
But this was just the kind of challenge Sofonias had always been eager to take on.
Born in Ethiopia, Sofonias grew up in a rural town where malaria was always a major threat. Seeing people die and suffer from the mosquito-borne disease got him interested in a career in public health. He earned a PhD in malaria genomics, an emerging field of research that uses genetic data of the malaria parasite to advance malaria eradication efforts. After graduate school, he was working as postdoctoral fellow at the University of California in San Francisco, where he was focused on how genomic data combined with mobile phone data could help researchers understand how malaria spreads from one country to another.
In 2019, when a call came from the Africa CDC asking if he would use his knowledge of genomic surveillance technologies to help Africa, he jumped at the opportunity. Sofonias saw the untapped potential of this new technology to make more informed public health decisions in Africa. And after years living abroad, he was also excited to return home to Ethiopia, where the Africa CDC is based.
Sofonias and his team scrambled to quickly build up Africa’s capacity to do genomic disease surveillance. The Africa CDC focused first on scaling up COVID-19 testing capabilities. At the beginning of the pandemic, only two African nations had the ability to perform PCR COVID tests, highly accurate tests that detect genetic material from the virus.
At the same time, his team worked to acquire next-generation sequencing technologies (NGS) for Africa. NGS technologies offer a more efficient, accurate, and cheaper way for researchers to track the slightest genetic changes in pathogens which may cause disease outbreaks. This effort received support from a group of public, private, and non-profit partners including the African Union, Illumina and Oxford Nanopore, which produce next-generation sequencing machines, the US Centers for Disease Control and our foundation.
Thanks to Sofonias and the rest of the Africa Pathogen Genomics Initiative team, 31 African nations now have the capability to do genetic sequencing for surveillance of COVID, malaria, cholera, Ebola, and other diseases.
Despite this progress, much remains to be done. Sofonias’s team faces challenges in bringing this technology to all African nations. Access to the equipment needed in the labs has been delayed because of global supply chain disruptions. Training enough lab technicians and data scientists to process and analyze the samples has been difficult. Finally, more coordination is needed between countries to share their genetic data and use it to inform collective health responses.
But every month, Sofonias’s team continues to strengthen and expand the system across the continent. The goal is to create a seamless, integrated network that includes laboratories at the community level, which can spot the first signs of an outbreak, perform genomic testing of pathogens, and analyze the results to guide a public health response.
“Our vision is bold. Our vision is optimistic. We always push forward and continue to work with the countries to show that this is actually feasible,” he said. “It really makes me hopeful that this technology can improve outbreak detection and response in Africa.”
Sofonias shared the progress and challenges of building a genomic disease surveillance network with a group of graduate students who participated in a recent Gates Notes Deep Dive on pandemic prevention.

Heroic acts
Meet the heroes in Africa fighting back against this pandemic—and working to prevent the next one
As Africa faces many challenges during the pandemic, these heroes are making a difference.
In Africa, the latest statistics on COVID-19 are discouraging. Just 6 percent—about 78 millionof the continent’s 1.3 billion people have been fully vaccinated. Worldwide, by comparison, 43 percent are fully vaccinated, and boosters are now widely available in many countries.
Without enough vaccines available in Africa, COVID-19 marches on infecting millions of people. Even assessing the true scale of the pandemic on the continent is difficult. A recent World Health Organization assessment estimated that only one in seven cases of COVID in Africa are being detected because of a limited amount of testing.
And while many Western and Asian countries are recovering economically from the pandemic and returning to some version of normalcy, most countries in Africa continue to struggle. Disruptions to schooling, health care, and livelihoods have sunk many families deeper into poverty, leaving them without enough food and basic services.
We should all be upset about this inequity. (I’ve written recently about this divide and the steps the world needs to take to get the virus under control.) It’s critical that more be done to get vaccines into the arms of the people at high risk for COVID, including the elderly and immunocompromised, who are living in low-income countries. And the recent detection of the Omicron variant serves as a reminder of how important increasing vaccination rates is to deter new mutations of the virus from emerging.
But even during this difficult time, I think it’s important to highlight the many Africans who are fighting back against this pandemic. They are stepping up to alleviate suffering, to combat misinformation, and to develop the tools needed to prevent future pandemics.
There are thousands of examples of heroic work being done in Africa during this pandemic. Here are three stories of organizations and individuals who are working to save lives and bring hope to their communities.
1. South Africa: The Truck
As COVID-19 swept across South Africa, one of the most pressing needs was access to public health information. People needed to know about the virus and how to stay safe. And as South Africa started rolling out COVID vaccines this year, health officials were also tasked with counteracting the spread of misinformation about the virus and vaccines. This was especially challenging in hard-to-reach communities in South Africa, where people don’t have access to television and other media. But UNICEF, in partnership with the national government, had an answer to this challenge: A truck. Not just any truck but a multi-media messenger on wheels. The truck has LED screens, which allows the truck’s organizer to broadcast videos telling local stories about COVID-19. They also organize presentations in communities to raise awareness of the virus, teach people how to prevent its spread, and promote COVID testing and vaccinations. The truck has logged more than 40,000 miles and delivered messages to hundreds of thousands of people.
2. Lesotho: Mamello Makhele
Mamello Makhele is a nurse-midwife working to improve health care for women in rural Lesotho, where there are high rates of maternal mortality. During the pandemic lockdowns many health facilities closed, leaving women living in these remote communities without access to family planning services. On foot and by donkey, Mamello travels high into the mountain to offer health care, deliver babies, and distribute contraceptives. Mamello has also worked nationwide to empower young women, encouraging them to take control of their health and prevent unwanted pregnancies. Thanks to her incredible work, many women are healthier today in Lesotho.
3. Tanzania: Afyadata
Even as the world seeks to end the current COVID-19 pandemic, we need to also be thinking about how to prevent future pandemics. That’s just what a mobile app called Afyadata is helping health officials do in Tanzania. Designed by the Southern African Center for Infectious Disease Surveillance (SACIDS), Afyadata is a digital surveillance tool that allows health workers and even ordinary people to serve as disease detectives. Users can report unusual health occurrences not only in humans, but also animals. Monitoring animals is critical because most new pathogens start in animals before they spread and sicken humans. With the app, farmers can easily report any suspicious illness among their livestock to health officials, who can then quickly follow up with further investigation, if necessary. While this app is still being piloted in several districts of Tanzania and other parts of Africa, it has already been effective in the detection and identification of several small disease outbreaks. I look forward to learning more about Afyadata’s progress.
Inspiring acts
7 unsung heroes of the pandemic
Incredible people caring for those in need during COVID-19.
When I was a kid, my image of a hero was largely inspired by my dad’s collection of early Superman comics. I read them all. A “hero” was somebody who had supernatural powers like flying, laser vision, or the strength to bend steel.
As humans, of course, we’re all pretty limited in our physical powers. We don’t fly. We can’t see through walls. But what’s unbounded in us is our ability to see injustices and to take them on—often at great risk to ourselves.
My work in global health and development has introduced me to many extraordinary heroes with this kind of superpower. And I’ve had the honor of highlighting many of them on this blog: An epidemiologist who helped eradicate smallpox. A doctor working to end sexual violence in Africa. A researcher working to end hunger with improved crops. Just to name a few.
Why do we need heroes?
Because they represent the best of who we can be. Their efforts to solve the world’s challenges demonstrate our values as a society and they serve as powerful examples of how to make a positive difference in the world. And if enough people hear about their actions, they can inspire others to do something heroic too.
If there’s ever been a time that we need heroes, it’s now. The COVID-19 pandemic has created unprecedented health and economic challenges, especially for the most vulnerable among us. The good news is that many people from all walks of life are doing their part to help them. Health care workers. Scientists. Firefighters. Grocery store workers. Aid workers. Vaccine trial participants. And ordinary citizens caring for their neighbors.
Here are portraits of a few individuals from around the world working to alleviate suffering during this pandemic. I hope their stories inspire you just as much as they have me.
To these heroes and heroes everywhere, thank you for the work you do!

Abundant air
Breathing new hope into Africa’s fight against COVID-19
In Africa’s battle against COVID-19, a Kenyan doctor is making sure every breath counts.
As the COVID-19 pandemic spreads across Africa, hospitals across the continent face shortages of essential medical supplies needed to treat the respiratory disease and keep patients alive.
Not just masks and ventilators, but oxygen.
For people living in wealthy countries, medical oxygen is often taken for granted. In many low-income countries, however, oxygen is often in short supply or not available at all. And globally, a lack of oxygen –needed to treat pneumonia, malaria, and other diseases—leads to hundreds of thousands of deaths each year.
Addressing this often overlooked challenge is the life’s work of Bernard Olayo, a Kenyan doctor who founded Hewatele, an innovative organization working to ensure all patients—even in remote areas of the country—have access to oxygen.
Now, he is playing a critical role in Kenya’s preparations to tackle COVID-19 by scaling up oxygen supplies that will be needed to keep the most critically ill patients alive.
While the number of COVID-19 cases in Africa remains low compared to other parts of the world, the continent is bracing for a surge of infections. According to the World Health Organization, up to 190,000 people could die of COVID-19 in Africa if the disease is not controlled. A widespread outbreak would flood many of Africa’s fragile health systems.
A lot of attention has been focused on the lack of ventilators in Africa. Ventilators are the mechanical devices that help patients breathe, pushing air in and out of their lungs, when they can’t on their own. And the shortage of them is a real problem. But the lack of oxygen itself is equally worrying. The coronavirus attacks the respiratory tract, inflaming the lungs and making it difficult for patients to breathe. Oxygen, delivered through a mask or nasal tube, is an essential and effective first line of treatment that’s less invasive than being on a ventilator. Oxygen is also needed to run a ventilator. If COVID-19 patients have access to oxygen as an initial treatment, however, it may prevent many of them from becoming so critically ill that they would require one of the limited number of ventilators to breathe.
What Bernard is hoping to avoid during this pandemic are the painful choices he faced as a young doctor because of a lack of oxygen. After medical school he was posted to a rural hospital, where many of the patients were children battling pneumonia who needed oxygen for treatment. But Bernard soon learned that there was never enough oxygen available. He and the other hospital staff often had to share a single cylinder of oxygen between patients. When there were too many patients and not enough oxygen, he and other doctors would be forced to decide which children would receive oxygen and live, and which would go without it and sometimes die—a choice that broke his heart, he says.
That experience inspired Bernard to investigate the source of Kenya’s oxygen supply shortages. He discovered that one of the biggest challenges is that oxygen is expensive in Africa. In Kenya, oxygen costs about 13 times more than what it does in the United States. The high cost was driven, in part, by a lack of competition. In many countries, including Kenya, there was just a single oxygen supplier for the entire country. And with many health facilities located hundreds of miles away from the oxygen plants, transportation costs drove up prices even higher. The long distances and poor roads also meant that deliveries were unreliable. Hospitals and clinics would regularly run out of oxygen supplies.
In 2014, Bernard founded a public-private partnership to try a new approach that would make access to medical oxygen more affordable and reliable. He named the organization Hewatele (Swahili for “abundant air”). Given the delivery challenges in Kenya, Bernard decided to build oxygen plants at several of the busiest hospitals in the country, where demand is highest and reliable electricity for production is available. The oxygen is then sent out for delivery using a milkman model, with oxygen cylinders regularly dropped off at remote hospitals and clinics and the empty cylinders returned to be refilled. This system ensures that there is always more than enough oxygen available at each facility. Using this new approach, Hewatele has cut the market price for oxygen in Kenya by 50 percent. Now, Bernard is working to expand the number of oxygen plants in Kenya and bring Hewatele’s business model to other parts of Africa.
While the COVID-19 pandemic has brought much needed attention to the oxygen gap in Africa, more needs to be done to ensure that everyone has access to this simple medical intervention. Thanks to Bernard’s efforts, progress is being made. His work has already helped save the lives of thousands of children and adults and will save many more in the future—one breath at a time.

High hopes
This organization is working to create a world without pandemics
The Coalition for Epidemic Preparedness is working to make sure we never again experience the hardship of a pandemic.
Here’s a fact that’s hard to believe: At this time two months ago, the world did not yet know about the omicron variant.
It’s both remarkable and horrifying how quickly omicron has become the dominant cause of COVID-19 in many countries. In just seven weeks, it has led to record-high case numbers and hospitalizations around the world. I’m still optimistic that the pandemic can come to an end sometime in 2022, but first we have to contend with a virus that’s spreading faster than any other in history. (I recently had a good discussion about this with global health Professor Devi Sridhar.)
The omicron surge has been an unfortunate reminder that the only way to eliminate the threat of COVID-19 somewhere is to eliminate it everywhere. As long as the virus continues to circulate at a high level in some parts of the world, we’ll always be at risk for another devastating variant. Game-changing innovations—including vaccines and new antivirals—will save lives but won’t truly accelerate the end of the pandemic until they’re accessible to everyone.
That’s why the Gates Foundation is renewing its investment in the Coalition for Epidemic Preparedness Innovations, or CEPI. I’m excited to announce a new $150 million commitment to its future work on COVID and beyond.
Our foundation helped create CEPI in 2017 to accelerate work on vaccines against new infectious diseases and make sure those vaccines reach people in the poorest countries. The organization has played an invaluable role in the COVID-19 pandemic as one of the leaders of COVAX, the global effort to get vaccines out to low- and middle-income countries.
As with malaria, polio, and many other diseases that our foundation works on, the key to pandemic prevention and preparedness is to keep on innovating. This pandemic’s most significant innovation is mRNA vaccines, which were available less than a year after the virus that causes COVID was identified. CEPI began funding efforts to develop mRNA vaccines for COVID just days after the virus was detected outside of mainland China. (One of the candidates CEPI backed in January 2020 was Moderna.)
But CEPI’s support for research on mRNA vaccines predates COVID-19—which is one of the reasons the approach was successful. The groundwork had been laid years before by investments from governments, pharmaceutical companies, and (more recently) CEPI. And the progress they’ve supported will continue to pay dividends long after the COVID pandemic ends. The mRNA platform is already being used to test new vaccines for TB and malaria diseases. Scientists are hard at work formulating next-generation vaccines that don’t require as many doses and don’t need to be kept frozen.
Altogether, CEPI has invested in 14 COVID vaccine candidates and it continues to work on variants of concern and develop next-generation vaccines that could protect against all coronaviruses. It is also focusing on six other diseases of epidemic potential.
But creating new vaccines isn’t enough. We also have to make sure that everyone who can benefit from vaccines has access to them, and that’s where the world has collectively failed in its response to COVID. While at least 9 billion doses were distributed in the past year, less than one percent went to people in low-income countries. It doesn’t make sense that so many people at lower risk of infection in wealthier countries got vaccinated before we reached the most vulnerable people, including the elderly, those with underlying medical conditions, and healthcare workers.
We need to do better the next time the world faces a pathogen that has the potential to spark a pandemic. (I’m currently writing a book about what the world needs to do to prevent the next pandemic, which will come out later this year.) I believe that the world can and should be ready to develop a new vaccine and make enough for everyone in the world within six months of detecting a potential pandemic—and CEPI will play a crucial role in achieving that. It is one example of how we need to be making investments now to support innovations that will prevent disasters in the future. For example, the organization is supporting efforts to increase manufacturing capacity and recently released a study that provides valuable insights into how we can improve the world’s production capabilities. This is the type of investment we need to make now to prevent disasters in the future.
And because CEPI is a global institution rather than a national one, it can focus on providing access for everyone, alongside other effective global institutions that have saved millions of lives like WHO, Gavi, and the Global Fund to Fight AIDS, TB and Malaria. These groups will help make sure that vaccines don’t just go to the highest bidders.
Imagine how different the last two years would’ve been if everyone in the world had had access to safe, effective COVID vaccines within six months. I know it’s hard to think about the next pandemic as the omicron variant surges around the world, but we have an opportunity to make sure the world never experiences this hardship again. Investing in organizations like CEPI is an important step that moves us closer to a world without pandemics.

COVID coverage
Next time, we can close the vaccine gap much faster
How to use vaccines more fairly and effectively.
Today, 46 percent of the world’s population has received at least one dose of a COVID-19 vaccine. It’s hard to overstate what a remarkable achievement this is. Humanity has never made and distributed a vaccine for a disease faster than it did for COVID-19. It accomplished in 18 months something that used to take a decade or more.
But within this amazing success there is a startling disparity: Just over 2 percent of people in low-income countries have received any COVID-19 vaccines. And the gap will be harder to close as rich-world governments buy up extra doses to serve as booster shots.
People are right to be upset about the inequity here. Vaccines make COVID-19 a largely preventable disease—and a survivable one in all but the rarest cases—and it is heartbreaking to know that people are dying of a disease not because it can’t be stopped but because they live in a low-income country.
Sadly, this inequity is not new. It is not even the worst gap in global health. There were shocking disparities in health long before any of us had heard of COVID-19.
Every year, more than 5 million children die before their fifth birthday, mostly from infectious diseases, and almost entirely in low- and middle-income countries. A child in northern Nigeria is 20 times more likely to die before the age of 5 than a child in a rich country. That is simply unjust, and reducing this inequity has been the Gates Foundation’s top priority for more than 20 years.
If you step back and look at the trends, though, there is good news. Since 1960 the childhood death rate has been cut by more than 80 percent, thanks in large part to the invention and distribution of vaccines for children around the world.
The fact that routine childhood vaccines are reaching so many people is reason to believe COVID-19 vaccines can too. Providing them to everyone who needs them is one of three crucial steps in controlling this pandemic, along with containing the virus so it doesn’t come roaring back and coordinating the global response. At the same time, we can learn from the inequities that were so clear during this pandemic so we can do a better job of closing the gap during the next one. (Assuming there is a next pandemic. I think it is possible to prevent them altogether. But that’s a subject for another time.)
How could we achieve vaccine equity in a future pandemic? I see two ways.
1. Change how the world allocates doses.
What would the optimal allocation look like? It’s not simply a matter of proportional representation, where if your county has X percent of the world’s population, you get X percent of the vaccines. There are two different benefits to consider, and both are important.
One benefit is to the individual who’s immunized; they get protection from the virus. The more likely you are to get infected—and the more likely you are to become seriously ill or die if you do get infected—the more benefit you get from a vaccine. A COVID-19 patient in their seventies is 90 times more likely to die of the disease than a patient in their twenties. From a global perspective, it is neither fair nor wise to protect that young person before the old one.
Second, when an individual is vaccinated, society gets the benefit of lowering the risk that the person will spread the disease to others. This is the core of the argument in favor of vaccinating health workers and people who work in elderly care facilities, since even when a lockdown is in place, they can transmit the virus to people at high risk.
When a virus is spreading, we should maximize both benefits—saving lives and stopping transmission. This means that, when supplies are short, we should prioritize vaccinating people who both have a high risk of death and live in the places where the virus is spreading fastest.
Those will not necessarily be low-income countries. When COVID-19 vaccines first became available, many of the most severe epidemics were in rich- and middle-income countries.
The gravest inequity, even more than vaccinating rich people before poor ones, is vaccinating young people in rich countries before older people in middle-income countries with bad epidemics, such as South Africa and most of South America.
To their credit, rich countries have pledged to share more than a billion doses with poorer countries during COVID-19. But they haven’t yet delivered fully on those pledges, and even if they had, the gap would still be enormous.
Although sharing doses needs to be part of the solution, it will never be sufficient to solve the problem. For one thing, the number of doses won’t be high enough. And will future politicians always be willing to tell young voters they can’t be vaccinated because the doses are going to another country, at a time when schools are still closed and people—including a few young people—are still dying?
That’s why it’s so important to find ways to produce more doses in less time. The world should have the goal of being able to make and deliver enough vaccines for everyone on the planet within six months of detecting a potential pandemic. If we could do that, then the supply of doses would not be a limiting factor, and the way they were allocated would no longer be a matter of life and death.
2. Make more doses.
As limited as the supply of COVID-19 vaccines has been, the situation could have been even worse.
We are fortunate that mRNA vaccines work so well, since this is the first disease for which the mRNA technology has been used. If they hadn’t, we would have been far worse off.
It is also great that some vaccine companies entered into second-source deals, which allowed huge volumes of their vaccines to be manufactured by other firms. This was a crucial and remarkable step. (It’s as if Ford let Honda use its factories to build Accords.) Just one example: In less than two years, a single manufacturer, AstraZeneca, signed second source deals involving 25 factories in 15 countries.
You may have heard the argument that waiving intellectual property (or IP) restrictions would have made a difference. Unfortunately, that’s not true in this case. IP waivers and licensing are a complicated issue, so I want to take some time to untangle it.
There are cases in which IP licensing is a great way to make something cheaper and better. For example, in 2017, the Gates Foundation and a number of partners were involved in an agreement to make a new, more effective version of an HIV drug cocktail that would be more affordable for the world’s poorest countries.
In the deal, a pharmaceutical company gave the recipe for the key ingredient in this cocktail to firms that specialize in producing generic drugs. These firms were able to reduce the cost so much that today nearly 80 percent of people who get HIV treatment in low- or middle-income countries are receiving the improved cocktail.
Unfortunately, IP licensing doesn’t work as well with vaccines. Here’s why.
Many drugs are made using chemical processes that are well defined and measurable. If you mix the same ingredients in the right proportion and so on, you’ll get the same product every time, and you can check your work by looking at the chemical structure after the drug is made. Company A can give a recipe to company B, and company B will be able to make precisely the same drug consistently.
But many vaccines don’t work that way. Manufacturing them often involves living organisms—anything from bacteria to chicken eggs. Living things don’t necessarily act exactly the same way every time, which means that even if you follow the same process twice, you might not get the same product both times. Even an experienced vaccine maker might not be able to simply take another’s recipe and replicate it reliably.
This is why broadly waiving IP protections would not meaningfully increase the supply of vaccines. (In the case of COVID-19, though, a narrow waiver that applied to specific easily transferred technologies during the pandemic made sense.) Supply has been limited not because of IP rules, but because there aren’t enough factories capable of handling the more complicated process of making vaccines.
Licensing IP—or having the rights to it waived—only guarantees that company A can’t sue company B. Second-source deals are far superior because they involve sharing not only the recipe but also knowledge about how to use it, as well as personnel, data, and biological samples. It was a second-source deal with AstraZeneca—not an IP waiver—that allowed Serum Institute of India to produce 100 million doses at a very low cost and in record time.
So how can the world make more doses faster next time?
First, decision makers should get serious about expanding the world’s vaccine-making capacity. In particular, governments and industry should make sure there’s enough capacity to quickly make huge volumes of mRNA vaccines; now that we know the mRNA platform works, it will allow new vaccines to be developed faster than any other approach. And if companies that have second-source deals now maintain their relationships with each other, they won’t have to start from square one in the next outbreak.
Another step is to develop prototype vaccines against the diseases that are most likely to cause future outbreaks, and to develop universal vaccines for flu and coronaviruses, which would protect people against any form of the two pathogens. The NIH and Coalition for Epidemic Preparedness Innovations are doing excellent work on both, but even more research is needed.
One longer-term step is for more countries to build the capacity to develop, manufacture, and approve vaccines themselves.
Historically, the companies that invent new vaccines have been based in higher-income countries. Because it costs so much to develop a new product, they try to recoup their costs as quickly as possible by selling doses at the higher prices that rich countries can afford. They have no financial incentive to try to lower their costs (by optimizing the production process, for example) so that the price can be cheap enough for lower-income countries.
The pentavalent vaccine—which protects against five diseases—is a great example. It was invented in the early 2000s, but there was only one manufacturer, and at more than $3.50 per dose, it was far too expensive for low- or middle-income countries. Our foundation and other partners worked with two vaccine companies in India—Biological E Limited and Serum Institute of India—to develop a pentavalent vaccine that would be affordable everywhere. Today that vaccine costs about $1, and it is given to 80 million children a year. That’s a 16-fold increase since 2005.
We need more examples like this. Pentavalent took years to pull off. If there were more high-volume vaccine manufacturers whose primary goal was to produce low-cost vaccines, then affordable doses would be available much faster. Middle-income countries are a natural home for these companies, and some have set ambitious goals for themselves. For example, a group of African leaders has set a target of manufacturing 60 percent of the continent’s vaccines by 2040.
Helping middle-income countries build their vaccine-making capacity is something the Gates Foundation has been working on for two decades. We’ve helped bring 17 vaccines to market, and we’re supporting the African efforts to build theirs out by 2040.
What we’ve learned is that creating an entire vaccine-making ecosystem is a tough challenge. But the obstacles can be overcome.
One issue is the need for regulatory approvals. Vaccine factories are required to be approved by what’s known as a “gold-standard” regulator. India is the only developing country with a gold-standard regulator; factories in any other developing country have to be approved by their own government first, and then by the WHO. It’s time-consuming.
Regional agencies in Africa are working with the WHO and the European Union to create gold-standard regulation on the continent. Governments are also collaborating on regional standards for vaccines, so manufacturers don’t have to meet different safety and efficacy requirements in each country.
Another challenge: If vaccine manufacturers don’t have other products to make between outbreaks, they’ll go out of business. Unfortunately, making existing vaccines isn’t a viable option, at least right now, because the market is already saturated with existing vaccines, and it would be hard for new entrants to compete on price with established low-cost / high-volume companies.
But new products are coming that would be ideal products for them. As vaccines become available for diseases like malaria, tuberculosis, and HIV, they’ll create opportunities for producers in middle-income countries. In the meantime, countries can take on the fill and finish process—putting vaccines made elsewhere into vials and distributing them.
To anyone who has lost a loved one to COVID-19, or had to choose between paying the rent or buying food, it is no comfort to suggest that anything has gone well in this pandemic. But as my friend the late Hans Rosling used to say, “The world can be both bad and better.” The situation today is bad, and also better than it would have been if COVID-19 had come along ten years ago. If the world makes the right investments and decisions now, we can make things better next time. And maybe even make sure there is no next time at all.
This post originally appeared on CNN.com.

Pandemic plan
How to end the COVID crisis
Three steps to getting the virus under control.
This week global leaders are coming together at the UN General Assembly, which presents an opportunity to refocus energy and commitment on ending the crisis phase of this pandemic and to make sure we’re better prepared for the next one. In this piece I talk about how we can apply what we have learned since early 2020 and embrace a set of global actions that chart an equitable course out of the pandemic—vaccinate now, contain the disease, and coordinate the global response.
We’ve reached the 18th month of the COVID-19 pandemic, a somber milestone marked by yet another surge of cases and deaths fueled by the Delta variant. This global crisis has been a health, economic and moral disaster playing out in waves in every geography, sparing none. While the pandemic has been a shared experience, the experience has not been the same everywhere.
In the past year-and-a-half, we have witnessed scientific breakthroughs with multiple safe and effective vaccines developed in record time, incredible multilateral cooperation resulting in billions of dollars raised for the response, and heroic efforts by healthcare and frontline workers in communities worldwide. But at the same time, we have also seen widening gaps in equity that go against everything our foundation and its partners have worked for over the past 20 years. The advent of vaccines was an opportunity to bend the curve in the direction of a global recovery. It turned out that unequal distribution and a lack of funding and supply meant the recovery has been precarious and halting.
In last year’s Goalkeepers report, Melinda and I shared modeling that warned that globally deaths would be higher if doses went predominantly to high income countries. To date, less than 2% of people in low-income countries have received a dose of a COVID-19 vaccine, compared to more than 60% of people in the U.S. The pull of the inequity we’re seeing isn’t only on the here and now—the economic recovery of low-income countries that are slow to be vaccinated is stuck in the starting blocks. These countries can expect to experience between 2-4% GDP losses through 2025 (averaging 3% per year in sub-Saharan Africa).
After 18 months of surprises around every corner with variants fueling new waves of disease there’s a tendency to say one cannot predict what will happen next. To some extent that’s true—nature is wily, and the virus will continue to mutate if it can transmit unchecked. But it’s also defeatist and incorrect to suggest that the acute phase of the pandemic will spiral on from one variant to the next. Just as the virus can change, so can the world’s response to it. Whether the world can finally turn the corner, however, will be determined by what we do next and how it’s done.
Our path out of the pandemic has always required one thing—a commitment to equity. A willingness to see that what happens in lower-income countries affects high-income countries. There is no nationalistic solution to this global problem. We’ve seen countries try and fail in that pursuit as variants emerge and threaten progression from the acute phase of the pandemic. There are three things that can be done in the coming months that can bring about the end of the acute phase of the pandemic and set the world on a different timeline in preparation for the next. I hope that leaders meeting virtually this week at the COVID Summit commit to actions that meet these needs:
1. Vaccinate Now
Governments and the private sector must work together to build a more transparent system to accelerate the global supply of vaccines. While a shortage of supply was a major issue in the first half of the year, recently 41 million doses per day have been distributed globally. It’s progress, but there’s a long way to go. The WHO/Gavi-led COVAX AMC, Africa CDC-led African Vaccine Acquisition Task Team (AVATT) and other channels can move vaccines, but they need more doses, visibility to supply, and sufficient money to acquire and deliver them. This is quickly turning into a logistics and financing challenge, and we know how to solve those types of problems. A consolidated global dashboard that provides real-time vaccine production and availability data will enable countries and global institutions to collaborate on filling access gaps. While donations to COVAX were slow to arrive, current funding can support delivery to about 30% of the population in lower- and middle-income countries. It’s a good start, and funding for 70% coverage in the lowest income countries needs to be made available by mid-2022 along with enhanced delivery capacity at the country level.
2. Contain the Disease
In addition to getting vaccines out to close the global equity gap we also must contain outbreaks as they happen. This can help keep countries out of the cycle of lockdowns that has left schools and businesses in constant flux. To reduce the risk of variants jumping from border to border, the world must invest in readily available rapid testing, a system for sharing genetic sequences, and a mechanism to deliver expertise and commodities (like oxygen, PPE, and life-saving drugs) quickly where they are needed. We’ve seen this done successfully with diseases like polio and malaria—using data to inform actions that bring outbreaks under control. We need to have expert support and response materials like oxygen, PPE, and life-saving drugs ready to deploy in the event of major outbreaks. The private sector has a role to play, using its expertise in logistics to reduce lead times and fill supply gaps.
3. Coordinate the Global Response
The establishment of the Access to COVID-19 Tools Accelerator (ACT-A) in early 2020 was a milestone: governments, international organizations and the private sector came together in response to the crisis. We now need all governments to appoint a COVID-19 global lead, reporting to the head of state, and for these leads to regularly convene through 2022. With the support of independent monitoring this globally coordinated, time-limited task force can complement ACT-A and take us from aspiration to ending the pandemic through collective action and provide a model for the long-term coordination needed to prevent future pandemics.
For people involved in global health, what happened during the pandemic is disappointing, but not a surprise. The system whereby lower-income countries rely on the generosity of high-income country donors broke down when those donor countries were experiencing the same struggles. The next 18 months do not have to look like the past 18 months. But we cannot turn the page on this pandemic until we’ve addressed the fundamental inequity that stands in our way.
I’m optimistic about the potential of this moment. Health is not a zero-sum game—we can meet everyone’s needs through planning, investment, collaboration, and applying lessons learned. The cost of this pandemic has already been unacceptably high. Ending it cannot come at the cost of progress on other global health and development priorities. Reducing poverty, advancing gender equality, and finishing the job of eradicating polio are all possible through the same collective action that is needed to end this pandemic.
For those that want to go deeper, Gargee Ghosh who heads up the policy and advocacy division at the Gates Foundation has shared a white paper with more details on actions the world could take to end the COVID crisis.

Changes
5 things you should know about variants
The virus that causes COVID-19 is evolving, and it’s complicating our efforts to end the pandemic.
I’ve spent a lot of time over the last year meeting with colleagues at our foundation and around the world about ways to test for, treat, and prevent COVID-19. In recent months, the experts in those meetings are increasingly asking the same question: How will new variants impact our efforts to end the pandemic?
The world has come a long way in the fight against COVID-19, but new variants of the virus could threaten progress we’ve made over the past year. Here are five things you should know if you want to understand how variants are (and aren’t) complicating the pandemic.
1. If you’ve ever gotten a flu shot, you’ve already dealt with a virus variant.
Viruses evolve all the time. Unless you work on infectious diseases, the idea of a “variant” might seem new and scary—but there’s nothing particularly unusual about them. Influenza’s ability to mutate quickly (I’ll talk more about this in the next section) is why we get a new flu shot every year. We need to update the vaccine annually to keep up with constantly shifting flu virus strains.
To understand why the virus that causes COVID-19 is changing, you need to understand how it works (or spreads) in your body. The coronavirus—like all viruses—has only one goal: to replicate itself. Every time the virus invades your cells, it tricks the cell into following the instructions encoded in its RNA to make more copies of the virus.
When the cell is making a new virus, it has to copy those instructions. If you’ve ever had to take a typing class in school, you know how hard it is to retype something without making a mistake. The code for the virus that causes COVID-19 is around 30,000 letters long. That’s a lot of opportunities to mess up—which the coronavirus often does.
Most mistakes lead to a virus that either is functionally identical or can’t replicate. But every once in a while, there’s a change that makes it easier for the virus to infect people or evade the immune system. When that change starts to spread through a population, a new variant emerges.
2. We’re seeing the same mutations pop up again and again. That may be good news.
All viruses evolve, but not all viruses evolve at the same rate and in the same way. Some, like the flu, change rapidly. Others mutate slowly. Fortunately for us, SARS-CoV-2 is in the latter camp. It mutates about half as fast as the influenza virus.
I know it feels like new variants are popping up all the time right now. That’s because there is so much virus circulating around the world, giving it more opportunities to change. Once case numbers go down, I suspect we’ll see new variants emerge much less often.
Compared to influenza viruses—which are made up of eight genetic segments that can be rearranged in lots of different ways—the coronavirus is a much simpler virus. The most notable mutations we’ve seen so far have happened in the same spot: the spike protein that sticks out of the surface of the virus.
That spike protein is the key to COVID’s spread. Its shape is what enables the virus to grab onto human cells. If the spike protein changes just a little, it might bind with cells more effectively (which makes the virus more transmissible) or become harder for the immune system to target (which makes people more susceptible to it). But if it changes too much, the virus can no longer gain the entry that’s key to its lifecycle.
That limited capacity for change may explain why we keep seeing the same mutations appear in different places rather than lots of distinct variations. Both B.1.1.7 (which was originally detected in the UK) and B.1.351 (which was first found in South Africa) evolved independently, yet they share a number of the same mutations. There’s clearly something about these specific mutations that makes them more likely to succeed than other changes.
Some experts think we may have already seen the most concerning mutations that this virus is capable of. But COVID-19 has surprised us before, of course, and it could surprise us again.
3. The virus is changing, but the path to ending the pandemic remains the same.
For the last year, public health experts have been repeating some form of the same message: we need to contain COVID-19 as best we can until the vaccine is ready and available for everyone.
The good news is that many of the vaccines being used today appear to prevent severe disease, even from the new variants. This is a tribute to how effective the vaccines are in general. We still need a lot more data about how effective every vaccine is against the different variants, but many of the early numbers are reassuring (especially out of Israel, where many people are already vaccinated and the B.1.1.7 strain is dominant).
The big question now is whether we need to update the vaccines to target the variants. Regulators and drug companies are working on a modified vaccine that could be out in a couple months if it’s deemed necessary. Here in the United States—where the majority of people will likely be vaccinated by the end of the summer—some people may end up getting a booster shot that protects against additional strains.
For now, the key is to keep following best practices. The best way to prevent new variants from emerging is by stopping transmission of the virus altogether. If we remain vigilant about social distancing, wearing a mask, and getting vaccinated, we will bring the pandemic to an end much sooner.
4. Variants make it even more important that vaccines are made available everywhere.
COVID-19 anywhere is a threat to health everywhere. That’s true with the original virus, and it’s true when it comes to variants.
The more the virus that causes COVID-19 is out there in the world, the more opportunities it has to evolve—and to develop new ways of fighting our defenses against it. If we don’t get the vaccine out to every corner of the planet, we’ll have to live with the possibility that a much worse strain of the virus will emerge. We could even see a new variant emerge that evades existing vaccines altogether.
No one wants that to happen. The best way to make sure it doesn’t is by getting the vaccine out to everyone who needs it, no matter where they live. That’s why our foundation is working with governments, vaccine manufacturers, organizations like CEPI and Gavi, the Vaccine Alliance, and others to deliver COVID-19 vaccines to low-income countries through an initiative called COVAX.
COVAX recently announced that it’ll be able to deliver 300 million doses by mid-2021. That’s great news, but the world is going to need a lot more if we’re going to truly stamp out the threat of COVID-19. I hope rich world countries continue to support COVAX’s work, even as life starts to get back to normal in some parts of the world over the summer.
5. We can do better next time.
Virus variants are inevitable. If we ever find ourselves in a pandemic scenario again where a pathogen is spreading around the globe, we should expect to see it adapt to survive our attempts to stop it—just as we saw with COVID-19. I hope the difference next time is that we’re better prepared to spot these variants earlier.
The key will be genetic sequencing in combination with better disease surveillance. Right now, if you test positive for COVID-19, there’s a possibility that your test sample gets selected to be sequenced. This lets researchers see the exact 30,000 letter code that makes up the virus’ RNA instructions. That code gets uploaded to a database, where a computer compares the virus in your sample to all the other strains in circulation. . If you have a new strain that’s starting to pop up over and over in your area, scientists can compare the sequence data to transmission, death, and hospitalization rates to see if there’s need for concern.
Researchers need to take a systematic approach to catch variants early. Some experts think we need to sequence at least 5 percent of all test samples to get an accurate picture of how a pathogen is mutating—although sequencing a large number of samples alone isn’t enough. The UK has analyzed nearly 8 percent of its tests and linked that data with their surveillance capabilities, which helped them see that B.1.1.7 was spreading much faster and was more lethal. South Africa was able to quickly see how vaccines worked on B.1.351 by comparing results from clinical trials there to sequenced data.
The tools we’re putting in place to monitor variants in this pandemic will prove invaluable long after the worst of COVID-19 is behind us. Widespread sequencing should be part of any plan to prepare for the next pandemic. If you’re doing enough sequencing and comparing that data with other measures, you can see concerning variants when they first emerge. The earlier you identify a change, the more time you have to study it and, if needed, to tune vaccines and therapeutics to address any changes that have taken place.
There’s no doubt that variants complicate our efforts to bring an end to this pandemic. Even once the worst is behind us, we’ll need to remain vigilant. Fortunately, we know what we need to do to stop them from emerging. For now, the best thing you can do to protect yourself is to follow public health guidelines and get vaccinated as soon as you’re eligible.
Exemplars
We’re finally learning why countries excel at saving lives
A new program is spreading the word about the most successful approaches to health.
Ever since I was a teenager, I’ve tackled every big new problem the same way: by starting off with two questions. I used this technique at Microsoft, and I still use it today. I ask these questions literally every week about COVID-19.
Here they are: Who has dealt with this problem well? And what can we learn from them?
They seem like obvious questions, but sometimes it's surprisingly hard to find the answers—especially when it comes to global health. There are low- and middle-income countries that have made huge leaps in, for example, delivering vaccines or ending malnutrition. But anyone who wants to identify those countries, find out how they did it, and apply the lessons in their own country would have their work cut out for them.
In sports, every coach is able to study the most successful teams and figure out what they’re doing well. There’s no reason that things should be any different when the goal is preventing childhood deaths instead of scoring touchdowns.
That’s why I was eager to be part of a global effort to fill the gap. Over the past three years, health experts and organizations from countries at every income level (including the Gates Foundation) have come together to find out who has made the most progress on certain health problems, identify what made them so successful, and help others put these lessons into action.
The result of all this effort—the Exemplars in Global Health program—launched earlier this year. If you want to know which countries have made the most progress with limited resources, Exemplars is a great place to start.
For now, Exemplars focuses on five areas: under-five mortality; vaccine delivery; the role of community health workers; epidemic preparedness and response; and childhood stunting (the reduction in physical and mental development caused by poor nutrition). The team will be adding other areas, including newborn and maternal mortality, family planning, maternal anemia, and primary health care systems.
The Exemplars team has scoured the world for the best performers and worked with experts in those countries to find out what worked so well. For example, they identified seven countries that have excelled at reducing the number of children who die before their fifth birthday: Bangladesh, Cambodia, Ethiopia, Nepal, Peru, Rwanda, and Senegal. The Exemplars website has a profile of each country, detailing insights from its work that other countries could learn from.
Bangladesh—whose childhood mortality rate dropped 56 percent between 2000 and 2015—used data, research, and testing especially well, and empowered women to make decisions about their children’s health. Peru, which achieved roughly the same decline as Bangladesh, conducted local studies to identify interventions that might suit specific communities. All seven countries built up strong community health systems and made specific efforts to close the equity gap by reaching the poorest people.
Of course, not all lessons can be applied in the same way everywhere. What works in one country may not work exactly the same way in another. And it is not always obvious how to implement big changes in national health systems, which are very complex and require a lot of coordination among the government, the private sector, and non-profits.
Recognizing these challenges, the Exemplars program is much more than a website. There is also a community of global and in-country experts ready to help countries make the case for investing in the most effective programs and figure out how to adapt the lessons to their particular needs. We’re not interested in simply getting the information out there—we want to help drive change.
Our hope is to connect with decisionmakers: people who work in the governments of low- and middle-income countries, at development agencies like America’s USAID and the World Bank, and at organizations that implement health programs. Exemplars is all about figuring out how to improve health care based on evidence of what works. It will help governments use time and money more efficiently—and with the COVID-19 pandemic, there has never been a greater need to get the most impact out of every dollar spent.
I’m grateful to all the people in governments, academia, and non-profits who made the Exemplars program possible. We all started out with one goal in mind: to accelerate the progress in improving health, so that the poorest countries don't have 20 times the childhood death rate of the richest ones. I think Exemplars is a great resource that will spread success stories so even countries with very little money can benefit. And that will, ultimately, save lives.
Innovation vs. the coronavirus
The first modern pandemic (short read)
The scientific advances we need to defeat COVID-19.
This post originally appeared as an opinion piece in the Washington Post. It’s adapted from a longer article, which you can read here.
It’s entirely understandable that the national conversation has turned to a single question: “When can we get back to normal?” The shutdown has caused immeasurable pain in jobs lost, people isolated, and worsening inequity. People are ready to get going again.
Unfortunately, although we have the will, we don’t have the way—not yet. Before the United States and other countries can return to business and life as usual, we will need some innovative new tools that help us detect, treat, and prevent COVID-19.
It begins with testing. We can’t defeat an enemy if we don’t know where it is. To reopen the economy, we need to be testing enough people that we can quickly detect emerging hotspots and intervene early. We don’t want to wait until the hospitals start to fill up and more people die.
Innovation can help us get the numbers up. The current coronavirus tests require that health-care workers perform nasal swabs, which means they have to change their protective gear before every test. But our foundation supported research showing that having patients do the swab themselves produces results that are just as accurate. This self-swab approach is faster and safer, since regulators should be able to approve swabbing at home or in other locations rather than having people risk additional contact.
Another diagnostic test under development would work much like an at-home pregnancy test. You would swab your nose, but instead of sending it into a processing center, you’d put it in a liquid and then pour that liquid onto a strip of paper, which would change color if the virus was present. This test may be available in a few months.
We need one other advance in testing, but it’s social, not technical: consistent standards about who can get tested. If the country doesn’t test the right people—essential workers, people who are symptomatic, and those who have been in contact with someone who tested positive—then we’re wasting a precious resource and potentially missing big reserves of the virus. Asymptomatic people who aren’t in one of those three groups should not be tested until there are enough tests for everyone else.
The second area where we need innovation is contact tracing. Once someone tests positive, public-health officials need to know who else that person might have infected.
For now, the United States can follow Germany’s example: interview everyone who tests positive and use a database to make sure someone follows up with all their contacts. This approach is far from perfect, because it relies on the infected person to report their contacts accurately and requires a lot of staff to follow up with everyone in person. But it would be an improvement over the sporadic way that contact tracing is being done across the United States now.
An even better solution would be the broad, voluntary adoption of digital tools. For example, there are apps that will help you remember where you have been; if you ever test positive, you can review the history or choose to share it with whoever comes to interview you about your contacts. And some people have proposed allowing phones to detect other phones that are near them by using Bluetooth and emitting sounds that humans can’t hear. If someone tested positive, their phone would send a message to the other phones, and their owners could get tested. If most people chose to install this kind of application, it would probably help some.
Naturally, anyone who tests positive will immediately want to know about treatment options. Yet, right now, there is no treatment for COVID-19. Hydroxychloroquine, which works by changing the way the human body reacts to a virus, has received a lot of attention. Our foundation is funding a clinical trial that will give an indication whether it works on COVID-19 by the end of May, and it appears the benefits will be modest at best.
But several more-promising candidates are on the horizon. One involves drawing blood from patients who have recovered from COVID-19, making sure it is free of the coronavirus and other infections, and giving the plasma (and the antibodies it contains) to sick people. Several major companies are working together to see whether this succeeds.
Another type of drug candidate involves identifying the antibodies that are most effective against the novel coronavirus, and then manufacturing them in a lab. If this works, it is not yet clear how many doses could be produced; it depends on how much antibody material is needed per dose. In 2021, manufacturers may be able to make as few as 100,000 treatments or many millions.
If, a year from now, people are going to big public events—such as games or concerts in a stadium—it will be because researchers have discovered an extremely effective treatment that makes everyone feel safe to go out again. Unfortunately, based on the evidence I’ve seen, they’ll likely find a good treatment, but not one that virtually guarantees you’ll recover.
That’s why we need to invest in a fourth area of innovation: making a vaccine. Every additional month that it takes to produce a vaccine is a month in which the economy cannot completely return to normal.
The new approach I’m most excited about is known as an RNA vaccine. (The first COVID-19 vaccine to start human trials is an RNA vaccine.) Unlike a flu shot, which contains fragments of the influenza virus so your immune system can learn to attack them, an RNA vaccine gives your body the genetic code needed to produce viral fragments on its own. When the immune system sees these fragments, it learns how to attack them. An RNA vaccine essentially turns your body into its own vaccine manufacturing unit.
There are at least five other efforts that look promising. But because no one knows which approach will work, a number of them need to be funded so they can all advance at full speed simultaneously.
Even before there’s a safe, effective vaccine, governments need to work out how to distribute it. The countries that provide the funding, the countries where the trials are run, and the ones that are hardest-hit will all have a good case that they should receive priority. Ideally, there would be global agreement about who should get the vaccine first, but given how many competing interests there are, this is unlikely to happen. Whoever solves this problem equitably will have made a major breakthrough.
World War II was the defining moment of my parents’ generation. Similarly, the coronavirus pandemic—the first in a century—will define this era. But there is one big difference between a world war and a pandemic: All of humanity can work together to learn about the disease and develop the capacity to fight it. With the right tools in hand, and smart implementation, we will eventually be able to declare an end to this pandemic—and turn our attention to how to prevent and contain the next one.

A fruitful partnership
How I cemented my friendship with Aliko Dangote
My friend Aliko Dangote and I are working together to fight malnutrition.
Have you ever met someone new and immediately felt like you could talk to them for hours?
That happened the first time I met Aliko Dangote. A couple years ago, he and I ended up going to the same event in New York. A mutual friend suggested that I meet him because he knew we were both super interested in global health. So we made sure to sit next to each other at dinner.
As soon as we shook hands, it was clear we had a ton in common. We both started successful businesses in the late 1970s. For our second act in life, we both chose to start foundations aimed at improving health and education. (Today, the Dangote Foundation is the largest such organization in sub-Saharan Africa.)
More importantly, we both love to geek out over things that make some people’s eyes glaze over, like cement, fertilizer, and iodized salt. Check out this video of Aliko’s recent visit to our foundation’s office in Seattle for proof:
That first meeting sparked the beginning of a fruitful friendship. In 2016, our foundations announced a joint, five-year $100 million commitment to reducing malnutrition in Nigeria.
Malnutrition is the greatest health inequity in the world. It’s responsible for nearly half of all under 5 deaths in Nigeria (and around the world). Even if you survive to adulthood, your chances of dying are much higher, and your quality of life is greatly reduced.
One of the ways our foundations are working together to fight malnutrition is through food fortification. Kids often become malnourished when they don’t get enough micronutrients—vitamins and minerals—to digest their food properly. One way to correct this is by adding micronutrients to the food that families—especially those from low-income households—are purchasing every day.
When you go to a grocery store in the U.S., a lot of food already has this fortification. Think iodized salt, or milk that comes with extra vitamin D and calcium. By introducing additional micronutrients to the food people are already eating, you can improve health without changing any habits. Our foundations are now working together to find other staple foods and condiments that could be used to deliver more micronutrients to more people in Nigeria, like fortified bouillon cubes.
Improving health in Nigeria is critical to making progress in sub-Saharan Africa. The country is home to nearly a quarter of all people living in sub-Saharan Africa, and that population is only going to grow in the future. By solving problems in Nigeria, you can have a huge impact on all of Africa.
Aliko Dangote understands this, and that’s why he’s committed to making progress in his home country. Melinda and I are lucky to have him as a partner (and friend!) in improving health.

Meet the X-shredder
Test-tube mosquitoes might help us beat malaria
Genetic editing might help us wipe out the disease.
It’s Mosquito Week again on the Gates Notes. This year I’m exploring some of the science behind malaria and other mosquito-borne diseases. You can read below about how gene editing could play a key role in eradicating malaria. I’ve also written about amazing advances in tracking the disease and how the parasite is a deadly shapeshifter.
Humans have spent thousands of years inventing new ways to kill mosquitoes. The Romans did it by draining swamps. Today you might have a bug zapper in your back yard. In low- and middle-income countries, it’s common to see people spraying insecticides or setting up sticky traps baited with sugar.
But evolution is smart. It is one-upping us by creating mosquitoes that are harder to kill. In sub-Saharan Africa and parts of South America and southeast Asia, we are seeing an alarming number of mosquitoes that can withstand insecticides.
This is especially problematic for the fight against mosquito-borne diseases like malaria. To eradicate these diseases, we need new tools to complement the ones we already have.
Our foundation is backing a lot of different advances. One that I’m especially excited about is a set of techniques for genetically modifying mosquitoes that could dramatically reduce the number of disease-carrying insects in certain areas.
What is cool about these genetic techniques is how precise they can be. Precision matters because out of more than 3,000 species of mosquitoes, only five are responsible for causing most cases of malaria. Of those, only females spread the disease, because they’re the only ones that bite humans. (They do it when they need extra protein for reproduction. Experts call it “taking a blood meal.”) The males just drink nectar.
The promise of gene editing is that, instead of killing a bunch of mosquitoes indiscriminately, we could eliminate only the dangerous ones in a particular area. That would buy us time to cure all the people there of malaria. Then we could let the mosquito population return without the parasite.
One exciting gene-editing technique is called gene drive. The term covers several different approaches, but the basic idea is to use the CRISPR method to rewrite the usual rules of inheritance. Normally, for any given gene, there’s a 50 percent chance that a parent with that gene will pass it on to a child. (It is competing with one from the other parent, and only one of the two can win.) With gene drive, the odds go up to 100 percent. You give a few mosquitoes an edited gene that inserts—or drives—itself into all their offspring. When those mosquitoes mate with wild mosquitoes, all their children will have the edited gene, and over time it will make its way through the entire population.
Imagine if blue-eyed mosquitoes had only blue-eyed children, no matter what color their partners’ eyes were. Eventually, every mosquito in that population would have blue eyes.
This chart shows you how gene drive eventually spreads a gene throughout an entire population:
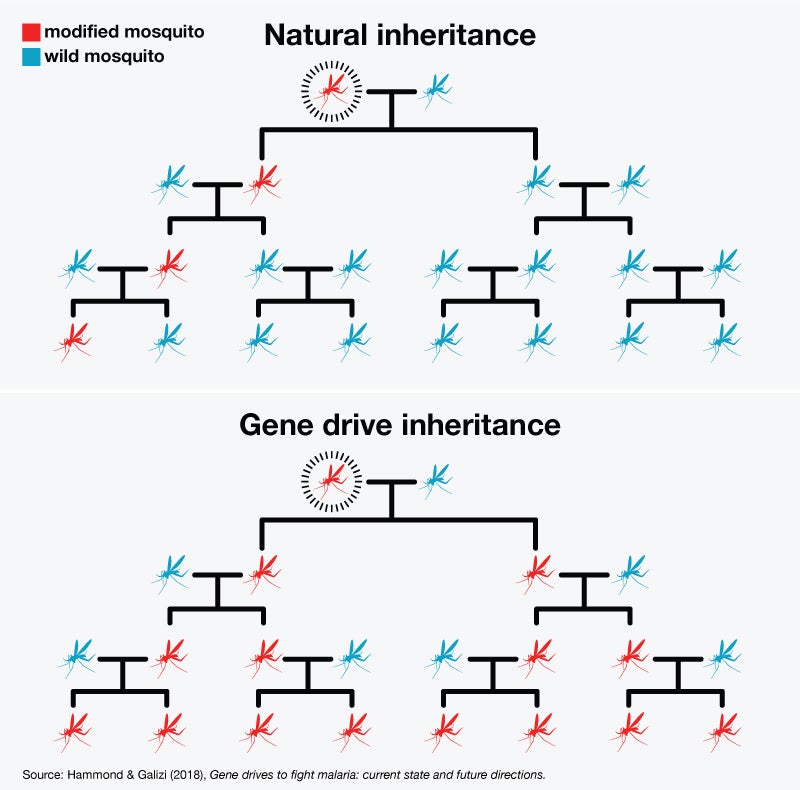
There’s no reason to think gene drive is even feasible in humans, let alone advisable. There are also serious questions surrounding the use of this technology on insects, which I will get to in a moment. But first I want to give you two examples of how it works.
One is the colorfully named X-shredder. As you might remember from biology class, the sex of a mosquito is determined partly by the sex chromosomes it inherits from its parents. Females got one X chromosome from each parent; males got an X from their mother and a Y from their father.
In 2014, scientists at Imperial College London and the Fred Hutchinson center here in Seattle were able to edit a protein in male mosquitoes so that it shreds the X chromosomes in their sperm. As a result, the males pass along mostly Y chromosomes, so most of their offspring will be males. Thanks to gene drive, those offspring will also have the edited protein, so most of their children will be males.
Within a few generations, the male/female ratio gets out of whack, and eventually the species dies off in that area.
Another example involves the doublesex gene, which in mosquitoes works along with the sex chromosome to determine whether an insect turns out male or female. Last year, researchers at Imperial College London found that females with edited doublesex genes develop a mix of male and female organs, including male genitalia and a proboscis that is too flimsy to break human skin. They can’t reproduce, so the population shrinks; and they can’t take a blood meal, so they won’t spread the parasite.
The doublesex edit doesn’t affect males, although thanks to gene drive, they will pass it to their offspring, which is how it keeps spreading through the population.
We know gene-drive technology works in the lab. When the Imperial College researchers put 150 males carrying a copy of the doublesex edit in a small cage with 450 wild-type mosquitoes, the population died off within a few months (about 10 generations). The sex bias edit produced similar results.
The next step is to run tests in larger cages and, eventually, get permission from governments to do them outdoors. We need to understand things like: What’s the impact on the food chain if a certain species of mosquito starts dying off? How many altered insects would we need to introduce? How long do we need the mosquitoes to be gone? Last year, the government of Burkina-Faso agreed to allow the release of sterile, non-gene-drive mosquitoes in the wild so researchers could begin to study some of these questions.
As I mentioned, social and regulatory issues also come into play. For example, because mosquitoes don’t exactly respect national boundaries, neighboring countries will probably need to agree on the rules surrounding the use of gene-editing technology. Policymakers and scientists have been debating these questions in forums like the World Health Organization and the African Union’s development agency, and they are moving toward a consensus.
I think we can have the regulatory approvals in place by 2024 and the first gene-drive mosquitoes ready for use by 2026. Although this technique will never replace the other tools we have for fighting malaria, I’m optimistic that it could become one more important weapon in eradicating the disease.

Disease atlas
These maps could point the way to stopping malaria
We’re using them to maximize scarce resources.
It’s Mosquito Week again on the Gates Notes. This year I’m exploring some of the science behind malaria and other mosquito-borne diseases. You can read below about how maps are revolutionizing the fight against malaria. I’ve also written about how the malaria parasite is a clever shapeshifter and how genetically editing mosquitoes could help us defeat the disease.
Imagine calling the fire department and telling them: “There’s a house burning somewhere in the city!” They ask you for the address or at least some nearby streets, but you’re not sure. Without more specifics, it’s just about impossible for them to help.
For decades, the malaria community has faced a similar problem, but on a national scale. In many of the countries with a lot of malaria, we have had a national estimate of how prevalent it is, but very little reliable information about the breakdown within the country. That means health officials have to distribute bednets across an entire region, hoping to get everyone who might be at risk while also covering people who aren’t.
This problem is especially urgent now. After more than 15 years of steady progress against the disease, the improvement is slowing down. Funding for malaria has also flatlined. If we simply stick with the same tools and the same strategies, progress will stall, and the disease might make a comeback. We need to do more with what we have.
I am happy to report that things are changing, thanks to better data. A combination of new technology and improved systems is helping us target lifesaving interventions in the places where there’s the greatest risk of malaria—making sure that each dollar spent has the biggest possible impact.
I admit that data isn’t as sexy as shapeshifters or the X-shredder. Yet the topic is super-important. It is a big focus for our foundation’s malaria strategy, one of the key things we bring to the table given our interest in technology and innovation. This post will get more in-the-weeds than I usually do on TGN, but if you are as obsessed with malaria as I am, I hope you’ll find it interesting.
Health experts estimate the burden of disease in two ways. One is to use anonymous information collected by health workers. But this information has a lot of gaps and gets aggregated as it moves up the chain from the clinic to the district to the province. This would be roughly equivalent to adding up the cases in every hospital in a U.S. state and only reporting the total. It obscures a ton of local variation, and by the time all the data is processed, the report may be a year out of date.
The other source is surveys. Health workers go out to a community and test a few volunteers for malaria, then repeat this at sites across the country. But this process is expensive and time-consuming, which limits the number of samples a country can take and how often it can take them.
The malaria community is tackling the problem in two ways. A nonprofit called the Malaria Atlas Project (funded by our foundation) started by gathering all the data they could find from every endemic country. They discovered something surprising: Although there were big gaps on the map where we had very little information, overall there was a lot more data than anyone expected.
Using the information they had, along with data on local conditions that affect the spread of malaria (such as the temperature, humidity, and the location of health clinics), MAP started building computer models that give us a much clearer picture of what’s going on.
The results are remarkable. We now have data-rich maps with pixels that are just 5 km square. Instead of blanketing entire regions with bednets and other anti-malaria measures, health officials can target efforts where they will do the most good.
Now comes the next step: getting even better data so we make maps with an even higher resolution. To accomplish this, our foundation and other partners are helping countries strengthen their systems for monitoring disease. In the poorest places, this might mean disaggregating their data and making sure it is accurate and timely. For others, it means equipping health workers with mobile phones or tablets so they can enter the information digitally. More than 60 countries already use the same software to report health data, vastly simplifying the process of collecting and analyzing information.
Below you can see a dramatic example of what the future of mapping looks like. Both are maps of Haiti. The one on the left uses the 5x5 km resolution, built with aggregated data. (Remember, this was already a huge leap forward from national estimates.) The one on the right uses data from individual health facilities to create pixels that are just 1x1 km square. See how much more detailed it is? When you need to maximize scarce resources, this kind of information is invaluable.
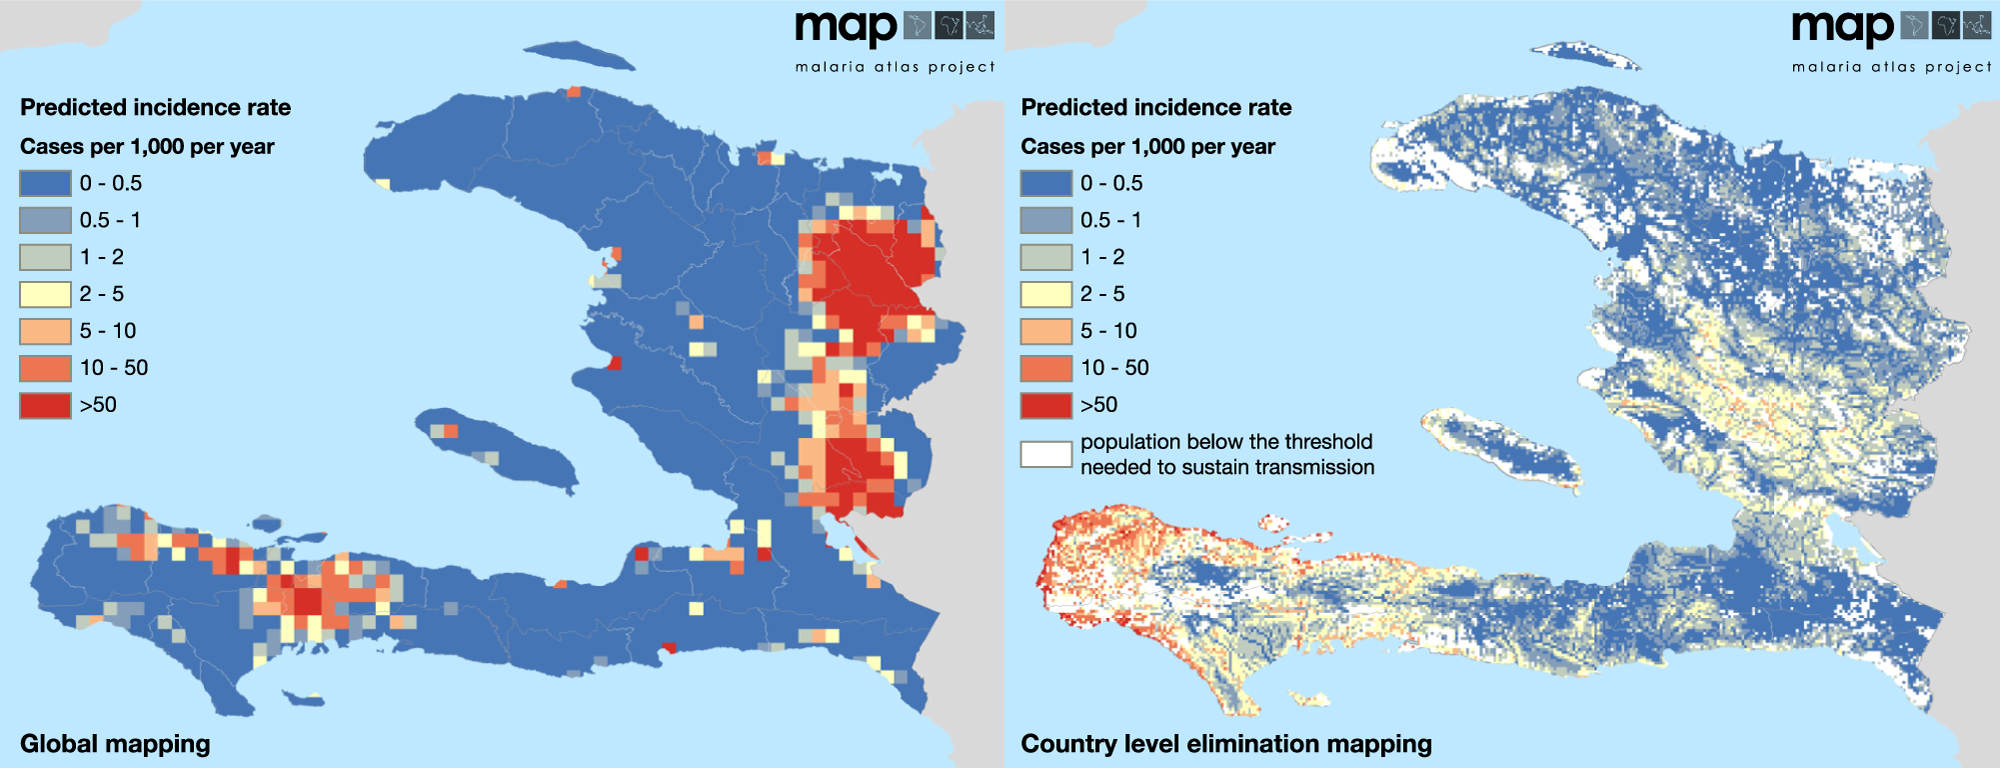
There is more to come. One promising approach uses genetic analysis of the malaria parasite to make the maps even more robust, for example revealing how the disease is transmitted from place to place.
Genetic data is also helping us identify insecticide-resistant mosquitoes and drug-resistant forms of the disease. In Vietnam, health officials recently noticed an alarming spike of cases in one region of the country. Then genetic analysis of the parasite in that region revealed that they were fighting a drug-resistant strain of malaria. They quickly switched to a more effective drug and expect to see the number of cases drop soon.
This kind of work is best done at the local level. So we’re funding programs that help scientists in developing countries do more of this analysis themselves, rather than sending samples off to a lab in the U.S. or Europe. Increasingly, scientists in Senegal, Thailand, and other countries are doing their own analysis, which both speeds up the process and puts local experts in the leading role where they belong.
There is a lot of innovation in the malaria field right now, including work on vaccines and other parasite-killers and a way to fight the disease using test-tube mosquitoes. Better data and malaria maps will help us put all these breakthroughs to their best use, and bring us closer to the day when this disease is gone forever.

Quality of life
What the plow and lab-grown meat tell us about innovation
I was honored to guest curate MIT Technology Review’s 2019 breakthrough technology issue.
I’m a big fan of the MIT Technology Review’s annual list of ten breakthrough technologies—so when they asked me to choose this year’s list, I jumped at the chance. It’s been a lot of fun working on the issue and picking which innovations to include. I think all ten entries will have a significant impact in the years to come, and I’m excited for you to learn more about them.
Here’s the opening essay I wrote for the issue. You can see the full list of breakthrough technologies here.
I was honored when MIT Technology Review invited me to be the first guest curator of its 10 Breakthrough Technologies. Narrowing down the list was difficult. I wanted to choose things that will not only create headlines in 2019 but captured this moment in technological history—which got me thinking how innovation has evolved over time.
My mind went to—of all things—the plow. The plow is an excellent embodiment of the history of innovation. Humans have been using them since 4000 BCE when Mesopotamian farmers used sharpened sticks to aerate soil. We’ve been slowly tinkering with and improving them ever since, and today’s plows are technological marvels.
But what exactly is the purpose of a plow? It’s a tool that creates more: more seeds planted, more crops harvested, more food to go around. In places where nutrition is hard to come by, it’s no exaggeration to say that a plow gives more years of life to people. The plow—like many technologies, both ancient and modern—is about creating more of something and doing it more efficiently, so that more people can benefit.
Contrast that with lab-grown meat, one of the innovations I picked for this year’s TR10 list. Growing animal protein in a lab isn’t about feeding more people. There’s enough livestock to feed the world already, even as demand for meat goes up. Next-generation protein isn’t about creating more—it’s about making meat better. It lets us provide for a growing and wealthier world without contributing to deforestation or emitting methane. It also allows us to enjoy hamburgers without killing any animals.
Put another way, the plow improves our quantity of life, and lab-grown meat improves our quality of life. For most of human history, we’ve put most of our innovative capacity into the former. And our efforts have paid off: worldwide life expectancy jumped from 34 years in 1913, to 60 in 1973, and has reached 71 today.
Because we’re living longer, our focus is starting to shift toward well-being. This transformation is happening slowly. If you divide scientific breakthroughs into these two categories—things that improve quantity of life versus quality of life—the TR10 list from 2009 looks not so different from this year’s. Like most forms of progress, the change is so gradual that it’s hard to perceive. It’s a matter of decades, not years—and I believe we’re only at the midpoint of the transition.
To be clear, I don’t think humanity will stop trying to extend lifespans anytime soon. We’re still far from a world where everyone everywhere lives to old age in perfect health, and it’s going to take a lot of innovation to get us there. Plus, “quantity of life” and “quality of life” are not mutually exclusive ideas. A malaria vaccine would both save lives and make life better for children who might have otherwise been left with developmental delays from the disease.
We’ve reached a point where we’re tackling both ideas at once, and that’s what makes this moment in history so interesting. If I had to predict what the TR10 will look like a few years from now, I bet technologies that alleviate chronic disease will be a big theme. This won’t just include new drugs (although I would love to see new treatments for diseases like Alzheimer’s on the list). These innovations might look like a mechanical glove that helps a person with arthritis maintain flexibility or an app that connects someone experiencing a major depressive episode with the help they need.
If we could look even further out—let’s say the TR10 list 20 years from now—I would hope to see technologies that center almost entirely on well-being. I think the brilliant minds of the future will focus on more metaphysical questions: How do we make people happier? How do we create meaningful connections? How do we help everyone live a fulfilling life?
I would love to see these questions shape the 2039 list, because it would mean that we’ve successfully fought back disease (and dealt with climate change). I can’t imagine a greater sign of progress than that. For now, though, the innovations driving change are a mix of things that extend life and things that make it better. My picks reflect both. Each one gives me a different reason to be optimistic for the future, and I hope they inspire you, too.
My selections include amazing new tools that will one day save lives, from simple blood tests that diagnose cancer to toilets that destroy deadly pathogens. I’m equally excited by how other technologies on the list will improve our lives. Wearable health monitors like the wrist-based EKG will warn heart patients of impending problems, while others let diabetics not only track glucose levels but manage their disease. Advanced nuclear reactors could provide carbon-free, safe, and secure energy to the world.
One of my choices even offers us a peek at a future where society’s primary goal is personal fulfillment. Among many other applications, AI-driven personal agents might one day make your email inbox more manageable—something that sounds trivial until you consider what possibilities open up when you have more free time.
The thirty minutes you used to spend reading emails could be spent doing other things. I know some people would use that time to get more work done—but I hope most would use it for more fulfilling pursuits, like connecting with a friend over coffee, helping your child with her homework, or even volunteering in your community.
That, I think, is a future worth working toward.
The Youngest Continent
Giving the Mandela Lecture
Africa could change faster in the next generation than any continent ever has.
I was 9 years old when Nelson Mandela was sent to prison on Robben Island. As a boy, I learned about him in school, and I remember seeing reports about the anti-Apartheid movement on the evening news. Decades later, I got to meet him and work with him. In person he was even more inspiring than I had imagined. His humility and courage left an impression that I will never forget.
So it was a special honor to be invited to give the Nelson Mandela Lecture in Pretoria, South Africa. I eagerly accepted the invitation and quickly began working on my remarks.
I decided to share my optimism about Africa’s future—to explain why I think the continent has the potential to change faster in the next generation than any continent ever has.
It’s because Africa is the world’s youngest continent, and youth can go hand in hand with a special dynamism. I was 20 years old when Paul Allen and I started Microsoft. The entrepreneurs driving startup booms in Johannesburg, Lagos, and Nairobi are just as young, and the thousands of businesses they’re creating are already changing lives across the continent. The potential will only grow as the digital revolution brings more advances in artificial intelligence and robotics.
But positive change across Africa won’t happen automatically. The real returns will come only if Africans can unleash this talent for innovation in all of the continent’s growing population. That depends on whether all of its young people are given the opportunity to thrive.
It is still an open question, and it is the crux of my speech, which I gave today at the University of Pretoria. It was an honor to give this lecture, and I’m grateful to the Nelson Mandela Foundation and the university for inviting me. You can read my full speech below the video.
Remarks as delivered
Nelson Mandela Annual Lecture
University of Pretoria, South Africa
July 17, 2016
BILL GATES:
Well, thank you. Good evening, ladies and gentlemen. Graça Machel, Professor Ndebele, Vice Chancellor de la Rey, members of the Mamelodi families, friends and dignitaries.
I can’t think of a greater honor than giving a lecture named after Nelson Mandela.
I’m also thrilled that the theme of this lecture this year is “living together.”
It’s truly fitting because in many ways, “living together” was also the theme of Nelson Mandela’s life.
The system he fought against was based on the opposite idea—that people should be kept apart, that our superficial differences are more important than our common humanity.
Today, South Africans are still striving to “live together” in the fullest sense. But you are so much closer to that ideal because Nelson Mandela and so many others believed in the promise of one South Africa.
I was only nine years old when Nelson Mandela was sent to Robben Island. As a boy, I learned about him in school. I remembered seeing reports about the anti-Apartheid movements regularly on the evening news.
The first time I got to speak to him was in 1994 when he called me to help fund South Africa’s election.
I was running Microsoft, and largely focused on software most of the time, but I admired him so much, and I knew the election was historic. So I did what I could to help.
My first trip to Africa had been just the year before that in 1993 when my wife Melinda and I had traveled to East Africa.
The landscape was beautiful, the people were friendly, but the poverty there, which we were seeing for the first time, disturbed us. It also energized us.
Obviously, we knew parts of Africa were poor, but being on the continent turned what had been an abstraction into an injustice we couldn’t ignore.
Melinda and I had always known that we’d give our wealth to philanthropy eventually. But when we were confronted with such glaring inequity, we started thinking about how to take action sooner.
This sense of urgency was further spurred on by another trip in 1997 when I came to Johannesburg for the first time as a representative of Microsoft.
I spent most of the time in the richer part of the city in business meetings, but I also went to the community center in Soweto where Microsoft was donating computers.
My visit to Soweto, which was quite different then than it is now, taught me how much I had to learn about the world outside the comfortable bubble I’d lived in all my life.
As I walked into the community center, I noticed there weren’t any electrical connections. To keep the computer on, the one I was donating, they had rigged up an extension cord connected to a diesel generator outside. I realized the minute I left, the generator would get moved to something more important.
So as I read my remarks about the importance of the technology gap, I knew that it was only a small part of the story. Computers could help people do very important things, and in fact, they are part of how life on the continent can be revolutionized. But computers alone can’t feed disease or cure children. And if they can’t be turned on, they can’t do much at all.
So after that, Melinda and I moved to start our foundation because the cost of waiting had become clear.
Our work is based on the simple idea that every person, no matter where they live, should have the opportunity to lead a healthy and productive life.
We’ve spent the past 15 years learning about the issues and looking for the leverage points where we can do the most to help people seize their opportunity.
It was when I started coming to Africa regularly for the foundation that I got to know Nelson Mandela personally. AIDS was one of the first issues our foundation worked on, and Nelson Mandela was both an advisor and an inspiration.
One thing we talked about was the stigma around AIDS. So I remember 2005 very clearly when his own son died of AIDS. Rather than stay silent about the cause of his son’s death, Nelson Mandela announced it publicly because he knew that stopping the disease required breaking down the walls of fear and shame that surrounded it.
It is important to recall Nelson Mandela’s legacy, and I’m grateful for the opportunity to do so.
But Nelson Mandela was concerned about the future. He believed people could make the future better than the past. And so that’s what I want to focus on for the remainder of my talk.
What can South Africa become? What can Africa become? What can the world become? And what must we do to make it that way?
The Millennium Development Goals adopted by the United Nations in 2000 laid a foundation that enabled the world, including Africa, to achieve extraordinary progress over the last 15 years.
And the Sustainable Development Goals that recently replaced them set even more ambitious targets for creating the better world we all want.
When I talk about progress, I always start with child survival because whether children are living or dying is such a basic indicator of a society’s values.
Since 1990, child mortality in sub-Saharan Africa has been reduced by 54 percent. That means one million fewer children dying each year compared to 25 years ago.
Ten African countries achieved the very ambitious MDG target of reducing child mortality by over two-thirds.
At the same time, the incidence of poverty and malnutrition is down. And though economic growth has slowed in the past few years, it’s been very robust in many African countries for more than a decade.
This is real progress, but the Africa Rising narrative doesn’t tell the whole story about the life on the continent.
First, the progress have been uneven. You know this very well here in South Africa.
In last year’s Nelson Mandela Annual Lecture, the French economist, Thomas Piketty, pointed out that income inequality in South Africa is, quote, “higher than pretty much anywhere else in the world.”
In general, African countries tend to have higher rates of inequality than countries on other continents.And despite healthy average GDP growth in the region, many countries have not yet shared in it. Inequalities exist within countries and between countries.
So until progress belongs to all people everywhere, the real promise of living together will remain elusive.
Second, even with the great progress Africa has made, it still lags behind the rest of the world in most indicators. In sub-Saharan Africa, one in 12 children still die before they turn five. Now, that’s a vast improvement compared to 25 years ago, but African children are still 12 times more likely to die than the average child in the world.
And because rates of poverty and malnutrition aren’t shrinking as fast as the population is growing, the number of people who are poor or malnourished has actually gone up since 1990.
Finally, the progress is fragile. The continent’s two largest economies, here in South Africa and in Nigeria, are facing serious economic challenges. And new threats require attention. The Ebola crisis pointed out weaknesses in many national health systems. The effects of climate change are already being felt among farmers in many countries.
In short, to meet the ambitious goals of the Sustainable Development Goals, Africa needs to do more, do it faster, and make sure everybody benefits. It won’t be easy, but I believe it can be done.
The successes and failures of the past 15 years have generated examples and lessons we can follow. Phenomenal advances in science and technology are expanding the range of solutions available to solve development challenges. And then there is the ingenuity of the African people.
One topic that Nelson Mandela came back to over and over again was the power of youth. He knew what he was talking about because he started his career as a member of the African National Congress Youth League when he was still in his 20s.
Later on, he understood that highlighting the oppression of young people was a powerful way to explain why things must change. There is a universal appeal to the conviction that youth deserve a chance.
I agree with Mandela about young people, and that is one reason I am optimistic about the future of this continent. Demographically, Africa is the world’s youngest continent. And its youth can be the source of a special dynamism.
In the next 35 years, two billion babies will be born in Africa. By 2050, 40 percent of the entire world’s children will live on this continent.
Economists talk about a demographic dividend. When you have more people of working age and fewer dependents for them to take care of, you can generate phenomenal economic growth. Rapid economic growth in East Asia in the 1970s and 1980s was partly driven by the large number of young people moving into their workforce.
But, for me, the most important thing about young people is the way their minds work. Young people are better than old people at driving innovation because they’re not locked in by the limits of the past.
When I started Microsoft at the age of 19, computer science was a young field. We didn’t feel beholden to old notions about what computers could or should do. We dreamed about the next big thing and we scoured the world around us for the ideas and tools that would help us create it.
But it wasn’t just Microsoft. Steve Jobs was 21 when he started Apple. Mark Zuckerberg was only 19 when he started Facebook.
The African entrepreneurs driving startup booms in the Silicon Savannahs from Johannesburg and Cape Town to Lagos and Nairobi are just as young in chronological age, but also in their outlook. The thousands of businesses they’re creating are already changing daily life across the continent.
In a few days, I’ll be meeting with some of these young innovators. People like the 21-year-old who founded Kenya’s first software coding school to provide other young people with computer programming skills. And like the 23-year-old social entrepreneur here in South Africa who manufactures school bags from recycled plastic shopping bags. Besides being highly visible to protect children as they’re walking to school, these school bags sport a small solar panel that charges a lantern during the journey to and from school, providing illumination so students can study at home.
The full returns will come if we can multiply this talent for innovation by the whole of Africa’s growing youth population. That depends on whether Africa’s young people—all of Africa’s young people—are given the opportunity to thrive.
Nelson Mandela said, “Poverty is not natural, it is man made and it can be overcome and eradicated by the actions of human beings.”
We are the human beings that must take action. And we have to decide now because this unique moment won’t last. We must clear away the obstacles that are standing in young people’s way so that they can seize all of their potential.
If young people are sick and malnourished, their bodies and brains will never fully develop. If they are not educated well, their minds will lie dormant. If they do not have access to economic opportunities, they will not be able to achieve their goals.
But if we invest in the right things, if we make sure the basic needs of Africa’s young people are taken care of, then they will have the physical, cognitive, and emotional resources they need to change the future. Life on this continent will improve faster than it ever has. And the inequities that have kept people apart will be erased by broad-based progress that is the very meaning of the words “living together.”
When Melinda and I started our foundation 15 years ago, we asked ourselves: What are the areas of greatest impact? It was clear to us that investing in health was high on the list. When people aren’t healthy, they can’t turn their attention to other priorities. But when health improves, life improves by every measure.
Over the last 15 years, our foundation has invested more than $9 billion in Africa. And we are committed to keep on investing to help Africa.
In the next five years, we will invest another $5 billion.
Some of this money has gone into discovering and developing new and better vaccines and drugs to help prevent infectious disease. We’ve also invested in global partnerships that work closely with countries across the continent to get these solutions to the people who need them most.
We’ve been fortunate to work with amazing partners, and together we’ve seen incredible progress.
For example, the entire continent of Africa has been polio free for two years, which puts us within reach of wiping polio out from the face of the earth forever.
The newest vaccines that protect children from two of the most devastating diseases—pneumonia and diarrhea—are reaching children across Africa at the same time they’re available for children in wealthier countries.
Countries that invest in strong, community-based primary healthcare systems—including Malawi, Ethiopia, and Rwanda—are making great progress reducing child mortality.
Malaria infections and deaths are down significantly thanks to better treatment and prevention tools.
And efforts like the Ouagadougou Partnership in West Africa are helping millions of women get access to contraceptives, which make it easier for them to care for their families.
HIV/AIDS is another area where there’s been good progress. Though it’s a complicated story, and there are still big challenges ahead.
In a few days, I’ll be speaking at the International AIDS Conference in Durban. When the global AIDS community last met there in 2000, only a few thousand Africans were receiving antiretroviral drugs. Today, more than 12 million Africans are on treatment, more than a quarter of them living here in South Africa.
So this is a huge achievement, and millions of lives have been saved. But the rate of new infections remains high. In sub-Saharan Africa, more than 2,000 young people under the age of 24 are infected every single day. The number of young people dying from HIV has increased fourfold since 1990.
We need to get people to get diagnosed, we need people to seek treatment, and people who are on treatment need to be fully adherent.
Along with HIV, we have high rates of tuberculosis, including here in South Africa where TB/HIV co-infection continues to wage a devastating toll.
So we need more creative ways to make testing and treatment accessible and easier to use.
We need to get much more out of existing prevention methods like condoms, voluntary medical male circumcision, and oral anti-HIV medicine.
And we’re going to have to invent new and better preventative solutions like medicines you only have to take once a month or an effective vaccine.
If we don’t act both on today’s treatment and create these tools, the hard-earned gains made against HIV in sub-Saharan Africa over the last 15 years could actually be reversed. Because of the population growth, just doing what we are today is not enough. We need to do more.
Nutrition is another critical area of focus for Africa. Nearly one-third of the continent’s children suffer from malnutrition that stunts their growth and robs them of their physical and cognitive potential. Millions more suffer from micronutrient deficiencies. These are impacts that last a lifetime and impact whole generations of African youth.
African Development Bank President Akin Adesina put it best when he said recently that the greatest contributor to Africa’s economic growth is not physical infrastructure, but gray matter infrastructure, people’s brainpower. The best way to build that infrastructure includes proper nutrition.
Without eliminating malnutrition, we won’t get the great potential that’s there.
We know that when mothers and infants get good nutrition, that breast feeding is a key part of that. We know that certain vitamins and minerals are essential for children.
We have a number of ways to intervene to help nutrition, things like fortified cooking oil, sugar fortified with vitamin A, and sugar and flour enriched with iron, zinc, and vitamin B.
One of the most exciting advances is the breeding of crops so they are naturally more nutritious. For example, when adolescents eat high-iron pearl millet, their likelihood of iron deficiency is reduced six-fold. And just half a cup of biofortified orange sweet potato is all it takes to meet a child’s daily vitamin A needs.
The toll of micronutrient deficiency is huge, but the costs of fighting it are not.
Recent estimates done in Nigeria and Uganda indicate that every dollar invested to reduce stunting returns $17 in greater earning capacity in the workplace.
When children’s bodies and brains are healthy, the next step is an education that helps them develop the knowledge and skills to become productive contributors to society.
Improving education is hard work. I’ve learned this first hand through our foundation’s efforts to create better learning outcomes for primary, secondary, and university students in the United States.
But this hard work is incredibly important. A good education is the best lever we have for giving every young person a chance to make the most of their lives.
In Africa, as in the United States, we need new thinking and new educational tools to make sure that a high-quality education is available to every child.
In Uganda, young innovators at the NGO called Educate! are helping high schools prepare young people for the workplace by teaching students how to start their own business.
And with the high level of mobile phone penetration in Africa, technology using mobile phones to connect to the Internet have the potential to help students build foundational skills while giving teachers better feedback and support.
Globally, the educational technology sector is innovating and growing rapidly and it’s exciting to see new models and tools emerging to meet the needs of educators and students who are not connected to current systems.
At the university level, we need not only to broaden access, we have to also ensure that we have high-quality public universities that will launch the next generation of scientists, entrepreneurs, educators, and government leaders.
South Africa is blessed with some of the best universities in Africa, like the one we’re at today.
For our foundation, we partner with these universities to do our work in health and agricultural research. Maintaining the quality of this country’s higher-education system, while expanding access to more students will not be easy, but it is critical to South Africa’s future.
Other countries in the region will do well to follow South Africa’s example and provide the highest-level university education to the largest number of qualified students.
Healthy, educated young people are eager to make their way in the world. But Africa’s youth must have economic opportunity to channel their energy into progress.
Some of those youths will work in agriculture, where still over half of the workforce toils today.
We need advances to make agriculture far more productive. Today, the seeds that are used are unproductive, the soils are not very good, and so many farmers grow just enough to feed their family.
With climate change leading to more severe weather, doing more of the same will not be good enough.
The key to this is a series of innovation at every step along the way from farm to market.
First, farmers need better tools to avoid disasters and grow surplus. Things like seeds that can tolerate drought, floods, pests, and disease; affordable fertilizers that have the right mix of nutrients to replenish the soil; and easy-to-administer livestock vaccines that can help prevent flocks and herds from being wiped out.
Next, farmers need to be connected to a market where they can buy these inputs at a good price, and sell their surplus, and earn a profit that they can invest not only in their family’s basic needs, but also back into the farm.
This, in turn, will provide employment opportunities both on and off the farm as more prosperous farmers begin to support a range of agribusinesses like seed dealers, trucking companies, and processing plants.
I recently met with a group of young crop breeders, one from Ethiopia, one from Kenya, one from Nigeria, one from Uganda. I really love talking about the science of plant productivity. And in this case, I was amazed at the expertise all of these scientists brought to their work on cassava, a staple crop that provides more than one-third of the calories in many African diets.
Some had ways of improving the nutritional content of cassava. Others were breeding a variety that can resist both of the devastating diseases that are threatening to wipe out the cassava crop.
Our foundation is also working with a young computer scientist from Makerere University who designed a mobile phone app that lets farmers upload a picture of their cassava plants to find out whether it’s infected or not.
These are examples of the kind of innovators who can drive an agricultural transformation across the continent if they have the support they need. For many decades, agriculture has suffered from dramatic underinvestment. Many governments didn’t see the link between their farmers and economic growth.
Now, however, this misconception is gone. And through the Comprehensive African Agricultural Development Program, countries have a framework for transforming agriculture. The investment needs to follow so that young Africans have the means to create the thriving agriculture they envision.
With Africa’s farms as a base, the next step in economic growth is to promote job creation in other sectors. Doing this will require investment in infrastructure including energy.
Seven in 10 Africans lack access to power, which makes it harder to do everything. Harder to get healthcare in a dark clinic. Harder to learn in school when it’s boiling hot. Harder to be productive when you can’t use labor-saving machinery.
Ultimately, a shortage of power, like many African countries—including South Africa—have experienced, is also a drag on economic growth.
Businesses will not invest fully in places where they can’t operate efficiently.
A recent report projected that 500 million Africans won’t have electricity even in 2040. We need to change that.
What Africa needs is what the whole world needs: An energy advance that provides cheap, clean energy for everyone.
I’ve spent a lot of my time in the last two years working on this issue because it’s such an important advance. I’m involved with a group of business people who are collaborating with governments to not only increase energy R&D, but also to vastly increase the private investment in this area.
I get angry when I see that Africa is suffering the worst effects of climate change, although Africans had almost nothing to do with causing this.
The rich countries need to follow through on their commitment to double their energy R&D budgets so that we get the breakthroughs that are applicable globally, and we need to do that urgently.
Africa needs power now. And so there are many pragmatic steps we need to take even in advance of these new inventions.
In parts of Africa, there’s hydro and geothermal sources which are both reliable and renewable that can be exploited. There’s been a lot of work on small-scale grids and the use if micro solar. This approach can provide individuals with electricity for basic purposes, but we also need large-scale power including well-managed electrical grids.
It means organizing the power system so that it’s economic, so that the electronic bills are paid for, and so that the network is reliable 100 percent of the time.
Once we get economic viability for these utilities, then it bootstraps the economy. It allows investments that are job creating.
So there are many challenges that I’ve laid out here: Challenges in health, education, agricultural productivity, energy, and creating enough job opportunities.
These advances only happen in the context of governments that function well enough to enable them. I applaud initiatives like Mo Ibrahim’s Annual Index of African Governments, which looks objectively at multiple measures of government performance in each country on the continent.
Citizens in other regions would be well served by this kind of comprehensive effort to spotlight and spread effective governance.
A lot can be accomplished by focusing on fiscal governance and accountability. Here in South Africa, the government gets strong marks for the budget information it provides to the public.
The International Budget Partnership, an independent monitoring organization, also ranks South Africa highly for its oversight of government spending.
In some countries, individual citizens are leading the way. In Nigeria, 30-year-old Oluseun Onigbinde gave up a career in banking years ago to devote himself full time to pulling back the curtain on the Nigerian federal expenditure.
With savvy use of data and social media, he founded BudgetIT Nigeria, which provides facts and figures the average Nigerian can understand. No doubt, he’s a thorn in the side of some of Nigeria’s elite, but to me he’s an example of what one person can do to make a difference.
Governments have an opportunity not only to learn from what’s been done in the past, but to do things in new ways. One of the exciting prospects is the role they can play in accelerating use of digital technology to leapfrog traditional models and costly infrastructure associated with banking and delivery of government services.
By using mobile phones, tens of millions of people are already storing money digitally and using their phones to make purchases as if they were debit cards.
A good example of this is M-PESA in Kenya. These services don’t just give people a better way to move money around, they give people a place to save cash to fund a startup of a micro enterprise or pay a child’s school fee. They create informal insurance networks of friends and families who can help with unexpected shocks. And they increase the profitability of small businesses by lowering transaction costs, making it easy to order products and supplies, and having greater security of financial assets.
A digital financial connection can also help governments deliver services more efficiently. Studies from India show the government able to save tens of billions a year by connecting households to a digital payment system and automating all government payments.
The early evidence suggests that similar programs in Africa can also yield substantial benefits. For example, recent research in Uganda showed that providing people with digital cash transfers rather than direct food subsidies not only saved the cost of delivery, it also improved nutrition because recipients used the money to purchase a greater diversity of foods and to space out meals as needed.
Governments can accelerate this digital transformation by implementing policies that encourage commercial investment, innovation, and healthy competition.
Countries like Kenya, Tanzania, and Nigeria are already investing in the building blocks of this new digital financial platform. And I believe they’ll see substantial positive returns.
If there’s one thing I’m sure of, it’s this: Africa can achieve the future it aspires to.
That future depends on the people of Africa working together across economic and social strata and across national borders to lay a foundation so that Africa’s young people have the opportunities they deserve.
Recently, I had a meeting with students at Addis Ababa University. I started asking them the kinds of questions you would ask college students in the United States like, “What do you want to do after you graduate? What fields are you thinking of going into?”
They looked at me like I was kind of crazy for asking those questions. Each of them had a plan for their future. They felt their parents had sacrificed for decades so they could go to this university. They weren’t weighing their options, they had come to the university to get specific training, and they were eager to take that training and use it to make their country more prosperous.
They saw themselves as part of a large community with great needs.And they were going to dedicate themselves to serving that community by meeting those needs.
I see that sense of purpose when I come to Africa, and especially when I talk to young Africans. I think it’s a unique asset that people see the need to change and that they want to give back.
The students here believe not only in themselves, they also believe in their countries and the future of the continent. Our priority is to make sure they have the opportunity to turn those beliefs into action because young people with this sense of purpose can make the difference between stagnation and faster progress.
Nelson Mandela said, “Young people are capable, when aroused, of bringing down the towers of oppression and raising the banners of freedom.” But our duty is not merely to arouse, our duty is to invest in these young people, to put in place the basic building blocks so they can build the future.
And our duty is to do it now because the innovations of tomorrow depend on the opportunities available to children today.
I’m sure it’s clear to everyone that these are big and complicated challenges. But it’s just as clear that people with bravery, energy, intellect, passion, and stamina can face big, complicated challenges and overcome them.
There is so much more work to be done to create a future in which we can all live together, but there are also so many people who are eager to get to work.
Let’s do everything within our power right now to help build the future that Nelson Mandela dreamed of and the future that we will achieve together.
Thank you.
Coop Dreams
Why I would raise chickens
I’m excited about the poverty-fighting power of poultry.
If you were living on $2 a day, what would you do to improve your life?
That’s a real question for the nearly 1 billion people living in extreme poverty today. There’s no single right answer, of course, and poverty looks different in different places. But through my work with the foundation, I’ve met many people in poor countries who raise chickens, and I have learned a lot about the ins and outs of owning these birds. (As a city boy from Seattle, I had a lot to learn!) It’s pretty clear to me that just about anyone who’s living in extreme poverty is better off if they have chickens.
In fact, if I were in their shoes, that’s what I would do—I would raise chickens.
Here’s why:
- They are easy and inexpensive to take care of. Many breeds can eat whatever they find on the ground (although it’s better if you can feed them, because they’ll grow faster). Hens need some kind of shelter where they can nest, and as your flock grows, you might want some wood and wire to make a coop. Finally, chickens need a few vaccines. The one that prevents the deadly Newcastle disease costs less than 20 cents.
- They’re a good investment. Suppose a new farmer starts with five hens. One of her neighbors owns a rooster to fertilize the hens’ eggs. After three months, she can have a flock of 40 chicks. Eventually, with a sale price of $5 per chicken—which is typical in West Africa—she can earn more than $1,000 a year, versus the extreme-poverty line of about $700 a year.
- They help keep children healthy. Malnutrition kills more than 3.1 million children a year. Although eating more eggs—which are rich in protein and other nutrients—can help fight malnutrition, many farmers with small flocks find that it’s more economical to let the eggs hatch, sell the chicks, and use the money to buy nutritious food. But if a farmer’s flock is big enough to give her extra eggs, or if she ends up with a few broken ones, she may decide to cook them for her family.
- They empower women. Because chickens are small and typically stay close to home, many cultures regard them as a woman’s animal, in contrast to larger livestock like goats or cows. Women who sell chickens are likely to reinvest the profits in their families. Read more about women and chickens in Melinda’s blog post.
Dr. Batamaka Somé, an anthropologist from Burkina Faso who has worked with our foundation, has spent much of his career studying the economic impact of raising chickens in his home country. In this video he explains why he is so passionate about poultry.
A big bet on chickens
Our foundation is betting on chickens. Alongside partners throughout sub-Saharan Africa, we are working to create sustainable market systems for poultry. It’s especially important for these systems to make sure farmers can buy birds that have been properly vaccinated and are well suited to the local growing conditions. Our goal: to eventually help 30 percent of the rural families in sub-Saharan Africa raise improved breeds of vaccinated chickens, up from just 5 percent now.
When I was growing up, chickens weren’t something you studied, they were something you made silly jokes about. It has been eye-opening for me to learn what a difference they can make in the fight against poverty. It sounds funny, but I mean it when I say that I am excited about chickens.
Ring the alarm
The next epidemic is coming. Here’s how we can make sure we’re ready.
I was honored to be asked to give this year’s Shattuck Lecture.
Four years ago, the world was stunned by the Ebola outbreak in West Africa. Panic broke out all over the globe. Governments scrambled to contain the infection. By the time the last patient tested negative for the disease, the outbreak claimed thousands of lives and caused billions of dollars in economic losses.
The 2014 Ebola outbreak was a stark reminder of how vulnerable our society is to epidemics of infectious diseases. We weren’t ready then, and we’re still not ready now—but we can be. We don’t know when the next epidemic will strike, but I believe we can protect ourselves if we invest in better tools, a more effective early detection system, and a more robust global response system.
When the Massachusetts Medical Society asked me to deliver this year’s Shattuck Lecture, I knew I wanted to talk about epidemic preparedness. I was honored to address their annual meeting earlier today. Here is the full text of my prepared remarks:
BILL GATES:
Thank you, Dr. Drazen, for that kind introduction. It’s an honor to be invited to deliver the Shattuck Lecture.
Most of the speeches I give on global health are about the incredible progress and exciting new tools that are helping the world reduce child mortality and tackle infectious diseases. Thanks to better immunization and other interventions, child mortality has been reduced by more than 50 percent since 1990. We are on the verge of eradicating polio. HIV is no longer a certain death sentence. And half the world is now malaria-free.
So usually, I’m the super-optimist, pointing out that life keeps getting better for most people in the world.
There is one area, though, where the world isn’t making much progress, and that’s pandemic preparedness. This should concern us all, because if history has taught us anything, it’s that there will be another deadly global pandemic.
We can’t predict when. But given the continual emergence of new pathogens, the increasing risk of a bioterror attack, and how connected our world is through air travel, there is a significant probability of a large and lethal, modern-day pandemic occurring in our lifetimes.
Watching Hollywood thrillers, you’d think the world was pretty good at protecting the public from deadly microorganisms. We like to believe that somewhere out there, there is a team ready to spring into action – equipped with the latest and best technologies.
Government agents like Jack Bauer in 24. Harvard professors like Robert Langdon in Inferno. And WHO epidemiologists like Dr. Leonora Orantes in Contagion – who even risked getting kidnapped as she pursued “Patient Zero.”
In the real world, though, the health infrastructure we have for normal times breaks down very rapidly during major infectious disease outbreaks. This is especially true in poor countries. But even in the U.S., our response to a pandemic or widespread bioterror attack would be insufficient.
Several things in the last decade have made me pay closer attention to the risk of future pandemics. One was the outbreak of Swine Flu in 2009. While H1N1 wasn’t as lethal as people initially feared, it showed our inability to track the spread of disease and develop new tools for public health emergencies.
The Ebola epidemic in West Africa four years ago was another wake-up call. As confirmed cases climbed, the death toll mounted, and local health systems collapsed. Again, the world was much too slow to respond.
And, as biological weapons of mass destruction become easier to create in the lab, there is an increasing risk of a bioterror attack.
What the world needs – and what our safety, if not survival, demands – is a coordinated global approach. Specifically, we need better tools, an early detection system, and a global response system.
Today, I’d like to speak with you about some of the advances in tools – vaccines, drugs, and diagnostics – that make me optimistic we can get a leg up on the next pandemic. And I’ll talk about some of the gaps we must address in preparedness and response.
Interestingly, the first Shattuck Lecture – given back in 1890 – focused on a pandemic . . . the Russian flu that struck Massachusetts the previous year. The Russian flu was not especially deadly. But it was the first flu pandemic to spread across continents connected by rail travel – and between continents connected by fast ocean liners. The virus circled the globe in just four months.
But the world was soon in for much worse. Less than 30 years later, the Boston area was one of the first places in the U.S. to feel the deadly effects of the 1918 flu. Military personnel getting off and on ships at the Commonwealth Pier – near where we are meeting today – helped carry the pathogen across the U.S. and back to the battlefields of World War I.
This animation shows how quickly the virus spread across the United States. It took five weeks and killed 675,000 people.
The death toll was so great that average life expectancy in the U.S. for that period dropped by 12 years.
Worldwide, the 1918 flu killed an estimated 50 million people, perhaps more.
We have better tools today than we did a century ago. We have a seasonal flu vaccine, although it’s not always effective, you have to get one every year, and most people in the world never get the shot. We also have antibiotics for secondary infections of bacterial pneumonia.
Despite these advances, this animated simulation by the Institute for Disease Modeling shows what would happen if a highly contagious and lethal airborne pathogen – like the 1918 flu – were to occur today.
Nearly 33 million people worldwide would die in just six months.
That’s the sobering news. The good news is that scientific advances and growing interest on the federal level, in the private sector, and among philanthropic funders makes development of a universal flu vaccine more feasible now than 10 or 20 years ago.
Our foundation is involved in a variety of research partnerships, including a collaboration between the Icahn School of Medicine at Mount Sinai, GlaxoSmithKline, and PATH.
Their work focuses on several vaccine candidates that did well in animal trials and which are now in human trials.
We are also supporting efforts by others, including the National Institute of Allergy and Infectious Diseases, whose vaccine candidate is expected to advance to human safety trials in about a year.
To broaden efforts even further, today we are launching a $12 million Grand Challenge in partnership with the Page family to accelerate the development of a universal flu vaccine. The goal is to encourage bold thinking by the world’s best scientists across disciplines, including those new to the field.
Lucy and Larry Page are also supporting efforts by the Sabin Vaccine Institute to encourage innovative approaches that eliminate the threat of a deadly flu pandemic.
However, the next threat may not be a flu at all. More than likely, it will be an unknown pathogen that we see for the first time during an outbreak, as was the case with SARS, MERS, and other recently-discovered infectious diseases.
The world took an important step last year to begin addressing this risk with the launch of a public-private partnership called the Coalition for Epidemic Preparedness Innovations (CEPI).
With funding commitments of more than $630 million, CEPI’s first order of business is advancing the development of vaccines for three of the priority diseases on the WHO list for public health R&D: Lassa fever, Nipah virus, and Middle East Respiratory Syndrome.
CEPI is also working on rapid-response platforms to produce safe, effective vaccines for a range of infectious diseases – almost as quickly as new threats emerge. Later this year, CEPI will announce grants to several companies working with a variety of technologies – including nucleic acid vaccines, viral vectors, and other innovative approaches. The goal is to be able to develop, test, and release new vaccines in a matter of weeks or months, rather than years.
I’m a big fan of vaccines, but they may not be the answer when we have to respond immediately to rapidly spreading infectious disease pandemics. Not only do vaccines take time to develop and deploy; they also take at least a couple of weeks after the vaccination to generate protective immunity. So, we need to invest in other approaches like antiviral drugs and antibody therapies that can be stockpiled or rapidly manufactured to stop the spread of pandemic diseases or treat people who have been exposed.
Earlier this year, the Shionogi pharmaceutical company received approval in Japan for a new influenza anti-viral, Xofluza This single-dose drug stops flu in its tracks by inhibiting an enzyme that the virus needs to multiply.
And PrEP Biopharm, a development stage biopharmaceutical company, has demonstrated in human challenge studies that pre-activating the innate immune response through intranasal delivery of a double-stranded viral RNA “mimic” can prevent both influenza and rhinovirus.
Since the host’s innate immune response is non-virus specific, such an approach has the potential to offer protection against other types of respiratory viruses as well.
Monoclonal antibody therapies have also made incredible advances in the last couple of decades, leading to several products for cancer and autoimmune diseases. During the Ebola outbreak in West Africa several years ago, researchers were able to identify and test a promising combination of monoclonal antibodies to treat infected patients.
And a growing pipeline of broadly neutralizing antibodies are being discovered in some individuals exposed to infectious diseases. For example, a small percentage of people infected with HIV develop antibodies with high potency and breadth of coverage sufficient to protect against many strains of the virus. The same is true for some people infected with the flu.
Different sets or cocktails of these exceptional antibodies may protect against a pandemic strain of a virus even if it has genetically evolved. It is conceivable that we could create libraries of these antibodies, produce manufacturable seed stocks, and have them ready for immediate use in an outbreak—or ready to scale up manufacturing if a pandemic ensues. If we can learn how to use RNA or DNA gene delivery effectively, we may not need to make the antibodies at all.
Rapid diagnosis is also critical, especially at the beginning of an outbreak when quarantine, treatment, and other public health measures are most effective. To that end, researchers at the Broad Institute and at UC-Berkeley have developed a highly-sensitive point-of-care diagnostic test that harnesses the powerful genetic engineering technology known as CRISPR.
But instead of using CRISPR to edit DNA, they have programmed an associated protein called Cas13 to hunt for specific pieces of RNA. When Cas13 locates the relevant genetic sequence, it releases a signal molecule that indicates the presence or absence of the target.
In a paper published yesterday in the journal, Science, the Broad researchers highlighted the field-use potential of this new diagnostic. Using paper strips similar to a pregnancy test – and with minimal sample processing – the diagnostic can check a patient’s blood, saliva, or urine for evidence of a pathogen.
What’s more, it can test for multiple pathogens at once. It could, for example, identify if someone is infected with Zika or dengue virus, which have similar symptoms.
There are also some interesting advances that leverage the power of computing to help predict where pandemics are likely to emerge and model different approaches to preventing or containing them.
Over the last few years, researchers at the Institute for Health Metrics and Evaluation at the University of Washington have developed a sophisticated computer model that combines data from dozens of sources with geospatial mapping to predict the pandemic risk of infectious diseases.
They recently looked at the pandemic potential of four viral hemorrhagic fevers in Africa – including Ebola. Their analysis confirmed that Guéckédouprefecture in Guinea – where the West African Ebola outbreak originated – was indeed one of the most likely places where an individual Ebola case could lead to a widespread epidemic.
The research also pinpointed dozens of other African communities that are at high risk of outbreaks of hemorrhagic fevers.
Meanwhile, researchers at the Institute for Disease Modeling are pushing the boundaries of computational epidemiology to provide a deeper understanding of both the spread of infectious diseases and the effectiveness of different control and eradication strategies.
In the effort to eliminate malaria, for example, IDM is combining surveillance data with computational modeling to tailor antimalarial efforts to unique local conditions. They are also using quantitative analysis and modeling to evaluate various control strategies for HIV, TB, and to eradicate polio. This kind of research could provide valuable information to help predict disease transmission and identify prevention measures and intervention tactics for epidemics and pandemics.
At the Munich Security Conference last year, I asked world leaders to imagine that somewhere in the world, there is a weapon that exists – or that could emerge – that is capable of killing millions of people, bringing economies to a standstill, and casting nations into chaos.
If this were a military threat, the response – of course – would be that we should do everything possible to develop countermeasures. In the case of biological threats, that sense of urgency is lacking.
The world needs to prepare for pandemics the way the military prepares for war. This includes simulations and other preparedness exercises so we can better understand how diseases will spread and how to deal with things like quarantine and communications to minimize panic.
We need better coordination with military forces to ensure we can draw on their mobilization capacity to transport people, equipment, and supplies on a mass scale.
We need a reserve corps of trained personnel and volunteers, ready to go at a moment’s notice. And we need manufacturing and indemnification agreements in place with pharmaceutical companies –with expedited review processes for government approval of new treatments.
Last month, Congress directed the administration to come up with a comprehensive plan to strengthen global health security – here and abroad. This could be an important first step if the White House and Congress use the opportunity to articulate and embrace a leadership role for the U.S. in global health security.
No other country has the depth of scientific or technical expertise that we do – drawing on the resources of institutions like the NIH, the CDC, and advanced research organizations like DARPA and BARDA.
Our biopharmaceutical industry is the global leader in biomedical innovation. And, on the world stage, the U.S. is an influential member of international forums like the UN, the WHO, the G7, and the G20.
The point is that the U.S. can and should play a leadership role in creating the kind of pandemic preparedness and response system the world needs.
As I said at the start, I’m fundamentally an optimist, and that gives me hope that we can get prepared for the next big pandemic.
The global community eradicated smallpox, a disease that killed an estimated 300 million people in the 20th century alone.
We are on the verge of eradicating polio, a disease that 30 years ago was endemic in 125 countries and that paralyzed or killed 350,000 people a year.
And today, nearly 21 million people are receiving life-saving HIV treatment, thanks primarily to the support of the world community.
America’s global HIV initiative, PEPFAR, was the catalyst for world action on the AIDS crisis. It’s an example of the kind of leadership we need from the U.S. on a broader effort to make the world safer from other infectious disease threats. With strong bipartisan support, PEPFAR has saved millions of lives and shown that national governments can work together to address pandemics.
Somewhere in the history of these collective efforts is a roadmap to create a comprehensive pandemic preparedness and response system.
We must find it and follow it because lives – in numbers too great to comprehend – depend on it.
Thank you for the opportunity to address you today.
Buzz Kill
Could this be the first country in sub-Saharan Africa to defeat malaria?
Swaziland’s success fighting malaria can teach the world valuable lessons.
In the tiny African kingdom of Swaziland*, one of the most effective tools in the fight against malaria is a telephone number: 977.
When someone tests positive for the mosquito-borne disease at a Swazi clinic, a nurse immediately dials those three digits to report the case to the country’s national emergency response center. The call triggers a text message to the national malaria program team, which dispatches investigators—armed with computer tablets that have built-in satellite maps and GPS software—to interview the patient and test all people living within a one-kilometer radius of their home. A separate team is called in to reapply insecticide to the walls of homes in the community to help protect other families from infection.
Such vigilance is one of the reasons why Swaziland may become the first malaria-free country in sub-Saharan Africa, where most malaria deaths occur.
Swaziland’s well-coordinated malaria program—including a robust surveillance and control system—has helped reduce the number of cases in the country by more than 90 percent since 2002. Now, Swaziland aims to eliminate malaria entirely within its borders by 2020.
Swaziland’s bold goal is evidence of the incredible progress the world has made against malaria. Between 2000 and 2015, the combination of increased donor investment, strengthened political commitment, and new tools (including artemisinin combination therapies, rapid diagnostic tests, indoor residual spraying, and insecticide-treated bed nets), led to a 60 percent decline in malaria deaths.
At the same time, the difficulties Swaziland has experienced trying to become malaria free are a sobering reminder of the challenges the world faces to reach its goal of eradicating the disease. While the number of malaria cases in Swaziland has fallen to just a few hundred cases each year, tackling those final cases is more difficult than anyone imagined. Swaziland thought it would eliminate the disease by the end of 2015, and again by the end of 2017, but each time fell short of its goal. Last year, Swaziland saw its number of malaria cases rise sharply.
Globally, progress in the malaria fight has stalled. Further progress is in peril given the plateauing funding levels which make it impossible to fill remaining gaps in prevention and treatment of malaria and address the challenges of drug and insecticide resistance. After years of dramatic declines in malaria cases and deaths, the world is starting to lose ground. In 2017, the World Malaria Report showed that for the first time in years the number of malaria cases went up.
These setbacks should not lead to despair. They should serve as a wake-up call. As I told health officials at the Malaria Summit in London last week, the world needs a new strategy to meet the challenges ahead. That means developing innovations that will keep driving down malaria cases and malaria deaths, while tailoring interventions to address the specific needs of a country or region.
Swaziland is a good example of how countries can adapt their malaria control strategies to meet their unique circumstances. One of Swaziland’s biggest challenges is the cross-border movement of people infected with the disease from outside the country. Mozambique, Swaziland’s next-door neighbor, has one of the highest malaria burdens in the world. Workers from Mozambique may come into Swaziland with malaria. And when Swazis go to Mozambique, they sometimes return with the disease, which can then be passed on to their neighbors. Unpredictable weather also poses a challenge. The sudden spike of new cases last year was driven by heavier rainfall in the region, resulting in more mosquito breeding.
Swaziland and Mozambique are part of the Elimination 8 regional malaria elimination effort, which aims to wipe out malaria from eight countries in southern Africa. Last year, as part of that effort, Swaziland and Mozambique set up malaria posts along their border. As people go back and forth between the two countries, they are offered malaria tests and treatment to help prevent the importation of new cases. Since the posts were set up last year, thousands of people have been tested and treated and the national malaria program is optimistic that the number of cases will fall this year as a result.
At the same time, Swaziland remains committed to the painstaking work of investigating every new malaria case and responding swiftly to reduce the chance the disease will spread. The country also organized intensive media campaigns to warn residents and travelers of the danger of malaria and teach them how to protect themselves. Malaria diagnosis and treatment are free to everyone in private and public clinics.
I look forward to hearing more about Swaziland’s progress in the months ahead. If successful eliminating malaria within its borders, Swaziland can achieve a major milestone toward a goal once thought impossible—making Africa malaria free. I hope to see many more countries follow its lead.
* Just before I posted this, King Mswati III of Swaziland announced that the name of the country was changing to the Kingdom of eSwatini. In order to avoid confusion, I’ve used Swaziland in this post.
Out for blood
This animal kills more people in a day than sharks do in a century
I’m bringing back Mosquito Week on the Gates Notes.
Mosquitoes keep me up at night.
If you ask someone about what things scare people the most, there’s a list of usual suspects: shark attacks, heights, enclosed spaces, etc. Mosquitoes usually don’t make the cut—but they frighten me more than almost anything else.
This fear might be a bit irrational in Seattle, where I live. Our climate is too mild for the types of mosquitoes that harbor serious diseases. In other parts of the world, however, families have good reason to be afraid. Mosquitoes and the diseases they carry kill more than half a million people every year. Consider this mind-blowing statistic:
Of all the illnesses mosquitoes spread, malaria is the worst by far. More than 200 million people suffer from it every year, and a child dies from malaria every other minute of every day. If you survive, it can leave you vulnerable to other debilitating diseases and chronic anemia. It’s an awful, painful disease (I wrote about what it feels like to have malaria a couple years ago).
Melinda and I encounter a lot of suffering through our work, but one of the worst things I’ve ever seen is a child having seizures from cerebral malaria in Tanzania. I will never forget watching his small body twist in agony, as his parents waited to find out if he would survive. I wouldn’t wish that experience on anyone.
So why exactly are people more afraid of sharks than mosquitoes? The late Hans Rosling would argue that humans are hardwired to fear things that cause us physical harm. This instinct is practical if you live in poverty (on level 1 or 2), where an animal attack is more likely to kill you. But if you can afford life-saving healthcare, it can distort your perception of how significant a threat really is.
Even if you know that you’re 50,000 times more likely to get killed by a mosquito than a shark, human instinct wins out. A photo of a shark attack victim on the evening news evokes a visceral reaction, because the threat is obvious. A picture of a malaria victim in a hospital ward doesn’t trigger our fear instinct in the same way.
Despite this, I’m determined to spread the word about mosquitoes—which is why I’m bringing back Mosquito Week here on Gates Notes.
Everything I’m posting this week is dedicated to my least favorite pest. You can read some good news about a country that hopes to eliminate malaria by 2020. You can see how the bed nets the Mozambique Ministry of Health and World Vision distributed last year on behalf of the Gates Notes Insider community are making a difference. I’m going to be talking about mosquitoes on my social channels all week, and I hope you’ll join the conversation.
As long as Hollywood keeps making blockbusters about sharks, I’ll keep talking about why everyone should be more scared of a tiny bug than a 3,000-pound carnivore. Jaws is nothing compared with the flying terror that is a mosquito.
Covered
Net impact
Learn how a new, long-lasting mosquito net is helping save lives in the southern African country of Mozambique.
The world is making incredible progress against malaria. New innovations—including more effective drugs for treatment, rapid diagnostic tests, and better insecticides—have helped prevent more than 600 million cases of malaria and saved 6.8 million lives between 2000 and 2015. One new tool that helps protect families in Africa is a long-lasting type of bed net. Learn more about the impact these bed nets are having in the southern African country of Mozambique.
Fourteen-month-old Judite Luis battles malaria (and complications from malnutrition) at Chicuque Rural Hospital in Inhambane, Mozambique with her mother, Adozinda Augusta, at her side. Malaria is the leading cause of death among children under 5 in Mozambique. Judite died the day after this photo was taken.
A boy points out the holes in an old mosquito net used in his home. While the older generation of bed nets helped protect families from malaria in Mozambique, they had some downsides. They needed to be soaked in insecticide every six months and didn’t stand up to repeated washings when they got dirty, leading to tears that mosquitoes could fly through.

In November, thousands of families in Inhambane, Mozambique lined up to receive long-lasting insecticidal mosquito nets from the Mozambique Ministry of Health’s National Malaria Control Program and World Vision partnership. The nets protect people from mosquitoes for three years and can even be washed when they get dirty. (The bed net donation was made possible, in part, by the participation of Gates Notes readers in a bed net giveaway campaign last year. Thanks for your help!)

Clayton Pedro Albert, age 6, and his 11-month-old sister, Sharmila, go to bed under one of the long-lasting insecticidal nets. “There is no malaria in this house this year. Last year, it was so many times,” said Carolina Alberto, their mother. Across Mozambique, World Vision, in partnership with the Ministry of Health, has distributed more than 21 million bed nets. Ensuring families use their new bed nets is critical for controlling malaria. World Vision follows up with households to show families how to hang and care for their nets and remind them of the importance of sleeping under them every night.

Silvina Jorge Mahoche and her daughter, Celineza Mahoche, share their new insecticidal net. The Mahoche family has had malaria more times than they can remember. What they don’t forget are the painful symptoms: “A fever, chills, joint pain, headaches, and vomiting,” Silvina said. Since receiving the net last year, no one in the family has been sick from malaria.

Villagers return home after receiving new mosquito nets. Ensuring communities have universal coverage of nets and follow up to ensure appropriate use is critical to achieving malaria control and elimination. Some mosquitoes are now developing resistance to the pyrethroid insecticides used in bed nets—so researchers are working on next generation nets that use combinations of insecticides and appear effective against all mosquitoes, including insecticide-resistant ones. Much more work needs to be done to eliminate malaria in Africa, but continued innovation in bed nets and other tools will ensure that the world will continue to make progress against this deadly disease.

Beans & rice
Lunchtime in Africa
More than a meal: The humblest of school lunches can transform lives and entire nations.
Could a plate of beans and rice help change the world?
Last month, I squeezed into a child’s-size desk to have lunch with a class of primary school students in Tanzania. I was there to join them for the launch of their new school lunch program. On the menu: red beans cooked with tomatoes and onions served over rice.
You can join us in this video. (We’ve saved a plate for you.)
Lunch was delicious. More than that, it filled me with hope. Watching my 67 lunchmates—most of them 8-year-olds—dig into their piles of rice and beans, I was reminded that even the humblest of meals can have a far-reaching impact not just for individuals, but entire nations.
Here’s why: This month, as children around the globe begin another school year, millions of students in the poorest countries (and even some in wealthy countries) will turn up for classes on an empty stomach, making it difficult for them to learn and continue their schooling. According to the World Food Program, 66 million primary school-age children attend classes hungry across the developing world, with 23 million in Africa alone.
A school lunch program, however, can make a world of difference. It encourages kids to come to school, gives them energy to learn, and improves their overall health. The benefits don’t stop at the classroom door. Economic modelling shows that every US$1 invested in school meals programs brings a US$3-10 economic return from improved health, education and productivity. And a new research paper by the World Food Program found that school meals can contribute to help achieving the Global Goals, including ending hunger, quality education, and gender equality and indirectly to reducing poverty, contributing to the economy, and helping to reduce inequality.
Not too bad for a plate of beans and rice.
Stay tuned for more stories from my trip to Tanzania in the months ahead.
Loaf actually
The bread lab in my backyard
These Washington state researchers are doing cool things with baked goods.
I’ve been to lots of labs, but until recently I had never seen one that was centered on a full working kitchen. Last month I got my chance when I visited the Bread Lab, located a couple hours north of my hometown Seattle. It brings together local farmers, expert plant breeders, and world-class bakers with the goal of producing wheat for baked goods that are both delicious and good for you.
I could smell the baking bread the minute I walked in the door. Canisters of flour from different types of wheat lined the walls. Bakers were pulling warm rolls out of large commercial ovens. In the corner there was a farinograph, a machine that measures the strength of dough.
It was all very impressive. But deep down, I was a little skeptical: How would the breads actually taste? The Bread Lab emphasizes using whole grains, and not just wheat—lab director Steve Jones loves buckwheat because it’s unusually high in lysine and other nutrients. Although eating whole-grain bread might make me feel virtuous, in my experience it just never seems to taste as good as white bread.
But I got to sample lots of their baked goods, and I’m happy to report that everything I ate was delicious—even the croissants, which are especially hard to get right when you’re using whole grains.
The lab is part of Washington State University, and although most of their work is with rich-world companies including Clif Bar, La Brea Bakery, and Chipotle, they are also applying their expertise to the problem of malnutrition in poorer countries. For example, I met a Pakistani Ph.D. student, Farah Ahmad, who’s looking at ways to make chapatis, cookies, and other foods from her home country using approaches developed by the Bread Lab.
Here’s a video from my visit:
Beasts of the southern tropics
What cowboys can teach us about feeding the world
Could a cattle ranch in Australia improve food security in Africa?
Beyond breeding, Wylarah Station uses technology to ensure that their herds receive proper nutrition. I was surprised to see their ranch hands use smart watches to track how much the cows are drinking.
In the past someone had to manually inspect all of the water troughs scattered across the ranch, driving hundreds of kilometers every day. Now they receive a notification on their watch when a sensor detects that a tank needs attention. The whole operation was a far cry from the John Wayne cowboy movies I used to watch as a kid.
Not all of AACo’s innovative approaches could work in the poor world. It’s unlikely that every farmer in Africa will be wearing a smart watch anytime soon (if ever). But as smartphone usage continues to grow across the continent, it’s easy to imagine a future where Africans might use an app to order the perfect bull DNA or make sure their cattle are eating enough—something that an African ICT company called iCow is promoting in Kenya, Ethiopia, and Tanzania with help from our foundation.
Farmers across sub-Saharan Africa are already raising cattle—beef and dairy—in massive numbers. Ethiopia, Sudan, and Tanzania are among the world’s top 15 cattle producing countries. While there are legitimate questions about whether the world can meet its appetite for animal products without destroying the environment, it’s a fact that many poor people rely on cattle for both nutrition and income. I believe they should be able to raise cattle as efficiently as farmers in rich countries do.
I’m optimistic that technology can improve the quality of African cattle. A typical dairy cow in the United States produces nearly 30 liters of milk every day. Compare that to your average cow in Ethiopia, which produces just 1.69 liters of milk a day. If you want to increase milk yield, you can’t just take a high-producing Holstein cow from Wisconsin and drop it into the tropical savannah. Unlike indigenous breeds, temperate cattle have no natural resistance to tropical diseases—like trypanosomiasis, or sleeping sickness—and they struggle to get enough nutrition from local food sources.
Instead, you could breed cattle that will flourish in the local climate. That means using artificial insemination—like the process they use at Wylarah Station—to crossbreed a native female cow (with her built-in resilience to tropical heat and diseases) with a bull from a genetic line that produces lots of milk.
Our foundation is already tackling this, but AACo’s technology could make the process much more precise than it is today. One of the things that amazed me most during my visit was how much they know about the ancestry of their cattle. The animals on their ranch have a more detailed family history than most people do. If farmers in Africa were equipped with the same level of knowledge, they could handpick the best possible cow parents and breed a better calf. But that leads us to another problem.
Because they lack adequate storage, most African farmers rely on artificial insemination stations (yes, that’s what they’re really called) to provide sperm samples. Depending on how far a farmer lives from a station, the sample can sometimes heat up too much and effectively die before it is delivered. Many farmers decide not to take the risk. Instead they get their cows pregnant the old-fashioned way, which makes it harder to control genetic integrity and can lead to calves that are less resilient or produce less milk.
AACo is looking into methods that extend the viability of sperm samples. Similar technology is currently used in Europe to improve the success rate of fertilization, but it hasn’t been tried yet with tropical cattle. If successful, it could double the amount of time a sample can survive outside of storage and make it easier for more farmers across Africa to use artificial insemination.
Beyond breeding, Wylarah Station uses technology to ensure that their herds receive proper nutrition. I was surprised to see their ranch hands use smart watches to track how much the cows are drinking.
In the past someone had to manually inspect all of the water troughs scattered across the ranch, driving hundreds of kilometers every day. Now they receive a notification on their watch when a sensor detects that a tank needs attention. The whole operation was a far cry from the John Wayne cowboy movies I used to watch as a kid.
Not all of AACo’s innovative approaches could work in the poor world. It’s unlikely that every farmer in Africa will be wearing a smart watch anytime soon (if ever). But as smartphone usage continues to grow across the continent, it’s easy to imagine a future where Africans might use an app to order the perfect bull DNA or make sure their cattle are eating enough—something that an African ICT company called iCow is promoting in Kenya, Ethiopia, and Tanzania with help from our foundation.
There’s a lot we can learn from Wylarah Ranch about how to more efficiently raise cattle, but I can’t ignore the big question: should we rely on animals for food at all? Eating too much meat contributes to higher levels of obesity and heart disease, and raising animals contributes to climate change. That’s why I’ve invested in companies working on meat substitutes, which could one day eliminate the need to raise and slaughters animals entirely.
Although it might be possible to get people in richer countries to eat less, we can’t expect people in low income countries to follow suit. When I went vegetarian for a year in my late 20s, all I had to do to get my daily serving of protein was buy a can of beans or a container of tofu at the grocery store. It’s not so easy for families in poor communities to get the nutrition they need.
For them, meat and dairy are a great source of high-quality proteins that help children fully develop mentally and physically. Just 20 grams of animal protein a day can combat malnutrition, which is why our foundation’s nutrition strategy wants to get more meat, dairy, and eggs into the diets of children in Africa. Cattle are also a huge economic driver in some parts of Africa. In Ethiopia alone, cattle account for 45 percent of their agricultural GDP. In addition, livestock can actually contribute to ecosystems by stimulating pasture growth, enhancing biodiversity, and recycling energy and nutrients.
As more people in poor countries move into the middle class, they will likely eat more beef and drink more milk. But we can mitigate the impact of that growth on the environment by increasing production from the cows they already have. The cowboys of Wylarah Ranch have mastered the art of raising tropical cattle. I don’t know yet how African farmers can benefit from their expertise—our foundation is just starting to dig into this—but I’m excited about the possibilities.
Safety first
Foreign aid keeps Americans safe
The strategic case for fighting disease and poverty abroad.
You may have seen in the news that elected officials in Washington, D.C., are working on next year’s federal budget. One of the ideas that has been floated is to make deep cuts in foreign aid—the investments that America makes to help other countries fight poverty and disease.
That would be a big mistake.
For one thing, these programs amount to less than 1 percent of the federal budget. For anyone worried about the budget deficit, cutting 1 percent will not make a dent.
More importantly, these programs give American taxpayers a phenomenal return on investment, one of the best anywhere in government. They do this in three ways:
- Making Americans safer and the world more stable
- Creating jobs at home and promote trading partners that will buy American goods
- Saving lives and building up health systems so other countries can take better care of their people
Together these three points make what you might call the strategic case for aid—the argument that aid helps the countries that give it as well as those that receive it.
To be honest, the strategic case is not what prompted Melinda and me to get involved in this work more than 17 years ago. We were moved by what you could call the moral case: the idea that it is terribly unjust that people in poor countries—especially children—die of diseases that can be prevented. That is still the main thing that drives us today. But over the years we have come to see the compelling strategic case too. And we have found that people often support aid who aren’t convinced by the moral argument but are by the strategic one.
In this post I want to focus on point #1 above. I’ll come back to #2 and #3 in subsequent posts.
Let’s look at how promoting health and development keeps Americans safe.
Preparing for the next epidemicYou may remember the Ebola epidemic of 2014–16. It killed more than 11,000 people in three West African countries. Each of those deaths was a tragedy, but the epidemic could have been far worse. If it had spread to neighboring Nigeria, home to more than 180 million people and a busy international travel hub with daily flights to the world’s capitals, it would have been very hard to contain. It could have easily jumped the Atlantic and infected Americans, and spread throughout Europe or Asia.
Why didn’t that happen? One key reason is that a number of health workers were stationed in Nigeria as part of the global campaign to stamp out polio. As the Ebola epidemic took hold, they were quickly reassigned from polio to Ebola. They already had a system in place for identifying possible cases, tracking them, and reporting the data to people organizing the response. They helped contain the disease and keep it from spreading farther than it did.
The polio eradication program helped stop Ebola and saved countless people, including Americans. Its biggest public funder? The United States government.
In addition, Ebola may have been only a preview of what is to come. The next epidemic—say, a virulent flu as bad as the Spanish Flu of 1918—could be far worse. Epidemiologists estimate it could kill 30 million people, more than three times the population of New York City.
Funding from the U.S. government helps keep that from happening. It helps other countries strengthen their health systems so they can identify dangerous diseases and contain them before they get out of control.
It is no accident that the Ebola epidemic hit hardest in three countries—Guinea, Sierra Leone, and Liberia—with especially weak health systems. Helping them improve makes it more likely that we can prevent a worldwide epidemic that destabilizes entire regions of the world and kills tens of millions of people.
Stabilizing vulnerable countriesPreventing pandemics is one specific way that U.S. funding makes Americans safer. There is also a broader point here: by fighting poverty and disease, we make the world a more stable place.
For example, both evidence and common sense tell us that when people don’t have reliable food supplies, they will pick up and move someplace else—becoming migrants or refugees—and that leads to more instability. Look at the countries with the least reliable food supplies in the world: Sudan, South Sudan, Eritrea, Burundi. Each of them is either at war or recently emerged from conflict.
Syria is another tragic example. In 2007, the country suffered the worst drought in its history. More than 1 million people fled rural areas for the cities, where they hoped to find food. This migration stoked political tensions and created the foundation for the horrific civil war that continues today. Of course that war has many causes, and not every drought-stricken country will become another Syria. But it is clear that the world is not a safer place when more people are going hungry—and that when we strengthen food and farming systems, we tackle some of the root causes of migration and instability.
Improving health is another way to make countries more secure. One of my favorite all-time examples is PEPFAR, the program America launched in 2003 to stop the spread of AIDS. Today it provides life-saving medicine for more than 11 million people living with HIV in some of the world’s poorest countries. Those 11 million people are teachers, health-care workers, and police officers—people who build strong, self-sufficient societies. So it should not be surprising that in countries where PEPFAR has a presence, political instability fell by 40 percent between 2004 and 2013. In non-PEPFAR countries, it dropped only 3 percent. And the PEPFAR countries grew three times faster.
Shoring up national securityAmerican military leaders understand that fighting poverty and disease is part of a smart national-security strategy. It was true after World War II, when the United States invented modern development assistance to combat instability in Europe and prevent a third World War, and it’s true today. The more stable poor countries are, the lower the odds that America will need to intervene in them.
More than 120 retired generals and admirals recently wrote a letter to Congress arguing that U.S. aid programs “are critical to preventing conflict and reducing the need to put our men and women in uniform in harm’s way.” While he was the head of U.S. Central Command, overseeing American operations in Syria, Pakistan, Afghanistan, and elsewhere, Secretary of Defense James Mattis said: “If you don’t fully fund the State Department”—which houses many aid programs—“then I need to buy more ammunition.”
Aid is an important part of our broad diplomatic and security relationships. Out of 135 countries that receive some health or development aid from the United States, we have bilateral defense agreements with 131 of them.
These are some of the arguments I have been making in Washington on behalf of American aid. In future posts I will explain how aid not only keeps Americans safe, but also creates jobs in the United States and helps other countries become more self-sufficient. All reasons why I believe this money is well-spent and ought to be maintained.
Progress 360
Strong coffee, stronger women
How Ethiopia’s 38,000 health workers have helped save children’s lives and improved the health of their nation.
Of all the charts I’ve seen, this one is the most beautiful:
Why?
First, that descending red line captures one of the most amazing stories of human progress: It shows how the number of deaths of children under 5 per year has been cut in half since 1990.
Second, hidden along that line are millions of stories of the incredible work being done by health officials, governments, donors, and parents around the world to help save all those lives.
Here’s one of those stories. It begins with some remarkable women I met in Ethiopia. They are part of an innovative program that’s improved the health of millions of children in their country.
You can meet them yourself (and join us for a cup of coffee) in this video.
Back in 1990, Ethiopia had one of the highest rates of child mortality in the world. One in five children were dying before their 5th birthdays. With few doctors and most of its population living in rural areas, Ethiopia struggled to provide basic health services to the country. Most women in rural areas gave birth at home.
Then in 2000, the Ethiopian government made a commitment to improve its healthcare system. Ethiopia signed on to the United Nations’ Millennium Development Goals, which focused the world’s attention on fighting disease and ending poverty by using data to measure progress on health and development progress. As part of the goals, Ethiopia pledged to reduce under-five death rates by at least two-thirds by 2015.
To achieve it, Ethiopia needed to find an effective way to deliver healthcare to the remotest corners of the country. But training thousands of new doctors to staff them would take years and would be extremely costly. Instead, Ethiopia created a community health worker program. They selected thousands of people, primarily young women with at least a 10th grade education, and trained them in a set of basic health skills—including how to deliver babies, administer immunizations, and provide family planning support—that are proven to save lives. Most of the health workers were recruited from the communities they served, helping to quickly build public trust in the new effort.
In 2012, I made my first trip to Ethiopia to see the program in action for myself. I was amazed. I visited a remote health post south of Addis Ababa run by two health workers, Yetagesu Alemu and Betula Shemesie. They spent many of their days walking from door to door in their village caring for pregnant women and families with newborns. Their health post didn’t have electricity or any high tech medical equipment. Still, their efforts had made an impact on the health of the families in their community.
What was exciting to see was how this success was being repeated in villages across the country. Despite being one of the poorest countries in the world, Ethiopia managed to dramatically reduce the rate of child mortality. By 2012, Ethiopia had met the target for the Millennium Development Goal on child survival, with under-five death rates dropping by 66 percent since 1990.
One of the key reasons the program has been so effective is that the health workers are dedicated to measuring their progress. Covering nearly every square inch of the walls of the health post I visited were large charts, where the health workers would track births, immunizations, malaria cases, and other indicators. Each indicator helped them understand how well they were performing and which areas demanded more attention.
Today, Ethiopia has more than 15,000 health posts delivering primary health care to the farthest reaches of this rural country of 100 million people. The health posts are staffed by 38,000 health workers like Betula and Yetagesu.
Last summer, I had a chance to visit Ethiopia again. I caught up with Yetagesu and Betula over coffee and to learn more about how the health worker program was going. They told me how women who once delivered their babies at home were now choosing to give birth at health centers. Their communities also had access to ambulances that would pick up any woman who is ready to give birth. Yetagesu and Betula were also proud to report that they had received additional medical training to sharpen their health skills.
To be sure, there’s a lot more work to be done to improve health services in rural Ethiopia. Their communities need more ambulances. Just one vehicle serves 17 health posts, Yetagesu said. They also hoped the country would hire more health workers so they would have the time to provide families with more comprehensive services. And as Melinda and I discussed in this year’s annual letter, one of the biggest challenge in child survival is newborn deaths. In Ethiopia, about 44 percent of all childhood deaths occur within the first 28 days of life. We need to find innovative ways to solve this challenge.
Still, I’m confident that Ethiopia will continue to make progress in child survival. And what’s most exciting is that Ethiopia’s health program has been so successful that it now serves as a model for other countries to follow. Sharing lifesaving innovations like Ethiopia’s ensures that in the years ahead the most beautiful chart in the world will become even more beautiful.
Future investment
Preparing for the next epidemic: a first step
A new organization will help accelerate the development of vaccines we’ll need to contain future outbreaks.
At a time when world leaders are understandably focused on terrorism and other security threats, another enemy is being largely overlooked—the next epidemic.
We don’t know when the next pathogen will emerge, what it will be, how it will spread, or who will be affected, but we do know that the world is not prepared to deal with it. That was the tough lesson that Ebola (and the Zika outbreak since) taught us. Ebola claimed thousands of lives, caused billions of dollars in economic losses, and showed how vulnerable our society is to epidemics of infectious diseases. As I’ve written about before, the world lacks an effective system to detect, respond to, or prevent the next outbreak.
That’s why I’m excited this week, at the World Economic Forum in Davos, to participate in the launch of a new organization that will help the world get ready for future epidemics. Backed by the governments of Norway, India, Japan, and Germany, along with the Wellcome Trust and our foundation, the Coalition for Epidemic Preparedness Innovations (CEPI) will invest in innovations to accelerate the development of vaccines we’ll need to contain outbreaks.
CEPI’s focus on vaccine development is a critical part of getting prepared for whatever pathogens threaten us next. We know from the world’s defeat of smallpox and its successful fights against polio, measles, and other diseases that vaccines are incredibly effective tools for preventing disease and saving lives. Now, this alliance of governments, philanthropies, vaccine manufacturers, academia, NGOs, and other partners needs to work together to develop new vaccines to make the world safe from future epidemics.
Traditional approaches to making new vaccines are too slow to respond to a sudden disease outbreak. Currently, the development of a new vaccine, including testing and deployment, is a process that can typically take more than 10 years. Fast-moving epidemics don’t allow us to be that patient. In 1918, an extremely infectious and deadly strain of the flu infected about one-fifth of the world’s population and killed at least 30 million people in less than two years. Ebola and Zika were also both frightening viruses, but the way they are transmitted—through bodily fluids and mosquitoes—helped limit their spread globally. A highly-contagious airborne disease would pose a far greater threat. It would thrive in densely populated urban areas and could easily cross national borders and oceans by air travel.
My great hope for CEPI is that it will help enable the world to produce safe, effective vaccines as quickly as a new threat like this emerges. With $460 million in initial funding, CEPI will work to bring together the most advanced vaccine technologies and resources from the private and public sector that can help lead to new breakthroughs in vaccine development. CEPI’s vaccine development strategy includes two areas of focus: “just in time” vaccines for those currently unknown pathogens that will emerge, and “just in case” vaccines for pathogens that we know are at high risk of causing another outbreak, like Ebola and Middle East respiratory syndrome or MERS.
One promising area of vaccine development research is using advances in genomics to map the DNA and RNA of pathogens and make vaccines. The vaccines can be decoded by human cells to make their own vaccines and antibodies inside the body. If successful, this technology could dramatically reduce the development timeline from years to possibly months or weeks.
What’s exciting about these new technologies is that they wouldn’t just protect us from future epidemics. They also would help us to develop vaccines for existing health threats to hundreds of millions of people around the world, including HIV, malaria, and TB.
At the same time, CEPI will work to minimize regulatory hurdles that further delay the deployment of vaccines. CEPI will fund studies to evaluate these newly-developed vaccines and build vaccine stockpiles before epidemics begin, so countries can move swiftly to full vaccine efficacy trials and emergency deployment during an outbreak.
As pleased as I am to see CEPI’s work get underway, it’s important for everyone to understand that this effort is just the first step toward getting us prepared for the next epidemic. It’s an important step, but CEPI alone won’t be enough to protect us. We have a lot more work to do.
We need a global warning and response system for outbreaks. It begins with strengthening local health systems in poor countries, which have gotten hit the hardest during recent epidemics. The thousands of remote health clinics around the world will be the backbone of our global effort to defeat future epidemics. They must have trained health workers who can provide primary health care, deliver vaccines, and monitor the health of their communities.
We must have a better disease surveillance system, which includes a global database so countries can share information on cases. We also need trained medical personnel ready to mount a rapid response to an outbreak.
Last, we need to continue to invest in health research to develop not just vaccines, but also new drugs and diagnostic tests that will strengthen our ability to respond quickly and effectively to the next epidemic.
Still, we’ll never know exactly when a new disease outbreak will emerge. It could arrive tomorrow, next month, next decade, or next century. But that uncertainty shouldn’t be an excuse for inaction. I hope that today’s announcement marks the first of many steps the world will take to get prepared for the next epidemic. All of our futures depend on it.
HIV’s Deadly Partner
Let’s make TB history
By investing in R&D, I know it will be possible to discover new innovations that will make TB a disease of the past.
I visited South Africa earlier this year to learn more about the progress the country is making in the fight against HIV. I toured health clinics, met with doctors and researchers, and listened to the stories of people living with HIV. Again and again, our conversations turned to an often forgotten disease which is HIV’s lethal partner: tuberculosis.
Tuberculosis, or TB, is an infection of the lungs that kills about 1.8 million every year, including 400,000 people with HIV and TB. Historically, TB was dubbed “consumption” because it caused such severe weight loss that the disease appeared to “consume” its patients.
Together, HIV and TB form a deadly duo. HIV weakens the immune system, which makes it susceptible to TB infection and much harder for the body to fight the disease. Last year, about one-third of people living with HIV were also infected with TB bacteria, and about 35 percent of deaths among HIV-positive people were due to TB. Worldwide, South Africa has the largest number of people infected with TB and HIV.
Since 2000, better testing and treatment programs have helped drive down TB deaths by more than 20 percent, saving tens of millions of lives. But a new World Health Organization report found that the TB epidemic is larger than previously estimated. New surveillance and survey data revealed hundreds of thousands of new cases, the bulk of them in India. In 2015, there were an estimated 10.4 million new TB cases worldwide, up from 9.6 million cases in 2014. The WHO report also found that of the 10.4 million people with TB, 4.3 million of them did not receive quality care because of significant gaps in testing, treatment, and reporting of TB by health providers. TB deaths climbed to 1.8 million, up from 1.6 million in 2014.
One of the key concerns among health officials fighting TB is the rising threat of drug resistance, something I learned about during a previous visit to South Africa. New strains of the disease have emerged that do not respond to the most commonly used drug treatments available. Treating people with drug-resistant TB is complicated and costly. It also places incredible hardships on the patients who must undergo months of treatment using drugs which are toxic and have serious side-effects.
Last year, Simbongile, a young mother living outside of Cape Town, learned she was infected with drug-resistant TB and started the difficult road to recovery. Her story is heartbreaking, but she is among the lucky ones. In 2015, nearly 600,00 people fell ill from drug resistant TB treatment worldwide. Just 1 in 5 received treatment.
While the impact of drug-resistant TB is a serious problem, the vast majority of TB cases are drug sensitive, meaning they can be cured effectively with medicines so long as they are taken properly. Drug resistance emerges because of incorrect prescriptions by health providers, low-quality drugs, and patients stopping treatment prematurely. That’s why the best way to prevent drug resistance is to improve TB testing and treatment programs for drug-sensitive cases.
TB, like so many other diseases, primarily impacts the world’s poorest people. If you live in a wealthy country, it might be easy to think, as many people do, that TB is a disease of the past. That fact is reflected in the lack of funding for TB programs around the world. In 2016, global support for TB care and prevention fell $2 billion short of the $8.3 billion needed.
Stories like Simbongile’s, however, are a powerful reminder that TB is still an active threat and the world is in dire need for new innovations to prevent and treat it. By investing more in research and development, I know it will be possible to create a new generation of TB drugs and develop a new and effective TB vaccine.
TB is not a disease of the past, but if the world works together to fight it, I have no doubt it can be.
So Long, Sucker
Mapping the end of malaria
Defeating the world’s deadliest creature and the terrible disease it carries is one of the greatest success stories in global health.
A few years ago, I pulled off a purposeful prank. While I was giving a TED Talk on malaria to a room full of influential people, I opened a canister and let loose a small swarm of mosquitoes. “There’s no reason that only poor people should have the experience,” I said. I let the audience squirm in their seats for about half a minute before I let on that the mosquitoes were not infected with malaria. My gimmick worked. A distant problem suddenly got very close to home.
Today, gimmicks are no longer necessary for convincing Americans of the danger of mosquito-borne diseases. The spread of Zika virus in south Florida, Puerto Rico, and other parts of the U.S. has given millions of Americans a direct understanding what it’s like to live with the fear of mosquitoes and the harm they can do, especially to pregnant women and children.
The world must focus serious attention and resources on ending the Zika epidemic. At the same time, we should keep in mind that the overwhelming toll of mosquito-related illness and death comes from malaria. Malaria is the key reason mosquitoes are the deadliest animal in the world.
Over the years, I have been in hospitals in several African countries when malaria is at its peak. I’ve seen beds out in the corridors and two children to a bed. There’s nothing more painful to see than a child experiencing cerebral malaria, when the parasite is attacking the brain and causing horrible seizures. As a parent, these memories will stay with me for life.
That’s why it gives me great joy to share a new report published todayin The New England Journal of Medicine. Rigorous new data show that the malaria death rate in sub-Saharan Africa has declined by a stunning 57% since 2000. With almost 500,000 children still dying of malaria every year, we obviously have a long way to go. But cutting the death rate by more than half is a miracle. It’s one of the greatest success stories in the history of global health.
We’ve known for some time that malaria deaths have been declining steeply. The significance of this new study, which was produced by the Institute for Health Metrics and Evaluation, is that we now have the strongest evidence ever of just how steep the decline has been.
This progress on malaria is no accident. It’s the result of an unprecedented increase in focus and commitment by rich and poor countries alike. The amount of money available to pay for bed nets, effective medications, and malaria research rose by 1,000 percent from 2000 to 2015, fueling massive new prevention and control efforts in countries hit hard by malaria.
In Tanzania, a country that has led the way with a major scale-up, the mortality rate fell more than 80 percent from 2000 to 2015. I remember visiting Tanzania years ago during the rainy season and seeing overflowing hospitals. When I went back years later, there were almost no children in the wards.
Tanzanian health authorities have launched major campaigns to distribute insecticide-treated bed nets and encourage people—especially children—to sleep under them every night. They’ve done widespread spraying of insecticides inside homes and in urban ponds, puddles, and marshes where mosquitoes breed. And they’ve used great medications that contain a drug called artemisinin, which earned its discoverer, Youyou Tu, the 2015 Nobel Prize in Medicine. If you take three days’ worth of these pills, you can get rid of the malaria parasites in your bloodstream, which helps you and also stops you from being the source of malaria spreading back to other people.
And now we have an awesome new tool in our arsenal: precision malaria maps. In the same New England Journal article I mentioned above, the authors report on cutting-edge mapping efforts that have given us an ability to see at a very high degree of granularity (5 km by 5 km) the burden of malaria in sub-Saharan Africa. That’s super valuable for short-term interventions, like helping a country determine where to deploy health staff. It’s just as valuable for long-term efforts to reduce the rate of transmission and shrink the malaria map.
When you zoom in with these high-definition maps, you can quickly home in on the hot spots where malaria is hitting hard and yet existing tools like bed nets are not being used widely enough. These maps show that in most countries it’s actually a very small percentage of the country where the disease burden is high and you need to focus your interventions.
And here’s more good news: After years of investment, we now have better diagnostics for detecting infections in people who show no physical symptoms (because people who are infected with malaria parasites but don’t show signs of illness are a big part of the chain of transmission). We have helped private-sector companies develop new, safe insecticides that will allow us to preserve the gains we have made against malaria. We have also helped bring to market simple technologies to protect families from mosquitoes, such as “eave tubes” that kill mosquitoes trying to enter homes and new traps which exploit mosquitoes’ attraction to sugar to kill them outdoors.
As a result of all this progress, I am confident that we can pursue the end goal of not just shrinking the malaria map but wiping malaria off the map altogether. Last year, Ray Chambers, the UN Secretary General’s special envoy for malaria, and I put forward a concrete plan for eradicating the disease by 2040. The potential upside is enormous: 11 million lives and $2 trillion dollars of economic impact. And the alternative to eradication—controlling the disease forever without eliminating it—is biologically and politically untenable. It would require endless investment in the development of new drugs and insecticides just to stay one step ahead of disease resistance. I also believe it would be impossible to maintain strong political commitment to fighting malaria unless we can define a clear end point. History has shown that unless countries rid themselves of malaria altogether, they eventually see the disease come roaring back on a massive scale.
To achieve eradication by 2040, we’ll need several other key innovations under development to come to fruition.
First, we’ll need new classes of drugs that completely clear malaria parasites from the body with just one dose. We should have these new cures in about a decade.
Second, we need new tools that can prevent malaria transmission. This can either be done with an effective malaria vaccine or by reducing mosquito populations. We will soon have a first-generation vaccine, but it protects a child for less than six months without a booster dose. I’m betting that within the next 10 years, researchers can produce a vaccine that provides much longer protection.
We have another potential game-changer in the works. Our foundation is supporting scientists who are using a powerful new tool called “genome editing” to introduce genetic changes in the Anopheles gambiae species of mosquito, one of the most effective transmitters of malaria in Africa. These genetic edits cause females to produce mostly male, sterile offspring. In theory, scientists could drive this trait throughout entire populations of mosquitoes in much of Africa, dramatically reducing malaria transmission in a very short time. While I’m excited about the potential of this technology, I know that changing the mosquito genome in a permanent way is something that should be done only with incredible caution and care. My hope is that it will be possible to deploy some version of this technique in a safe manner within 10-12 years.
In 1999, Melinda and I made our first major investment in malaria—a grant to establish the Malaria Vaccine Initiative. Funding for malaria research was so diminished at the time that we nearly doubled the resources with that one single grant. That blew my mind.
Today, this is no longer a lonely fight. More than 50 countries have joined together to mobilize billions of dollars through The Global Fund. And these resources are coming not just from wealthy countries. African countries such as Benin, Côte d’Ivoire, Kenya, Namibia, Nigeria, Senegal, South Africa, Togo, and Zimbabwe are contributing as well. In fact, African countries are now, for the first time ever, mobilizing more of their own resources for malaria than they’re receiving from donors.
So the next time you hear skeptics charging that foreign aid doesn’t work, point to malaria. Foreign assistance has not chased away local resources. On the contrary, it’s encouraged African nations to step up their own health efforts. And the results have been nothing short of remarkable.
360⁰ of Connection
South Africa: Virtually There
Travel with me to South Africa to see how the country is hoping to win the fight against AIDS.
If you could shuffle all of the homes in the world like a deck of cards so that people in wealthy countries lived side by side with people from poor countries, it would transform the world’s fight against poverty, hunger, and disease. It would be impossible for people to look away, impossible for them not to help.
I was naïve about the deep poverty in the world until I took my first trip to Africa with Melinda in 1993. Seeing the disparities with our own eyes made all the difference and inspired us to start our foundation.
Since then, I’ve continued to travel regularly to Africa, India, and other parts of the developing world. I always return from my trips humbled and inspired. My one disappointment is that I wish everyone could have seen what I did. I have no doubt it would help more people become aware of the challenges the world’s poorest people face. It would also leave them as optimistic as I am about the incredible progress the world is making in health and development.
During my trip to South Africa in July, I tried something new that I hope will allow people to experience what I have. I had highlights of my visit recorded in virtual reality. It’s still an emerging technology but what excites me about it is that it allows viewers to immerse themselves in another world. You can look up and down. Turn right or left. Listen to sounds all around you. I used to think there was no substitute to being there and seeing things for yourself. But virtual reality is a close second. It fulfills my dream of allowing people to see what I’m seeing and, perhaps, feel what I’m feeling, too.
In this video, you will hear the stories of young women living with HIV. Sit beside me as I drive from the leafy suburbs of Johannesburg to the dusty township of Soweto. Feel what it’s like to be in the center of a stomping gumboot dancing troupe. And be inspired by the power of South Africa’s youth, who will drive the next generation of innovations to create a future free of AIDS.
If you want to know more about my trip to South Africa, you can read about my visit here and here. I also encourage you to learn more about The Global Fund, which has helped provide lifesaving treatment to millions of people living with HIV.
Thanks for watching and look out for more virtual reality videos in the months ahead.
Status Check
We Haven’t Turned the Corner on AIDS
Why we need to invest more in the fight.
Next week I’ll be traveling to Durban, South Africa, to attend the International AIDS Conference. It’s an important opportunity for members of the AIDS community to discuss our ongoing efforts to fight the disease. I’ll be there to listen and learn. But I’ll also be delivering my own message.
The good news is that the fight against AIDS has seen many successes. The infection rate declined for several years and millions of people have been put on treatment, allowing them to live full, productive lives.
But we have not turned the corner. The infection rate has essentially stopped declining. That’s a particular problem in sub-Saharan Africa, which has a growing population of young people, who are most susceptible to the disease. If the infection rate stays the same while the at-risk population rises, then the number of people in sub-Saharan Africa who contract HIV each year could start going up instead of down.
One reason the infection rate has stagnated is that AIDS funding has stagnated. Another reason is that the current prevention tools have not had as much impact as any of us had hoped. Voluntary medical male circumcision is a very effective prevention approach, but the programs offering the procedure have not been scaled up sufficiently to reach all those who would benefit. The newest tool, using AIDS treatment as a way to prevent HIV infection among healthy people, has not been rolled out fast enough, and asking people to take a pill every day for prevention presents its own challenges.
There is the idea of “treatment as prevention”: Treating people who have HIV not only saves their life, it also makes them much less likely to pass the virus along to others. This is a promising approach and certainly we should treat as many people as possible so we can save their lives. But it is not yet clear to me that it is financially feasible to treat enough people to get a large prevention effect. I hope to learn more about this question at the conference next week.
For all these reasons, we need to invest more in both delivering the best prevention tools we have and developing new ones that are even more effective. For example, researchers are working on prevention and treatment tools that last for several months after a single dose, which would make it easier for people to stick to the regimes. I am also optimistic that within a decade we will have an AIDS vaccine that provides an acceptable level of protection.
In this video, I explain what it will take to make the most of these opportunities and ensure that AIDS cases keep going down:
17 Million Saved
Let’s preserve this lifesaver
Why we need to keep supporting the Global Fund.
Let me cut to the chase. There’s a program that has helped save the lives of 17 million people in poor countries since 2002. It’s called the Global Fund to Fight AIDS, TB, and Malaria. It’s poised to do even more good in the years ahead, but to continue its work, it needs donors to make new funding pledges.
I just got back from Europe, which is starting to think through many tough decisions surrounding Brexit. Despite that challenge, the governments of France and Italy became the latest to make commitments to the Global Fund, building on recent pledges from Japan, Canada, the United States, and the European Commission. When I was in London, a senior member of the British government confirmed to Parliament that they remain committed to the Global Fund’s success. Although I’m confident the Global Fund will raise the money it needs—donors have consistently recognized that it’s an effective and low-cost way to save lives—we are not there yet.
Since the Global Fund started, Melinda and I have committed $1.6 billion to it. Here are four reasons why we are such big believers:
- Saving lives. In countries where the Global Fund operates, deaths from HIV, TB, and malaria have dropped by a third since 2002. Certainly the Fund doesn’t deserve sole credit for that phenomenal progress, but it has played an irreplaceable role. And its work is far from finished: Three million people still die every year from these diseases.
- Getting rid of diseases so we never have to fight them again. In my lifetime I expect to see the end of malaria, which kills nearly half a million children every year. When you eradicate a disease, you not only save lives, you free up billions of dollars and many hours of effort. One reason I’m so optimistic about ending malaria is the work of the Global Fund, which has slowed the spread of the disease and saved lives by distributing hundreds of millions of bed nets.
- Helping poor countries become more self-sufficient. If you ever hear people say “poor countries just keep getting foreign aid forever,” tell them about the Global Fund. It helps the countries it works with improve their health systems so they can take better care of their people. They also devote an increasing share of their own budgets to health (they have promised to spend 50 percent more between 2015 and 2017 than they did in the previous three years). That translates into less spending by rich governments.
- Using aid efficiently. The Fund has a done a great job keeping costs low and streamlining its work. Its operating costs are just over 2 percent of all the grants it gives out. That means the vast majority of the money that flows through the Global Fund is reaching the people who need it most.
The Global Fund raises money in three-year batches; the current batch will cover the years 2017-19. They’re asking for $13 billion, which will go toward delivering lifesaving drugs and bed nets as well as developing new tools like better diagnostics and next-generation prevention techniques. To put that number in context, it’s about 3 percent of the total foreign aid that rich countries give over three years. And consider the payoff: By one estimate, the $13 billion raised by the Global Fund will generate about $300 billion in economic benefits.
It is never easy to raise large sums of money like this, and it certainly isn’t easy now, with the refugee crisis in Europe compounding an already difficult global economy. Although I don’t think anyone would argue that fighting disease will directly end wars or stop the flow of refugees, improving health certainly makes countries more stable and more prosperous—and less likely to spread disease and instability to their neighbors.
If you want to save and improve lives, health is one of the most effective investments you can make. And if you want to improve health, the Global Fund is one of the most effective investments you can make. It is one of the kindest things people have ever done for one another, and I am inspired by the countries and leaders who are stepping up to support it.
Innovation Nation
America’s secret weapon
By investing in R&D, the U.S. creates jobs at home and helps people around the world.
This presidential election has the country captivated. As many commentators have pointed out, the primaries are more focused on personalities than policy. While the parties focus on who is going to represent them in the fall, I want to make the case for something that I hope every candidate will agree on in November: America’s unparalleled capacity for innovation. When the United States invests in innovation, it creates companies and jobs at home, makes Americans healthier and safer, and saves lives and fights poverty in the world’s poorest countries. It offers the next president a tremendous opportunity to help people in America and around the world.
Of course, America’s capacity for innovation is nothing new. We have been inventing for more than two centuries: think of Benjamin Franklin, Margaret Knight, Thomas Edison. By the end of World War II, the United States led the world in automobiles, aerospace, electronics, medicine, and other areas. Nor is the formula for success complicated: Government funding for our world-class research institutions produces the new technologies that American entrepreneurs take to market.
What is new is that more countries than ever are competing for global leadership, and they know the value of innovation. Since 2000, South Korea’s R&D spending (measured as a percentage of GDP) has gone up 90 percent. China’s has doubled. The United States’ has essentially flatlined. It’s great that the rest of the world is committing more, but if the U.S. is going to maintain its leading role, it needs to up its game.
I have seen first-hand the impact that this type of research can have. I was lucky enough to be a student when computers came along in the 1960s. At first they were very expensive, so it was hard to get access to them. But the microchip revolution, made possible by U.S. government research, completely changed that. Among other things it enabled Microsoft, the company I co-founded, to write software that made computers an invaluable tool for productivity. Later, the Internet—another product of federal research—changed the game again. It is no accident that today most of the top tech companies are still based in the United States, and their advances will have a massive impact in every area of human activity.
My favorite example is health. America’s investment in this area creates high-paying jobs at universities, biotech companies, and government labs. It leads to new treatments for disease, such as cancer therapies. It helps contain deadly epidemics like Ebola and Zika. And it saves lives in poor countries. Since 1990, the fraction of children who die before age 5 has fallen by more than half. I think that’s the greatest statistic of all time, and the United States deserves a lot of credit for making it happen.
The next few years could bring even more progress. With a little luck we could eradicate polio, a goal that is within reach because of vaccines developed by U.S. scientists. (Polio would be the second disease ever eradicated, after smallpox in 1979—in which the U.S. also played an irreplaceable role.) There is also exciting progress on malaria: The number of deaths dropped more than 40 percent from 2000 to 2012, thanks in part to America’s support for breakthrough tools like drugs and bed nets. But to make the most of these opportunities, we need to invest more in basic health research and specific areas like vaccines.
Energy is another great example. American-funded research defines the state of the art in energy production. Early advances in wind and solar technology were developed with federal money. And this research offers a strong return on investment. Between 1978 and 2000, the Department of Energy spent $17.5 billion (in today’s dollars) on research on efficiency and fossil fuels, yielding $41 billion in economic benefits. Yet until this year, the DOE’s research budget hadn’t seen a real increase since the Reagan administration.
If we step up these investments, we can create new jobs in the energy sector and develop the technologies that will power the world—while also fighting climate change, promoting energy independence, and providing affordable energy for the 1.3 billion poor people who don’t have it today. Some of the more promising areas include making fuel from solar energy, much the way plants do; making nuclear energy safer and more affordable; capturing and storing carbon; and creating new ways to store energy that let us make the most of renewables.
There’s a lot of momentum right now on clean energy research. Last year the leaders of 20 countries, including the United States, committed to double federal investments in this area. Complementing that crucial effort, I helped launch the Breakthrough Energy Coalition, a group of private investors who will back promising clean-energy companies. The next president will have a chance to accelerate this momentum.
Investing in R&D isn’t about the government picking winners and losers. The markets will do that. It’s about doing what we know works: making limited and targeted investments to lay a foundation for America’s entrepreneurs. This approach has been fundamental to U.S. leadership for decades, and it will become only more important in the years ahead.
By the end of this summer, the political parties will have chosen their leaders and will start looking ahead to the November election. The nominees will lay out their vision for America and their agenda for achieving it. These visions will probably have more differences than similarities. But I hope we can all agree that, no matter how you see America’s future, there will always be an essential role for innovation.
This article was originally published by Reuters News Agency.
Lessons From Ebola
We’re not ready for the next epidemic
We’re not ready for it. But we can get there.
I am in Vancouver this week attending the TED conference. I just gave a brief talk on a subject that I’ve been learning a lot about lately—epidemics.
The Ebola outbreak in West Africa is a tragedy—as I write this, more than 10,000 people have died. I’ve been getting regular updates on the case counts through the same system we use to track new cases of polio. Also, last month I was lucky enough to have an in-depth discussion with Tom Frieden and his team at the Centers for Disease Control and Prevention in Atlanta.
What I’ve learned is very sobering. As awful as this epidemic has been, the next one could be much worse. The world is simply not prepared to deal with a disease—an especially virulent flu, for example—that infects large numbers of people very quickly. Of all the things that could kill 10 million people or more, by far the most likely is an epidemic.
But I believe we can prevent such a catastrophe by building a global warning and response system for epidemics. It would apply the kind of planning that goes into national defense—systems for recruiting, training, and equipping health workers; investments in new tools; etc.—to the effort to prevent and contain outbreaks.
This is what my TED talk was about. You can watch it here:
The more I learn about what it takes to respond to an epidemic, the more impressed I am by the health workers who have been risking their lives to care for the sick. Just putting on a protective suit is huge undertaking. Once it’s on, it’s hard to hear what anyone else is saying, and you start to sweat after just a few minutes.
Here’s a short photo essay about one attempt to solve this problem that I was involved with.
At TED we also put together an exhibit where attendees could try on a suit for themselves:
Finally, if you’re interested in learning more, you might want to check out this op-ed I wrote for the New York Times. And if you are willing to read a little more (okay, a lot more), here is a longer paper I wrote for the New England Journal of Medicine.
Melinda and I remain committed to improving the health of the poorest 2 billion. The good news is, many of the steps required to save lives in poor countries—such as strengthening health systems—also improve the world’s ability to deal with epidemics. So I’m optimistic that we can solve this problem. Making the right investments now could save millions of lives.
An Anti-Viral Campaign
Hard questions about the next epidemic
I hit the road to talk about preventing epidemics. Here’s what I heard.
Normally when I post here on TGN, give a speech, or write an op-ed, I’m out to share good news about how the world is getting better. But last month I made an exception. In a TED talk, an op-ed in the New York Times, and a longer paper in the New England Journal of Medicine, I wanted to highlight a sobering fact: The world is not prepared to handle a major epidemic. I shared a few thoughts about what it might take to get ready, based on lessons from the Ebola epidemic in West Africa.
I was curious to hear people’s feedback on my suggestions, so it was great to meet in Berlin with a group of health experts from governments, non-profits, and pharmaceutical companies, and then with U.S. senators in Washington, D.C. In this post, I want to share a few of the things I heard.
There is general agreement that this is a big challenge. Everyone I talked to, politicians and technical experts alike, felt strongly that the world isn’t doing enough to prepare. There is also broad agreement about what to do: we need to create a global alert and response system for epidemics.
As we got into the details, though, we ran into some tough issues.
For example, I argued that in a severe epidemic, the military has to play a role. It’s the only group that can quickly move large numbers of people and equipment in and out of an affected area. But in my conversations in D.C., it became clear that the U.S. military is not chartered for this work and doesn’t prepare for it, which meant that in West Africa they were learning on the fly.
In addition, what happens when there’s an outbreak in a region where people see the army—whether it’s domestic or foreign—as the bad guy? Some NGO leaders and health workers worry that being associated with armed forces could put them in harm’s way by making them a target.
This is one of the toughest issues that came up and it deserves more discussion. At a minimum I think we need a diverse set of military groups from different countries ready to help. And we can take steps to make it clear that troops are on a humanitarian mission, for example by running simulations in different countries so citizens can see what they’re up to.
Another big topic was drug trials. In an epidemic you want to develop and test new treatments very quickly. But how do you make that happen when the usual drug-approval process takes years? Should there be an emergency regulator who decides which drugs to test, how to test them quickly, and whether to deploy one? Should (and can) they indemnify whoever is producing the drug to protect them from lawsuits?
All these conversations raised a larger issue that is fascinating to me: How should the world get ready for rare, potentially cataclysmic events? When an epidemic strikes, we will want the best health and logistics experts ready to spring into action. But which group has the budget to maintain that kind of spare capacity? Even more importantly, how do we get brilliant people to sit around waiting for an event that has a small chance of occurring in any given year?
The closest analogy I can think of is the military, where troops might go years at a time without seeing combat. They use training exercises and war games to stay sharp. I think we should be doing something similar—germ games—for epidemics.
What happens next? Even though the experts mostly agree on the broad strokes of what should be done, I don’t know whether the world will choose to put meaningful resources into this effort. But I am hopeful that it will happen. The group I joined in Berlin is providing input to German Chancellor Angela Merkel and the G7 group of wealthy countries as they think about how they can help solve this problem. Creating a global plan would help more nations see how they can contribute and hopefully draw them in. The United Nations and WHO are also looking at various steps that could improve their ability to respond. And at the Gates Foundation we’re talking about how we might be able to assist.
It is great to see this issue rising up the global agenda. The world isn’t ready yet for a serious epidemic, but I think we have a good chance to make real progress in the next few months.
Well Suited
Arming doctors to fight Ebola
As I learned recently, it’s one thing to find a new tool that will help the people fighting this deadly disease. Getting it to them is another story.
Getting new tools into the hands of the people fighting Ebola is much harder than it needs to be. I have experience with one alarming example.
Health workers in protective suits get so hot that they have a hard time caring for their patients. (For example your goggles fog up and you sweat profusely.) I asked a team of experts who work on technology for keeping vaccines cold to refocus on keeping the medical workers cool.
Within days, the team had found an existing solution: a vest with pockets where you could insert cooling packs.
Doctors who had treated Ebola patients in West Africa helped test and improve these cooling vests. Here you see Dr. Colin Bucks of Stanford University testing a vest and suit at home while under quarantine after working in Liberia. He rode a stationary bike to simulate the heat of West Africa.

Unfortunately, there was no coordinated system for getting the vests to West Africa. The team had to create new distribution channels by working directly with treatment centers in the region. They eventually got the suits to over a thousand health workers.

Although this wasn’t a critical issue, it is just one example of the challenge of preparing for a highly infectious disease. We see similar breakdowns in detecting outbreaks early, training and deploying volunteers, coordinating with the military, and more. But I’m optimistic that if we start now and stay focused, we can get ready for the next epidemic.

Spending Pennies, Saving Lives
The Miracle of Vaccines
Vaccines, one of the best investments you can make for improving health.
Imagine there’s an infectious disease spreading through your community. It leaves some people crippled; others die from it. Then someone comes along and says: “Here’s something that will protect you from this disease for the rest of your life. You and your family can have it, for free.” You would be very relieved, right?
This scenario may seem hypothetical (though perhaps less so given how much the Ebola virus has been in the news). But it is very real for millions of people in the world’s poorest countries. Vaccines that were once out of reach for them are being delivered in greater numbers every year. That means more parents are feeling the relief of knowing their families are protected.
I’ve been looking at some of the data on vaccines and thought I would share what I’m seeing. At a time when so many news headlines are grim, it is inspiring stuff.
I’ll start with polio. Cases are down more than 99 percent since 1988. Earlier this year, we celebrated a fantastic achievement: India was declared polio-free. And in Nigeria, the number of polio cases is at an all-time low, just 6 so far this year versus more than 50 by this time last year. It’s one of only three countries that have never been polio free (the others are Pakistan and Afghanistan).
Wherever we make progress on polio, it’s a testament to the amazing work of many people: political leaders who prioritize stopping the disease, donors who help fund the effort, and—most importantly—the health workers who doggedly go from house to house to deliver vaccines. Thanks to all this work (and with a little luck), 2015 could be the first time Nigeria goes a year without a case of wild poliovirus, and the first time all of Africa is polio-free. If we maintain this commitment, I’m quite optimistic that by 2018 we will get rid of this crippling disease, everywhere, forever.
There’s also fantastic progress in delivering basic immunizations for diseases like measles and pneumonia. The impact is phenomenal: By next year, the public-health group known as Gavi, the Vaccine Alliance will have helped prevent 3.9 million deaths. And expanding vaccine coverage over the next five years can save as many as 6 million lives and unlock more than $100 billion in economic benefit.
Along those lines, we hit a big milestone in September. With the addition of South Sudan, pentavalent vaccine—which protects against five debilitating diseases—has now been introduced in all 73 countries that get financial support from Gavi. Pentavalent replaced a vaccine that protected against only three diseases, which means kids are protected from more diseases without getting any extra shots. This would never have happened without Gavi: By negotiating with manufacturers and bringing in new suppliers, it drove down the cost of pentavalent vaccine from $30 per dose in rich countries to just $1.19 for poor countries.
Another big step has been the rollout of a vaccine for rotavirus, which causes severe diarrhea. Rotavirus is one of the reasons Melinda and I first got involved in global health; in the late 1990s, we were shocked by a newspaper article that said it killed 800,000 children a year—nearly all of them in poor countries—more than almost any other disease. After more research, we decided rotavirus should be a focus of our giving. We’re gratified to see that 65 countries are now rolling out rotavirus vaccines, and more are signing up. Manufacturers in India are working on a new vaccine and talking about exporting it to other countries, which would help save even more children.
We’re also getting closer to solving some big delivery problems, like the fact that many vaccines spoil if they get too warm. Researchers are field-testing a specially designed container that keeps vaccines cold for a month or more, using just a single batch of ice and no electricity. These trials are helping thousands of African children get immunized. I’m very hopeful that containers like this one will eventually help health workers reach far more people.
A Ripple Effect
Vaccines save lives, which is reason enough to make sure they get out there. But that’s not their only benefit. Healthy children spend more time in school, and they learn better while they’re there. When health improves, poor countries can spend more on schools, roads, and other investments that drive growth, which makes them less dependent on aid.
Vaccines deliver all this for, in some cases, just pennies per shot. That’s why I say that if you want to save and improve lives around the world, vaccines are a fantastic investment.
How You Can Help
One way you can help is to ask your political leaders to support Gavi next year, when donor governments need to renew their commitments. In the United States you can do that through Shot@Life, whose website makes it easy to send a message to your representatives.
You can also help by donating to Shot@Life. For $20, you can help protect a child from pneumonia, diarrhea, polio, and measles. And Shot@Life has teamed up with Walgreens for a “Get a shot. Give a shot” program: Get a vaccine at Walgreens and they will provide one for a child in a poor country.
This is flu season in the United States, so you may already be planning to get immunized. Why not help out someone else while you’re at it?
On the Front Lines of an Epidemic
“Your blood tested positive for Ebola. I am sorry.”
A Nigerian doctor’s harrowing account of outlasting the deadly virus.
Once in a while, you read something that’s so compelling, you want to share it with everyone you can. Dr. Ada Igonoh’s story had that effect on me.
Dr. Igonoh is a physician in Lagos, Nigeria, where she helped care for Patrick Sawyer, the patient who introduced Ebola into Nigeria in July. After coming down with the deadly virus herself, she spent two harrowing weeks getting treatment in isolation wards.
When I met her at a conference in New Orleans last week, Dr. Igonoh handed me a written account of her experience. Even knowing she was going to be okay, I couldn’t stop reading—I had to know what happened next. Her optimism was inspiring. Her story also gave me a deeper appreciation for all the health workers who are heroically caring for patients and trying to stop this epidemic. And it is a good reminder of the way uncertainty reigns in the early days of an epidemic. The world’s response since then has been remarkable, and Nigeria has now been certified free of Ebola.
I want to thank Dr. Igonoh for her courage, and for agreeing to let me share her story here. It is well worth your time to read it. — Bill Gates
On the night of Sunday July 20th, 2014, Patrick Sawyer was wheeled into the emergency room of the First Consultants Medical Centre, Obalende, Lagos, with complaints of fever and body weakness. The male doctor on call admitted him as a case of malaria, and took a full history.

Knowing that Mr. Sawyer had recently arrived from Liberia, the doctor asked if he had been in contact with an Ebola patient in the last couple of weeks, and Mr. Sawyer denied any such contact. He also denied attending any funeral ceremony recently. Blood samples were taken for full blood count, malaria parasites, liver function test, and other baseline investigations. He was admitted into a private room and started on antimalarial drugs and analgesics. That night, the blood count result came back as normal and not indicative of infection.
The following day, however, his condition worsened. He barely ate any of his meals. His liver function test result showed his liver enzymes were markedly elevated. We then took samples for HIV and hepatitis screening.
At about 5:00 p.m. he requested to see a doctor. I was the doctor on call that night, so I went in to see him. He was lying in bed with his intravenous (IV) fluid bag removed from its metal stand and placed beside him. He complained that he had stooled about five times that evening and that he wanted to use the bathroom again.
I picked up the IV bag from his bed and hung it back on the stand. I told him I would inform a nurse to come and disconnect the IV so he could conveniently go to the bathroom. I walked out of his room and went straight to the nurses' station where I told the nurse on duty to disconnect his IV. I then informed my consultant, Dr. Ameyo Adadevoh, about the patient's condition, and she asked that he be placed on some medications.
The following day, the results for HIV and hepatitis screening came out negative. As we were preparing for the early morning ward rounds, I was approached by an ECOWAS [Economic Community of West African States] official who informed me that Patrick Sawyer had to catch an 11 o'clock flight to Calabar for a retreat that morning. He wanted to know if it would be possible. I told him it wasn't, as he was acutely ill. Dr. Adadevoh also told him the patient could certainly not leave the hospital in his condition. She then instructed me to write very boldly on his chart that on no account should Patrick Sawyer be allowed out of the hospital premises without the permission of Dr. Ohiaeri, our Chief Medical Consultant. All nurses and doctors were duly informed.
During our early morning ward round with Dr. Adadevoh, we concluded that this was not malaria, and that the patient needed to be screened for Ebola Viral Disease. She immediately started calling laboratories to find out where the test could be carried out. She was eventually referred to Professor Omilabu of the LUTH Virology Reference Lab in Idi-Araba, whom she called immediately.
Prof. Omilabu told her to send blood and urine samples to LUTH straightaway. She tried to reach the Lagos State Commissioner for Health but was unable to contact him at the time. She also put calls across to officials of the Federal Ministry of Health and National Centre for Disease Control.
Dr. Adadevoh at this time was in a pensive mood. Patrick Sawyer was now a suspected case of Ebola, perhaps the first in the country. He was quarantined, and strict barrier nursing was applied with all the precautionary measures we could muster. Dr. Adadevoh went online, downloaded information on Ebola, and printed copies which were distributed to the nurses, doctors and ward maids. Blood and urine samples were sent to LUTH that morning. Protective gear, gloves, shoe covers and facemasks were provided for the staff. A wooden barricade was placed at the entrance of the door to keep visitors and unauthorized personnel away from the patient. Despite the medications prescribed earlier, the vomiting and diarrhea persisted. The fever escalated from 38°C to 40°C.
On the morning of Wednesday, 23rd July, the tests carried out in LUTH showed a signal for Ebola. Samples were then sent to Dakar, Senegal for a confirmatory test. Dr. Adadevoh went for several meetings with the Lagos State Ministry of Health. Thereafter, officials from the Lagos State came to inspect the hospital and the protective measures we had put in place.
The following day, Thursday 24th July, I was again on call. At about 10:00 p.m. Mr. Sawyer requested to see me. I went into the newly created dressing room, donned my protective gear and went in to see him. He had not been cooperating with the nurses and had refused any additional treatment. He sounded confused and said he received a call from Liberia asking for a detailed medical report to be sent to them. He also said he had to travel back to Liberia on a 5:00 a.m. flight the following morning and that he didn't want to miss his flight. I told him that I would inform Dr. Adadevoh. As I was leaving the room, I met Dr. Adadevoh dressed in her protective gear, along with a nurse and another doctor. They went into his room to have a discussion with him, and as I heard later to reset his IV line which he had deliberately removed after my visit to his room.
At 6:30 a.m., Friday 25th July, I got a call from the nurse that Patrick Sawyer was completely unresponsive. Again I put on the protective gear and headed to his room. I found him slumped in the bathroom. I examined him and observed that there was no respiratory movement. I felt for his pulse; it was absent. We had lost him.
It was I who certified Patrick Sawyer dead. I informed Dr. Adadevoh immediately and she instructed that no one was to be allowed to go into his room for any reason at all. Later that day, officials from WHO came and took his body away. The test in Dakar later came out positive for Zaire strain of the Ebola virus. We now had the first official case of Ebola virus disease in Nigeria.
It was a sobering day. We all began to go over all that happened in the last few days, wondering just how much physical contact we had individually made with Patrick Sawyer. Every patient on admission was discharged that day and decontamination began in the hospital. We were now managing a crisis situation.
The next day, Saturday 26th July, all staff of First Consultants attended a meeting with Prof. Nasidi of the National Centre for Disease Control, Prof. Omilabu of LUTH Virology Reference Lab, and some officials of WHO. They congratulated us on the actions we had taken and enlightened us further about the Ebola Virus Disease. They said we were going to be grouped into high risk and low risk categories based on our individual level of exposure to Patrick Sawyer, the "index" case. Each person would receive a temperature chart and a thermometer to record temperatures in the morning and night for the next 21 days. We were all officially under surveillance. We were asked to report to them at the first sign of a fever for further blood tests to be done. We were reassured that we would all be given adequate care. The anxiety in the air was palpable.
The frenetic pace of life in Lagos, coupled with the demanding nature of my job as a doctor, means that I occasionally need a change of environment. As such, one week before Patrick Sawyer died, I had gone to my parents' home for a retreat. I was still staying with them when I received my temperature chart and thermometer on Tuesday, 29th of July. I could not contain my anxiety. People were talking about Ebola everywhere—on television, online, everywhere.

I soon started experiencing joint and muscle aches and a sore throat, which I quickly attributed to stress and anxiety. I decided to take malaria tablets. I also started taking antibiotics for the sore throat. The first couple of temperature readings were normal. Every day I would attempt to recall the period Patrick Sawyer was on admission—just how much direct and indirect contact did I have with him? I reassured myself that the contact with him was quite minimal. I completed the anti-malarials but the aches and pains persisted. I had loss of appetite and felt very tired.
On Friday, 1st of August, my temperature read a high 38.7°C. As I type this, I recall the anxiety I felt that morning. I could not believe what I saw on the thermometer. I ran to my mother's room and told her. I did not go to work that day. I cautiously started using a separate set of utensils and cups from the ones my family member were using.
On Saturday, 2nd of August, the fever worsened. It was now at 39°C and would not be reduced by taking paracetamol. This was now my second day of fever. I couldn't eat. The sore throat was getting worse. That was when I called the helpline and an ambulance was sent with WHO doctors, who came and took a sample of my blood. Later that day, I started stooling and vomiting. I stayed away from my family. I started washing my plates and spoons myself. My parents, meanwhile, were convinced that I could not have Ebola.
The following day, Sunday, 3rd of August, I got a call from one of the doctors who came to take my sample the day before. He told me that the sample which they had taken was not confirmatory, and that they needed another sample. He did not sound very coherent and I became worried. They came with the ambulance that afternoon and told me that I had to go with them to Yaba. I was confused. Couldn't the second sample be taken in the ambulance like the previous one? He said a better-qualified person at the Yaba Centre would take the sample. I asked if they would bring me back. He said "yes." Even with my symptoms, I did not believe I had Ebola. After all, my contact with Sawyer was minimal. I only touched his IV fluid bag just that once without gloves. The only time I actually touched him was when I checked his pulse and confirmed him dead, and I wore double gloves and I felt adequately protected.
I told my parents I had to go with the officials to Yaba and that I would be back that evening. I wore a white top and a pair of jeans, and I put my iPad and phones in my bag.
A man opened the ambulance door for me and moved away from me rather swiftly. Strange behavior, I thought. They were friendly with me the day before, but that day, not so. No pleasantries, no smiles. I looked up and saw my mother watching through her bedroom window.
We soon got to Yaba. I really had no clue where I was. I knew it was a hospital. I was left alone in the back of the ambulance for over four hours. My mind was in a whirl. I didn't know what to think. I was offered food to eat but I could barely eat the rice.
The ambulance door opened and a Caucasian gentleman approached me but kept a little distance. He said to me, "I have to inform you that your blood tested positive for Ebola. I am sorry."
I had no reaction. I think I must have been in shock. He then told me to open my mouth and he looked at my tongue. He said it was typical Ebola tongue. I took out my mirror from my bag and took a look and was shocked at what I saw. My whole tongue had a white coating, looked furry, and had a long, deep ridge right in the middle. I then started to look at my whole body, searching for Ebola rashes and other signs, as we had been recently instructed. I called my mother immediately and said, "Mummy, they said I have Ebola, but don't worry, I will survive it. Please go and lock my room now; don't let anyone inside and don't touch anything." She was silent. I cut the line.
I was taken to the female ward. I was shocked at the environment. It looked like an abandoned building. I suspected it had not been in use for quite a while. As I walked in, I immediately recognized one of the ward maids from our hospital. She always had a smile for me but not this time. She was ill and looked it. She had been stooling a lot, too. I soon settled into the corner and looked around the room. It smelled of feces and vomit. It also had a characteristic Ebola smell to which I became accustomed. Dinner was served—rice and stew. The pepper stung my mouth and tongue. I dropped the spoon. No dinner that night.
Dr. David, the Caucasian man who had met me at the ambulance on my arrival, came in wearing his full protective hazmat suit and goggles. It was fascinating seeing one live. I had only seen them online. He brought bottles of water and ORS, the oral fluid therapy, which he dropped by my bedside. He told me that 90 percent of the treatment depended on me. He said I had to drink at least 4.5 litres of ORS daily to replace fluids lost in stooling and vomiting. I told him I had stooled three times earlier and taken Imodium tablets to stop the stooling. He said it was not advisable, as the virus would replicate the more inside of me. It was better, he said, to let it out. He said good night and left.
My parents called. My uncle called. My husband called crying. He could not believe the news. My parents had informed him, as I didn't even know how to break the news to him.
As I lay on my bed in that isolation ward, strangely, I did not fear for my life. I was confident that I would leave that ward some day. There was an inner sense of calm. I did not for a second think that I would be consumed by the disease.
That evening, the symptoms fully kicked in. I was stooling almost every two hours. The toilets did not flush, so I had to fetch water in a bucket from the bathroom each time I used the toilet. I then placed another bucket beneath my bed for the vomiting. On occasion, I would run to the toilet with a bottle of ORS, so that as I was stooling, I was drinking.
The next day, Monday, 4th of August, I began to notice red rashes on my skin, particularly on my arms. I had developed sores all over my mouth. My head was pounding so badly. The sore throat was so severe I could not eat. I could only drink ORS. I took paracetamol for the pain. The ward maid across from me wasn't doing so well. She had stopped speaking. I couldn't even brush my teeth; the sores in my mouth were so bad. This was a battle for my life but I was determined I would not die.
Every morning, I began the day with reading and meditating on Psalm 91. The sanitary condition in the ward left much to be desired. The whole Ebola thing had caught everyone by surprise. Lagos State Ministry of Health was doing its best to contain the situation but competent hands were few. The sheets were not changed for days. The floor was stained with greenish vomitus and excrement. Dr. David would come in once or twice a day and help clean up the ward after chatting with us. He was the only doctor who attended to us. There was no one else at that time. The matrons would leave our food outside the door. They hardly entered in the initial days. Everyone was being careful. This was all so new. I could understand, was this not how we ourselves had contracted the disease? Mosquitoes were in our room until they brought us mosquito nets.
Later that evening, Dr. David brought another lady into the ward. I recognized her immediately as Justina Ejelonu, a nurse who had started working at First Consultants on the 21st of July, a day after Patrick Sawyer was admitted. She was on duty on the day Patrick reported that he was stooling. While she was attending to him that night, he had yanked off his drip, letting his blood flow almost like a tap onto her hands. Justina was pregnant and was brought into our ward bleeding from a suspected miscarriage. She had been told she was there only on observation. The news that she had contacted Ebola was broken to her the following day after results of her blood test came out positive. Justina was devastated and wept profusely—she had contracted Ebola on her first day at work.
My husband started visiting but was not allowed to come close to me. He could only see me from a window at a distance. He visited so many times. It was he who brought me a change of clothes and toiletries and other things I needed because I had not even packed a bag. I was grateful I was not with him at home when I fell ill or he would most certainly have contracted the disease. My retreat at my parents' home turned out to be the instrumentality God used to shield and save him.
I drank the ORS fluid like my life depended on it. Then I got a call from my pastor. He had been informed about my predicament. He called me every single day, morning and night, and he would pray with me over the phone. He later sent me a CD player, CDs of messages on faith and healing, and Holy Communion packs through my husband. My pastor, who also happens to be a medical doctor, encouraged me to monitor how many times I had stooled and vomited each day and how many bottles of ORS I had consumed. We would then discuss the disease and pray together. He asked me to do my research on Ebola since I had my iPad with me, and told me that he was also doing his study. He wanted us to use all relevant information on Ebola to our advantage. So I researched and found out all I could about the strange disease that had been in existence for 38 years. My research, my faith, and my positive view of life, the extended times of prayer, study and listening to encouraging messages boosted my belief that I would survive the Ebola scourge.
There are five strains of the virus, and the deadliest of them is the Zaire strain, which was what I had. But that did not matter. I believed I would overcome even the deadliest of strains. Infected patients who succumb to the disease usually die between 6 to 16 days after the onset of the disease from multiple organ failure and shock caused by dehydration. I was counting the days and keeping myself well-hydrated. I didn't intend to die in that ward.
My research gave me ammunition. I read that as soon as the virus gets into the body, it begins to replicate really fast. It enters the blood cells, destroys them and uses those same blood cells to aggressively invade other organs where they further multiply. Ideally, the body's immune system should immediately mount up a response by producing antibodies to fight the virus. If the person is strong enough, and that strength is sustained long enough for the immune system to kill off the viruses, the patient is likely to survive. If the virus replicates faster than the antibodies can handle, however, further damage is done to the organs. Ebola can be likened to multi-level, multi-organ attack, but I had no intention of letting the deadly virus destroy my system. I drank more ORS. I remember saying to myself repeatedly, "I am a survivor, I am a survivor."
I also found out that a patient with Ebola cannot be re-infected and they cannot relapse back into the disease as there is some immunity conferred on survivors. My pastor and I would discuss these findings, interpret them as it related to my situation and pray together. I looked forward to his calls. They were times of encouragement and strengthening. I continued to meditate on the Word of God. It was my daily bread.
Shortly after Justina came into the ward, the ward maid, Mrs. Ukoh, passed on. The disease had gotten into her central nervous system. We stared at her lifeless body in shock. It was a whole 12 hours before officials of WHO came and took her body away. The ward had become the house of death. The whole area surrounding her bed was disinfected with bleach. Her mattress was taken and burned.
To contain the frequent diarrhea, I had started wearing adult diapers, as running to the toilet was no longer convenient for me. The indignity was quite overwhelming, but I did not have a choice. My faith was being severely tested. The situation was desperate enough to break anyone psychologically. Dr. Ohiaeri also called us day and night, enquiring about our health and the progress we were making. He sent provisions, extra drugs, vitamins, Lucozade, towels, tissue paper; everything we needed to be more comfortable in that dark hole we found ourselves. Some of my male colleagues also had been admitted to the male ward two rooms away, but there was no interaction with them. We were saddened by the news that Jato, the ECOWAS protocol officer to Patrick Sawyer, who had also tested positive, had passed on days after he was admitted.
Two more females joined us in the ward; a nurse from our hospital and a patient from another hospital. The mood in the ward was solemn. There were times we would be awakened by the sudden, loud cry from one of the women. It was either from fear, pain mixed with the distress, or just the sheer oppression of the isolation.
I kept encouraging myself. This could not be the end for me. Five days after I was admitted, the vomiting stopped. A day after that, the diarrhea ceased. I was overwhelmed with joy. It happened at a time I thought I could no longer stand the ORS. Drinking that fluid had stretched my endurance greatly.
I knew countless numbers of people were praying for me. Prayer meetings were being held on my behalf. My family was praying day and night. Text messages of prayers flooded my phone from family members and friends. I was encouraged to press on. With the encouragement I was receiving, I began to encourage the others in the ward. We decided to speak life and focus on the positive.
I then graduated from drinking only the ORS fluid to eating only bananas, to drinking pap and then bland foods. Just when I thought I had the victory, I suddenly developed a severe fever. The initial fever had subsided four days after I was admitted, and then suddenly it showed up again. I thought it was the Ebola. I enquired from Dr. David, who said fever was sometimes the last thing to go, but he expressed surprise that it had stopped only to come back on again. I was perplexed.
I discussed it with my pastor, who said it could be a separate pathology and possibly a symptom of malaria. He promised he would research if indeed this was Ebola or something else. That night as I stared at the dirty ceiling, I felt a strong impression that the new fever I had developed was not as a result of Ebola but malaria. I was relieved. The following morning, Dr. Ohiaeri sent me an antimalarial medication, which I took for three days. Before the end of the treatment, the fever had disappeared.
I began to think about my mother. She was under surveillance along with my other family members. I was worried. She had touched my sweat. I couldn't get the thought off my mind. I came across a tweet by WHO saying that the sweat of an Ebola patient cannot transmit the virus at the early stage of the infection. The sweat could only transmit it at the late stage.
That settled it for me. It calmed the storms that were raging with me concerning my parents. I knew right away it was divine guidance that caused me to see that tweet. I could cope with having Ebola, but I was not prepared to deal with a member of my family contracting it from me.
Soon, volunteer doctors started coming to help Dr. David take care of us. They had learned how to protect themselves. Among the volunteer doctors was Dr. Badmus, my consultant in LUTH during my housemanship days. It was good to see a familiar face among the care-givers. I soon understood the important role these brave volunteers were playing. As they increased in number, so did the number of shifts increase and subsequently the number of times the patients could access a doctor in one day. That allowed for more frequent patient monitoring and treatment. It also reduced care-giver fatigue. It was clear that Lagos State was working hard to contain the crisis.
Sadly, Justina succumbed to the disease on the 12th of August. It was a great blow and my faith was greatly shaken as a result. I commenced daily Bible study with the other two female patients and we would encourage one another to stay positive in our outlook, though in the natural it was grim and very depressing. My communion sessions with the other women were very special moments for us all.
On the 10th day in the ward, the doctors having noted that I had stopped vomiting and stooling and was no longer running a fever, decided it was time to take my blood sample to test if the virus had cleared from my system. They took the sample and told me that I shouldn't be worried if it comes out positive as the virus takes a while before it is cleared completely. I prayed that I didn't want any more samples collected from me. I wanted that to be the first and last sample to be tested for the absence of the virus in my system. I called my pastor. He encouraged me and we prayed again about the test.
On the evening of the day Justina passed on, we were moved to the new isolation centre. We felt like we were leaving hell and going to heaven. We were conveyed to the new place in an ambulance. It was just behind the old building. Time would not permit me to recount the drama involved with the dynamics of our relocation. It was like a script from a science fiction movie. The new building was cleaner and much better than the old building. Towels and nightwear were provided on each bed. The environment was serene.
The following night, Dr. Adadevoh was moved to our isolation ward from her private room where she had previously been receiving treatment. She had also tested positive for Ebola and was now in a coma. She was receiving IV fluids and oxygen support and was being monitored closely by the WHO doctors. We all hoped and prayed that she would come out of it. It was so difficult seeing her in that state. I could not bear it. She was my consultant and my mentor. She was the imperial lady of First Consultants, full of passion, energy and competence. I imagined she would wake up soon and see that she was surrounded by her First Consultants family but sadly it was not to be.
I continued listening to my healing messages. They gave me life. I literally played them hours on end. Two days later, on Saturday the 16th of August, the WHO doctors came with some papers. I was informed that the result of my blood test was negative for the Ebola virus. If I could somersault, I would have, but my joints were still slightly painful. I was free to go home after being in isolation for exactly 14 days. I was so full of thanks and praise to God. I called my mother to get fresh clothes and slippers and come pick me up. My husband couldn't stop shouting when I called him. He was completely overwhelmed with joy.
I was told however that I could not leave the ward with anything I came in with. I glanced one last time at my CD player, my valuable messages, my research assistant, a.k.a my iPad, my phones and other items. I remember saying to myself, "I have life; I can always replace these items."
I went for a chlorine bath, which was necessary to disinfect my skin from my head to my toes. It felt like I was being baptized into a new life as Dr. Carolina, a WHO doctor from Argentina poured the bucket of chlorinated water all over me. I wore a new set of clothes, following the strict instructions that no part of the clothes must touch the floor and the walls. Dr. Carolina looked on, making sure I did as instructed.
I was led out of the bathroom and straight to the lawn to be united with my family, but first I had to cut the red ribbon that served as a barrier. It was a symbolic expression of my freedom. Everyone cheered and clapped. It was a little but very important ceremony for me. I was free from Ebola! I hugged my family as one who had been liberated after many years of incarceration. I was like someone who had fought death face to face and come back to the land of the living.
We had to pass through several stations of disinfection before we reached the car. Bleach and chlorinated water were sprayed on everyone's legs at each station. As we made our way to the car, we walked past the old isolation building. I could hardly recognize it. I could not believe I slept in that building for 10 days. I was free! Free of Ebola. Free to live again. Free to interact with humanity again. Free from the sentence of death.
My parents and two brothers were under surveillance for 21 days and they completed the surveillance successfully. None of them came down with a fever. The house had been disinfected by Lagos State Ministry of Health soon after I was taken to the isolation centre. I thank God for shielding them from the plague.
My recovery after discharge has been gradual but progressive. I thank God for the support of family and friends. I remember my colleagues who we lost in this battle. Dr. Adadevoh my boss, Nurse Justina Ejelonu, and the ward maid, Mrs. Ukoh were heroines who lost their lives in the cause to protect Nigeria. They will never be forgotten.
I commend the dedication of the WHO doctors, Dr. David from Virginia, USA, who tried several times to convince me to specialize in infectious diseases, Dr. Carolina from Argentina who spoke so calmly and encouragingly, Mr. Mauricio from Italy who always offered me apples and gave us novels to read. I especially thank the volunteer Nigerian doctors, matrons and cleaners who risked their lives to take care of us. I must also commend the Lagos State government, and the state and federal ministries of health for their swift efforts to contain the virus.

To all those who prayed for me, I cannot thank you enough. And to my First Consultants family, I say a heartfelt thank you for your dedication and for your support throughout this very difficult period.
I still believe in miracles. None of us in the isolation ward was given any experimental drugs or so-called immune boosters. I was full of faith, yet pragmatic enough to consume as much ORS as I could, even when I wanted to give up and throw the bottles away. I researched on the disease extensively and read accounts of the survivors. I believed that even if the mortality rate was 99 percent, I would be part of the 1 percent who would survive.
Early detection and reporting to hospital is key to patient survival. Please do not hide yourself if you have been in contact with an Ebola patient and have developed the symptoms. Regardless of any grim stories one may have heard about the treatment of patients in the isolation centre, it is still better to be in the isolation ward with specialist care, than at home where you and others will be at risk.
I read that Dr. Kent Brantly, the American doctor who contracted Ebola in Liberia and was flown out to the United States for treatment was being criticized for attributing his healing to God when he was given the experimental drug, Zmapp. I don't claim to have all the answers to the nagging questions of life. Why do some die and some survive? Why do bad things happen to good people? Where is God in the midst of pain and suffering? Where does science end and God begin? These are issues we may never fully comprehend on this side of eternity. All I know is that I walked through the valley of the shadow of death and came out unscathed.
Beyond the Plow
4 innovations for poor farmers
Four new tools that are helping poor farmers grow more food.
Whenever I visit small farmers in a poor country, I’m struck by how many are laboring with hoes, plows, and other implements that haven’t changed in generations. Yet farmers in wealthier countries have benefited from wave after wave of technological improvements. This gap is one big reason why some farmers produce much more food than others.
Thankfully, some of the brightest minds in Africa, India, and elsewhere are creating new tools to close the gap.
Here are four especially promising innovations…
For many years, so little agriculture research was being done in Africa that we knew less about the soil there than we did about the surface of Mars. Now that’s changing, thanks to an initiative to map the continent’s soil. The Africa Soil Information Service is creating digital maps that help farmers make informed decisions about which seeds to plant, which fertilizers to use, and how to raise their crop yields. They’re available free to anyone with a cell phone or Internet connection.
In Africa, half a billion people depend on cassava as a staple crop. But breeding more-nutritious, disease-resistant varieties of the root takes a long time—a decade or more. Now scientists with the Next Generation Cassava Breeding (NEXTGEN) project have cut that time in half, using computer modeling techniques and a treasure trove of new information on the plant’s genome. They have also improved the breeding cycle, so they can zero in on the most desirable traits earlier in the process.
How do you cheaply spread good information about farming? The Indian nonprofit Digital Green is having success with simple YouTube videos. They’ve shot thousands of videos featuring farmers sharing best practices. (See for yourself.) Farmers, they’ve found, are much more likely to listen to peers who look and sound like them. The idea isn’t limited to farming either: The UK’s development agency is now helping Digital Green use its platform to spread health messages.
Being a dairy farmer has risks. As I learned on a trip to Kenya, milk can spill or spoil on its way from the cow to the chilling station. So I asked the team at Global Good to study the problem. Working with Heifer International, they made a jug that’s easy to clean and won’t spill. Partners in Kenya and Ethiopia will make and sell them for about $5 each, versus up to $30 for other jugs. This modest step could help dairy farmers earn more money—and create new manufacturing and sales jobs too.
Cornell’s Corn
The love life of plants
Studying the love life of plants could help millions escape poverty.
Of all the things I did when I visited Cornell University recently, I probably had the most fun brushing up on how plants have sex.
Cornell is one of the world’s top universities for research on improving crops. Their work involves a lot of plant breeding. During one meeting, I got to try my hand at cross-pollinating wheat, which is a surprisingly delicate procedure. It gave me even more respect for the people who do it every day.
Cornell’s work on crop improvement also involves a lot of cutting-edge genetics. You might see the words “crop improvement” and “genetics” in the same sentence and think I’m talking about GMOs. Although Melinda and I do support research in that area—we don’t think poor farmers should be denied the choice to use any tools that might benefit them—the work I saw at Cornell is different. It’s focused on how the science of genetics can improve agriculture in other ways. And the advances are really exciting.
I got interested in crop breeding through my work with the Gates Foundation. Because most of the world’s poor people are farmers, helping farmers grow more food is one of the most powerful levers we have for fighting poverty. The faster we can improve crops—making them more nutritious or drought-tolerant, for instance—the faster we can help farmers become more productive.
My main guide was Dr. Ed Buckler, a scientist in his mid 40s who works at Cornell for the U.S. Department of Agriculture (USDA). Over the four hours we spent together I asked Ed dozens of questions (I’ve learned a lot about agriculture, but I’m still a city boy at heart), and he was always quick with an answer. Yet Ed and his colleagues aren’t just experts in their field—they’re also deeply passionate about their work. I can see why: The advances they’re working on will change people’s lives by dramatically accelerating a process that is now slow and laborious.
Here’s how it works today. Suppose you want a variety of corn with a natural resistance to a certain pest. You start by planting as much corn as you can. You wait 8 to 12 weeks for it to grow, and then you take pollen from some of the plants that aren’t infested and use it to pollinate others. If the offspring of those plants is pest-resistant, you’re in luck—your plant won the genetic lottery. If not, you have to start over. Because you’re limited by the growing season, the process can take seven to ten years.
Genetics research will cut that time in half.
Getting there takes three steps. One is to understand the crop’s genetic makeup. Ed took me on a short tour of a lab where machines called sequencers were analyzing DNA from thousands of plants. They were mapping the genes that give each plant its physical traits: its height, color, etc.
The second step is to go into the field and record those physical traits for each individual plant whose genes you’re studying. Cornell researchers are growing hundreds of acres of corn and other crops not far from campus, and they make regular treks out there to collect data. Unfortunately, I didn’t have time for a field trip on this visit.
Finally, you build a computer model that puts the two together—the genetic maps of individual plants, along with the data about their physical traits. Once you have that model, you no longer need to cross two plants and just hope for the best. You can ask the computer, “Out of all the plants I have in my field, which two should I breed in order to produce one that is pest-resistant?” Think of it as a highly sophisticated Match.com for plants.
Cornell and the USDA have already built such a model for some traits in corn; because people in rich countries eat corn, there’s a big market for better varieties. Meanwhile, crops that are eaten mostly by the poor have largely been ignored by scientists. But that’s starting to change.
With support from the British government, our foundation, and others, researchers at Cornell and the USDA are now working on a model for cassava, a root vegetable that’s a staple crop in many tropical regions. Partners in Uganda and Nigeria are growing lots of plants, recording their traits, and sending genetic samples to Cornell for sequencing. When the cassava model is finished, it will help breeders develop new varieties faster than ever. (Incidentally, I’m fascinated by cassava—and you may not know that it is responsible for the fun factor in bubble tea.)

During my visit, I learned about one trait that I had never thought about before: poundability. Over lunch with several graduate students, a Ugandan researcher named Paula Iragaba told me that women in her country do most of the work to turn cassava into flour, and they wish it were easier to process. “Women’s preferences have to be taken into account,” she said. I couldn’t agree more.
Keep in mind, none of the genetics research I saw changes the basics of plant sex. Breeders in the field still have to move pollen from one plant to another, as they have for ages. We’re just getting a lot smarter about helping them pick the best partners. And the result will be phenomenal—a much faster path to more-productive crops so that millions of people can eat better food, earn more money, and improve their lives.
An Eye for Innovation
From idea to reality
A reminder from two young Aussies about what it takes to innovate.
There are two reasons I want to tell you about the pair of bright young people I met earlier this month. First, because they’re working on a project that could be a real life-saver in the developing world. And second, because the way they’re going about it is a great example for anyone who’s trying to turn an idea into reality.
Jarrel Seah and Jennifer Tang are medical students at Monash University in Australia who share a passion for technology. The 22-year-olds teamed up late last year to create an app called Eyenaemia, which lets people use their cell phone to screen for anemia. As the winners of this year’s Imagine Cup, a competition run by Microsoft, they visited the Seattle area and stopped by my office to talk about their work.
Anemia affects some 2 billion people around the world, and more than 290 million children. It’s an awful condition—you’re exhausted, your heart beats erratically, you get dizzy—and while it’s often caused by a lack of iron in your diet, it can also be a symptom of serious illnesses like malaria and bowel cancer. Jarrel told me, “In Australia’s aboriginal indigenous communities, over half of young children are anemic. And a large percentage of that is actually due to helminth infections—hookworms.”
Diagnosing anemia isn’t always easy. One method requires drawing blood and running lab tests, which simply isn’t possible in a lot of poor areas. And the cheapest test is very imprecise: A doctor pulls down your eyelid and checks the underside to see if it looks pale.
Eyenaemia is designed to take out both the expense and the guesswork. It lets you take a photo of the underside of your eyelid and then, judging by the color, tries to tell whether you’re anemic. “What's different about this is it’s noninvasive,” Jennifer said. “You don't need all that sterile equipment, and an untrained user can use it.” (Their idea is part of a promising trend: Researchers are studying whether cell phones can reduce the need for lab tests by detecting pneumonia, HIV, TB, and other conditions.)
It’s exciting to see bright young people like Jennifer and Jarrel applying their talents to problems that disproportionately affect the poor. As I told them, I could see a future version of Eyenaemia being used in developing countries, especially with pregnant women, since anemia contributes to nearly 20 percent of deaths during pregnancy.
So the tool has real promise. But Jennifer and Jarrel aren’t under any illusions. They know that having a great idea—“screen for anemia with a cell phone”—was only the beginning. In the early stages, they had a lot to learn: They went online to read up on design and cloud computing, which they didn’t know much about. Now the challenge is different. They have to keep improving their work.
We spent a lot of time talking about how they want to do that. For example, “We still have a high false positive rate,” Jarrel said. They’re looking at ways to bring it down by adding in factors like the patient’s age and gender, which they suspect affect the results by changing the color of the eyelid.
The idea that you have to keep refining your work might seem like old hat to a scientist who has spent decades perfecting a vaccine. Or to a software developer: When I was at Microsoft, we were maniacal about constantly learning from our customers and improving our products. But Jennifer and Jarrel’s efforts serve as a good reminder, especially for young people who are just getting started. Although innovation begins with a great idea, it certainly doesn’t end there.
John Green in Ethiopia
“It was invigorating and encouraging. And sad.”
The bestselling author reflects on our visit to Ethiopia.
I was playing bocce with a close friend recently when he told me, “I can’t bring myself to watch any of your videos about Ethiopia.”
Now, I don’t care if my friends watch my videos or read my books; I don’t know much about their jobs and don’t expect them to know much about mine. But the specificity of the comment surprised me, so I asked him why, and he said, “Well, it’s all just so SAD.”
I understand it: It’s difficult to look directly at suffering. And the challenges of our own lives can be so overwhelming that at times it feels like there’s no room left to consider the vast and tangled challenges of absolute poverty. We have to look away. “It’s too much,” my friend said.
But my visit to Ethiopia wasn’t sad—at least not merely so. It was invigorating and encouraging. And sad. And by being unable to look away—at least for a short time—I had the opportunity to listen to extraordinary people who’d brought tremendous positive change to Ethiopia.
The successes of the past twenty years are truly unprecedented in human history: Child mortality in Ethiopia has dropped by two thirds. Agricultural yields are improving. More kids are in school, and more of those kids go on to attend college.
Those are all very encouraging developments, but for narratively oriented people like me, it can be hard to internalize statistics until you see what this change looks like for individuals and families. At the rural health care outposts I visited, women told me about how radically the health care options for their children had improved. It was easier to get vaccines and antibiotics and rehydration solutions. Fewer of their kids were dying of malaria and pneumonia. Better family planning options allowed them to make choices about when to have kids. And while every mother I spoke to had been born at home, almost all of their kids had been born in a health care facility.
Maternal death is still far too common in Ethiopia, and infant mortality is still far too high. Ethiopia is a nation of 90 million people with just seven neonatologists. There are no CT scanners or MRI machines. Most of the people I met walked for miles twice a week to get water. And people die, every day, of easily preventable and treatable illnesses. But Ethiopia is also a nation with a growing middle class and an increasingly educated population (the University of Addis Ababa now has more than 40,000 students).
When we assume that stories about developing world countries will be merely sad, we do ourselves a great disservice, because the truth—as Oscar Wilde put it—is rarely pure and never simple. I emerged from my time in Ethiopia feeling not discouraged but energized. I was energized by people like Bill Gates and Sue Desmond-Hellmann, whose focus and commitment were inspiring. But mostly, I was energized by the parents and students and health workers I met in Ethiopia, who have helped bring radical improvement to their communities. There is, of course, so much still to do. But we shouldn’t look away or feel discouraged. We should get to work.
On the Subcontinent
Going—and listening—to India
What Melinda and I hope to discuss with the country’s leaders when we visit.
Melinda and I will visit India later this month. I’ve been there many times over the years, but I’m especially excited about this trip.
For one thing, India has reached some remarkable milestones in health. Earlier this year, the country was officially declared free of the polio virus for the first time ever, which is a huge accomplishment not only for India but for the global effort to eradicate the disease. Now India is starting to roll out its first home-grown vaccine, which protects children from rotavirus—a disease that each year kills more than 100,000 children in India and 400,000 worldwide. Overall, childhood deaths there have dropped by more than 50 percent since 1990.
All this adds up to a pivotal moment for India: If the country seizes the opportunity to improve health even more, especially for its poorest citizens, it can help hundreds of millions of people improve their lives and share in the country’s prosperity.
On our trip, Melinda and I will get to meet with several government leaders. We plan to do a lot of listening. Prime Minister Modi has made key commitments in some areas where our foundation works, like improving the health of women and girls, giving more people access to toilets, and expanding banking services to the poor. We hope to talk with India’s leaders about how we might help accomplish some of their goals.
Take India’s amazing efforts to fight child mortality. Along with the Health Minister, we will help launch a new plan for saving newborn lives by reaching every mother and baby with basic services. We’ll also see the leaders of Bihar and Uttar Pradesh, two of the poorest regions in India, for updates on efforts to strengthen the health systems there. We’re learning a lot through our partnerships there and hope they will ultimately serve as a model in other developing countries.
Sanitation is another priority. The Prime Minister has called for ending open defecation by 2019. Today some 630 million people in India—roughly half the country’s population—don’t have access to a toilet. That has terrible consequences: Poor sanitation will leave 62 million Indian children too sick to reach their physical and mental potential. It’s a tough challenge that requires building new infrastructure, developing new ways to handle waste, and persuading people to change longstanding hygiene habits. Among other things, our foundation co-hosted a Reinvent the Toilet Fair in India earlier this year, and it will be great to talk with the leaders there about how we can work together even more.
A third big goal of India’s is to extend banking services to every household in the country by next August. Giving poor families a safe place to save their money is one of the most effective ways to help them move out of poverty, but right now, fewer than half of Indian adults have access to a bank account. Our foundation’s work on reaching the unbanked puts a special focus on using digital technology, so we’ll be discussing that in detail.
No matter how many times I travel to India, I always come home impressed by the energy, intellect, and innovation I see there. I’m sure this time will be no different. I’ll post a few thoughts about the trip after we get home.
Africa’s Table
Why does hunger still exist in Africa?
Not starving, but still hungry in Africa.
When I first started traveling to Africa, I would often meet children in the villages I was visiting and try to guess their ages. I was shocked to find out how often I guessed wrong. Kids I thought were 7 or 8 years old based on how tall they were—would tell me that they were actually 12 or 13 years old.
What I was witnessing was the terrible impact of malnutrition in Africa. These children were suffering from a condition known as stunting. They were not starving, but they were not getting enough to eat, leaving them years behind in their development—and it was hard to see how they could ever catch up.

Stunting not only affects a child’s height. It also has an impact on brain development. Stunted children are more likely to fall behind at school, miss key milestones in reading and math, and go on to live in poverty. When stunted children don’t reach their potential, neither do their countries. Malnutrition saps a country’s strength, lowering productivity and keeping the entire nation trapped in poverty.
Worldwide, one in four children is stunted. Three-quarters of them live in South Asia and sub-Saharan Africa. However, while stunting has declined by more than a third in South Asia since 1990, in sub-Saharan Africa, the number of stunted children is still on the rise, up 12 million since 1990 to 56 million. Forty percent of all children in sub-Saharan Africa are stunted.
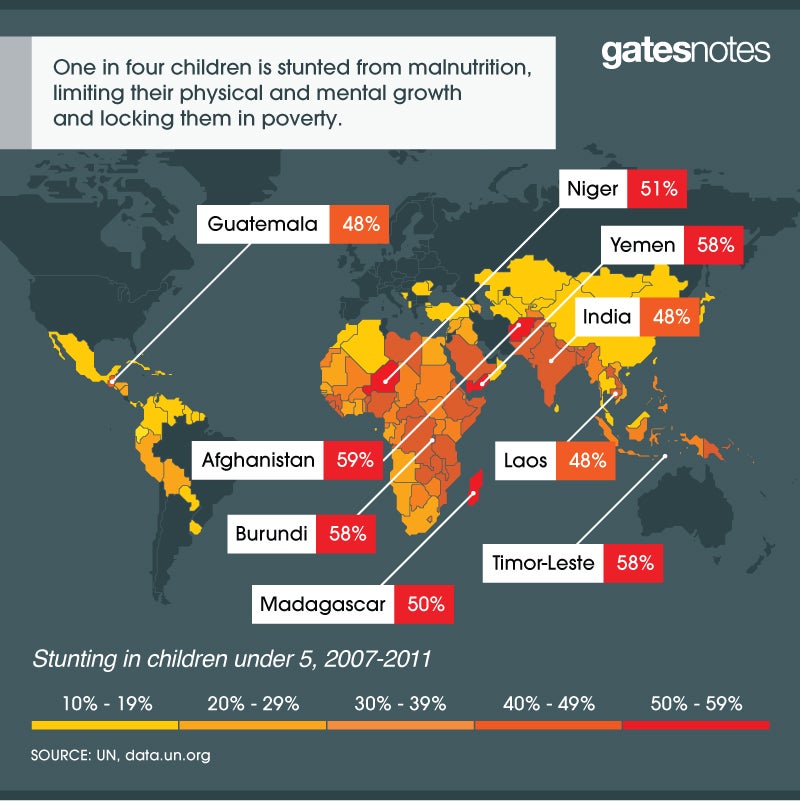
I run into a lot of people from rich countries who still think of Africa as a continent of starvation. The fact is, that’s an outdated picture (to the extent that it was ever accurate at all). Thanks to economic growth and smart policies, the extreme hunger and starvation that once defined the continent are now rare. As I saw when I was back in Africa last month with best-selling author John Green, today the issue isn’t quantity of food as much as it is quality—whether kids are getting enough protein and other nutrients to fully develop.
As Melinda and I have grown aware of the scale of this challenge, we’ve made improving nutrition a bigger priority for our foundation. One thing we’ve quickly come to appreciate is the problem’s complexity. There’s no vaccine to prevent stunting. Proper nutrition involves eating enough food, and the right kinds, every day of your life. While the global health community is still working to understand all of the causes and solutions to malnutrition, we do know a lot about how to ensure children get the nutrition they need for a healthy start to life.
We know that getting children the right nutrition in the first 1000 days—from the start of a woman’s pregnancy until her child’s 2nd birthday – is the best down payment on their future, giving them the opportunity to grow and develop physically and mentally. We also know that exclusive breastfeeding in the first six months of a child’s life is the single most effective intervention to help the brain develop and protect against life-threatening diseases. That’s why we continue to research the best ways to address cultural beliefs and other barriers that have kept almost half of all women from using optimal breastfeeding practices.
We know kids have a hard time getting the nutrients they need when fruits, meats, and vegetables are in short supply—so fortifying staple foods like cooking oil, flour, and salt with essential vitamins and minerals can fill the gap. We’re also beginning to develop new crops that are more-nutritious--including a sweet potato that’s enriched with vitamin A—and also produce a higher yield. Not only does this help smallholder farmers earn more income that can be used to diversify their family’s diet, it also puts more nutritious food directly on their table.
Providing better health care can make a difference too. Children who receive the rotavirus vaccine, for example, have fewer bouts of diarrhea, which can drain kids of vital nutrients and make them more susceptible to infection. Likewise, clean water and sanitation play a role in improving nutrition by reducing illness and disease.
We have many great interventions on our side, but with so many factors at play it can be difficult to measure which interventions have the most impact on improving nutrition and why. If I could have one wish, I would want the world to have a better understanding of malnutrition and how to solve it.
We have much more research to do in this area and we will continue to make progress. But what’s not in doubt is the importance of giving all children the nutrition they need for a healthy start to life. Their future depends on it. So does Africa’s.
Mosquito Week
“Mosquitoes are smart. We have to be smarter.”
A Tanzanian scientist on the front lines of the malaria fight.
One of the things I love most about my work in global health is getting to meet with amazing scientists who are trying to save lives. For Mosquito Week I thought I would introduce you to one of them: Dr. Prosper Chaki, whom I met in Tanzania in 2011.
Dr. Chaki runs a project in Dar es Salaam designed to kill Anopheles mosquito larvae. He spends his days wading into ponds, puddles, and marshes, spreading a biological insecticide in the areas where mosquitoes breed. His project has helped dramatically reduce malaria cases in the city. “Mosquitoes are smart,” Dr. Chaki told me. “We have to be smarter.”
He is just one of thousands of innovative researchers around the globe designing new and better ways to fight malaria. Thanks to their efforts the world is making progress against the disease.
You can learn more about how we’re getting smarter in our fight against malaria by watching this video about Dr. Chaki’s work.
Mosquito Week
What It Takes to Wipe Out Malaria
My visit to Cambodia, which is trying to eliminate the disease for good.
Many tourists know Siem Reap, Cambodia, as the base for exploring the beautiful 12th-century ruins at Angkor Wat. But when Melinda and I stopped there last week, we weren’t thinking about visiting a historic site. In fact we may have been the first visitors who ever passed through Siem Reap and skipped the temples completely.
We were on our way to see another piece of history in the making—Cambodia’s effort to eliminate malaria from within its borders. What we saw may eventually point the way toward a goal that’s shared by many of us in the global health community: eradicating malaria.
Malaria is one of the biggest killers of children on the planet, and Cambodia has made phenomenal progress fighting it over the past decade or so. Deploying an army of more than 3,000 village malaria workers who administer tests, give out medicine, and distribute bednets, they have reduced malaria from about 130,000 cases in 2000 to about 2,000 in 2012. Now the goal is to build on this progress by wiping out malaria entirely within Cambodia.
From Siem Reap, Melinda and I traveled to the remote province of Pailin in western Cambodia, near the border with Thailand, where researchers are running a pilot project to explore the best way to eliminate malaria.
They face a number of obstacles in their work. One is a kind of arms race, as drug-resistant strains of the malaria parasite keep emerging. For reasons that are not entirely clear, some of the most effective drugs against malaria have been rendered useless in Cambodia. There’s the potential for a real nightmare scenario here. If a strain of malaria that’s resistant to artemisinin were to spread to Africa—where artemisinin is the most commonly used anti-malarial drug—it would be the worst disaster ever in malaria control. But if we can eliminate malaria in Cambodia, we can not only save the lives of Cambodians, we can also prevent any new drug-resistant strains from developing and spreading to other places.
Another obstacle to eliminating malaria is that people can be infected by the parasite without showing any symptoms. Because the parasite is in their blood, they can transmit it to other people via mosquitoes, and those people can get very sick or die. The parasite is sort of like a James Bond villain who finds a secret lair from which he can carry out his deadly plot, undetected. So we need to treat everyone who’s infected, even if they don’t look or feel sick.
The project in Pailin is designed to try to get over these obstacles. The idea is to test everyone in the community to see who’s carrying the parasite and how much of it they’re carrying. Anyone who tests positive is given free treatment with the latest drugs. Here’s a video where I explain how it works:
Of course, there are downsides to this approach. People who don’t feel sick can be reluctant to get tested or take medicine. It’s also hard to keep people participating in the project, because they have to give blood every three months. So it was great to hear that Pailin’s village malaria workers, who have spent years building up trust in the community, are helping the project get over these hurdles.
Melinda and I met one of them, a man named Long Vuthy. He has been a village malaria worker since 2003 and is also the village leader. He told us he decided to join the program after watching the disease devastate his community. He proudly showed us his malaria kit—a tackle box containing tests, medications, and a log book where he records each case he encounters.
After meeting Mr. Vuthy, we walked to a local school where the screening is taking place. That morning, about 120 people had come to get their blood drawn and tested for the malaria parasite. They also answered a few questions designed to find out whether they might have been exposed to the parasite (e.g., “Do you work in the forest?”). For their trouble, they were paid a day’s wages, the equivalent of about $2.50, and got a free lunch.
As you might imagine, a project this involved would be hard to scale up using the drugs and diagnostics we have today. For example, the blood samples have to be shipped 250 miles to a lab in Bangkok that can run more-sensitive tests; that’s one reason our foundation is investing in a highly sensitive test that could be used in the field. We’re also funding research on new drugs that would cure malaria with one dose instead of the several doses now required. The fewer the doses, the more likely it is that patients will take all of them, and the more likely that the parasite will be killed off completely, which prevents drug resistance.
A lot more work needs to be done in the years to come. But I left Cambodia thinking that if we can be successful there, it will be a giant step toward the long-term goal of wiping out malaria everywhere.
Mosquito Week
The deadliest animal in the world
Sharks are wimps, compared to this beast.
What would you say is the most dangerous animal on Earth? Sharks? Snakes? Humans?
Of course the answer depends on how you define dangerous. Personally I’ve had a thing about sharks since the first time I saw Jaws. But if you’re judging by how many people are killed by an animal every year, then the answer isn’t any of the above. It’s mosquitoes.
When it comes to killing humans, no other animal even comes close. Take a look:
What makes mosquitoes so dangerous? Despite their innocuous-sounding name—Spanish for “little fly”—they carry devastating diseases. The worst is malaria, which kills more than 600,000 people every year; another 200 million cases incapacitate people for days at a time. It threatens half of the world’s population and causes billions of dollars in lost productivity annually. Other mosquito-borne diseases include dengue fever, yellow fever, and encephalitis.
There are more than 2,500 species of mosquito, and mosquitoes are found in every region of the world except Antarctica. During the peak breeding seasons, they outnumber every other animal on Earth, except termites and ants. They were responsible for tens of thousands of deaths during the construction of the Panama Canal. And they affect population patterns on a grand scale: In many malarial zones, the disease drives people inland and away from the coast, where the climate is more welcoming to mosquitoes.
Considering their impact, you might expect mosquitoes to get more attention than they do. Sharks kill fewer than a dozen people every year and in the U.S. they get a week dedicated to them on TV every year. Mosquitoes kill 50,000 times as many people, but if there’s a TV channel that features Mosquito Week, I haven’t heard about it.
That’s why we’re having Mosquito Week on the Gates Notes.
Everything I’m posting this week is dedicated to this deadly creature. You can learn about my recent trip to Indonesia to see an ingenious way to combat dengue fever by inoculating not people, but mosquitoes. (Somehow this story involved me offering up my bare arm to a cage full of hungry mosquitoes so they could feed on my blood.) You can read a harrowing account of what it’s like to have malaria and hear from an inspiring Tanzanian scientist who’s fighting it. And I’ve shared a few thoughts from Melinda’s and my recent trip to Cambodia, where I saw some fascinating work that could point the way to eradicating malaria, which would be one of the greatest accomplishments in health ever.
I hope you’ll have a look around. I can’t promise that Anopheles gambiae will be quite as exciting as hammerheads and Great Whites. But maybe you’ll come away with a new appreciation for these flying masters of mayhem.
Mosquito Week
What It Feels Like to Have Malaria
How the disease saps human potential.
Search the Web for “what it feels like to have malaria” and you will find a lot of harrowing descriptions.
Here’s an especially gripping one:
I awoke to what felt like lightning going through my legs, and then spreading through my body and in my head. Probably the worst headache, body aches, and chills you could possibly imagine. It felt like I was being stung repeatedly by an electric shock gun and could barely control my movements. The pain was so intense; I actually believed I was dying, literally crying out in pain so bad that I was taken to a 24 hour clinic that night at 3am.
Imagine feeling like that and trying to go to school, work, or take care of your family. It would be impossible.
It’s no surprise that economic growth in countries with severe malaria is significantly lower than in countries without it, even after accounting for other factors. As the economists Jeffrey Sachs and John Luke Gallup have written, “The only parts of Africa free of malaria are the northern and southern extremes, which have the richest countries on the continent.” Malaria is far from the only cause of poverty—but it is a significant one.
Whenever someone asks me why we should fight malaria, I have a simple answer: Because it kills so many people (more than 600,000 every year), and it leaves so many more people too sick to function, which holds back the world’s poorest from making the most of their lives. Malaria is gone from the United States and Europe. But where it is still a problem, few diseases do more to limit human potential.
This may all sound hopeless, but I’m actually optimistic that we can eventually eradicate malaria. I wrote about why here. I hope you’ll take a look.
Tax-Day Blues?
A reason to smile on April 15
A reason to smile on April 15.
There can’t be many days that are less popular than April 15. But I want to remind you of a fact that might ease the pain: The income taxes you’re paying will save lives in poor countries.
If your family makes the U.S. median household income of roughly $51,000, together you will buy someone in a poor country about seven months’ worth of HIV treatment. Or provide a lifesaving vaccine for 48 children. Or buy eight bednets that will protect people from mosquitoes that cause malaria.
These numbers might make you wonder if a large portion of your income taxes goes to foreign aid. After all, seven months of AIDS treatment can’t be cheap. You wouldn’t be alone in wondering this: Polls show that Americans tend to think nearly a quarter of the budget goes to aid.
It turns out that foreign aid is just 1 percent of the federal budget, or about $30 billion a year. Another way to think about it is that just 1 percent of your income taxes goes to foreign aid.
Compare that to other items in the budget. Defense for example is 17 percent, or more than $1,500 out of the median household’s income tax bill.
I believe that if more people knew what a small share of the budget goes to these programs, and how effective these programs are at saving lives, they’d want to do even more.
April 15 will never be anyone’s idea of a fun day, but I hope it helps to remember how much good American aid is doing around the world.
Maintaining Aid
Why I high-fived a colleague in Paris
Why I high-fived a colleague in Paris.
I don’t generally do a lot of high-fives. But as I climbed into the car after meeting with President Hollande in Paris this week, I held up my hand and slapped palms with one of my fellow passengers.
We were both celebrating and feeling relieved. Just a few hours before, it had seemed unlikely that the meeting would happen at all. The president had just announced a major reorganization of his Cabinet, and I didn’t think he would have time to talk with me about French foreign aid, the subject of our meeting. And even if he did have time, I thought the president might tell me that there was no way his government could maintain its aid commitments in the years ahead. Although France has an amazing track record in this area (it’s the second-largest contributor to the Global Fund, for example), the federal budget is under a lot of pressure. They are facing cuts on the order of 50 billion euros over the next three years.
So I definitely appreciated it when the president decided to keep our meeting even with everything else he had going on. And I was quite encouraged when he told me, without being asked, that he’s going to do his best to preserve France’s commitments. Of course, neither of us is under any illusion about how tough the budget situation is. But it was great to hear the president talk about the impact of France’s support and pledge to try to maintain it.
Paris was the second of three stops on this trip. I had been to Stockholm the day before and would be taking a quick trip to London the next day. In each place I wanted to encourage political leaders and voters to maintain their commitments to foreign aid, even in tough economic times. I wanted to remind people of all the lives they are saving.
This is an important year for Sweden, with elections for the national government and the European Parliament coming up later this year. I was pleased to hear from leaders in the major parties that they want the country to keep playing a leading role in global health and development, no matter how the election turns out. I had an especially productive meeting with Finance Minister Anders Borg, who oversees Sweden’s aid-related programs. He’s so interested in the work that he travels to Africa to learn and see the impact first-hand. We discussed some innovative ideas about how Sweden could take a leading role in funding infrastructure projects, like roads, in Africa. Improving its infrastructure is one of the keys to the continent’s growth in the coming decades, so I hope donors step up with creative funding ideas.
In Stockholm I also had a great time at an event hosted by one of my favorite global health experts, Hans Rosling, and three of his colleagues. Hans is unmatched in his ability to get you excited about the topic while also teaching you something. While I was there we shot a video about vaccination rates that involves me pouring orange juice out of a pitcher. (It will make sense when you see it, I promise.)
In London I got to visit Deputy Prime Minister Nick Clegg and thank him and Prime Minister David Cameron for committing to spend 0.7 percent of the country’s GDP on foreign aid. The U.K. reached that milestone last year, and they’ve said they want to maintain this level. The impact is phenomenal. For example the U.K. supports the GAVI Alliance, which provides vaccines that prevent millions of children’s deaths each year.
I also met with the CEOs of major pharmaceutical companies. We’ve gotten together every year for the past five to talk about the work they’re doing on diseases that affect the poor; I especially want to hear about the obstacles they’re running into and how we can work together to overcome them. This week we marked exciting progress on much faster tests and treatments for sleeping sickness (a.k.a. human African trypanosomiasis), which threatens millions of people in sub-Saharan Africa—during epidemics, it has been known to overtake HIV/AIDS as a leading cause of death in some communities. These advances make it possible for the first time to imagine eliminating this terrible disease. In fact I helped announce $240 million in new funding to treat neglected tropical diseases, including sleeping sickness.
I’ll close by sharing this selfie I took in Paris with a few Youth Ambassadors from the ONE Campaign. They’re part of a program that ONE started in Germany and is now taking to other countries to help keep foreign aid on the agenda. It’s always energizing to meet young people who are so enthusiastic about saving lives. Even on a trip where I heard a lot of a good news, they left me feeling especially optimistic.
Toilet Talk
The next great market opportunity: sanitation for India’s poor
To address a health crisis, India, hosted a Reinvent the Toilet fair.
If you’re inclined to take your toilet for granted, consider this. Half of all patients in hospitals in developing countries are there because of problems with water and sanitation. It’s a staggering health crisis that demands new ideas and new approaches. Last week we saw an encouraging sign that the sanitation issue is starting to get the traction it deserves: Delhi, India, hosted its first Reinvent the Toilet fair.
One problem is that flush toilets are impractical for billions of people. They require vast amounts of water and connections to expensive infrastructure, like sewer systems. Unfortunately, the current-day toilet works just well enough for rich people that no one seems to see the market for a new-and-improved toilet. That’s why we have been working with innovators from dozens of countries to reinvent the toilet so that it works for poor people.

The Next Great Market Opportunity: Sanitation for India's Poor
Last year, I went to New Delhi to talk to government leaders about this toilet initiative. They were very interested. More Indians have access to cell phones than to toilets that are clean and private. One consequence is a terrible diarrhea epidemic, which contributes to India’s huge burden of malnutrition and 200,000 deaths every year.
The Department of Biotechnology and other government agencies worked with us to put on the fair and showcase next-generation sanitation solutions. Solutions like toilets that need no water and convert fecal waste into electricity—or waste processing plants not much bigger than a shipping container that can turn thousands of gallons of fecal sludge into fertilizer.
It’s great to see India at the cutting edge on sanitation. When I joined Prannoy Roy last year for a taping of his TV show, he said people laughed at him 20 years ago for saying that one of the most important things India could do to be a better country is provide better toilets for women. Nobody’s laughing anymore. According to a recent World Bank report, inadequate sanitation costs India nearly $54 billion a year – equivalent to 6.4% of India’s GDP. Some smart people are starting to realize that on the flip side of this economic penalty is a big economic opportunity. As the World Bank report notes, improving India’s sanitation infrastructure could be a $152 billion market.
Just like any other sector, there is a value chain in sanitation. And all across this value chain—from the design of next-generation toilets that don’t require a sewer connection to the development of new markets for the collection and treatment of waste—there is amazing business potential.
India is especially well-positioned to lead in sanitation innovation. It is a proven leader in addressing difficult health problems, like eliminating polio. The country has a well-educated workforce and a demonstrated capacity for technological innovation. And it has a ready market of 630 million people looking for affordable sanitation solutions.
At the Gates Foundation, we see a lot of market failures—situations where poor people’s needs are ignored because it’s impossible to make a profit meeting them. India’s sanitation crisis is different. There is a desperate need. There are also billions of dollars to be earned. The toilet fair demonstrated that there is finally a wealth of innovative thinking about solutions. It will be fascinating to watch this market develop in the next decade.
Global Health Hero
A visit to Haiti, and the biggest hellraiser I know
Last month we caught up with Paul Farmer, a hero of global health.
Last month, Melinda and I took the kids on a vacation during their mid-winter break—and managed to get in a quick visit to Haiti, where we caught up with one of the heroes of global health, Paul Farmer.
If I had to list ten amazing people I’ve had the honor of meeting, there’s no question Paul would be right up there (Nelson Mandela would be at the top). I don’t have enough space in this post to do justice to what a special person he is, so if you want the full story, I’d suggest the book Mountains Beyond Mountains, by Tracy Kidder, which tells the whole story. Paul co-founded Partners in Health (PIH), which helps run medical clinics at 12 sites in Haiti, providing phenomenal levels of care—dealing with everything from ophthalmology to women’s health to HIV and TB. They reach more than a million people and employ thousands of Haitians. PIH also runs clinics and hospitals in several other countries, including Rwanda and Russia.
I don’t know anyone who does a better job than Paul of calling attention to the cause of global health. He’s not a scold—he really draws people in and gets them excited about the work. He chose to work not only in Haiti, but in some of most remote regions within Haiti. The poorest places in one of the poorest countries anywhere. He’s driven by a strong sense of justice. As he says, “The idea that some lives matter less is the root of all that's wrong with the world.” Short of meeting Paul in person, you can get a good sense of his passion from his book To Repair the World, a collection of speeches where his moral vision really shines through. If you really want to dig in to the details, Reimagining Global Health: An Introduction is a good place to start—it’s based on a course he co-taught at Harvard.
Melinda and I have met Paul in various places, but we hadn’t visited him in Haiti for nine years. I had read a lot about the earthquake that devastated the country in 2010 and was eager to see how things had progressed. Plus, just being around Paul is an inspiration in itself.
We started our day in Cange, a town in the Central Plateau of Haiti where PIH has a clinic. When we arrived, a small student orchestra was performing a song that I later learned was from Pirates of the Caribbean. At least judging from what we saw, life in Cange has improved since the last time Melinda and I were there. The health clinic has a lot more space now, and the local school has expanded too. While it used to take four hours over bumpy roads to get there from Port-Au-Prince, you can now make the trip in less than 90 minutes, thanks to a road that the European Union helped pay for.
I’ve met a lot of doctors working in poor communities. Sometimes they’re reluctant to get too attached to their patients, because the emotional toll would be so high. But not Paul. As we made our way through the clinic, he seemed to draw more energy from everyone he met—stopping to offer clinical advice to a nurse or a word of encouragement to a patient. I got the feeling he would have been happy to spend the day just roaming the halls and caring for people.
After Cange, we drove about 15 minutes to see a factory that makes a kind of fortified peanut butter for undernourished children. Abbott Laboratories helped fund the factory, and it is quite fancy. They have huge propane tanks to run heaters and big generators to power the machines inside. The peanuts are grown by 200 local farmers who trained at the facility. We watched as the nuts were roasted, shelled, and ground, and then mixed up with other ingredients to make the paste. A machine pours it into big 1 kg jars that will be distributed to families. There’s even a lab with technicians who test the paste for contaminants.
Next we drove into the city of Mirebalais to see the new hospital run by PIH and the Haitian government. I was blown away. The hospital opened last summer and was built using money donated after the 2010 earthquake (people who were injured in the quake still need ongoing treatment). As you can see from the video here, they spared no expense to make it a first-class facility. There’s a machine for performing CAT scans. There’s a sophisticated system for keeping medical records. The staff can send digital images to Harvard and get input from specialists there. They have modern incubators for premature infants. The hospital gets electricity from an enormous solar array (plus a diesel generator at night).
As we pulled up to the hospital, I noticed a bunch of kiosks set up out front. They weren’t part of the hospital, but they were a natural outgrowth of it. Every day several hundred people come to the hospital for care, but the staff can’t deal with them all at once. Local entrepreneurs have created this impromptu market where they sell food and other items to the waiting patients.
Inside, we met some of the patients and staff. One of our daughters is thinking about becoming a doctor, so she peppered Paul with questions as we walked around. We all visited the ward for premature infants. Later, on the flight out of Haiti, the kids told me how moving it was. They had never seen anything like that before.
In another ward, Paul introduced me to one boy who had had cholera, and another whose appendix had burst. For a lot of Haitians, those conditions would almost certainly have killed them. But thanks to the great care they got here, both boys were well on their way to being cured.
Overall we had a great visit. I saw real evidence of progress. Of course, Haiti has a long way to go: It remains quite poor. And I worry about how the projects I saw will generate enough revenue and enough generosity from donors so they can maintain such great facilities. Operations and maintenance—whether for a CAT scanner or a peanut processor—takes funding and technical expertise. I left Haiti wanting to learn more about how countries at various levels of wealth are able to build strong health care systems, especially for primary care.
But even understanding all the challenges, I felt hopeful about the opportunity for more Haitians to improve their lives. You know you’ve had a good trip if you can visit a country as poor as Haiti and leave feeling optimistic about its future.
On the Right Track
What I Learned About Polio in Nigeria
In Nigeria I saw firsthand how work is progressing on polio eradication.
I had a great visit to Nigeria last month and was able to learn firsthand about how work is going on polio eradication and immunizing kids against preventable diseases. There’s a tremendous opportunity now for Nigeria to eradicate polio and it was exciting to meet with many of the government and traditional leaders who are making this progress possible. I was joined on the trip by Aliko Dangote, a Nigerian and one of Africa’s most successful business leaders and philanthropists. Having his point of view on Nigeria and our efforts was really helpful.
On my first day in Abuja, Aliko and I went to the Polio Emergency Operations Centre, where government and donors come together to analyze the latest polio data, and plan the polio vaccination campaigns that are at the heart of this effort. They reported the fewest number of polio cases in three years, down 56% from this time last year and restricted to only two areas of the country. It was great to see Nigerians and partners work together to grab this opportunity. The rest of Africa and the world are watching. It can be done. And I believe it must be done.
Later in the day, Aliko and I met with the Speaker of the National Assembly, Ministers for Finance and Agriculture, as well as a private meeting with Nigeria’s President Goodluck Jonathan. I’m excited about our broad range of investments in health, agriculture and digital money in Nigeria. By increasing agricultural productivity – in a sustainable way – and supporting widespread access to digital money services, we can reduce hunger and poverty, and help improve the health and prospects of millions of families. Science and technology offer amazing opportunities for innovative solutions to tackle tough challenges in Nigeria for those most in need.
We joined a meeting of the Presidential Task Force on Polio Eradication, and were happy to take part in a ceremony to recognize state Executive Governors who have improved vaccine coverage rates and reduced polio cases. We paid tribute to the all-important traditional leaders who are often at the front line of changing behavior and encouraging mothers to have their kids vaccinated. The spiritual head of Nigeria’s Muslims, His Eminence, the Sultan of Sokoto, gave me a traditional robe and hat.
At the same event, President Jonathan announced he was conferring on me the Commander of the Order of the Federal Republic. Both honors were very kind, and I appreciated both the tributes as well as the commitment of so many people in Nigeria who are working to improve public health and reduce poverty.
Aliko and I had private meetings with some of the Executive Governors on the front line in the fight against polio, and the huge push to get life-saving vaccines to more kids. I was really impressed by the courage and commitment of Governor Shettima of Borno. That state has more polio than anywhere else in the country and there are big security challenges to reach every child. We also met with Governor Kwankwaso and his team from Kano, which is the most populous state in the north and has the second highest number of polio cases. Both Governors are determined to improve the public health systems in their states.
Aliko and I joined the Minister of Health, the Sultan of Sokoto, and the House and Senate Chairmen on Health to launch Nigeria’s newest Routine Immunization Strategy. It includes plans for the introduction of new vaccines, sets out a multi-year budget and describes strategies for reaching all children. This is also the first time there has been a focused look at fixing accountability at every level of the program – from the release of funds at the Minister’s level, to the delivery of vaccines by health workers in the field. This is a tremendous milestone. I was encouraged by the increasing attention to measurement and using accurate data to diagnose problems and help health workers better manage their programs.
The next day Aliko and I were in Lagos to learn more about Nigeria’s efforts to improve its vaccine supply chain. We visited the Lagos State Cold Store where the staff showed us how they are now monitoring vaccine stocks at each district level to improve the availability of life saving supplies. We also learned more about their work to streamline vaccine distribution. Prior to the program, 43% of the facilities were running out of vaccines. Under the new delivery system, this has dropped to just one percent. Transforming health systems is not easy. But it’s exciting to see this kind of innovation taking root in Nigeria. It’s making a real difference.
Aliko and I got a lot accomplished in a short amount of time, and we met with some truly committed leaders and field workers. I left Lagos more convinced than ever that Nigeria is on the right track. Next, it was on to Berlin.
Unite Against AIDS
On World AIDS Day, a Call to Action
We can all take action against AIDS, by learning, acting, and giving.
The theme for World AIDS Day this year is "Working Together for an AIDS-Free Generation." This year is especially important because the world is making huge progress against HIV, but we still don’t have all the tools we need to end the epidemic. This is a time for everyone to learn the facts about AIDS and put knowledge into action.
When you look at the facts, you see there’s a very clear, cause-effect relationship between the world’s level of investment in HIV treatment and prevention and the number of lives saved. Providing women, men and children with access to low-cost treatment literally means the difference between life and death. Access to treatment is reviving entire communities by helping people live healthy and productive lives.
But we still have much more to do. The rate of new infections is going down, but the number of people who get infected every year is still double the number who gain access to treatment. We need to stay focused on developing new prevention methods, like long-lasting pills and injectables, that can provide people with sustained protection over time.
And we have to stay focused on finding an HIV vaccine. A lot of new discoveries have given us hope that we can produce a safe and effective vaccine to protect future generations.
The organization leading the international anti-AIDS effort is The Global Fund, which currently provides HIV treatment to nearly 4 million people in Africa and is also a key partner in efforts to end mother-to-child transmission of HIV. The Global Fund has a new executive director, Mark Dybul, the former U.S. global AIDS coordinator. And it recently adopted a new approach to funding grants by investing additional money in health programs that are poised to achieve the strongest impact.
I’m convinced that the right people and organizations are assembled to push toward beating this epidemic. What’s not yet in place are the necessary financial resources. The Global Fund relies on voluntary contributions. Many governments and private organizations, including our foundation, have invested significant amounts, but the donations received so far fall short of what is needed to expand affordable treatment to those who need it.
One of the best ways that people can support the fight against AIDS is to donate to the Global Fund. You can contribute through the UN Foundation or by buying great holiday gifts through Product Red.
Take a few minutes to learn more about World AIDS day from these sites: UNAIDS for global information and AIDS.gov for information about the state of HIV in the United States. Then consider helping with a contribution to the Global Fund.
A Very Good Year
Good news you might have missed in 2013
Looking back at 2013, I wanted to share a different kind of list.
You’re probably seeing a lot of people’s year-end lists right now, going through the best movies, books, YouTube clips, grumpy cat memes, etc.
I thought I would share a different kind of list: some of the good news you might have missed. I’ve limited my list to global health and development, where Melinda and I spend a lot of time, but even so, there’s a lot to report. If you measure progress by the number of children who die of preventable causes, or by the number of people who escape extreme poverty—as I do—then 2013 was definitely a good year.
For example:
We got smarter and faster at fighting polio. You may have heard about recent polio outbreaks in Syria, Kenya, and Somalia. What you may not know is just how rapid and effective the response has been. It looks like the outbreak in the Horn of Africa was controlled in 4 months, less than half the time it took to control an outbreak there in 2005. That speed is due in part to the work done at the Global Vaccine Summit held inAbu Dhabi this year. In the past, the world has had to make tough trade-offs between responding to outbreaks, improving routine immunization, and fighting the disease in the last three countries where polio is still circulating (Afghanistan, Pakistan, and Nigeria). There was no coordinated plan or long-term funding for doing all three at once. At the summit the world got both. We adopted a comprehensive plan for pursuing all three goals, including making the world polio-free by 2018. And more than 30 donors—including a number of very generous private individuals—backed the plan with a total of $4 billion in long-term funding. That means we won’t have to make those trade-offs anymore. It’s a huge step forward.
There’s also great news from India. In early 2014, India will have gone three years without a single polio case (assuming no new ones are reported between now and then). That’s a testament to the fantastic job they’ve done immunizing every child, even in the most remote parts of the country. Now they’re focused on keeping the disease from coming back.
Next door, in Pakistan, the political leaders are clearly resolved to get polio out of the country once and for all. When I met Prime Minister Nawaz Sharif this fall, he made it clear that he sees vaccinating children as a matter of justice. Despite the ongoing violence there and in Afghanistan—including horrifying reprisals against vaccine workers—the next couple of years are a good opportunity for us to make progress on this goal.
Child mortality went down—again. One of the yearly reports I keep an eye out for is “Levels and Trends in Child Mortality.” The title doesn’t sound especially uplifting, but the 2013 report shows amazing progress—for example, half as many children died in 2012 as in 1990. That’s the biggest decline ever recorded. And hardly anyone knows about it! If you want to learn more—and I’d urge you to—the report has a good at-a-glance summary on page 3.
The poverty rate went down—again. If you want to read just one article that explains the state of the world’s poor and the future of the fight against poverty, check out “Not Always With Us,” which the EconomistEconomist ran in June. It gives a short but thorough overview of the progress so far—the poverty rate has dropped by half since 1990—and the prospects for keeping it going. As the article says, the biggest factor in reducing poverty over the past few decades has been economic growth—growth that touches not just those who are already rich, but a broad range of people. We’ll need to maintain this growth in the coming decades to keep the poverty numbers coming down. That’s one reason I argue for stepping up our investments on health: Health may not cause growth directly, but it does help lay the foundation for it. I never miss an issue of the , and this might be the best piece they ran this year.
Rich countries re-committed to saving lives. Just this month, donors met in Washington, D.C., to renew their funding commitments to the Global Fund to Fight AIDS, TB, and Malaria. I was there and I got to meet Connie Mudenda, a Zambian woman living with HIV who started getting treatment in 2004 thanks to the Global Fund. The medicine she takes costs just 40 cents a day, and it helped her get healthy, go back to work, and support her family. Connie says that a decade ago, she’d often see people who were so sick with AIDS that they couldn’t even walk. A family member would push them down the street in a wheelbarrow. Today, though, 80 percent of Zambians with HIV have access to treatment, the country’s economy is growing, and Connie says the wheelbarrows have vanished.
There’s a terrible Catch-22 in global health: You need new tools to fight diseases, but if you can’t pay to deliver them, they don’t get made; and if they don’t get made, then no one gives money to deliver them. So it’s fantastic that donors are stepping up to avoid this problem by making big commitments to the Global Fund.
A fantastic Web site got launched. If you love data, and if you’re curious about what causes the most suffering around the world, you should check out the Global Burden of Disease Web site, which was launched early this year. (The foundation helped pay for it.) Personally I am a yes on both categories, which is why I have spent a lot of time on there. It lets you make beautiful charts that help you understand the impact of disease in different countries and even see how things change over time.
On a personal note, I should say how grateful I am to everyone who made time to meet with me, from world leaders to health workers in India, Nigeria, Pakistan, and around the globe. Some of these workers take great risks to help people, facing attacks from extremists in order to vaccinate children. They are true global-health heroes.
What’s Ahead in 2014
Next year I’m excited about the continued rollout of a vaccine called pentavalent (because it prevents five diseases). Next year it will be available in South Sudan, the last of the 73 poorest countries to introduce it. India just announced that they’ll start giving it to every child in the nation in 2014. If other countries follow India’s example, pentavalent could prevent 7 million deaths by 2020. Next up are new vaccines to prevent pneumonia and rotavirus (which causes diarrhea). And we’re seeing more middle-income countries like China and India develop the ability to manufacture vaccines, which drives the cost down.
Crucial to delivering all these vaccines is GAVI, an alliance that has helped 440 million children get immunized since 2000. (Go back and read that again: 440 million.) Next year GAVI will be asking donors to renew their commitments, just as the Global Fund did this year. It will be a challenge to raise more money, but I know from experience that people want to help kids get vaccinated when they see what a phenomenal impact it has. It’s hard to resist the thrill of helping to save the life of a single child, let alone millions.
One last note about 2014: I’ll be publishing my sixth annual letter in January. This time I’m planning to take a slightly different tack from years past—Melinda and I will be tackling some of the biggest myths we encounter in our work on health and poverty. It should be a fun one to write. If you’d like to get an e-mail notice when the letter is out, you can sign up here.
MDG
Dream with a deadline: The Millennium Development Goals
In 2000, the U.N. set eight goals that changed the world. What's next?
Although it was several years ago, I still remember how Melinda and I felt when we learned about the Millennium Development Goals. We were hopeful, but we had reservations.
We were hopeful because the goals—eight specific targets for improvements in health, education, and other areas—shone a light on issues we were passionate about. We had been learning a lot about poverty, and about diseases that disproportionately affect the poor. We learned that millions of children die of preventable causes every year, and yet much of the world didn’t seem to be paying attention. So we were glad to see that three of the MDGs were specifically about global health, including reducing childhood deaths.
But as I said, we also had reservations. The MDGs were hardly the first time someone had declared that children shouldn’t die. And the U.N. had passed many resolutions calling for things that never came to pass. Why would this time be different?
Charles Kenny. Senior Fellow, Center for Global Development
Why I came to love the MDGs
It’s hard to pinpoint exactly when it happened, but over time Melinda and I moved from cautious optimists to full-throated fans. I think the MDGs are the best idea for focusing the world on fighting global poverty that I’ve ever seen. Next week in New York City, I will attend the U.N. General Assembly, where I’ll be meeting with a number of partners to talk about the progress of the MDGs and what comes next.
First, unlike so many vaguely worded international resolutions, the MDGs came with concrete numbers. You can use the goals to measure progress around the world and in specific countries. (This site lists all the targets and shows the progress toward them.) And the measures apply to things that everyone can rally around, like saving children’s lives and preventing maternal mortality. I’ve been writing about measurement a lot this year, because I’ve found that measuring progress is the only way to drive lasting success.
Second, the MDGs quickly got on the global agenda, even if they’re not that well-known here in the United States. I would visit a country like Ghana, and the leaders would be eager to discuss how they were doing on the MDGs. (Quite well, in Ghana’s case: They cut hunger by 75 percent between 1990 and 2004, for example.) I remember going to the World Economic Forum in Davos, Switzerland, and seeing for the first time a series of sessions on health and development. I doubt that would have happened without the MDGs. And Melinda and I never would have expected that in 2008, one of our daughters would come home from school with an assignment to learn about the Millennium Development Goals.
Third, the MDGs show how we can solve problems that might seem intractable. Sometimes people look at poverty or childhood deaths and say, “I feel bad about that, but there’s no way we can make progress on that in my lifetime. It’s just too depressing and complex.”
The MDGs cut through that complexity. The results prove that success is possible and real. Fewer children are dying and fewer people are living in poverty. The death rate from malaria has fallen by more than 25 percent since 2000. The proportion of people in extreme poverty has been cut by more than half, meeting MDG 1 five years early.
The River of Myths by Hans Rosling. Hans Rosling shows the amazing progress that poor countries have made in saving children’s lives and imagines what could come next
The success has been infectious. When donors see that their money is having an impact, they want to do more. Net foreign aid has gone up since 2000, and a large part of the increase has gone to global health.
How much credit do the MDGs get for this progress? There’s no way to put a precise number on it, but they probably had a bigger impact on health and education than on poverty. About three quarters of the drop in extreme poverty is due to China’s economic growth, which would have happened with or without the MDGs. But without the goals, it’s unlikely the world would have focused as much as it did on malaria, HIV/AIDS, maternal mortality, or childhood diseases.
A report card for the world
We have to acknowledge that we’re not going to meet all the goals.
Some people point to this fact and say, “Oh no, we’re failing.”
But I don’t look at it that way.
The MDGs aren’t a test that the world will either pass or fail. They’re more like a report card. Some country is getting an A in every subject. The ones that aren’t doing as well can go learn from the ones that are. Without the MDGs, we wouldn’t have any idea who was acing the test and who was struggling to get by.
In some cases, we’ll miss an MDG because the goals were unrealistically high to begin with. For example, MDG 4 is to reduce childhood deaths by two thirds. We won’t hit that number by 2015. But we have achieved the largest reduction in child deaths ever recorded. Millions of children’s lives have been saved. I dare anyone to call that a failure.
Time to double down
We can’t be satisfied with this progress. We have to double down on it. Various groups under the auspices of the U.N. are now talking about the new round of goals that will be adopted after the current ones expire in 2015. I don’t have a position on what the new goals should be, but I do think they should build on what made the current goals so successful—starting with the fact that there were only eight MDGs, which let the world zero in on the most important areas.
Next week in New York, I’ll be making the case for four other qualities that I hope the new MDGs will also reflect:
Focused on extreme poverty, including childhood deaths in the poorest countries. We can cut the number of childhood deaths by more than half—to well below 3 million—by 2030. In addition, the next round should focus on the poorest of the poor. Much of the progress in fighting poverty over the past 15 years has been among people who lived just below $1.25 a day. Those living on far less have largely been left behind. They are harder to reach, but just as deserving of the chance to make the most of their lives.
Measurable. The MDGs create a positive feedback loop by setting clear, specific targets and measuring the progress toward them. If the new goals are going to have lasting impact, they too need to have concrete targets that can be measured.
Actionable. The MDGs are focused on areas where we have the tools that will drive progress, like vaccines to stop childhood diseases and bednets to prevent malaria. The new goals should meet this same test. For example, improving governance is a worthy end, but do we have the tools to make it happen? It’s not clear.
Built on consensus. I hope people stay focused on goals that will get unanimous support. Otherwise, the U.N. could get bogged down in endless debate that could sap our momentum. No one can object to saving children and mothers.
Moving Ahead
Let’s remember what the MDGs have accomplished. They saved lives, and they helped rich and poor countries come together to make measurable progress on reducing inequity. That had never happened before. It is a wild success. It should inspire and guide our actions in the years ahead.
Tour of Progress
Video highlights of my India trip
India is making more-affordable vaccines and more-productive crops.
On my trip to India a few weeks ago, I got an update on the country’s progress with making more-affordable vaccines and more-productive varieties of crops. I also had a fun onstage Q&A with the very impressive Bollywood star Aamir Khan. Here’s a short video with a few highlights from my trip, including a look inside an agricultural research center that’s doing some exciting work on new crops.
(You can also read my blog posts about the trip here and here.)
Longer Lives, Smaller Families
Don’t Miss the Best News in Those New Population Numbers
These projections have two key points that are worth calling out.
The United Nations released some new population projections last week that are worth taking a closer look at.
The news coverage about the reports hit the high points: the UN projects that the world’s population will reach 9.6 billion by 2050, and India could overtake China as the most populous nation around 2028.
But a lot of the stories I’ve seen have missed two key points that are worth calling out.
First, life expectancy has been going up at an historic rate. You may know that the average life span went up in the 20th century—but did you know it increased faster in the past 100 years than at any other time in history? Life spans rose by nearly 50 percent, from 47 years in the 1950s to 69 years in 2010. And the U.N. projects that the average will keep going up for the rest of this century.
Of course, the average obscures a lot of variation among countries. In most rich countries today, the average life span is over 75 (in Japan it’s over 80), while in the poorest it is only 58. But even in those poor countries, the UN projects that life spans will reach 70 years by the middle of this century.
So if anyone tries to tell you how much better things were in the old days, you can ask them if they preferred it when 20 million kids a year died before age 5 (versus about 7 million today) and the average human being died before age 50.
That leads to the second point, and it’s a really important one:
As child mortality goes down, families get smaller. It’s counterintuitive, but it becomes crystal-clear when you look at the data: Just about all the countries where health is still bad also have high birth rates. And as more children in a country survive past age 5, the number of children born per woman goes down. It’s happened in China, India, Indonesia, Iran, Brazil, and South Africa, among other countries.
Why does this happen? Because when parents know their children will live long enough to support them in their old age, they decide to have fewer kids. The economist Jeff Sachs has written a lot about this point. The Swedish researcher Hans Rosling nailed it a few years ago in a brilliant and entertaining TED talk.
Of course, it’s one thing for people to want smaller families, and another for them to be able to act on this wish. That’s why it’s so important to make sure women have access to voluntary family planning, which our foundation does a lot of work on and is a big focus for Melinda.
These two facts—increasing life spans and the strong link between family size and child health—drive a lot of the work Melinda and I do. They tell us that the world is getting better; that the challenge is to make sure it gets better faster, and for everyone; and that one of the best ways to do that is by working to save children’s lives and supporting family planning. When health improves, life improves, by every measure.
Meeting Problems with Solutions
Getting better all the time
Halfway through the first day of my India trip, TV personality Prannoy Roy told a story I think really highlights the progress of India’s long journey to better health.
Halfway through the first day of my India trip, TV personality Prannoy Roy told a story I think really highlights the progress of India’s long journey to better health.
We were filming a question-and-answer segment in front of a studio audience for his show on New Delhi Television, one of India’s largest news networks.Prannoy was asking me and Bollywood star Aamir Khan about philanthropy, health, and India’s development when he recounted a discussion he had about 20 years ago. A former prime minister asked him and a group of other people what India could do to be a better country. Prannoy said his answer – provide better toilets for women – was met with nothing but laughter.
Things have really changed. Just before seeing Prannoy, I had spent several hours in meetings with Indian parliamentarians and ministers. Our wide-ranging conversations about health and vaccines almost always returned to how to stop the spread of diseases through better sanitation and, specifically, toilets.
I was glad: the toilet is one of my favorite topics. At each meeting I got to talk about how flush toilets (ones that use water to clear the waste away through plumbing) won’t make it anytime soon to much of the world, including rural India where infrastructure is poor and water is scarce. Instead, we need to invent a better toilet, one that doesn’t use water yet eliminates harmful microbes and gets rid of any smell. Last year our foundation sponsored a “re-invent the toilet” fair where 14 universities submitted innovative answers to that problem. None were perfect but they all were a step in the right direction.
After several meetings it was clear there was strong interest in holding a similar “re-inventing the toilet” event in India early next year. We set some follow-up meetings to start figuring out how to make it happen. We agreed that applying India’s many creative minds to the sanitation problem could speed the path to a breakthrough.
In my post, “Why I’m Going to India,” I wrote that the country is an ideal place for understanding both the problems and the solutions in areas that our foundation focuses on. In my meetings yesterday, the sanitation discussions were just one example of the great optimism I felt from government leaders and health experts for overcoming the problems. I also heard about several new solutions.
A group of polio experts updated me on how India’s focus on ridding itself of that disease is paying dividends to broader health efforts. After a lot of hard work, India has been polio free since January 2011. India will be certified polio-free if there isn’t another case by next January. I’m confident we can get there. Yesterday the experts walked me through how they are using satellite mapping to not only see where they need to provide the polio vaccine but also to expand the country’s system of routine vaccinations (the vaccines children get in their early years). With satellites and cellphones we are getting far more detailed health data on hard-to-reach places. I’m convinced those tools, pioneered with polio, will be a game changer for expanding routine vaccination.
I also sat down with some of India’s top scientists, public health experts and pediatricians. This group was celebrating amazing progress of the phase 3 trial of Rotavac, India’s first home-grown vaccine for rotavirus, the world’s main cause of diarrheal disease—which, after pneumonia, is the second leading killer of children under age five. I touched on rotavirus in yesterday’s post but it’s worth emphasizing again. The work the group did to create the vaccine, and run a very high quality trial is nothing short of phenomenal. Rotavac is a rare global collaboration among the Indian government, vaccine manufacturer Bharat Biotech, and others including PATH, the U.S. Centers for Disease Control and Prevention and the National Institutes of Health. Our foundation provided grants to support the work.The next milestone is to get the vaccine licensed by Indian authorities.
Dr. M.K. “Raj” Bhan, former secretary of India’s Department of Biotechnology and a pediatrician who shepherded the vaccine’s creation, told me that he expects the vaccine to clear India’s regulators by the end of the year, an estimate the country’s minister of health echoed later in the day. That means that India could start introducing the vaccine next year and start saving tens of thousands of kids’ lives a year.
In answering the prime minister two decades ago, Prannoy, our TV interviewer, pointed to a health problem that India still hasn’t fixed. Yet things are absolutely getting better. Since that time, India’s child mortality has dropped 45%, better than 35% for the world as a whole. With every visit to the country I see how India will drop that further as it gradually solves its health issues. An official I met at India’s Planning Commission yesterday described how India is “slow and deliberate” and ultimately successful in working through challenges. “That’s what this country is all about: finding a way,” she told me.
Today I’ll see another example of how India is finding a way when I visit a research center using old and new technologies to help boost agriculture productivity andfight malnutrition.
Off to a Great Start
Global Vaccine Summit: We Changed History
The Summit was a big success.
I want to share with you my excitement over the outcomes of the Global Vaccine Summit in Abu Dhabi to celebrate the huge progress we’ve made toward ending polio and protecting all children with life-saving vaccines. The Summit was a big success.
World leaders including health and political ministers from Afghanistan, Nigeria and Pakistan, EU President Jose Manuel Barroso and former UNSG Kofi Annan appeared alongside polio survivors and vaccine heroes like Ade Adepitan, a British Paralympic medalist who contracted polio as a child in Nigeria, and Sikha Patra and Salim Shekh, two kids from India who organize polio immunizations for their community in Calcutta.
We had an amazing cross-section of participants, including community leaders like the Sultan of Sokoto from Nigeria and Rotarian Deepak Kapur from India, industry representatives, and leaders from our organizing partners UNICEF, GAVI, WHO and GPEI. Although he couldn’t attend, Archbishop Desmond Tutu, a polio survivor, also added his voice to the gathering.
We were also in Abu Dhabi to have some frank discussions on what still needs to be done to reach our ambitious goals.
And I’m proud to say that collectively, we changed history. The Global Polio Eradication Initiative rolled out a new strategy to achieve a polio-free world by 2018. Global leaders demonstrated their confidence in the six-year plan by pledging their financial and political commitments to help ensure its success.
In all, we raised a total of $4 billion dollars. That’s close to three-quarters of the plan’s projected $5.5 billion cost over six years, and enough to protect more than one billion children from polio forever.
Countries like Norway, Canada, Germany, Ireland, and the UK made generous pledges, as did His Royal Highness the Crown Prince of Abu Dhabi. The $4 billion also includes $335 million from private philanthropists such as Carlos Slim, His Royal Highness Alwaleed Bin Talal, and Mayor Michael Bloomberg. The foundation stepped in with $1.8 billion, a third of what’s needed for the polio campaign.
The Summit pledges are a huge step towards a fully funded plan, and I hope that financing won’t be the thing that stands in the way of achieving the miracle of polio eradication.
Collectively, we sent a powerful message that the world remains committed to fulfilling the vision of the Decade of Vaccines to end polio and reach all children, no matter where they live, with the vaccines they need.
Midwife Calling
Ghana: Mobile technology for global health
Mobile phones keep midwives and patients connected.
In Ghana, the Grameen Foundation is using mobile applications to improve the quality of maternal health and childcare. With the MOTECH Mobile Midwife program, pregnant women can register and receive voice messages that provide reliable advice for a health pregnancy. Smartphones are also used to record health services delivered.
Texting Immunity
Mozambique: Mobile Technology for Global Health
Text messaging has increased immunization rates in Mozambique.
In Mozambique, Margarida Mathshinhe and VillageReach use text messaging to improve routine immunization. VillageReach deployed the Dedicated Logistics System (DLS) to increase the scale and efficiency of vaccine delivery to children living in rural areas.
First, Celebrate
Not Your Typical Vaccine Conference
This week I'm going to Abu Dhabi to attend the Global Vaccine Summit to celebrate the tremendous progress the world has made in ending polio and immunizing children.

This week I’m going to Abu Dhabi to attend the Global Vaccine Summit to celebrate the tremendous progress the world has made in ending polio and immunizing children.
This isn’t going to be typical conference. We aren’t going to have breakout sessions or canvas bags crammed with printed reports to take home. We’ll be there to do just two things: first, celebrate the progress we’ve made in the Decade of Vaccines to reach all kids, everywhere, with the vaccines they need; and second, to share best practices and have some frank discussions on what still needs to be done. As part of that, the Global Polio Eradication Initiative will roll out a new strategy to end polio once and for all. Global leaders will discuss their confidence in the plan and pledge political and financial commitments to help ensure its success.
Why Abu Dhabi? His Highness General Sheikh Mohamed bin Zayed bin Sultan Al Nahyan, Crown Prince of Abu Dhabi, is joining UN Secretary-General Ban Ki-moon and me to host the Summit, the first of its kind. The Crown Prince, an important partner of the foundation across several issues, represents to me the inspirational leadership we are seeing from the Middle Eastern and Islamic communities to improve child health worldwide.
In my talk, I’m going to share some of the numbers that impress me, such as the measurement systems that have allowed Ghana to build a strong immunization system. And I’ll share numbers that make me angry. For example, a child born in a low-income country is 18 times more likely to die before reaching the age of five compared to a child in a high-income country—largely due to preventable causes. That inequity is simply unacceptable and completely fixable.
I’m excited to meet some pretty amazing heroes while I’m there, too. World leaders like Jose Manuel Barroso and Kofi Annan will appear alongside Ade Adepitan, a British Paralympic medalist who contracted polio as a child in Nigeria, and Sikha Patra and Salim Shekh, two kids from India who organize polio immunizations for their community in Calcutta. I get to meet the two winners of my annual Gates Vaccine Innovation Award, too. Archie Panjabi will be our emcee. She appears on the American series The Good Wife and is using her celebrity to be a strong advocate for ending polio.
Thousands of people—scientists, investors, health experts, community leaders—share involved in the process of immunizing a child. We need to have the right vaccines, developed and manufactured at affordable prices, delivered to the hardest-to-reach children. It is crucial to build up strong routine immunization systems to protect our gains against polio and provide a platform for primary care. When the world comes together, we can set ambitious goals, we can measure our progress, and we can achieve even more. I’m counting on the Global Vaccine Summit to do just that.
CIMMYT
Mexico will lead innovation in agricultural development for the world
Mexico is at the forefront of advances in agricultural development to help poor countries become food self-sufficient.
Building on its success a half-century ago pioneering new varieties of wheat and maize that saved a billion people from starvation, Mexico is again at the forefront of advances in agricultural development to help poor countries become food self-sufficient.
Combining the latest breakthroughs in agricultural science and farming practices with digital technology, Mexico’s innovative efforts will enable even the poorest farmers to grow and sell more crops.
Against the dramatic realities of climate change, a growing global population, rising food prices, and a shrinking agricultural land base, Mexico’s leadership in agricultural innovation is critically important—especially to the countries of Sub-Saharan Africa where hundreds of millions of people face severe hunger and poverty.
At the center of these efforts is Centro Internacional de Mejoramiento de Maíz y Trigo (CIMMYT), where Mexican and international researchers have worked for decades to develop higher-yielding, more resilient seeds for maize and wheat, and to introduce better agricultural practices that help farmers be more productive. One of CIMMYT’s greatest strength is its partnership approach. In addition to bringing together the world’s leading scientists and agricultural experts, CIMMYT has also involved farmer associations, the private sector, governments, international organizations, and NGOs in developing effective solutions to meet the needs of poor farmers worldwide.
This week, CIMMYT will be celebrating the completion of new agricultural research and training facilities made possible through the financial support of Fundación Carlos Slim. These state-of-the-art labs and greenhouses will ensure CIMMYT’s continued leadership developing high-yielding maize and wheat varieties equipped to tolerate the stresses of climate change. Expanded training facilities will enhance CIMMYT’s ability to develop and deliver resource-conserving farming practices and advance digital technologies that enable poor farming families to increase their productivity and income.
Helping poor farming families increase production in a sustainable way, and sell more crops, is the most effective way to reduce hunger and poverty over the long term. This has been proven in Mexico, India, Pakistan, Brazil, China, and many other countries over the last half century.
The unique partnership between CIMMYT, the government, and our foundations ensures that Mexico will continue to lead in agricultural development—first in Mexico and then the rest of the world.
The new infrastructure funded through Fundación Carlos Slim will enable CIMMYT to carry out cutting-edge agricultural science using the latest digital innovations, and to accelerate the use of mobile technology to provide farmers everywhere with vital information about weather, prices, and new techniques to improve their productivity. The Mexican government’s MasAgro initiative is helping farmers adopt more sustainable and profitable farming practices to increase food production. As these agricultural advances achieve scale in Mexico, the Gates Foundation will ensure that they reach maize and wheat farmers in Africa and South Asia, along with the resources needed to improve productivity.
Fifty years ago, Mexico’s leadership in agricultural innovation helped lift hundreds of millions of people in Latin America and Asia from hunger and poverty. More recently the UN’s Millennium Development Goals have reduced the number of people living in extreme poverty by half, since 1990.
The world is counting on Mexico to continue leading the way in agricultural research and sustainable farming practices to ensure global food security. Meanwhile, the global community must do its part by aligning around a new set of goals—including an agricultural productivity target—and achieving measurable outcomes that improve the lives of the world’s poorest people.
Gene Banks for Crops
Mexico, Carlos Slim, and me
Mexico and philanthropists like Carlos Slim are helping lead the global fight against hunger and poverty through agricultural development.
This week I’m excited to be in Mexico for a series of events with Carlos Slim, probably Mexico’s best-known business leader, whom I’ve enjoyed getting to know for his business insights—but also because of some of the innovative approaches he’s taking to philanthropy.

We’ve been invited by the International Maize and Wheat Improvement Center (known by its acronym in Spanish, CIMMYT) to help launch new facilities at its headquarters near Mexico City. With a staff of 1,100 in Mexico and 13 regional offices around the world, CIMMYT is helping reduce hunger and raise living standards in many poor countries through programs focused on increasing maize and wheat productivity. Our foundation has invested in CIMMYT, and Carlos Slim has been a big supporter.
Carlos is a very interesting guy. His father immigrated to Mexico from Lebanon. Carlos started several businesses when he was quite young and was already very successful by his mid-20s. His interests in construction, real estate and mining eventually branched out into many other businesses, including Mexico’s largest telecommunications company. He reminds me a little of Warren Buffett in his ability to find undervalued investment opportunities. I’ve enjoyed the time I’ve spent with him, getting to hear his thoughts on business trends and the future of Latin America.
Among many other great projects, the Slim Foundation has funded the new CIMMYT facilities that we’re helping open this week. Carlos’ foundation and ours have collaborated before in helping launch the Salud Mesoamérica 2015 initiative to support health projects in Chiapas, Mexico and across Central America.
This week we’ll get a chance to tour the new CIMMYT facilities including the gene bank, which holds the genetic diversity of 130,000 wheat and 28,000 maize varieties worldwide. This information is being uploaded onto databases that will be available to plant breeders everywhere. We’ll also get into the field with farmers who’ve been helped by the MasAgro project, sponsored by the Mexican government to help strengthen food security through R&D, capacity building and technology transfer.
One reason why I always enjoy going to Mexico is because of the country’s incredible progress, which has been really encouraging for me to get to see as I’ve spent time there over the years first for Microsoft and lately for our foundation. Despite the many challenges Mexico still faces, Mexico’s extreme poverty rate (those living on less than $1.25 per day) went from 13.6 percent in 1996 to 4.03 percent in 2010 (as per latest World Bank figures). A major driver in reducing poverty has been agricultural development, especially innovations that have helped improve crop yields for smallholder farmers, whose lives have improved a lot as a result.
Part of what makes this week’s visit particularly exciting for me is that the expansion of CIMMYT represents a very important and positive global trend: newly industrialized countries such as Mexico, China, India and Brazil are becoming leaders in efforts to help less developed countries. Mexico is in a great position to work closely with poor countries both because of its progress and because of its quite advanced technical capabilities in agricultural development. CIMMYT is a prime example of that.
Poor countries, donors and rapidly growing countries are increasingly working together in partnerships that I believe are a model for how to deploy the world’s combined resources. These sorts of partnerships, combined with rigorous goal-setting and measurement, can produce enormous benefits for the poorest around the world.
“Developing Countries”?
The River of Myths by Hans Rosling
Hans Rosling shows how countries are making progress in saving lives.
Hans Rosling shows how measurement reveals incredible progress in saving the lives of children in what were once labeled "developing countries." If the few countries that still have high child mortality rates can follow the path of Ethiopia, preventable child deaths may be history by 2030. We must continue to closely measure this progress.
Video created in partnership between The Gates Notes and Gapminder. #BillsLetter. License: Creative Commons 3.0.
Closing in on 1%
Turning the Corner on Polio in 2012
The Global Polio Eradication Initiative is making important changes.
Working to support the effort to rid the world of polio has taken me to some exotic places. But earlier this month, it took me to Washington, DC (I suppose you could argue this is also quite an unusual spot) to talk with policy makers about the historic opportunity we have to end polio forever.
My conversations with lawmakers gave me a chance to discuss some of the doubts people have expressed about whether we can really do this. But it also provided the opportunity to bring lawmakers up-to-speed on the results of important changes in the Global Polio Eradication Initiative’s (GPEI) approach—including cool new technology being used and the increased engagement on the part of governments in the countries where polio transmission continues.
In my opinion, the changes and progress in 2012 have made for the most convincing case yet that ending polio is possible—and is one of the most concrete accomplishments possible for global health.
For more than 10 years, we have been 99 percent of the way toward ridding the world of polio. Since then, every few years the global community would vow that year would be the year when polio transmission would stop.
However, 2012 is notably different from the earlier stagnation in progress. And while the global program hasn’t stopped transmission of the wild polio virus everywhere as some had predicted, it did close a big gap in that last one percent when India became polio-free early in the year after a long and hard battle to protect more than 172 million children under the age of five from polio. This was incredible tough terrain in which to run thousands, if not tens of thousands of vaccination campaigns. So, the lessons learned from India’s success are serving as a great guide for what’s needed in the remaining three countries where polio transmission persists—Nigeria, Pakistan and Afghanistan.
There’s no doubt that these countries aren’t easy places to get rid of the disease. There are a number of factors that need to be in place including improved campaign quality, meeting the program’s global funding needs, and anticipating political challenges.
I heard from U.S. lawmakers that the news regularly coming out of Afghanistan and Pakistan has led to reasonable concerns about the role insecurity plays in being able to reach children with vaccines. But in the last 11 months, incredible efforts are being made in these two countries by government officials, religious and community leaders and non-government organizations to negotiate access to children in hard-to-reach places.
And those efforts are paying off.
The polio program has been partnering with a number of NGOs to conduct negotiations to secure access to children, leading to breakthroughs in the past few months. In Afghanistan, the average number of inaccessible children in thirteen of the highest risk districts of the country has been reduced by more than half, from nine percent in June 2012 to 3.4 percent this November. And in the Terah Valley in Pakistan, where children hadn’t received vaccines in three years, approximately 30,000 children were reached with the polio and other critical vaccines during a vaccination campaign earlier this fall.
On the other front, in Nigeria, while cases have actually gone up this year, there is a full-scale effort to revamp the program, with many changes based on what vaccinators in India implemented to great success. Included in these changes are decreases in the size of vaccination teams and the addition of female vaccinators, tracking of nomadic populations, rigorous microplanning and scaling up of additional staff to help with all of these activities.
Another major innovation that is leading to early reports of impressive progress is the work on GIS mapping and GPS tracking to improve polio campaign planning and performance. (It’s a really ingenious use of the technology that you can learn more about here.) GPEI’s focus on using the polio program to increase routine immunization is ensuring that the polio program has an even broader long-term impact on the population.
The Independent Monitoring Board of the GPEI also notes the positive changes in a report released last week and their conclusion that the GPEI “has never been in a stronger position” reflects what I’m seeing too. Their assessment about what comes next for the history books is telling: “The time is momentous for public health history. A final concerted effort could indeed mean writing the story of polio’s last stand.”
I couldn’t agree more.
A Good Team
Partnering with Bono on foreign aid
For the past decade, we've teamed up to speak in support of aid.
This week, Bono and I met with European leaders to encourage them to renew their commitments to fund development assistance programs that help the world’s poorest. Bono is incredibly dedicated and it was great to partner with him on telling the aid story.
Giving in Tough Times
France committed to foreign aid
I'm thankful that France renewed its development commitment.
I was in Paris this week with Bono, talking about the importance and effectiveness of foreign aid with senior French officials, including France’s new President, Francois Hollande. I’m excited that France remains committed to development, even in these tough budgetary times.
“Last Mile” to Polio
Digital Mapping Technology Helps Polio Vaccinators Zero In
Health workers are using digital mapping to target polio in Nigeria.
One of the challenges getting from 99% to 100% on global polio eradication is making sure that all children are getting the multiple doses of the polio vaccine necessary to build up immunity.
To stop polio from circulating, you need to ensure that most children under the age of five receive several doses of the vaccine to build up their immunity. This is very difficult when there are hundreds of remote villages and hamlets that vaccinators don’t know about, nomadic tribes, and people in a castes or religious sects that don’t mix with the rest of the population.
Recently, public health officials began using GIS technology in Nigeria—one of the three remaining polio-endemic countries—to improve the quality of maps that tell vaccinators where to go. They are also using GPS technology to monitor the movement of vaccination teams. This kind of surveillance reduces the chances a team will miss an area that still harbors the disease.
The global health community has done an amazing job on polio, reducing the number of paralysis cases from 350,000 in 1988 to less than 200 so far this year. In 1988, more than 125 countries were endemic. Today, only three remain.
Yet, people sometimes ask me why we haven’t finished the job. It’s an understandable question since most countries got rid of polio a long time ago. One of the biggest reasons is that polio is a highly-contagious disease that travels quickly and easily. Another is the need to give each child multiple doses of the vaccine.
The use of digital mapping technology underlines the minute level of detail, planning, and organization required to completely eradicate polio. I’m optimistic that it will really help vaccinators cover the “last mile” in the delivery of polio vaccines.
Meanwhile, we can’t afford to ignore the other important pieces necessary to eradicate polio—sustaining political will and funding so vaccinators can reach children in every village, and ensuring accountability so the disease has nowhere else to go.
A Targeted Effort
GIS Mapping & GPS Tracking for Polio in Nigeria
A digital mapping system is being used in Nigeria to help health workers target specific areas for immunization efforts in the fight or eradicate polio.
In order to deliver vaccines, immunization teams go door-to-door throughout the country, including settlements in remote, rural regions.
Before going into the field, these teams use a process called “microplanning” to determine where they need to go in order to deliver the polio vaccine.
Before Geographic Information Systems (GIS) maps were made available through the mapping project, hand-drawn maps popularly known as “cartoon maps” were used to show the distribution of settlements. These maps were drawn from memory and not based on real geographical data.
GIS combines satellites, mobile device and mapping software capabilities to capture, analyze and present data as legible and informative maps.
The imagery of states is downloaded and organized for local government area (LGA) and ward map creation.
These maps make it possible to read distance and proximity with realistic placement of mapping features, to ensure that all settlements and hamlets are visited by vaccination teams, and the correct number and type of teams are deployed.
Phones are loaded with tracking software and the final settlement list before the vaccination teams are sent out in the field.
These vaccination teams are using tracking devices in the field. The phones collect geo-location readings through GPS.
The data from the phones is then processed in the GIS lab.
Detailed analytics report tracking results for each settlement.
These results make it easy to identify which settlements were missed and need to be revisited.
In Europe with Bono
Europe with Bono, defending aid
Shoring up support for international development assistance programs.
I spent Wednesday in Paris, talking about the importance and effectiveness of foreign aid. My partner in many of those meetings was Bono, who has used his voice so effectively to advocate for development aid and the needs of the poorest people on earth.
By any estimation, my few days in Europe were off to a good start.
We spent the better part of the day meeting with senior French officials, including France’s new president, Francois Hollande, his finance minister, Pierre Moscovici, the Minister of Foreign Affairs, Laurent Fabius, and their new Development Minister, Pascal Canfin.
France plays a critical role in encouraging the European Union to keep its commitments to overseas development assistance programs, particularly in the face of Europe’s economic difficulties. Its own commitment to foreign aid is a tremendous example to other donor countries. That was the context for our meetings.
President Hollande was clear that he remains committed to aid, and that he is an advocate for both the effectiveness of foreign aid when it is carefully done, and the responsibility developed countries have in working with the developing world. France has a remarkable history of support for Africa and for its assistance efforts around the world, with organizations like Médecins sans Frontières. The President also spoke about how aid can benefit both the recipient and donor countries.
France’s finance minister Pierre Moscovici made this point last month when he noted that Europe’s growth over the next 20 years will depend heavily on Africa’s growth and development. Ensuring that all Africans have a chance for a better future is not only the right thing to do, but also the smart thing to do from an economic standpoint.
We had a good exchange about getting the most out of every Euro of aid. I’m a big advocate for the incredible impact that investments in vaccines can achieve, and was very happy to hear the President specifically call out France’s commitment to staying involved with the Global Fund, which provides funding for programs to fight AIDS, TB, and malaria. France should be particularly proud in their leadership with the Global Fund. Their help is making a real difference in millions of lives around the world.
Support from leaders like President Hollande is critical to preserving those life-saving investments in aid and explaining why staying true to the EU goal of devoting .7% of national budgets to foreign aid is the right course.
Bono was very persuasive about the impact foreign aid is having, as well as the devastating consequences withdrawing it could have on poor countries, particularly in Africa.

I was really pleased with our meetings. They took place in spectacular surroundings (the Élysée Palace is a stunning example of French style and decoration). But the focus was on the poor, on both sides of the table. And that made for a very good first day in Europe.
A Busy Day in NY
At the UN: Talking health and development
As the United Nations General Assembly convenes in New York this week, I’ve been asked to come and speak about the need for nations around the world to recommit to eradicating polio. Here are some notes from my first day at the UN.
UN Week is a crazy time in New York. Getting around can be tough with increased security, various protesters, and heads of state and other important visitors coming and going. But as I wrote yesterday, it’s also an incredible opportunity to see people, and to discuss issues of real importance to the world.
I got a chance to spend some time with UN Secretary General Ban Ki-moon this morning. He’s about the busiest guy in New York this week, so it was super nice of him to make the time. We got to talk about polio, and the important meeting he’s hosting tomorrow, which is the main reason I’m here. Having his voice continue to make the case for why we need to end this disease in the few places it remains is so important. As Secretary General, he’s called out five of the world’s major "killers" he wants to see eliminated during his second five-year term. Polio is on that list, along with malaria, pediatric HIV infections, maternal and neonatal tetanus, and measles.
In the morning I had the chance to meet the Prime Minister of Ethiopia, Hailemariam Desalegn, who was sworn into office just last week. I was really happy to get to meet him because Melinda and I both had a great working relationship with his predecessor, Meles Zenawi, who died in August of this year. It was a great loss for Ethiopia, and for Africa and the world. But I was impressed with the new Prime Minister, not only for his thoughtfulness and knowledge about the issues we work on as a foundation in Ethiopia, but also for his commitment to continuing the policies of Prime Minister Zenawi, which have made real progress in helping the people of Ethiopia. Some of the foundation’s most exciting projects are happening in Ethiopia, particularly our partnership with the government in improving agricultural output for small farmers. I was in Ethiopia earlier this year, and I told the Prime Minister I looked forward to getting back there sometime in the future.
WC: Winners' Circle
And the winners of the reinvent the toilet challenge awards are…?
Today I attended the Reinvent the Toilet Fair — a fascinating learning experience and an important step in providing safe sanitation for everyone in the world.
A year ago, the foundation launched an initiative to tackle the problem of sanitation in the developing world. We called it the Reinvent the Toilet Challenge. In this photo gallery you can learn more about each of the grantees and their sanitation solutions.
This week in Seattle, the foundation is holding a Reinvent the Toilet Fair. Today I awarded prizes to three universities who responded to our challenge a year ago to come up with solutions for capturing and processing human waste and transforming it into useful resources. The winners included: first place to California Institute of Technology in the United States for designing a solar-powered toilet that generates hydrogen and electricity, second place to Loughborough University in the United Kingdom for a toilet that produces biological charcoal, minerals, and clean water, and third place to University of Toronto in Canada for a toilet that sanitizes feces and urine and recovers resources and clean water. A special recognition was awarded to Eawag (Swiss Federal Institute of Aquatic Science and Technology) and EOOS for their outstanding design of a toilet user-interface.
A solar-powered toilet that generates hydrogen and electricity
California Institute of Technology, USA
A self-contained, solar-powered toilet and wastewater treatment system. A solar panel will produce enough power for an electrochemical reactor that is designed to break down water and human waste into hydrogen gas. The gas can then be stored for use in hydrogen fuel cells to provide a backup energy source for nighttime operation or use under low-sunlight conditions.
A sanitation system that converts human waste into biological charcoal
Participating organizations: Stanford University and the Climate Foundation, USA
A self-contained system that pyrolyzes (decomposes at high temperatures without oxygen) human waste into biological charcoal (biochar). After the fair, the system will be shipped to Nairobi to process two tons of human waste daily, at a facility located in the slums.
A toilet that converts human waste to fuel gas
Delft University of Technology, The Netherlands
A toilet system that applies microwave technology to transform human waste into electricity. The waste will be gasified using a microwave-induced plasma. This process will yield synthesis gas (syngas), a mixture of carbon monoxide and hydrogen. The syngas will then be fed to a solid oxide fuel-cell to generate electricity.
Diversion for safe sanitation
Participating organizations: Eawag: Swiss Federal Institute of Aquatic Science and Technology; EOOS, Switzerland
A functional model of a urine-diverting toilet that recovers water for flushing. The urine and feces will be safely transported to a decentralized processing center. The water used for cleaning will be recycled by a gravity-driven biological membrane.
A toilet that produces biological charcoal, minerals, and clean water
Loughborough University, United Kingdom
A toilet that transforms feces into a biological charcoal (biochar) through hydrothermal carbonization (decomposition at high temperatures without oxygen and in water) of fecal sludge. The proposed system will be powered from heat generated by combusting the produced biochar and will be designed to recover water and salts from feces and urine.
A urine-diverting combustion toilet
National University of Singapore, Singapore
A toilet that uses biological charcoal (biochar) to dry and combust feces. The heat generated will be used to extract water from urine by boiling it under pressure. The system can be fitted with activated carbon and exchange resin to recover highly purified water.
A community bathroom block that recovers clean water, nutrients, and energy
University of Kwazulu-Natal, South Africa
A toilet system that can safely dispose of pollutants and recover materials such as water and carbon dioxide from urine in community bathroom blocks. The system will separate the urine from the feces and extrude the feces into thin strands for faster drying and stabilization.
A toilet that sanitizes feces and urine to recover resources and energy
University of Toronto, Canada
A technology for treating solid waste streams through mechanical dehydration and smoldering (low-temperature, flameless combustion) that will sanitize feces within 24 hours. Urine will be passed through a sand filter and disinfected with ultra-violet light.
Not Flush with Cash
Simple, affordable sanitation innovation in Durban
I met with sanitation experts in Durban who have developed a safer and inexpensive alternative to the pit toilets used by many poorer families around the world.
In 2009, during a foundation trip to South Africa, I met with Neal Macleod, head of Durban Water and Sanitation. Neal is a health expert working to improve sanitation so people no longer have to use pit toilets such as the one in the photo.

The typical developing world toilet is just a pit. You dig a hole in the ground, you put up a shack around it, and in some cases you put some kind of seat in there. There may or may not be water or toilet paper. It’s pretty unattractive, particularly the smell.
Neal showed me an improved toilet model called a Ventilated Improved Pit latrine or V.I.P. The Ventilated Improved Pit latrine is set up so that air flows down through the toilet, down into the pit and up through a pipe which dramatically reduces the smell problem. And by putting the right mesh wiring on the top of the pipe, flies can’t get in.
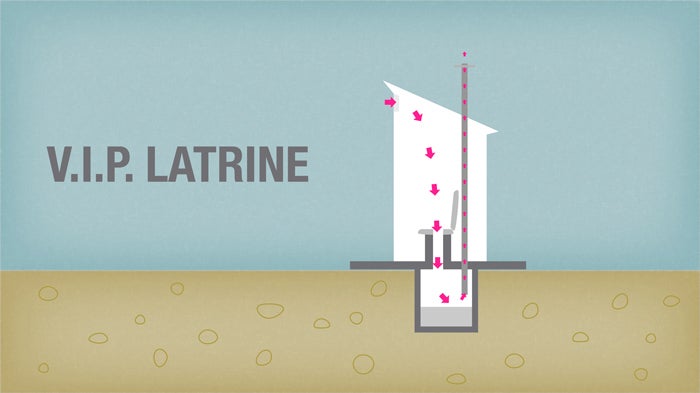
One challenge is that you’ve got to empty the pit. In preparation for emptying a pit latrine, large plastic containers are lined up behind the toilet.

The workers have to wear gloves and protective masks to empty the latrines.

Workers pump out waste from a pit latrine. They would remove the liquid waste by using a hand pump.

Workers empty the waste from a pit latrine into large plastic containers. Each pit would yield 25-60 of these huge buckets full of waste.

Treatment is Working
Why I’m Committed to Turning the Tide on AIDS
A decade ago, almost no one in Africa was receiving drugs to treat HIV. AIDS was a death sentence. Now more than 8 million people in developing countries, the majority of them in Africa, have access to life-saving treatment.
Florence Daka is a healthy mother of four who lives in Lusaka, Zambia. She sees her children off to school every morning and works a full day cleaning offices.
That may not sound extraordinary, but it is. It’s extraordinary because Florence is alive and well and living with HIV, thanks to the effective treatment that she takes. What’s more, the medicines that Florence received during her last pregnancy helped her avoid transmitting HIV to her youngest son, Stephen, who is now a healthy two-year-old.
When I met Florence during a visit to Zambia earlier this year, I was struck by her story and how she and Stephen are living proof of the tremendous progress that we’ve made in the fight against AIDS.
A decade ago, almost no one in Africa was receiving drugs to treat HIV. AIDS was a death sentence. Now more than 8 million people in developing countries, the majority of them in Africa, have access to life-saving treatment. The cost of HIV drugs in Africa has plummeted by more than 99%, and most pregnant African women who are infected with HIV now have access to treatment to prevent mother-to-child transmission of the virus.
It’s important to celebrate this tremendous progress—progress that seemed unimaginable just a decade ago – and to stay committed to the fight against HIV. That’s why I joined government leaders, philanthropists, faith leaders, entrepreneurs and entertainers at the Kennedy Center’s Eisenhower Theatre last night to recognize what the world has achieved in turning the tide on AIDS.
This week, the International AIDS Conference will be held in the United States for the first time in more than 20 years. And last night’s Kennedy Center event – with 1,000 global health advocates in attendance—offered a great stage to share success stories and talk about the importance of sustained HIV funding.
I talked about the strong leadership that the President’s Emergency Plan for AIDS Relief (PEPFAR); the Global Fund to Fight AIDS, Tuberculosis and Malaria; and developing country governments have taken to expand access to treatment and prevention.
I also thanked public and private sector leaders in the U.S. for maintaining America’s long-standing commitment to HIV research and development (R&D). Our country still provides 70 percent of all funding for HIV R&D, including efforts to develop more effective and longer-lasting prevention methods and an HIV vaccine. Americans can be justifiably proud of the tremendous moral leadership that the U.S. has taken in producing breakthrough innovations in the fight against HIV.
But America isn’t in this effort alone. I’ve been honored to meet people around the world who are committed to funding and leading critical R&D activities. And I have told them that the Bill & Melinda Gates Foundation is committed to working with partners everywhere to accelerate the discovery and development of new tools to treat and prevent HIV.
Tomorrow, I will be part of a panel at the International AIDS Conference that will discuss what’s needed to sustain progress against HIV in tough economic times. I look forward to sharing my ideas in a follow-up post.
A Test Worth Taking
Florence Daka, an HIV-Infected Mother of Four
In Zambia, I met Florence, who was successfully treated for HIV.
On my trip to Zambia earlier this year, I visited the Coptic Mission Hospital in Lusaka and had a chance to meet with Florence Daka, a mother of four who is alive today because of the effectiveness of HIV drugs.
It was important to hear Florence’s story, because she helped me understand why the decision to get tested and take HIV drugs isn’t always so easy. In Florence’s case the drugs also prevented transmission of HIV to her newborn son—an example of what can be achieved if we keep our focus on HIV treatments, in addition to fundamental research. In Zambia, the spread of HIV from mother-to-child is one of the most frequent ways AIDS has spread—where more than 15% of the adult population is living with the disease but many do not know it.
A Tough Challenge
In Pakistan, Victory Against Polio is in the Hands of Local Officials
Pakistani leaders are working hard to support polio activities.
I met recently with a group of Pakistani national and provincial leaders waging war against polio in a handful of areas where the dreaded disease still exists.
Over the last 25 years, 122 countries where polio was once endemic have eliminated the disease. Just three countries remain: Pakistan, Afghanistan, and Nigeria. Reducing polio infections by more than 99 percent over the last quarter-century could not have been achieved without a sustained commitment from all countries to mount this successful global public health effort. But the hard work of reaching thousands of vulnerable children is largely a challenge that falls to local officials.
In Pakistan, eradicating polio is an especially unique challenge—although I’m optimistic, Pakistan will continue to make progress. A recent report by the Independent Monitoring Board affirms this optimism.
Last year, Pakistan had more polio cases than any other country. But since the beginning of this year, overall, polio cases in Pakistan have dropped by 67%, from 69 cases in 27 districts at this time last year, to 23 cases in 13 districts since the beginning of 2012.
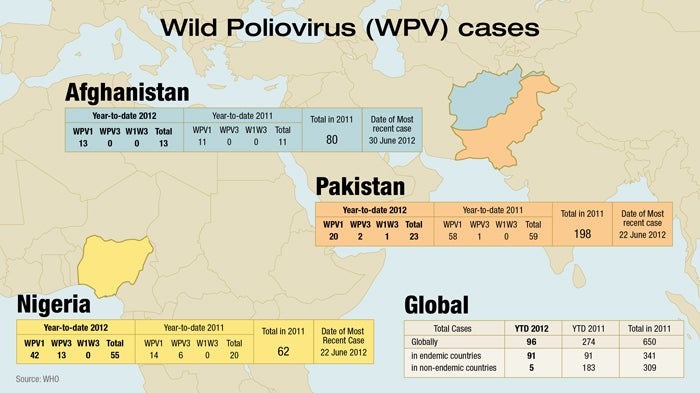
It recently devolved its national health ministry, which means provincial and local officials have to work extra hard to coordinate polio and immunization activities. There are areas such as the semi-autonomous tribal region in northwest Pakistan where conflict and insecurity prevent vaccination activities. Much has recently been written about new challenges that have arisen, including an alleged ban on immunizations by some local leaders in North and South Waziristan, Federally Administered Tribal Areas (FATA). While this further complicates running immunization campaigns in an already-challenging environment, efforts are being undertaken to address the situation. It also is important to note that this affects not even 1% of the country’s target population. However, there are still some areas where the management of local polio campaigns needs to improve. Pakistan is effectively tackling these challenges with new approaches and adopting lessons learned from India.
In the U.S. and other developed countries, we take the administration of vaccines for granted. Young children get immunized when they visit the doctor. But in Pakistan, heroic health workers often have to surmount obstacles, and even risk their lives to reach children who are unprotected. Vaccine teams are enlisting the support of religious leaders to help counter misperceptions about immunizations and suspicions that they are part of a plot. They also are adopting proven methods to reach children in migrant communities where vaccinator teams that speak the local dialect have been recruited to reach local populations and give them more confidence in their efforts. And where it’s encountered political instability and insurgency, the polio program has tried to coordinate with the Pakistani military to get access for vaccinator teams and to try to ensure their safety.
As of last month, there were 16 cases of polio reported in Pakistan.
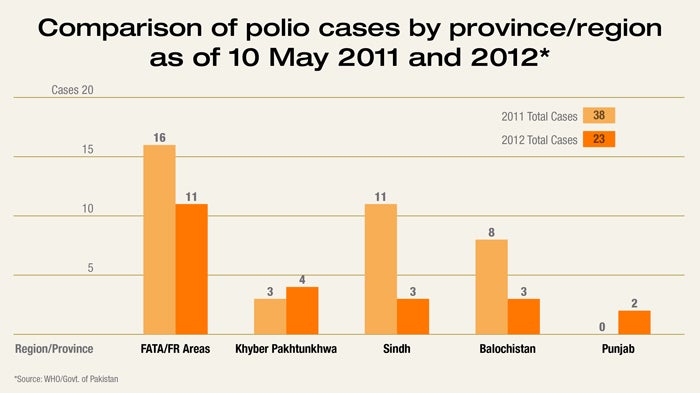
That doesn’t sound like a large number, and the progress that it demonstrates is worth acknowledging.
But polio is a cunning disease. Ninety-nine percent of the people who carry the virus don’t show any visible effects, so it’s hard to know who has it and where it’s traveling until a reported case shows up. In a country with a population of 175 million people, you can imagine how difficult this is.
But India has proven that it can be done in a country with a population of 1.1 billion. Earlier this year, it was removed from the list of polio endemic countries after going a full year without a new case of wild poliovirus. India’s success proves that polio can be defeated in the most challenging circumstances.
It was clear in my meeting with the Pakistani provincial leaders and several national officials who joined them that there’s a strong resolve to finish the job. They were very open about where efforts have fallen short. And the fact that the Pakistanis were willing to travel to India to meet with Indian health officials after their meeting with me really underscored their commitment.
India and Pakistan don’t always see eye-to-eye on things, so seeing the Pakistanis and the Indians sharing what is working and some of their common problems in solving polio was very encouraging. Their meeting was also a chance for India to help their neighbor, and a reminder that they need to stay vigilant in their own country.
Failing to completely eradicate polio would create a very real risk for the rest of the world - a resurgence that could affect tens of thousands of children worldwide getting infected. On the other hand, eradicating polio will result in benefits of up to $50 billion by 2035 in the world’s poorest countries. Our investment in polio eradication is also laying the foundation for delivery of other cost-effective health services—including vaccines for other preventable diseases.
Despite current challenges, my meeting with the Pakistanis and action taken on polio and vaccines by the World Health Assembly reinforce my confidence that we truly are on the verge of ending polio. India has proven that a strong commitment by political and community leaders, well-managed and high-quality vaccination programs tailor-made to local circumstances, and adequate financial resources can get the job done.
When it comes to polio, the Pakistanis and the Indians want the same thing we all do—a world in which no child ever gets this preventable disease again. But the responsibility to end this disease doesn’t just lie with the countries where polio transmission continues, we all have a responsibility to ensure a polio-free world.
One Success Story
HIV/AIDS & Avahan
The Avahan center is helping to reduce the spread of AIDS.
One of the reasons for my recent trip to India was to congratulate the team at Avahan on their fantastic work and transition to management by the government of India—this is an incredible achievement. The Indian government will be scaling the program and supporting it over the long term.
When I was in Bangalore recently, I visited an Avahan supported drop-in center for sex workers that is one of the success stories in India’s effort to reduce the spread of HIV. The center is run by a local community organization that provides counseling, medical help, HIV prevention training, and a microfinance bank to about 19,000 sex workers. This center is one of many programs which are part of the larger Avahan HIV prevention project. The program is targeted at millions of the people most at-risk for contracting and spreading the virus. The foundation helped get Avahan off the ground and has supported it for the last 10 years—its transition to government management is a great example of what collaboration with governments can achieve.
Meeting the People
The Urban Health Initiative in India
The Urban Health Initiative helps women in slums get contraception.
I always look forward to visiting India for the opportunity to meet people who are benefiting from projects we’re supporting in key health areas, like family planning, polio eradication, and HIV/AIDS.
On my recent trip, I spoke with several women in one of Lucknow’s urban slums who told me how grateful they are to have a choice of contraceptives. That hasn’t always been the case and there are still many poor women who don’t know about or have access to contraceptives. Efforts like the foundation-supported Urban Health Initiative are designed to change that by educating more women about contraceptive choices and practices like spacing births further apart.
This is a top health priority for the foundation because it directly affects the health (and often the survival) of poor women and their babies. And it offers them something that all mothers desire and deserve—the opportunity to provide their children with a high-quality education and the best chance of success growing up.
Exporting Hope
The Serum Institute of India
I toured the Serum Institute and met founder Dr. Cyrus Poonawalla.
Serum Institute is an impressive company that was founded by Dr. Cyrus Poonawalla and his brother in 1966 to manufacture low-cost vaccines for Indian use. Today their company makes more vaccines than any other manufacturer and delivers them to 140 countries around the world. And the great thing is their products are very high quality so they’ve really been able to fill a huge need for affordable vaccines. It was an honor to meet with Dr. Poonawalla during my visit to India. Serum’s contribution to global health has just been amazing.
20 Years of Growth
India’s progress
In India I saw how aid and spending on health can make a difference.
India’s progress over the past 20 years has been quite phenomenal. It deserves recognition especially now, as rich countries consider whether to continue investing in global development assistance despite all the economic problems they face at home.
India still faces many challenges. More than 400 million Indians live in extreme poverty. The country is home to half of all the world’s malnourished and underweight children and one fourth of the world’s tuberculosis.
But over the past 20 years, India has really emerged as a dynamic, influential country. It’s been one of the world’s fastest growing major economies, and it’s playing an increasingly important role in world affairs, including as a member of the G20 and the BRICS group of newly industrialized nations.
The current situation in India is quite hopeful. The country has a lot of talented people. The universities are improving. Government spending is going up because of the nation’s economic strength. Some reforms are needed, and that’s progressing, gradually. India represents all the challenges you face when you have lots of people living in poverty. And so India can contribute to how we solve problems globally.
A lot of progress has come from the nation’s culture of innovation, which has produced some really original and creative solutions. Yet, aid also has played an important role. Our foundation has invested more than $1 billion USD in programs to fight disease and poverty in India. I’m pleased with the results, and we will invest more in the future.
During my recent visit, I had a chance to see the latest progress on things that matter a lot to us: on eradicating polio and curtailing the spread of infectious diseases like HIV/AIDS and tuberculosis, for example. And I saw how India is emerging as a model and increasingly a catalyst for improvement in other developing countries. For example, India has become a world leader in the development of high-quality, low-cost vaccines and other bio-pharmaceuticals, which are playing a huge role in improving health not only in south Asia but also in Africa and elsewhere.
Ending Polio
It’s now been more than a year since the last new case of polio was reported in India. In February, India was officially removed from the list of polio-endemic countries.
This is especially great when you look at it in context. Three years ago, India had more polio cases than anywhere else in the world. Its polio problem seemed like the toughest to tackle. Compared with the countries where polio persists, India is bigger by far, with the most kids, and still has regions where sanitation is poor. Within the country there’s lots of movement, which tends to spread infection.
Yet, India really stepped up to the challenge on polio. The government funded its own eradication program. They really educated mothers about why vaccination is good for kids. Twice a year, 2 million volunteers prepare 800,000 vaccination booths around the country—at schools, hospitals, and community centers. They immunize more than 172 million children one by one. Working with partners like Rotary International, WHO, and UNICEF, they have built an impressive infrastructure for delivering health services to some of the most underprivileged children in the world. And they have been very persistent in following up to find kids, even the kids of migrant workers, to get vaccination levels up above 90 percent. And so the disease stopped.
India is very proud of this achievement, and rightly so. It’s a direct result of political will, dedicated resources, and rigorous management and accountability. The commitment of government leaders has been critically important.
And that commitment is helping with other health problems. By extending vaccination into the poorest and most inaccessible places, the drive against polio has helped establish better public-health delivery systems that can improve the well-being of millions of children and families.
India’s experience carries lessons for developing and newly industrialized countries around the world. It proves that success can be achieved – against polio and other diseases, as well – even in the most challenging circumstances.
Curbing HIV/AIDS & Tuberculosis
Another great example of India’s progress is in its work to halt the spread of HIV/AIDS. Our foundation has been helping with this for a long time. With a number of Indian partners, we started the Avahan program. It’s fighting HIV/AIDS in communities and at the street level, helping local groups deploy peer-to-peer counselors, distribute condoms and provide HIV testing, treatment and care.
Important leadership has been provided by the national government, which has increased funding for HIV/AIDS and established a national strategic plan that includes community-led HIV prevention. The National AIDS Control Organization has done great work. NACO and Avahan have contributed to a 50-percent reduction in the incidence of HIV/AIDS over the past six years. That’s saved India something like $100 million USD in health costs averted because of fewer AIDS cases.
Now, NACO is facilitating a smooth transition of Avahan to management by the state governments. This transition is very important and encouraging because it indicates India’s resolve to sustain the fight against HIV/AIDS for the long haul, which is what it will take to really beat this thing. This is a great example of what collaboration between funders and governments can achieve.
Lessons learned from HIV/AIDS work have helped with other critical health efforts, like the Ananya partnership, which is really scaling up programs to improve maternal and child health. India is also a model for other countries on how to scale up HIV prevention efforts.
The country faces many other health challenges. For example, India has the largest tuberculosis epidemic in the world, with nearly one thousand deaths from TB each day. But there’s a solid basic TB control program and a real commitment to getting TB under control. The government has an ambitious strategic plan to provide universal access to good diagnosis and treatment to all TB patients. This plan can prevent the emergence of multidrug resistant TB thru prompt diagnosis and appropriate treatment.
India has begun to execute this strategy by making TB a nationally notifiable disease, which means cases must be reported to authorities. This will help ensure they get the care they need regardless of whether they are being treated by government or private doctors.
India is also using its leadership in information technology, which could be a big help to government and private health providers in monitoring the spread of the disease, improving the efficiency of the TB control program and in treating patients.
Leading on Low-cost Vaccines
Just a few decades ago in India, many basic vaccines were hard to get. They were almost all imported from overseas. But today, Indian manufacturers play a critical role in driving down prices for vaccines and making them available to not only Indians but also millions of poor people worldwide.
One of the leaders in this transformation is the Serum Institute, in Pune. I visited with Serum’s chairman Cyrus Poonawalla and other executives. Their work is absolutely vital to our foundation’s work around the world, because Serum is extremely good at making high-quality vaccines for many different diseases – and doing it at low cost so that poor countries can afford them.
Serum has gradually evolved from making relatively simple vaccines for things like tetanus to making more advanced ones. In response to a request from African leaders for a better weapon against meningitis epidemics, Serum developed a vaccine for meningitis A, the first vaccine created specifically for poor countries. Serum is developing important new vaccines against rotavirus, which causes diarrhea and vomiting that kills hundreds of thousands of children in poor countries every year.
Serum's the world's highest-volume provider of vaccines – does it at very high quality, very low price. It’s a great example of the potential for innovation in developing and newly industrializing countries – innovation that can benefit poor people everywhere.
Achieving Progress through Collaboration
Prime Minister Manmohan Singh recently committed to raising government investments in health to 2.5 percent of GDP by 2017, which will really help extend health services to more people and will pay big economic dividends in the long term.
During my recent India trip, I was very glad to see the evolution and strengthening of our partnerships with government. I spoke with many government leaders including the dynamic chief ministers of two states, Bihar and Uttar Pradesh, which are among the poorest in the country. I was very impressed with the forward strides they’re making. The chief minister of Uttar Pradesh, Akhilesh Yadav, is under 40, the state’s youngest chief minister ever.
In Bihar, chief minister Nitish Kumar has helped drive remarkable improvements in farm productivity and is taking steps toward big improvements in health. Bihar’s maternal mortality rate is among the highest in India. But good things are happening. Last year our foundation launched a five-year, $80-million USD grant made in partnership with the state government and leading Indian and international non-government organizations. Bihar is becoming one of the nation’s biggest success stories.
As in Bihar, one important reason we invest in India is that we’ve found the government can be a very effective partner. Our government partners there are especially good at scaling up the very best ideas and sustaining them over the long term, as they’ve done with polio and now with HIV/AIDS.
This pattern has been repeated across the country over the past several decades. And as a result, aid has steadily become a smaller and smaller portion of the national economy. This is the good that can happen when aid donors and governments work hand in hand.
The People I Met
My trip to India
When I visit India, I speak with many people to learn about the country.
India is a fascinating country and I always learn so much from the people I meet. Sometimes it’s a challenge to reconcile the extremes. On the one hand, there are a lot of talented people and some amazing things going on there. But there’s also a huge amount of abject poverty in places like the Ujariaon slum in the state of Uttar Pradesh. People live in makeshift homes and face a lot of health problems. Yet, when I got a chance to talk with them, they’re like people everywhere. The people living in the slums want their kids to get educated and they are optimistic that things are going to get better. It was touching to hear their stories.
Reasons to Visit
Why India?
In this visit, I was interested to learn about India's progress in health.
I’ll soon be posting a full video about my recent trip to India. But first, a preview video and some thoughts about why I went. I go to India at least once a year to see the progress of the work our foundation is doing there. India is a fascinating, dynamic country, and I always learn so much from the people I meet.
We’ve been working in India for a long time, investing more than $1 billion in programs to fight disease and poverty. Originally we were focused mostly on preventing the spread of HIV/AIDS. That effort has become a great model for how to really scale up HIV/AIDS prevention, and it’s now transitioning to government sponsorship. This year’s trip was a chance for me to thank and congratulate everyone involved in the transition and in India’s progress against HIV/AIDS.
The trip also was a chance to celebrate the fact that India has now gone more than a year without recording a new case of polio. I also wanted to learn more about India’s progress as a developer and manufacturer of vaccines and other medicines that can help improve public health throughout the developing world.
Those are just some of the reasons why I went to India. The video on this page explains more, and I’ll share a lot more in the video that will be posted later this week.
Wash Your Hands
Can a simple, safe childbirth checklist save lives in developing countries?
I had the privilege recently of meeting Atul Gawande, a brilliant physician who’s using an amazingly simple concept—checklists for medical practitioners—to save lives and reduce health care costs. With support from our foundation, Gawande is investigating whether a safe childbirth checklist can increase the survival rate of mothers and newborns during childbirth in India and other developing countries.

It’s a well-known fact that hand washing and sterile instruments prevent the transmission of germs during medical procedures. Yet, many doctors and nurses frequently don’t follow these basic protocols.
It’s an especially big problem in developing countries—where many hospitals and clinics lack a basic standard of care.

Dr. Atul Gawande, a high-regarded U.S. surgeon and researcher, may have found the solution: a 1-page checklist that helps health workers avoid the major causes of maternal, newborn, and intrapartum (stillborn) deaths. Although it seems like a simple and obvious approach, no one has ever created a safe childbirth checklist. And until Gawande showed a few years ago that a simple checklist could save lives and avoid complications during surgery, there was no common checklist for that either. His work on developing and implementing checklists has had a dramatic impact on health care in the U.S. and around the world. Could we extend that insight to the developing world for childbirth?
I was a bit skeptical when I first heard about the power of a simple checklist. It sounded almost too good to be true. But Gawande’s research team tested the checklist idea with 8,000 patients undergoing surgery in eight cities around the world. On average, the checklist resulted in a 47% reduction in deaths and a 35% reduction in other complications.

At a time when most things about healthcare are getting more complex and costly, Gawande’s checklist is simplifying healthcare and saving money and lives. And the great thing is that it’s proving to be scalable without adding additional expense—a rare achievement in healthcare. So far, 4,000 hospitals worldwide are using the checklist approach to reduce errors during surgery.
In India, the safe childbirth checklist that Gawande’s research team developed in consultation with the World Health Organization is showing promising results. At the start of a pilot study at one childbirth center, health workers used only about one-third of the practices on the checklist—things like washing their hands before a vaginal exam, using a sterile blade to cut the umbilical cord, and introducing breastfeeding within an hour of birth. After the checklist was introduced—and with the coaching and guidance of the hospital administrator—compliance with best practices checklist shot up to 86%.
Our foundation is now funding a more extensive trial to see if the checklist can be scaled effectively to increase maternal and newborn survival in 120 hospitals in the Indian state of Uttar Pradesh. We focused on Uttar Pradesh because it is one of the poorest states in India. The mortality rate there for women giving birth is more than twice the rate elsewhere in India and over 30 times greater than in the U.S. So the potential impact in terms of saving lives is huge. And if the results are as positive as we hope, the childbirth checklist could be introduced in other developing countries.

One of the things that excites me about the checklist approach is that it focuses on improving health care by empowering the people working in local hospitals and clinics. And it doesn’t cost a lot of money. Getting the checklist right is critical, and not as easy as you might think. But once that’s done, Gawande’s approach is to train a handful of doctors or administrators and encourages them to coach their colleagues. We know that this kind of peer-to-peer coaching works well in other professions, such as teaching.
I first came across Gawande when I read one of his articles in The New Yorker, where he’s a staff writer (in addition to being a practicing surgeon, associate professor at Harvard, researcher, and book author). Gawande writes about his profession—and about his own experiences as a doctor—with an honesty and authenticity that is both refreshing and eye-opening.
I had the opportunity to meet him recently and he’s an impressive guy—one of a handful of people who’s really thinking creatively about how to improve the quality of health care and get costs under control. I’m optimistic there are other simple solutions that can similarly increase the quality of health care and lower costs at the same time. And if we can show their effectiveness in health care, we may discover they can be applied in other fields—such as education—where we also need to improve quality and make the most of limited resources.
Reaching High-Risk Groups
Avahan: Winning Against HIV/AIDS in India
One reason I was very excited to be visiting India recently was to get a chance to check on our foundation’s efforts to support the work of the government of India to halt the spread of HIV/AIDS. India is making good progress and learning lessons that could be helpful in other countries.
In 2003, we worked with Indian partners to launch a project called Avahan, which means “call to action” in Sanskrit, an ancient language of India. The project is a partnership with many Indian NGOs, state and local governments and the national government, which has increased funding for HIV/AIDS and established a national strategic plan that includes community-led HIV prevention.
Avahan’s efforts have been focused on reaching high-risk groups in six states of southern India, where the virus is most prevalent, and elsewhere along the nation’s major trucking routes, long-haul truckers being among those at high risk. Others we’re trying to reach include sex workers, their clients and partners, men who have sex with male partners, and injection drug users.
About 2.7 million people in India are infected with HIV, but that number is far below the dire forecasts that some experts predicted for India a decade ago. Avahan and India’s other efforts have contributed to a 50-percent reduction in HIV/AIDS incidence in the past six years, saving $100 million USD in averted health costs and, more importantly, saving many lives. One estimate puts the number of infections averted in the six states at more than 100,000.
Avahan is engaged in communities and at the street level, helping local groups deploy peer-to-peer counselors, distribute condoms and provide HIV testing, treatment and care. A big part of the effort is aimed at reducing the stigma that often prevents people from seeking HIV prevention and treatment services.
India has taken ownership of its national response to HIV/AIDS and is transitioning the Avahan program to state governments, facilitated by India’s National AIDS Control Programme. During my recent trip to India I was pleased to congratulate in person a number of the leaders who has been involved in transitioning Avahan and sustaining India’s HIV/AIDS prevention efforts.
In Bangalore, I got to spend time at a community center that’s part of Avahan. The center, known as Swathi’s Women's Group, was set up by sex workers to help prevent the spread of AIDS in their community. It’s been quite successful at that, and now it does lots more, like running a micro-finance bank and helping members defend their rights. It’s a great self-help success story.
The India program stands out as one of the best examples of effective national scale up of HIV prevention efforts, but those efforts will need sustained funding and government leadership. We’re hoping that what we learn in India will encourage and guide increased prevention efforts in other parts of the world.
In Bangalore
India: day three
My third day in India started with a visit to a community center that’s doing great work helping reduce HIV and providing support to sex workers. The day concluded with a meeting with a number of business leaders and philanthropists to talk about giving.
I started my last day in India at a Bangalore community center called Swathi’s House—a drop-in center for sex workers that’s part of a foundation-supported HIV prevention project called Avahan. The community members gave me a traditional Indian welcome, called an aarti. It was a day to celebrate, because the program is being handed off to the government for long-term support. But the real driver of success are the members themselves.
The center is run by a remarkable community-based organization called Swathi Mahila Sangha, which has approximately 8,500 members out of a population of about 19,000 sex workers in Bangalore. They provide counseling, medical help, HIV prevention training and a micro-finance bank. All of this is done with a cadre of peer educators and outreach workers. It’s a great model for self-help and empowerment.
I was touched by the community’s honesty and resolve—and their entrepreneurial spirit. Roughly half of the members now have savings accounts and their micro-finance bank has $800,000 USD in assets, with a recovery rate of nearly 100%. (I think most U.S. banks would be envious.) Thanks, in part, to their efforts, rates of HIV and sexually-transmitted diseases are down and the woman I talked with spoke of no longer feeling alone and helpless. They were proud of being able to keep their money, instead of remaining victims to “the thugs and the goons.”
Even though they are still a marginalized group, the sex workers are succeeding in advocating for their own rights and are enthusiastic about getting even more sex workers signed up and involved. There’s also been tremendous progress at the government level tackling the problem of HIV infection head-on, and Avahan and community centers like Swathi House are great examples.
I spent the last part of my trip at a gathering of a number of business leaders and philanthropists. I was the guest of two remarkable individuals. Azim Premji is the founder of Wipro and one of Asia’s biggest philanthropists. Ratan Tata is one of the country’s foremost business leaders and a member of the Tata family well known throughout Indian industry and philanthropy. They were nice enough to invite me to make a few remarks at the beginning, but mostly it was an opportunity to listen and learn about their perspectives on philanthropy in India.
While the circumstances for giving are unique in India, it was amazing just how much their discussion sounded like the conversations I’ve had with wealthy business people and philanthropists in the U.S. and elsewhere. A few common themes emerged. People agreed it was often easier to make the money than to give it away in a thoughtful way. There was a huge feeling of personal satisfaction in their philanthropic work, and a deep sense of societal obligation to give back. With so many problems to address, deciding where to engage and how to do it weighs heavily on their minds.
The group decided they wanted to get together again to learn from one another and talk through issues of common interest. That was fantastic. India is in a new phase of its long history of charitable giving, and I am certain many of these families are going to lead the way by doing remarkable things.
It’s been a very productive and moving three days. I’m grateful I had the chance to meet with so many amazing people in a short time. I’ll post some thoughts on the trip as a whole as well as some video the week of June 11. There’s a lot to reflect on.
Vaccines and Mangoes
India: day two
My second full-day in India started with a meeting with a high-level delegation from Pakistan of people working on eradicating polio in their country. It was tremendously kind of them to come to Delhi to see me. We had a lot to discuss.
The delegation was led by Shannaz Wazir Ali, who is Prime Minister Syed Yousaf Raza Gillani’s Special Assistant for polio eradication. I’d met her early last year in Dubai, to talk about ridding Pakistan of this terrible disease, and so it was good to catch up on progress made in the intervening months.Accompanying her were a group of public health officials and, most importantly, leaders from many of the provincial governments who are on the ground working toward this tough but important goal.
That this meeting happened in India is significant for several reasons. But the fact that India has been without a case of polio for over a year now is a terrific achievement. Besides meeting with me, the group will also spend time with Indian public health officials, sharing best practices and learning from one another. The conditions in Pakistan are really difficult, but you could not hope to find a more committed group of people than the delegation I met with. Many of the public health workers fighting to end polio in Pakistan risk their lives doing so. These are true heroes who face incredible obstacles -- misperceptions about the vaccines, remote and migrant communities, the need to go into villages that are dangerous because of violence and political instability.
But if India could beat polio (at least so far) in places like Uttar Pradesh and Bihar, I know Pakistan can do the same for its people. There are 16 cases reported in Pakistan so far this year. While that’s not a big number, it represents a huge vaccination challenge. I don’t wish to underplay the challenge, but seeing the Pakistani delegation’s resolve and desire to make polio eradication a national priority encouraged me.
Later in the day I visited the Serum Institute of India. This is an amazing company, and its facilities would be considered state of the art anywhere in the world. Serum produces low-cost, high-quality vaccines used in 140 countries around the world. It started out in 1966 to manufacture low-cost vaccines for Indian use. But over the years, Serum’s low-cost vaccines have literally transformed the world of health. By lowering the cost, you expand the reach of these miracle drugs. So I was really honored to be welcomed by Dr. Cyrus Poonawalla, who started Serum with his brother, and whose commitment to low-cost access has made a huge difference to millions of people around the world. This year, Serum will ship a billion doses of vaccines worldwide.
I was able to meet with a number of Serum’s top scientists and got to look at their impressive manufacturing line. I was particularly happy to see their work on the Pentavalent vaccines. This is a 5-in-1 vaccine given to children to protect them from life-threatening haemophilus influenza type B, diphtheria, pertussis, tetanus and hepatitis B. Serum’s work has dramatically lowered the cost of these vaccines (and a great many others) and is a true contribution by India to the well-being of the world.
A couple of commenters have asked about the weather, and I’ll admit – as a guy from Seattle – that the temperatures have been a challenge (44 Celsius – 112 Fahrenheit today). The upside is that it’s the height of the mango season right now, and I’ve been lucky enough to get them at just about every meal. They’re spectacular.
I finish up in Bangalore on Friday where I’ll once again be spending time with two distant ends of the spectrum. In the morning, a meeting with sex workers involved in an HIV prevention program called Avahan and I’ll end the day listening to some of India’s wealthiest families about their thoughts on philanthropy.
Real Courage
Zambia: On the front lines waging war against HIV and Malaria
The hints of progress I saw at an HIV clinic in Zambia.
The AIDS epidemic in Zambia is a sobering reminder of the big health challenges many African countries face. However, we are beginning to see encouraging signs of progress.
The government of Zambia and non-profit health clinics like the Coptic Mission Hospital that I visited in Lusaka are doing great work treating HIV patients. I wish more people could have an opportunity to meet people like Florence Daka, a mother of four who is alive today in Zambia because of the effectiveness of HIV drugs. Florence’s story is even more compelling because the drugs she takes also prevented transmission of HIV to her newborn son. The spread of HIV from mother-to-child is one of the most frequent ways AIDS has spread in Zambia—where more than 15% of the adult population is living with the disease but many do not know it.
Even more encouraging, I talked with men who are courageously setting aside cultural views and getting circumcised because they understand it significantly reduces their risk of getting or transmitting AIDS. The goal with AIDS is to have a vaccine that will prevent anyone from getting the disease. But we're more than a decade away from having that. So one of the best tools we have right now, other than behavior change, is male circumcision.
One of the important things we’ve learned about the spread of AIDS is that it occurs less often in communities where men have been circumcised for cultural or religious reasons. But the big question was whether you could convince a large percentage of adult men who weren’t circumcised as infants to come in for the procedure. An important breakthrough was the invention of a small device called a Shang Ring. It is considered safer than the standard surgical procedure, costs less, and is acceptable to men. This is great news because it enables health officials to scale up the procedure.
Many countries in Africa are launching national programs to encourage circumcision. In Zambia, the government has set a target of circumcising 80 percent of the male population—nearly 2 million men. Kenya, South Africa, Botswana, and Tanzania are also starting to show leadership in this area.
I was also heartened to see the progress in Zambia against malaria, which like AIDS is a devastating disease that disproportionately affects the poor. Fifty years ago, the only way to slow malaria was to spray DDT—a highly toxic chemical—on walls. But in recent years, countries like Zambia have launched an intensive effort to distribute mosquito bed nets, medicines, diagnostics and insecticides that have dramatically reduced the number of young children dying from the disease.
Zambia was one of the first countries to pilot widespread distribution of bed nets and the foundation has been a funder of that effort. Zambia’s program is so well run and effective that the government hopes to eliminate malaria in five regions by 2015 and completely eliminate it throughout the country by 2030. That kind of goal would have been unimaginable even a decade ago.
Combined with the successes I saw in Ethiopia providing basic health services for women and children and boosting agricultural productivity for small farmers, there are a many reasons to be optimistic that many people in Africa are on the road to self-sufficiency. One of the jobs of our foundation is to make sure other donor countries and governments understand the important progress being made—progress that is really changing the quality of life for millions of people in Africa.
Modeling Progress
Ethiopia: exciting innovations in agriculture and health
In Ethiopia, I saw advancements in farming and health services.
Ethiopia is one of the poorest countries in the world and has faced enormous challenges feeding its people and providing critical health services to mothers and their children. Yet, I returned from a recent visit excited about advances the country is making in agriculture and health.
If these innovations—which are a top priority for our foundation—succeed, they can be replicated in other African countries that also face big challenges in health and agriculture.
One factor in Ethiopia’s progress is Prime Minister Meles Zenawi and his leadership team, who have played a key role in reinventing the country’s agricultural and health systems. Making changes to either would be a big challenge in any country, so it’s even more impressive in Ethiopia, which has the second largest population of any country in Africa but a limited economic infrastructure.
Around 85 percent of the country’s population survives by growing crops on small plots of less than five acres. But frequent droughts and soils that have been depleted of nutrients often led to low crop yields and considerable food insecurity. More than half of the country’s population of 83 million is malnourished and more than 5 million households receive food aid each year.
Our foundation has been working with the Ministry of Agriculture, the county’s new Agricultural Transformation Agency, and other partners to help farmers plant higher-yielding, drought-tolerant seeds, improve soil health and fertility, and get higher prices for their crops by selling to global markets.
At the Melkassa Research Station, one of 13 government-run agricultural outposts, Dr. Markus Walsh, Sr. showed me a new, state-of-the-art technology called NIR spectroscopy that’s part of a digital revolution in agriculture. This portable device, which quickly and cheaply analyzes soil conditions, is a fantastic breakthrough that will help farmers everywhere. But it’s especially valuable in countries like Ethiopia, where farmers haven’t been able to afford laboratory tests but need to know how to amend soils to grow better crops. The spectroscopy is part of an even bigger agricultural digital information system that will provide a comprehensive and detailed map of soil properties across the country.
I also met with a number of farmers to talk about new varieties of sorghum (a grain) and beans they are growing. Beans are very important because they provide protein and people need a combination of protein and grain to have a reasonable diet.
Helping small farmers sell their crops in world markets is another important part of the work we’re supporting in Ethiopia. It’s currently a big challenge because poor farmers may not be growing the right crops for world markets and they often lack the roads, trucks, and other infrastructure necessary to enable exports. And getting foreign investors to help build this “value chain” can be difficult. But I visited one agricultural processing facility called ACOS, that is processing and shipping a variety of beans to European markets. It is jointly owned by an Italian company and Ethiopian investors and is a great example of private investment in developing countries.
What Ethiopia is doing in health is really a model system because it reaches everyone in the country. I visited the Germana Gale Health Post, where I talked to several of the more than 30,000 health extension workers who have been trained in recent years to deliver basic health education, prevention, and treatment. Most of the health workers are women, and those I met were energetic and well-trained.
These kinds of primary health services—giving vaccines, educating women about family health, and promoting hygiene and environmental sanitation—is the foundation for building good health systems in poor countries. Ethiopia’s health system also includes district health centers like the Dalocha Health Center I visited. There, they do a little bit of surgery and have more expertise and a wider variety of drugs. There are also primary hospitals that focus on higher level treatment and some emergency surgery, and general hospitals that deal with serious emergencies and high-risk and specialized care.
Ethiopia still faces some big problems. But the people I met and what I saw re-energized me and increased my optimism that the big investments we and other donors are making in health and agriculture will pay off for the people of Ethiopia and can serve as model activities in other African countries. Improving agricultural productivity and the quality of life through better health services is the key to unleashing the potential of Ethiopia and other poor countries and getting them on the road to self-sufficiency.
Science, Soil, and Seeds
Agriculture in Ethiopia
Most of the world’s poorest people are farmers, and so helping them improve their lives involves expertise in soil science, seed hybridization, and agricultural marketing. All of which are being used to end hunger and raise living standards in Ethiopia, as I observed during my recent visit.
Africa’s farmers get their food and income from farming small plots of land. They grow a variety of crops, which are often threatened by diseases, pests and drought.
One of the biggest challenges farmers face is unproductive soil. For Ethiopia, the Africa Soil Information Service is generating a digital soil map to diagnose local conditions and make targeted recommendations for improved crop production.
Soil samples are collected and analyzed using near-infrared spectroscopy, which is both portable and less expensive than traditional wet chemistry analysis. Samples are analyzed against a library of 500,000 entries.
The Ethiopian Institute of Agriculture Research has 13 stations that support technology development for sorghum, maize, common beans, and horticulture crops (onion, tomato, fruits). Bill visited the Melkassa Research Station in Nazaret, Ethiopia.
One of Ethiopia’s main crops is sorghum. It grows well in harsh conditions and is self-pollinating. There are many varieties, used for food and brewing.
Sorghum breeder Alemu Tirfessa shows Bill the diverse breeds, and describes hybrid seed production. The new hybrid seeds are more resistant to disease and drought.
The many varieties of beans grown in Ethiopia are grouped by market classes. Beans are a very important crop because they provide protein, which helps create a balanced diet when paired with grain.
Bill spoke with representatives from the Lume Adama Farmers’ Cooperative, which helps farmers set pricing, get credit, and gain access to improved seed. One farmer said that thanks to increased chickpea production, she’s doubled the number of oxen she owns and has earned enough money to send her four children to school.
Keeping the Pests Out
A simple advance in crop storage aids poor farmers in Africa
Reducing spoilage from weevils helps farmers store and sell more crops.
On a recent trip to Africa, I saw the incredible impact that simple innovations can have on the world’s poor. For years, farmers trying to eke out a living growing cowpeas—a protein-rich staple—would lose as much as half their crop to weevils. As I showed students during a recent talk at Stanford, a simple, inexpensive triple-layer bag invented by researchers at Purdue University enables farmers to protect their entire crop. This allows farmers to charge more for their crops and has increased their incomes by as much as 30 percent.
Innovation on Small Plots
Working together for small farmers
I urged leaders of the international agriculture community that they need to do better for small farmers.
If you care about poor people, you need to care about agriculture.
Most extremely poor people in the developing world get their food and income from farming small plots of land. Many others live in big cities and need access to inexpensive food to be healthy and productive. So helping small farmers grow more food sustainably is the best way to fight hunger and poverty over the long term.
History is on our side. In the past several decades, agricultural yields in many places have doubled, and hunger and poverty have been cut in half. Now it is time to continue and accelerate that progress.
This week, I am speaking to the leaders of the international agriculture community at a meeting at the International Fund for Agricultural Development. The audience will be made up of the key people working in developing countries, aid agencies in developed countries, and international groups like the World Food Program and the Food and Agriculture Organization—and my message is that they need to do better for small farmers.
I am urging them to get together to set a common productivity target and create a system of public scorecards to hold themselves accountable. If they take these steps, I believe it is possible to meet the world’s most aggressive goals for reducing hunger and poverty.
One of the most important priorities is connecting the poorest farmers in the world to breakthroughs in agricultural science and technology. Right now, a digital revolution is changing the way farming is done, but poor small farmers aren’t benefitting from it.
For example, we now have satellites that can identify instantly and precisely how much wheat there is in a field. However, many developing countries are still sending people out with a pad, pencil, and tape measure to estimate yields. As a result, we take more time and expense to get less accurate and incomplete data. Better data, collected in a timely way, means decision makers have better information to make policies that can help farmers. That is one examples of how a digital revolution can make a difference.
Innovation is the concept on which Melinda and I created the foundation. For years, we saw the impact that innovation in the computer industry had on the richest people in the world. But at the same time, the poorest half was hardly benefitting from innovation at all. We hope our foundation can work with partners to help change that.
The stakes could not be higher. The world’s ability to help small farmers be more sustainably productive will determine whether or not they remain in poverty or whether the hard work results in self-sufficiency for hundreds of millions of people.
Swatting Mosquitoes
Using Disease to Fight Disease
A novel approach to controlling mosquito populations
Most people probably wouldn’t want to visit a mosquito research lab on their family vacation, but Melinda and I were in Australia recently and were excited to see some amazing work in molecular biology that could lead to a breakthrough in controlling mosquito-borne diseases such as dengue fever.
Mosquitoes are a plague in much of the developing world, not just because they are a nuisance, but because they are transmission agents for some truly terrible diseases. The scientists we met with in Cairns have discovered a way to infect mosquitoes that are normally capable of carrying diseases like dengue and yellow fever with a bacterium called Wolbachia. Wolbachia is naturally present in many types of insects, but not in these mosquitoes. Although it is harmless to humans and most other animals, when placed in these mosquitoes Wolbachia shortens their lifespan by about 50 percent and inhibits the development of dengue virus and several other pathogens.
If mosquitoes with the Wolbachia strain can be successfully introduced into wild mosquito populations, it could greatly reduce the transmission of infectious diseases to humans because most mosquitoes would die off before the viruses that cause human disease could replicate in their body. Another plus for Wolbachia is that it alters the mosquitoes’ reproductive biology, so that when female mosquitoes that do not carry Wolbachia mate with male mosquitoes that do carry Wolbachia nearly all of their embryos die off. Since Wolbachia is passed through the mother mosquito to her offspring, this means that Wolbachia can spread very rapidly through a mosquito population.
Some of these discoveries were a surprise to scientists. If they can be proven in field trials, Wolbachia could create a cheap, natural, and self-sustaining method of control that dramatically reduces dengue fever and other major infectious diseases such as yellow fever and malaria.
The research, led by Professor Scott O’Neill of Monash University, has been funded since 2005 by the Foundation for the National Institutes of Health (FNIH) under the Grand Challenges in Global Health initiative, which encourages innovation to solve persistent health problems in the developing world. Diseases spread by mosquitoes are definitely at the top of that list.
O’Neill’s work is mainly focused on preventing mosquitoes from transmitting the virus that causes dengue fever, an infectious tropical disease that causes 22,000 deaths—mostly among children—and results in 500,000 cases of severe illness each year. Scientists are optimistic that this approach could also work with other insect-transmitted diseases such as malaria, which kills nearly 1 million people annually, mostly children under 5 years of age.
Historically, the battle against disease-carrying mosquitoes has relied on repellants, insecticides, bed nets and eliminating stagnant water breeding sites. More recently, scientists have been working on vaccines that would prevent people from getting infected with mosquito-borne diseases.
To do his current research, O’Neill has had to convince people in Cairns that releasing mosquitoes in their neighborhoods is a good thing. Melinda and I participated in one release of about 20 jars of mosquitoes—probably 1,000 mosquitoes in all. I was bitten by several dozen, but was safe from getting dengue fever because the mosquitoes being released were lab-reared and not infected with dengue. I have a lot of respect for the volunteers who go into mosquito cages and allow themselves to be bit in the name of science. The average number of bites they get is over 50!
It was fascinating to see the project first-hand. There’s a real possibility that this approach will get deployed broadly and could really help reduce a lot of disease transmission. But as exciting as it was for Melinda and me, our kids said they definitely didn’t mind not going along.
A Bunch of Reasons
Building better bananas
I'm sometimes asked why the foundation has made agricultural development a priority along with global health. Actually, the two are intertwined. One example comes from Australia and Uganda, where researchers are using advanced technology to try to improve the banana.
Our foundation’s work around the world gives me opportunities to meet really smart, visionary people who are doing pioneering work in fields that I might not get a chance to learn much about otherwise. For example, in December Melinda and I went to Cairns, Australia, where James Dale and his team from Queensland University of Technology are doing advanced research on bananas. As odd as that might sound, this research could make a big contribution to public health in a lot of Africa and Asia.
Before our visit, I didn’t know much about bananas. Dale, an agricultural scientist, is one of the world’s leading experts. He has been profiled in The New Yorker, in a fascinating article about the history of bananas as an export crop. As the article explains, a blight has spread among plantations in Asia and Australia in recent years, badly damaging production of the one type of banana that is grown for export, the Cavendish. This disease, a fungus, hasn’t spread to Latin America yet, but if it does, bananas could get a lot scarcer and more expensive in North America and elsewhere. Dale is working to develop new versions of the Cavendish that resist the fungus. He does this by inserting genetic material from other organisms into banana plants.
This work is separate from the research that our foundation supports, although some of the same techniques and scientific principles are involved, including transgenic experiments. Making banana plants less susceptible to diseases is a secondary goal for us. Our primary goal is to help Dale develop new types of banana that are more nutritious—specifically, much richer in Vitamin A and Iron that the body can absorb.
This is important because the diets of millions of people in Africa are deficient in both of these vital nutrients. While rare in the developed world, Vitamin A deficiency in developing countries causes hundreds of thousands of children to go blind each year. It also reduces the body’s ability to fight infection, which raises the fatality rates in poor countries from infectious diseases like measles. Iron deficiency is so serious and widespread that in Uganda, for example, more than 40 percent of young children have stunted growth and 73 percent are anemic.
Meanwhile, bananas are a primary staple of people’s diet in Uganda and many other African nations. (Our foundation also has supported research to enhance the micronutrient content of cassava, rice and sorghum, all staples for millions of the world’s poorest people.) An average Ugandan consumes about five times his or her weight in bananas each year. Fortunately, Ugandans have more varieties of banana to choose from than we usually do in the developed world. Some varieties are eaten raw, while others are cooked as part of a dish with other ingredients. The kind that are cooked are sometimes called plantains, but they’re all bananas. For dessert there’s the sweet Sukali Ndizi, which children especially love.
Unfortunately, the banana varieties grown in Uganda are low in essential micronutrients, particularly Vitamin A and Iron. To increase these levels, Dale and his team in Australia are collaborating closely with Ugandan scientists at that country’s National Agricultural Research Organization. The NARO team, led by Dr. Wilberforce Tushemereirwe, has made important contributions—developing research protocols, conducting field trials, and planning distribution of new, more nutritious banana varieties to Ugandan farmers. The NARO team’s involvement is a great example of young African scientists playing a major role as full partners in using state-of-the-art science for development of new products important to agriculture and health in their own country.
Our foundation has supported this work since 2005, initially as part of our Grand Challenges in Global Health initiative, which fosters early-stage research aimed at breakthroughs on the world’s most pressing health problems. If you had asked me at the time, I would have said the project was one of the more wild things we funded. Some of the original Grand Challenges projects, even some of the ones I thought were the most likely to succeed, have come to an end, but that’s scientific discovery.
Other funders have not been focused on the kind of work that Dale and NARO are doing, so our funding has been important, and the work is progressing well. New banana varieties have been developed that have as much as five times more Vitamin A than before. You have to get the levels just right, though, because too much makes the banana look orange, which consumers might not like. Boosting iron levels seems to be a tougher challenge.
It all takes a long time, though, for a few reasons. Not much was known before about how to work with banana cultures at the molecular level, so a lot of basic science had to be done first. Then, it takes two or three years to take a new banana culture from inception to the point where it produces fruit and you can see if it’s more nutritious. And there have been some unfortunate setbacks. In early 2011, Cyclone Yasi roared through Cairns and destroyed the fruit crop from field trials there. Luckily, the cyclone did not uproot the plants, but the trials were delayed at least nine months until a new crop of bananas could grow.
Once some clearly superior banana varieties are developed and proven, it will take time to do the research to show the health benefits, for regulators to approve them, and for farmers to begin planting them.
It’s great that we started back in 2005.
Fighting Crop Disease
Cassava: can science save a diet staple?
In Tanzania last year, I visited with farmers whose survival – like that of millions of other Africans – depends on the cassava, a diet staple threatened by disease. I also visited with African scientists on the forefront of efforts to protect the cassava and other vitally important crops.
In Tanzania last year, I visited with farmers whose survival—like that of millions of other Africans—depends on the cassava, a diet staple threatened by disease. I also visited with African scientists on the forefront of efforts to protect the cassava and other vitally important crops.
Cassava is a staple crop that provides a basic diet for more than 500 million people worldwide.

Cassava is a starchy root that must be processed before eating because it contains small traces of cyanide. It is often grated, dried, and roasted to make garri, a flour; the leaves are eaten as vegetables in a stew.

When dried to a powder, cassava is known as tapioca.

These cassava plants are infected with mosaic disease, making the cassava root much smaller and less nutritious.

Christina supports her family by farming cassava. In the past two years, Christina’s crop has been invaded by two cassava diseases. Because of these diseases, she is depleting her savings to buy cassava to feed her three children. For Christina and other small farmers getting food is the most pressing daily concern.(Mapinga Village, Tanzania)

When I was in Tanzania last year, I met Dr. Joseph Ndunguru, a plant scientist leading a project to fight the mosaic and brown streak diseases that attack cassava crops. Dr. Ndunguru is part of a new generation of African scientists building up the capacity to do innovative science in Africa.

Keep Giving
A plan to assist the world’s poor
Advances in agriculture, education, health, and sanitation have led to a dramatic decline in child deaths over the last 50 years. But the global economic crisis is putting at risk the development aid so critical to continuing this progress. As Congress considers foreign aid in the coming weeks, I encourage policymakers to consider the remarkable impact of American aid, its benefits to the U.S., and the contributions of a growing number of donor countries.
Fifty years ago, almost 20 million children under the age of 5 died every year. In 2010, the figure was down to 7.6 million. This 60 percent decline in childhood deaths — reflecting advances in agriculture, education, health and sanitation — is compelling evidence of the increasing justice in our world.
But the global economic crisis is putting the long-term trend of progress at risk, as Congress’s debates about the foreign aid budget underscore.
I am giving a report Thursday to the heads of the Group of 20 governments, including President Obama, suggesting creative ways for the world to continue investing in development despite fiscal constraints. I hope three key ideas become part of congressional deliberations over the coming weeks.
First, programs funded by U.S. generosity have been a core component of this 50-year project of raising living standards around the world.
Aid is targeted to fill specific gaps in development. The most important of these gaps is innovation. When the private sector doesn’t have incentive, and poor governments don’t have the money, smart aid pays for breakthrough solutions. The green revolution that fed a billion people in the 1950s and ’60s never would have happened without advanced agricultural science funded by U.S. aid. In just the past 10 years, millions of children have been saved from diseases such as measles and whooping cough by vaccines that Americans paid for through their contribution to an organization called the GAVI Alliance. Immunization is a great example of how aid can be effective. Thirty-six cents worth of measles vaccine protects a child for a lifetime.
Second, development isn’t just good for people in poor countries; it’s good for all of us. It used to be that the world was, roughly speaking, one-third rich and two-thirds poor. Now, the number of dynamic, healthy, highly educated countries is much higher, which is a recipe for prosperity. Imagine the world economy without Brazil, China, India, Indonesia, South Korea, Mexico or Turkey.
If countries that are currently poor can feed, educate and employ their people, then over time they will contribute to the world economy. On the supply side, they’ll increase the production of key commodities such as food, keeping prices lower. On the demand side, as their citizens are more productive, they’ll become important markets for trade.
But if people don’t get access to basic necessities, continued suffering will lead to economic stagnation and instability. It is, for example, not only unconscionable but also a strategic mistake to allow famine to devastate the livelihoods of millions of people in the Horn of Africa.
Third, the United States is not doing development alone. We spend about 1 percent of our total budget on aid, as do dozens of donor countries.
And with only a few exceptions, the amount poor countries spend on their own development is much greater than the amount donors invest. Ethiopia, for example, has in the past five years built 15,000 rural health posts to provide improved services for its citizens.
There is also a group of rapidly growing countries — including Brazil, China and India — that combine recent experience with development and significant technical capacity, giving them the insight and the skill to have special impact. For instance, China is sequencing 10,000 varieties of rice to help small farmers cope with climate change. These efforts can make a big difference. For example, a new submergence-tolerant rice variety being used in flood-prone areas of Bangladesh and India can more than double farmers’ yields. We predict that 20 million farmers will be planting this variety in the next six years.
The private sector hasn’t always invested as much in development as it should because the market incentives haven’t always been clear, but there are ways to encourage involvement. In my report to the G-20, I’ll make half a dozen recommendations for mobilizing tens of billions of dollars annually from private sources. The African diaspora is sitting on $50 billion in savings that could fund development in their home countries if it were captured through diaspora bonds.
If the transaction costs on remittances worldwide were cut from an average of 10 percent to an average of 5 percent, it would unlock $15 billion a year in poor countries. In addition, there are trillions of dollars in sovereign wealth funds, and a portion could be reserved for key infrastructure projects in poor countries.
Sometimes Americans get the impression that we’re shouldering the whole burden of development and that, ultimately, our aid doesn’t make a big difference. I see it very differently. We’re providing strategic investments that link up with many other investments to systematically make a better, more prosperous and safer world. If we do it right, we can keep shrinking the number of countries where aid is needed to zero.
This was originally published on November 1, 2011 in the Washington Post.
More Work to Do
Why we must outsmart mosquitoes
The decisions we make now will determine what happens to malaria in the future.
On October 18, at the foundation’s second annual Malaria Forum, I spoke about the progress being made in the war against the dreaded parasitic disease. But more needs to be done to control and eradicate it, including a higher level of preventive drug treatment for pregnant women, additional research on chemical repellants, and further investigation of vaccines and drugs to treat those who are infected.
Prepared Remarks by Bill Gates
Thank you, Melinda.
Melinda told you about some of the people we met in Tanzania recently. I was impressed by a man named Prosper Chaki, who runs a larviciding project in Dar es Salaam. He spends his days wading into the standing water where anopheles mosquitoes breed, so he can poison them. It’s not so surprising that he’s gotten malaria 20 times.
“Mosquitoes are smart,” Mr. Chaki said. Then he told us, “We have to be smarter.”
I believe we will be smarter. One reason is that you have come from all over the world to this forum—to challenge each other, to disagree with each other, and to learn from each other. When you leave tomorrow, our team at the foundation will move forward with the benefit of the most rigorous thinking in the world. We are grateful to you for that, and I hope each of you will take inspiration back with you as you continue your personal fight against malaria.
The other reason I believe we will be smarter is that human beings have a spectacular ability to innovate. Innovation is one of the most powerful forces in the world. It can make the impossible, possible.
Melinda talked about the innovations that have changed the course of malaria and saved a million lives in the past 10 years.
But innovations are only as good as our commitment to delivering them. We have to get better at using the innovative tools we have.
Intermittent preventive treatment with drugs during pregnancy and infancy are two proven methods of protecting those most at risk from malaria, but they’re not saving as many lives as they should be. For example, most countries in sub-Saharan Africa provide IPTp in less than 20 percent of pregnancies. That is not good enough.
We have to demonstrate the same level of commitment as new tools come online. I am very optimistic that Seasonal Malaria Chemoprevention will be available starting early next year, when the WHO’s approval process is complete. We must be aggressive in launching pilot studies to understand how this intervention should fit into control strategies, so we save as many lives as possible, as quickly as possible.
We also have to be thinking simultaneously about the next generation of tools. If we think big, bring more partners into the fold, and take smart risks, we will invent novel tools—powerful ways of fighting malaria that don’t exist now. This is the kind of innovation that will enable us to plan for the eventual eradication of malaria.
Eradication is an ambitious goal—and a long-term goal. It is also a goal to which we remain 100 percent committed.
We are committed to it for moral reasons. My children will not die from malaria, thank God. Since that is true, no child should die. It should never be too expensive or too inconvenient to give the poorest a chance to survive when the richest already have it. Equity is not yet a reality, but it is what we believe in and what we are striving for.
We are also committed to eradication for strategic reasons. The only alternative to charting a course to the end of malaria is an eternity of trying to stay just one step ahead of the parasite and the mosquito. If we have to fight in perpetuity, the cost in lives will be enormous. The opportunity cost of never being able to divert our attention to other challenges will be incalculable.
I know some people in the malaria community worry that focusing on the uncertain goal of eradication could distract us from control measures that are working today. I understand the desire to stay focused on saving lives. But I don’t see eradication and control as two separate approaches to the fight against malaria. Instead, they are two compatible parts of a single approach. To achieve elimination and eradication, we need to start with control, drive it up to high levels, and sustain it. But if we don’t target elimination and eradication, control will lapse, and malaria will continue taking lives.
It will take leadership and innovation and money to extend the recent success. It will also take leadership and innovation and money to plan for malaria’s eventual eradication. The conclusion is daunting, but inescapable: We will need enough leadership and innovation and money to do both. We do not have the luxury of choosing one or the other.
I am an optimist. I believe we are capable of setting our sights on an ambitious goal with a generation-long time horizon and multiple, shifting milestones along the way. But eradication will never happen as long as it remains a general aspiration. We must turn it into a specific plan, and our job now is to lead the constant search for new and better tools that will help us execute our plan, step by step.
The best tool we have now is bed nets. Nets are a fantastic innovation, but they’re not perfect and they won’t be sufficient. They are expensive, they are unpleasant to sleep under, and they don’t protect against outdoor- and daytime-biting mosquitoes. There is a clear need for cheaper, easier to use, and more powerful vector control methods.
I am enthusiastic about spatial repellants, chemicals that can keep mosquitoes away from treated areas. Repellants could be a big improvement over nets, because the people benefitting from them wouldn’t have to make the choice to sleep under them every single night. The likelihood of human error or human resistance would shrink by a lot. And spatial repellants would be effective against all types of mosquitoes, no matter when or where they bite.
Recent trials in China showed that mosquito coils containing a chemical repellent decreased people’s odds of contracting malaria by about 80 percent—and coils plus nets were much more effective than coils or nets alone. Right now, additional trials are taking place in Indonesia to confirm the impact of coils on transmission and to measure their impact on the mosquito population. We expect data from this critical proof of principle study in the middle of next year.
Researchers are also busy identifying potential active ingredients for spatial repellants. Larry Zwiebel of Vanderbilt University just isolated a compound that is 1,000 times more powerful than DEET. Other researchers are looking at other formulations, and results from these studies will be available in two or three years.
ACTs are the second tool that has changed the course of malaria control over the past several years. Obviously, they represent a vast improvement over the old drugs that weren’t effective, but, like nets, they are not ideal. Artemisinin is expensive, the course of treatment lasts several days, and resistance is already developing.
The Medicines for Malaria Venture currently has a drug candidate in phase II trials, OZ 439, that has the potential to be a single-dose cure. This could solve many of the problems with ACTs. It should be cheaper, since the total amount of drug needed for treatment will be lower. Adherence will be much higher, since people will have adhered completely as soon as they swallow the pill. This will decrease the risk of treatment failure and slow the development of resistance.
OZ 439 could be licensed as early as 2016, depending on the suitability of the quinolines currently being tested as partner drugs. In addition to finishing the trials, MMV is working to find a partner from the pharmaceutical sector to help it make and market OZ 439 when the time comes.
One of the most important innovations for the future of the fight against malaria will be a tool we don’t yet have: a vaccine. A vaccine is a wonderful thing. It’s the simplest, most cost-effective way to save lives. The smallpox vaccine, plus the innovative approach of ring vaccination, led to the eradication of smallpox. The polio vaccines have pushed the world to the threshold of eradicating polio. Vaccines have slashed the number of deaths caused by diphtheria, measles, tetanus, and a host of other diseases.
But the search for a malaria vaccine has been a long and frustrating process. There has never been a vaccine for a parasitic disease. The scientific complexity is dizzying.
Today, however, we are closer than ever before to tackling that complexity. Four years ago, I announced interim results from phase II trials of the RTS,S vaccine. Today, I am pleased to announce the interim results from the phase III trials. Among five to seventeen month old children, the vaccine prevented clinical malaria in 55.8 percent of trial participants over a period of one year. RTS,S prevented severe malaria in 47.3 percent of trial participants aged five to seventeen months. It prevented severe malaria in 34.8 percent of the entire study population, including infants.
These are only interim results. We need to study the data over a longer period of time to understand whether the effect of the vaccine diminishes. We also need to evaluate the impact of a booster dose. Leaders must have all this information before they can make decisions about how to use the vaccine if and when it’s approved.
Nevertheless, these results signal a huge milestone, and I want to congratulate the many partners that have been working on this project for decades. First, this is proof that it is possible to create a vaccine that is effective against malaria. For a long time, we didn’t know. Now, we know. Second, if RTS,S continues to show effectiveness of around 50 percent—above and beyond bed nets—it has the potential to protect millions of children and save thousands of lives.
And RTS,S is a first-generation vaccine. It is an early outcome of a long process of innovation that will ultimately yield more effective vaccines. Researchers are currently recruiting participants for the phase I trials of a second-generation RTS,S vaccine.
There are many vaccines that work according to completely different mechanisms in various stages of development. I am particularly excited by the potential of transmission blocking vaccines, vaccines that prevent mosquitoes from picking the infection up from human hosts. In the drive toward elimination and eradication, these vaccines will be invaluable.
But the fact is there are still many basic science questions about malaria that we need to answer to make the search for vaccines less challenging. We know there are mechanisms by which people become immune to malaria. We can even produce that immunity artificially, but we don’t understand it. If we get a better sense of what underlies immunity in those cases, we will have a much better chance of filling the vaccine pipeline with good products.
As we develop these new tools, we also have to develop a more sophisticated understanding of how to deploy them. When you have several ways to fight more than one species of parasite, carried by many species of vector, you can’t afford to guess about strategy. What is the smartest way to combine our interventions so they have the maximum effect? We need to be able to answer these questions with evidence.
I believe modeling can help generate that evidence. I want to walk you through some charts from one malaria model to give you a sense of the kinds of answers they can provide.
When our friend and mentor Warren Buffett made his gift to our foundation five years ago, he was clear about the purpose philanthropy should serve. One of his famous quotes about finance is, “I don’t look to jump over 7 foot bars. I look around for 1 foot bars that I can step over.” Philanthropy is the other way around, he tells us. We should be looking around for the 7 foot bars; that’s why we exist.
Malaria eradication is a high bar. To reach it, it will take a constant, concerted effort to innovate. But we can do it. We can drive down the number of cases, lower and lower. We can keep introducing new and better tools, until we interrupt transmission like we’ve done in dozens of countries already. And, eventually, with relentless focus, we can eradicate malaria. We’ve already shrunk the malaria map considerably. We can make it disappear.
It won’t happen in four years, or in eight years. But the decisions we make now will determine what happens to malaria in the future.
The parasite has been killing children and sapping the strength of whole populations for tens of thousands of years. It is impossible to calculate the harm malaria has done to us. Now, we can chart a course to end it.
Thank you.
In Africa
Visiting Tanzania: A Battleground in the Fight Against Malaria
On my most recent trip to Tanzania, Melinda and I spent time looking into how the foundation’s partnerships to reduce malaria are progressing.
On a recent trip to Tanzania with Melinda, we spent time focused on the foundation's efforts to reduce malaria. We were particularly interested in learning about the progress of research into a malaria vaccine.
Bagamoyo District Hospital
These children were waiting to see a doctor at the Bagamoyo District Hospital in Tanzania. They are among several thousand children participating in field trials of the vaccine, known as RTS,S. Just this week, interim results from the clinical trials were reported, and they prove that it’s possible to create a vaccine that’s effective against malaria. It was exciting to visit this clinic because it is so well run, they're offering lots of good health services, and people are coming from far away to participate in the vaccine trial.
Meeting with Health Officials
We met with health officials from the Bagamoyo District Hospital and the Ifakara Health Institute. There were a lot of visiting scientists from the Swiss Tropical and Public Health Institute, which has a close relationship with the IHI. We saw scientists who are working on ways of repelling mosquitoes so people don’t just have to rely on bed nets, which are only partly successful protection against malaria. It's great that the foundation’s support is helping with the vaccine, and that it is also helping train young scientists and building up a research infrastructure, which will have a lot of long-term benefits.

Ifakara Health Institute
Scientists at the Ifakara Health Institute were great at educating us about their work, including techniques for capturing mosquitos to help prevent malaria, what species of mosquito they were focused on, how they get the vaccine out into the field, and how they saw if the vaccine worked.

Meeting with Hospital Staff
We also met with staff at the local hospital to discuss progress treating and preventing malaria.

Mapinga Village Dispensary
We visited the Mapinga Village Dispensary, which is an example of how healthcare is delivered in Africa. These dispensaries are the first place people go for care in or near their villages. We saw how the dispensaries keep their vaccines, and we talked to people like Neema Malachi Najwale, the nurse in charge of the Mapinga Dispensary, about how they get mothers to come in for the vaccines. We also talked about how they can now use cell phones to send regular status reports on their inventory.

Meeting with Parents
We talked with some of the parents of children participating in the vaccine trials. Although Tanzania is quite poor and hasn't developed a very extensive infrastructure of roads and electricity, in the health area they've done pretty well. They have good vaccine coverage and are on track to meet a lot of the Millennium Development Goals. It’s a great example of the progress taking place in Africa.

Defeating Malaria
At the Mapinga Village Dispensary, we talked with the head nurse about a number of diseases they have to deal with besides malaria. But by far the biggest killer of children and adults in that area of Tanzania is malaria. So the enthusiasm among health officials for the new malaria work there is very high. I’m an optimist when it comes to defeating malaria. There is good progress with the vaccine, drugs to prevent and treat malaria, and other preventive measures. Eradicating malaria won’t happen overnight, but it’s a moral and economic imperative for Africa, and for the entire world.

How We Fight Epidemics
Tackling TB Through Innovation
I explored innovation in testing and treating tuberculosis, as I spent World TB Day in India.
Many people think tuberculosis is a disease of the past, but this ancient epidemic remains a huge global problem. Each year there are 9 million new TB cases and 1.7 million deaths.
Yet there is a tremendous opportunity to turn this situation around. Most new TB cases are in major emerging economies like India, China and South Africa, which have a remarkable history of using innovation to address tough health challenges. They are adopting new TB strategies, and are poised to develop the next wave of innovations. This could change the way the world fights the epidemic.
The major problem is outdated tools. TB is preventable and treatable, but the most common TB test is more than 125 years old and misses half the cases. By the time most TB patients are correctly diagnosed and treated, they may have unknowingly infected many others – creating an endless cycle.
At the same time, today’s TB drugs are more than 40 years old and take six months to work. The combination of poor tests and outdated treatments is driving the spread of drug resistance, undercutting global efforts to stop the epidemic.
I witnessed this firsthand in 2009, when I visited the King George V TB hospital in Durban, South Africa. I met a woman with HIV who had been diagnosed with a highly drug-resistant type of TB. She told us about the despair she felt when she learned she had such a dangerous form of the disease.
Fortunately, there is a promising pipeline of new TB diagnostics, drugs and vaccines under development. And we are starting to see results. Just today, I saw how India is using these innovations. I marked World TB Day by visiting the state-of-the-art L.R.S. Institute of Tuberculosis and Respiratory Diseases in New Delhi with Dr. Ashok Kumar, head of India’s TB program. L.R.S. uses a new molecular test, GeneXpert, which can accurately determine whether a patient has TB in about two hours.
Molecular diagnostics could revolutionize TB care, and things will continue to improve as the price comes down and new tests are developed. This is where India could have global impact. India is a leader in developing low-cost health technologies, and the country could produce high-quality, inexpensive molecular TB diagnostics. This would increase access at home and across the globe.
Meanwhile, South Africa is stepping up its own efforts. The country will likely begin widespread use of GeneXpert soon. This could profoundly impact health in a country where thousands of lives are lost each year to TB/HIV co-infection.
India and South Africa’s leadership shows the extraordinary potential for high-burden countries to pioneer TB innovations. Their success could be a model for other countries—and save millions of lives in the process.
Let's Finish the Job
My Annual Letter: End Polio Now
Polio, once a worldwide scourge, threatens to make a comeback unless all countries do their part to eliminate it. Eradication is tantalizingly close but funding to fight the disease still falls short.
Aid for the poorest has already achieved a lot. For example, because of donors’ generosity, we are on the threshold of ending polio once and for all.
Polio is a terrible disease that kills many and paralyzes others. Fifty years ago it was widespread around the world. When you talk to people who remember polio in the United States, they’ll tell you about the fear and panic during an outbreak and describe grim hospital wards full of children in iron lungs that maintained their breathing. At its peak in the United States in 1952, polio paralyzed or killed more than 24,000 people.
As a result of mass mobilizations to administer the polio vaccine, polio was eliminated in the United States and most developed nations decades ago. Most people who live in rich countries assume the disease is long gone and that it doesn’t kill or paralyze children anymore. But it is still a frightening presence in a number of places around the world.
In 1988 the global community adopted the goal of ending polio altogether. At that time more than 350,000 children a year worldwide were killed or paralyzed by the disease. Since then, vaccination coverage has increased significantly and the number of cases has gone down by 99 percent, to fewer than 1,500 last year. There are now just four countries where polio transmission has never been stopped: India, Nigeria, Pakistan, and Afghanistan.
That’s incredible progress, but the last 1 percent remains a true danger. Eradication is not guaranteed. It requires campaigns to give polio vaccine to all children under 5 in poor countries, at a cost of almost $1 billion per year. We have to be aggressive about continuing these campaigns until we succeed in eradicating that last 1 percent.
Therefore, funding is critical to success. Organizations such as Rotary International and the governments of India, the United States, the United Kingdom, and Japan are all major contributors to the polio campaign. Our foundation gives about $200 million each year. But the campaign still faces a 2011-12 funding gap of $720 million. If eradication fails because of a lack of generosity on the part of donor countries it would be tragic. We are so close, but we have to finish the last leg of the journey. We need to bring the cases down to zero, maintain careful surveillance to ensure the virus is truly gone, and keep defenses up with polio vaccines until we’ve confirmed success.
Why is it so important to end polio? Eradication will have three huge benefits.
The first is that getting rid of polio will mean that no child will die or be paralyzed by the disease in the future. One thing most people don’t realize is that if we don’t finish the job on eradication, we will lose a lot of the ground we’ve gained over the past two decades. The disease will not stay at its current low level. If we don’t get rid of it, it will spread back into countries where it’s been eliminated, and it will kill and paralyze children who used to be safe. Only eradication will guarantee that all children are safe.
The second benefit is that the money that will be saved by eradicating polio far exceeds what we are spending on eradication efforts now. The long-term benefits of the last couple of billion dollars spent on eradication will be truly phenomenal. A recent estimate added up the cost of treatment that won’t be necessary and the enhanced economic contribution of adults who won’t get polio. Eradication could save the world up to $50 billion over the next 25 years.
The third benefit is that success will energize the field of global health by showing that investments in health lead to amazing victories. The eradication effort illustrates so well how a major advance in the human condition requires resolve and courageous leadership. To win these big important fights, partnerships, money, science, politics, and delivery in developing countries have to come together on a global scale.
The history of polio and polio eradication is fascinating. (One of the best books I’ve read on the subject is David Oshinsky’s Polio: An American Story.) Polio was the first disease that raised significant money from the broad public. The March of Dimes was created to combat the disease. Although President Roosevelt and lots of Hollywood stars helped the campaign, its huge success came from neighborhood-based fundraising. I remember March of Dimes volunteers ringing our doorbell when I was growing up and asking for a donation. By any measure, the public’s generosity in supporting that charity made it one of the most successful health-related fundraising campaigns ever.
The March of Dimes funded research into the first polio vaccine, which was invented by Dr. Jonas Salk and introduced in 1955. It was such an important priority to get the polio vaccine out widely that the U.S. government sponsored the campaign, which it had never done before. The campaigns of the late-1950s were wildly successful, and by 1961 the number of cases in the United States was down to just 161.
A second polio vaccine—this one in the form of liquid drops that children swallow instead of an injection in the arm—was invented by Dr. Albert Sabin and licensed in 1963. By 1979 there was no more poliovirus in circulation in the United States. Dr. Salk’s and Dr. Sabin’s vaccines are still the key tools used for eradication today.
To this day, the smallpox campaign is the only successful human disease eradication campaign in history. At its peak, smallpox killed over 2 million people every year and also blinded and disabled large numbers. The eradication campaign started in 1967, the last naturally acquired case of smallpox was in 1977, and the world was certified as being free of smallpox in 1979. (Two excellent books on the smallpox eradication are Dr. D.A. Henderson’s Smallpox: The Death of a Disease and the forthcoming House on Fire by another key smallpox warrior, Dr. Bill Foege.)
Smallpox had a number of characteristics that made it easier to eradicate than polio. Almost everyone who got smallpox developed a distinct rash. In contrast most polio infections are not noticed because less than one in 100 people infected are paralyzed, even though all those infected can transmit the virus. This means by the time a paralytic case is found, the poliovirus has probably spread.
Also, the vaccines against polio are not as effective as the smallpox vaccine, which was so powerful that a single vaccination protected almost everyone. In the case of the most common polio vaccine, at least three doses are required to get 85 percent of children fully protected. In many countries of the developing world, even more doses are needed to reach the immunity levels needed to stop transmission of the virus.
But the polio campaign also has some huge advantages that the smallpox campaign did not have. The advanced science we have today lets us sequence the DNA of the polio virus and develop an understanding of the history of transmission, which guides our work. We also have far better communications and modeling tools than were available in the 1970s, and those are being used in smart ways to respond rapidly to every outbreak.
In 2003 I would have said we were just a couple of years away from ending polio, and I would have been wrong. That year there were false rumors in Nigeria that the polio vaccine caused women to become sterile. This allowed the disease to have a resurgence and to spread to many other countries. The experience of 2003 serves as a reminder to be humble as we move forward. But humility does not mean fatalism.
Fortunately those false rumors have been almost completely eliminated through the leadership of key political and religious figures. In 2009 when I visited Northern Nigeria to meet with the most important traditional leader, the Sultan of Sokoto, he committed to the campaign. It was fantastic to see him publicly giving his support. (He also gave me a horse to thank me but I told him I couldn’t take it.)
Last year both India and Nigeria had substantially fewer cases than ever before. In India the number of cases went down from 741 in 2009 to just 41 in 2010. In Nigeria, thanks in large part to the renewed leadership in the northern part of the country, the number went down from 388 to just 18. But alongside the phenomenal progress was another reminder that gains can be lost without sustained action.
The majority of cases in 2010 were in countries that had been polio-free until the virus travelled back across borders and caused outbreaks in areas where people had gotten lax about vaccination. There was a large outbreak in Tajikistan in the first half of 2010 and another in Congo in the second half. In both regions there were a number of immunization campaigns organized as a response. Today the outbreaks appear to be under control.
What those outbreaks in formerly polio-free countries prove is that eradication is a global project requiring every country to do its part. Very few projects demand global participation. In most areas each country can pursue its own approach, and countries can compare outcomes to see which approach is the most successful.
Philosopher and historian Will Durant once observed that the only thing that could get countries to join forces would be an alien invasion. To my mind, terrible diseases are surrogates for an alien invasion. If we are to succeed, the world needs leadership from a global institution and significant, coordinated resources from rich countries to fund activities in the poorest countries.
For polio, the World Health Organization (WHO) has played the central role with Rotary International, the Centers for Disease Control, and UNICEF as key partners. Polio eradication has benefited immensely from having Rotary’s support. Rotary had the vision to get involved in 1985 and has kept polio eradication as its top priority. Everywhere I go to learn about polio, I see Rotary members helping out with the hard work.
I feel sure that with continued support we will be able to show significant progress building on this year’s work. The site www.polioeradication.org tracks the key parts of the campaign including fundraising and the latest cases. I will make a number of trips focused on polio this year, including additional trips to India and Nigeria, and will write a report for the foundation website. For anyone who wants to support the polio campaign, which would be fantastic, visit www.rotary.org/myrotary/en/take-action/end-polio.
Not Letting Up
Going the last mile in India
Eastern India's Bihar state closes in on eradicating polio.
“The last mile is when people get most fatigued,” says Dr. Hemant Shukla, who leads polio eradication efforts in eastern India’s Bihar state. But having made major strides against polio, India now is closing in on it with vaccination programs for nomadic peoples and others who are hardest to reach.
Building Dreams
In China, speeding toward the future
In September 2010, I traveled through China to visit with vaccine makers, computer scientists, energy technology companies and car manufacturers.
I travelled to China for the first time in 1990 on Microsoft business and have been back many times since. One very memorable trip was in 1995 with Melinda, my father and Warren Buffett. We rode the trains and traveled around as tourists for several weeks—it was an incredible trip and a lot of fun.
My recent trip was unique and especially exciting, as I had the opportunity to do work that spans my various interests. I met with our team at Microsoft Research Asia, where I saw some incredible innovations in search and related technologies. I also met with a number of vaccine companies that are working with our foundation. For the last part of the trip, I joined Warren Buffett, Charlie Munger and other Berkshire Hathaway board members. Our main focus was a visit to BYD, an incredible company in which Berkshire owns a 10 percent stake. BYD fully lives up to its name, which stands for Build Your Dreams. It manufactures batteries, electric and hybrid cars and buses, and many highly innovative green products.
The meetings with vaccine manufacturers were about the potential for expanding development of new vaccines in China for use worldwide. Historically, most important vaccines have originated in Europe and the United States. Now, countries like Brazil, India and China are providing lower-cost versions of some of them. Ideally, they’ll also get involved in inventing new vaccines. Because these countries suffer from many of the infectious diseases that we need new vaccines for, local development could help speed vaccine dissemination. Also, because countries like China have experience in making low-cost vaccines, they could be better at designing new ones in ways that make them low in cost from the very beginning. That would be wonderful.
And so the foundation is reaching out to new vaccine companies, seeing how we can help them and what holds them back. This was my first visit with some of the companies in China. I was impressed at how quickly the industry is moving ahead. They really understand low-cost manufacturing, and they’re getting their quality up to world standards. Over the next five to ten years, they have the potential to create many breakthrough vaccines, as well as to help get current vaccines to the world’s poorest people, for whom price can be a significant obstacle.
Specifically, the foundation is trying to make sure that every child in the world gets three vaccines: pentavalent (against diphtheria, tetanus, whooping cough, hepatitis B and influenza B), rotavirus (against severe acute gastroenteritis) and pneumococcal (against pneumonia). Together, these three could reduce child deaths by almost one million per year. If we can get their cost down, then we’ll be able to get all three to even the poorest children in the world. It looks like China could help out on low-cost rotavirus and pneumococcal. So we have possibilities there, as we do in India and Brazil.
Gearing up to manufacture vaccines that meet international standards is a costly and complex process. In China we saw a flu vaccine manufacturing line that is unique in that it involves growing flu virus in chicken eggs. The plant has to buy a huge number of eggs and make sure they're all sterile. It’s quite a process, and people worry that, in the event of a big epidemic, they might not be able to buy enough eggs and grow the virus quickly enough. But in our visit to Sinovac Biotech, headquartered in the Beijing University Biological Industry Park, we saw that it has really distinguished itself by rapidly building up its flu vaccine capability. That was quite impressive.
I love any excuse for spending time with Warren Buffett, whether we’re playing golf (which neither of us is very good at) or playing bridge, which we're kind of just okay at.
Our visit to BYD was amazing. The company was started back in 1995 by a battery expert. It grew to be very strong in phone batteries and car batteries, and then, in 2003, BYD decided to make its own cars. It has about six percent of the domestic car market and plans to expand its product line and volume quite dramatically. It’s an innovative company, pushing forward on battery technology, doing electric taxis, electronic buses and electric storage systems.
BYD has created an entirely electronic bus using special batteries and a special electronic motor. The company has innovated to bring the battery cost down and the battery life up. If it works as well as planned, the operator saves enough on fuel to be able to pay quite a premium for the bus. We rode around on a prototype and participated in a ceremony where a local city committed to buy a thousand of these buses. They will be a huge help in reducing the smog in Chinese cities and could even help start to reduce CO2 emissions.
BYD headquarters is in Shenzhen, in the southeast part of China next to Hong Kong. Shenzhen is where the Chinese economic miracle started; it was a special economic zone. So I wasn’t surprised to see a lot of modern buildings and a pretty impressive car factory. But I was blown away when I heard how quickly they put up the buildings. In the U.S., you just can’t build nearly as fast.
What was even more amazing was to go to a city in the middle of China, Changsha, which has six million people, and see a new factory that will turn out 400,000 cars a year. It was built in less than two years from start to completion. Around the city, new high-rise buildings are going up where only cornfields stood just a few years ago. You hear about China’s 10-percent annual economic growth, but to fully understand you really have to see it in person. China is moving at incredible speed.
Hello, Biosensor?
Cell phone science
Most of us think of cell phones primarily as a convenient tool to stay in touch with people and store information. But increasingly, scientists are exploring ways to use cell phones to deliver critical health care to people in developing countries.
If you’re like me, you’ve probably become quite attached to your cell phone. These amazing devices allow us to do things that previously could be done only with a computer, such as search the Internet, read books, watch TV and movies, and purchase things online.
But what I find even more impressive is how researchers are examining ways to put cell phones to use to improve health in developing countries. This week, the foundation announced grants of $100,000 each to eight scientists who are pioneering the use of cell phones to improve health care in communities where resources are limited. The grants are part of Grand Challenges Explorations, a foundation-funded effort to jumpstart unconventional projects that we believe have the potential to improve global health.
For example, Peter Lillehoj and Chih-Ming Ho of the University of California, Los Angeles, received a grant to develop a disposable malaria biosensor based on a SIM card platform. The SIM card-biosensor will allow malaria detection to be performed using a cell-phone, which will make diagnostic testing more widely available in rural and remote areas.
Terry Ferrari of World Vision will be field testing the use of two cell phone modules that will help community health workers in Mozambique caring for pregnant women and newborns to assess, to take action, and to refer cases with complications and emergencies. Another mobile-phone based tool being developed by Marc Mitchell of D-Tree International uses clinical algorithms to quickly identify women at risk during labor and delivery and assist with emergency transfer to a hospital. If these tools are successful, they could significantly reduce maternal and infant mortality rates.
Mark Thomas will be leading a team at VaxTrac to field test a mobile phone-based vaccination registry that uses fingerprint scans to track people who have received immunizations. The goal is to reduce redundant doses and increase coverage levels in developing countries.
I shared information about these and other innovative cell phone projects that we’re funding today at the 2010 mHealth Summit, an international conference focusing on the use of mobile technology to improve health care in the developing world.
Cell phones are amazing tools. For some of us, they’re about staying in touch. For millions of people, it could be about staying alive.
Showing Promise
Discovery science – taking the challenge
Five years ago, the Bill & Melinda Gates Foundation awarded $458 million to research projects aimed at creating breakthrough treatments for diseases that cause millions of deaths each year in developing countries. The results are showing promise and leading to new approaches in discovery science.
This week in Seattle, I’ll be speaking at our annual Grand Challenges in Global Health (GCGH) conference. We’ll be looking at what has been accomplished and what we’ve learned since awarding the first round of GCGH grants in 2005.
We launched GCGH five years ago with an ambitious goal: find innovative ideas to tackle the most persistent health issues in developing countries. We knew that to find the tools we needed to improve health around the world, we had to think beyond conventional science. We turned to the best, most creative minds from all scientific fields—immunology, physics, biology and even engineering—and asked them to apply their talents to global health research.
In five years, scientists from around the world have taken up this challenge. For example, Dr. James Baker, a scientist and professor at the University of Michigan created a new way to prepare and administer vaccines as nasal drops. They don’t require constant refrigeration—a huge challenge in many developing countries. During the grant period, Dr. Baker was able to apply this technology to three diseases—Hepatitis B, influenza, and respiratory syncytial virus.
I find this kind of “technology platform” that you could apply to multiple diseases particularly exciting because our work is not simply about scientific discovery. It’s about delivering effective solutions. Some of what I consider the greatest successes are grants that have led to new partnerships with the potential to turn great scientific ideas into real-world solutions.
Dr. Rafi Ahmed, an immunologist at Emory University, for example, built a partnership with Genentech, a biotech company. Ahmed and his team have shown that it is possible to reinvigorate T-cells “exhausted” from chronic viral infections such as Hepatitis C and HIV—an approach that could be applied to a therapeutic vaccine or new combination treatments.
Similarly, Richard Axel, a Nobel Prize-winning neuroscientist, and Leslie Vosshall, a scientist at The Rockefeller University, are now collaborating with Bayer CropSciences and SentiSearch to continue their research on novel compounds that block insects’ abilities to find plant or human targets. The compounds they identify could become the insect repellent of the future.
Even projects that weren't scientifically successful taught us valuable lessons. For me, investing in these projects is worth the risk. I believe that risk-taking is essential if we are to develop truly transformative health technologies. And the Grand Challenges program continues to evolve as we learn the best ways to push the envelope further. So while we will continue to support this kind of innovative research, it is important that new donors and organizations do more to fund this kind of work. I believe that projects like Baker’s, Ahmed’s and Axel’s—among many others—prove that these are challenges worth tackling.
We Have Proof
Real Lives. Real Progress.
Optimism is always in short supply, but it’s needed to sustain efforts to improve global health and support development. Fortunately, thanks to development aid, reasons for optimism abound. To help highlight them, and Melinda and I are actively involved in the Living Proof campaign.
Melinda and I are heading to London in a couple of days to thank the UK for its history of generosity and remarkable commitment to foreign aid. We want to share the proof that investments in global health and development are saving lives, improving livelihoods, and building prosperous societies.
In the last 50 years, child deaths in the developing world have been cut by more than 50 percent; polio cases have been reduced by 99 percent; measles deaths in Africa dropped by 92 percent between 2000 and 2008; and malaria cases have been reduced by 50 percent in 38 countries between 2000 and 2008. Through our work, especially our visits to the field, Melinda and I have been deeply touched by personal stories of lives changed for the better. We have seen clear evidence that targeted foreign investments are saving lives, preventing and curing disease, and helping people to lift themselves and their communities out of poverty.
Earlier this year, we transferred the Living Proof campaign to the ONE Campaign. Living Proof highlights the positive impact foreign aid is making. It aims to challenge stereotypes and misconceptions about development assistance, using a series of success stories that will galvanize support, energize activists and ultimately inspire action. With the message that effective aid in global health and development is working, the campaign will share the proof that smart aid is having a lasting impact on people’s lives and livelihoods and advancing real progress in developing countries.
ONE is expanding Living Proof to reach new audiences in more countries and to highlight the lasting impact of European investments. On October 18, the ONE Campaign is launching Living Proof in London. Both Melinda and I will be there to share stories about real lives and real progress being made around the world.
For us, these success stories have a profound impact on the way we look at our investments, and we believe that telling these stories to as many people as possible can help change the way they look at what we can achieve in the future. Together with ONE and our partners, we want to get these stories and facts out and inform the conversation around the opportunities in global health and development.
We are confident that spreading the word about what’s working is one of the most important things we can do to motivate governments and others to invest in effective development aid.
Health Affects Minds
A disturbing link: disease and intelligence
For me personally and for the Bill & Melinda Gates Foundation, improving global health is a way to fight poverty as well as to save lives. The role of health in social and economic development is highlighted by new research on infectious disease and IQ.
Central to our work in global health has been the effort to reduce infectious diseases such as diarrhea and malaria in developing countries. Because these diseases no longer affect the rich world, they haven’t received the attention they should given their truly devastating impacts on poor communities, where they’re prevalent.
Infectious diseases in developing countries are important not only because of the tragic toll they take in human lives lost, but also because of the tremendous social and economic costs associated with them.
Recently I read an article in The Economist, which looks at growing evidence that disease and intelligence are connected in ways that are pretty shocking and troubling. Although more studies are needed, the evidence makes me even more convinced that we need to get after malaria and diarrhea – and many other diseases far too common in the developing world – in a big way.
Specifically, new research by University of New Mexico researchers has found that cognitive ability (IQ) is generally lower in places where infectious diseases are widespread, i.e., poor countries.
People are just now realizing this. It’s a huge scandal and yet another reason why it’s so critically important to fight infectious disease, which takes a huge toll on people’s ability to learn and climb out of poverty.
What’s going on is that fighting off parasites and microbes associated with things like diarrhea and malaria takes away energy that the body needs for brain development. This is especially true among children and infants. Newborns use almost all their metabolic energy for their rapidly developing brains. Analyzing IQ and epidemiological data from around the world, the UNM researchers found that the burden of infectious disease plays a much bigger role in depressing IQ than other possible explanations that have been talked about.
There’s also clinical evidence. For example, research in Uganda found that children who survive cerebral malaria, which affects more than a half-million African children every year, continue to suffer significant cognitive impairments, mainly memory and attention deficit, even two years later. The Ugandan researchers found that these children can be helped by weekly sessions where they use cognitive training software on PCs. But this is an expensive, intensive and only partially effective approach to a problem that could have been prevented to begin with.
The cognitive problems created by malaria are another strong reason why our foundation has made fighting it a priority. We’re trying to help develop a safe, highly effective and affordable malaria vaccine, while also supporting efforts to improve treatment, diagnostics and other malaria control measures.
Widespread infectious disease may even impair kids who don’t get sick themselves. Adults who are ill are less productive; farmers grow less food, for example. Less food means less energy available for their kids and their kids’ brain development. An article in The Lancet medical journal estimates that because of malnutrition, poverty and poor health, over 200 million children under five years are not fulfilling their developmental potential.
In the past, some people have suggested that poor countries are poor because the people there have lower IQs. But it’s really the other way around. Poverty breeds disease, which can affect brain development, which reinforces poverty. Improving global health is a way to break this cycle.
More and Better Crops
Better farms – improved lives
With support from the foundation, six nonprofit agricultural development organizations are helping hundreds of thousands of poor farmers in Sub-Saharan Africa and South Asia grow more productive, profitable, and sustainable crops.
Three-quarters of the world’s poorest people rely on farming small plots of land to feed themselves and their families. Helping these small farmers grow more crops and get them to market can have a tremendous impact on reducing hunger and poverty and associated problems.
But it’s a complicated challenge that requires support and investments across the agricultural value chain—from cultivating better seeds and soil conditions to improving farm management, access to markets, and government policies.
In 2008, we announced $306 million in grants to six organizations to help poor farming families in Sub-Saharan Africa and South Asia boost their productivity, increase their incomes, and improve their lives. When we announced the grants, I promised to post annual updates about the projects as a way to share the progress, setbacks, and lessons of our work in agricultural development.
Looking at the 2010 updates that have just been posted to the foundation website, I’m amazed at the life-changing results that our grantees have achieved in such a short time. In the last year, these organizations have touched the lives of hundreds of thousands of farmers and they are on track to help more than 5 million farming families in the years ahead.
Highlights From the 2010 Updates
In many parts of India and Africa, small farmers rely solely on rainwater to grow their crops and can produce barely enough food for their own subsistence. International Development Enterprises (IDE) last year worked with 731 agricultural equipment dealers to make affordable small-scale irrigation systems available to more than 100,000 farmers. IDE also helped about 12,000 farmers secure microfinancing to pay for the new systems. As a result, these small-farm families have been able to produce and sell surplus crops and increase their incomes by an average of $600 per year—enough to pay for school, healthcare, and invest in their farms.
The International Rice Research Institute (IRRI) is making steady progress toward its goals of providing 400,000 farmers with heartier varieties of rice that can withstand drought, flood, extreme cold, and harsh soil conditions. IRRI has trained more than 750 scientists in rice breeding and crop management, developed more than 200 new varieties of stress-tolerant seeds, and distributed over 6,500 tons of seed to farmers in the last year. And through a process called “participatory variety selection,” IRRI gets farmers directly involved in developing rice varieties that will grow best under local conditions.
In 2009, TechnoServe used its foundation grant to help provide 67,000 small-holder coffee growers in East Africa with access to equipment that enables them to process their beans into high-quality coffee. TechnoServe also helped train thousands of farmers in sustainable agronomy practices, and how to evaluate the quality of their coffee beans.
Working in Bangladesh, CARE organized more than 15,400 dairy farmers into groups that can collectively buy better feed and receive training in animal husbandry to produce larger amounts of higher-quality milk from their cows. Largely because of a sudden drop in demand for fresh milk in Bangladesh, CARE managed to link only about 5,400 farmers—a quarter of its target—to refrigeration facilities where they could store surplus milk for sale. But the organization met its goal of deploying 120 community veterinary workers, and more than 4,400 local dairy farmers used artificial insemination services provided by CARE.
In East Africa, more than 47,000 dairy farmers received help from Heifer International to form business associations and establish chilling plants that will help get the farmers’ milk to market. Although Heifer was able only to secure financing for five new chilling plants instead of 23 as planned, the new and existing plants helped farmers sell more than 118,000 liters of milk per day, more than we had expected. Heifer also helped local breeding services perform more than 56,000 artificial inseminations and is investigating new approaches to substantially increase that number in the next two years.
In Kenya and other sub-Saharan countries, the Alliance for a Green Revolution in Africa (AGRA) is bringing affordable fertilizers and training in integrated soil fertility management techniques to farmers. Although the start of these projects was delayed in 2008 because of political unrest in Kenya and rising fuel costs, AGRA has begun to make progress in helping farmers adopt more environmentally sustainable farming practices.
The annual progress reports on these organizations enable us to see what’s been working well in each program, and to adjust our strategies to address unexpected challenges and to adapt to the evolving needs of local communities and individual farmers. I’m encouraged by the strides that our nonprofit partners and the farmers are making through these programs despite challenging conditions. At the same time, I see how much more needs to be done.
Since 2006, the foundation has committed more than $1.5 billion in grants to support agricultural development efforts. The G8 and G20 nations have committed $22 billion to food security over three years and African countries and leaders are also making big increases in their domestic investment in agriculture.
This renewed attention to agricultural development is important. We know that better farming is the most important solution for overcoming hunger and poverty, and that the investments the foundation and others are making can have an incredible impact in a relatively short period of time.
Microbicide Trial
Exciting News for HIV Prevention
I believe that one important way to stop the spread of AIDS is by empowering women to protect themselves from infection. I'm encouraged that new research shows positive results from women using antiretrovirals for HIV/AIDS prevention.
As I mentioned in my speech to the XVIII International AIDS Conference on Monday, one promising area in the fight against HIV/AIDS is antiretroviral (ARV) -based prevention: pills, injections, and gels that contain the drugs now used for treatment.
And so it really was a privilege to be in Vienna when the incredibly exciting results of a new study were released. The Centre for the AIDS Programme of Research in Africa (CAPRISA) microbicide trial, the first of a new generation of ARV-based microbicides, showed reduced risk of HIV and herpes infections in women. This is the first time that a microbicide has been found to be effective.
What makes this so important is that we are a big step further in putting HIV prevention in the hands of women, who account for the majority of HIV infections worldwide.
The CAPRISA microbicide is a topical gel that contains tenofovir—an antiretroviral drug widely used to treat HIV infections which women in the study inserted up to 12 hours before sex and soon after having sex for a maximum of two doses in 24 hours.
The tenofovir gel was found to be 39 percent effective in reducing a woman's risk of becoming infected with HIV during sex. The study also found that the microbicide is 51 percent effective in preventing genital herpes, important because women with genital herpes are at greater risk for HIV infection. Widespread use of the gel, at this level of protection, could prevent more than half a million new HIV infections in South Africa alone over the next ten years saving many lives.
The CAPRISA microbicide trial findings are an exciting advance for HIV prevention. They give us reason to be hopeful, not just for an effective microbicide, but also for other ARV-based prevention tools now in development. As with any promising new HIV prevention tool, we look forward to discussions on how we might collaborate with other funders to support projects to confirm and extend these findings.
I’m really glad I attended the conference this year. As I said in my speech, even as we advocate for more funding, we need to be much more efficient in our approaches for treatment and prevention. But there was tremendous energy in Vienna and I am optimistic that we can push ourselves to make the most of every dollar of funding, to identify the most effective ways to save lives, and to share what we learn as widely as possible.
A Hopeful Message
A Roadmap for HIV Prevention
I traveled to Vienna to speak at the 2010 International AIDS Conference, the premier gathering for those working to prevent and treat HIV infection, which is a priority of the Gates Foundation. My message was hopeful, but advocated for changes to make anti-AIDS efforts more effective.
I’m honored to speak at the XVIII International AIDS Conference in Vienna today. This conference marks an important turning point in the fight against AIDS.
There are good reasons to be hopeful—we have seen amazing progress. The number of people getting treatment for AIDS has increased twelve-fold since 2003. The people at this conference and major partners such as the Global Fund to Fight AIDS, Tuberculosis and Malaria and PEPFAR have helped make this possible.
At the same time, we have to recognize that these are tough times for those of us who are passionate about fighting HIV. Economic turbulence has driven up government deficits, and some countries have responded by reducing their investments in global health. These are the challenges we all face, but they don’t have to define our time.
And that is why, even as we are hopeful, we have to be honest with ourselves: We don’t have the money to treat our way out of this epidemic. Even as we continue to advocate for more funding, we need to make sure we’re getting the most benefit from each dollar of funding and every ounce of effort.
If we push for a new focus on efficiency, especially in prevention, we can, over the next two decades, drive down the number of new infections dramatically.
Here’s how we can do that:
- We need to scale up existing tools, like male circumcision and preventing mother-to-child transmission.
- We need to focus prevention efforts on the communities where transmission is the highest, such as men who have sex with men, injecting drug users, and sex workers.
- We also need innovations in basic science, diagnostics, computer modeling, and our understanding of the virus itself. This would make it possible to create new weapons for our fight against AIDS, prevent even more infections, and save even more lives. Vaccines, new diagnostics, and antiretroviral-based prevention (pills, injections and gels) are some of the new tools I’m really excited about.
If we scale up existing interventions and add new tools in the hardest-hit countries, it would change the face of AIDS. New cases would plunge. Millions more could be treated. The control of HIV would stand alongside the eradication of smallpox as one of the great public health victories in history.
This is the opportunity we have. We can keep doing things the old way, and keep getting the same result. Or we can push ourselves to make the most of every dollar of funding and every ounce of effort: to identify the most effective ways to save lives, and to share what we learn as widely as possible.
If we do that, we will have matched our compassion with the growing capacities of science, and we will start to write the story of the end of AIDS.
Travels in India
Seeing self-help in action in India
I was on the road again in May 2010 on a visit to northern India. I came back excited by the progress I saw in villages that have suffered from dire poverty and the persistence of polio.
India is always a fascinating place to visit. I’ve now been there more than a dozen times. I went in July 2009 to look at the government’s efforts to improve health care in poor communities. I returned in May 2010 to see how things are going with projects that are trying to help eliminate polio and other infectious diseases, and help improve things for people in some of the poorest areas, specifically the states of Uttar Pradesh and Bihar in the north of the country.
I traveled to Uttar Pradesh with Rahul Gandhi, a member of Parliament. He has been a real innovator in organizing women’s self-help groups, and one of our first stops was a meeting of self-help group leaders. It was incredible to listen in on their discussions and hear them encouraging one another with songs and chants about vaccinations, sanitation and safe birthing practices. You could hear in their voices how they had gained optimism and confidence from their experiences working together.
These women go out to other villages and in the past three years they’ve helped form over 20,000 new self-help groups. The groups enable women to get microloans at lower rates than the moneylenders charge and work to improve services, like health and education, in their villages. I really can't express how uplifting it was to listen to these women talk about how they organized. If one woman couldn't get something to be done, then ten would show up. If that didn't work, 100 would show up. Rahul was making the point that self-help groups are a key enabler, not super expensive, with all sorts of additional benefits that contribute to our health and education goals.
I also went to Bihar, the poorest state in India, but one that’s making lots of progress. Polio is still a significant problem there, and the campaign against it is very intense. As in Utter Pradesh, self-help groups play an important role in Bihar, particularly groups organized by PRADAN, a nonprofit group of professionals who provide development assistance to India’s remotest villages whom we support through the Bill & Melinda Gates Foundation.
Among other things, PRADAN helps farmers improve their agricultural practices so they can increase their crop yields and even find new sources of income, such as by developing arjuna tree plantations for rearing silkworms and weaving silk. It was amazing to see how self-help groups aided by PRADAN expertise had completely transformed the villages we visited, keeping kids in school, encouraging girls to marry later and to take control of their family size, all things that improve the well being of their families and the village as a whole.
While in Bihar, I also met with the Chief Minister of the state. Under his leadership, Bihar has made significant progress, improving health outcomes and increasing vaccination rates. It’s really encouraging to see progress being made in one of the poorest places in India. You realize if it can happen here, it can happen almost anywhere.
My last few days were spent in India’s capital, New Delhi. I met with innovators from some of the Indian companies that make inexpensive vaccines, which are helping make vaccination more affordable for kids around the world. I also met with government officials including Prime Minister Manmohan Singh and Health Minister Ghulam Azad, whose energy and commitment were also very impressive.
So it was an uplifting trip. India has a good chance of eliminating polio in the next few years, which would be a huge achievement. And the progress being made toward many development goals is truly inspiring.
Making Medicines Available
Eliminating killer diseases with new medicines
For people suffering from serious but treatable diseases like pneumonia and tuberculosis, access to drugs can mean the difference between life and death. A new report and two recent announcements are signs of progress in efforts to expand access.
In the developed world, we sometimes take life-saving medicines for granted. But as I’ve traveled in the developing world, I’ve seen first-hand the huge difference they can make. A new report and two recent announcements are reminders of the important role of the pharmaceutical industry, especially in helping save the lives of people in poor countries.
The new report is the Access to Medicine Index 2010 from the Access to Medicine Foundation, based in the Netherlands. The index ranks 20 of the world's largest pharmaceutical companies on their efforts to make sure that medicines are made for and reach people in developing countries. The latest index found that companies are being more transparent about their efforts to expand access. They’ve also taken steps to make drug pricing more equitable and to increase R&D on diseases affecting poor countries. But in the words of the Index’s founder Wim Leereveld, “the industry as a whole still has a long way to go.”
One example of progress on access is the announcement by GlaxoSmithKline and Pfizer Inc. that they will accelerate production and distribution of new vaccines against pneumococcal disease, which kills 1.6 million people a year—mostly in developing countries, and half of them children under the age of five.
Glaxo and Pfizer will supply 30 million doses a year, for 10 years, at a price that is more affordable for developing countries. Estimates are that the vaccines could save 900,000 lives by 2015, and up to 7 million lives by 2030. Key to this effort was an innovative financing mechanism, known as an Advance Market Commitment, piloted by the GAVI Alliance. I am pleased that our foundation was able to support this effort in partnership with GAVI, the World Bank, the World Health Organization, UNICEF and the national governments of Italy, Canada, Norway, Russia, and the United Kingdom.
In another important effort supported by the foundation, the non-profit Critical Path Institute (C-Path) and the Global Alliance for TB Drug Development (TB Alliance) will coordinate testing of promising combinations of tuberculosis drug candidates from at least 11 different pharmaceutical companies early in the development pipeline.
If you used the historical approach to testing and getting regulatory approval for new TB drugs—individually and then in combination with other drugs—it could take 24 years. This new approach, which the foundation created in partnership with C-Path and the TB Alliance, hopes to develop effective new combination TB treatments in just six years. Importantly, the U.S. Food and Drug Administration and regulatory authorities in Europe have indicated strong support for accelerating approvals of safe, effective new treatments.
Although many people think of TB as a disease that was conquered long ago, it still kills 1.8 million people a year, mainly in the poorest countries on earth. The current four-drug course of treatment for TB is now 50 years old and requires patients to take numerous pills for six months or longer, which many find difficult, especially given the often-unpleasant side effects. When patients don't complete their course of treatment, the disease can become resistant to the initial drugs. In 2007, there were more than 500,000 cases of drug-resistant TB. New and easier ways to treat TB would be a great step forward.
I believe that these kinds of innovative collaborations between pharmaceutical companies, governments and the non-profit sector are critical to accelerating the delivery of medicines, which is critical to saving lives.
A Gates Foundation Trip
Simple advances, amazing benefits in Africa
On this trip to Africa, I saw simple technologies having big impacts.
In December 2009, I went to Africa on a Gates Foundation trip. It’s really helpful to get a view on the ground of work we’re doing, and to meet the people who are making it happen.
For all the benefits that modern healthcare technology has to offer, it was amazing to see how simple advances in basic sanitation and personal hygiene are making such a difference for the poor in South Africa. And in Kenya, I saw first-hand how the innovative use of cellphones and modest investments in food handling are improving people’s lives.
My trip started in Durban, South Africa, where I met with Neal Macleod, head of Durban Water and Sanitation. Neal has been a leader in thinking through how to improve sanitation for the poor in Durban. Most of us take for granted the convenience and sanitation benefits of flush toilets. But in Durban, many people don’t have access to water. So reducing the incidence of diarrheal diseases and worm infections associated with the use of pit toilets is important – especially for young children who are the most vulnerable. Neal showed me the VIP toilet – which isn’t as fancy as its name suggests, but is a breakthrough in basic sanitation through the use of simple ventilation methods and other inexpensive construction methods, such as installing a fly screen on the ventilation pipe.
After that, I travelled 590 kilometers northwest of Durban to Bophelo Pele, a male circumcision center near Johannesburg that has had incredible success demonstrating how this simple procedure can reduce—by more than 60 percent—the transmission of AIDS from women to men. I met with Professor Bertran Auvert, a French scientist, whose research also proves to skeptics that teenage and adult men are willing to be circumcised. Since the project began, more than 14,000 men have been circumcised, in a procedure that takes a doctor just 7 minutes and costs less than $40. It’s a remarkable example of how modest and wise investments can save lives and significantly reduce the financial impact of AIDS, especially in countries where the infection rate is so high.
In Kenya, I visited Eldoret, where we saw how M-PESA, an innovative cell phone service offered by Safaricom, the local telecommunications provider, is making basic financial services available to poor people. This is a big goal of the foundation, so I was excited to see how popular M-PESA has become. Everywhere I went, I saw the M-PESA logo (“pesa” is Swahili for “money”). M-PESA is an affordable, fast and safe way for people to deposit, save and transfer money anywhere in Kenya. Safaricom is now getting banks and insurance companies involved and the service is spreading to other countries.
In the nearby town of Kabiyet, I saw how an even simpler and older technology—a chilling plant—is helping improve the lives of local dairy farmers. In the past, farmers had to sell their milk within two to three hours or it would go sour. With the new chilling plant at Kabiyet Dairies Company, Ltd. (which the foundation’s grantee, Heifer International, helped finance), the milk can be properly chilled and checked for quality. Now, farmers are getting almost double the price. I met one farmer who told me that he is now able to send his kids to school because of the extra income he earns. In addition, the Kabiyet facility has become a center for a lot of other services that local farmers need, including artificial insemination of cows, veterinary services, and supplements that help dairy cows produce more milk.
Africa is home to 15 percent of the world’s population and many of its poorest citizens. While the continent faces many challenges in reaching the targets of the Millennium Development Goals, the projects I visited show how progress in reaching these goals is possible and can be accelerated. That’s why Africa is a particular focus for the foundation.
Visiting Health Clinics
Delivering health care in India
In July, I traveled to India to see how new investments by the Indian government are improving medical care in poor communities. During the trip, I visited health clinics in the state of Uttar Pradesh and saw how vaccines and other basic health care is being delivered to mothers and children.
My visit to India is a part of my ongoing efforts to see first-hand the impact of issues that people in poor rural and urban communities are facing and to assess how innovative approaches to addressing these issues are working. Look for additional videos in the future as I travel to other regions where the Bill & Melinda Gates Foundation is supporting programs in global health and development.
How to Help
We need productivity and sustainability
Helping poor farmers improve productivity is a critical step in reducing global hunger. But there is an ideological divide over how best to help them. The truth is that both sides have something important to offer.
While the World Summit on Food Security in Rome in November did not achieve all it should, it shined a welcome spotlight on small farmers who make up the vast majority of hungry and poor people in the world. Coming on the heels of a commitment by the G20 to invest $22 billion in developing-country agriculture, the summit provided reason to be optimistic that after decades of neglect, we’ll start investing in the single best strategy to reduce global hunger and poverty.
At the same time, I am worried that as momentum builds behind agricultural development as a long-term alternative to food aid, a growing ideological divide may cause the world to squander a real opportunity to fight hunger and poverty.
The global movement to help small farmers is increasingly divided into two camps. On one side is a technological approach focused on improving productivity. On the other side is an environmental approach that promotes sustainability. Productivity or sustainability – they say you have to choose.
A recent Time Magazine article “Different Shades of Green in Africa,”for example, pits the idea of organic development to help African farmers against the heavy input approach being promoted by the Alliance for a Green Revolution in African (AGRA) and the Bill & Melinda Gates Foundation, calling it “a battle between two very different agricultural philosophies.”
As I said during my speech at the World Food Prize in October, this is a false choice that is dangerous for the field of agricultural development.
At a time of rising population and climate change, we need both organic solutions that promote sustainability and the technological approaches that increase productivity—and there is no reason we can’t have them both.
Many environmental advocates highlight the excesses of the original Green Revolution. They have a point. The Green Revolution increased yields dramatically in many poor countries in the second half of the 20th century, but it also led to over-irrigation and over-fertilization. The next Green Revolution has to be greener than the first.
Some have tried to restrict the spread of biotechnology regardless of its potential to increase productivity. They act as if there is no emergency, even though there are already 1 billion hungry people in the world, and climate change is going to make conditions harsher in the future. The Food and Agriculture Organization estimates that developing countries will have to boost their yields by half to meet the challenge of global hunger. We simply won’t be able to meet that goal without using all the scientific tools at our disposal.
Of course, new technologies must be proven safe for farmers, consumers, and the environment before they’re adopted. That’s why countries should have a strong regulatory infrastructure guided by experts with access to the latest science-based information.
I have seen proof that agricultural science can make people’s lives better. This summer, I attended a roundtable discussion in New Delhi with scientists who developed a new variety of rice called Swarna-sub1. The amazing thing about Swarna-sub1 is that it can survive underwater for more than two weeks, which means it could revolutionize life for millions of farmers in flood-prone areas of India. The researchers used a fascinating technique called marker assisted selection to introduce a single allele, a version of a gene, into an existing rice variety to make it flood tolerant.
I also met with representatives from local NGOs, seed companies, and the government of India to talk about their plans for delivering new seeds to farmers. The government’s goal is to have more than 5 million hectares planted with Swarna-sub1 in just five years.
The tendentious debate pitting productivity against sustainability doesn’t just threaten important scientific advances. It also obscures another crucial lesson from the first Green Revolution: that developing more productive seeds is just one element of an effective strategy. In addition to new seeds, farmers also need training, access to new markets, and organizations to represent their interests. Governments need better data so they can devise sound agricultural policies. By placing so much emphasis on just one link in a very long agricultural value chain, we distract ourselves from a goal we can all agree on: helping small farmers and their families.
Success requires progress on many fronts. African countries must lead the way by spending more on agriculture. Donor countries must do a better job of listening so they can understand what poor countries really need. They should explain more clearly how the money they’re pledging will be spent. I am optimistic that these obstacles can be cleared away and that the world can tap into the opportunity offered by agricultural development. That’s why the Bill & Melinda Gates Foundation has committed more than $1.4 billion to initiatives that support small farmers.
However, if the field doesn’t move past this counterproductive debate, hungry and poor people will suffer. We have a choice: We can let our disagreements get in the way of real progress, or we can agree to help more than a billion people live healthier, happier lives.


