




Mosquito Week
The deadliest animal in the world
Sharks are wimps, compared to this beast.

What would you say is the most dangerous animal on Earth? Sharks? Snakes? Humans?
Of course the answer depends on how you define dangerous. Personally I’ve had a thing about sharks since the first time I saw Jaws. But if you’re judging by how many people are killed by an animal every year, then the answer isn’t any of the above. It’s mosquitoes.
When it comes to killing humans, no other animal even comes close. Take a look:
What makes mosquitoes so dangerous? Despite their innocuous-sounding name—Spanish for “little fly”—they carry devastating diseases. The worst is malaria, which kills more than 600,000 people every year; another 200 million cases incapacitate people for days at a time. It threatens half of the world’s population and causes billions of dollars in lost productivity annually. Other mosquito-borne diseases include dengue fever, yellow fever, and encephalitis.
There are more than 2,500 species of mosquito, and mosquitoes are found in every region of the world except Antarctica. During the peak breeding seasons, they outnumber every other animal on Earth, except termites and ants. They were responsible for tens of thousands of deaths during the construction of the Panama Canal. And they affect population patterns on a grand scale: In many malarial zones, the disease drives people inland and away from the coast, where the climate is more welcoming to mosquitoes.
Considering their impact, you might expect mosquitoes to get more attention than they do. Sharks kill fewer than a dozen people every year and in the U.S. they get a week dedicated to them on TV every year. Mosquitoes kill 50,000 times as many people, but if there’s a TV channel that features Mosquito Week, I haven’t heard about it.
That’s why we’re having Mosquito Week on the Gates Notes.
Everything I’m posting this week is dedicated to this deadly creature. You can learn about my recent trip to Indonesia to see an ingenious way to combat dengue fever by inoculating not people, but mosquitoes. (Somehow this story involved me offering up my bare arm to a cage full of hungry mosquitoes so they could feed on my blood.) You can read a harrowing account of what it’s like to have malaria and hear from an inspiring Tanzanian scientist who’s fighting it. And I’ve shared a few thoughts from Melinda’s and my recent trip to Cambodia, where I saw some fascinating work that could point the way to eradicating malaria, which would be one of the greatest accomplishments in health ever.
I hope you’ll have a look around. I can’t promise that Anopheles gambiae will be quite as exciting as hammerheads and Great Whites. But maybe you’ll come away with a new appreciation for these flying masters of mayhem.


Hero in the field
Counting the dead to save the living
Andrew Moseray walks, rides, and even wades through Sierra Leone to find out why people die. What he learns helps save lives.
In Sierra Leone’s Bonthe District, there’s a village called Segbelleh. During the country’s dry season, when the river levels drop too low for boats, the only way to get there is wading ten miles in knee-high water. On the other side are two houses and about 15 people.
As a field supervisor and master trainer for Healthy Sierra Leone, or HEAL-SL, Andrew Moseray has made that journey. His job is to go door to door, in hundreds of randomly selected communities, and ask families a hard question: Has anyone in this household died? If the answer is yes, his questions keep going. When did the person first get sick? Did they have a fever, a cough, maybe a swollen belly? What medicines did the person get, and what happened next?
Some of those communities are a short drive from Bo, Sierra Leone’s second-largest city, where Andrew lives. Others take nine hours by boat, or a motorbike ride followed by miles walking through mud. Andrew calls himself the “health soldier” of Sierra Leone; after hearing what he does, I think the title fits.
Why counting deaths matters
You can’t fix a problem you don’t understand. But in Africa, most deaths are never recorded, and the ones that are rarely list a cause. Until recently, Sierra Leone was one of those places, so global estimates had to fill the gap with models and projections that were often inaccurate.
That’s why our foundation funded HEAL-SL from its launch in 2019. Its surveyors conduct what’s called a verbal autopsy: They sit with the person closest to someone who died and record their whole story, from their earliest symptoms to their final breaths. Using that information, two physicians then assign a cause of death.
HEAL-SL’s first nationwide round surveyed about 343,000 people across Sierra Leone and recorded more than 8,000 deaths. The data revealed that malaria was a leading cause of death in the country for young children.
In places without reliable death records, verbal autopsies are often the only practical way to learn why people are dying. They give researchers a good first picture—a hypothesis to test—and show them where to look more closely and investigate. Of course, verbal autopsies have limits. A parent can tell a surveyor that their child had a fever, but not necessarily which disease caused it. In addition to working to make verbal autopsies more accurate, our foundation supports more precise ways of finding out why people die. One example is the minimally invasive autopsies used by CHAMPS, a mortality surveillance network with a site in Sierra Leone. The two approaches work best together: Verbal autopsies can cover a whole country and help experts ask the right questions, and minimally invasive autopsies can help answer them.
“How will this data impact me?”
Early in Andrew’s career, a young man whose wife had just died during childbirth asked him a question he’s never forgotten: “I won’t eat today, and I don’t know if I’ll eat tomorrow. What will you do for me? How will this data impact me?”
He didn’t have a great answer then, he admits. He has a better one now. HEAL-SL’s findings, along with other research, helped show health officials how many of Sierra Leone’s children were dying of malaria. In 2024, with support from Gavi, the Vaccine Alliance, UNICEF, and WHO, the country began vaccinating young children against the disease. Now, when Andrew visits a community, he asks mothers to bring out their children’s clinic cards, points to the malaria vaccine, and tells them that HEAL-SL’s data helped demonstrate it was necessary. Their kids have an extra layer of protection, he explains, because of what other people were willing to share.
His reasons for doing this work are personal. In his teenage years, he wanted to be a doctor. But as he was finishing secondary school, Ebola hit Sierra Leone, and he watched as people reported sick neighbors and family members to the authorities. At first, it looked like a betrayal. But Andrew now understands that they were protecting not just themselves but their communities—which is the essence of public health, the field he decided to pursue instead.
Years later, while Andrew was doing verbal autopsies for CHAMPS, his two-year-old cousin died after spending two months in the hospital with no diagnosis. Only afterward did a minimally invasive autopsy reveal the cause: tuberculosis. Andrew shares that story with families who don’t want to talk. “Evidence-based data is quite important,” he says.
Teaching the next generation
Andrew joined HEAL-SL as a data collector and quickly stood out. He became a team lead, then a trainer, and he has since trained surveyors in Sierra Leone and other West African countries. His wife Isha says his true calling is teaching. Alieu Fatorma, one of the surveyors he trained, says, “He makes it simple.”
Andrew asks every new trainee two questions: Who are you, and what is your mandate? His answers: You are a surveyor. Your job is to listen and record, and you never judge or diagnose. Trust, he says, comes from small things. “We eat what they eat. We sleep where they sleep. If they took off their shoe, we take our own shoe off.”
The HEAL-SL team has a saying: “We count the deaths for the living to live.” I can’t think of a better description of Andrew’s work.
A daily fight
6 things you should know on World Polio Day
There’s good news and bad news about the eradication effort.
I’ve been following the fight against polio almost daily for more than two decades, ever since I got involved in the global coalition to eradicate it. But polio hardly ever makes headlines anymore, and most people are understandably not as focused on it as I am. So with World Polio Day coming up on Saturday, I want to give a quick update on how things are going.
Thanks to the world’s efforts—led by national governments with support from the Global Polio Eradication Initiative, which is a coalition of Rotary International, WHO, UNICEF, the United States CDC, the Gates Foundation, and the vaccine alliance known as Gavi—polio cases are down by 99 percent since 1988, and the virus is endemic in just two countries.
One of them, Pakistan, is making major progress. Thanks to continued vaccination programs and strong leadership from the government, the number of children newly paralyzed by polio there dropped from 74 in 2024 to 31 in 2025 and just 7 so far this year. I think it is possible to get to zero if we keep up this momentum.
In Afghanistan, unfortunately, polio cases have increased this year compared with last year. But the program is taking steps to do a better job getting the vaccine to all children, especially in the South region of the country. And it’s finding new ways to work with community leaders to hear from families who have doubts about vaccinations and to address their concerns.
Some encouraging news is coming out of Africa. Five variant polio outbreaks on the continent have been closed, interrupting transmission of the virus in those countries. It’s a testament to phenomenal work by governments at every level, local health workers, and the polio eradication initiative.
However, there continue to be outbreaks of variant polio in especially fragile settings. Humanitarian crises, weather-related disasters, and resource constraints are making it harder to vaccinate children. As global immunization rates remain low, the risk that the disease will spread internationally—even to places that have long been free of polio—is high.
India and South Asia have now been free of wild poliovirus for 15 years. This region, which is home to a quarter of the world’s population, recorded its last case of wild poliovirus in 2011. Staying polio-free since then is a huge accomplishment in itself. But countries in the region are also building on infrastructure and lessons from the polio program to expand people’s access to other public health services.
An affordable six-in-one vaccine is making it easier to protect children in low-income countries. In most low- and middle-income countries, children get their polio vaccines in two ways: orally, via a few drops in their mouth, and by injection. The injectable vaccines require two shots, the second one weeks or months after infants have received all their other routine shots. Many families don’t come back for this second visit, which means those children aren’t fully protected.
The six-in-one vaccine incorporates polio protection into the vaccines that children already get routinely, reducing the need for another injection later. When a baby gets the shots that protect them from whooping cough, tetanus, and so on, they’re also getting protection against polio.
Six-in-one vaccines aren’t new; they have been used in wealthier countries for years. The breakthrough was to develop one that’s affordable for low-income countries. Thanks to support from Gavi, Senegal and Mauritania are already using it, and Pakistan just approved its use last month.
I wish there were better news to share about funding. Even some of the most generous partners have cut back on their giving. GPEI, the eradication initiative I mentioned earlier, had to cut its budget by 30 percent this year. I am grateful to the donors who have stayed committed and to new donors who have made significant contributions in recent years. These include the Kingdom of Saudi Arabia, the United Arab Emirates, the European Investment Bank, Qatar, Australia, Canada, Monaco, and the United States.
This has accelerated a process that was already under way: lower-income countries taking more ownership of the program. For example, in the past 18 months, three more labs in Africa have been certified to do genomic sequencing of poliovirus samples. If the virus is detected somewhere on the continent, a sample can be sent to one of these labs, where scientists study its genome to figure out where it came from. The plan is to keep expanding capacity in Africa, further reducing the need to send samples overseas.
Unfortunately, none of this makes up completely for the funding shortfall. Around the world, leaders of polio programs are making painful tradeoffs. If this shortfall continues, we could lose decades of progress and see polio return everywhere. I’ll continue to do my part, supporting the work through the Gates Foundation and using my voice to raise awareness.
This is a winnable fight. It is giving us a blueprint for eradicating other diseases, including malaria. It has also created a global network of labs and experts that has alerted public health officials to outbreaks of cholera, measles, Ebola, and COVID-19 at the height of that pandemic.
But for me, what it comes down to is that we should eradicate polio because it is entirely preventable. There is no reason any child should ever be paralyzed by it again. That’s why I’m proud to be part of the global partnership that is committed to getting rid of it forever.
Body of evidence
Ramesh Ferris wants you to look at his legs
A powerful reminder of why polio eradication matters.
When Ramesh Ferris speaks in public, which he does a lot, he has an unusual way of getting to the stage. He crawls across the floor.
Ramesh was paralyzed by polio when he was six months old. Today, at age 46, he can walk with crutches and leg braces, but as an advocate for polio eradication, sometimes he chooses not to. He wants his audience to see what the disease does to the human body.
“I’m the voice of the polio survivors that I’ve met crawling in the streets of their communities,” he says. “Showing my legs is the most powerful tool I can use to educate people about the reality of what happens when kids don’t receive the polio vaccine.”
Ramesh contracted polio in 1980, when he was six months old. The first polio vaccine had been invented 25 years earlier, and millions of children had received it, but it still hadn’t reached low-income communities like the one in the state of Tamil Nadu, India, where he was born.
His birth mother had never heard of the disease, much less a vaccine for it. She just knew that her boy kept getting sick, and she couldn’t afford medical care for him, so she made what must have been an agonizing decision. She put him in the care of an orphanage in her community.
A year later, Ramesh was adopted by a Canadian couple who raised him and five other adopted children in the Yukon. Life was hard at times—kids at school mocked and bullied him—but he got expert medical care. Through three surgeries, doctors straightened his legs, and after intensive physical therapy, he learned to walk with crutches and braces.
When Ramesh was 22, he took a trip that changed his life. He went to India to meet his birth mother for the first time, so he could tell her how grateful he was that she had sacrificed so much so he could get the care he needed.
On the same trip, he had another powerful emotional moment. “I saw a fellow human being that had polio because he didn’t receive the polio vaccine as a child,” Ramesh says. “He was crawling around the streets as a beggar.” The person he was traveling with told him: “You’re looking at your life if you weren’t adopted.”
Since that time, Ramesh has been traveling around the world as a volunteer with Rotary International to spread the word about how much progress the world has made and the work that still remains. He’s raised awareness and funds with eye-catching campaigns including a 7,140 km trip across Canada… by hand bike.
We’re close to eradicating the disease—there were 52 cases of wild poliovirus in 2025, down from 350,000 in 1988—but finishing the job is a tough challenge that takes continued funding and effort.
People like Ramesh remind us not only how we can do it, but why we should.
The last mile
We’re closer than ever to eradicating polio
...And closer than ever to seeing a resurgence.
When most Americans think of polio, we probably picture President Franklin Delano Roosevelt. In 1921, at age 39, he was paralyzed by the virus and never regained the use of his legs. His story helped turn polio into a national cause. But in many ways, his experience was an anomaly.
After all, polio is overwhelmingly a childhood disease, with the vast majority of cases affecting those younger than five. That was true when FDR fell ill, and it’s true today. The typical patient isn’t an adult with an already established political career—it’s a little kid, often a little kid in a low-income country, who might never get the chance to take his first steps.
That injustice is one big reason I've spent the past two decades working to eradicate polio. The other reason is that eradication is actually possible, realistic, and well within reach. This is a disease we can get rid of—not just control, but eliminate everywhere. That is a rarity in global health.
The world has already made extraordinary progress. Back in 1988, when Rotary International and the World Health Assembly set the goal of eradication, the virus was paralyzing more than 350,000 children each year across 125 countries. Since then, cases have dropped by 99.9 percent. The strains known as Type 2 and Type 3 wild poliovirus have been eradicated. The entire African continent is certified wild-polio free. Only two countries—Afghanistan and Pakistan—still have persistent transmission of Type 1 wild poliovirus.
Now we're closer than ever to total polio eradication. But the last mile is proving the hardest because viruses find ways to exploit any immunity gaps or weaknesses. Wherever vaccination rates slip—even briefly—they can resurface.
One of the biggest challenges comes from what are called variant outbreaks. In communities where immunization is low, the weakened virus used in the oral polio vaccine can circulate asymptomatically and rarely, over time, mutate enough to regain the ability to cause paralysis in unvaccinated children.
While most variant outbreaks happen in places with extremely low vaccination coverage, poor sanitation, and weaker health systems, no place is risk-free until the world is polio-free. In 2022, the United States confirmed its first paralytic polio case in nearly a decade, and the virus was detected in New York wastewater samples. In the time since, variant polioviruses have also been found in the U.K., Ukraine, Indonesia, and other countries.
The good news is that today’s tools are better than anything we had even five years ago, and they make every dollar spent on the cause go further than ever before. We have a new oral vaccine, nOPV2, that’s far less likely to mutate and lead to new variant outbreaks; nearly two billion doses have already been given worldwide. New regional labs in Ghana, Nigeria, South Africa, and Uganda that test wastewater samples and sequence viruses have cut detection times by over 30 percent, which gives health workers a critical head start on outbreak response. And the surveillance network for polio is one of the most sophisticated ever built—also helping alert public health officials to outbreaks of cholera, measles, Ebola, and even COVID-19 at the height of that pandemic.
The Gates Foundation has been proud to support these advances as part of the Global Polio Eradication Initiative, a coalition of the WHO, UNICEF, the CDC, Gavi, Rotary International, and dozens of countries’ governments. It’s one of the most successful collaborations in the history of global health.
But right now, GPEI is facing a $1.7 billion funding gap, with various long-term donor governments cutting back their support. Without the right resources, vaccination campaigns may have to be scaled back, surveillance sites will likely close, and the virus could spread globally.
In the century since FDR was paralyzed by the virus, American leadership and generosity have helped turn polio into a fight the whole world could win. From the March of Dimes, which funded research, to the development of the first vaccines, to support for eradication campaigns, U.S. commitment has been decisive.
The world is at the brink of ending this terrible disease, and the stakes of this moment couldn’t be higher. If we finish the job, we free up billions of dollars for other health priorities and—most importantly—protect generations of children from a virus that has paralyzed millions. If we back down from the fight, up to 200,000 children could be paralyzed each year within a decade.
We have the scientific tools and infrastructure needed to cross the finish line. And we have hundreds of thousands of committed vaccinators who are determined to get us there—who go door to door across deserts, jungles, floodplains, and war zones to make sure no child is missed. I've met them, I've heard their stories, and I've seen how determined they are to finish the job.
We should be too.

Eyes on eradication
Optimism and resolve on Pakistan’s last mile to end polio
I made my first trip ever to Pakistan to learn about the country’s incredible efforts to wipe out polio.
Earlier this year, I made my first trip ever to Pakistan to learn more about the country’s incredible efforts to wipe out polio.
At the time of my visit in February, Pakistan had gone more than a year without a single child being paralyzed by the crippling disease. This was a huge achievement made possible by the skill and dedication of the polio program’s leadership and its more than 300,000 polio workers. Their energy and enthusiasm reminded me of what I saw in India and Nigeria when those countries were traveling the final mile to eliminate polio within their borders.
But the last mile is often the toughest. The gains made against this highly contagious disease are often fragile.
In recent weeks, the world received a sobering reminder of this fact when three new cases of wild poliovirus were detected in Pakistan: 12 and 15-month-old boys, and a two-year-old girl all living in the same district in Khyber Pukhtunkhwa Province, Pakistan, near the border with Afghanistan. (Pakistan and Afghanistan are the only two countries where the wild poliovirus has not been eliminated.)
It is heartbreaking to see these three children paralyzed by a preventable virus that has been eliminated in nearly every part of the world. (The government of Pakistan is providing rehabilitation services and other support to help the children and their families.)
At the same time, the emergence of these new cases was not entirely unexpected given the challenges of wiping out the virus in one of the most challenging places on Earth. The border region between Pakistan and Afghanistan, where the cases were detected, struggles with insecurity and misinformation that can sometimes prevent vaccinators from reaching every child who needs the polio vaccine.
When I learned about the new cases, I was disappointed. But I was also heartened by the response of Pakistan’s polio program. Despite having every reason to be frustrated, Dr. Shahzad Baig, who runs Pakistan’s National Emergency Operations Center for polio, said his team was not deterred. “This strengthens our resolve to reach every child with the polio vaccine,” he said.
After what I saw during my visit to Pakistan, I shouldn’t have been surprised by the team’s unfailing confidence. The polio workers are driven and detail oriented. They understand that running effective polio vaccination drives is not about getting one thing right. It’s about getting everything right that’s necessary to ensure all children get vaccinated.
In Pakistan, that has meant training 300,000 frontline workers who walk from house to house to vaccinate over 43 million children under the age of five; creating detailed maps for those teams to use to ensure no child is missed; running public information campaigns to inform communities about the risks of polio and the benefits of vaccination; organizing security to protect vaccinators; and building strong supply chains so vaccines are available across the country.
In between vaccination drives, Pakistan’s polio surveillance workers are constantly hunting for signs of acute flaccid paralysis in children and testing the environment for the presence of the virus. Pakistan currently has the largest environmental surveillance network in the world. From tiny villages to larger cities and urban areas, Pakistan’s system has the capacity to find the poliovirus wherever it exists.
The nerve center for all this work is the National Polio Emergency Operations Center, which was a highlight of my visit. A wall of screens in a control room displayed real-time information about vaccinations, security, and supplies, as well as detailed maps following the movements of polio workers. This data helps the team see where they need to make improvements to the vaccination programs to ensure they reach all the children. You probably know I have an insatiable appetite for data, especially health data. So, it should be no surprise I lingered here for longer than planned to look at all the information and learn from the polio experts who are as passionate about data as I am.
What was also remarkable to see is how Pakistan has continued to build community support for its polio activities by integrating them with other essential health programs, like routine immunization programs. During the pandemic, polio workers used their deep knowledge of local communities to reach out to families to raise awareness of COVID-19, teach them how to protect themselves with handwashing and mask wearing, and encourage people to get vaccinated.
Polio workers constantly battle rumors and misinformation about the polio vaccines. But by engaging openly with the public’s questions they’re making headway against this challenge.
I got a glimpse of part of this effort at a national immunization call center where doctors and other health workers respond to tens of thousands of queries every month from the public about immunization, including polio. If families hear a rumor about the polio vaccine, they can call for free and ask about it. Pakistan has reduced the number of vaccine refusals and I believe that the work of this call center is one of the key reasons why. The call center was set up to support polio inquiries, but due to the success of the program, the call center expanded its services to answer questions about COVID-19 vaccines and all other vaccines.
Pakistan’s polio effort also benefits from the strong support it receives from the very top of its government. I recently had an opportunity to speak with Pakistan’s new Prime Minister, Shehbaz Sharif, and it was clear that his administration is actively engaged in stopping transmission for good.
Even with the three new polio cases in Pakistan, the virus is still circulating at very low levels and the world has an historic opportunity to make sure this virus never paralyzes a child again. The fact is, we’ve never been closer to ending polio and it’s critical that the world doesn’t lose sight of this goal.
The last mile to end polio, of course, will be challenging. And that’s why it’s important that the world keep up its support for the polio programs in Pakistan and Afghanistan, so they don’t travel it alone.
I look forward to keeping you posted on their progress in the months ahead.

Polio progress
Going door to door, this hero brings the world closer to ending polio
19 million people who would have otherwise been paralyzed are now walking today thanks to heroes like Shumaila Rehmani.
The world is so close to ending polio.
Since the start of the global eradication effort in 1988, the number of polio cases worldwide has fallen 99.9 percent.
19 million people who would have otherwise been paralyzed are now walking today because of vaccines. And 1.5 million people are alive who would have otherwise died from the disease.
Much of the credit for this progress goes to the thousands of polio workers who have gone door to door vaccinating more than 3 billion children over the last 33 years.
October 24 is World Polio Day and to mark the occasion I’d like to share the story of one of these dedicated polio fighters.
Her name is Shumaila Rehmani.
Shumaila is a polio vaccinator in Pakistan, which is one of the two countries in the world—the other is Afghanistan—where the wild poliovirus is still endemic.
Shumaila’s job is to deliver the polio vaccine to every child under age five in the community she serves. While that probably sounds like a straightforward job, what it takes to get it done is not. Reaching every child requires hard work, meticulous planning, and patience.
During polio immunization drives in Pakistan, Shumaila sets out on foot early in the morning with a cooler filled with vaccines and a detailed plan for all the homes she needs to visit. Then she begins knocking on doors to give the oral polio vaccine drops to every child.
The overwhelming majority of families she visits want their children to be vaccinated. Some parents, however, out of fear or a lack of information, refuse to have their children vaccinated.
But Shumaila doesn’t give up.
She talks with the mothers and fathers, answering all their questions about polio and reassuring them that the vaccine is safe and effective. She also works with community and religious leaders to speak with families about the importance of vaccination.
Progress can be slow. In the community she serves, Shumaila says this year she initially had more than 250 families refuse vaccinations. But today, because of her efforts to work closely with the families, all but four of them have had their children vaccinated. And she continues to talk with those families to encourage them to get vaccinated.
And thanks to the thousands of dedicated health workers like Shumaila and the leadership of Prime Minister of Pakistan Imran Khan, there’s been just one case of wild polio in Pakistan so far this year, compared with 84 in 2020.
While the incredible efforts of Shumaila and other polio fighters have brought us to the brink of a polio-free world, COVID-19 has created new challenges. The pandemic has disrupted polio campaigns and routine immunizations in many parts of the world, causing outbreaks of other forms of polio to crop up in Africa and Asia.
That’s why the global polio program adapted its approach to help contain the spread of COVID-19 while also working to end polio. The Global Polio Eradication Initiative used its workforce and laboratory and disease surveillance network to respond to the pandemic, investigating suspected COVID cases, coordinating response operations, and training health care workers. In Pakistan, the national polio team now operates a toll-free number for anyone who wants to speak with a doctor about COVID, polio, or get any questions answered about routine immunization. They have received more than 17 million calls during the pandemic.
Like other polio workers, Shumaila has used her community relationships to raise awareness of COVID, teach families how to stay safe, and provide handwashing and hygiene lessons. This has made for longer days, but Shumaila says it’s easy to stay motivated. As a mother of three children herself, she is driven by her dream of a day when polio will no longer be a threat to her children or any child in Pakistan.
It’s a day she knows will come soon, she says. Again and again since the start of the global polio eradication effort, one country after the next has eliminated this crippling disease from within their borders. Less than a decade ago, for example, Nigeria accounted for more than half of all wild polio cases worldwide. But last year, Nigeria, along with the 47 countries in the African region, were certified free of the wild poliovirus.
With Afghanistan recently announcing it would conduct a nationwide polio campaign in November—the first in over three years to reach all children in the country—and Pakistan’s continued commitment to eradication, the final two polio endemic countries will hopefully soon follow others on the path to ending wild polio.
“If other countries can be polio free, why can’t Pakistan be?” Shumaila asks.
An epochal shift
The turbulent AI era is here. The choices we make now are critical.
We need a plan to ensure that the good outweighs the bad.
During my entire life I’ve only had two jobs. In the first one, I played a role in developing software to empower people through my work at Microsoft.
In my second one, which I started full time in 2008, I am giving back the wealth I made at Microsoft with the goal of making the world a healthier, better educated, and more equitable place. This is the job I will have for the rest of my life.
Both of these experiences inform my perspective on artificial intelligence. When I first learned about computers at age 13 I was fascinated by the idea of making them more intelligent and able to perform things that, at the time, only humans could do. Although the term “AI” was used from around the time I was born, the technology has only made significant progress in the last decade. It is now incredibly capable and it is continuing to improve at a mind-blowing rate. AI for the first time can replace and even exceed human cognition.
In terms of equity, AI will either be the greatest equalizer ever invented, or the worst source of injustice. The challenge is monumental. Even under the best circumstances, the transition to this new AI era will be one of the most turbulent times in human history. How will we use this technology to make the world a fairer place and keep it from widening the divide between rich and poor? How will we protect the people who are most vulnerable to the harms caused by artificial intelligence, including those who lose their livelihoods and the sense that they are in control of their future?
I believe that answering these questions and acting on the answers should be the world’s top priority. If the world takes the right steps AI will be a force for good and leave everyone better off.
Unfortunately, right now we are not preparing for it. I don’t see evidence that leaders, experts, and communities are confronting the challenges adequately. There is no plan to ease the entry into the AI era.
Part of the reason for this is that many commentators underestimate the extent of the impact AI will have. I think there are a few reasons why.
One is the fact that AI models still make mistakes. It is hard to envision any of them replacing human cognition when, not long ago, they couldn’t solve a simple Sudoku puzzle or figure out how many R’s are in the word strawberry.
But the reliability problem is being fixed quickly, as researchers create models that can check their own work and improve themselves. Soon they will be substantially better than humans at many tasks.
Another reason people underestimate AI is that analogies to the effects of past innovations are misleading. We have no experience with a technology that can be adopted quickly or that can think and move like a human. When the PC came along, it took twenty years to significantly change how we worked because the software had to be developed, the price had to come down, and people had to learn how to use the tools and incorporate them into their business processes. AI, on the other hand, runs on the devices we already have, and it uses natural language. We don’t have to adapt to it because it can adapt to us. It can watch the same training video that is used to train human workers and learn from existing data.
I want to acknowledge a potential bias. I have benefited enormously from the technology industry. Although I have diversified my portfolio quite a bit, I still have financial ties to it. I am working with Microsoft and other AI companies in my role as chairman of the Gates Foundation to try and ensure AI is deployed in ways that will truly benefit people around the world.
However, my views on AI are not motivated by the potential to make money for myself. Any profits generated by my investments, including those related to technology, will go to the Gates Foundation to tackle global inequity. Of course, readers will have to decide for themselves whether this clouds my view.
This time really is different.
For as long as I can remember, I’ve wished innovation could happen faster. With AI, my feelings are more complicated.
I wish the world could get the benefits rapidly and delay the problems it will cause as long as possible, but the benefits and problems are arriving at the same time. I believe we need time to prepare for the period of social, political, and economic upheaval we are about to enter. The people who need the most time are the ones who have the least—the accounting worker who’s replaced by a bot or the $20-an-hour worker who loses their job to a $10-an-hour robot.
Many observers say that this technology transition will be like previous ones. They give the example of how jobs in the United States shifted from agriculture to office work. However, that proceeded over several generations and created new jobs where human cognition was required. In this case, the technology can substitute for human cognition.
Because it can see, listen, speak, and reason and will eventually do physical work just as smoothly as any human, it will not just affect one sector. AI will take on work in law, customer service, medicine, software, and manufacturing. It will hit these industries rapidly, over the course of a decade rather than a few generations. There will be some new jobs, but without the right policies there will be far fewer than exist today.
If someone had a credible plan for slowing down AI advances globally, I would likely support it. However, I don’t think that’s going to happen. The geopolitical and economic incentives are pushing too hard to go full speed ahead.
To make sure we maximize the positive effects of this unprecedented technology and minimize the bad so we are better off overall, we need to understand both the benefits and the risks. I’ll start with the risks.
The transition to AI comes with three big risks.
I plan to write about each of these in more detail in the future, so I’ll touch briefly on them for now.
Many jobs will disappear forever.
In 1933, during the Great Depression, unemployment in the United States was roughly 25 percent. It remained in double digits for much of the following decade. It ultimately recovered as demand, investment, and growth returned.
AI may not reach this level, but its impact will not go away with an economic cycle. The jobs at most risk are entry- and mid-level, and the new jobs being created will mostly require skills that take many years to learn.
White-collar jobs are already being hit modestly. After the widespread adoption of generative AI, employment fell significantly among young workers in jobs that are especially vulnerable to replacement, but not among their older colleagues.
I think this trend will continue, but it will not be confined to a handful of industries or occupations. Jobs in sales and customer support (online and over the phone), software engineering, and paralegal work may be among the first affected, but the disruption will reach much further as AI takes on tasks that today still require trained workers: things like assessing loan applications, doing data analysis, and even triaging patients. A few areas like software engineering will generate new demand as the costs go down, so the net job loss in those areas will be less than in others as long as some tasks, such as design, are better done by humans.
Blue-collar jobs will be affected as well. Although robots are not as far along as AI, eventually their cost will be dramatically lower too. Many Americans I talk to don’t realize how fast dexterous robots are advancing because much of the advanced work is being done in other countries, primarily China. Or they may be confused by those videos of robots dancing badly that have been going viral lately. I think “smart” robots will begin to compete with people on some physical tasks—in the construction and hospitality industries, for example—by the end of the decade.
Robots and AI combined can create a vicious cycle. After one company adopts them and uses the savings to lower its prices, its competitors will feel immense pressure to do the same. If existing companies don’t adopt them, then start-ups will. Many people will shift to other jobs, but the turmoil of losing work, getting retrained, and finding other work will be significant. Market forces will make adoption go faster and faster and, unless we intervene, there will be fewer good jobs available and the benefits will accrue to a small group.
I’m especially worried about young people, who will enter a workforce with fewer entry-level openings. They understand the challenge because they are the most active users of AI and see both the capabilities and the rate of improvement. It’s no wonder that so many of them feel negatively about AI.
The biggest shift for workers will happen when AI provides nearly error-free work. At that point, it will be able to function on its own without a human checking in on it, and companies will have every economic incentive to let it.
This will lead to a fundamental change in how we think about work, income, and economic security. How will an economy that’s been built around employment operate if fewer people are working, or if many people are working fewer hours?
In a capitalist society, employment is the way most people get the money they need to pay for the basics of life as well as being a key source of dignity and social connection.
When a community has high unemployment, the ripple effects can be pervasive. Research suggests that in some parts of the United States, factory closures contribute to a rise in deaths from opioid overdoses. Now imagine similar pressures on both white-collar and blue-collar workers nationwide.
We have to think now about how to reduce job losses so that everyone can share in the prosperity that AI creates. Waiting until people are already displaced or underemployed will be too late. AI is a structural challenge to the way our economy is organized, and it requires thinking and action now.
AI will empower people (and perhaps AIs) to do more harm.
Long before AI entered the mainstream, there was information online about how to create weapons like bombs, bioweapons, even computer viruses. AI will make it much easier to not only get this information but act on it. Even criminals with very limited skills will be able to target victims at every scale: individuals, companies, and governments.
AI-enabled fraud, disinformation, deepfakes, and surveillance are the harms that many people will feel most keenly in their everyday lives.
AI capabilities are starting to be used for cyberattacks. The smartest cybersecurity experts I know are scared about the next few years, because the attackers are getting powerful new capabilities faster than the defenders can fix all the weaknesses. After all, the same AI model that can find a flaw in software so a company can fix it can also help a criminal exploit it. The resources needed to make an attack are going down significantly and we haven’t been able to separate those abilities from benign usage.
Think about the infrastructure that will be vulnerable: hospitals, financial institutions, water systems, power grids, systems for managing government benefits. When these institutions are attacked, it’s the patients, customers, and benefits recipients who stand to lose.
The same goes for bioterrorism. Although AI will lead to lifesaving advances in drugs and vaccines, it will also make it easier to design a deadly new disease. Again, the positive capabilities are hard to separate from the dangerous ones. This is a global problem.
The risks I’ve just mentioned are all about how AI will empower bad actors who have relatively little power now. The same tools will also concentrate power in places where it already exists. Autonomous weapons, for example, will make governments even more capable of using deadly force without a human being part of the decision. Monitoring and manipulating public opinion will be easier and cheaper, and more effective too.
Eventually, the power to use AI to harm people will not be limited to people or institutions. AI systems themselves already occasionally act in ways their designers didn’t intend. The technology is improving faster than anyone expected and in surprising ways, and as the models become more powerful, they could begin to act against our interests and we could lose control. I’ll have more to say about this in the future.
AI could stunt our kids’ development and replace human relationships.
When I was growing up in Seattle, I didn’t have that many friends aside from a few other boys who were like me. It took hard work and a lot of help from my mom to develop my social skills so I could relate to different kinds of people. I still draw on those lessons today at the age of 70.
I doubt I would have put in the same work if I had had an AI companion back then. They talk to you in ways you’re already comfortable with. They don’t push you outside your comfort zone. They are always available and never get mad at you. This gives them the potential to become highly addictive and to rob us of the lessons we learn from connecting with other people.
The body of evidence on this subject is still small and a bit mixed, but there are signs that we should be very concerned. For example, in one study of more than 1,100 people who use AI companions, researchers at Stanford and Carnegie Mellon found that those with smaller social networks were the most likely to turn to a chatbot for companionship. And the heavier and more emotionally personal that use became, the worse they felt.
Young people could be affected for their entire lives. In his book The Anxious Generation, Jonathan Haidt makes an observation about the effect of social media that is even more true for AI: “Like young trees exposed to wind, children who are routinely exposed to small risks grow up to become adults who can handle much larger risks without panicking. Conversely, children who are raised in a protected greenhouse sometimes become incapacitated by anxiety before they reach maturity.”
An AI companion designed to never upset you is a big, protected greenhouse.
We are only beginning to understand the dangers that the internet—especially social media—can pose to young people’s development. We’re seeing compulsive use, disrupted sleep, cyberbullying, and exposure to harmful content. AI could magnify many of these risks by making them more persuasive and difficult to escape, and we should not wait another generation to start taking them seriously. Countries including Australia, the United Kingdom, and Norway are adopting protections for children online. China has gone the furthest. Its rules restrict AI companion apps broadly, bar designs that foster emotional dependence, and ban virtual relatives and romantic partners for minors.
I’m also worried about AI’s impact on education. Ironically, the same tool that will allow people to learn more than ever could also lead to many people learning less. One preliminary survey suggested that heavier AI use was associated with less critical thinking. The effect was stronger for younger people.
This would be the worst possible time for humans to lose their critical thinking skills. In an era of deepfakes and misinformation that can be tailored to you individually, the ability to tell what is true from what is not becomes an essential life skill.
It’s unclear where to draw the line on these psychosocial problems. In some cases, AI may help people understand how to do better in their human relationships. It may be the only contact with the outside world for isolated elderly people and people with limited mobility, and it will be better than nothing. Wherever we end up drawing the line, it should be our decision, made intentionally.
The good things we do with AI could be very, very good.
It’s often said that we overestimate how much will change in the short term and underestimate how much will change in the long term.
With AI, I see something different going on. Some people see only the upside of AI and do not focus enough on the negatives. Others make the opposite mistake, which is to focus exclusively on the dangers—which are real—at the cost of missing the potential benefits.
We need both: deep concern about the AI harms we need to minimize, and grounded optimism about the positives if we maximize them for everyone.
Maximizing the benefits is just as important as minimizing the harms. If people see how AI makes their lives easier, it will help build the public trust that is necessary for managing the harder parts of the transition. If the first thing AI does in most people’s lives is take away their job, those who are already skeptical about it will outright reject it. This will make it harder to ever deliver on the benefits and it is another reason why governments, industries including the medical industry, and AI companies should be working together now.
With its ability to synthesize knowledge from every scientific field, AI can accelerate innovation in the world’s toughest technical challenges: providing reliable clean energy for everyone, combating climate change, growing enough food, eradicating diseases, and more. Researchers working on cancer treatments or nuclear energy can use AI to search through massive amounts of scientific literature. It can help them identify patterns that a human might miss and decide which experiments offer the most promise. When intelligence is no longer the limiting factor that it is today, smaller companies will be able to compete with organizations that have far larger research budgets. R&D and innovation will be supercharged.
Healthcare is one area where AI can help solve real-world problems. Many small American hospitals lack on-site specialists who can quickly diagnose a patient during a life-threatening emergency. In those places, AI could make sure a heart attack is caught in time and a family avoids the crushing expense of a medical emergency. Viz.ai is one example. It analyzes scans to detect strokes and other emergencies and helps medical teams coordinate their patients’ care. It is being used in nearly 2,000 U.S. hospitals.
AI will also help primary-care doctors make better diagnoses and keep in touch with their patients when they’re not in the clinic. It will help patients understand test results and complicated schedules for taking their medicine.
I surprise a lot of people when I tell them that a second area—agriculture—is where I see the fastest impact of AI in low-income countries. In most low-income countries, farmers don’t get reliable weather forecasts or advice on what seeds to plant, how to protect their crops and livestock from disease, or how to improve their soil. With population growth in these countries and the challenges of climate change, these farmers need more help than ever. Using AI, low-income farmers will soon be able to get better advice about all these things than even the richest farmers get today and increase their output substantially.
Government services are a third area where AI can make people’s lives easier. In the United States, I’ve met families who, understandably, were overwhelmed by the process of applying for health insurance, student aid, or food assistance. Faced with a huge stack of complicated bureaucratic forms, many felt like giving up. AI can streamline things dramatically so they get the help they need faster and the government can operate more efficiently. Governments can make the citizen’s experience far better, starting with those who need its safety net services the most.
Despite my concerns about its impact on our mental health, I think AI can also help a lot there. Most communities have too few counselors, psychiatrists, and addiction specialists. With the right privacy safeguards in place, AI tools could help people recognize warning signs. Then, if needed, they can offer evidence-based coping strategies and team up with a human to provide more responsive treatment.
AI can be a boon for education as well, despite the concerns I mentioned earlier. It can free teachers up to spend more time working with students one on one or in small groups and give them a clearer view of where the whole class is struggling. For students, an AI tool that preserves what researchers call “productive struggle”—the cognitive work that builds understanding—can strengthen learning. When a student first encounters a new idea, the AI gives substantive explanations and offers both questions and answers. Later, when it’s checking their comprehension, it holds the answer back and helps them arrive at it on their own.
Taken together, the advances in all these areas could make everyday life easier, more affordable, and less constrained by a person’s income or connections.
AI could give individuals and small businesses access to capabilities that today require expensive professional help or large staffs, while making products and services better and cheaper. It could help people with disabilities live more independently and enable workers and entrepreneurs with good ideas to accomplish far more than they can today.
Most importantly, it could give people back some of the time and attention now consumed by paperwork, bureaucracy, searching for reliable information, and tasks they cannot afford to pay someone else to handle. These benefits may seem modest, but multiplied across millions of lives, they would be profound: more people getting good advice when they need it and having greater freedom to focus on the lives they want to build.
In all these areas, the operative word is “can”—AI can improve life for people at every income level. But it won’t do that automatically. As with any new technology, we have to be deliberate about ensuring that it benefits everyone and not just a wealthy few. This will require governments and philanthropy to play a strong role so that less wealthy citizens and low-income countries are full beneficiaries.
The Gates Foundation has 19 years left of the 20 years in which it will spend its remaining $200 billion. AI will help it achieve its ambitious goals by both accelerating the discovery of vaccines and medicines for HIV, TB, malaria, and malnutrition and helping the healthcare workforce and patients know how to use those tools. The foundation’s goals include cutting the number of children who die every year in half again, as was done from 2000 to 2024. All of our work, not just health but also agriculture and education, will take full advantage of AI.
I will write much more about these efforts next month in the foundation’s annual Goalkeepers report—including our focus on making sure that AI models are available in the languages spoken by people in all the countries where we support work, and not just the ones that are common in rich and middle-income countries. Many of the leading AI companies, including OpenAI, Anthropic, Google, and Microsoft, are partnering with the foundation on all of these initiatives, which is making a big difference.
The world needs a plan.
It is great that some AI companies are proposing solutions to challenges raised by their own technology, but we should not expect them to lead the charge. Some of the issues are outside their area of expertise, and in a democratic society it’s not their role to decide these things.
Instead, solutions should be developed through a public democratic process that includes elected officials, policymakers, educators, health workers, local officials, and community leaders. Millions of people will have their lives disrupted, and we’ll need a stronger, more flexible social safety net to help them manage the transition. Local communities are already raising concerns about the energy and water needed for data centers. Without solutions, some groups will push for stopping AI development and deployment altogether.
The solutions should be shaped by our answers to the profound questions raised by AI, including how we preserve our humanity in a time when machines can out-think us. As people who spend their lives thinking about what it means to be human, religious leaders can play a key role in this. I was fascinated by Pope Leo XIV’s encyclical on AI, “On Safeguarding the Human Person in the Time of Artificial Intelligence.” It lays a strong foundation for the work that needs to be done.
In the coming months, I will share more ideas for making sure that AI’s benefits outweigh the harm it causes. Here are three to start, beginning with what I think is the most important one.
Build a new system for managing the transition.
The highest priority is a monumental task: creating a domestic and international framework for dealing with AI.
None of our current institutions were designed to handle a technology that spreads so fast and touches so many parts of our lives. So we’ll need to make new ones.
It’s hard to overstate what an enormous undertaking this will be. After the attacks of 9/11, the U.S. government went through its biggest reorganization since World War II for the purpose of improving just one function, national security.
AI will require much, much more. It will affect national security as well as employment, education, taxation, energy, elections, air and water, public health, the financial system, law enforcement, transportation, public lands, and IT systems.
These sectors overlap in ways our existing bureaucracy is not designed to manage. A labor department may understand workforce disruption but not security risk. A business regulator may understand market concentration but not AI’s effects on children and teenagers. Left to themselves, institutions will see only one part of the system, while the consequences of AI will ripple across the entire system.
At the national level, countries will need bodies that can set priorities across government agencies. The goal will be to make sure that every risk is accounted for. Otherwise, an AI-enabled attack might succeed because no one thought it was their job to stop it.
But even a country that gets its own house in order will still be exposed to risks that cross borders. This is why an international organization will need to be built in parallel.
It will be unlike any other institution we have ever created, though it can follow the model of some existing systems. There’s an inspections regime for nuclear weapons, regulations for international aviation, and agreements that protect the ozone layer. A new global organization for AI will need elements of all three and more.
It is fair to wonder whether the world’s institutions are up to the task of designing and implementing this new architecture. Government moves slowly when it moves at all, and polarization within and between countries makes it harder than ever to get things done. Some cooperation between the U.S. and China will be required.
We do not have the luxury of moving slowly. The place to start is with a process for building the right institutions before the disruption forces governments into crisis mode. National leaders should convene economists, technologists, labor experts, business leaders, and workers themselves regularly to identify where existing institutions are failing and what new authorities may be needed. Countries will need to learn from each other.
And the countries that host the leading AI developers and control critical parts of the supply chain should begin meeting now to set up shared norms, before competitive pressure makes it harder for them to cooperate.
Building the framework I’m talking about will take years, which is why we need to start now.
Set aside some jobs for humans.
My dad died of Alzheimer’s in 2020. In the later stages of his illness, he was cared for day and night by paid caregivers who understood him even when he struggled to express himself. He couldn’t always tell them when he was hungry, but they always knew.
My family and I will always be grateful to that amazing group of professionals. Something in the care they gave my dad was irreplaceably human. No robot could or should have done it.
I think about that team when the question of which jobs will disappear and which will remain comes up. I believe that as AI and robots improve, we’ll set aside certain things for only people to do. I’ve started calling this domain Human Reserved, and it’s an example of the kinds of ideas we’ll need to consider.
I like the phrase Human Reserved because it makes me think of nature reserves—places where we could put buildings and roads, but we choose not to because the loss would be too great.
We might set something aside as Human Reserved for economic reasons. For example, we may do it because allowing machines to take over a certain role will displace a large number of people who can’t easily change jobs. You can’t tell a 55-year-old who has worked in construction their whole career that they need to go work at an elder care facility and expect them to find it fulfilling.
Sometimes the decision to make something Human Reserved will be driven by other factors. In health, for example, imagine a robot giving you the awful news that you have an incurable disease. There’s no technical reason why it couldn’t. Yet it shouldn’t.
The Human Reserved domain will evolve over time—for example, we should consider setting aside some jobs now and phasing in AI slowly over years or decades with a commitment to preserve some jobs. Some areas, like education and mental health care, will be a mix, with a human in charge who’s using the technology to extend what they can do.
The lines will also vary from place to place. Some countries might insist on having humans take care of the elderly. But a country like Japan, which has a shrinking workforce and not enough young people to care for the old, may welcome a caregiving robot.
The idea of Human Reserved raises a host of questions I don’t have answers to. Who gets to decide what we reserve for humans? What criteria should we use? How do you keep companies from cheating and using robots anyway? What happens to international trade when one country lets robots make something and another country doesn’t? These will need to be worked out in public as part of the transition plan.
Rebalance how we tax labor and capital.
As workers are pushed into different jobs, they will need retraining and other support from the social safety net. But they will be working less, which means they will be paying less in income taxes, and government revenues will drop just when the demand for those services is greatest. The funds will have to come from somewhere at a time when budgets are stretched.
I believe we should tax AI tokens and robots. Right now, if you’re an employer and you hire someone, you pay payroll taxes on their earnings. But if you buy a robot, you can usually write it off right away as a business expense. The tax system nudges you toward replacing people with machines.
A tax would slow the rush away from human labor a little and raise money for retraining and a stronger safety net. It would need to be targeted so it does not slow down the purely beneficial uses of AI, like making medicine and education cheaper.
Critics of this idea point out that it’s not optimally efficient in an economic sense, but they’re not considering the broader value of work for individuals and society. And with all the accelerated innovation we will have, we’ll be able to afford a little inefficiency as the price for keeping people employed.
I proposed a robot tax years ago and most of the reaction was that it was a strange idea. I’m still a big proponent of it. Although it is not the whole solution to the threat of AI, it is part of a wise response.
However we raise money for more assistance, it needs to reach the people who need it most, including workers who lose their jobs to AI and robots, people whose hours or wages decline, and communities where the losses are concentrated. We need to start doing that work now so that the systems are ready when the need becomes acute.
What I’m doing.
I will use my voice and time to get AI and equity higher on the public agenda. I will raise the issue with lawmakers every time I visit Washington, D.C., and when I meet with leaders around the world. It will be front and center in my conversations with the people who are developing AI models. I will advocate for the national and international framework I described earlier. The Gates Foundation will help drive beneficial usage, including in Africa. Breakthrough Energy, a company I founded, will use AI to help companies develop cheap clean energy and help solve the climate problem. I will also be writing about AI on a regular basis.
My message to leaders is:
You have a chance to act now, before unemployment rises sharply, communities are hurting, and public trust has eroded. You can make sure that your government handles the problem holistically, rather than divvying it up into multiple bureaucratic fiefdoms. You can make sure AI benefits everyone. And you can work with other governments to meet this national and global challenge.
Finally, I will try to widen the circle of people shaping this debate. It should include workers, college students who are about to enter the workforce, community leaders, religious leaders and faith-based organizations, parents, educators, and others whose voices often aren’t heard but who have insight into how the transition will affect people’s lives.
How do we ensure that the benefits of AI reach people who do not already have wealth, influence, and access?
How do we strengthen the social safety net and help workers and communities thrive even when they’re displaced?
How should public institutions adapt?
And how do we preserve our humanity through all of this?
This unprecedented technology demands an unprecedented global response. If we get it right, the payoff for humanity will be phenomenal and the world will be a more equitable place.
I rarely stop thinking about AI—not because I have all the answers, but because the questions it raises are too consequential to leave to a small group of technologists. Leaders across academia, business, government, and civil society all have a role to play in shaping what comes next.
The doctor can see you now
Expanding access to health care through AI
Today’s AI can transform health care systems and support health care workers the world over.
A core principle underlying the Gates Foundation’s work is closing the innovation gap between rich countries and everyone else. People in poorer parts of the world shouldn’t have to wait decades for new technologies to reach them. That’s why we've worked for 25 years to accelerate access to life-saving medicines and vaccines in low- and middle-income countries.
It's also why, today, the Gates Foundation and OpenAI are announcing an initiative called Horizon 1000 to support several countries in Africa, starting in Rwanda, as they apply AI technology to improve their health care systems.
Over the next few years, we will collaborate with leaders in African countries as they pioneer the deployment of AI in health. Together, the Gates Foundation and OpenAI are committing $50 million in funding, technology, and technical support to back their work. The goal is to reach 1,000 primary healthcare clinics and their surrounding communities by 2028.
Today’s AI can help save lives
A few years ago, I wrote that the rise of artificial intelligence would mark a technological revolution as far-reaching for humanity as microprocessors, PCs, mobile phones, and the Internet. Everything I’ve seen since then confirms my view that we are on the cusp of a breathtaking global transformation.
All over the world, AI, in the form of LLMs and machine learning models, are improving far more quickly than I first anticipated. From science to education to customer service and more, AI tools are reshaping every facet of our lives.
I spend a lot of time thinking about how AI can help us address fundamental challenges like poverty, hunger, and disease. One issue that I keep coming back to is making great health care accessible to all—and that’s why we’re partnering with OpenAI and African leaders and innovators on Horizon 1000.
Not enough doctors in the house
We have seen amazing successes in global health over the past 25 years: child mortality has been cut in half, and there are now real pathways to eliminating or controlling deadly diseases like polio, malaria, TB, and HIV. But one stubborn problem that keeps slowing progress is the desperate shortage of health care workers in poorer parts of the world.
In Sub-Saharan Africa, which suffers from the world’s highest child mortality rate, there is a shortfall of nearly 6 million health care workers, a gap so large that even the most aggressive hiring and training efforts can’t close it in the foreseeable future.
These huge shortages put health care workers in these countries in an impossible situation. They’re forced to triage too many patients with too little administrative support, modern technology, and up-to-date clinical guidance. Partly as a result, the WHO estimates that low-quality care is a contributing factor in 6 to 8 million deaths in low- and middle-income countries every year, and that’s not even counting the millions who die because they aren’t able to access health care at all.
Rwanda leads the way
Today’s AI can help save those lives by reaching many more people with much higher-quality care.
Rwanda currently has only one health care worker per 1,000 people, far below the WHO recommendation of about four per 1,000. It would take 180 years for that gap to close at the current pace of progress. So, as part of the 4x4 reform initiative, Minister of Health Dr. Sabin Nsanzimana recently announced the launch of an AI-powered Health Intelligence Center in Kigali to help ensure limited health care resources are being used as wisely as possible.
As part of the Horizon 1000 initiative, we aim to accelerate the adoption of AI tools across primary care clinics, within communities, and in people’s homes. These AI tools will support health workers, not replace them.
On the horizon
Minister Nsanzimana has called AI the third major discovery to transform medicine, after vaccines and antibiotics, and I agree with his point of view.
If you live in a wealthier country and have seen a doctor recently, you may have already seen how AI is making life easier for health care workers. Instead of taking notes constantly, they can now spend more time talking directly to you about your health, while AI transcribes and summarizes the visit. Afterwards, AI can handle much of the onerous paperwork, so doctors and nurses can focus on the next patient.
In poorer countries with enormous health worker shortages and lack of health systems infrastructure, AI can be a gamechanger in expanding access to quality care. I believe this partnership with OpenAI, governments, innovators, and health workers in sub-Saharan Africa is a step towards the type of AI we need more of: systems that help people all over the world to solve generational challenges that they simply didn’t know how to address before. I invite others working on AI to think about how we can put these massively powerful tools to the best use.
This announcement is a great example of why I remain optimistic about the improvements we can make. I’m looking forward to seeing health workers using some of these AI solutions in action when I visit Africa, and I plan to continue focusing on ways AI technology can help billions of people in low- and middle-income countries meet their most important needs.
Buzz off
Small bugs, big breakthroughs
Science holds the key to stopping deadly pests like mosquitoes and screwworms.
What do humans and cows have in common? Among other things, we’re both victims of tiny insects.
For cows, the latest culprit is the New World screwworm. Despite the name, the screwworm is actually a type of fly that likes to lay its eggs on animals like cows, which creates an often-fatal wound on the animal’s hide. Screwworms once killed up to one million cattle a year here in the United States, and sixty years after we eliminated them in our country, they’re back.
For humans, one of our greatest nemesis is the mosquito. There are plenty of reasons to hate mosquitoes, but malaria is easily at the top of the list. The disease kills more than 600,000 people every year, most of them children, and it’s transmitted when a mosquito infected with a parasite called Plasmodium bites you.
Protecting people (or cattle) from an insect poses an interesting challenge. How do you stop something so small from hurting anyone? There are lots of different ways to approach the problem.
One approach is to keep insects out of the places where people are. There are already lots of tools that do this with mosquitoes, with more in the pipeline. The most widely used is the bed net, a gauzy sheet of fabric treated with an insecticide that kills any mosquito that tries to reach the person sleeping under it.
Bed nets are magical. In some places where malaria is endemic in Africa, they’ve reduced the number of children who die before the age of 5 by 20 percent. But there’s a problem: Mosquitoes can develop resistance to the insecticide used in bed nets, just like bacteria can evolve resistance to antibiotics.
Enter the dual active ingredient bed net. (You’ll often see them referred to as dual AI nets, even though they have nothing to do with artificial intelligence.) By treating bed nets with two different insecticides, scientists have been able to figure out how to negate a mosquito’s resistance and keep people safe. The catch is that dual AI nets are more expensive than regular bed nets, which is why the Global Fund and the Gates Foundation stepped in to make them affordable for the countries that needed them most. The results so far have exceeded my expectations. Dual AI nets now make up more than half of the bed nets used, just two years after they became available.
Bed nets have another flaw: They only protect you while you’re under them, even though mosquitoes are also active in the hours before you go to sleep and after you wake up. A new tool called a spatial emanator aims to bridge that gap. It basically works like a plug-in air freshener—but instead of releasing a nice fragrance, it slowly releases an insecticide at a low-enough dose that doesn’t harm people but drives away any mosquito that might enter your home.
When spatial emanators received the green light for use a year ago, they became the first new malaria-prevention tool the WHO has recommended in over a decade. I’m super excited about their ability to protect people from mosquitoes for more hours of the day.
Another approach to stopping insects is to target them at the population level. That’s how the world stopped screwworm the first time. In 1954, scientists figured out a way to use radiation to make the males sterile. They released the neutered insects into the target area, and since they couldn’t reproduce, the population died off. This approach worked sixty years ago, and it still works today (and scientists are working on even more effective methods).
What if we could use a similar approach to stop mosquitoes? Last year, I wrote about an incredible project in Tanzania called Transmission Zero. The idea behind it is simple: a mosquito that can’t give you malaria.
Tanzanian scientists have found a way to make Anopheles gambiae mosquitoes—the species responsible for most of the malaria in Africa—produce two types of molecules, naturally found in frogs and bees, that block the parasite from developing inside the insect. The mosquitoes would continue flying around, doing their mosquito business, but they wouldn’t be able to make anyone sick with malaria. Each time they mated with another mosquito, they would pass on the gene that protected them from the parasite. (I just published a new profile of Dr. Lina Finda from the Ifakara Health Institute in Tanzania, who is helping lead this work.)
These malaria-free mosquitoes could potentially help save tens of thousands of lives every year. And Tanzania isn’t the only country on the cutting edge of advancing this work. The Ugandan Virus Research Institute and the University of Sciences, Techniques and Technologies of Bamako in Mali are also doing pioneering work to move the field forward. Scientists are learning more every day about the role mosquitoes play in ecosystems, and research is now underway on two other species beyond Anopheles gambiae.
Dual AI bed nets, spatial emanators, and malaria-free mosquitoes are just the latest breakthroughs to come out of the robust malaria innovation pipeline. Treatments continue to get better, and vaccines are already proving to save lives, with even more effective next-gen vaccines to come. A lot of interesting work is underway with endectocides, a type of drug that could potentially make your blood toxic to mosquitoes. There’s even a fascinating trial that looks at whether targeting mosquito larvae in rice paddies could make a difference. The goal of this trial is to stop malaria, but early results from Nigeria and Rwanda indicate that larval control could boost rice yields as much as 50 percent, which would be incredible for farmers.
Unfortunately, while the R&D progress we’re making is remarkable, the same can’t be said for the fight against malaria overall. Donor governments are cutting health aid—including money for the Global Fund, which has saved more than 70 million lives to date by helping deliver lifesaving tools like bed nets. Last year, our partners across Africa pulled off a miracle to minimize the impact of the cuts. With support from our foundation, they found creative ways to distribute supplies that were already in warehouses across the continent.
This year, the picture looks different. While some funding has since been restored, cuts from multiple donor governments mean it's not yet enough to guarantee bed nets and other tools reach every family who needs them. Our foundation is doing everything we can to help close that gap. I continue to advocate for increased funding, because it is ridiculous to put the health of the world’s children at risk when we know how to save them.
I believe we can end malaria forever. We have some of the tools we need already, and I think we’ll have the rest soon. We can defeat mosquitoes, just like we stopped screwworm more than half a century ago and just like we’ll stop it again. The question is whether the world will choose to make it happen.
The choice is obvious to me. We have an opportunity to ensure that no child dies from malaria ever again. Let’s take it.
Lend an ear
The art and science of listening
Dr. Lina Finda is making sure African communities have a say in how the world fights malaria.
Dr. Lina Finda’s work sounds simple. “My job is to listen,” she says. But the reality is much more complicated. On a typical day, she has to walk into a village in southern Tanzania or a meeting hall in Uganda and gauge reactions to the idea of ending malaria by an unusual method: releasing more mosquitoes.
It’s not as crazy as it seems.
That’s because the mosquitoes she’s talking about in this case carry a gene that blocks the malaria parasite from developing, so the mosquito can’t get you sick even if you get bitten. (I just wrote about the project researching these malaria-free mosquitoes, Transmission Zero, along with the other tools that are helping us fight this disease.) Release enough of them into the wild and, in theory, the trait spreads on its own until the local mosquitoes can no longer transmit the disease.
The science is advancing, and it’s exciting. But none of these malaria-free mosquitoes have been released in Africa yet. Whether that ever happens is a decision that will be made by African governments and the people who live where these mosquitoes would circulate. Finda co-founded the African Conversations Initiative to make sure those people have a say. Her team is now working in eight countries: Tanzania, Kenya, Uganda, Rwanda, Zambia, Ghana, Nigeria, and Senegal.
The question that started it
Finda first learned about the potential of malaria-free mosquitoes in 2017, at the beginning of her PhD in public health.
“My thought was, oh my God, we might eliminate this disease in my lifetime,” she says.
All the scientists in the room with Finda were equally impressed and excited. But she knew this kind of idea would never leave a lab if there wasn’t community trust and buy-in.
So she asked herself a question: “How might other people react to this?” She dedicated the rest of her career to understanding the answer.
Listening and learning
Her first attempts to explain malaria-free mosquitoes went poorly. The process that creates malaria-free mosquitoes is hard to describe, and Finda assumed that a farmer with no formal schooling would never get there. So she gave up on finding the right words and told the truth instead: She didn’t know how to talk about it. “I was honest with the community members and saying, I really don’t know what to call this or how to talk about it.”
The response surprised her.
One of those community members was Aloyce Kimario, a farmer who also teaches at a primary school outside Ifakara. He had never heard of malaria-free mosquitoes before Finda came to see him. He had, however, spent his whole life rearing animals.
The pigs he keeps are a local breed, hardy against the diseases that circulate around Ifakara. But they’re small. When he wants animals big enough to sell well, he crosses them with a heavier breed and hopes the piglets come out with the best traits of both sides. There’s a Swahili phrase for this, kubadilisha mbegu, which translates to “changing the seed.”
So, Finda started asking farmers to describe their ideal animal. One told her he wanted a pig that was 90 percent of the heavy breed and 10 percent of the local one.
“So what this technology does,” she told him, “is it makes sure that you get exactly what you want.”
Aloyce can now explain the science behind malaria-free mosquitoes, and the case for them, without any help from Finda, in terms other farmers immediately understand.
What she wishes scientists understood
Finda admits to underestimating what local farmers would be able to grasp, and she says she sees the science community making the same mistake. Worse, she says, “they assume that when someone opposes something it is because they don’t know it, and if they could know it, then they would definitely accept it.”
“From my years of listening to everyone, I have learned that these groups are quite knowledgeable,” she says. They may not use the scientific terminology, “but they understand it in their context.”
Finda’s team has now sat down with national malaria programs, regulators, scientists, civil society organizations, faith leaders, and youth groups from more than 25 African countries. Each group worries about something the others don’t, and all of the worries are valid.
“You don’t ever hear someone say, I want to develop a solution for this disease. Let me go talk to a priest,” Finda says.
But that’s exactly what Finda did. One of the leaders she convened was the presiding bishop of the Moravian Revival Church in Tanzania, who had learned about genetically modified organisms while studying theology in the UK but had never encountered the idea applied to mosquitoes. He prayed about it and came out in favor. According to Finda, many Muslim leaders she connected with reached a similar conclusion. They just had to be asked.
Making sense of the numbers
Still, Finda has encountered substantial opposition and even anger.
When she presented the latest national malaria mortality figures to a group of community leaders in Nigeria, they took the statistics as an accusation and nearly threw her out. “You are saying that many people have died of malaria in Nigeria. Show us where they are buried,” they demanded. “Why aren’t our hospitals flooded with malaria patients?”
Finda learned a lesson from this that I’ve had to learn and relearn myself: It’s not the scale of lives lost or saved that captures people’s attention. It’s the individual stories.
“The mothers want to talk about the children they lost,” Finda says. “Those numbers do not mean anything at all.”
So now, when she meets with people, she starts by asking about their own experiences. Aloyce, the teacher-farmer, told her he gets malaria roughly twice a year. So do his children, with some episodes landing them in the hospital. The bishop told her his firstborn child died of it.
Finda herself got malaria around the age of six. Her mother was traveling, so it fell to Finda to administer chloroquine, the recommended treatment at the time, to herself and her toddler brother twice a day for seven days, while both of them were vomiting. She shares this experience, too.
The preparation is worth it
Finda thinks we are still at least a decade away from any government decisions to release malaria-free mosquitoes. In the meantime, African-led research will continue to advance scientific understanding that can inform these decisions and those required to strengthen regulatory systems to govern them. Everything she does is working up to that moment, and aimed at making it as anticlimactic as possible.
“When it is released in the newspapers or the radio or TV,” she says, “that should not be the first time that people hear about this technology.”
For many people, because of Finda’s work, it won’t be.
Bug fix
The buzz stops here
African scientists are engineering mosquitoes that can’t spread malaria.
A genetic cheat code
Moving ahead responsibly
No fever dream
How the U.S. got rid of malaria
This is how a parasite helped build the CDC and changed public health forever.
I spend a lot of time thinking and worrying about malaria. After all, it’s one of the big focuses of my work at the Gates Foundation. But for most Americans, the disease is a distant concern—something that happens “there,” not here.
That’s true today. It wasn’t always.
It was especially rampant in the South, from the Carolinas and the Mississippi Delta down to Florida and all along the Gulf Coast.
Every summer, people braced for the start of “fever season.” In her Little House on the Prairie books, Laura Ingalls Wilder wrote about what she called “fever ‘n’ ague.” A laundry list of presidents—including George Washington, Andrew Jackson, Abraham Lincoln, and Ulysses S. Grant—battled the disease.
During the Civil War, Confederate General Robert E. Lee was even counting on malaria to weaken Union troops, confident that “the climate in June will force the enemy to retire.” (It ended up crippling his own army more.)
Without modern medicine, or any understanding of how the disease spread, people reached for whatever remedies they could find: drinking vinegar and whiskey, rubbing onions on their skin, and boiling bitter herbs into tea. Powdered quinine, a substance derived from cinchona bark, actually worked—but it was expensive and hard to obtain, so few people had access to it.
For most people, the fevers kept returning year after year and summer after summer.
The first breakthrough came at the turn of the 20th century. Scientists finally proved that malaria was transmitted by mosquitoes—not, as had been previously thought, by contaminated water or poor air quality. (Malaria means “bad air” in medieval Italian.) It was a crucial discovery. Finally, people knew what to target. Across the South, some communities began draining swamps to try to control their mosquito populations. But most of these efforts were basic and improvised. What was needed was the kind of massive, coordinated, well-funded approach that only the federal government could mount. Enter one of the most ambitious and impactful infrastructure projects in American history: the Tennessee Valley Authority.
Enter one of the most ambitious and impactful infrastructure projects in American history
the Tennessee Valley Authority.
The TVA wasn’t created to fight malaria. Launched in 1933 as part of the New Deal, its mission was mainly economic: to bring electricity and jobs to the rural South, where some of the country’s poorest people lived, during the Great Depression. But the region also had some of the nation’s highest malaria rates, with 30 percent of its population infected. TVA leaders quickly realized their work wouldn’t succeed unless public health improved too.
So they incorporated malaria prevention into their projects. As engineers built dams and power plants across the region, they also drained thousands of acres of swamps, reshaped rivers, regraded land, and upgraded housing—which all helped to destroy mosquito breeding grounds. At the same time, public health campaigns educated people on installing window screens and eliminating standing water around their homes after storms. Then came World War II.
Then Came
world war II
As military bases popped up across the South, malaria became a growing threat to soldiers and defense industry workers. So the U.S. responded by launching a new program in 1942: the Office of Malaria Control in War Areas, headquartered in Atlanta. It was the federal government’s first centralized program created explicitly to fight malaria—and it laid the groundwork for what would become the Centers for Disease Control and Prevention, or CDC, which officially took over the malaria effort in 1947.
The goal of the campaign, which began with wartime control before transitioning to peacetime eradication, was simple but ambitious: Stop mosquitoes from spreading malaria, and stop people from carrying it.
ON THE MOSQUITO FRONT
The campaign launched the largest insecticide operation in U.S. history and paired it with an aggressive effort to destroy mosquito breeding grounds. Teams of sprayers went door-to-door with tanks of DDT strapped to their backs, covering millions of homes in what was essentially a chemical shield against mosquitoes. In some areas, airplanes dusted entire counties with insecticide. Meanwhile, construction crews drained ditches by hand or with bulldozers. In Florida, they used dynamite to blast open drainage paths from mosquito-infested marshland.
ON THE HUMAN SIDE
Quinine and later chloroquine—its synthetic successor—were distributed widely, especially in rural areas with high infection rates. These drugs cleared the parasite from the bloodstream, which meant that even if someone was bitten by a mosquito, they wouldn’t pass the disease on. Mobile teams traveled from town to town, testing and treating entire communities. In the Mississippi Delta, they even set up roadside treatment stations where people could stop for a dose on the way to work or school.
Public health messaging played a huge role, too. One memorable cartoon featured a mosquito named Bloodthirsty Ann—yes, short for Anopheles—that taught troops how to reduce their risk of contracting malaria. Its creator was a young army captain named Theodor Geisel, who eventually became better known as Dr. Seuss.
Perhaps the most impressive part of the program was its scale and speed. In just a few years, tens of thousands of public health workers across fifteen states were hired and trained. Doctors, nurses, scientists, teachers, technicians, and trusted community figures knocked on doors, gathered data, treated patients, and made sure no outbreak went unchecked. In 1951, America declared victory over malaria.
In 1951
AMERICA DECLARED VICTORY OVER MALARIA
I think about this history a lot when I’m visiting Sub-Saharan Africa, where the parasite still kills 600,000 people a year. Because in many ways, the strategy hasn’t changed: Stop transmission, clear infections, and build public health systems that prevent malaria from roaring back.
Malarious area of the United States
But the U.S. had some key advantages that made elimination much easier. Compared to the species responsible for most malaria today, our mosquitoes weren’t as efficient at transmitting the parasite. Our climate also limited transmission to the summer months; in tropical regions, people get infected year-round. And by the 1940s, our country had relatively strong infrastructure, even in rural areas, that many malaria-endemic countries today still lack.
ON THE TREATMENT SIDE
So the challenge today is much bigger. Fortunately, today’s malaria-fighting toolbox is much bigger—and better—too.
Instead of blanket spraying DDT, which has since been banned, modern prevention relies on safer insecticide-treated bed nets and indoor spraying techniques that use smaller doses of more targeted chemicals. Sugar baits, which lure mosquitoes to ingest a lethal dose of insecticide, are already helping reduce their numbers. And gene drive technology could soon block the parasite inside the mosquito itself—so even if someone gets bitten, they won’t get infected.
Chloroquine has been replaced by artemisinin-based combination therapies, or ACTs, which are more effective and less prone to resistance. New drugs like tafenoquine are helping eliminate recurring strains. Seasonal chemoprevention protects children during peak transmission months. And the first malaria vaccine has been approved, with more on the way.
Malaria elimination is never easy. But unlike a century ago, it’s no longer a mystery. The world knows how to stop this disease. We’ve done it before. And with the right investments and innovations, we can do it again—this time, for everyone.

Bite back
Great news for mosquito haters
With some breakthrough tools, the end of malaria could be here soon.
I was scrolling Reddit recently when I saw a video of a mosquito trying and failing to suck someone’s blood. Some of the replies were pretty funny, but I noticed that most of them were just some form of “How do I get this person’s superpower?” It was a great reminder of how universally hated these bloodsuckers are.
But I have good news—for Reddit users and everyone else: Real progress has been made in the fight against mosquitoes and specifically against malaria, the deadliest disease they carry. And I believe we’ll soon have the transformational tools needed to end malaria entirely.
Eradication is a goal Melinda and I set back in 2007, when we stood before a group of global health leaders and called for something many considered impossible: wiping malaria out completely from every country. And until that happened, our goal was—and is—to save as many lives as possible by maximizing the impact of the tools we already have. Eradicating the disease wasn't a new idea; the World Health Organization had made a similar declaration back in 1955. But that earlier campaign, while successful in many wealthier parts of the world, had fallen short across Africa, Asia, the Middle East, Eastern Europe, Central and South America, the Caribbean, and Oceania. Despite half a century of effort, malaria was still infecting up to half a billion people—and claiming a million lives—annually.
Today, the landscape has changed dramatically. In 2022—the last year we have data on—there were 249 million cases worldwide and 608,000 deaths. Those are staggering numbers, but they’re also improvements from where the world was back in 2007. Since then, 17 additional countries have been declared malaria-free by the World Health Organization. Outside of Africa, deaths from the disease have mostly been eliminated.

Proof of progress
Bad news isn’t the only news
There are reasons to be hopeful about the future, if you know where to look.
Sometimes when I tell people I’m optimistic about the future, they look at me like I’m crazy. How could I say that when there’s so much violence in the world, the international order seems to be collapsing, and AI may end up doing more harm than good?
I see all these problems too, and I’m deeply concerned about them. (I am working on a long memo about the risks and benefits of AI that I plan to publish later this month.)
But through my work with the Gates Foundation and other organizations, I also get to see signs of progress that help me stay optimistic.
To me, being hopeful about the future doesn’t mean you ignore the bad news. It’s actually the opposite: You look directly at it and then search for people who are doing something about it. In most cases, you’ll find them. And then you will start to see the broader trend of progress they are contributing to.
Here are some of my favorite signs of progress.
IN THE PAST:
- We’ve cut the number of children who die every year by more than half, from more than 9 million in 2000 to fewer than 5 million now.
- For the first time, we have a blood test for Alzheimer’s and drugs that may slow its progress.
- Electric vehicles now make up about one in four new cars sold worldwide, with sales topping 20 million in 2025.
- There are 1.5 billion fewer people living in extreme poverty today than in 1990, even though the population has risen 50 percent since then.
- Nearly 95 million girls have been fully immunized with HPV vaccine, so they’re much less likely to develop cervical cancer later in life.
- More than 86 percent of the world’s adults can read and write, up from about 68 percent in 1979.
IN THE PIPELINE:
- The newest obesity drug in trials produces nearly 30 percent weight loss, almost as good as what surgery achieves. The same class of drugs is expanding fast into related conditions, including sleep apnea, fatty liver disease, and hopefully, osteoarthritis.
- Scientists are developing a single-shot cure for sickle cell disorders, which kill tens of thousands of people every year, and it could be available within five years. The underlying technology is also being used to develop a single-shot HIV cure.
- We’re close to eradicating polio, which is endemic in only two countries. We’re nearly done with Guinea worm disease as well, cutting it from 3.5 million cases in 1986 to just ten last year.
- The mRNA technology behind some COVID vaccines is now being used for cancer vaccines, with nearly 100 in clinical trials for melanoma, lung, pancreatic, and other cancers.
- A new tuberculosis vaccine is in final-stage trials. If it works, it will be the first new TB vaccine in more than a century and could prevent tens of millions of cases over the next 25 years.
I love telling these stories. Here’s a video where you can see the amazing impact of the Green Revolution.
I find that trying to keep a positive attitude is valuable in itself. It keeps me grounded so I don’t swing toward one political extreme or another. I think the world might be less polarized if more people had a sense of the positive things that are going on in addition to the problems we need to solve.
You can find more videos here about progress. If you see one that strikes a chord for you, I’d encourage you to share it.

A remarkable transformation
Memories from an inspiring trip to Rwanda
Rwanda's long-term investments in people, strong institutions, and delivery have translated into real progress.
I just got back from the most incredible week in Rwanda. My favorite trips are always the ones that leave me feeling inspired and energized. And if you’re looking for reasons for optimism, Rwanda is a good place to start.
What stood out to me was how Rwanda's long-term investments in people, strong institutions, and delivery have translated into real progress. Over the last 25 years, the country has delivered one of Africa’s most remarkable health transformations. Since the year 2000, the number of children who die before the age of five has dropped by 73 percent. Maternal deaths have fallen by over 80 percent, and nearly all pregnant women now give birth in a health facility with a skilled birth attendant present.
I was lucky to meet many of the local leaders and innovators driving that progress. Africa is entering a new era that is increasingly shaped by African leadership, and it’s amazing to see firsthand. At the Gates Foundation, our role is to listen to leaders like the ones I met, and to support them with resources, data, and technical expertise so they can get the greatest value from every dollar they invest in saving and improving lives.
These were some of the highlights from the week:
Rwanda’s frontline health heroes: My trip started in Mwulire, where Gaudence Ngendahayo, a community health worker, showed me what her work looks like as she made the rounds in her catchment. Rwanda’s community health worker program is the backbone of its health system, and when you watch Gaudence work, it’s easy to see why. She goes house to house checking in on how families are doing. If someone isn’t feeling well, she either treats them herself or refers them to the health center nearby. (Around 60 percent of all malaria cases in Rwanda are treated by community health workers.) Along the way, she collects invaluable information that helps connect communities to the broader health system.
Primary healthcare in the community: If Gaudence isn’t able to treat someone herself, their next stop is the Mwulire Health Center. I visited the facility, which is primarily staffed by nurses and offers all of the services you would expect from a primary care provider: outpatient consultations, prenatal and maternal care, normal deliveries, family planning, immunization, and HIV and TB services. (More complex cases are referred to district hospitals.) It was interesting to learn more about how the data collected here flows through the health system to Rwanda’s National Health Intelligence Center, or NHIC, connecting every level of care and helping health workers make quick and informed decisions.
Digging into the data: Next was seeing the NHIC firsthand, where real-time data from clinics, hospitals, and community health workers is used to generate insights that the Ministry of Health uses to make quick, evidence-based decisions. Rwanda has done an incredible job building digital public infrastructure, or DPI, and I got to learn more about how its investments have paid off over the last decade. Rwanda has created a culture where data and evidence matter. They track what they're doing, they see what needs to improve, and they take action. The NHIC is also where Horizon 1000, our partnership with OpenAI to improve quality care by accelerating the adoption of AI tools in primary health clinics, is housed. I wrote about the initiative earlier this year, and it was exciting to see it taking shape on the ground. Seeing real pilots underway rather than plans on paper was one of the best parts of the trip. I can’t wait until the day we can point to a patient who got better healthcare because of it.
Manufacturing key medical supplies: Most people don’t think about the supply chain when they picture healthcare systems, but it’s essential to ensuring health workers have the tools they need. The staff at Mwulire Health Center use auto-disable syringes—injectors that can only be used once, which prevents the spread of bloodborne pathogens like HIV—made nearby at the TKMD Rwanda Manufacturing Facility. Being able to make key supplies locally makes the system more resilient and reduces its dependence on imported products, while also benefiting neighboring countries that rely on these essential medical products.
Up close with Rwanda’s digital transformation: I’ve followed Rwanda’s work on DPI closely for many years, but there is nothing quite like seeing it in person at the Upanzi Digital Experience Center at Carnegie Mellon University Africa. The Upanzi Network was created to build Africa’s capacity to develop, test, adopt, and govern open-source digital technologies—like identity, payments and cybersecurity—in a way that is secure, inclusive, trustworthy, and locally relevant. I got to see their DPI stack up close, which is built on open-source platforms like MOSIP and Mojaloop and is now being adopted by a growing number of African governments to run their national critical infrastructure. It was super interesting to hear from the young researchers shaping it with their lived experiences across Africa. This is exactly the kind of African-owned, African-built infrastructure that will improve lives across the continent.
Young innovators leading the way with AI: I always love meeting with brilliant young innovators, so I knew visiting the Rwanda AI Scaling Hub in Kigali would be fascinating and inspiring. I met founders who are using technology and AI to tackle local development challenges, from expanding access to healthcare to helping communities access critical services. Dr. Loza Admassu, founder of Ambucycle, is using data-driven logistics to improve emergency medical transport and connect patients more quickly to life-saving care. Audace Niyonkuru, founder of Digital Umuganda, told me about the efforts she’s leading to collect and curate African local-language voice data to help train AI models that better understand and serve African communities. What stood out was not just the technology itself but the ambition, creativity, and determination of young Africans who are building solutions for their own communities and creating innovations with the potential to benefit people around the world.
The next generation of African health leadership: If I had to pick one highlight of my trip, it would be my day at the University of Global Health Equity in Butaro. My friend Paul Farmer was working at the university when he died, and it was moving to see how his vision of equity continues to shape the university, the hospital, and the community around it. Watching medical students train for the kinds of emergencies they will one day manage in their own communities was especially inspiring. I was honored to help launch the Butaro Dialogues and speak with students from across the continent, including members of the Consortium of Medical Students' Associations. Their questions reflected both a deep understanding of today's challenges and an ambitious vision for a more equitable future of global health. Africa’s greatest resource has always been its people. Sitting across from these young people as they talked about their big ideas for global health, it was crystal clear that they are the next generation of leaders who will shape the continent’s future.
Growing farms with data and AI: My last stop was the One Acre Fund, an African-focused organization that helps millions of smallholder farmers get more out of every harvest. I met farmers who work with the program and leverage on-time delivery of seeds and fertilizer, along with hands-on training, to help their families grow more food and earn more money. (Rwandan farmers in the program generated $118 million in new profits last year alone.) One Acre Fund connects farmers with technology by building on Rwanda’s digital farmer registry and subsidy system, connecting government data with on-the-ground support. They then pull in AI-powered tools like Virtual Agronomist, which can answer farmers’ questions over WhatsApp using real data on their soil and local weather. I’m super excited to see how innovations like this can arm more farmers across Africa with the information they need.
My time in Rwanda reminded me how much progress can be made when innovation reaches the people who need it most. Across the country, scientists, entrepreneurs, and governments are driving breakthroughs that are practical, affordable, and designed for local needs. Rwanda has already achieved major progress with even greater opportunities ahead, and its young people are poised to shape not only the African continent, but the world.















Gone for good
“AIDS-free generation” is no empty promise
New tools mean we’ll be able to stop the pandemic forever.
PrEP talk
From once a day to twice a year
Long-acting preventatives will save more lives from HIV/AIDS.
I’ve been working in global health for two and a half decades now, and the transformation in how we fight HIV/AIDS is one of the most remarkable achievements I’ve witnessed. (It’s second only to how vaccines have saved millions of children's lives.)
At the dawn of the AIDS epidemic, an HIV diagnosis was often a death sentence. But in the years since, so much has changed. Today, not only do we have anti-retroviral medications that allow people with HIV to live full, healthy lives with undetectable viral loads—meaning they can’t transmit the virus to others. We also have powerful preventative medications known as PrEP, or pre-exposure prophylaxis, that can reduce a person’s risk of contracting the virus by up to 99 percent when taken as prescribed. It’s an incredible feat of science: a pill that virtually prevents HIV contraction.
In theory, if we could get these tools to everyone who needs them and make sure they’re used correctly, we could stop HIV in its tracks. Because when people with the virus receive proper treatment, they can’t transmit it to others. And when people at risk take PrEP, they can’t contract it. In practice, however, getting these tools to people—and making sure they’re used correctly—is the hard part. Especially for PrEP.
That’s because current preventatives require people to take medication every single day. Miss a dose, and protection drops. It’s like trying to remember to lock your front door 365 times a year—if you mess up once, you’re vulnerable. For many people, the barriers stack up quickly. Some have to walk hours to reach a clinic. Others struggle to store medication safely or discreetly at home. And many face judgment and stigma for taking PrEP, especially young women in conservative communities. The very act of protecting yourself can lead to being shamed or ostracized.
That’s why I’m so excited about a new wave of innovations in HIV prevention. Scientists are in the process of developing several longer-lasting PrEP breakthroughs, each with distinct advantages that could help more people protect themselves on their own terms.
Lenacapavir, which requires only two doses per year through injection, could open HIV prevention up to people who can’t make frequent clinic visits. Cabotegravir, another injectable option that works for two months at a time, offers a more flexible dosing schedule than daily PrEP pills, too. Meanwhile, a monthly oral medication called MK-8572, still in the trial stage, could provide an alternative for people who prefer pills to injections. The Gates Foundation is even exploring ways to maintain a person’s protection for six months or longer. And researchers are working on promising PrEP options that include contraception, which would be particularly valuable for women who need both types of protection.
To understand how these options work in real life, and not just in labs, our foundation has supported implementation studies in South Africa, Malawi, and elsewhere. Unlike traditional clinical trials that test safety and efficacy in highly controlled settings, these studies examine how medications fit into people’s lives and work in everyday circumstances—looking at ease of use, cultural acceptance, and other practical challenges. This real-world understanding is crucial for successful adoption.
Some people ask me if these new preventative tools mean the Gates Foundation has given up on finding an HIV vaccine. Not at all. In fact, these advances push us to aim even higher in our research for a vaccine that could prevent HIV for a lifetime—and not just a few months at a time. Our goal is to create multiple layers of protection, much like modern cars have seatbelts, airbags, and even collision-warning sensors. Different tools work better for different people in different ways, and we need every tool we can get.
But even the most brilliant innovations make no difference unless they reach the people who need them most. This is where partnerships become crucial. Through grants to research institutions around the world, the foundation is working to lower manufacturing costs for HIV drugs so they’re accessible to everyone, everywhere. Then there are organizations like the Global Fund and PEPFAR, which have been instrumental in turning scientific advances into real-world impact.
The Global Fund—which needs to raise significant new resources next year to continue its work—currently helps more than 24 million people access HIV prevention and treatment. And PEPFAR has saved 25 million lives since its inception in 2003—a powerful example of how American leadership can build tremendous goodwill while transforming the world. Motivated by the belief that no person should die of HIV/AIDS when lifesaving medications are available, President George W. Bush created PEPFAR with strong bipartisan backing and it continues to serve as a lifeline to millions of people.
We're at a pivotal moment in this fight. Twenty years ago, many believed it would be impossible to deliver HIV treatment at scale in Africa’s poorest regions. Since then, we’ve made fantastic progress. Science has shown us promising paths forward—for better prevention options, easier treatment regimens, and, maybe one day, an effective vaccine. Our task now? Ensuring the life-saving innovations we already have reach the people whose lives they can save.

Game changer
Grassroot Soccer scores a hat trick for African youth
This organization uses the beautiful game to reach millions of young people with lifesaving services.
I’ve never been much of a soccer fan. (Tennis and pickleball are my favorite sports.) Still, seeing the athleticism and passion on display during the World Cup, I understand why soccer has earned the nickname “the beautiful game.” What makes soccer even more beautiful is the positive impact it can have off the field.
There may be no better example of this than the work of a unique non-profit organization called Grassroot Soccer, which was featured at a health innovation event where I spoke earlier this week.
For the last two decades, Grassroot Soccer has used the incredible popularity of the game to help young people across Africa navigate some of their toughest health challenges.
Despite significant progress in health and development in Africa, including a dramatic decline in child mortality, HIV/AIDS continues to be a leading cause of death among youth in Africa. Sexual violence threatens the health and safety of girls. A lack of access to contraceptives contributes to high rates of teen pregnancy. And mental health services are often unavailable.
Solving these challenges is difficult—and especially important given that 60 percent of Africans are under the age of 25. So, how can soccer make a difference?
Because it’s so popular, soccer offers a hook to capture the attention of young people. Grassroot Soccer uses the game to involve them in activities that encourage them to live healthier, more productive lives.
Here’s one simple example. In an activity called “Risk Field,” players are asked to dribble a soccer ball through cones labeled with some of the risky behaviors that young people often encounter, such as unprotected sex, HIV, multiple partners, and alcohol.
The local youth who serve as Grassroot Soccer coaches are a critical component of the program. Trained in basic counseling skills, the coaches play an important role as trusted mentors to the young participants.
The coaches also accompany adolescents to clinics where they can get HIV testing, contraceptives, and other services. (In some countries, young people might be turned away because of their age or criticized by health staff for seeking contraceptives and testing. The coaches serve as advocates to support their right to health services.) Coaches also conduct home visits to talk with parents and guardians about their programs and health services.
Founded in 2002 by Dr. Tommy Clark, a pediatrician and former professional soccer player, Grassroot Soccer initially focused on stopping the spread of HIV. (The Gates Foundation was an early funder of its work.) Today the organization works in more than 60 countries and has reached more than 18 million young people.
Studies have shown that its participants had better access to sexual and reproductive health services, were more likely to stick with their HIV treatment, and were less likely to experience depression.
That kind of impact gives everyone, even casual soccer fans like me, something to cheer about.

Inspired by a farmer
These married scientists are leading the way on HIV
The Abdool Karims revolutionized the fight against AIDS. Now they’re helping the world tackle COVID-19 too.
Quarraisha and Salim Abdool Karim are two of the most respected HIV/AIDS researchers in the world. This year, the wife-and-husband team has also helped shape the world’s response to COVID-19. But it was a more humble setting that sparked their careers in epidemiology more than 30 years ago.
They had met in medical school in their native South Africa before moving to New York City for graduate school. In 1988, shortly after they were married, they took a trip to Mexico, where they met up in a tiny village in the Sierra Madre mountains with a friend, a physician who had written a seminal textbook on health care in remote rural settings.
Outside the village’s health clinic, they saw a man pedaling a bicycle that was mounted on a stand and connected to a power cable. It turned out that a local farmer also doubled as the village’s dentist—a pretty good one, apparently—and volunteers would pedal the bike to power his drill.
“We watched how this community took their destiny in their own hands,” says Salim, “and they had the most amazing dental care from this bicycle powering a drill. It imprinted on us how people can really change their own world.”
It was a powerful lesson about the need for scientists to understand and collaborate with the people they’re trying to help. The experience in that village would shape the rest of their careers, especially when they created a research center in South Africa designed to address two of the biggest problems in HIV/AIDS in Africa.
By the 1990s, the disease was devastating the Abdool Karims’ home country—and still is today. One out of every five people in the world with HIV lives in South Africa. The couple saw two issues that were rarely on the agenda of other HIV experts. One was that young women were bearing a disproportionate burden in the epidemic, and that there was no way to control the epidemic if their needs weren’t addressed. The other was that people living with HIV are at a high risk of contracting and dying from tuberculosis—a link that’s now known as HIV-TB coinfection.
“These were very much our problems in Africa that few others were working on,” says Quarraisha, “and if we waited for solutions from elsewhere, it wasn’t going to come. We had to take the lead.”
In 2001, they brought together a group of researchers they felt could make a bigger impact on HIV and named the group CAPRISA (for the Center for the AIDS Program of Research in South Africa). Today CAPRISA runs three clinics where they provide antiretrovirals to people living with HIV and study new approaches to treating and preventing the disease. It is regarded as one of the world’s most influential AIDS research programs.
CAPRISA is probably best known for a landmark study published in 2010 proving for the first time that a microbicide—a gel that a woman could use before and after sex—can offer some protection from the virus. Scientists had been trying to make effective microbicides for nearly two decades, but the Abdool Karims’ formulation—one that used tenofovir, a drug normally given to people who already had HIV—was the first to offer any protection. Although the field has now moved on from microbicides and is focused on a more effective daily pill instead, the concept is still based on CAPRISA’s microbicide findings.
CAPRISA is as admired for the way it works as for its results. Inspired by the farmer-dentist they met in Mexico, Salim and Quarraisha make it a priority to empower the people they’re trying to help. They work closely with community leaders to make sure their research efforts are informed by realities on the ground and embraced by their neighbors. Here’s the story of one remarkable CAPRISA staff member, Gethwana Mahlase, and the way she represents the program in her community of Vulindlela.
Over the next few years, Quarraisha and Salim hope to build on their study of tenofovir as an HIV preventative. Right now, the best option is a pill you have to take every day, a regimen that can be hard to keep up. So CAPRISA is working on a form of the drug that could protect a woman for as long as a year at a time.
They’re also working on a fascinating approach called “broadly neutralizing antibodies,” which dates back several years. In 2012, they discovered that an HIV-positive woman in one of CAPRISA’s studies had a trait that was, as far as they knew, unique. The antibodies made by her immune system could attack not only the strain of HIV that she had, but also—this was the impressive part—80 percent of the other known strains of HIV from around the world. If they could isolate the cells that made these antibodies, reproduce them, and use them to create antibodies for other people, it would be a game changer.
After years of painstaking work with a number of partners, they were able to create the broadly neutralizing antibodies in a lab and test them in monkeys, with very positive results. Now the antibodies are being studied in humans for safety and, eventually, efficacy. If this approach works, you would need to get an injection just twice a year in order to get protection—a dosage that is far more practical than a daily pill. Success would also point the way toward the ultimate goal of an HIV vaccine.
Unfortunately, much of the Abdool Karims’ attention has been elsewhere this year. Drawing on their experiences from HIV and TB, they are helping guide the COVID-19 response in South Africa and around the world. It is a shame that they haven’t been able to focus on HIV/AIDS, but on the other hand, it is a reminder of how fighting old diseases like HIV helps the world prepare for new ones like COVID-19. Investing long-term in programs like CAPRISA—or work on polio or malaria—not only prevents deaths and disability from specific diseases, it also strengthens the overall field of global health. So when a pandemic comes along, we have a network of experts like Quarraisha and Salim ready to pitch in.
What strikes me about this couple is how upbeat they are, even in the face of devastating diseases like the coronavirus and HIV. Their motto at CAPRISA is, “Each day that you come to work, you should be looking for how today is going to be better than yesterday.” That is a lesson we can all take to heart.
Heroes
Strength in numbers
The story of this amazing woman living with HIV in Mozambique fuels my optimism about our world.
Last year, at an event in New York, I learned about an impressive woman whose story I want to share with you. Her name is Cacilda Fumo, she lives in Mozambique, and every year she helps save hundreds of lives—by reminding them they are not alone.
Mozambique has one of the highest HIV infection rates in the world. More than 1.6 million people—10 percent of the adult population—are living with HIV.
Cacilda was diagnosed with HIV in 2002. “When I first learned about it, I thought I would die,” she recalls. “I used to wake up early morning and check if I am alive or not.”
But then she started meeting other people living with HIV, and as their numbers grew so did her strength and her belief she would live. Cacilda was one of the first in Maputo to be open about her status. She started wearing a t-shirt emblazoned with a logo that reads: “HIV POSITIVE.”
At times, people rejected her because of her status. Many more in her community, however, admired her for her courage, helping her create an even larger circle of friends and supporters. They met every week, praying together, cooking together, and sharing their stories. Eventually, the group had about one hundred people, many of them receiving life-saving anti-retroviral treatment. Cacilda emerged as their leader.
About the same time, Mozambique’s Ministry of Health was struggling to improve the delivery of anti-retroviral treatment. While the program was successful in putting thousands of patients on treatment for the first time, medical staff were overburdened with caseloads. People on HIV treatment often walked miles to reach their clinic and waited in long lines to get care. Every year, about 30 percent of HIV patients dropped off their life-saving treatment.
Working with Doctors Without Borders, the government of Mozambique decided to try a new approach to simplify care to help keep more people on treatment. They started organizing small peer support groups for people on HIV treatment. The idea was simple. Make treatment easier by putting more control into the hands of the patients. A representative from each patient group could pick up all the drugs for the group each month, saving the rest of the group the hassle of going to the clinic. Members of the groups, known as Community antiretroviral therapy (ART) Groups or CAGs, would also support one another to ensure they were all staying on their treatment.
When the program reached Maputo, Cacilda was ready to join. She helped organize dozens of support groups from her network. Then she went one step further. She kept track of the groups, checking whether members were attending their meetings and taking their treatment. If someone fell off treatment, she took upon herself to locate them and find out what was wrong.
“We help people feel strong knowing they are not alone,” she says.
Some patients who stop treatment are addicted to alcohol and forget to take their treatment, she says. Some don’t understand how the treatment works and the stop taking their medication as soon as they feel better. Others get busy with their jobs and drift away.
Whatever the reason, Cacilda warns them of the dangers of stopping treatment and encourages them to restart. Her efforts to bring back residents of Maputo to treatment has become nearly full-time work. Most days residents of Maputo see Cacilda traveling on foot—which is remarkable because due to a childhood injury she uses crutches—through the dirty alleyways and crowded markets in search of people who have stopped treatment. She doesn’t give up until she finds them.
Cacilda’s persistence pays off—in lives saved. Cacilda estimates that she tracks down about 500 people every year and encourages them to resume their treatment.
That’s a remarkable achievement—one that proves how much difference one life can make in the world.
World AIDS Day
The fight against AIDS is filled with heroes. Learn how you can be one too.
Thanks to many heroes, the world has made amazing progress against HIV/AIDS.
On December 1st, the global community will observe World AIDS Day. This year I would like to mark it by highlighting the work of two heroes who are making a difference in the fight against this deadly disease.
Chief Jonathan Eshiloni Mumena is chief of the Kaonde people, who live along Zambia’s border with the Democratic Republic of Congo. Risking his position as his people’s leader, Chief Mumena challenged long-held traditions to encourage Kaonde men to embrace voluntary medical male circumcision as a strategy to prevent HIV transmission. (Male circumcision can reduce a man’s risk of acquiring or transmitting HIV by up to 60 percent.) I had the privilege of meeting Chief Mumena in 2012. His story is an inspiring tale of courageous leadership and deep compassion for his people.
Guided by her belief that health care is a basic human right, Dr. Krisana Kraisintu, a pharmacist from Thailand, has worked tirelessly to make medicines affordable to even the poorest in the world. Her development of generic versions of the lifesaving HIV drugs dramatically reduced treatment costs, saving and improving countless lives. She has also dedicated her pharmaceutical skills to reduce treatment costs for malaria and other diseases.
Of course, Chief Mumena and Dr. Kraisintu are just two of the countless individuals—doctors, policymakers, researchers, activists, and political leaders—whose contributions have helped turn the tide against the disease. Today, 19.5 million people receive lifesaving antiretroviral therapy, giving them the opportunity to live full, productive lives. Improved access to treatment has also meant that millions of babies are now born HIV-free.
Much of this progress has been made possible by the world’s enormous investments in efforts to defeat the epidemic, including the Global Fund to Fight AIDS, Tuberculosis and Malaria, and the U.S. HIV/AIDS program known as PEPFAR, President’s Emergency Plan for AIDS Relief.
Still, many challenges lie ahead in the fight against the AIDS epidemic.
Funding for HIV control has been flat and there’s talk about cuts as the world turns to other priorities. Cuts in funding for HIV/AIDS would lead to sharp increases in deaths and new infections, reversing the gains that have been made the last decade. That’s why it’s more important than ever for the world to reaffirm its commitment to this fight. We need more AIDS heroes—from health care workers and advocates to global leaders. Together, we can bring an end to this public health threat.
If you want to be a hero this World AIDS Day, support the (RED) Shopathon. Our foundation is matching every dollar raised—up to $15 million—to fight HIV/AIDS in Africa.
Eye opener
What my favorite chart leaves out
Every year, 2 million babies are stillborn. A simple retinal scanner can change that.
If you’re anything like me, you have a favorite chart. Mine has been the same for years. It plots under-five mortality year over year—a figure that has dropped by half since the turn of the century, from over 10 million deaths in 2000 to fewer than 5 million in 2023.
In my view, this data is the strongest evidence we have that progress is possible, even in tough times, and that the investments the world has made in vaccines, oral rehydration, bed nets, and better nutrition are working.
But there's a rule in global health statistics that complicates the story: To count as a death, someone must have first been born alive. It sounds simple and obvious. But in practice, it isn't. That's because every year, about 2 million pregnancies end in stillbirth, which is when a baby is lost at 28 weeks or later. That's late enough that the mother has been feeling the fetus move for months. Many parents have already picked out a name. Often, the loss occurs in the final stretch of a pregnancy, or during labor itself, when everyone was expecting a healthy birth.
These tragedies should be central to how we measure child survival. Instead, they've fallen through the cracks—not quite a maternal health issue, not quite a child mortality issue. The UN didn't publish its first full global estimate of stillbirths until 2020, and stillbirth research is still badly underfunded in both rich and poor countries.
What gets measured gets managed, as the saying goes—and what doesn't, well, doesn't.
The data reflects this disparity. Stillbirths have fallen just 34 percent since 2000, compared to 50 percent for under-five mortality over the same period. In 81 countries—mostly low- and middle-income—the stillbirth rate hasn't meaningfully improved at all in 25 years. For every one stillbirth in Europe, there are roughly 40 in sub-Saharan Africa.
What's frustrating is that we know what causes, and therefore how to prevent, most stillbirths. One of the biggest drivers is pre-eclampsia—a dangerous spike in blood pressure during pregnancy—which is responsible for half a million fetal deaths every year, along with 70,000 maternal deaths. Beyond that, the bulk of stillbirths stem from a cluster of conditions we understand well: maternal infections, obstetric complications during labor, and chronic conditions like untreated diabetes.
If we could catch these problems earlier, we'd have a much better chance of intervening before it's too late. But that's hard to do in the rural clinics where most pregnant women receive care, which often have unreliable electricity, no specialists, and little in the way of lab equipment. By the time pre-eclampsia is obvious, or gestational diabetes has gone unmanaged through the third trimester, the harm is often irreversible. Even emergency intervention may not help.
But a few months ago, I got to hold a device that has the potential to make a huge impact: the Remidio fundus camera. You hold it up to a patient's eye to get a high-resolution image of their retina in seconds, no dilation required. A community health worker with a few hours of training can use it. The device itself is about the size of a handheld video camera, battery-powered, and portable enough to carry from village to village.
Why the retina? It's the only place in the body where you can see blood vessels from the outside.
Remidio is a medtech startup out of India, and its camera was originally built to screen for diabetic eye disease. With an AI system running on a phone the camera plugs into, it can pick up early signs of the disease that would otherwise require blood draws and specialist follow-up to catch. It's already been used that way for more than 15 million patients in 40 countries.
But that same hardware, with different software, can also flag the conditions that drive so many dangerous pregnancies. Gestational diabetes sharply increases the risk of pre-eclampsia, preterm birth, and fetal death, and in most of rural sub-Saharan Africa or South Asia, it usually isn't screened for at all, because the standard test requires a lab. A retinal scan offers a different way in. Remidio’s device is currently being used in India to screen pregnant women for conditions that drive stillbirth. And researchers are now adapting the same hardware to screen for anemia and hypertension, too.
A tool like Remidio’s won’t solve the problem of stillbirths alone. We also need more skilled birth attendants, better emergency obstetric care, and stronger health systems. But small, portable, affordable diagnostics in the hands of community health workers are exactly the kind of lever that can start to move a number that hasn't moved in a long time. That's a big part of why the foundation committed $2.5 billion to women's health research and development last year, our largest investment in this area ever.
In 25 years, I hope my favorite chart in the world will have two lines on it: one tracking under-five mortality, and one tracking stillbirths. With the right commitment, I believe both will have fallen dramatically, and both could be approaching zero.

Life and death
How to cut child mortality in half… again
We already know how to save millions of newborn lives.
When Paul Allen and I started Microsoft, we had an ambitious goal: to put a computer on every desk and in every home. A lot of people thought we were out of our minds. But we believed in the power and potential of these machines to change the world. So every day, we came to work determined to make it happen. Now, it’s hard to imagine the world any other way. In a few short decades, that goal became reality for billions.
In 1990, the possibility that the world would be able to cut child mortality in half over the next thirty years would have seemed just as remote. But that’s exactly what happened. And I believe the world can do it again by 2040—we can cut child mortality in half once more—and get even closer to ending all preventable child deaths.
My introduction to this issue came 27 years ago, when I read a piece in The New York Times about deadly drinking water in the world’s poorest countries that contained the following statistic: “Diarrhea kills some 3.1 million people annually, almost all of them children.” Learning that shocked me to my core. There’s no greater pain than the death of a child. The death of millions of them—from something easily treatable in much of the world—is tragedy after tragedy on an almost unfathomable scale.
Before long, I was learning everything I could about global health generally and child mortality specifically. And shortly after, the Gates Foundation, which was just getting off the ground, made it our mission to fight preventable health disparities like this around the world—with an emphasis on children whose lives were being cut short before they ever had a chance.
My look ahead
What it takes to take a breath
New tools can help millions more newborns—and their mothers—survive.
In a rural health clinic, a baby tries to take her first breath.
But her lungs aren’t ready. Because she was born too early, they haven’t developed the slick, soap-like substance that keeps her air sacs from collapsing. Without that substance—called lung surfactant—breathing becomes a desperate, exhausting act.
She’s suffering from respiratory distress syndrome, or RDS, a life-threatening condition that appears within hours of birth in premature babies. Unless she gets treatment, her oxygen levels will plummet and her organs will begin to shut down. In one study from India, every baby born with RDS outside of a hospital setting died. In Ethiopia and Nigeria, RDS is responsible for almost half of all neonatal deaths.
At hospitals in higher-income countries, there’s a way to save her: a liquid form of organically-derived surfactant delivered directly into the lungs. But the procedure requires a highly-trained specialist to guide a breathing tube down the newborn’s windpipe—avoiding the stomach and placing it just right—at a cost of up to $20,000. In many parts of the world, that kind of care simply doesn’t exist.
But what if any healthcare worker anywhere in the world could simply hold a small nebulizer to the baby's face and deliver surfactant as an easy-to-administer inhalant?
This breakthrough—a synthetic surfactant that’s stable enough to be delivered through a nebulizer—is still in development, drive in part by Gates Foundation-supported research at Virginia Commonwealth University, Seattle Children’s Research Institute, and The Lundquist Institute. But its promise is extraordinary: an RDS treatment that costs less to make, doesn’t require a specialist to administer, and eliminates the need for intubation.
In other words, a therapy currently limited to the most advanced hospitals could become accessible in rural clinics and community settings around the world. Even in places with top-tier care, it could make treatment gentler, faster, and easier to deliver. In the United States—where RDS still affects 24,000 newborns a year—it could reduce the risks that come with intubating babies who might weigh only two or three pounds.
It’s the kind of innovation that could help solve one of the most persistent problems in global health: delivering intensive care without an intensive care unit, and helping millions more babies survive their first, most fragile moments.
Since 1990, the mortality rate for children under five has been cut by more than half—an amazing mark of global progress. But another statistic hasn’t fallen as fast: the number of babies who die in their first month of life.
Each year, 2.3 million newborns don’t survive past their first 28 days. And the day a baby is born is the most dangerous day of their life. The single biggest cause of these deaths is prematurity. Nearly 900,000 babies a year die from complications related to being born too soon, including infection, underdeveloped organs, and RDS.
Lower cost, easier-to-deliver surfactant is one way to give newborns a fighting chance, but it’s not the only way. Around the world, simple, affordable interventions already exist to identify at-risk pregnancies earlier, prevent more preterm births, and ensure a healthy birthing experience for mothers. Not only are these tools designed to work in the hardest-to-reach places—many of them start working even before a baby takes that first breath.
One of these innovations is a new type of ultrasound that’s changing who can catch the risks of preterm birth—and where.
Around the world, two thirds of women never get an ultrasound screening during pregnancy. Traditional machines are bulky and expensive, with specialized training required to operate them and interpret their results. In places where medical resources are already stretched thin, these types of ultrasounds are rarely an option.
But now, we have ultrasound devices about the size of a phone that can be operated by a nurse or midwife—no on-site specialist required. They weigh less than a pound. They process scans instantly. Their AI interface automatically detects high-risk conditions, like a shortened cervix or signs of early labor, so patients are referred for further care. And they have built-in telehealth functions to share images with remote specialists when needed.
By finding and flagging risks early, these AI-enabled ultrasounds are giving healthcare workers more time to act. In some cases, that means transferring the mother to a higher-level facility. In others, it means providing her with antenatal steroids—an inexpensive, underused treatment that speeds up fetal lung development—and, when needed, medications that delay labor just long enough for those steroids to take effect.
Early warning is essential, but we can save even more lives by going further upstream, starting with the health of pregnant women themselves.
In many low-income countries, undernutrition isn’t an exception. It’s the norm. And the intense demands of pregnancy make nutritional deficiencies even worse—putting mothers at increased risk of complications or death in childbirth, and raising the odds of early labor, low birth weight, and developmental delays for their babies.
But there’s a surprisingly simple fix: a daily supplement called MMS, or multiple-micronutrient supplementation, developed by the United Nations. It contains 15 essential vitamins and minerals for pregnancy—like zinc to reduce the risk of early labor, folic acid to help prevent birth defects, iron and vitamin D for healthy birth weight, and iodine for brain development. For an entire pregnancy, it costs just $2.60.
If MMS became the standard prenatal supplement in every low- and middle-income country, it could save nearly half a million newborn lives each year—and prevent serious complications in 25 million births by 2040.
The innovations above focus on treating, detecting, and preventing premature birth, a huge threat to newborn survival. But one of the most powerful ways to protect babies, preterm or full-term, is by ensuring their mothers stay healthy through pregnancy and childbirth.
When a woman dies during delivery, her baby is 46 times more likely to die in that first month of life. That’s why any serious effort to tackle infant mortality must also address postpartum hemorrhage—which tragically kills 70,000 women a year and is the leading cause of maternal mortality. Fortunately, two innovations are already helping healthcare workers catch and treat it before it becomes fatal.
The first is a calibrated drape—a simple plastic sheet placed under a woman during delivery that collects blood and shows, through printed measurement lines, exactly how much she’s losing. It gives healthcare workers a fast, accurate way to spot dangerous bleeding before it becomes life-threatening. The second is a one-time, 15-minute iron infusion during pregnancy that treats severe anemia—so if a woman does hemorrhage during childbirth, she’s less likely to experience catastrophic blood loss and more likely to survive.
Neither of these tools is complicated or expensive. But in combination, they can make a life-or-death difference for mothers and the babies who depend on them.
Taken together, these innovations form a chain of survival. They help mothers stay healthy through pregnancy. They detect problems before they become emergencies. They give fragile newborns a fighting chance. And they make it possible for families to celebrate a baby’s birth rather than mourning a loss.
Some of these tools are already saving lives. Others are on the verge of doing so. But their impact will be limited unless we prioritize and fund their delivery, not just their development. The world needs to make sure these innovations don’t get stuck in labs or warehouses—so they can reach the mothers and babies who need them most.
My look back
The breakthrough that transformed the Gates Foundation
This is the story of how better data helped us cut child mortality in half.
We started the Gates Foundation 25 years ago to save and improve children’s lives. But no one can solve a problem they don’t fully understand. And back in 2000, the world’s understanding of childhood mortality was occasionally inaccurate, often imprecise, and almost always incomplete.
That’s why I believe the breakthrough that transformed our foundation in the two-and-a-half decades since wasn’t a single vaccine or treatment—it was a revolution in the world’s understanding of childhood mortality. Through advances in how researchers collect and analyze global health data, we now know much more about what kills children, where these deaths occur, and why some kids are more vulnerable than others. By putting those insights to work, we’ve been able to save lives.
The first challenge was knowing exactly what was killing children.
Reading the 1993 World Development Report opened my eyes to the scale of the problem: Around 12 million children under the age of five were dying every year, with a staggering disparity between rich and poor countries. But the available data was fragmented and inconsistent. That made it difficult to understand trends or allocate resources effectively.
So the foundation helped create the Institute for Health Metrics and Evaluation at the University of Washington, to give a permanent home to the Global Burden of Disease study—originally developed in the 1990s by researchers at Harvard University and the World Health Organization. We wanted to expand it from a static snapshot of the problem into a regularly updated tool that tracked how diseases impact people around the world. That gave us something the world never had before: a comprehensive—and current—picture of child mortality across every country.
Measuring symptom-based causes of children’s deaths was an important step. But broad disease categories like “diarrhea” or “respiratory infection” didn’t give us enough information to act on. We needed to know which specific pathogens were responsible for the most common and fatal cases. So the Gates Foundation funded two landmark studies to find out.
In 2013, the Global Enteric Multicenter Study, or GEMS, found that rotavirus was causing 20 percent of lethal diarrhea cases in kids. At the time, diarrhea was the second-leading infectious killer of children. While oral rehydration therapy had already helped bring down deaths over previous decades, GEMS helped fast-track the rollout of a more targeted tool—a new rotavirus vaccine—in the hardest-hit countries, in close partnership with Gavi, the Vaccine Alliance.
A year later, the Pneumonia Etiology Research for Child Health study, or PERCH, revealed that respiratory syncytial virus, or RSV, was a much more common cause of severe pneumonia—the leading infectious killer of kids around the world—than previously understood. (And not just in low- and middle-income countries, where 97 percent of RSV deaths occur, but in higher-income ones too, where the virus still fills pediatric hospital wards each winter.) That prompted us to expand our investments in RSV prevention, which led to the approval of the first maternal vaccines for RSV in 2023.
But understanding what causes childhood mortality wasn’t enough on its own, because deaths aren’t distributed evenly across countries—or even within them. That’s why our second challenge was to figure out where exactly children were dying.
At the time, most health data was collected at national or regional levels. That masked major differences in disease burden from one community to the next—and made it harder to target interventions effectively.
To solve this second challenge, the foundation invested in new approaches to health mapping that combined satellite imagery, GIS technology, GPS data, and local health surveys. These maps gave Ministries of Health and implementing partners unprecedented, anonymized detail about disease patterns and population distribution, down to individual neighborhoods, that transformed how and where public health resources are deployed—while still preserving the privacy of the individual children and families in these places.
In Pakistan—one of just two countries where wild polio remains endemic—advanced mapping tools have helped vaccination teams reach and protect kids in settlements that weren’t on any official maps. Across sub-Saharan Africa, better geographic data has transformed the fight against malaria by revealing that transmission often clusters in small, hyper-local pockets. Through the Malaria Atlas Project, countries like Nigeria can now track those patterns more precisely—and then get bed nets, testing, and treatment where they’ll have the greatest impact.
With better knowledge of what was killing children, and where, one more fundamental question remained: Why might one child die from a disease while another—who lives in the same place, faces the same risks, and gets the same treatment—survives? This was our third big challenge.
In theory, traditional autopsies would provide the answer. But in the places where most childhood deaths still occur, these invasive procedures are often impossible to perform—too costly, and sometimes opposed for religious, cultural, or personal reasons.
So in 2015, the foundation launched the Child Health and Mortality Prevention Surveillance network, or CHAMPS, which now operates in nine countries across Africa and South Asia. Working with in-country partners, CHAMPS pioneered a new autopsy alternative—using minimally invasive tissue sampling—that can determine causes of death quickly and accurately while respecting local customs and beliefs.
Through CHAMPS, we discovered that childhood deaths rarely have a single cause. Instead, kids often have multiple conditions at the same time, with malnutrition frequently leaving them much more vulnerable to a whole host of infections. (While it rarely shows up on death certificates, it’s an underlying cause of death in nearly half of all child mortality cases.) That finding helped solidify nutrition as a core focus of the foundation’s global health work—and the research, innovation, and product development we invest in. On the ground, we’re supporting partners as they integrate nutrition screening into routine care and train healthcare workers to manage multiple risks at once.
CHAMPS also demonstrated that inadequate prenatal care is responsible for a majority of stillbirths, newborn deaths, and maternal deaths, prompting us to further expand access to maternal health services—like prenatal vitamins and AI-enabled ultrasounds—in the communities where we work.
But the biggest takeaway from CHAMPS is also the most hopeful—and a reminder of why we started the Gates Foundation in the first place: So many childhood deaths could be prevented with existing interventions. We just need to ensure they reach the right children at the right time.
Twenty-five years in, our work on child mortality is far from complete. Still, the impact of what we have learned has been enormous
The Global Burden of Disease, GEMS, and PERCH studies helped shift global priorities by showing the world what was really killing kids—and where new vaccines and treatments could make the biggest difference. Better geospatial tools have empowered countries to pinpoint disease hotspots, find previously unmapped settlements, and distribute life-saving resources where they’re needed most. And CHAMPS is giving governments better data on why children are dying—data that’s now shaping policies, improving reporting, and guiding more effective care.
Most importantly, even as the number of children born every year has gone up, the number of overall childhood deaths has fallen by more than half—from 11.3 million in 1990 to 4.5 million in 2022. Playing a part in making that happen is the best job I’ve ever had, and the most meaningful work I’ve ever done.
At the Gates Foundation, we used to say we could cut child mortality in half again by 2040. The truth, though, is that goal feels further out of reach now—not because the science has stalled, but because support for global health has. The progress we’ve been part of was only possible because governments around the world, including here in the U.S., made long-term commitments to saving lives and followed through. That kind of leadership gave millions of children who would have died a chance at life—and made life better for millions more.
The last 25 years have shown us what’s possible. The next 25 will depend on whether the world keeps showing up for the children who need it most.
Life Line
A phone call that saves lives
m-mama uses mobile technology and community drivers to solve one of global health’s most persistent problems: Getting pregnant women to hospitals in time.
In the United States, when someone has a medical emergency, we take for granted that an ambulance will arrive. It will get to some places faster than others—a disparity driven by wealth and other factors. Still, by calling 911, we’re immediately connected to a vast fleet of emergency vehicles plugged into a system that’s designed to get people to hospitals in times of crisis.
But what about countries where ambulances aren’t readily accessible? What about places where even cars are scarce, where the nearest hospital with surgical capacity might be 100 miles away down an unpaved road, and where a family facing a medical crisis has no reliable way to get there or pay for the journey?
This is the reality for millions of pregnant women across sub-Saharan Africa.
Thanks to modern medicine, we now know how to prevent most maternal and newborn deaths. And maternal mortality has declined by 40 percent over the last two decades as a result. But hundreds of thousands of women and babies still die every year from complications during pregnancy and childbirth, because they can’t get to a place where someone can treat them in time.
In maternal health, this problem is called the “second delay.” It’s a terrible tragedy, one that the Gates Foundation has been trying to address for years.
Back in 2013, partners including Vodafone Foundation and local health organizations started tackling this problem by asking a simple question in rural Tanzania: What if you could create something like a 911 system that worked with whatever transportation was available in a community? They tested the idea in a few districts, and it worked well enough that they decided to scale it up. They called it m-mama.
m-mama works like this: When a community healthcare worker identifies an emergency—maybe it’s severe bleeding after delivery, or a premature baby who can’t breathe—they call a free hotline. A trained nurse dispatcher uses an app to figure out what kind of care is needed and where it’s available, then coordinates whatever transportation makes sense for that location (a community driver with a car where there are good roads, a motorcycle where there aren’t, a boat for island communities, even a horse for mountainous terrain.) The dispatcher stays on top of everything, tracking the journey, alerting the receiving facility, and handling payment at the end.
The numbers speak for themselves. Since 2013, m-mama has responded to more than 125,000 emergencies and saved an estimated 5,266 lives. And in regions where m-mama launched, maternal emergency transports more than doubled. That means there was a massive need that was going unmet for far too long. About 58% of the deliveries transported by m-mama end up requiring a C-section, compared to the 10-15% you would expect in the general population. These are genuinely high-risk cases that would have likely ended in tragedy without emergency transport.
What’s especially impressive about m-mama’s impact is that it hasn’t required building new hospitals or buying any expensive equipment. Instead, it makes existing health systems work better by coordinating resources that are already there—ambulances, facilities, healthcare workers—and filling gaps with options that cost a fraction of what traditional ambulances do.
And it is scaling. m-mama started as a pilot serving 750,000 people and now reaches 62 million in Tanzania. It’s gone nationwide in Lesotho. It just launched in Malawi and is scaling up in Kenya. There are plans for more countries across sub-Saharan Africa, supported in part by the Beginnings Fund—a partnership that includes our foundation, the Mohamed bin Zayed Foundation for Humanity, and other organizations working to improve maternal and newborn health across Africa.
The program is financially sustainable too. Once the program is up and running, the governments cover operating costs. m-mama has proven it can be owned and run locally, which is the only way something like this works long-term.
m-mama is a reminder that not all breakthroughs in global health are new drugs or sophisticated technology. Sometimes they’re just smart ways of getting the right care to the right person at the right time. When a mother or baby is in crisis, minutes can make the difference between life and death.
m-mama is making sure those minutes count.
The Year Ahead
Optimism with footnotes
As we start 2026, I am thinking about how the year ahead will set us up for the decades to come.
I have always been an optimist. When I founded Microsoft, I believed a digital revolution powered by great software would make the world a better place. When I started the Gates Foundation, I saw an opportunity to save and improve millions of lives because critical areas like children’s health were getting so little money.
In both cases, the results exceeded my expectations. We are far better off than when I was born 70 years ago. I believe the world will keep improving—but it is harder to see that today than it has been in a long time.
Friends and colleagues often ask me how I stay optimistic in an era with so many challenges and so much polarization. My answer is this: I am still an optimist because I see what innovation accelerated by artificial intelligence will bring. But these days, my optimism comes with footnotes.
The thing I am most upset about is the fact that the world went backwards last year on a key metric of progress: the number of deaths of children under 5 years old. Over the last 25 years, those deaths went down faster than at any other point in history. But in 2025, they went up for the first time this century, from 4.6 million in 2024 to 4.8 million in 2025—an increase driven by less support from rich countries to poor countries. This trend will continue unless we make progress in restoring aid budgets.
The next five years will be difficult as we try to get back on track and work to scale up new lifesaving tools. Yet I remain optimistic about the long-term future. As hard as last year was, I don’t believe we will slide back into the Dark Ages. I believe that, within the next decade, we will not only get the world back on track but enter a new era of unprecedented progress.
The key will be, as always, innovation. Consider this: An HIV diagnosis used to be a death sentence. Today, thanks to revolutionary treatments, a person with HIV can expect to live almost as long as someone without the virus. By the 2040s, new innovations could virtually eliminate deaths from HIV/AIDS.
Budget cuts limit how many people benefit from lifesaving tools, as we saw to devastating effect last year. But nothing can erase the fact that for decades we didn’t know how to save people from HIV, and now we do. Breakthroughs are a bell that cannot be unrung. They ensure that we will never go back to the world in 2000 where over 10 million children died from preventable causes every year—and they form the core of my optimism about where the world is headed.
But as I mentioned, there are footnotes to my optimism. Although the innovation pipeline sets us up for long-term success, the trajectory of progress hinges on how the world addresses three key questions.
1.
Will a world that is getting richer increase its generosity toward those in need?
The “golden rule” precept is more important now than ever with the record disparities in wealth. This idea of treating others as you wish to be treated does not just apply to rich countries giving aid. It must also include philanthropy from the wealthy to help those in need—both domestically and globally—which should grow rapidly in a world with a record number of billionaires and even centibillionaires.
Through the Giving Pledge, I get to work with a number of incredible philanthropists who set a great example by giving away substantial portions of their wealth in smart ways. However, more needs to be done to encourage higher levels of generosity from the rich and to show how fulfilling and impactful it can be.
Turning to aid budgets for poor countries, I am worried about one number: If funding for health decreases by 20 percent, 12 million more children could die by 2045. I know cuts won’t be reversed overnight, even though aid represented less than 1 percent of GDP even in the most generous countries. But it is critical that we restore some of the funding. The foundation’s Goalkeepers report lays out what is at risk and how the world can best spend the aid it gives.
I will spend much of my year working with partners to advocate for increased funding for the health of the world’s children. I plan to engage with a number of communities, including health care workers, religious groups, and members of diaspora communities to help make this case.
2.
Will the world prioritize scaling innovations that improve equality?
Some problems require doing far more than just letting market incentives take their course.
The first critical area is climate change. Without a large global carbon tax (which is, unfortunately, politically unachievable), market forces do not properly incentivize the creation of technologies to reduce climate-related emissions.
Yet only by replacing all emitting activities with cheaper alternatives will we stop the temperature increase. This is why I started Breakthrough Energy 10 years ago and why I will continue to put billions into innovation.
The world has made meaningful progress in the last decade, cutting projected emissions by more than 40 percent. But we still have a lot of innovation and scaling up to do in tough areas like industrial emissions and aviation. Government policies in rich countries are still critical because unless innovations reach scale, the costs won’t come down and we won’t achieve the impact we need.
If we don’t limit climate change, it will join poverty and infectious disease in causing enormous suffering, especially for the world’s poorest people. Since even in the best case the temperature will continue to go up, we also need to innovate to minimize the negative impacts.
This is called climate adaptation, and a critical example is helping farmers in poor countries with better seeds and better advice so they can grow more even in the face of climate change. Using AI, we will soon be able to provide poor farmers with better advice about weather, prices, crop diseases, and soil than even the richest farmers get today. The foundation has committed $1.4 billion to supporting farmers on the frontlines of extreme weather.
I will be investing and giving more than ever to climate work in the years ahead while also continuing to give more to children’s health, the foundation’s top priority. The need to ensure money is spent on the most important priorities was the topic of a memo I wrote in the fall.
A second critical area where the world must focus on innovation-driven equality is health care. Concerns about healthcare costs and quality are higher than ever in all countries.
In theory, people should feel optimistic about the state of health care with the incredible pipeline of innovations. For example, a recent breakthrough in diagnosing Alzheimer’s will revolutionize how we test for—and ultimately prevent—this disease, saving billions of dollars in costs. (Funding Alzheimer’s research is a particular focus for me.) There’s similar progress on obesity and cancer, as well as on problems in developing countries like malaria, TB, and malnutrition.
Despite so much progress, however, the cost and complexity of the system means very few people are satisfied with their care. I believe we can improve health care dramatically in all countries by using AI not only to accelerate the development of innovations but directly in the delivery of health care.
Like many of you, I already use AI to better understand my own health. Just imagine what will be possible as it improves and becomes available for every patient and provider. Always-available, high-quality medical advice will improve medicine by every measure.
We aren’t quite there yet—developers still have work to do on reliability and how we connect the AI to doctors and nurses so they are empowered to check and override the system. But I’m optimistic we will soon begin to scale access globally. I am following this work so the Gates Foundation and partners can make sure this capability is available in the countries that need it most—where there aren’t enough medical personnel—at the same time it is available elsewhere. We are already working on pilots and making sure that even relatively uncommon African languages are fully supported.
Governments will have to play a central role in leading the implementation of AI into their health systems. This is another case where the market alone won’t and can’t provide the solution.
A third and final area I will mention briefly is education. AI gives us a chance for the kind of personalized learning to keep students motivated that we have dreamed of in the past. This is now a focus of the Gates Foundation’s spending on education, and I am hopeful it will be empowering to both teachers and students. I’ve seen this firsthand in New Jersey, and it will be game changing as we scale it for the world.
All three of these areas—climate, health, and education—can improve rapidly with the right government focus. This year I will spend a lot of time meeting with pioneers all over the world to see which countries are doing the best work so we can spread best practices.
3.
Will we minimize negative disruptions caused by AI as it accelerates?
Of all the things humans have ever created, AI will change society the most. It will help solve many of our current problems while also bringing new challenges very different from past innovations.
When people in the AI space predict that AGI or fully humanoid robots will come soon and then those deadlines are missed, it creates the impression that these things will never happen. However, there is no upper limit on how intelligent AIs will get or on how good robots will get, and I believe the advances will not plateau before exceeding human levels.
The two big challenges in the next decade are use of AI by bad actors and disruption to the job market. Both are real risks that we need to do a better job managing. We’ll need to be deliberate about how this technology is developed, governed, and deployed.
In 2015, I gave a TED talk warning that the world was not ready to handle a pandemic. If we had prepared properly for the Covid pandemic, the amount of human suffering would have been dramatically less. Today, an even greater risk than a naturally caused pandemic is that a non-government group will use open source AI tools to design a bioterrorism weapon.
The second challenge is job market disruption. AI capabilities will allow us to make far more goods and services with less labor. In a mathematical sense, we should be able to allocate these new capabilities in ways that benefit everyone. As AI delivers on its potential, we could reduce the work week or even decide there are some areas we don’t want to use AI in.
The effects of this disruption are hard to model. Sometimes, when a game-changing technology improves rapidly, it drives more demand at lower cost and, by making the world richer, increases demand in other areas. For example, AI makes software developers at least twice as efficient, which makes coding cheaper while also creating demand elasticity for code. (Computing is a good historical example where lower costs actually caused the overall market to grow.)
Even with this complexity, the rate of improvement is already starting to be enough to disrupt job demand in areas like software development. Other areas like warehouse work or phone support are not quite there yet, but once the AIs become more capable, the job disruption will be more immediate.
We’re already starting to see the impact of AI on the job market, and I think this impact will grow over the next five years. Even if the transition takes longer than I expect, we should use 2026 to prepare ourselves for these changes—including which policies will best help spread the wealth and deal with the important role jobs play in our society. Different political parties will likely suggest different approaches.
By including these footnotes, particularly the last one, some readers may find my continued optimism even more surprising. But as we start 2026, I remain optimistic about the days ahead because of two core human capabilities.
The first is our ability to anticipate problems and prepare for them, and therefore ensure that our new discoveries make all of us better off. The second is our capacity to care about each other. Throughout history, you can always find stories of people tending not just to themselves or their clan or their country but to the greater good.
Those two qualities—foresight and care—are what give me hope as the year begins. As long as we keep exercising those abilities, I believe the years ahead can be ones of real progress.
The big chill
Can this cooler save kids from dying?
These innovations are helping deliver vaccines to the most remote places on earth.
Two of the things I love most about my job are getting to see amazing innovations and talk to remarkable people. During a recent trip to New York, I got to check both boxes. I met a woman named Papa Blandine Mbwey who is using a revolutionary new invention to help more kids get vaccinated.
Blandine has worked as a vaccinator in a remote part of the Democratic Republic of the Congo for over a decade. Most days, she travels on foot to villages all over her region so she can vaccinate kids who live too far from a health clinic to make the trip themselves.
Blandine’s job is complicated by a simple fact: vaccines must be kept between 2 and 8° C. If they get too warm, they spoil. If they get too cold, the water in them freezes, and they can stop working. Vaccines must stay within this temperature range through each step of what’s called the “cold chain.”
By the time Blandine reaches the children, the vaccines she’s carrying have traveled nearly 5,100 miles. They could have spoiled at any point during that journey, but vaccines are particularly at risk during the last two stops.
First there’s the health clinics where vaccinators like Blandine usually pick up their supply of vaccines. Many of these clinics are in areas with frequent power outages or no electrical grid at all, which means the refrigerators can’t always keep the vaccines cold.
But even if the vaccines survive the clinic, they still need to make it to the children. Most vaccinators carry them in ice-lined coolers. If you’ve used a cooler to keep your drinks cold at a picnic, you know the big problem with ice: it starts melting as soon as you take it out of the freezer. This means that some of the kids never get vaccinated, because coolers can’t keep vaccines cold long enough to reach them.
Several years ago, I asked a group of inventors called Global Good that I support to take on the cold chain problem. They came up with two remarkable innovations that are changing the game for vaccinators like Blandine.
The first is the MetaFridge. Although it looks like a regular refrigerator, MetaFridge has a hidden superpower: it keeps vaccines cold without power for at least five days. The electrical components are designed to keep working through power surges and brown-outs. During extended outages, an easy-to-read screen tells you how much longer it can stay cool without power so health workers know when to run a generator or move vaccines elsewhere. And if the fridge stops working properly, it transmits data remotely to a service team so they can fix it before vaccines are at risk of spoiling.
The other innovation Global Good invented is the Indigo cooler, which is the device you see Blandine using in the video above. It keeps vaccines at the right temperature for at least five days with no ice, no batteries, and no power required during cooling.
It sounds counterintuitive, but the Indigo needs heat before you can use it. When exposed to a heat source, water inside its walls evaporates and moves into a separate compartment. It can then sit on a shelf for months after heating, ready for use.
When it’s finally time to head out to the children, you open a valve, and the water starts moving back where it started. Because the pressure inside the Indigo has been lowered to the point where water evaporates at 5° C, the water particles take heat with them (the way sweating lowers your body temperature) and cool the storage area down to the perfect temperature for vaccine storage.
Both inventions are already making an impact in the field. A Chinese manufacturer started selling the MetaFridge last year, and a new solar-powered version will hit the market soon. One of the biggest surprises so far is just how much we’ve learned from its remote data monitoring capabilities. We knew the electrical grids in sub-Saharan Africa were unreliable, but we now know exactly how much the power fluctuates. This information will be helpful moving forward for health providers and anyone designing a product meant to work in these areas.
The Indigo is in the field trial phase. It’s still early, but the data suggests that the Indigo is allowing vaccinators to reach four times as many places as they could with the old ice-based coolers. That’s a big deal, and I’m excited to learn more.
Keeping vaccines cold when you’re delivering them to the most remote places on earth is a tough problem—and these devices show how innovation can help solve tough problems. I hope MetaFridge and Indigo inspire other inventors to find creative solutions.

Incredible innovation
A promising new vaccine candidate to protect children from their #1 killer
More than 670,000 children die from pneumonia every year. A new vaccine could save many lives.
The leading cause of death among children under age 5 often begins with little more than a cough.
Followed by chills, fever, and nausea.
And then as the child’s lungs get flooded with fluid, each breath becomes a desperate gasp for air.
What I’m describing is known as pneumonia, an acute respiratory condition that kills over 670,000 children every year.
And here’s a sentence I find difficult to write: Nearly all those deaths could have been prevented.
Access to vaccines, diagnostic tools, and treatments can protect children from deadly pneumonia. But these solutions are often not available or accessible in many low- and middle-income countries, where children are at greatest risk.
Even as child deaths have declined by nearly 50 percent over the past two decades, deaths from pneumonia have remained stubbornly high.
That’s why our foundation is focused on improving access to and development of vaccines that can prevent it.
One of the most exciting areas of progress is the development of a powerful new vaccine designed to protect children against pneumococcal bacteria, which is the leading cause of deadly pneumonia. Of the 670,000 children who die from pneumonia ever year, pneumococcal pneumonia is responsible for killing 400,000 of them.
What makes this new vaccine unique is that it is designed to protect against 25 different types of pneumococcal bacteria, more than any other available vaccine. Existing pneumococcal vaccines protect against about half as many types of pneumococcal pneumonia. To address the remaining deaths from pneumococcal pneumonia, vaccines that offer broader protection like this new vaccine will be needed.
The vaccine, called IVT-PCV25, is being developed by Inventprise, a small biotechnology company based outside Seattle. I recently took a tour of their new vaccine manufacturing plant and got an update on their progress.
It was amazing to see the innovations underway at Inventprise. Making a vaccine that is effectively 25 vaccines in one is an extremely complex challenge. Past efforts to add more strains of pneumococcal bacteria to vaccines using conventional technologies have resulted in vaccines that didn’t produce a strong enough immune response. Inventprise intends to overcome this obstacle with its proprietary vaccine technology that is designed to guard against many types of pneumococcal bacteria without any decline in protection.
Inventprise’s new factory, supported by a grant from our foundation, is a highly automated facility that marks an important step forward in Inventprise’s development of the vaccine. Clinical trials of the vaccine are expected to begin later this year.

Pioneering research
She helped change vaccines forever
Long before most of us heard of mRNA vaccines, this hero saw their potential to save lives.
For most people, the highly effective mRNA COVID vaccines made by Moderna and Pfizer-BioNTech seemed to come out of the blue. But these new vaccines, which were essential to end this pandemic and will likely play a critical role in preventing future pandemics, are the product of decades of painstaking work by researchers.
One of those researchers is Dr. Katalin Karikó, a Hungarian biochemist who long ago saw the potential of mRNA to save lives when few others did.
The daughter of a small-town butcher in Hungary, Karikó knew from a young age that she wanted to become a scientist. She was drawn to biochemistry and developed a particular fascination with messenger RNA, or mRNA, molecules that (among other things) direct the creation of proteins in your body.
Messenger RNA functions as a kind of middleman—it carries the directions for making proteins from your DNA to the factories in your cells where the proteins will be assembled. It’s a bit like the waiter in a restaurant who writes down your order and takes it to the kitchen, where the cooks will make your meal.
In the 1980s, while working on her PhD in her native Hungary, Karikó became convinced that tiny strands of mRNA could be injected into cells to send instructions to the body to make its own medicines. She was interested in developing mRNA treatments for stroke, cancer, and other diseases.
Although vaccines were not the focus of Karikó’s work, other researchers saw that it would be possible to use mRNA to make those as well—for flu, coronaviruses, and maybe even various forms of cancer.
Using mRNA to make vaccines would be a major departure from the way most vaccines work. Many conventional vaccines operate by injecting a weakened or dead form of the virus you’re trying to stop. Your immune system sees the new shapes on the virus, kicks into gear, and builds up immunity. While conventional vaccines have been very effective, it takes years of lab work and clinical studies to make sure that they are safe and will produce a good immune response.
The idea behind mRNA vaccines was quite clever. Since mRNA takes the orders for proteins from the DNA and delivers them to the cooks in your cells’ kitchen, what if we could change those orders in a very targeted way? By teaching your cells to make shapes that match shapes on the actual virus, the vaccine would trigger your immune system without having to introduce the virus itself.
If they could be made, mRNA vaccines would be a huge advance over conventional vaccines. Once you had mapped out all the proteins that make up the virus you wanted to target, you’d identify the one that you want antibodies to grab. Then you’d study the virus’s genetic code to find the instructions for making that protein, and you’d put that code into the vaccine using mRNA. If, later, you wanted to attack a different protein, you’d just change the mRNA. This design process would take at most a few weeks. You would ask the waiter for fries instead of a side salad, and your immune system would do the rest.
There was just one problem: It was only a theory. No one had ever actually made an mRNA vaccine. What’s more, most people in the field thought it was crazy to even try, not least because mRNA is inherently unstable and prone to degrading quickly. Also, cells have evolved to avoid being hijacked by foreign mRNA, and there would need to be a way of getting around this defense system.
Karikó’s interest in mRNA eventually brought her to the U.S. And in 1993, while doing research at the University of Pennsylvania, Karikó and her boss managed a feat that told them they were on to something: They got a human cell to produce a tiny amount of new proteins using a modified version of mRNA that had been altered so it could get past the cell’s defense system. This was a breakthrough, because it meant that if they could expand the production dramatically, they would be able to make a cancer treatment using mRNA.
Stories of medical discoveries often don’t travel in straight line from breakthrough to lifesaving impact. And Karikó’s story is no different. Karikó’s work lost momentum when her boss left academia for a biotech firm. She no longer had a lab or financial support for her work; although she applied for grant after grant, every application was rejected. In 1995, she had a cancer scare, she was taken off the tenure track at work, and her husband was stuck in Hungary because of a problem with his visa. But Karikó was undeterred.
Then in 1997, she began working with Drew Weissman, a new colleague who came to the University of Pennsylvania with a promising background: He had done a fellowship at NIH under the supervision of Tony Fauci, and he was interested in using Karikó’s work on mRNA to develop vaccines.
Together Karikó and Weissman kept pursuing the idea of working with mRNA that had been engineered in a lab. But they still had to get more mRNA past the cell’s defense systems, a problem that other scientists helped solve. In 1999, a cancer researcher named Pieter Cullis and his colleagues proposed that lipids—basically, tiny bits of fat—could be used to encase and protect a more delicate molecule, such as mRNA. Six years later, working with Cullis, biochemist Ian MacLachlan did it for the first time. The lipid nanoparticles he developed paved the way for the first mRNA vaccines.
As late as 2010, hardly anyone in the federal government or private industry was interested in trying to make vaccines using mRNA. Major pharmaceutical companies had tried and failed, and some scientists felt that mRNA would never trigger enough of a response in the body. But an official at DARPA, the little-known research program for the U.S. military, saw enough promise in the technology that he started funding mRNA vaccines for infectious diseases.
As pioneering as this work was, it didn’t lead immediately to new vaccines. Accomplishing that would be the task of companies dedicated to translating the breakthrough into a product that could be approved and sold; the U.S.-based Moderna and Germany-based CureVac and BioNTech were founded to do just that.
In 2014, Karikó joined BioNTech, which was working on an mRNA vaccine for cancer. Early efforts didn’t work, although a test of a rabies vaccine showed promise. Still, Karikó and her BioNTech colleagues persevered, as did scientists at Moderna. When COVID hit, they immediately set out to make a vaccine for the new virus. It was a good bet.
The notion that mapping a virus’s genome would allow you to create an mRNA vaccine in a matter of weeks proved to be exactly right. In March 2020, just six weeks after scientists sequenced the COVID virus’s genome, Moderna announced that it had identified an mRNA-based candidate and begun making it for clinical trials. On December 31, the mRNA vaccine made by BioNTech in partnership with Pfizer was approved for emergency use by the World Health Organization. When Karikó received the first dose of the vaccine she had done so much to create—a few days before it was officially approved—she wept.
For all her amazing foresight, I doubt even Dr. Karikó imagined that mRNA vaccines would one day play an essential role in ending a pandemic – and giving us a tool to prevent the next one. And to me, that’s the important lesson of her story: It’s impossible to predict exactly how breakthroughs will shape the future. That’s why it’s critical, if the science makes sense, that we should be willing to bet on crazy sounding ideas and the researchers like Dr. Kariko willing to fight tooth and nail to pursue them. They just might change the world.

Just the facts
Health aid saves lives. Don’t cut it.
Here’s the proof I’m showing Congress.
I’ve been working in global health for 25 years—that’s as long as I was the CEO of Microsoft. At this point, I know as much about improving health in poor countries as I do about software.
I’ve spent a quarter-century building teams of experts at the Gates Foundation and visiting low-income countries to see the work. I’ve funded studies about the effectiveness of health aid and pored over the results. I’ve met people who were on the brink of dying of AIDS until American-funded medicines brought them back. And I’ve met heroic health workers and government leaders who made the best possible use of this aid: They saved lives.
The more I’ve learned, the more committed I’ve become. I believe so strongly in the value of global health that I’m dedicating the rest of my life to it, as well as most of the $200 billion the foundation will give away over the next 20 years.
People in global health argue about a lot of things, but here’s one thing everyone agrees on: Health aid saves lives. It has helped cut the number of children who die each year by more than half since 2000. The number used to be more than 9 million a year; now it’s fewer than 5 million. That’s incontrovertible.
So when the United States and other governments suddenly cut their aid budgets the way they've been doing, I know for a fact that more children will die. We’re already seeing the tragic impact of reductions in aid, and we know the number of deaths will continue to rise.
A study in the Lancet looked at the cumulative impact of reductions in American aid. It found that, by 2040, 8 million more children will die before their fifth birthday. To give some context for 8 million: That's how many children live in California, Texas, Florida, New York, Pennsylvania, and Ohio combined.
I’ve submitted written testimony on this topic, which you can read below, for the Senate Appropriations Committee hearing occurring later today. In it, I discuss what’s already happened and what needs to happen next.
Testimony to the United States Senate Committee on Appropriations
June 25, 2025
Over the past 25 years—the same span of time I spent leading Microsoft—I have immersed myself in global health: building knowledge, deepening expertise, and working to save lives from deadly diseases and preventable causes. During that time, I have built teams of world-class scientists and public health experts at the Gates Foundation, studied health systems across continents, and worked in close partnership with national and local leaders to strengthen the delivery of lifesaving care. I have visited hundreds of clinics, listened to frontline health workers, and spoken with people who rely on these programs. Earlier this month, I traveled to Ethiopia and Nigeria, where I witnessed firsthand the impact that recent disruptions to U.S. global health funding are having on lives and communities.
Global health aid saves lives. And when that aid is withdrawn—abruptly and without a plan—lives are lost.
Yet, in recent months, some have questioned whether the foreign assistance pause has caused harm. Concerns about the human impact of these disruptions have been dismissed as overstated. Some people have even claimed that no one is dying as a result.
I wish that were true. But it is not.
It is important to note that while this hearing is about the Trump Administration’s $9 billion recission package, what is really at stake is tens of billions of dollars in critical aid and health research that has been frozen by DOGE with complete disregard for the Congress and its Constitutional power of the purse.
In the early weeks of implementing the foreign aid freeze, DOGE directives resulted in the dismissal of nearly all United States Agency for International Development (USAID) staff and many personnel at the Centers for Disease Control and Prevention (CDC). Some funding was later restored to allow for the continuation of what has been categorized as "lifesaving" programs. However, to date that designation has been applied narrowly and with limited transparency, in an inconsistent manner, often prioritizing emergency interventions when a patient is already in critical condition over essential preventative or supportive care.
For example, providing a child with a preventive antimalarial treatment, ensuring access to nutrition so that HIV/AIDS medications can be properly administered, testing pregnant women for HIV to see if they are eligible for treatment to prevent transmission to their children or identifying and treating tuberculosis cases early have not consistently qualified for exemption. As a result, many of the programs delivering these services have been suspended, delayed, or scaled back.
Recent reporting from the New York Times has shed light on the devastating human cost of the abrupt aid cuts. One especially tragic example is Peter Donde, a 10-year-old orphan in South Sudan, born with HIV, who died in February after losing his access to life-saving medication when USAID operations were suspended. His story is one of many.
During my recent visit to Nigeria, I met with leaders from local nonprofit organizations previously funded by the United States. One group shared the remarkable progress they had made in tuberculosis detection and treatment. In just a few years, case identification increased from 25 percent to 80 percent, a critical step toward breaking transmission and reducing the overall disease burden. That progress has now stalled. The grants that enabled this work were tied to USAID staff who have been dismissed, and with their departure, the funding ended, and the work stopped.
The broader effects of these sudden shifts are difficult to overstate. For example, funding for polio eradication has been preserved in the State Department budget but cut from the CDC—even though the two agencies collaborate closely on the program. This type of fragmented decision-making has left implementing organizations uncertain about staffing and operations. Many no longer feel confident that promised U.S. funds will materialize, even when awards have been announced. In some cases, staff continue to work without pay. Some organizations are approaching insolvency.
Meanwhile, in warehouses across the globe, food aid and medical supplies sourced from American producers are sitting idle—spoiling or approaching expiration—because the systems that once distributed them have been disrupted. Clinics are closing. Health workers are being laid off. HIV/AIDS patients are missing critical doses of medication. Malaria prevention campaigns, including bed net distributions and indoor spraying, have been delayed or canceled, leaving hundreds of millions of people unprotected at the peak of transmission season.
Efforts to track data that would illustrate the severity of this worsening crisis have also been severely compromised. Many of the people responsible for collecting and reporting health information—health workers, statisticians, and program managers—have been laid off or placed on leave. The systems that once monitored health outcomes are shutting down, and the offices where that data was once analyzed now sit empty. As a result, the true scope of the harm is becoming harder to measure, just as the need for information is most urgent.
The situation we face is not about political ideology, and it is not a debate over fiscal responsibility. U.S. government spending on global health accounts for just 0.2 percent of the federal budget. Shutting down USAID did nothing to reduce the deficit. In fact, the deficit has grown in the months since.
Furthermore, many of the allegations regarding waste, fraud, and abuse have proven to be unsubstantiated. For example, the widely circulated claim that USAID sent millions of dollars’ worth of condoms to the Gaza Strip is inaccurate. In fact, the Wall Street Journal reported that the program allocated approximately $27,000 for condoms as part of an HIV transmission prevention initiative—not in the Middle East, but in Gaza Province, Mozambique.
What we are witnessing because of the rapid dismantling of America’s global health infrastructure is a preventable, human-caused humanitarian crisis—one that is growing more severe by the day. DOGE made a deadly mistake by cutting health aid and laying off so many people. But it is not too late to undo some of the damage.
A Record of Progress—and What is at Risk
Since 2000, child mortality worldwide has been cut in half. Deaths from HIV/AIDS, tuberculosis, and malaria have declined significantly. And we are on the verge of eradicating only the second human disease in history: polio. These are not abstract statistics; they represent tens of millions of lives saved. None of this progress would have been possible without consistent, bipartisan U.S. leadership and investment.
Over the past several decades, the United States has built one of its most strategic global assets: a respected and robust public health presence. This leadership is not just a humanitarian achievement—it is a core pillar of American soft power and security. For example, a Stanford study analyzing 258 global surveys across 45 countries found that U.S. health aid is strongly linked to improved public opinion of the United States. In countries and years where U.S. health aid was highest, the probability of people having a very favorable view of the United States was 19 percentage points higher. Other forms of aid—like military or governance—did not have the same effect. Another example is the 2014 Ebola outbreak in West Africa. The rapid deployment of U.S. scientists, health workers, and CDC teams helped contain the virus before it could spread globally. Their presence allowed the U.S. to help shape the response strategy, speed up containment, and prevent a wider outbreak. Many African countries are facing the dual burden of rising debt and pressing health needs, forcing painful choices between repaying creditors, and protecting their citizens. Helping them navigate this challenge is not just the right thing to do—it is a strategic imperative. If the United States retreats, others will fill the gap, and not all of them will bring our values, our priorities, or our interests to the table. Preserving American global influence will require restoring the staff, systems, and resources that underpin it—before the damage becomes irreversible.
I understand the fiscal pressures facing Congress. I recognize the need to prioritize spending and to hold programs accountable for results. I also share the Trump Administration’s commitment to promoting efficiency and encouraging country-led solutions. But I believe those goals can—and must—be pursued while still protecting the programs that deliver the highest return on investment and the greatest impact on human lives.
The United States’ support for Gavi, the Vaccine Alliance; the Global Fund to Fight AIDS, Tuberculosis, and Malaria; the President’s Emergency Plan for AIDS Relief (PEPFAR); and the Global Polio Eradication Initiative (GPEI) represent some of the smartest, most effective investments our country has ever made. These initiatives are proven, strategically aligned with American interests, and cost-effective on a scale few other government programs can match.
Together, Gavi and the Global Fund have helped save more than 82 million lives. Gavi has helped halve childhood deaths in the world’s poorest countries and returns an estimated $54 for every $1 invested. The Global Fund has contributed to a 61% reduction in deaths from HIV/AIDS, TB, and malaria. PEPFAR has saved over 26 million lives and helped millions of children be born HIV-free. GPEI has brought us closer than ever to the eradication of polio. Pulling back now would not only jeopardize these historic gains—it would invite a resurgence of preventable disease, deepen global instability, and undermine decades of bipartisan American leadership.
This is not a forever funding stream for the U.S. Government. These programs set out clear pathways for countries to “graduate” from aid, which many have already done. For example, nineteen countries, including Viet Nam and Indonesia, have successfully graduated from Gavi support and now fully finance their own immunization programs. Others—from Bangladesh to Cote d'Ivoire—are on track to do the same. This is how U.S. development policy should work: catalytic, cost effective, and designed to help countries become self-reliant and drive their own progress. I agree that aid funding should have an end date, but not overnight. The most effective path to that end date is innovation. By investing in the development and delivery of new medical tools and treatments, we can drive down the cost of care, and in some cases, make diseases that were once a death sentence treatable, or even curable. Advances in therapies for chronic conditions like sickle cell disease, HIV, or certain types of cancers could transform lives and health systems. American innovation offers a sustainable exit strategy—one that reduces long-term costs, allows the United States to responsibly step back, and builds lasting trust and good will that far exceed the original investment.
Over the past 25 years, the Gates Foundation has invested nearly $16 billion in global health partnerships like Gavi, the Global Fund, and GPEI. We will continue to invest, through innovation, research, and close coordination with partners. But no private institution—or coalition of them—can replace the scale, reach, or authority of the U.S. government in delivering lifesaving impact at the global level.
The decisions made in the coming weeks will shape not only the lives saved in the near term—but the legacy of American leadership for generations to come.
Download a PDF of the testimony with appendices that include reflections from Gates Foundation staff in Africa on the impact of the U.S. aid cuts; analytical projections from respected organizations; and a selection of first-hand reporting from reputable news organizations and journalists.

No laughing matter
A gut-wrenching problem we can solve
Diarrhea used to be one of the biggest killers of kids—but now it’s one of the greatest global health success stories.
In 1997, I came across a New York Times column by Nick Kristof that stopped me in my tracks. The headline was “For Third World, Water Is Still a Deadly Drink,” and it included a statistic I almost didn’t believe: Diarrhea was killing 3.1 million people every year—most of them kids under the age of five.
I didn’t know much about the problem back then, except that it seemed so solvable. After all, in rich countries it felt like it already had been. My oldest daughter was a toddler at the time, and we never worried that an upset stomach would kill her. None of the other parents I knew worried about that either.
But in much of the world, kids without clean drinking water or basic sanitation were constantly being exposed to rotavirus, cholera, shigella, typhoid, and more—dangerous pathogens that spread easily when toilets are scarce and water is contaminated.
Nick’s column ended up changing my life. I sent it to my dad with a note: “Maybe we can do something about this.” He agreed. And after he traveled to Bangladesh to see the problem firsthand, we made a $40 million investment in vaccine research for diarrheal diseases. That grant helped shape what would become the Gates Foundation—and kickstarted decades of progress that’s now saved millions of lives.
Within a few years, I stepped away from Microsoft to focus on this work full-time. Once you’ve seen what’s possible in global health, it’s hard to do anything else.
When we first got involved, diarrhea was one of the biggest killers of kids worldwide. But over the past two and a half decades, these deaths have dropped by more than 70 percent.
The biggest breakthrough came from making vaccines for rotavirus, the leading cause of severe diarrhea and death in kids, affordable and accessible. When the vaccines first debuted in the early 2000s, they were priced at around $200 per dose—which meant they were completely out of reach for most families in most of the world. So the foundation partnered with vaccine manufacturers in India like Bharat Biotech and Serum Institute to develop high-quality, low-cost alternatives. Today, rotavirus protection costs about a dollar.
But getting the vaccines developed was only half the challenge. The other half was getting them to the kids who needed them most.
That’s where Gavi came in. The organization was set up a few years earlier to help low-income countries pay for lifesaving vaccines that had existed for decades but weren’t reaching the world’s poorest. But they were well-positioned to do the same with a new vaccine, and they did—purchasing the rotavirus vaccine for millions of children and supporting countries as they added it to their routine immunization programs. USAID played a huge role in this work, too, by helping local governments train community health workers and strengthen their vaccine delivery systems. Meanwhile, public health campaigns promoted treatments like oral rehydration salts and zinc supplements that can save a sick child's life for pennies. (Think of it as the medical-grade equivalent of Pedialyte.)
As all this was happening, countries quietly made enormous progress on clean water and sanitation too. Since 1990, 2.6 billion people around the world have gained access to safe drinking water—and the number of people who now have basic sanitation similarly has skyrocketed. These improvements help break a cycle where kids get sick, recover, and then get reinfected a few weeks later.
Despite the incredible progress, around 340,000 kids under five are still dying from diarrhea each year.
Part of the problem is that many kids still don't get vaccinated. Some live in places where health systems are weak or vaccines are hard to transport and store. Others are caught in conflict zones that make it dangerous for health workers to reach them.
And new challenges make the fight against diarrheal diseases even harder than it was 25 years ago. Shigella—one of the nastiest bacterial causes of diarrhea—is becoming more and more resistant to antibiotics, and we still don't have a vaccine. Climate change is making cholera and typhoid outbreaks more frequent, as floods contaminate water supplies and droughts force people to drink from unclean, unsafe sources.
For malnourished kids, everything is harder: They're more vulnerable to diarrheal diseases in the first place, and their damaged digestive tracts don't respond as well to oral vaccines or treatments. For families barely scraping by, diarrhea is both a medical crisis and an economic disaster. Parents miss work to care for sick kids. Kids miss school. Expenses pile up. It's one of the ways that disease keeps families trapped in poverty—and one of the reasons that a country’s public health is key to its development.
The encouraging news is that there’s a promising pipeline of innovations that builds on what we already know and could save even more lives.
At the foundation, we’re supporting scientists who are working on a vaccine for Shigella, which has become the leading bacterial cause of childhood diarrhea. We’re also funding efforts to combine different vaccines into a single shot, which would lower costs and make things easier for health workers and kids alike.
New delivery methods could make a big difference too. One example: vaccine patches for measles that don’t require needles, refrigeration, or trained staff to administer them. Just peel, stick, and protect.
We've already learned a lot about how chronic infections damage kids’ guts and make it harder for them to absorb nutrients or respond to vaccines. Now, scientists are researching how to repair that damage, which could help the sickest kids recover faster.
And outside the lab, environmental monitoring tools are being developed to detect early signs of outbreaks—by regularly testing sewage for typhoid, for instance. It’s like having an early warning system for epidemics.
We can’t afford to look away now
I’ve been talking about diarrhea for 25 years, even though it makes some people squeamish, because it’s a microcosm of global health. It’s proof that the world can come together to solve big problems. When we refuse to accept that some children won’t make it to their fifth birthday, we can save millions of lives.
But it’s also a warning of what can happen when we look away.
Right now, global health funding is being slashed around the world. According to one estimate, cuts to aid from the U.S. have already led to almost 60,000 additional childhood deaths from diarrhea. If nothing changes, by next January that number could rise to 126,000. These are projections, not final counts, but the reality is undeniable: When lifesaving programs are eliminated, kids pay the price.
Diarrhea is one of the most solvable problems in global health. We’ve come a long way, but we’re not done yet.
Lung Story Short
A book about tuberculosis, and everything else
Here’s how John Green turned a forgotten disease into a #1 NYT bestseller.
What do Adirondack chairs, Stetson hats, the city of Pasadena, and World War I have in common? According to John Green, all of their origin stories include tuberculosis.
In his new book, John argues that it’s impossible to separate the deadliest disease in history from, well, the rest of history. Adirondack chairs were designed by a man who vacationed in the New York mountains—a popular spot for TB patients seeking fresh air—and soon became staples of sanatorium porches across the country. John B. Stetson, who had TB himself, traveled west for dry mountain air and invented the cowboy hat to protect from sun, wind, and rain. Pasadena became a hub for TB treatment in the late 1800s, and TB “tourism” was a major driver of the city’s early economy, real estate, and identity. And the teenage assassins who killed Archduke Franz Ferdinand, which kicked off World War I? They were more willing to die for their cause since they were already dying of TB.
No wonder John calls this book Everything Is Tuberculosis. In so many ways, TB shaped the world we live in. Even though the disease is now both rare and treatable in rich countries, in poorer places it’s on the rise and still a death sentence for so many.
John is best known as the author of some of the best young adult novels of all time (at least according to my daughter Phoebe, whose encouragement led me to read The Fault in Our Stars and Turtles All the Way Down). So a lot of people were surprised when he announced that his next book would be about global health—about a disease most people in the western world think of in the past tense.
I wasn’t. After all, I first met John over a decade ago, when he joined me on a Gates Foundation trip to Ethiopia. While traveling, we talked about a lot of the big questions John wrestles with in Everything Is Tuberculosis—like why the place a person is born influences their odds of surviving childhood (or childbirth), and what people like us can do to increase those odds.
Since then, John has been an invaluable partner to the foundation, bringing his curiosity and clarity to our events and helping raise awareness of our work. But he’s also become a powerful advocate for global health in his own right. I don’t know anyone else who could turn a book about tuberculosis into a number one New York Times bestseller.
Everything Is Tuberculosis is poignant, smart, and at times infuriating. At its heart is the story of a boy named Henry, whom John met at a TB clinic in Sierra Leone. Henry was just six when he started showing classic signs of the disease: fatigue, weight loss, night sweats. But the first tests he got came back negative, so he was sent home from the hospital. By the time he was eventually diagnosed, Henry was already very sick.
He began treatment with the standard cocktail of decades-old antibiotics. It’s a brutal regimen that involves months of pills, painful injections, constant side effects—and, once the infection starts to subside, aching hunger from having an appetite again. The drugs only work if they’re taken consistently and on schedule, but that’s often unrealistic for patients. In much of the world, TB treatment means walking miles to a clinic, missing work or school, going into debt, and facing social stigma and isolation. Even though Henry’s mom did everything she could to support him, there were interruptions to his treatment, and eventually the TB became drug-resistant.
In the end, Henry got lucky. Even as he got sicker and ran out of options, his doctors wouldn’t give up on him. They fought to get him access to a personalized drug regimen—something that’s rarely available to kids in poor countries. That care ended up saving his life, and today Henry is thriving. After years stuck in the hospital, he’s caught up academically and now in university (and even has a YouTube channel where he shares his journey and advocates for other TB patients). John doesn’t romanticize Henry’s story as some kind of miracle. Instead, he uses it as proof: that TB is curable, that good care works, and that the real question isn’t whether we can save lives—but whether we’re willing to make that care available to everyone.
Even though John finished writing the book last year, he nails the urgency of this moment. He shows how a disease that most people in rich countries have forgotten is still killing over a million people a year, and how easily that number could keep climbing. That’s especially true now, as foreign aid cuts disrupt TB care across the globe. Henry might not be alive today if it weren’t for organizations like Partners In Health—funded in part by U.S. health aid—which fought to get him the treatment he needed. These aid cuts will be devastating for kids like him, who may lose access to treatment altogether. They’ll also lead to more interrupted care, more cases, more drug resistance, and more strains of an infectious disease that will be harder and more expensive for the entire world to contain.
This is a book about the central challenge of global health today: the reality that, in John’s words, “the cure is where the disease is not, and the disease is where the cure is not.”
A book about tuberculosis could be pretty boring, but John makes it super compelling by weaving in TB’s long and strange history, from the myth that it only afflicted white people, to the theory that it inspired creative genius, to its influence on Victorian beauty standards. (I didn’t know about those last two… or the Stetson hats.) If you’re familiar with John’s work, this approach won’t surprise you. He has a gift for getting people to care about things they might not think are “for me,” whether that’s poetry, astrophysics, or infectious disease.
John ends Everything Is Tuberculosis with a stirring call to action. He makes the case that saving lives from TB isn’t really a scientific challenge anymore; it’s a moral one. I largely agree. But I also think there are more reasons for hope than the book lets on.
While John is clear-eyed about the failures of the past and present—the slow pace of progress, the sky-high prices of new TB drugs, the inequality that determines who gets treated and who doesn’t—he doesn’t spend much time on what comes next. Having spent the last two-and-a-half decades investing in the science behind TB care through the Gates Foundation, I’ve seen a different side of the story. I know what’s in the pipeline, and I know what’s possible.
Today, we’re closer than ever to breakthroughs that could change everything about how we treat and even prevent TB: shorter drug regimens, better diagnostics, and even vaccines. These tools will only make a difference if they’re affordable enough to reach kids like Henry. But I think it’s important to recognize that the companies often criticized for pricing are also, ironically, the only ones that have been willing to invest in TB at all. We need to keep working with them as partners, keep the innovation coming, and keep bringing costs down.
If we do, we can make Henry’s story of survival the norm, not the exception—and make tuberculosis a disease of the past, not the future.
Such great heights
This heroic nurse climbs 1000-foot ladders to save lives
Agnes Nambozo goes to extraordinary lengths to vaccinate children in Uganda.
How do you get to work? Some people roll out of bed and move 10 feet to their desk. Others walk to the office or take public transit. I usually drive a car.
No matter how you get there, I guarantee that your commute isn’t as wild as Agnes Nambozo’s: She regularly climbs a rickety ladder that is nearly 1,000 feet tall—or 300 meters—before she can start work for the day.
Agnes is a nurse based in Buluganya, located in the shadow of Mount Elgon in eastern Uganda. Like many nurses in rural communities across sub-Saharan Africa, she wears a lot of different hats. She might spend one day delivering babies and treating wounds and the next as a health educator, promoting good nutrition and sanitation in her community. The days Agnes believes she makes the biggest difference, though, are the ones when she treks deep into the Ugandan countryside to vaccinate children.
Uganda has done an amazing job of reducing childhood mortality over the last 25 years. In 2000, about 145 children died per every thousand live births. By 2023, that figure had dropped to fewer than 40 deaths per 1,000 births. A lot of that progress can be attributed to vaccines and vaccinators like Agnes.
Eastern Uganda is a gorgeous place, but parts of it are incredibly difficult to cross. Many of the communities Agnes visits are high in the mountains. Some are only accessible by ladders, which act as links between communities. Older children can climb down them to go to school, but they are too steep for the little ones. Mothers can’t safely carry their babies down the ladders to the health clinic, so Agnes comes to them.
When Agnes was a little girl, she wanted to be a police officer—until her mom convinced her the job was too dangerous. Instead, she took a nursing course. She fell in love with the profession, even though it ended up being a much riskier job than her mom ever imagined. She travels to the villages to vaccinate kids in all kinds of weather. It’s often rainy in the mountains, and the ladders become slippery. “The ladders are risky because you might miss a step,” she says. “If you are lucky, you can get a fracture. If you’re not lucky, you can lose your life.”
On the days when she heads into the field to vaccinate children, Agnes leaves her house by 6:00 am. She takes a taxi from where she lives in Sironko to Buyaga, a town closer to where the health clinic is located. Cars can’t drive on the road to the clinic, so she takes a motorbike for the last stretch.
She arrives at the clinic around 8:00 am and starts packing for the day. Rural vaccinators like Agnes must carry their supplies on their backs, and there’s an art to making sure everything is loaded properly. The vaccines must be kept cold so she wears a heavy insulated backpack stuffed with ice packs.
Agnes then hops on another motorbike to a staging location before heading off on foot to the ladders. By the time she reaches the village and starts setting up to immunize the community, it’s usually around 10:30—more than four hours after she left her house for the day.
She comes in with a plan for how many people she’ll vaccinate, but Agnes always brings a couple extra doses just in case. A typical day usually means around 50 patients. Most are children under 5, who get vaccinated against deadly diseases like polio, measles, tetanus, and pneumonia. The latter is especially important in a region as rainy as this one, where the damp weather makes people more susceptible to respiratory diseases.
Agnes and her colleagues are often the only health workers who visit the most remote communities in the mountains, so they also provide general nursing care while they’re there. Agnes regularly gives kids deworming treatments and key supplements like vitamin A. She answers questions from the adults and offers them health guidance, including advice on planning a family.
After she wraps up for the day, Agnes makes the long trek back home. It’s exhausting, difficult work, but she is proud to help so many people. “Our motto for nurses in Uganda is ‘To love and serve,’” she says. “And to me, love is not just a word. It’s a verb.”
Unfortunately, Agnes’s job recently became a lot more difficult. Many of her colleagues at the health clinic in Buluganya were supported by USAID, and they lost their jobs when funding was cut. Some of the positions that were eliminated supported new and expectant mothers. Others worked on HIV and tuberculosis, distributing medication and testing high-risk individuals to prevent further spread.
Agnes and the others who are left are doing their best to ensure communities still receive care, but they can only do so much. “Our community is suffering a lot,” she says. She is worried about burnout if funding isn’t restored.
Still, Agnes won’t rest until she has helped as many people as she can. Thanks to the support of the Rotary Club of Kampala, she recently went back to school and is working towards a degree in nursing. She hopes to learn new skills that will save even more lives.
“My dream is to make people feel good, to make them happy, and to give my service to the people,” says Agnes. “When you have positivity, nothing is impossible.”

Everyday miracles
A perilous time for the world’s poorest children
My latest speech about why we need to keep funding vaccines.
I’ve been giving speeches about vaccines for 25 years. After so much time, it could have become routine for me. But it never has.
One reason is that the impact of vaccines—a single dose can protect a child from deadly diseases forever—is like a miracle to me, and who gets tired of talking about miracles?
The other reason is tied to this particular moment. There’s never been a point in the past 25 years when more lives hung in the balance. In all likelihood, 2025 will be the first year since the turn of the century when the number of children dying will go up instead of down.
Why? Governments are cutting health aid—including funds for Gavi, the vaccine organization that the Gates Foundation helped start. As a result, Gavi will likely not have all the money it needs to fund its next five years of work.
So when I spoke this week at a summit in Brussels where donors committed a new round of funding for Gavi, I focused on why it’s so important to keep the money flowing and maintain our momentum on vaccines. You can read my remarks below.
Remarks as delivered
June 25, 2025
Global Summit: Health & Prosperity through Immunisation
Brussels, Belgium
Good evening, and thank you to everyone joining us here tonight—and for all your support for one of the most transformative efforts in the world.
I want to particularly thank President von der Leyen and President Costa, and the European Union, for co-hosting this summit. President von der Leyen has long been an incredible champion for health and development, and the EU has been one of the Gavi's biggest supporters since the very beginning—support that's more crucial now than ever.
This chart is one that I think about a lot. It's really my most favorite chart. And I consider it almost kind of a report card for humanity. Because over the last 25 years, the reduction of under-five deaths has been far faster than any time in history. We've gone from over 9 million to now half as many deaths taking place by children. This is an unbelievable result.
And it doesn't fully state the benefit of these vaccines. The vaccines leave a lot of kids far more healthy, and so their ability to achieve their potential is increased.
Gavi prioritizes saving lives, and it's done with incredible scientific rigor. We're constantly improving vaccines. We're constantly looking at the safety, and I'm very proud of the work that's done to make sure that these vaccines are incredibly safe.
The founding of Gavi actually goes back to about the time the Gates Foundation was first started. And after 25 years, I can still say that it's at the top of the list of things that I'm very, very proud of. At that time, kids were not getting access to vaccines. They were too expensive. They hadn't been formulated properly. And I was stunned to learn that so many kids were dying from a disease like rotavirus because the vaccine wasn't getting out to all the children of the world.
So Gavi was created to not only help finance vaccines, but work with countries to adopt these new vaccines.
We've done an amazing job of getting these prices down. A good example is the pneumococcal vaccine, PCV. This vaccine became available in high-income countries the year that Gavi was founded. And it does a fantastic job of protecting kids against pneumonia, which was the single most deadly childhood infection. But it was very expensive.
And so Gavi and its partners incentivized vaccine manufacturers to develop a new, much cheaper PCV, which was introduced in 2017. Today, the manufacturers make PCV vaccines available to low-and middle-income countries for just $2 a dose.
And of course, we've seen similar reductions across all of the different vaccines, allowing us to add new vaccines to save even more children.
Since the founding of Gavi, the overall cost of fully vaccinating a child has been cut in more than half.
And we have a pipeline of new vaccines coming along, vaccines to address new diseases and that bring down costs even further.
A good example of this is the HPV vaccine. Cervical cancer, which HPV prevents, is the fourth most common cancer in women around the world. And this vaccine can prevent over 90% of these cases.
But countries were slow to adopt this vaccine, in part because it was hard to deliver: initially, it required three doses spread across six months.
Scientists believed that perhaps it could be done with fewer doses. And so the Gates Foundation funded a trial to see whether a single dose was essentially fully protective. And after seeing the incredible results, the WHO approved a single dose schedule in 2022.
Now, we have 75 countries around the world that have moved to this single dose approach.
And because the single dose is cheaper and easier to deliver, it's now getting to far more girls around the world. For example, after Nigeria introduced the single-dose vaccine, it was able to vaccinate more than 12 million girls in less than a year. That's really incredible.
Across Gavi countries, HPV vaccine coverage has increased dramatically. The year after this single-dose approval, we doubled the number of girls getting the vaccine. And [the next year] we doubled it again, and this year we'll double it again.
There's more than just making vaccines available. We have to work with our partner countries on helping improve their health systems. So the Gavi Alliance has spent a lot of its resources and a lot of its technical support in helping improve those primary health care systems, which are so vital. We've helped countries understand where they're missing kids and how to invest in raising those coverage levels.
As you've heard, over this 25-year period, that means over a billion children have been vaccinated—resulting in the saving of over 19 million lives.
Nineteen million is a big number. It's almost easier to understand if I just say: okay, here's a child whose life was saved. But you have to take your reaction to how valuable that is and multiply it by this absolutely gigantic number.
The total cost to save those lives was about $22 billion. And that means that Gavi saved children's lives for only about $1,000 per life saved.
And in addition, the kids who these vaccines have kept healthy not only go to school; they do well in school. They join the economy. They contribute to their country. And really, this is why improving health through vaccines is part of the formula for helping countries be self-sufficient.
Gavi's vaccination has generated $250 billion in economic benefits in the countries it supports. In fact, Gavi has had such an extraordinary economic benefit that over 19 countries that were Gavi recipients have now graduated, meaning they now fully fund their own immunization programs.
A great example is Indonesia. Since partnering with Gavi, it’s doubled the number of vaccines offered through its routine immunization program—and it’s seen childhood deaths fall to a quarter of what they were before. And now, Indonesia is not only transitioning to be fully self-supportive—it’s also become a Gavi donor.
Of course, this is a challenging time. All the progress we’ve made is at risk. Budgets are tight, and we all have to show our priorities when there’s tough trade-offs to be made.
There’s no denying: this is a global health crisis. Between the U.S. cuts and other funding cuts, in total, aid in total has gone down by 30 billion this year alone. It reinforces the incredible values being shown by the people who are showing up here today and being incredibly generous.
But with the cut in health resources, along with the financial situation a lot of these low-income countries are in, we are going to have a few years where things will go backwards.
As we think about this, think of a mother who will bring a baby wheezing for breath to a help center, and because the vaccines aren't available, that baby will not survive.
Think of a health worker trying to deal with a measles outbreak who, because there's less resources for that primary health care system or vaccines, that measles epidemic will continue.
This is agonizing. I mean, we have to put ourselves in the position of the parents who lose these children and how tough it must be for them to realize that the life could have been saved by a vaccine that costs just 30 cents.
So though our trend lines will briefly go into reverse, I believe that we can come back. I believe that we will resume that incredible progress that you saw.
I don't know if it'll be in two years or four years or six years, but I do know that as we bring these resources back, and we take advantage of an incredible pipeline of innovation, new drugs, new vaccines—lots of amazing things to help with these diseases—we will resume progress.
So everyone here, I'd say, is recommitting themselves, just like the Gates Foundation, to doubling down and staying committed.
You know, I'm not pessimistic. In fact, we have things like polio eradication that we are, as we say, this close to elimination. That'll be a mind-blowing thing. Likewise, malaria: we have tools, a variety of tools that brought together will give us a chance in the next 20 years to completely eradicate that as a disease, just like we're doing with polio.
This is all why the Gates Foundation is pledging $1. 6 billion to Gavi for this next five-year period. Thank you.
And it's why we'll invest billions in making sure that pipeline of new and lower-cost vaccines continues to make Gavi even more effective.
In closing, I think we can reflect on what Nelson Mandela once said: “There can be no keener revelation of a society's soul than the way it treats its children.”
In the last 25 years, Gavi has helped over a billion children live better, healthier lives—thanks to the extraordinary support of partners like you.
If we get this right, this trajectory of progress will continue for decades to come.
Thank you.
The last chapter
My new deadline: 20 years to give away virtually all my wealth
During the first 25 years of the Gates Foundation, we gave away more than $100 billion. Over the next two decades, we will double our giving.
When I first began thinking about how to give away my wealth, I did what I always do when I start a new project: I read a lot of books. I read books about great philanthropists and their foundations to inform my decisions about how exactly to give back. And I read books about global health to help me better understand the problems I wanted to solve.
One of the best things I read was an 1889 essay by Andrew Carnegie called The Gospel of Wealth. It makes the case that the wealthy have a responsibility to return their resources to society, a radical idea at the time that laid the groundwork for philanthropy as we know it today.
In the essay’s most famous line, Carnegie argues that “the man who dies thus rich dies disgraced.” I have spent a lot of time thinking about that quote lately. People will say a lot of things about me when I die, but I am determined that "he died rich" will not be one of them. There are too many urgent problems to solve for me to hold onto resources that could be used to help people.
That is why I have decided to give my money back to society much faster than I had originally planned. I will give away virtually all my wealth through the Gates Foundation over the next 20 years to the cause of saving and improving lives around the world. And on December 31, 2045, the foundation will close its doors permanently.
This is a change from our original plans. When Melinda and I started the Gates Foundation in 2000, we included a clause in the foundation’s very first charter: The organization would sunset several decades after our deaths. A few years ago, I began to rethink that approach. More recently, with the input from our board, I now believe we can achieve the foundation’s goals on a shorter timeline, especially if we double down on key investments and provide more certainty to our partners.
During the first 25 years of the Gates Foundation—powered in part by the generosity of Warren Buffett—we gave away more than $100 billion. Over the next two decades, we will double our giving. The exact amount will depend on the markets and inflation, but I expect the foundation will spend more than $200 billion between now and 2045. This figure includes the balance of the endowment and my future contributions.
This decision comes at a moment of reflection for me. In addition to celebrating the foundation’s 25th anniversary, this year also marks several other milestones: It would have been the year my dad, who helped me start the foundation, turned 100; Microsoft is turning 50; and I turn 70 in October.
This means that I have officially reached an age when many people are retired. While I respect anyone’s decision to spend their days playing pickleball, that life isn’t quite for me—at least not full time. I’m lucky to wake up every day energized to go to work. And I look forward to filling my days with strategy reviews, meetings with partners, and learning trips for as long as I can.
The Gates Foundation’s mission remains rooted in the idea that where you are born should not determine your opportunities. I am excited to see how our next chapter continues to move the world closer to a future where everyone everywhere has the chance to live a healthy and productive life.
Planning for the next 20 years
I am deeply proud of what we have accomplished in our first 25 years.
We were central to the creation of Gavi and the Global Fund, both of which transformed the way the world procures and delivers lifesaving tools like vaccines and anti-retrovirals. Together, these two groups have saved more than 80 million lives so far. Along with Rotary International, we have been a key partner in reviving the effort to eradicate polio. We supported the creation of a new vaccine for rotavirus that has helped reduce the number of children who die from diarrhea each year by 75 percent. Every step of the way, we brought together other foundations, non-profits, governments, multilateral agencies, and the private sector as partners to solve big problems—as we will continue to do for the next twenty years.
Over the next twenty years, the Gates Foundation will aim to save and improve as many lives as possible. By accelerating our giving, my hope is we can put the world on a path to ending preventable deaths of moms and babies and lifting millions of people out of poverty. I believe we can leave the next generation better off and better prepared to fight the next set of challenges.
The work of making the world better is and always has been a group effort. I am proud of everything the foundation accomplished during its first 25 years, but I also know that none of it would have been possible without fantastic partners.
Progress depends on so many people around the globe: Brilliant scientists who discover new breakthroughs. Private companies that step up to develop life-saving tools and medicines. Other philanthropists whose generosity fuels progress. Healthcare workers who make sure innovations get to the people who need them. Governments, nonprofits, and multilateral organizations that build new systems to bring solutions to scale. Each part plays an essential role in driving the world forward, and it is an honor to support their efforts.
Of course, although the Gates Foundation is by far the most significant piece of my giving, it is not the only way I give back. I have invested considerable time and money into both energy innovation and Alzheimer’s R&D. Today’s announcement does not change my approach to those areas.
Expanding access to affordable energy is essential to building a future where every person can both survive and thrive. The bulk of my spending in this area is through Breakthrough Energy, which invests in companies with promising ideas to generate more energy while reducing emissions. I also started a company called TerraPower to bring safe, clean, next-generation nuclear technology to life. Both of these ventures will earn profits if successful, and I will reinvest any money I make through them back in the foundation, as I already do today.
I support a number of efforts to fight Alzheimer’s disease and other related dementias. Alzheimer’s is a growing crisis here in the United States, and as life expectancies go up, it threatens to become a massive burden to both families and healthcare systems around the world. Fortunately, scientists are currently making amazing progress to slow and even stop the progress of this disease. I expect to keep supporting their efforts as long as it’s necessary.
The success in both areas will determine exactly how much money is given to the foundation since any profits they earn will be part of my overall gift.
What the Gates Foundation hopes to accomplish
Over the next twenty years, the foundation will work together with our partners to make as much progress towards our vision of a more equitable world as possible.
The truth is, there have never been more opportunities to help people live healthier, more prosperous lives. Advances in technology are happening faster than ever, especially with artificial intelligence on the rise. Even with all the challenges that the world faces, I’m optimistic about our ability to make progress—because each breakthrough is yet another chance to make someone’s life better.
Over the next twenty years, the foundation’s funding will be guided by three key aspirations:
In 1990, 12 million children under the age of 5 died. By 2019, that number had fallen to 5 million. I believe the world possesses the knowledge to cut that figure in half again and get even closer to ending all preventable child deaths.
We now understand the essential role nutrition—and especially the gut microbiome—plays in not only helping kids survive but thrive. We’ve made huge advances in maternal health, making sure that new and expectant mothers have the support they need to deliver healthy babies. We have new, life-saving vaccines and medicines, and we know how to get them to the people who need them most thanks to organizations like Gavi and the Global Fund. The innovation is there, the ability to measure progress is stronger than ever, and the world has the tools it needs to put all children on a good path.
Today, the list of human diseases the world has eradicated has just one entry: smallpox. Within the next couple years, I expect to add polio and Guinea worm to the list. (When we eradicate the latter, it will be a testament to the late President Jimmy Carter’s leadership.) I’m optimistic that, by the time the foundation shuts down, we can also add malaria and measles. Malaria is particularly tricky, but we’ve got lots of new tools in the pipeline, including ways of reducing mosquito populations. That is probably the key tool that, as it gets perfected and approved and rolled out, gives us a chance to eradicate malaria.
In 2000, the year that we started the foundation, 1.8 million people died from HIV/AIDS. By 2023, advances in treatment and preventatives cut that number to 630,000. I believe that figure will be reduced dramatically in the decades ahead, thanks to incredible new innovations in the pipeline—including a single-shot gene therapy that could reduce the amount of virus in your body so much that it effectively cures you. This would be massively beneficial to anybody who has HIV, including in the rich world. The same technology is also being used to treat sickle cell disease, an excruciating and deadly illness.
We’re also making huge progress on tuberculosis, which still kills more people than malaria and HIV/AIDS combined. Last year, a historic phase 3 trial began that could be the first new TB vaccine in over 100 years.
The key to maximizing the impacts of these innovations will be lowering their costs to make them affordable everywhere, and I expect the Gates Foundation will play a big role in making that happen. Health inequities are the reason the Gates Foundation exists. And the true test of our success will be whether we can ensure these life-saving interventions reach the people who need them most—particularly in Africa, South Asia, and across the Global South.
To reach their full potential, people need access to opportunity. That’s why our foundation focuses on more than just health.
Education is key. Frustratingly, progress in education is less dramatic than in health—there is no vaccine to improve the school system—but improving education remains our foundation’s top priority in the United States. Our focus is on helping public schools ensure that all students can get ahead—especially those who typically face the greatest barriers, including Black and Latino students, and children from low-income backgrounds. At the K-12 level, that means boosting math instruction and ensuring teachers have the training and support they need—including access to new AI tools that allow them to focus on what matters most in the classroom. Given the importance of a post-secondary degree or credential for success nowadays, we’re funding initiatives to increase graduation rates, too.
As I mentioned, having access to a high-quality nutrition source is key to keeping kids’ development on track. Smallholder farmers form the backbones of local economies and food supplies, and they play a key role in making that happen. One of the main ways the foundation helps farmers is through the development of new, more resilient seeds that yield more crops even under difficult conditions. This work is even more important in a warming world, since no one suffers more from climate change than farmers who live near the equator. Despite that, I’m hopeful that we can help make smallholder farmers more productive than ever over the next two decades. Some of the crops our partners are developing even contain more nutrients—a win-win for both climate adaptation and preventing malnutrition.
We’ll also continue supporting digital public infrastructure, so more people have access to the financial and social services that foster inclusive economies and open, competitive markets. And we’ll continue supporting new uses of artificial intelligence, which can accelerate the quality and reach of services from health to education to agriculture.
Underpinning all our work—on health, agriculture, education, and beyond—is a focus on gender equality. Half the world’s smallholder farmers are women, and women stand to gain the most when they have access to education, health care, and financial services. Left to their own devices, systems often leave women behind. But done right, they can help women lift up their families and their communities.
The United States, United Kingdom, France, and other countries around the world are cutting their aid budgets by tens of billions of dollars. And no philanthropic organization—even one the size of the Gates Foundation—can make up the gulf in funding that’s emerging right now. The reality is, we will not eradicate polio without funding from the United States.
While it's been amazing to see African governments step up, it’s still not enough, especially at a moment when many African countries are spending so much money servicing their debts that they cannot invest in the health of their own people—a vicious cycle that makes economic growth impossible.
It's unclear whether the world’s richest countries will continue to stand up for its poorest people. But the one thing we can guarantee is that, in all of our work, the Gates Foundation will support efforts to help people and countries pull themselves out of poverty. There are just too many opportunities to lift people up for us not to take them.
The last chapter of my career
Next week, I will participate in the foundation’s annual employee meeting, which is always one of my favorite days of the year. Although it’s been many years since I left Microsoft, I am still a CEO at heart, and I don’t make any decisions about my money without considering the impact.
I feel confident putting the remainder of my wealth into the Gates Foundation, because I know how brilliant and dedicated the people responsible for using that money are—and I can’t wait to celebrate them.
I'm inspired by my colleagues at the foundation, many of whom have foregone more lucrative careers in the private sector to use their talents for the greater good. They possess what Andrew Carnegie called “precious generosity,” and the world is better off for it.
I am lucky to have been surrounded by many generous people throughout my life. As I wrote in my memoir Source Code, my parents were my first and biggest influences. My mom introduced me to the idea of giving back. She was a big believer in the idea of “to whom much is given much is expected,” and she taught me that I was just a steward of any wealth I gained.
Dad was a giant in every sense of the word, and he, more than anyone else, shaped the values of the foundation as its first leader. He was collaborative, judicious, and serious about learning—three qualities that shape our approach to everything we do. Every year, the most important internal recognition we hand out is called the Bill Sr. Award, which goes to the staff member who most exemplifies the values that he stood for. Everything we have accomplished—and will accomplish—is a testament to his vision of a better world.
As an adult, one of my biggest influences has been Warren Buffett, who remains the ultimate model of generosity. He was the first one who introduced me to the idea of giving everything away, and he’s been incredibly generous to the foundation over the decades. Chuck Feeney remains a big hero of mine, and his philosophy of “giving while living” has shaped how I think about philanthropy.
I hope other wealthy people consider how much they can accelerate progress for the world’s poorest if they increased the pace and scale of their giving, because it is such a profoundly impactful way to give back to society. I feel fulfilled every day I go to work at the foundation. It forces me to learn new things, and I get to work with incredible people out in the field who really understand how to maximize the impact of new tools.
Today’s announcement almost certainly marks the beginning of the last chapter of my career, and I’m okay with that. I have come a long way since I was just a kid starting a software company with my friend from middle school. As Microsoft turns 50 years old, it feels right that I celebrate the milestone by committing to give away the resources I earned through the company.
A lot can happen over the course of twenty years. I want to make sure the world moves forward during that time. The clock starts now—and I can’t wait to make the most of it.
Field notes
The world needs more Nick Kristofs
I loved this journalist’s story of chasing hard problems and holding onto hope.
If you’re a big reader, you can probably point to a book or two that changed the course of your life. For me, it was a 1997 New York Times column by Nicholas Kristof about diarrhea, which was killing three million kids a year.
At the time, I had wealth—and knew I planned to give it away—but no clear mission. Nick’s article gave me one. I faxed it to my dad with a note: “Maybe we can do something about this.”
That ended up setting the direction for what became the Gates Foundation. It didn’t just give us a what—it gave us a how. Nick’s reporting showed us that the biggest challenge in global health isn’t always discovering new breakthroughs. Often, it’s making sure the tools we already have—vaccines, medicines, bed nets, or oral rehydration therapies for rotavirus—reach every child, no matter where they’re born.
Reading Nick’s new memoir, Chasing Hope, brought me back to that moment and showed me how it fit into the bigger story of his life. The book is a deeply personal account of a life spent documenting injustice and refusing to look away, whether it’s genocide in Darfur, refugee camps in Sudan, or the streets of his hometown in rural Oregon.
Nick’s impulse to go where the suffering is, and to make people care, has defined his career. He’s reported from more than 150 countries, covering war, poverty, health, and human rights. He and his longtime collaborator and wife, Sheryl WuDunn, won a Pulitzer Prize for their work. Together and individually, they’ve brought injustices around the world into view for millions of readers.
But Chasing Hope isn’t just a greatest-hits collection of his past reporting. It’s the story of how someone becomes Nick Kristof. He writes about growing up on a sheep and cherry farm in Oregon, driving tractors as a teenager, and nearly becoming a lawyer before deciding on journalism. He also reflects on the toll his career has taken on him, his family, and his capacity for hope.
I’ve known Nick for many years now, and I’ve admired his work since that 1997 rotavirus column. On paper, we don’t seem all that similar. He’s a journalist, I’m a technologist; he tells stories, I talk numbers. But reading Chasing Hope, I was struck by what we have in common: growing up in the Pacific Northwest, learning about the value of service from our parents, thinking globally.
We both attended Harvard and left early—me because I dropped out, him because he graduated in three years before heading to Oxford as a Rhodes Scholar. But neither of us ever stopped learning. I think we both believe the world’s pretty interesting if you remain a student.
Nick’s curiosity didn’t come out of nowhere, and neither did his sense of purpose. His mother was an art history professor and a civic leader who helped influence local politics. His father, a political science professor who fled both Nazism and communism, believed deeply in education and the responsibilities that come with freedom. That kind of upbringing left a mark on him and shaped the kind of journalist he became.
Over decades, he’s built a career reporting on crises that are often ignored because they happen in far-off places, far from centers of power. In Chasing Hope, he recounts his experiences chronicling river blindness in Ethiopia, maternal mortality in Cameroon, and malaria in Cambodia. Through the foundation, I mobilize science, data, and funding to address many of the same global challenges Nick reports on. Our approaches are different, but the underlying questions we ask (and try to answer) are the same: Why are some lives valued less than others? And how can we use the tools we have—information, resources, attention—to close that gap?
Nick has an admirable commitment to nuance, especially when it comes to hard subjects like China. Nick lived there for years, speaks Mandarin, and understands the country in a way most Western commentators don’t. I’ve always appreciated his ability to go beyond the headlines—and focus not just on what’s going wrong, but on what’s changing and why it matters.
Nick is also an optimist, which might sound strange given the kinds of suffering he writes about. But his work is grounded in a belief I share: The right data—or the right story—can move people to act. As Nick puts it, “A central job of a journalist is to get people to care about some problem that may seem remote.” People, when given the chance, want to make things better. Progress, while never guaranteed, is possible.
That optimism feels especially important, if increasingly difficult, right now. Isolationism is on the rise around the world, and governments are cutting back on foreign aid at the very moment when we should be doing more, not less. Millions of lives are at stake. Nick’s work reminds us what’s possible when we care about people beyond our own borders—and what happens when we don’t.
Chasing Hope made me think a lot about what kind of person chooses to run toward the hardest problems—and keep going back until they’re solved. It also made me think the world would be a much better place if there were more Nick Kristofs. In the meantime, we’re lucky to have this one.
Back for the future
I’m heading back to India
This trip will give me the chance to see what’s working, what’s changing, and what’s next—for India and the Gates Foundation.
In a few days, I’ll be traveling to India—my third visit in three years. India is a place where big challenges meet even bigger ambitions, and where innovation is transforming lives at an incredible scale. Every time I’m there, I see firsthand how much progress is being made in public health, agriculture, and technology. And I come away with new ideas, because India is full of smart, ambitious people tackling some of the world’s hardest problems in creative ways.
This visit will also be significant because—as we mark our 25th anniversary—the Gates Foundation’s Board of Trustees is meeting in the Global South for the first time. India is the right place for this milestone. The foundation has been working in the country for more than two decades, partnering with the government, researchers, and entrepreneurs to improve health and development. Today, India is home to some of the most impactful programs we’ve contributed to, from disease eradication and sanitation to women’s empowerment and digital financial services. This trip will give me a chance to see what’s working, what’s changing, and what’s next—for India and the foundation.
India’s track record in public health shows what’s possible. When I visited in 2011, it was one of the last places in the world still fighting polio. But that year, after relentless effort, India recorded its last case—and it’s remained polio-free ever since. Avahan, the HIV prevention program launched by the Gates Foundation two decades ago, is another success story. It pioneered a community-led approach to reduce infection rates that complemented the government’s efforts in high-prevalence states; eventually, management of the program transitioned to the Indian government, becoming part of the country’s broader health strategy.
That same model—leveraging local leadership, innovative solutions and data-driven insights—is now driving India’s fight against tuberculosis. The country has the world’s highest TB burden, but its investment in new diagnostics, AI-powered detection tools, and improved treatment strategies is accelerating progress toward elimination.
India’s success in childhood immunization is another reason I’m eager to return and learn more. Over the past several years, the country has scaled up routine vaccination programs, ensuring every major childhood vaccine is available. It has also used digital dashboards to track vaccine coverage, monitor cold storage, and improve maternal and child healthcare. These efforts have helped drive down mortality rates and create a stronger health system that can respond to new challenges.
India’s global health leadership is also transforming how the country approaches diagnostics and treatment for infectious diseases. As a result, it’s become a leader in low-cost vaccine manufacturing, ensuring that life-saving vaccines are available around the world. Indian companies are also tackling another critical challenge: making diagnostics more affordable. One effort I’m following closely is the push to make a saliva-based TB test for under $2, which could help millions of people in India and globally detect the disease earlier and get treatment faster.
Beyond health, India is also at the forefront of digital transformation. I’ve written before about how digital public infrastructure (DPI)—like Aadhaar and India’s digital payments system—has made it easier for millions of people to access banking, healthcare, and government services. Now, India is using AI-powered DPI tools to help rural health workers improve early disease detection, optimize pregnancy care, and manage patient data more effectively.
AI is also transforming agriculture across the country. When I was in Odisha last year, I saw farmers using AI-powered tools to predict weather patterns, choose crops, and reduce disease risks. I’m looking forward to seeing how much better those tools have gotten in the short time since.
What makes India’s progress so transformative, though, is that it doesn’t just benefit India. During India’s G20 Presidency in 2023, Prime Minister Modi declared his intent to make Indian innovations and know-how available to solve development problems globally. And that’s exactly what is happening. The solutions being developed there, from vaccine manufacturing to AI-powered diagnostics, are being shared with the world. Indian companies are making TB tests that could be game-changing across Africa. They’re developing AI models that could help farmers across Asia. And they’re proving that digital technology can make healthcare work better for everyone, especially the most vulnerable.
At the Gates Foundation, we tackle tough problems by working in close partnership with the people and governments most affected by them. India has been an incredible partner in this work because of the country’s deep expertise and willingness to develop and scale new ideas. The challenges remain: eliminating TB, improving nutrition, expanding access to AI-driven health and development services. But India has shown time and again that progress happens when innovation, local leadership, and investment come together.
That’s why I’m so excited for this trip. I’ll be meeting with government leaders, scientists, and philanthropists who are shaping the future of health and development in India. I’ll be visiting innovators who are working on solutions that could help people in India and around the world. And I’ll get to see how the foundation’s work fits into this bigger story—and how we can continue to support Indian-led efforts to improve lives.
I always leave India inspired. I know this trip will be no different.
The sky’s the limit
The Drone Didis are taking flight
Drones are helping rural women boost their income and India’s agricultural productivity.
I was excited to get a drone for my birthday last year. I couldn’t wait to get it into the air and see what my backyard looked like from the sky. But, as anyone who has used one can tell you, I quickly learned a harsh truth: Flying a drone isn’t easy. It takes a lot of practice and skill.
Maybe it’s time to pull the drone back out, because I was lucky to get a lesson from the experts last month in India. During my visit to Delhi, I met with Sangita Devi, Sumintra Devi, and Kajol Kumari—three Drone Didis from Bihar who are taking India’s agricultural productivity to new heights.
The women I met are part of the Indian government’s Namo Drone Didi program. (Didi is the Hindi word for “sister.”) It was launched in 2023 to help rural women boost their income and boost India’s agricultural productivity—and although the program is still in its early days, I’m already impressed by its results.
Right now, the Drone Didis primarily use their flying skills to fertilize crops. Applying fertilizer via drone has a lot of benefits over doing it by hand. Since you can spray farther away from the plant, the liquid fertilizer becomes more atomized—which means that it turns into finer droplets that cover more area. This benefits both farmers and the environment, because you need significantly less fertilizer and less water to help distribute it. Plus, it’s faster. One Drone Didi can cover as much as five acres in the same time it would take five people to cover half an acre.
I cannot wait to see how the program expands in the years ahead. The Indian government has plans to equip the drones with advanced sensors and imaging technology. This will allow Drone Didis to use real-time data to deliver targeted interventions to improve the quality and quantity of farmers’ crops. They will be able to detect diseases and pests, assess soil moisture levels, monitor crop growth, and more.
I’m equally excited to track how the Drone Didi program continues to empower women across India. Every Didi is affiliated with a self-help group, or SHG. The plan is to provide nearly 15,000 drones to SHGs across India by the end of next year.
In the United States, where I live, self-help groups are usually associated with mental health. In India, they’re a form of mutual aid. Each SHG is small—most are around 12 people, although some are as big as 25—and brings together women to support each other socially and financially. They pool their savings, access microloans at lower interest rates, and solve problems in areas like health and education.
The Didis I met with were longtime members of SHGs organized by JEEViKA, an organization in Bihar that works to lift people from rural areas out of poverty. During our time together in Delhi, Kajol told me about how JEEViKA helped her open her own shop three years ago, where she sells seeds and fertilizers. She loves being an entrepreneur, and when she was approached about becoming a Drone Didi, she knew it would do wonders for her business.
Each Didi attends a training program in Hyderabad or Noida, where they are taught how to pilot the drone and apply fertilizer effectively. (I was surprised to hear that learning to fly is apparently easier and takes less time than learning to fertilize!) Other women in their SHGs are trained as drone technicians, ready to repair the machines if any problems arise.
In the less than two years, the Drone Didi program is already transforming the lives of its pilots. Kajol is using the extra income she’s earned to expand her shop offerings and build a warehouse to store her stock. She also plans to send her children to a better school. Sangita’s family couldn’t afford a bicycle before she became a Drone Didi—today, she is the proud owner of an auto rickshaw.
Sumintra hopes that, when people see someone like her flying a huge drone, it changes their perception of what women are capable of. Like many women in her area, she married very young and was expected to stay home with her children. Today, her kids call her “Pilot Mummy” and dream about her flying airplanes one day.
I hope you think of the Didis the next time you hear the buzz of a drone above you at a wedding or a park. It’s remarkable how one piece of technology can reshape what is possible in a community. Kajol told me that people sometimes look at her and say, “She’s flying too high! What will she do next?”
Her response? “This is just the beginning. Wait and see what’s coming.”

Farm work
On Africa’s farms, the forecast calls for adaptation and innovation
In Kenya, I visited with a smallholder farmer using new tools and practices to fight back against climate change.
I planted drought-tolerant seeds, fed and weighed chickens, and used a mobile phone to monitor weather forecasts and local crop prices.
These were a few of the chores I was given during my visit with Mary Mathuli, a smallholder farmer in rural Kenya.
I stopped at her home in Makueni County, south-east of Nairobi, during my recent trip to Kenya to better understand how farmers like Mary are faring in the face of climate change.
I arrived expecting to hear her talk about the record droughts and smaller harvests many farmers are experiencing throughout Africa.
Instead, to my surprise, she led me out to her fields to show off the innovations that are allowing her to continue to grow crops and earn an income to support her family, despite the drastic changes in rainfall and weather patterns.
A natural teacher, Mary encouraged me to learn by doing. She put me to work so I could understand how these new agricultural inputs and practices can make a big difference in their lives.
This experience taught me a couple important lessons.
First, my farming skills—like holding a chicken and swinging a hoe—need some work.
Second, and more importantly, I got a personal reminder of how resourceful and resilient African smallholder farmers like Mary are. Battered by years of drought and other extreme weather patterns, they are developing new skills and embracing new technologies to adapt to some of the toughest conditions for growing crops and raising livestock.
To be clear, African farmers face huge challenges due to climate change. Although sub-Saharan Africa accounts for only about four percent of the world’s carbon emissions, the continent is bearing the brunt of climate change impacts. Climate-related losses on many African farms are more than double those seen globally. In Makueni County, where Mary farms, yields of maize have been falling since 1994, largely due to changes in the weather.
While more innovation is needed to help Africa’s smallholder farmers keep pace with the threats posed by climate change, Mary and other farmers in Kenya are adopting some incredible new tools and practices that can limit crop losses and help their farms thrive even in extreme weather:
As farms go, Mary’s farm is quite small. Just about 4 acres, which is typical for farms in Africa. Still, she packs a lot of activities in this space, growing commercial and subsistence food crops and rearing poultry and livestock. In sub-Saharan Africa, more than half of the population works in agriculture. Together, they produce about 80 percent of the continent’s food supply. And most of the people doing the backbreaking farm work—like the chores I performed—are women.
I was impressed by Mary’s entrepreneurial spirit and her optimism. She appeared to seize every opportunity to try out new technologies and agricultural practices. It’s one of the reasons why she was trained as a model farmer and Village Based Advisor by the Cereal Growers Association, an organization that works with smallholder farmers to help improve their productivity. In this role, Mary provides guidance to several hundred farmers in her community, showing them how to use drought-tolerant seeds, raise chickens, and adopt other climate adaptation agricultural strategies.
She is clearly doing a good job in this role because more than 90 percent of farmers in her area have embraced one of the new adaptation practices.
I look forward to hearing how the seeds I planted with Mary are doing, despite the disappointing rains in recent months. I can’t imagine them in better hands than hers.
Thanks so much for the visit, Mary!
Food for thought
What it will really take to feed the world
In his latest book, one of my favorite authors argues that solving hunger requires more than producing more food.
In the introduction to his latest book, How to Feed the World, Vaclav Smil writes that “numbers are the antidote to wishful thinking.” That one line captures why I’ve been such a devoted reader of this curmudgeonly Canada-based Czech academic for so many years. Across his decades of research and writing, Vaclav has tackled some of the biggest questions in energy, agriculture, and public health—not by making grand predictions, but by breaking down complex problems into measurable data.
Now, in How to Feed the World, Vaclav applies that same approach to one of the most pressing issues of our time: ensuring that everyone has enough nutritious food to eat. Many discussions about feeding the world focus on increasing agricultural productivity through improved seeds, healthier soils, better farming practices, and more productive livestock (all priorities for the Gates Foundation). Vaclav, however, insists we already produce more than enough food to feed the world. The real challenge, he says, is what happens after the food is grown.
This kind of argument is classic Vaclav—questioning assumptions, forcing us to rethink the way we frame problems, and turning conventional wisdom on its head. His analysis is never about the best- or worst-case scenarios; it’s about what the numbers actually tell us.
And the numbers tell a striking story: Some of the world’s biggest food producers have the highest rates of undernourishment. Globally, we produce around 3,000 calories per person per day—more than enough to feed everyone—but a staggering one-third of all food is wasted. (In some rich countries, that figure climbs to 45 percent.) Distribution systems fail, economic policies backfire, and food doesn’t always go where it’s needed.
I’ve seen this firsthand through the Gates Foundation’s work in sub-Saharan Africa, where food insecurity is driven by low agricultural productivity and weak infrastructure. Yields in the region remain far lower than in Asia or Latin America, in part because farmers rely on rain-fed agriculture rather than irrigation and have limited access to fertilizers, quality seeds, and digital farming tools. But even when food is grown, getting it to market is another challenge. Poor roads drive up transport costs, inadequate storage leads to food going bad, and weak trade networks make nutritious food unaffordable for many families.
And access is only part of the problem. Even when people get enough calories, they’re often missing the right nutrients. Malnutrition remains one of the most critical challenges the foundation works on—and it’s more complex than eating enough food. While severe hunger has declined globally, micronutrient deficiencies remain stubbornly common, even in wealthy countries. One of the most effective solutions has been around for nearly a century: food fortification. In the U.S., flour has been fortified with iron and vitamin B since the 1940s. This simple step has helped prevent conditions like anemia and neural tube defects and improve public health at scale—close to vaccines in terms of lives improved per dollar spent.
One of the most interesting parts of the book is Vaclav’s exploration of how human diets evolved. Across civilizations, people independently discovered that pairing grains with legumes created complete protein profiles—whether it was rice and soybeans in Asia, wheat and lentils in India, or corn and beans in the Americas. These solutions emerged from practical experience long before modern science could explain why they worked so well.
But just as past generations adapted their diets to available resources, we’re now facing new challenges that require us to adapt in different ways. Technology and innovation can help. They’ve already transformed the way we produce food, and they’ll continue to play a role. Take aquaculture: Once a tiny industry, it’s grown over the past 40 years to supply more seafood for the world than traditional fishing—a scalable way to meet global protein demands. The Green Revolution is another example. Beginning in the 1960s, innovations in higher-yielding crops, more effective fertilizers, and modern irrigation prevented widespread famine in India and Mexico. These changes were once seen as unlikely, too.
New breakthroughs could drive even more progress. CRISPR gene editing, for instance, could help develop crops that are more resilient to drought, disease, and pests—critical for farmers facing the pressures of climate change. Vaclav warns that we can’t count on technological miracles alone, and I agree. But I also believe that breakthroughs like CRISPR could be game-changing, just as the Green Revolution once was. The key is balancing long-term innovation with practical solutions we can implement immediately.
And some of these solutions aren’t about producing more food at all—they’re about wasting less of what we already have. Better storage and packaging, smarter supply chains, and flexible pricing models could significantly reduce spoilage and excess inventory. In a conversation we had about the book, Vaclav pointed out that Costco (which might seem like the pinnacle of U.S. consumption) stocks fewer than 4,000 items, compared to 40,000-plus in a typical North American supermarket.
That kind of efficiency—focusing on fewer, high-turnover products—reduces waste, lowers costs, and ultimately eases pressure on global food supply, helping make food more affordable where it is needed most.
How to Feed the World had a lot to teach me—and I’m sure it will teach you a lot, too. Like all of Vaclav’s best books, it challenges readers to think differently about a problem we thought we understood. Growing more and better food remains crucial—especially in places like sub-Saharan Africa, where there simply isn’t enough. But as the world’s population approaches 10 billion, increasing agricultural productivity alone won’t solve hunger and malnutrition. We also need to ensure that food is more accessible and affordable, less wasted, and just as nutritious as it is abundant.
After all, the goal isn’t to make more food for its own sake—it’s to feed more people.

Alphabet soup
You’ve probably never heard of CGIAR, but they are essential to feeding our future
No other institution has done as much to feed our world as CGIAR.
What’s for dinner?
It’s a question asked every day in homes around the world. No other organization has done as much to ensure families—especially the poorest—have an answer to that question as CGIAR, the world’s largest global agricultural research organization.
More than 50 years ago, CGIAR’s research into high-yielding, disease-resistant rice and wheat launched the Green Revolution, saving more than a billion people from starvation. In the years since then, their work on everything from livestock and potatoes to rice and maize has helped reduce poverty, increase food security, and improve nutrition.
Never heard of CGIAR? You’re not alone. It’s an organization that defies easy brand recognition. For starters, its name is often mistaken for “cigar,” suggesting a link to the tobacco industry. And it doesn’t help that CGIAR is not a single organization, but a network of 15 independent research centers, most referred to by their own confusing acronyms. The list includes CIFOR, ICARDA, CIAT, ICRISAT, IFPRI, IITA, ILRI, CIMMYT, CIP, IRRI, IWMI, and ICRAF, leaving the uninitiated feeling as if they’ve fallen into a bowl of alphabet soup.
It’s too bad that more people don’t know about CGIAR. Their work to feed our hungry planet is as important now as it’s ever been. By 2050, as the world’s population gets bigger and incomes increase (which causes dietary changes like eating more meat), global food demand is expected to increase by 60 percent. Meeting this challenge is made tougher by climate change, which is affecting food production in every corner of the globe. Farmers are under assault from shifting rainfall, more frequent and extreme droughts and floods, and severe pest and disease outbreaks among crops and livestock.
The people who are most affected by these changes today are the world’s smallholder farmers. About 500 million farming households, in South Asia and sub-Saharan Africa, earn their living by raising crops and livestock on small parcels of land. These families have the fewest resources to cope with the many impacts of a warming climate.
I’ve been writing a lot this year about why reducing emissions from all sectors of our economy, including agriculture and electricity generation, is critical in our fight against climate change. But it’s equally important for the world to stay focused on helping vulnerable populations, like smallholder farmers, prepare for the disruptive impacts of climate change. We owe it to them. The people who will suffer most from climate change, especially in sub-Saharan Africa, are the least responsible for emitting these greenhouse gases. According to an Africa Progress Panel report, an average Ethiopian would have to live for 240 years to equal the carbon footprint of the average American.
I’m now co-chairing the new Global Commission on Adaptation, which is playing a key role in building government and public support for efforts to reduce the impacts of climate change on communities most at risk. We will need CGIAR’s research to help supply farmers with a steady stream of climate-smart crop varieties.
A great example of a CGIAR innovation helping smallholder farmers adapt to climate change is its drought-tolerant maize program. More than 200 million households in sub-Saharan Africa depend on maize for their livelihoods. Maize productivity in Africa is already the lowest in the world. And as weather patterns have become more erratic, farmers are at greater risk of having smaller maize harvests, and sometimes no harvest at all.
In response to this challenge, CGIAR’s International Maize and Wheat Improvement Center or CIMMYT, with funding from our foundation, USAID and the Howard Buffett Foundation, developed more than 150 new maize varieties that could withstand drought conditions. Each variety is adapted to grow in specific regions of Africa. At first, many smallholder farmers were afraid of trying new crop varieties instead of more commonly planted ones. But as CIMMYT worked with local farmers and seed dealers to share the benefits of these new varieties, more and more farmers adopted drought tolerant maize. The results have been life changing for many farming families.
In Zimbabwe, for example, farmers in drought-stricken areas using drought-tolerant maize were able to harvest up to 600 kilograms more maize per hectare than farmers using conventional varieties. The additional harvest was enough to feed a family of six for 9 months. For farming families who chose to sell their harvests, it was worth $240 in extra income, giving them much-needed cash to send their children to school and meet other household needs.
CIMMYT, in partnership with another CGIAR center, the International Institute of Tropical Agriculture or IITA, has gone on to develop other maize varieties for farmers who are not only vulnerable to drought, but also poor soils, disease, pests, and weeds. These varieties are expected to give farmers up to 30 percent greater yields and help them fight malnutrition.
CGIAR’s team of more than 8,000 scientists and staff around the world are also developing other tools to help farmers adapt to unpredictable weather and diseases. They have created a smart phone app that allows farmers to use the camera on their phone to identify specific pests and disease attacking cassava, an important cash crop in Africa. There are also new programs to use drones and ground sensors to help wheat and sugarcane farmers determine how much water and fertilizer their crops need.
We will need many new ideas like these to help farmers be prepared to meet the challenges of our changing climate. If they are, we will all have an answer to the question “What’s for dinner?” for years to come.

Farm aid
A warmer world will hurt this group more than any other
We need to help the world’s poorest people adapt to climate change.
I’ve spent a lot of time over the last month talking about climate change. Whether it’s on my book tour, in media interviews, or just during conversations with colleagues, it’s been great to have so many thoughtful conversations with people about how we prevent the worst effects of climate change.
Most of the questions I’ve gotten are about how we get to zero greenhouse gas emissions. Mitigation is the biggest climate problem we need to solve, and it’s been great to see it get so much attention. But I’ve noticed there’s one key topic that people don’t ask about as much: how we can help the world adapt to climate change.
I understand why. I dedicated five chapters of the book to mitigation and only one to adaptation. (In retrospect, I wish I had written more about the subject.) But there’s a reason I named my book “How to Avoid a Climate Disaster” and not “How to Stop Climate Change:” Our climate is already changing.
You just need to look at last month’s freeze in Texas and last year’s wildfires in California to see that extreme weather events are becoming more common. The scary thing is that these events aren’t the only (or even the most devastating) way a warming world is making life more difficult for people. The biggest damage is happening too gradually to make headline news, mostly in places near the Equator—and no one is more at risk than the world’s poorest people.
About two-thirds of those living in poverty work in agriculture, often relying on the food they grow to feed their families. A warmer world will be problematic for relatively well-off farmers in America and Europe, but potentially deadly for low-income farmers in Africa and Asia.
The closer you live to the Equator, the worse the effects of climate change will be. Droughts and floods will become more frequent, wiping out harvests more often. Livestock will eat less and produce less meat and milk. The air and soil start to lose moisture, leaving less water available for plants; in South Asia and sub-Saharan Africa, tens of millions of acres of farmland will become substantially drier.
When you’re already living on the edge, any one of these changes could be disastrous. We’re likely going to see a situation for these farmers where, instead of your crop getting wiped out every ten years, it gets wiped out every four years. If you don’t have money saved up to buy imported food—which is the case for most smallholder farmers—your children will likely become malnourished and more susceptible to disease.
The worst impact of climate change in poor countries will be to make health worse—which is yet another reason why we need to help the poorest improve their health. This starts with raising the odds that malnourished children will survive by improving primary healthcare systems, doubling down on malaria prevention, and continuing to provide vaccines for conditions like diarrhea and pneumonia. We also need to ensure that fewer children are malnourished in the first place by helping poor farmers grow more food.
This is a problem we can help solve with innovation. We need better methods and tools to grow food, just like we need to find zero-carbon ways to move around and generate electricity. No other organization is in a better position to create the innovations that will help poor farmers adapt to climate change in the years ahead than CGIAR, a global partnership that helps make plants and animals more resilient and productive. (I’ve written about how amazing CGIAR is before.)
Our foundation first got involved with CGIAR more than a decade ago, when we supported their work to develop drought- and flood-tolerant varieties of staple crops like maize. We’re already seeing big improvements in places like Zimbabwe. Farmers in drought-stricken areas there who used drought-tolerant maize were able to harvest up to 500 more pounds per acre than farmers who used conventional varieties—producing enough to feed a family of six for nine months.
CGIAR and other organizations are also creating tools to help farmers adapt to unpredictable weather, like sensors that tell you when to plant seeds and phone apps that help identify pests. Poor farmers need more advances like these, but to provide them, we need to invest more money in agricultural R&D. Doubling CGIAR’s funding so it can reach more farmers is one of the main recommendations by the Global Commission on Adaptation, which I led along with former UN secretary-general Ban Ki-moon and former World Bank CEO Kristalina Georgieva. (Other recommendations include shoring up water infrastructure and building a stronger safety net to help farmers recover faster.)
If we don’t take steps now to help farmers adapt, we’re setting ourselves up for a humanitarian and geopolitical disaster. The U.S. military predicts that climate change will become a huge driver of global instability. When people can’t grow enough food to feed themselves, they often leave those areas for places that can better support their families. We’re going to see more “climate refugees” move to cooler regions as the world gets warmer. The Department of Defense is already thinking about where a warmer climate could cause conflicts that they would be asked to intervene in.
It’s deeply unfair that the people who contribute the least to climate change will suffer the worst from its effects. Extreme poverty has plummeted in the past quarter century, from 36 percent of the world’s population in 1990 to 10 percent in 2015 (although COVID-19 is a huge setback that is undoing a great deal of progress). Climate change could erase even more of these gains, increasing the number of people living in extreme poverty by 13 percent.
Rich and middle-income countries are causing the vast majority of climate change, and we need to be the ones to step up and invest more in adaptation. The world’s poorest deserve our help, and they need more of it than they’re getting.

Net gains
Planes, trains, and smartphones
The future of public infrastructure is digital, efficient, and for everyone.
Almost thirty years ago, I wrote a book called The Road Ahead, about the transformative potential of the internet and other new digital technologies. Back then, I envisioned a world where online payments and e-government would change how we interact with money, services, and each other. Today, much of that has become a reality, in part due to the development of digital public infrastructure. In my recent travels around the world, I’ve seen up close how DPI is revolutionizing the way entire nations serve their people, respond to crises, and grow their economies. And at the Gates Foundation, we see it as an important part of our efforts to help save lives and fight poverty in poor countries.
There are a few core components that constitute DPI: digital ID systems that securely prove who you are, payment systems that move money instantly and cheaply, and data exchange platforms that allow different services to work together seamlessly. These systems and platforms are to the digital world what roads, bridges, and power lines are to the physical one—an underlying structure that connects people, data, and money online. Strong DPI can propel a country forward by making it easier for people to access essential services, participate in the formal economy, and improve their lives. On the flip side, DPI that is poorly implemented (or simply non-existent) can slow a country’s development and perpetuate inefficiencies and inequities.
In the 21st century, digital public infrastructure is proving to be as important for progress as its brick-and-mortar predecessors—and the effects have been impressive around the world, wherever it’s been embraced.

Accounting for accounts
Digital tech is turning the unbanked into the banked
More people have accounts than ever. Here’s what we need to do next.
In the worst days of COVID-19, when people around the world were out of work and struggling to pay for food and housing, many national governments came to the same conclusion about the best way to offer immediate help: send people cash. More than 200 countries introduced emergency cash transfer programs or expanded existing ones; India, for example, transferred money to 300 million people, 200 million of whom were women, in the weeks after its first lockdown. Brazil reached 70 million people with emergency transfers.
Imagine the risk involved in making these payments with paper money during a pandemic. Government workers would have to physically deliver these payments, potentially exposing them and everyone they encountered to the virus. In addition, the whole process would be expensive and time-consuming at a time when people need help as quickly as possible.
Fortunately, most governments didn’t have to resort to in-person payment. They were able to deposit cash transfers directly into people’s accounts—allowing them to give crucial support without paper bills changing hands. And during the pandemic, even more users were brought into the digital fold. For example, after financial regulators in West Africa temporarily allowed people to open accounts by text or telephone, more than 8 million signed up for accounts while their countries were in lockdown.
Globally, transferring so much money without cash was possible thanks to more than a decade of painstaking work by governments, financial service providers, nonprofits, and other partners. Today, about three quarters of people worldwide have an account at a financial institution or through a mobile money provider. That’s a 50 percent increase in the past ten years, and the growth has not just been in higher-income countries. Developing countries have increased 71 percent in that time.
This growth is great news because it means that more low-income people—and especially low-income women—are being empowered to use products that let them make and receive payments, save and borrow money, and get insurance. Both research and experience show that this financial inclusion helps people exit and stay out of poverty. And using digital technology to do it is a low-cost way to build economic resilience and reduce extreme poverty, which is why it’s an essential part of the Gates Foundation’s strategy. We have granted several hundred million dollars to partners who are helping low- and middle-income countries build digital financial systems.
Whenever I talk to friends about this work, they’re surprised to learn that roughly 1.4 billion adults can’t or don’t use any type of formal financial account, and most of those unbanked people live in low- and middle-income countries. One reason is that analog banking requires buildings, piles of paperwork, security guards, and tellers, making the cost per transaction so high that it’s not economical for a company to serve people with low balances and small transactions. As a result, people create ingenious informal banking methods—doing things like pooling cash with family and neighbors or creating community savings groups. As creative as these solutions are, they don’t allow people to build assets or move money instantly. And they are often risky—cash stashed under a mattress can be stolen, for example.
Today, the proliferation of mobile phones means that you no longer need so much expensive infrastructure to provide modern financial services. With digital technology, costs are low enough that it makes economic sense for companies to serve more of the people whom the old system has ignored.
An early example was M-PESA in Kenya, which let people living in cities send money to their relatives in rural areas efficiently and inexpensively. As it caught on, it was eventually used to make payments in shops. Likewise, India’s Universal Payment Interface allows users to make instant digital payments to each other at extremely low cost; it now includes 323 financial service providers throughout the country and handles nearly 6 billion transactions each month. During the pandemic, more than 80 million adults in India made their first digital payment to a merchant.
Yet even the exemplar countries aren’t reaching everyone who needs digital banking. That’s why the World Bank (with support from the foundation) runs the Global Findex database, a comprehensive survey of how adults borrow, save, and send money and manage risks. The Findex has been updated periodically since 2011, and the latest version was just published earlier today. Using data gathered from 128,000 adults in 123 economies, it highlights steps that will expand formal banking to everyone in the world who wants it.
I eagerly read an early copy of the Findex report as soon as I had the chance, and I’m glad I did. I recommend the report to anyone, especially policymakers, who wants more people to benefit from financial inclusion. When the world knows more about where inclusion is growing and where it isn’t, we’re better equipped to make sure we’re reaching the people who are still left out.
One Findex finding that jumped out to me is the gender gap. Although the world has made progress in empowering women to use formal financial services as much as men do, there’s still work to do. In developing countries, the gap was 9 percent in 2017 and 6 percent in 2021. The world can do better. Leaders should focus even more directly on expanding account ownership and use among women.
Another section of the report looks at a crucial question: What prevents the people who are still unbanked from joining the formal system? Knowing the answer will make it easier to create services that will work for them.
To find out, the researchers behind the Findex did extensive surveys of the unbanked. Their top explanations: The accounts are still too expensive, a family member already has one, banks are too far away, or they don’t have enough money to use an account. So making the accounts even more affordable, accessible, and appealing needs to be a priority. Introducing digital payments via mobile phones is a great way to start: Between 2014 and 2021, the percentage of people in Ghana using formal banking services went up 28 points, and virtually all of the increase was driven by people signing up for mobile-enabled digital payments.
I’ve heard people argue that there’s a simple way to automatically expand financial inclusion: introduce digital currencies, and specifically cryptocurrencies. But that idea isn’t rooted in an understanding of what poor people require—the kind of understanding that the Findex provides.
In many areas where the unbanked live, many transactions are still done in cash, so even people with digital accounts need the ability to convert digital money into paper money quickly, and vice versa. But today, that’s extremely difficult to do with cryptocurrencies, particularly in rural areas. In addition, cryptocurrencies don’t solve the problem of identification; buyers and sellers would still need to be able to prove they are who they say they are.
When it comes to financial inclusion, the most important thing is to consider what poor people require. That means creating secure financial systems that identify who is making transactions, and that are interoperable, so that a person using one system can make transactions with someone on another system. It also means updating regulations so they protect consumers while encouraging innovation.
I’m excited about the great progress that’s documented in this year’s Findex. More people around the world, including more women and low-income people, have and use bank accounts than ever before. A lot of people are still excluded, but we have a roadmap that is feasible without billions of dollars of extra money to build systems that empower them. By following the roadmap, we can help them lift themselves out of poverty and make the world a fairer place.

Two countries, five days
Highlights of my trip to Nigeria and Ethiopia
A few photos from my latest visit to Africa.
I’ve just wrapped up a busy five-day trip to Ethiopia and Nigeria. It’s the kind of trip that’s both tiring and energizing at the same time. Even though I stay in touch with a lot of partners in both countries—the Gates Foundation has been funding work in them for more than 15 years—there’s nothing quite like visiting to see the work in action.
Whenever I get home from a trip like this, friends are curious to hear how it went. Here’s what I’m telling them. From 2000 to 2019 or so, Ethiopia and Nigeria led the way on dramatic improvements in health and poverty that rippled across Sub-Saharan Africa. Since then, the pandemic, extreme weather, and political and economic instability have set both countries back, along with much of the rest of the continent. But as I saw on this trip, there’s great work going on in both places that makes me optimistic about their future, and Africa’s.
I want to share a few photos from the week. Thanks to everyone who shared their time and insights with me, including Prime Minister Ahmed of Ethiopia, Nigerian health minister Muhammad Ali Pate, and a special guest who came along for the trip: the amazing musician Jon Batiste. The foundation will be working with African partners even more in the future, and based on what I saw this week, my next visit will be just as inspiring.

Production diary
Behind the scenes of my new Netflix series
I had a lot of fun filming What’s Next?, which you can watch now.
I've always thought of myself as a student trying to get to the bottom of things. A good day for me is one where I go to sleep with just a little bit more knowledge than I had when I woke up in the morning. So, when I am deciding how to spend my time these days, I usually ask myself three questions: Will I have fun? Will I make a difference? And will I learn something?
My new Netflix Series, What’s Next? The Future with Bill Gates, is out today. And when I think back on the process of working on it over the last two years, the answer to all three questions is a resounding “yes.”
I had an amazing time working with the super talented director, Morgan Neville. Morgan directed one my favorite documentaries, Best of Enemies, which is about Gore Vidal’s and William Buckley’s debates during the 1968 U.S. presidential election. Morgan also won an Oscar for his terrific film 20 Feet from Stardom.
As you might guess from the title, What’s Next? is a show about the future. I’m very fortunate to get to work on a number of interesting problems. Between fighting to reduce inequities through the Gates Foundation, leading Breakthrough Energy’s work on the climate crisis, and my continued engagement with Microsoft, I have a front seat to some of the biggest challenges facing us today.
I feel extremely grateful to have had the opportunity to work with and learn from some truly incredible people during the making of this show. (I’m hesitant to even use the word “work” because the process was so much fun!) My hope is that people watch What’s Next? and feel like they’re joining me on my learning journey.
Each episode focuses on a different challenge: artificial intelligence, climate change, misinformation, disease eradication, and income inequality. I sat down with some of the big thinkers and innovators who are pushing for progress. Some of them have different ideas than I do about how to tackle these challenges, and I loved getting to hear their perspectives. It was an eye-opening experience.
I got to have conversations on camera with familiar faces like Dr. Anthony Fauci, Open A.I. co-founder Greg Brockman, and the groundbreaking director James Cameron. And I made a lot of new friends as well—including an ingenious malaria researcher from Burkina Faso named Abdoulaye Diabaté, young climate activists who impressed me with their intelligence and passion, and an amazing group of people from across the Bay Area who overcame tremendous adversity in their path from poverty to stability.
There also were dozens of people who participated in the series with standalone interviews, like my friend Bono and the brilliant Mark Cuban—each of whom brings an inspiring and grounded view of the challenges we’re facing. My hope is that, together, we can combat the doomsday narratives that so often surround these issues.
It’s hard to pick which discussion I learned the most from. But three conversations will always stand out in my memory: the ones with Lady Gaga, Senator Bernie Sanders, and my younger daughter, Phoebe.
Going Gaga
I couldn’t help but feel a little nervous.
I was in Palm Desert, CA, preparing to have a filmed conversation with Lady Gaga for our episode about misinformation. Being around famous people doesn’t normally affect me. But I’m a big fan of A Star is Born—especially its music—and I was aware of her reputation as an outsized personality. I couldn’t wait to hear what she had to say.
Luckily, I had nothing to worry about. I was blown away by how thoughtful Gaga was. She made me laugh with the outrageous stories of how she’s been the subject of misinformation in the past—and inspired me with some of the ways she thinks about the topic.
In the early years of her career, one of the most persistent internet rumors about Gaga was that she was actually a man. It became so mainstream that reporters would ask about it during interviews. She refused to confirm or deny it. Instead, Gaga turned it back on the interviewer and asked, “Would it matter if I was?”
On the day of our Netflix conversation, I had been filming earlier with my two sisters, Kristi and Libby. So I asked them to come and watch the conversation between Lady Gaga and me.

Start spreading the news
Amazing stories I wish everyone knew
Meet some of the heroes who are fighting poverty and saving lives.
Have you ever heard a story that was so cool you couldn’t help telling everyone you met about it? Something you knew and wished that everyone else did too?
That’s how I feel about the people whose work I get to learn about through the Gates Foundation. Every day, around the world, they save lives and help people lift themselves out of poverty. Some are scientists. Others are educators, nurses, midwives, or advocates. Their work is so inspiring to me that I’ve committed virtually all of my wealth to supporting it.
When I see how much passion people like Josephine have for helping themselves and their neighbors, I’m inspired to help too. I hope these stories will be as inspiring for you as they are for me.

More than a job
For Eva Nangalo, saving mothers and babies is a calling
She’s a midwife, teacher, and advocate—and she’s changing childbirth in Uganda.
Officially, Uganda’s maternal mortality rate is double the global average. But because that number doesn’t count those who give birth at home—in a country where poverty, distance, stigma, and distrust are all barriers to medical care—Eva Nangalo believes the real one may be much higher.
That’s why, as a midwife determined to eliminate these deaths altogether, she’s spent the past 23 years working to make hospital deliveries both more safe and more common.
For Nangalo, this is more than a job. It’s her life’s work, and something she’s felt called to do for as long as she can remember. “I was created to be a midwife, born to be a midwife, trained to be a midwife,” she said. “It’s what is in my DNA. That’s what I am.”
Working the night shift at Nakaseke General Hospital in rural central Uganda and tending to her family’s farm while off the clock, Nangalo is known for sleeping maybe one or two hours, if that, a day. When the power goes out in the middle of a delivery—which happens often—she uses the flashlight on her cellphone to get the job done. She even keeps her hair short rather than style it the way she’d prefer.
In her own words: “I’ve wanted my hair to be like other women. But then I think of the one dollar saving a mother’s life.”
That isn’t theoretical. Nangalo regularly reaches into her own pockets to ensure that expecting mothers have the transportation they need to get to the hospital in the first place—and the food, milk, and medicine they and their babies need to survive not only childbirth but also what comes next. She once tore a piece of her own bedsheet to give to a mother who didn’t have one at home.
It’s no wonder she’s made a name for herself—literally—among the women she’s served, with many choosing to name their daughters after her.
Her advocacy efforts—and their effects—are broad and far-reaching. Understanding the fears and misconceptions that exist in Uganda around healthcare facilities, she uses the radio to reach skeptics and explain the merits of hospital deliveries and the higher risks of fatal infection and bleeding inherent to home births. She helped establish a newborn clinic in Nakaseke, improving the safety of childbirth at the hospital and increasing the number of families served. She even pushed the government to make good on its own policies and open a health facility in every sub-county.
It’s no exaggeration to say that Eva Nangalo is making childbirth in Uganda safer for everyone involved.
“The future looks bright,” one colleague said, “if we have more and more people like Eva.” Fortunately, she’s working to ensure that’s exactly what happens.

The worst tragedy
Why do children die?
The toughest question I’ve ever had to answer.
Twenty-five years ago, I encountered a question that I have thought about literally every day since: Why do children die?
Before I tell you what drew me to this mystery, I want to acknowledge that child mortality is not an easy subject to talk about. As a parent, I can’t imagine what it would be like to lose a child. It is shocking even to see the words “children” and “die” used in the same sentence.
But I think “why do children die?” is one of the most important questions ever. It is hard to think of a measure of how a society is doing that reveals more than whether it is protecting its children, and especially its most vulnerable children. And the better we understand why children die, the more we can do to save them.
The very good news is that the world has made phenomenal progress in this area over the past several decades. Since 1990, the number of children who die every year has fallen by more than half! If progress on child mortality is a good measure of the state of the world, then—despite the huge global setbacks of the past few years, including COVID-19—the state of the world has improved dramatically. And based on what I know about innovations that are still to come, we can look forward to even more progress in the years ahead.
My introduction to the subject came 25 years ago, when I read a New York Times article about the health problems caused by unsafe drinking water in low- and middle-income countries. I was shocked to learn that every year, 3.1 million people—nearly all of them children—died of diarrhea, often because they had drunk contaminated water. Diarrhea kills 3.1 million children?, I thought. That can’t be true, can it? But it was.
I had to know more. What other major inequities did I not know about?
I read everything about global health that I could find, and I spoke to as many experts as I could. I learned that researchers define child mortality as the death of anyone under the age of 5. They use that age because the first five years are the riskiest time of childhood, when kids are the most vulnerable.
Learning about the history of child mortality helped me put the statistics in context. In 1950, some 20 million children died. In 1990, it was down to 12 million children, even though more babies were being born. By 2000, the number had dropped to fewer than 10 million. By 2019, it was below 5 million. Virtually all of these deaths occur in low- and middle-income countries.
So the next question was, why were so many children dying?
Around 18 percent of the deaths were caused by non-communicable conditions, such as cancer and cardiovascular problems. The large majority—82 percent—of the deaths were caused by communicable diseases, such as diarrhea and malaria, and health problems that their mothers experienced—and exacerbated by risk factors including malnutrition. (This 18:82 ratio still holds true today.)
On one hand, this was heartbreaking. The worst killers were all things that people in rich countries considered just an unpleasant episode (such as diarrhea) or never experienced at all anymore (such as malaria). In other words, although it was obviously true that children were dying because of deadly diseases, that was only part of the explanation. They were also dying because of where they were born.
On the other hand, it was encouraging to learn that such a large share of the deaths was preventable. When I saw the breakdown of diseases, I thought: Here is our road map. This is what the Gates Foundation should be working on. With the right team, partners, and funding, we could help the world move through the list, systematically going after the worst killers. The solutions that already existed could be made more affordable and delivered to people in low-income countries. The ones that didn’t exist could be invented.
Here is the chart as it looks today:
As you can see, pneumonia is the top preventable cause, but the story here is one of real progress. In 2000, it took the lives of more than 1.5 million children, but by 2019, the number was around 670,000—still an awful number, but a reduction of more than 55 percent. The innovation related to pneumonia that’s going on today is so exciting that I made a separate post and video about it.
Diarrhea is another example of progress. In two decades, its death toll has dropped 58 percent. A key reason is the use of low-tech interventions like oral rehydration solution (sugar water, essentially), which replaces lost electrolytes. Governments also ran large-scale sanitation programs to cut down on the spread of bacteria. And scientists developed an affordable rotavirus vaccine, and the world came together to deliver it. Between 2010 and 2020, this vaccine prevented more than 200,000 deaths. By 2030, it will have prevented more than half a million deaths.
Even though the overall number of deaths has gone down by half, the relative positions of the top three killers have not changed. They are the same today as in 1990: neonatal disorders, pneumonia, and diarrheal diseases. As you can see in this graphic, the fourth slot is where there has been a huge shift. In 1990, it was occupied by measles, responsible for half a million deaths. Today, it’s malaria that is in the fourth slot—not because malaria deaths went up (they actually went down), but because measles deaths fell by a whopping 87 percent.
Why? Vaccines. Since 2000, Gavi, the Vaccine Alliance has provided measles vaccines to more than 500 million children—half a billion!—through routine immunization and special vaccination campaigns. (This is just one example of the magic of vaccines—although unfortunately vaccination rates have dropped because of the pandemic and other factors.) And malaria may not be #4 on that list for long, thanks to innovations like malaria vaccines, improved insecticide-treated bed nets, and sugar baits.
Many groups deserve credit for the decades of progress I’ve described in this post. Countries with high disease burdens have launched massive vaccination campaigns, strengthened their health systems, and shared best practices with each other. Wealthy countries generously give aid that supports these efforts. Pharmaceutical companies have contributed technical expertise and made products affordable for low- and middle-income countries. Foundations including the Gates Foundation have stepped up with additional funding for innovative ideas. (At the foundation, we have staff and partners dedicated to each slice of the pie you see above.)
Although it’s still true that too many children do not live to see their fifth birthday, the world is moving in the right direction. If everyone keeps doing their part, we can move even faster and save even more lives. Because of COVID and other setbacks, the United Nations’ goal to cut childhood deaths in half again to below 3 million by 2030 will be missed, but it can still be achieved the following decade.
At a time when war and pandemic are in the news every day, it is important to look for reasons to be hopeful. The world’s opportunity—and ability—to save children’s lives is surely one of those reasons.

Bad air
A big threat to malaria eradication
Climate change could stall the world’s amazing progress on health.
It’s mind-blowing how much health has improved for the world’s poorest people over the past two decades. Malaria deaths, for example, have dropped by more than a third. Eradicating the disease has become a realistic goal.
Unfortunately, climate change threatens to slow or even reverse this progress. As temperatures go up and extreme weather events become more common, it will get harder to do things like provide bed nets, get rid of malaria-carrying mosquitoes, and offer basic health care in the world’s most vulnerable communities.
I’m optimistic that the world can avoid a climate disaster. But that effort can’t come at the expense of continuing progress on health care including malaria efforts.
If we fight only climate change and stop working on health, then we might reduce carbon emissions but allow malaria to make a comeback. Eradication would become even harder. No one will be better off in a world with fewer carbon emissions but more illness and death.
In this video, I talk more about the connection between climate change and malaria and explain why I’m optimistic that we can solve both problems.

The life of Neandersquito
This scientist uses old insects to help fight malaria
Mara Lawniczak has an ingenious approach to studying mosquito evolution.
Of all the things I thought would help fight malaria, 100-year-old mosquitoes would not have been high on the list. Then I learned about the work of Dr. Mara Lawniczak.
An evolutionary geneticist at the Wellcome Sanger Institute in the United Kingdom, Mara has spent much of her career trying to understand how the genomes of various mosquito species have changed in response to humans’ attempts to kill them. When, where, and how fast has it happened? What does that say about how they might evolve in the future?
In recent years, genetics has become an increasingly important tool for fighting malaria. Because mosquitoes breed so fast (a female can lay thousands of eggs in her lifespan of a couple of weeks), they evolve rapidly, at least compared to humans. By studying their genes, researchers are able to understand things like how they develop resistance to insecticides, crucial information that helps humans stay one step ahead.
After a few years of studying mosquitoes’ genomes, Mara had grown frustrated by the fact that the only insects available for study were ones that had been captured recently. Without DNA from their ancestors, there was no way to know how their genomes had responded to decades of human attacks. “We were often saying, ‘If only we could look into the past,’” Mara says. “And then it suddenly struck me: I'm sure there are historical collections of mosquitoes around.”
She was right. The Natural History Museum in London has a collection of 34 million insects from all over the world, carefully collected and preserved. Among the collection is a large sample of mosquitoes dating from 1936, when a British entomologist named H.S. Leeson spent a year in East Africa capturing and cataloguing the insects in the hope of learning more about malaria. Leeson didn’t know it at the time—DNA wouldn’t be discovered until the 1950s—but his collection of mosquitoes would become a vast source of genetic material that someone like Mara could study.
Mara reached out to the museum’s curators. They wanted to help, but there was a problem: Extracting DNA from the insects would require Mara to grind them up. Since the museum’s mission is to preserve its collection for future generations, they couldn’t let her do that.
So Mara and her colleagues invented a way around the problem. Working with the museum’s team, they developed a novel way to extract DNA from mosquitoes without damaging the specimen.
They affectionately call this work Project Neandersquito. It’s not because the mosquitoes date from the time of Neanderthals, some 40,000 years ago—this isn’t Jurassic Park, where they extract dinosaur DNA from a prehistoric mosquito trapped in amber. It’s because the mosquitoes they’re studying are 1,000 or 2,000 generations removed from modern ones, just as Neanderthals are more than 1,000 generations removed from modern humans.
Mara’s team has made some surprising finds. For example, because mosquitoes started developing resistance to the insecticide DDT in the 1950s, they expected to see genetic mutations for resistance appearing around the same time. But they didn’t. “We still don't see them even as late as the 1980s,” she says. “So the mosquitoes were somehow making themselves resistant to DDT in ways that we still don't really understand.”
They also hope to get insight into what's coming. “How fast can mosquitoes evolve? And as we throw new control initiatives at them, how quickly are they going to get around them?” Other labs are now using the process devised by the Lawniczak Group to do their own research.
Project Neandersquito is just one of the ways Mara and her team are using genomics to advance the fight against malaria. A different project, the Malaria Cell Atlas, is providing new genetic data that could inform the effort to make better malaria drugs and vaccines. Another project is designed to make it easier and cheaper to identify a mosquito’s species using its DNA—it’s surprisingly hard to do just by looking—as well as whether it’s carrying the parasite that causes malaria, and even which species of the parasite it has. Ultimately, the project’s goal is to help governments get data that will help them get the most out of their anti-malaria efforts.
Mara would be the first to say that these are just a few examples of the tools the world needs to eradicate malaria. It’s going to take global cooperation from governments, the private sector, and academia. And now we can add natural history museums to the list.

Urban invader
The world’s newest weapon against malaria? Mosquitoes
A city-dwelling mosquito threatening Africa sparks innovation in the fight against malaria.
About 10 years ago, the African country of Djibouti had nearly succeeded in wiping out malaria. The country’s leaders hoped that getting rid of the disease would help them attract new investment, development, and tourism.
Then suddenly the disease roared back. Cases surged from just 27 in 2012, to more than 73,000 in 2020—a huge number for this East African nation of just one million people.
The cause?
A highly invasive mosquito that had migrated from South Asia and the Arabian Peninsula into Africa.
This pest—the Anopheles stephensi mosquito—has now emerged as one of the biggest threats to malaria elimination in sub-Saharan Africa. Since establishing a beachhead in Djibouti, An. stephensi mosquitoes have been detected in Ethiopia, Sudan, Somalia, Kenya and as far away as Nigeria and Ghana, in West Africa. According to one study, if this mosquito is left unchecked an additional 126 million people on the continent will be at risk of malaria.
What makes An. stephensi particularly dangerous is where it has chosen to reside. Unlike other malaria-carrying mosquitoes in Africa that primarily breed in rural areas, An. stephensi thrives in urban environments. Cities are already home to 40 percent of the population in sub-Saharan Africa and continue to experience rapid growth, creating a fertile habitat for this mosquito. Making matters worse, An. stephensi has been found to be resistant to many of the insecticides used to control mosquito populations. And they bite in the evening before bedtime—not in the middle of the night like other mosquitoes—making bed nets less effective as protection.
But this story doesn’t end here.
In 2018, the government of Djibouti, in search for a new approach to combat these urban invaders, heard about a biotechnology company called Oxitec that has a potentially game-changing solution to mosquito control.
The fight against mosquitoes and the diseases they carry has always been a game of cat and mouse. Humans develop new interventions—like bed nets, insecticides, and treatments—to protect themselves from mosquitoes. Mosquitoes, meanwhile, have an incredible capacity to adapt, allowing them to eventually dodge or develop resistance to the latest control methods. Then humans respond with more innovations to outsmart the mosquitoes. And so on.
Oxitec, however, aims to change this game from cat versus mouse to mouse versus mouse. Or in this case, mosquito versus mosquito. Oxitec specializes in using mosquitoes to fight other mosquitoes. With its genetic technology, Oxitec has already developed mosquitoes to effectively combat the dengue fever–carrying mosquito, Aedes aegypti, in Brazil. Now Oxitec plans to use the same technology to help African governments control An. stephensi and reduce the spread of malaria.
Here’s how Oxitec’s technology would work against An. stephensi mosquitoes: Oxitec male mosquitoes carry a special gene to prevent their female offspring from surviving into adulthood. (Only female mosquitoes bite and spread malaria.) Released into the wild, the male Oxitec mosquitoes mate with wild female mosquitoes. All the female offspring die. All the male progeny, which don’t bite, will survive and go on to mate with other wild females. With sustained releases of male Oxitec mosquitoes, more females die off, dramatically reducing the mosquito population and the spread of malaria. After the mosquito releases stop, however, because half of the gene’s carriers (the females) cannot survive, the gene steadily declines and disappears from the mosquito population within a few generations.
Genetic technology like Oxitec’s understandably raises many questions. Is it safe? What are the lasting environmental impacts? Here’s what’s important to know:
Because it’s passed through mating, the gene the Oxitec male mosquitoes carry only targets the An. stephensi mosquitoes. It doesn’t have any impact on other insects and cannot be established in the local ecosystem. After evaluating the potential risk of genetically modified mosquitoes, the U.S. Food and Drug Administration in 2016 and the EPA in 2022 have confirmed that the Oxitec mosquitoes do not pose a threat to humans or the environment. More than one billion Oxitec mosquitoes have been released worldwide, with no negative impacts. In Brazil, the Oxitec Aedes aegypti mosquitoes have been so successful in reducing the spread of dengue fever that they are in demand by communities, governments, and businesses in Brazil. Homeowners can even buy a kit to raise the mosquitoes in their own backyards. (If you want to learn more about this technology, I encourage you to visit the Oxitec website and the Centers for Disease Control and Prevention.)
Last year, the government of Djibouti formed a partnership with Oxitec, Association Mutualis (a non-profit public health organization in Djibouti), and the Djibouti National Malaria Control Programme to use this new technology to defeat An. stephensi.
No Oxitec mosquitoes have been released in Djibouti during the current pilot phase of the project. But the government of Djibouti expects to move forward with the first releases of Oxitec mosquitoes next year in Djibouti’s capital city, where 70 percent of the population live.
This solution is being pursued with the support of the people of Djibouti. The government of Djibouti, Oxitec, and its local partners have been working together to educate and engage the public about this technology, going door to door to listen to their concerns, and ensuring all the communities’ questions have been addressed before moving forward with the release of the mosquitoes. Local support has been outstanding to date.
To end malaria, we need many new tools and innovations to reduce the burden of this disease and move the world closer to eradication. I’m excited about the potential of Oxitec’s technology to help Djibouti and the rest of Africa achieve this goal.

Welcome to Mosquito City
It’s always buzzing in Mosquito City
A city where researchers study how to repel, attract, and kill the world’s deadliest animal.
When’s the best time to kill mosquitoes?
While they’re making love—at sunset.
No kidding.
This is just one of many fascinating discoveries being made at a place called Mosquito City. Located in the swamplands of central Tanzania, the “city” is home to the world’s largest captive colony of mosquitoes used for researching ways to combat malaria and other mosquito-borne diseases. Day and night scientists work to better understand mosquito behavior (like when and where they enjoy having sex) as well as cutting-edge approaches to trap, repel, and most importantly, kill them.
I first learned about Mosquito City during a trip to Africa several years ago when I met scientists from Ifakara Health Institute, a Tanzanian health research organization which runs the site. While I haven’t had the opportunity to visit, Fredros Okumu, Ifakara’s chief scientist, offered a behind-the-scenes look at some of the research underway there in this video. If you’re wondering how they get enough blood to feed all the mosquitoes, watch for the moment when Fredros puts his arm in a cage containing more than 500 very hungry mosquitoes for a feed! (For larger mosquito colonies, too big for one human to feed, a cow is on the mosquitoes’ dinner menu.)
Mosquito City is located in a region of Tanzania that’s hot, humid, and swampy. In other words—perfect conditions for its primary residents. Malaria has been so widespread in this part of the country—once infecting 80 percent of the population—that one meaning of the name of the local town, Ifakara, is, “the place people go to die.”
Fortunately, malaria deaths are on the decline in recent years. One reason is the use of insecticide-treated bed nets, which remain one of the most effective means to control the disease. (New bed net distribution efforts like the one that just launched in Benin are helping to ensure every person at risk of malaria is protected by one.)
Still, much more needs to be done to fight the disease, especially as mosquitoes become resistant to some of the pesticides used to control them. That’s why scientists at Mosquito City are working to better understand mosquito behaviors and find ways to outsmart them.
“It's kind of a love- hate relationship. If you can't beat them, you join them for now, but then you can kill them from the inside. And that's what we try to do here at the Mosquito City,” Fredros says.
Fredros and his team are studying one of the deadliest mosquito species, Anopheles funestus. In southeastern Tanzania, it is responsible for nearly 9 out of every 10 cases of malaria even though other species of mosquito are far more common. And yet, it is one of the least understood species of mosquitoes because it is difficult to raise in a lab environment. Our foundation is supporting the Ifakara Health Institute’s research into its behavior so they can mount a targeted campaign against them.
One promising approach may be killing them while they are mating. Ifakara scientists learned that mosquitoes, including Anopheles funestus, have favorite locations—like rice fields, trash heaps, and banana trees—to mate. The male mosquitoes appear at their favorite mating spots at sunset to begin a ritualistic flight dance, drawing in the females. Because these mating events occur at predictable times and locations, researchers are experimenting with regularly targeting these swarms with pesticides, dramatically reducing the mosquito populations and malaria transmission.
As the researchers dig deeper into the unique characteristics of different mosquito species, it’s become more important to be able to quickly identify them. Once they understand which species is posing the greatest threat, they can choose the best methods to eliminate them. But identifying mosquito species and other indicators, like age, can be a laborious process. At Mosquito City, scientists are working on some alternative identification approaches that would accelerate their research. One is to use their buzzing sound to identify them. Another option uses infrared spectroscopy. Mosquitoes have a unique electromagnetic signal. By crushing the abdomens of mosquitoes and analyzing them under a spectrometer, researchers can identify the species and age of the mosquito.
Many of the innovations coming out of Mosquito City are designed to meet the immediate needs of the local community, who work in small farming villages and spend most of their day outdoors. Researchers have developed a variety of mosquito traps, some mimicking the odor of sweaty feet, a smell that mosquitoes find irresistible. They’ve created a range of mosquito repellents too, including furniture treated with repellent that allows people to sit outside in the evening and stay protected. They’ve even developed a line of sandals which will keep mosquitoes at bay from the sweatiest feet, protecting their owner from bites.
What will the team at Mosquito City think of next? I can’t wait to find out.

The nose knows
Could perfume be our secret weapon in the war on mosquitoes?
Mosquitoes use their sense of smell to find new victims. A Swiss fragrance company is hoping to thwart them.
Are you a mosquito magnet? If you don’t seem to get your unfair share of mosquito bites every summer, chances are you know someone who does. Some people are just more attractive to the pests than others.
The reason why is probably how you smell. Mosquitoes rely on their sense of smell to find their targets, and they’re drawn to certain odors naturally produced by the human body. Although some people may be a little more attractive, the unfortunate truth is that we all smell like a delicious meal to mosquitoes. You can hide yourself for a while using a bug spray like DEET or treating your clothes with permethrin. But if you want sustained protection, you have to add another step to your routine, which not everyone has the time to do or can afford.
There’s good news on the horizon, though: A company called dsm-firmenich is working to make repelling mosquitoes as easy as washing up in the morning.
I actually visited dsm-firmenich’s lab in Geneva back in 2016, when I checked out their innovative work to improve sanitation for the world’s poorest by reducing toilet odors. The nutrition, beauty, and health company is one of the world’s largest manufacturers of flavors and fragrances. Most of their products are used to make our food taste better and our household products smell more appealing, but they also have a history of using their scent expertise to fight disease transmission. Their latest efforts are focused on stopping mosquitoes, because the diseases they carry kill hundreds of thousands of people each year, most of whom are children in low-income countries.
The team’s goal is simple: Incorporate scents that repel mosquitoes into everyday products. After doing extensive research into the household products used most frequently in places where mosquito-borne diseases are common, they decided to focus mostly on bar soap and powdered laundry detergent. (They’re also thinking about other things like body lotion and body cream.) These products are already scented with a fragrance—what if that fragrance also helped keep mosquitoes away?
The idea is that you gain an added halo of protection without having to add any new steps to your daily routine or buy any new products. No one at dsm-firmenich thinks this kind of protection will be a silver bullet, but their hope is that, when combined with other proven tools like bed nets, people can significantly and sustainably lower their risk of catching deadly diseases like malaria and dengue.
Making a bar soap that gives you all-day protection against mosquitoes is a lot more complex than just infusing it with citronella. The scientists in Geneva started by identifying a wide array of scent ingredients that keep the pests away and are commonly used to create perfumes. Some of these ingredients are true repellants, giving off a smell that causes mosquitoes to fly in the opposite direction. Others block receptors in the mosquito’s brain that usually perceive and draw them to humans.
As they were combining the ingredients to create new fragrances, the team knew they had to keep a human-centered design approach in mind. The best candidates wouldn’t necessarily be the most effective—they also had to smell clean and fresh. I love the smell of cheeseburgers, but I don’t think I’d want my laundry to smell like them every day even if they protected me from mosquitoes!
To test the most promising odors, researchers used a tool I know all too well: The arm-in-cage test, where a human puts their arm—which has been coated in the fragrance being studied—into an enclosed area filled with hundreds of mosquitoes. Sensors track how the mosquitoes respond and whether they’re biting the arm. The team considered any test with two mosquito bites a failure.
Behavioral tests like those being done in collaboration with the Swiss Tropical and Public Health Institute are still ongoing, but they’ve already revealed some surprising results. One of the most effective fragrances so far smells like lily-of-the-valley, a light floral scent that is commonly used in perfumery. It’s exactly the kind of fresh scent that people like in their soaps and laundry detergents. The team’s early results indicate that some lily-of-the-valley odors could be as effective as DEET when used at certain doses.
The next step is the most difficult, and it remains to be seen whether it will succeed. The mosquito experts at dsm-firmenich have handed off the best scent candidates to the company’s product formulation experts and perfumers, who are now looking for ways to make them last all day in consumer products.
It’s a tall order. Scent ingredients are fragile, and activities like scrubbing your hands or washing your clothes cause them to vanish quickly. (Think about how quickly that freshly laundered smell can fade from your clothes.) A perfume that protects you from mosquitoes all day will likely end up being the result of a whole lot of innovation and a complex combination of different scents, rather than one single ingredient. And, of course, the final result has to smell good enough that people are willing to use it every day.
Still, I’m optimistic the scent wizards in Geneva will find a way. The Gates Foundation is supporting their research with the hope that, one day, people in high-risk areas will gain more mosquito protection without having to do any extra work or spend any extra money. When the world gives children and families more tools to protect themselves, we save lives—and take the bite out of the world’s deadliest animal.

Sweet dreams
Sugar Fix
Mosquitoes love blood, but did you know they have an even bigger sweet tooth?
Everyone knows mosquitoes have a taste for blood, but did you know they have an even bigger sweet tooth?
Mosquitoes love sugar.
Just as humans are drawn to the sweet smell of a chocolate shop or bakery, mosquitoes find the smell of sugar irresistible.
All mosquitoes need sugar to survive. Female mosquitoes consume blood to lay eggs, but both male and female mosquitoes require sugar for energy. In fact, even though mosquitoes buzzing in your ears may appear single-minded about biting you, they need sugar more often than they need blood.
Exploiting this craving, researchers have developed a lethal new tool to kill mosquitoes and protect people living in areas at high risk for malaria and other mosquito-borne diseases.
Here’s how it works: In nature, mosquitoes get sugar from flower nectar and plants. But scientists have developed a tempting bait that lures mosquitoes with a highly attractive fruit scent. When they land on it to get their sugar fix, the mosquitoes begin feasting on a sweet meal laced with insecticide. Not long after, they drop dead, reducing mosquito populations and, researchers hope, the spread of malaria in the communities where the traps are used.
While other insects, like bees and butterflies, may also be drawn to the bait’s sweet scent, the bait is just lethal for mosquitoes. A protective membrane, only accessible to mosquitoes, covers the bait and prevents other insects from feasting on the deadly meal inside.
This new mosquito control tool, called Attractive Targeted Sugar Baits or ATSBs, developed by Westham Co., is simple to use, affordable, and has the potential to be a game changer in the effort to eradicate malaria.
And it couldn’t arrive soon enough.
Over the past two decades, the world has dramatically reduced the global burden of malaria, preventing 1.7 billion cases and saving 10.6 million lives. This progress has been attributed, in large part, to the widescale use of long-lasting insecticide-treated bed nets, which protect people from bites while they sleep, and indoor residual spraying, which kills mosquitoes that land on insecticide-treated walls and ceilings in homes.
As effective as these tools have been, both mosquitoes and the malaria parasite are constantly evolving, sometimes making these interventions less effective. We’ve seen this again and again with resistance to insecticides and malaria drugs. And that’s why it’s critical that the world continues to innovate with new ways to prevent the spread of malaria.
In response to the widespread use of bed nets and indoor insecticide spraying, mosquitoes have changed their behaviors, according to some researchers. In some areas, instead of seeking their blood meals only inside homes after bedtime, malaria-carrying mosquitoes are now biting outside homes, and earlier in the evening, when people will often cook and socialize.
And this is how the sugar baits fit in.
By attracting mosquitoes outside, sugar baits offer a highly effective mosquito control tool for households. About the size of a sheet of notebook paper, sugar baits can be easily installed with a hammer and a nail. Two baits hung on the adjacent outside walls of a home are enough to offer months of protection.
In studies conducted in Mali in 2016 and 2017 researchers found that the sugar baits dramatically reduced mosquito populations and malaria cases in the communities where they were used.
A more recent modeling analysis predicted that sugar baits, when used to complement long-lasting insecticide-treated bed nets and indoor spraying, could reduce malaria cases by 30 percent in areas with high malaria burdens.
In 2020, there were an estimated 241 million malaria cases. A 30 percent reduction in malaria cases would be a huge breakthrough and save many lives.
That’s why our foundation has been supporting the development of sugar baits, including sponsoring a large-scale field trial currently underway in Kenya, Mali, and Zambia. So far, the results have confirmed the effectiveness of the bait stations.
If all goes well with the trials, sugar baits could be available for widespread use as soon as next year.
No need to sugarcoat it. For the millions of people at risk of malaria around the world, that would be welcome news.

Benin in front
Full coverage: Bed nets for Benin
Its bed net distribution system will help save lives from malaria and other diseases too.
If you’ve ever traveled to a part of the world where there’s a risk of malaria or other mosquito-borne disease, you probably slept under a mosquito net.
The gauzy fabric creates a physical barrier that protects you from mosquitoes. At the same time, you serve as bait in a deadly trap. Treated with potent insecticides, the net kills mosquitoes that land on it during their futile efforts to bite you.
It’s a remarkably simple tool, but it’s proven to be one of the most effective weapons we have against malaria. Increased bed net use is largely responsible for the more than 50 percent drop in malaria deaths worldwide since 2000.
Still, more needs to be done to ensure that communities at highest risk of malaria have access to them.
That’s why I’m excited that the government of Benin this year launched a new, innovative approach to distributing bed nets to their population.
Using smartphones, real time data collection, satellite mapping and other surveillance techniques, Benin’s distribution program will give health officials the data they need to provide full bed net coverage to the country.
Benin is faced with one of the highest burdens of malaria in the world. The West African country of nearly 12 million people has about 2 million cases each year. If successful, this new bed net distribution effort will save thousands of lives and serve as a blueprint for other high burden malaria countries to follow.
As you might imagine, distributing bed nets to every household is a massive logistical effort involving thousands of people—from truck drivers to health workers. And the job is made even harder in Benin where exact population numbers are uncertain.
For many years, Benin’s distribution campaigns were run with pencil and paper systems. Health officials used thick ledgers to keep track of the names and addresses of residents and how many beds nets they needed. It was time-consuming and often inaccurate. No one knew exactly how many nets would be needed or if they reached their intended destinations. As a result, many families were missed during the distribution, putting them at higher risk of malaria because they lacked the protection of a bed net.
But this year’s distribution is different. In partnership with Catholic Relief Services and our foundation, Benin’s national malaria program created a new, digitized distribution system that is more accurate and efficient in getting bed nets into the homes of all households in the country.
In many ways, this effort is based on the lessons the global health community has learned in the fight against polio. As vaccinators sought to immunize every child against polio in India and Nigeria, they would sometimes miss households, especially in remote areas. But with satellite mapping and better data collection, health workers were able to quickly identify gaps in vaccination coverage and reach every home.
Benin’s new bed net distribution operates in much the same way. Walking door to door, health workers make home visits throughout the country and perform a brief census: the number of people living there, including number of children and pregnant women, number of bed nets needed, etc. Using cell phones, they enter this information into a database. They also give each household a uniquely coded voucher to redeem at a nearby distribution center where they can collect their bed nets.
On the distribution day, people come to collect their nets and get lessons on the proper way to set up and care for them. As people arrive to redeem their vouchers for the nets, the malaria team has real time data on which households have received their nets and which ones have not. This data—which can be reviewed on a digital map—allows the malaria team to quickly identify any problems with their delivery system. It also gives health workers detailed information about which households need to be targeted for follow up to ensure they all have nets.
I admit none of what I’ve just described may sound that revolutionary. But in global health, I’ve learned again and again that saving lives is the result of getting the smallest details—from the temperature of a vaccine to the address of a beneficiary—right. And Benin’s new digitized bed net distribution program does just that by giving the government a powerful tool to manage a complex job.
And with this new digital distribution system in place, Benin can use it as a platform to manage other big health campaigns—like vaccinating against meningitis and door-to-door efforts to eliminate neglected tropical diseases.
I’m looking forward to hearing more about Benin’s progress in the fight against malaria and other diseases because of this new system—and I hope other countries will learn from their success.
Trip photos
I found inspiration in India
Here are a few pictures from my latest visit to this amazing country.
Around this time last year, I wrote a Gates Notes post that began: “I just returned from my visit to India, and I can’t wait to go back again.”
Last week, I got my wish and returned to India—and now that I’m home, I can’t wait to go back for another visit.
My goal was to get an update on some of the world-changing ideas and inventions that are coming out of India, and that’s exactly what I got. I spent four days there, meeting with political leaders, government officials, scientists, philanthropists, women who are lifting their communities out of poverty, and many others. The Gates Foundation funds more work in India than in any other country (other than the United States), and it’s always uplifting and educational to be there in person and see the impact of the efforts we’re supporting. Here are a few photos from my visit.

Ancient country, new ideas
India’s innovations are still changing the world
I’m excited to see the latest breakthroughs during my visit this week.
I’ve been visiting India since the 1990s, and I’m on my way to visit again this week. Over the years, I’ve learned about its rich history and visited some of its stunning monuments, including the Taj Mahal.
But when I think about India’s most important contributions to the world, these are not the first things that come to mind. India’s greatest gift is its ability to innovate.
This country has a long history of important breakthroughs. (Mathematicians in ancient India are widely credited with introducing the decimal system for numbers.) More recently, India has made advances that are saving and improving millions of lives in India and around the world. The Gates Foundation has been a partner in some of these efforts, and I’m visiting this week to learn about how we can continue working with India to help its ideas and inventions reach everyone who needs them, no matter where they live. This will be a main topic when I meet with Prime Minister Modi this week.
Health is one area where India is making a big difference. This country is the world's largest producer of vaccines—it supplies more than 60 percent of all vaccines distributed by Gavi, the organization that has helped vaccinate more than 1 billion children in lower-income countries. Indian companies pioneered the creation of high-quality, low-cost vaccines and drugs, leading the world in making affordable treatments for diseases like HIV/AIDS as well as vaccines for rotavirus, pneumococcal pneumonia, and COVID. The government has helped deliver huge supplies of vaccines to its own people and to other low- and middle-income countries, and now it’s looking to do the same for medical devices and diagnostics.
Thanks in large part to India, developing countries now get new medicines and vaccines much faster than they used to. I rank these efforts as one of the most important health achievements ever. (We’ve made progress, but we’re not done. The world should still do more to shrink the gap between when a drug or vaccine becomes available in rich countries and when it reaches lower-income ones.)
Another area where I admire India’s innovative spirit is what’s known as digital public infrastructure, or DPI. In short, DPI refers to the digital platforms and tools that help deliver various services. India’s biometric identity program, Aadhaar, covers more than 1.4 billion people, allowing them to take advantage of all kinds of government services without needing a photo ID. UPI, a digital payment system that ensures that the person you’re doing business with is who they say they are, processes more than 12 billion transactions a month.
During my trip I’ll get to see India’s DPI in action. I’ll visit an agricultural monitoring center in the state of Odisha where government officials use DPI to give farmers real-time guidance. Thanks to Aadhaar, this center is able to maintain a registry of 7.5 million farmers—even if they don’t own land—and their crops, so officials can keep track of who is growing what (and, therefore, what kind of farming advice they need). It has also developed a chatbot that makes it easy for farmers to get the latest information about their crops, using AI to tailor content to their particular needs and in their local language.
This service’s pest-management program now reaches more than 4 million farmers, and since it began in 2018, the volume of crops that participating farmers lose to pests every year has dropped by 90 percent. Now others—including other states in India as well as Ethiopia, Sri Lanka, and the World Bank—are looking to learn from Odisha’s experience with this service as well as its biometric ID and digital payments systems.
I'm also looking forward to learning more about how India is addressing urban poverty, especially among women. It has one of the fastest-growing urban populations in the world, and more than 100 million people there live in slums, where it’s hard and often impossible to get even basic services like health, education, and clean water. Women are particularly vulnerable because they face discrimination and violence.
This week, I’ll visit a low-income community in Odisha where a government program is helping women get the skills to fulfill government construction contracts. Since 2018, this program has helped 22,000 groups of women deliver on more than 52,000 projects including building roads, drains, and toilets.
This program could be a model for other countries that are facing similar challenges. The women who participate in it are partners in creating the projects: They get training in engineering, accounting, negotiating contracts, and other skills, and they’re involved in planning the project, making a budget, doing the construction, and doing maintenance on whatever they build. I'm looking forward to meeting a few women who are part of this program so I can hear about the challenges they face and the successes they’ve had.
India’s capacity to innovate will also become increasingly important to stopping climate change. Indians are already being affected by higher temperatures and less-predictable weather, and eliminating the greenhouse gases that are causing the problem is a huge scientific challenge. So it’s great that India is ramping up its ability to invent, manufacture, and deploy climate breakthroughs. The government is investing in research to raise the productivity of crops and livestock even in a warmer climate, and it’s expanding its plans for clean energy.
These are just a few of the ways in which India's innovations are changing the world. I could list many more, and I’m sure I’ll learn about a few new ones during my visit. I’m looking forward to speaking with government leaders, CEOs, and students who will drive innovation in India. This country has a lot to offer, and I'm optimistic that it will continue to lead the way in creating a more equitable world.


Exemplary
Lessons in lifesaving from Brazil
What the biggest country in South America can teach the world about healthcare.
I’ve been a big fan of Brazil for a while. I first visited back in 1995 when Microsoft was building out our operations there, including working with one of the national banks to launch home banking. And some of my favorite family trips have been to the Amazon, whose river, basin, and rainforest come up often during conversations on climate change. But it wasn’t until I began working in public health that I started appreciating just how impressive the country’s track record in this area is—and how much the rest of the world could learn from it.
In roughly three decades, Brazil has cut maternal mortality by nearly 60 percent, slashed under-five child mortality by 75 percent—far outpacing global trends—and increased life expectancy by almost a decade. None of these achievements was accidental. Instead, they’re the result of long-term, laser-focused investments Brazil has made in its primary healthcare system that other countries can learn from and emulate.
The story starts in the late 1980s. Two decades under military dictatorship had turned Brazil into one of the least equitable countries in the world. In 1985, the country became a democracy; a few years later, it created a universal health system.
In the decade that followed, deaths from non-communicable diseases and maternal, neonatal, and nutritional causes all started to decline, and life expectancy rose. With an increase in primary healthcare services, even hospitalizations dropped.
But it’s one thing to guarantee healthcare. It’s another thing to fund it—and another thing entirely to make sure it reaches the people who need it most. While Brazil had been making progress, there was much more to do. So at the turn of the century, the government accelerated its efforts and took steps to close the gaps in its healthcare system, including a dramatic increase in healthcare spending. One of the most important steps was massively expanding the size and scope of its community health worker (CHW) program.
Community health workers are trained public health professionals who work within communities, especially in remote or underserved areas. While their roles vary around the world based on local needs, they generally include things like disease tracking, vaccine drives, and basic health screenings.
In Brazil, CHWs had already shown they could improve public health access and outcomes during a pilot program in the Ceara state. As federal funding for primary healthcare increased, almost fivefold in fifteen years, the ratio of CHWs tripled.
Today, Brazil has over 286,000 CHWs who serve almost two thirds of the population—almost 160 million people. Each one visits about 100-150 households a month, offering guidance on health and hygiene, advocating for preventive care, following up after medical appointments, collecting socioeconomic data, and helping people navigate other government services.
In Brazil, CHWs act as the front door to the world’s largest universal free public healthcare system, and their impact has been transformative. They’re credited with further cutting child mortality and pushing immunization coverage to near-universal levels. (Unfortunately, the pandemic impacted vaccination rates, but there are efforts underway to bring them back up.)
The country’s Bolsa Familia program—which provides cash transfers to poor families if they meet certain conditions, including vaccination for children and prenatal care—deserves credit too. Expanded in tandem with primary healthcare, Bolsa Familia is just one of the many social programs Brazil has built out over the past few decades that have helped lift almost a fifth of the country’s population out of poverty. But it’s also helped broaden healthcare access and usage by giving people an incentive to enter the healthcare system—which is how Bolsa Familia has contributed to reductions in child mortality as well.
I’ve been able to learn about these initiatives through the Gates Foundation's partnership with Brazil's Ministry of Health—which has focused on combatting malaria, improving vaccine production, leveraging local brainpower to address global health issues, and documenting the impact of social and health programs through data sciences. And I’ve been really impressed.
Of course, despite all the progress that’s been made in recent decades, Brazil still faces challenges. Financial crises and austerity budgets have led to cuts in healthcare spending, for example, and there are still districts where poorer residents have no access to CHWs.
But Brazil’s healthcare system doesn’t have to be perfect to serve as proof of what happens when a country invests strategically in care for its most vulnerable: The returns are often far-reaching and life-changing.
That is why Brazil is highlighted by the Exemplars in Global Health program, which I helped launch in 2020. The program's mission is to identify countries that have made remarkable progress on health problems, understand the keys to their success, and share those insights globally so others can make similar progress. By that standard, Brazil has a lot to teach.
That’s not to say any country can or should replicate Brazil’s approach exactly, since no two countries are alike. But with the right mix of investment and innovation, Brazil has made great strides in becoming a healthier place for its people. If the country continues on that path and keeps doing what it’s done well already, and if other countries follow—or simply forge their own paths with Brazil in mind—we’ll have a healthier world, too.

Rise to the challenge
5 of the coolest innovations I saw in Senegal
I got to meet with amazing scientists working on the next big breakthrough while I was in Dakar.
I had an amazing trip to Senegal last month. I always love getting the chance to travel and see the remarkable work the foundation’s partners are doing firsthand. These visits leave me more energized than ever to go to work every day—and my time in Senegal was no exception.
Senegal is a particularly interesting country to visit, because it has made exemplary progress improving the health of its people thanks to a focus on community-led care and many years of smart policymaking. Some of the statistics are mind-blowing: Since 1992, the country has cut its stunting rate in half. Since 2000, the number of Senegalese children who die before their 5th birthday has dropped by 70 percent. And since 2005, the number of women giving birth in health facilities has increased from 62 percent to 80 percent. It’s the perfect place to talk about progress.
One of the highlights of my visit was a trip to the Institut Pasteur de Dakar, or IPD—a research center that has been pushing the frontiers of global health for nearly a century. The facility does it all: IPD plays a key role in monitoring for disease outbreaks in the region; produces millions of diagnostics every year; serves as an educational hub for the next generation of health workers and biomanufacturing workers; and will soon resume manufacturing vaccines.
It was inspiring to meet with brilliant Senegalese scientists who are doing remarkable work to keep their country healthy. Senegal’s health transformation is, in large part, a testament to their dedication and deep understanding of their communities, and I loved talking to them about how they’re constantly evolving to meet the needs of the moment. For example, when COVID hit in 2020, IPD quickly built up a test manufacturing facility. They’re now in the process of expanding that capacity so they can produce other essential tests, like one for measles and rubella.
I was also excited to attend the annual meeting of the Grand Challenges initiative in Dakar last month. The Gates Foundation launched Grand Challenges 20 years ago with a single goal in mind: to identify the biggest problems in health and give grants to the researchers who might solve them. Our hope was to inspire more brilliant scientists to think more ambitiously about transforming health in low-income countries. We hoped to create a scientific community that had support to sustain R&D for the benefit of billions of people whose health needs had been neglected.
In 2003, we put forth 14 Grand Challenges. The initial list included developing a vaccine that didn’t require refrigeration, creating a TB treatment for latent infection, and inventing a needle-free drug delivery system. In the years since, we’ve issued more than 200 challenges—and we even launched our first AI-specific call-to-action earlier this year.
I was lucky to spend a lot of time in Senegal with amazing scientists working on the next big breakthrough. Here are 5 of the coolest innovations I saw:
- An AI trainer that teaches health workers in India how to treat high-risk pregnancies. Here’s a devastating statistic: One woman dies in childbirth every 2 minutes. Amrita Mahale and the team at ARMMAN are using artificial intelligence to improve the odds for new mothers in India. Their large language model will one day teach health workers how to treat high-risk pregnancies. The training chatbot can be used in both English and Telugu, and the coolest part is that it automatically adjusts to the experience level of the person using it. Whether you’re a brand-new nurse or a midwife with decades of experience, ARMMAN’s trainer can arm you with the knowledge needed to save lives.
- A low-cost mRNA vaccine platform that puts manufacturing where it’s needed most. mRNA vaccines helped prevent millions of deaths during the height of the COVID pandemic. A company called Quantoom developed a new platform that will make it cheaper and easier to build and run factories that can be adapted to make different mRNA vaccines. I was proud to announce that the foundation is investing $40 million to scale up local mRNA vaccine manufacturing in low- and middle-income countries—which includes funding for IPD to use Quantoom’s platform. This will increase supply, lower costs, guard against the possibility of vaccine hoarding in emergencies, and provide a path for local scientists to discover and develop their own vaccines.
- A new way of tracking mosquitoes on the molecular level to stop malaria. Cases of mosquito-borne diseases like malaria are increasing for the first time in decades. Although climate change is a big contributor, other reasons include conflicts and drug resistance. Fortunately, Isabella Oyier at the Kenya Medical Research Institute is fighting back against mosquito evolution. She uses molecular epidemiology to track mosquitoes who have the genes that cause drug resistance and integrate it into national malaria surveillance and monitoring efforts. This will give stakeholders more insight into where resistance is spreading—and how to stop it.
- A novel approach to treating a common microbiome disorder. Our bodies are home to more microbial cells than human cells, and the good bacteria in our microbiome play an essential role keeping bad bacteria in check. When that balance is off, you get diseases like bacterial vaginosis—a common disorder that, among other problems, can make women more susceptible to HIV infection or more likely to give birth preterm. Today’s treatments are not very effective, so I was excited to talk to Meilin Zhu and her team about a new approach they’re exploring. It uses oleic acids to inhibit the growth of a “gateway” bacteria that can lead to more bad microbes, as well as promote the growth of the good bacteria. This research is still in its early stages, but it’s promising.
- A new drug development platform that will make us better prepared for the next pandemic. Although the world made remarkable progress on vaccines when COVID struck, the same can’t be said for therapeutics. The team at Decoy Therapeutics is working to speed up the process of developing drugs with their promising new biologic platform. The idea is that lipopeptide molecules could be used to inhibit a virus’ fusion machinery and prevent it from infecting cells. If Decoy’s research pans out, scientists could one day use the platform to design therapies for novel viruses within days or even hours.
My time in Senegal reaffirmed my belief in the power of science and innovation. There is no question that our world faces some difficult problems. But when brilliant scientists dedicate their talents to taking on the world’s biggest challenges, progress becomes possible, and we move closer to a future when all people lead healthy lives.
The big picture
On the road in Nigeria and Niger
These were some of my favorite moments from the last week in West Africa.
Have you ever visited a place you haven’t been in a while, and it somehow manages to feel both new and familiar? That’s how I feel every time I go back to Nigeria.
It was amazing to return to Lagos and Abuja this week. I’ve been fortunate to spend a lot of time in Nigeria over the last two-plus decades, but it’s been nearly five years since my last visit due to the pandemic. Nigeria—and especially Lagos—is one of the most dynamic, vibrant places in the world, and I am always blown away by how much it's changed. At the same time, I loved getting to catch up with old friends and reconnect in person with longtime partners. (Remote meetings are great, but it’s nice to meet face-to-face on occasion.)
This week also marked my first-ever trip to Niger. Our foundation has been working with talented Nigeriens for years to help ensure children's health and prevent the spread of polio, and it was exciting to see the country for myself and talk about the future of that work.
It was a great week. These were some of my favorite moments:

Photo Album
My trip to India in pictures
Why my travels in India made me optimistic about the future.
I just returned from my visit to India, and I can’t wait to go back again.
I love visiting India because every trip is an incredible opportunity to learn.
During my travels last week in Mumbai, Delhi, and Bangalore, I met some amazing people, including political leaders, bureaucrats, philanthropists, and scientists, who taught me how they are using the power of innovation, science, and collaboration to find solutions to the world’s health, climate, and development challenges.
Along the way, I met a teen bridge champion, had fun conversations with two of India’s most popular YouTubers, and I even drove an electric rickshaw!
But instead of telling you about it, let me show you. Here are some photos from my trip and some of the stories behind them:

Multitasking
My message in India: To fight climate change, improve global health
Climate change and global health are inextricably linked. We need to make progress on both problems at the same time.
I’m headed back to India next week. Although I’ve spent a lot of time there over the years—doing everything from checking out toilets to visiting a village that’s home to the one poorest, most underserved castes in India—I haven’t been back since before the pandemic. I can’t wait to see how much progress has been made in that time.
This essay originally ran in the Times of India and Dainik Jagaran. You can read it here:
More than two decades ago, I set out to give the vast majority of my resources back to society. My goal from the beginning was to help reduce the awful inequities I saw around the world.
When I started this work, my biggest focus was global health, because it’s the worst inequity in the world and it’s a solvable problem. That’s still the case today. But as time went on—and as the disastrous consequences of a warming world became more evident—it became clear that you can’t improve life for the world’s poorest without also tackling climate change.
Climate change and global health are inextricably linked. Hotter temperatures will make poverty reduction harder by increasing food insecurity and the prevalence of infectious diseases and diverting resources away from those who need them the most. It’s a vicious cycle. The poorer a community is, the more vulnerable it is to climate change. And the more impacted a community is by extreme weather events, the more entrenched in poverty it becomes. To break the cycle, we need to make progress on both problems at the same time.
When I talk to people about this, I often hear the same response: “There isn’t enough time or money to solve both at the same time.” But this idea that we can only tackle one thing at a time is just wrong. I’m stubborn in my belief that with the right innovations and delivery channels to get them to the vulnerable, we’re capable of making progress on lots of big problems at once—even at a time when the world faces multiple crises. There is no better proof than the remarkable progress that India has accomplished.
Consider the field of next-generation chickpea plants currently growing at the Indian Agricultural Research Institute, or IARI, in Pusa. Chickpeas are a staple crop in India. They provide an important source of income for many smallholder farmers, and families across the country rely on them for nutrition. But the chickpea harvest is threatened by climate change. Higher temperatures could reduce yields by as much as 70 percent, putting lives and livelihoods at risk.
So, the Gates Foundation joined hands with India’s public sector and CGIAR institutions to support the work of researchers at IARI. They found a new solution: chickpea varieties that have more than 10% higher yields and are more drought-resistant. One variety is already available to farmers, and others are currently in development at the institute. As a result, India is better prepared to keep feeding its people and supporting its farmers even in a warming world. It’s no exaggeration to say that India’s agricultural future is growing right now in a field in Pusa.
One of the reasons why challenges like climate, hunger, and health seem insurmountable is that we don’t yet have all the tools to solve them. But I’m optimistic that one day soon we will, thanks in part to innovators like researchers at IARI.
India as a whole gives me hope for the future. It’s about to become the world’s most populous country—which means you can’t solve most problems there without solving them at scale. And yet, India has proven it can tackle big challenges. The country eradicated polio, lowered HIV transmission, reduced poverty, cut infant mortality, and increased access to sanitation and financial services.
How did they do it? India has developed a world-leading approach to innovation that ensures solutions reach those who need them. When the rotavirus vaccine—which prevents the virus that causes many fatal cases of diarrhea—was too expensive to reach every child, India decided to make the vaccine themselves. They worked with experts and funders (including the Gates Foundation) to build factories and create large-scale delivery channels to distribute the vaccines. By 2021, 83 percent of 1-year-olds had been inoculated against rotavirus—and these low-cost vaccines are now being used in other countries around the world.
There is no question today’s challenges will test the limits of that ingenuity and cooperation. India is on the frontlines of climate change. But the progress it has made on health will make its people more resilient and provide helpful insights for how to tackle other major challenges. And the pace of its development, its skill in rolling out large-scale programs, and its people’s innovative expertise mean that India can be a key part of making progress on today’s biggest challenges.
I’m going to India next week to see firsthand the work being done by innovators and entrepreneurs. Some are working on breakthroughs that will help us mitigate the effects of climate change, like the work being done by Breakthrough Energy Fellow Vidyut Mohan and his team to turn waste into biofuels and fertilizers in remote agricultural communities. Others are finding new ways to help people adapt to a warmer world, such as IARI’s efforts to create more drought-tolerant crops. I’m looking forward to seeing the progress that’s already underway by both the Gates Foundation’s and Breakthrough Energy’s amazing partners.
Like every other country on the planet, India has limited resources. But it has shown us how the world can still make progress in spite of that constraint. By collaborating and trying novel approaches, the public, private, and philanthropic sectors can turn limited resources into big pools of funding and knowledge that lead to progress. If we work together, I believe we can fight climate change and improve global health at the same time.
Back in China
I’m visiting the country after four years away
I’m seeing first-hand some of the innovations that could contribute to global progress.
I want to share a few impressions from my time in China. I just had a meeting with President Xi, in which we discussed the importance of addressing global health and development challenges, like health inequity and climate change, and how China can play a role in achieving progress for people everywhere.
As part of my work with the Gates Foundation, I’ve tried to visit China, India, countries in Africa and Europe, and Washington D.C. each year. On these trips, I’d talk to researchers, government leaders, advocates, and other experts who are working on inequities in health and development. I’d always learn a lot, returning inspired by what I saw and heard.
It’s great to be able to resume these regular visits. This was my first trip to China in four years, and immediately after this trip, I’m headed to West Africa for the first time in five years. And I went to India in March.
On each trip this year, I have a key message: Over the past two decades, the world made significant strides in reducing poverty and improving health outcomes, but COVID was a big setback and even reversed progress on some global goals like reducing poverty and fighting TB and malaria. Many African countries, for example, are particularly impacted by overlapping challenges, including the effects of climate change, high food prices, escalating poverty rates, surging infectious diseases, and significant debt pressures.
Even though the challenges facing many African countries are complex, I’m optimistic that innovation in health, agriculture, digital finance, and energy will help improve lives there. I’m looking forward to meeting leaders and young people helping to accelerate progress when I visit West Africa.
Solving these problems requires innovation—both new tools and new ways of doing things. China has eliminated diseases, including polio and malaria, within its borders, developed drugs like artemisinin that have saved millions of lives around the world from malaria, made great strides in poverty reduction, and has made significant investments in clean energy and climate adaptation. So I was looking forward to seeing what’s changed since my last visit four years ago.
One highlight was my visit to the Global Health Drug Discovery Institute, an organization our foundation helped establish six years ago in partnership with the Beijing Municipal Government and Tsinghua University. GHDDI represents a productive way for public and private partners to work together on discovering new medicines for diseases that disproportionately impact the world’s most vulnerable populations but have applications for the world. I spoke about the institute’s work on TB and malaria yesterday, and we also extended our partnership over the next five years.
I also got to visit the National Crop Genebank of China. This facility is a prominent crop research center and also serves as a long-term preservation storage space for seeds so that scientists around the world have access to important genetic data. During my visit, I met with agricultural scientists who are working with their counterparts worldwide, particularly in Africa, on new rice varieties that help farmers increase their productivity and minimize the need for fertilizers, pesticides, and irrigation.
The benefits of their work have reached millions of farming households across Asia and Africa. The continued investment in technology and innovation within the agricultural sector has played a significant role in the increase in agricultural productivity throughout China. What excites me even more is China’s commitment to share their expertise and innovative practices with low-income countries. By assisting farmers in adapting to climate change, increasing their income, and combating food crises, they are making a substantial contribution to global food security.
The genebank and GHDDI are just two examples of the promising work the foundation has seen in China in the more than 15 years we’ve been partnering here. And there will be more opportunities for China and others to step up later this year, including a summit on development financing in Paris, a meeting of the G20 in New Delhi, and the COP28 climate conference in Dubai.
I’m convinced that if the world works together to address climate change, health inequity, and food security we can make extraordinary progress. And I’m looking forward to exploring new opportunities for collaboration and innovation that will make a better future for everyone.

Across the finish line
Makoy Samuel Yibi won’t stop until the world eradicates its next disease
Guinea worm once infected 3.5 million people every year. Thanks to heroes like Makoy, that number dropped to 13 last year.
When you see someone suffering from a terrible disease, it’s hard not to imagine a world where no one has to feel this way ever again. But the problem with eradication is that it’s really, really hard. The fewer cases remain, the more difficult it is to find them. That’s why, in all of human history, we’ve only eradicated two diseases: smallpox and the cattle disease rinderpest.
That might change soon.
The world is close to eradicating Guinea worm disease, a debilitating and painful condition that once devastated an estimated 3.5 million people in Africa and South Asia every year. Thanks to heroes like Makoy Samuel Yibi, that number dropped to 13 people in 2023.
As the national director of the South Sudan Ministry of Health’s Guinea Worm Eradication Program, Makoy helped reduce the number of cases in his country last year to just two. That’s a remarkable accomplishment by any standard, but it’s truly impressive when you consider the circumstances he and his team have faced: civil wars, the COVID-19 pandemic, the political changes brought by South Sudan’s decision to become an independent country in 2011, and the fact that the nation was once home to 90 percent of the world’s Guinea worm cases.
I recently caught up with Makoy at the COP climate conference in Dubai, where we both participated in an event focused on ending neglected tropical diseases, or NTDs, like Guinea worm. When you meet him in person, it’s hard to imagine a better person for the job. Makoy is passionate, brilliant, and laser-focused on making life better for the people of South Sudan. So I was surprised to learn that, as a young man, he never imagined a career in health.
Makoy was born in Terekeka County, a rural area located on the shores of the West Nile in southern Sudan. When he was a young man, Makoy had one primary focus: avoiding military service, which could be extremely dangerous. A chance meeting with a general from Terekeka resulted in a position with the national health department. A measles outbreak was ravaging parts of Sudan at the time, and Makoy’s first assignment was to travel from village to village providing care.
“What struck me,” he recalls, “was that, in every household we went to, we found at least half of the household was down with Guinea worm.”
The Guinea worm is a particularly nasty parasite. It’s unlikely to kill you, but the disease it causes—which is also called dracunculiasis, or “afflicted with little dragons”—can incapacitate you for months at a time and leave you permanently disabled. That can have devastating consequences if your family counts on you to grow the food you eat and sell it to make a living, as many people in South Sudan do.
The way the disease works is horrifying. If a person drinks water contaminated with Guinea worm larvae, the larvae enter the digestive system and mate. The impregnated female worm grows, undetected by the body’s immune system. Around a year later, the infected person will start to feel an itch somewhere on their body (usually the lower leg or foot). After a couple days, a painful blister appears and eventually bursts. The worm—which is now about one meter long—slowly starts to emerge from the wound.
This can take weeks or even months, and the pain it causes is excruciating. The wound can get infected, which could result in permanent disfigurement or even require amputation. And people often endure multiple worms emerging at the same time. Makoy has seen patients with as many as 40 worms.
And here’s the most insidious part: One of the few ways to relieve the pain of the blister is by soaking it in cold water, like a pond or a puddle. But that’s exactly what the worm wants. As soon as it touches water, it releases its larvae, starting the cycle anew. The Guinea worm is scarier and more efficient than any monster in a horror movie.
Makoy has seen countless times how devastating Guinea worm can be. “This is a situation where you see serious disruption of the livelihood of the community,” he says. “You see people going through a cycle of hunger because they don’t have enough. They have lost the window of cultivation. They’re not able to tend to their cattle, and there’s nothing they can do.”
There is no cure or treatment for Guinea worm, and yet, the world is on the doorstep of eradicating it. How? Through a series of highly effective interventions and a network of incredibly dedicated health workers.
Makoy’s team has built a network of volunteers in virtually every village in the country, who report rumors of Guinea worm cases. They spend every day searching for cases, getting the word out, and building trust in a country where more than 60 languages are spoken.
Makoy and his colleagues investigate every single rumor, no matter how remote. During the rainy season when the majority of cases happen, he often spends days hiking through the Sudd or up a mountain with all of his supplies on his back just to reach his destination. Last year, in a country the size of France with less than 100 miles of paved road, the team responded to nearly all of the 50,000 rumors they received within 24 hours.
Once the team finds a confirmed case, they make the patient as comfortable as possible and do what is called “controlled immersion.” This means soaking the affected area in a bucket of water and encouraging the worm to come out.
Makoy also spends a lot of time preventing people from getting Guinea worm in the first place. His team distributes free water filters and educates communities about safe water practices. The system they’ve built to support this work has strengthened health systems across the country, providing a platform for delivering other health services like childhood vaccination.
Makoy’s team has had a tremendous partner in all of this work: former U.S. President Jimmy Carter and the Carter Center. In 1995, when Makoy was first starting his public health journey, President Carter negotiated what remains the longest humanitarian ceasefire in history when he helped convince both sides of the Second Sudanese Civil War to lay down their arms and allow health workers access to treat Guinea worm and other diseases, like polio and river blindness. Today, the Carter Center continues to lead the global eradication campaign’s march to zero. The Gates Foundation is proud to support the Carter Center as part of our overall efforts to tackle NTDs. (You can learn more about Makoy’s partnership with the Carter Center in a new film called The President and the Dragon that is coming out later this year.)
Eradication is now within sight, although it won’t be easy to eliminate the last few cases. South Sudan previously reported no Guinea worm in 2018, but cases were subsequently discovered after a peace agreement was reached in the South Sudanese Civil War. And Guinea worm has recently been detected in dogs and other animals, mainly in Chad. Eradication will require stopping all transmission, both human and animal.
But Makoy Samuel Yibi is optimistic we can get there—and so am I. His determination to root out every last case makes me hopeful that we will someday soon celebrate the end of Guinea worm disease.
“In the places where Guinea worm has been eliminated,” he says, “you can actually see how communities have been energized. They are more active, and they are productive. The communities are now empowered to be more self-sufficient, because they don’t have to worry about Guinea worm.”

Ick!
What’s gross and better to see on an empty stomach? This museum in Tokyo
Welcome to the bizarre, creepy, and endlessly fascinating exhibits at the world’s foremost parasite museum.
You may want to skip lunch—and probably avoid sushi for dinner—when visiting the world’s foremost museum of parasites in Tokyo.
At the quirky and endlessly fascinating Meguro Parasitological Museum, which I toured during my trip to Japan in August, you’ll find hundreds of stomach-turning displays featuring creepy parasite specimens.
Some of the strangest-looking ones have resided inside the bodies of fish, turtles, pigs, and other animals. But by far the most horrific specimens are the parasites that have chosen humans as their hosts.
What steals the show is the world’s longest tapeworm. In 1986, this garden-hose length parasite was discovered living in the small intestine of a Japanese man. He had dined on a piece of raw salmon that was infected with a tapeworm egg smaller than a grain of rice. Over the next three months it grew and grew until it reached 29 feet long! (If you’re a follower on my Instagram account, you may have gotten a glimpse of this impressive specimen.)
The man who recovered the tapeworm from this unfortunate patient was Dr. Satoru Kamegai, the founder of Meguro Parasitological Museum. A physician, Dr. Kamegai started practicing medicine after World War II. At the time the country’s water and sanitation systems were in ruins and many people throughout Japan suffered from parasitic diseases. Dr. Kamegai became fascinated by the strange world of parasites and started collecting them from his patients. In 1953, he opened a small museum to display his findings and raise awareness of these creatures. Dr. Kamegai passed away in 2002, but the museum has continued to operate as a private research and educational facility.
Today, the museum has a collection of 60,000 different parasites, about 300 of which are on display in the two-story collection. Entrance to the museum is free and it draws a steady stream of visitors. It even has a gift shop with parasite-themed t-shirts, pens, and jewelry. (I picked up a t-shirt with the famous tapeworm on it.)
While I had a busy trip to Japan, I took time to stop at this museum because of our foundation’s efforts to reduce the burden of so-called neglected tropical diseases, many of them caused by parasites. More than 1 billion people suffer from these overlooked diseases with often difficult to pronounce names, including dracunculiasis (Guinea worm disease), human African trypanosomiasis (sleeping sickness), visceral leishmaniasis (black fever), onchocerciasis (river blindness), and schistosomiasis (snail fever).
These diseases can cause anemia and blindness, stunt children’s growth, lead to cognitive impairments, complicate pregnancies, and result in thousands of deaths each year. And it’s not uncommon for people living in extreme poverty to suffer from more than one of these diseases at the same time, affecting their ability to go to school or make a living.
Our foundation works with partners on the treatment and control of these diseases. One of the most successful efforts has been mass drug administration, which seeks to treat everyone against a disease—even if they are not actually infected or show any symptoms. I observed this incredible work in Tanzania, where I joined a group of health workers going from house to house to distribute medicine to wipe out lymphatic filariasis, one of the world’s most painful and debilitating diseases.
The good news is that there’s been a lot of progress in reducing parasitic diseases around the world. But there’s still more work to be done. That makes this museum a great place for people to learn about where these diseases still exist and the incredible work that’s going on to wipe them out.
If you happen to be in Tokyo, I encourage you to visit.
Neglected no more
A massive success
How to stop disease by treating everyone—even healthy people.
Health workers have an unusual tool for fighting disease that turns our old thinking about treatment on its head. I saw it at work recently in a remote hilltop village in Tanzania, where I joined a group of health workers going from house to house to distribute medicine to wipe out lymphatic filariasis, one of the world’s most painful and debilitating diseases.
At each home, one health worker told the family about the swollen limbs, disfigurements, and other symptoms of the parasitic disease. Another carried a tall stick to measure the height of each family member to determine the correct dosage. Then, if they were willing to be treated, the parents and children took their pills and washed them down with a cup of water before our team moved on to the next house.
What was surprising about this effort is that none of the people who took the medicine were sick.
The village I visited was participating in what’s known as a mass drug administration campaign, which seeks to treat everyone against a disease—even if they are not actually infected or show any symptoms. Typically, of course, the sick are the ones who get treated, not the people who are healthy. But when it comes to combating some diseases, like lymphatic filariasis, it’s critical for health workers to try to treat the entire at-risk population to break the cycle of transmission. If not, the disease could continue to be spread by those who are not aware they are infected.
Ten countries have successfully eliminated lymphatic filariasis in this way, including Togo, which this year became the first country in sub-Saharan Africa to wipe out the disease. Still, more than 800 million people in 52 countries worldwide remain threatened by lymphatic filariasis.
Mass drug administration is not only effective against lymphatic filariasis, but also other neglected tropical diseases, including schistosomiasis, onchocerciasis, trachoma, and soil-transmitted helminths. These diseases go by names that are largely unknown and often difficult to pronounce. But it should be easy to understand why we should all care about them. They afflict people living in the poorest countries and cause untold suffering.
Lymphatic filariasis is one of the worst of these diseases. It’s caused by a parasite that’s spread by mosquitoes, and in the severest cases people may develop swollen limbs, a thickening of the skin known as elephantiasis, or other severe disfigurements. Beyond the pain and disabilities they experience, people affected by the disease are often ostracized by their communities and are unable to work, sinking them deeper into poverty.
To combat lymphatic filariasis, health officials could test everyone and then treat only those people who are infected. But testing the population for these diseases would be expensive and slow. The medicines used for treatment (ivermectin and albendazole), however, are inexpensive and have no side effects, making mass treatment a more effective approach to protect people from the disease. (And thanks to the generosity of the many pharmaceutical companies, billions of doses of these and other medicines combating neglected tropical diseases are being donated for free.)
Like many countries running mass drug administration programs, Tanzania’s biggest challenge is treating enough of its population at risk of the disease. To break the cycle of transmission, health workers must treat at least 65 percent of the population every year for 5 to 10 years. As you might imagine, meeting this target year after year is not easy.
Health officials must have strong public awareness campaigns, thousands of trained health workers, a well-organized supply chain to distribute medicines to the remotest corners of the country, and regular disease surveying to track their progress. At the same time, the program provides treatment and care for people who are suffering from the debilitating symptoms of the diseases.
Walking from door to door in the village with the health workers, I was struck that perhaps the most important element of the program is trust. Taking the medicine is strictly voluntary, making it important that the health workers distributing it earn the confidence of the community. The health workers I met certainly had. They were knowledgeable, passionate about their work, and clearly cared about the community they were serving. At each home, they took the time to explain the goal of the program and address any of the villagers’ questions or concerns. Thanks to their hard work the latest survey of lymphatic filariasis in their district showed that the cycle of transmission had been broken. For the first time, the village was not at risk of the disease.
By 2020, Tanzania hopes to eliminate lymphatic filariasis entirely within its borders. Based on what I saw in this village, I’m optimistic they will.
24:00:00
Record-breaking generosity
On January 30, 2017, a group combatting neglected diseases did something extraordinary. Guinness World Records took notice.
Page through the Guinness Book of World Records and you’ll learn that a lot can happen in 24 hours.
On February 14, 2004, Dan Meyer of Davis, California, set the record for the longest paperclip chain by an individual in 24 hours. Length: 5,340 feet. Total number of paper clips: 54,030.
On June 4, 2011, Nabi Salehi, a barber in London, set the record for giving the most consecutive haircuts in 24 hours. Total haircuts: 526.
And on January 30, 2017, another achievement—one that will improve millions of lives—was added to the Guinness World Record list. A group fighting neglected tropical diseases—including Guinea worm, river blindness, and elephantiasis—set the record for most drugs donated in a 24-hour period. Total number of drugs: 207,169,292!
This week in Geneva, I was excited to participate in the ceremony to celebrate the group that achieved this incredible feat, Uniting to Combat Neglected Tropical Diseases, a coalition of drug companies, governments, health organizations, charities, and other partners who work to reduce the burden of tropical diseases that impact the world’s poorest.
On January 30th, they organized drug manufacturers, warehouse workers, delivery drivers, government officials, and health workers to deliver this historic number of donated drugs on four continents for distribution to people living in the remotest parts of the world.
What’s truly amazing is that the 207 million drugs donated on January 30th represent just a small amount of this group’s generosity. Since 2012, when United to Combat Neglected Tropical Diseases signed a declaration to control or eliminate 10 of the worst neglected diseases, they have donated 7 billion treatments. I’m grateful to the pharmaceutical companies that have been making these donations year after year: Bayer, Eisai, Gilead, GSK, Johnson & Johnson, MSD, Merck KGaA, Novartis, Pfizer, and Sanofi.
Thanks to the efforts of these drug companies and their partners millions of people are receiving the medicines they need to cure and protect them from these diseases. These diseases are in retreat and the world is moving closer to the day when they will be eliminated altogether.
Of course, all world records get challenged. And I for one will be thrilled for the day when this record for drug donations gets broken. So will the millions of families around the world who need them.
Warning!
Neglected no more
These diseases may be difficult to pronounce, but it should be easy to see why everyone should care about them.
Warning: you may find what I’m about to write disturbing.
Imagine a fly infected with parasites bites you. First you get a fever, then headaches, joint pains, and itching. Eventually, when the parasites cross the blood-brain barrier, you lose your mind, you can’t control your muscles, and then you lose your life.
Now, imagine you drink a glass of water. The water contains tiny fleas containing even tinier larvae. The larvae mate and grow in your body. One year later, a painful blister forms on your foot. The head of a worm pokes out. It’s 3-feet-long and takes weeks to remove.
Finally, imagine a mosquito bites you. It’s infected with tiny larvae. They set up camp in one of your lymph nodes, where they mate and nest, causing your leg to eventually swell to 10 times its size.
Sound horrific? Well, I haven’t told you the most disturbing part. I’m not making up these diseases (Human African trypanosomiasis, Dracunculiasis, and Lymphatic filariasis). They are just three of more than a dozen tropical diseases that afflict some of the poorest people in the world. As I write this, more than a billion people suffer from at least one of them.
These diseases go by names that are largely unknown and often difficult to pronounce.
Still, it should be easy to understand why we should all care about them. Spread by worms and insects, they disfigure and disable people living in the remotest areas of the world, keeping children out of school and parents from being able to work. In the worst cases, they kill. And all of them can be prevented—if the world continues to work together to end them.
I am in Geneva, Switzerland this week for a meeting to raise awareness and continue support for the fight against these overlooked diseases. Collectively, they’ve been dubbed “Neglected Tropical Diseases,” but lately they’ve been getting some of the attention they deserve.
Five years ago, Uniting to Combat Neglected Tropical Diseases, a group of pharmaceutical companies, governments, health organizations, charities, and other partners, came together to treat and prevent these diseases. They set a goal to control or eliminate at least 10 of them by 2020. Today, there’s a lot of progress to celebrate. Fewer people are suffering from them, and many countries are on their way to eliminating them altogether.
Here are some examples of the progress that’s been made.
Dracunculiasis (also known as Guinea worm), the parasitic disease I described above in which a large worm grows inside its victims, is nearing its end. In 1985, the disease afflicted an estimated 3.5 million people in 21 countries in Africa and Asia. Last year, thanks to the work of Uniting to Combat NTDs, The Carter Center, and other partners the number of Guinea worm cases has been reduced by more than 99 percent to 25 cases.
Lymphatic filariasis, also known as elephantiasis, is thepainful, disfiguring disease spread by mosquitoes. Five years ago, 1.5 billion people needed preventive drug treatment to protect them from the disease. Since then, it has been eliminated in six countries and reduced in 18 others.
Human African trypanosomiasis (HAT), commonly known as sleeping sickness, is also in retreat. Cases have declined by more than 90 percent, from 26,000 cases in 2000 to 2,733 in 2015.
What’s driving this progress? It’s been the result of drug donations by pharmaceutical companies and generous commitments by donors and governments. More than one billion people were reached with NTD treatments in 2015 alone—across nearly 150 countries.
New innovations for testing and treatment have also made a big difference. For example, the diagnostic test for sleeping sickness used to require electricity, bulky equipment, and refrigeration, making it difficult to deliver to remotest areas of the world. Now, a simple finger-prick blood test allows health workers to test for the diseases. And new smartphone-based mapping tools could make it easier to map these diseases so health workers can target their treatment efforts in real time down to the household level.
Still, there’s a lot of work to be done. We need continued support from donor governments to finish the job. We need more research on improved drugs and tests to help make it easier to treat people quickly. And we must support the frontline health workers who have the tough job of delivering the drugs in the hardest to reach regions of the world.
If the world keeps up the fight against these diseases, we can improve the lives of millions of the poorest families. They won’t be neglected anymore.
Take Action
Help us eliminate these debilitating diseases that afflict the world’s poorest by supporting The END Fund. The END Fund is a GiveWell Top Charity.

Wrapping up 2018
What I learned at work this year
Thoughts on Alzheimer’s, climate change, polio, and more.
Every Christmas when I was a kid, my parents would send out a card with an update on what the family was up to. Dad’s law firm is growing, Mom’s volunteer work is going strong, the girls are doing well in school, Bill is a handful.
Some people think it is corny, but I like the tradition. These days, at the end of each year, I still enjoy taking stock of my work and personal life. What was I excited about? What could I have done better?
I thought I would share a few of these thoughts as 2018 concludes.
One thing that occurs to me is that the questions I am asking myself at age 63 are very different from the ones I would have asked when I was in my 20s.
Back then, an end-of-year assessment would amount to just one question: Is Microsoft software making the personal-computing dream come true?
Today of course I still assess the quality of my work. But I also ask myself a whole other set of questions about my life. Did I devote enough time to my family? Did I learn enough new things? Did I develop new friendships and deepen old ones? These would have been laughable to me when I was 25, but as I get older, they are much more meaningful.
Melinda has helped broaden my thinking on this point. So has Warren Buffett, who says his measure of success is, “Do the people you care about love you back?” I think that is about as good a metric as you will find.
It may sound grand, but I think the world is slowly going through a similar transition to a broader understanding of well-being. For most of human history, we have been focused on living longer by fighting disease and trying to grow enough food for everyone. As a result, life spans have gone up dramatically. Technology has played a key role in that through vaccines, medicines, and improved sanitation.
We still need a lot of innovation to solve problems like malaria or obesity, but we are also going to be focusing more on improving the quality of life. I think this will be the thrust of many big breakthroughs of the future. For example, software will be able to notice when you’re feeling down, connect you with your friends, give you personalized tips for sleeping and eating better, and help you use your time more efficiently.
There are not the same clear measures of these things as there are for diseases, and there may never be. But there is nascent work in this field and I think it is going to accelerate.
As I look back on the year, I am also thinking about the specific areas I work on. Some of this is done through our foundation but a lot of it (such as my work on energy and Alzheimer’s work) is not. What connects it all is my belief that innovation can save lives and improve everyone’s well-being. A lot of people underestimate just how much innovation will make life better.
Here are a few updates on what’s going well and what isn’t with innovation in some areas where I work.
Alzheimer’s disease
I saw two positive trends in Alzheimer’s research in 2018.
One is that researchers focused on a new set of ideas about how to stop Alzheimer’s.
The first generation of theories, which dominated the field for years, emphasized two proteins called amyloid and tau. These proteins cause plaques and tangles in the brain, clogging up and killing brain cells. The idea was to stop the plaques and tangles from forming. I hope these approaches pay off, but we have not seen much evidence that they will.
In the past year, researchers have doubled down on a second generation of hypotheses. One theory is that a patient’s brain cells break down because their energy producers (called mitochondria) wear out. Another is that brain cells break down because part of the immune system gets overactivated and attacks them.
This is a great example of how improving our understanding of biology will reduce both medical costs and human suffering.
The other trend this year is that the Alzheimer’s community focused on getting more and better access to data. We’re working with researchers to make it easier for them to share information from their studies broadly so that we can better understand questions like how the disease progresses.
Over the past few years, the U.S. government has dramatically stepped up funding for Alzheimer’s research, from $400 million a year to over $2 billion a year. There is also a big push to create better diagnostics.
The only problem where I don’t yet see a clear path forward yet is how to develop more efficient ways to recruit patients for clinical trials. Without a simple and reliable diagnostic for Alzheimer’s, it’s hard to find eligible people early enough in the disease’s progression who can participate in trials. It can take years to enroll enough patients. If we could find a way to pre-screen participants, we could start new trials more quickly.
But there is so much momentum in other areas—scientific tools, better diagnostics, improved access to data—that as long as we can solve the recruitment problem, I am confident that we will make substantial progress in the next decade or two.
Polio
I thought we would be closer to eradicating polio today than we are. Unfortunately, there were more cases in 2018 than in 2017 (29 versus 22).
I underestimated how hard it would be to vaccinate children in places where there’s political violence and war. Families move around to escape fighting, which makes it hard to keep track of children and make sure they get all the doses of the vaccine. Or sewage systems get destroyed, allowing the virus to spread as children come into contact with an infected person’s excrement.
This is a key reason why Afghanistan and Pakistan have never been free of polio—in fact they are the only two countries that have never been free of polio.
I spend a lot of time on polio, part of it talking to the funders to make sure they continue their commitment even though eradication is taking longer than any of us would like. I remind them of the huge benefits of success, and the risk that the disease will return in a big way if we don’t finish the job.
I also remind them what a difference innovation is making. We’re now able to test sewage samples to track the virus and find the source before an outbreak starts. And the global health community is finding creative ways to work in war zones, having stopped outbreaks in Syria and Somalia in recent years.
Finally, I am hopeful about a new oral vaccine being tested in Belgium and Panama. The results should be out in 2019, and if this one proves effective, it would overcome some of the problems with previous oral vaccines when they’re used in places where few children are immunized. The new vaccine could be in use as soon as 2020.
Despite all the challenges, I am still optimistic that we can eradicate polio soon.
Energy
Global emissions of greenhouse gases went up in 2018. For me, that just reinforces the fact that the only way to prevent the worst climate-change scenarios is to get some breakthroughs in clean energy.
Some people think we have all the tools we need, and that driving down the cost of renewables like solar and wind solves the problem. I am glad to see solar and wind getting cheaper and we should be deploying them wherever it makes sense.
But solar and wind are intermittent sources of energy, and we are unlikely to have super-cheap batteries anytime soon that would allow us to store sufficient energy for when the sun isn’t shining or the wind isn’t blowing. Besides, electricity accounts for only 25% of all emissions. We need to solve the other 75% too.
This year Breakthrough Energy Ventures, the clean-energy investment fund I’m involved with, announced the first companies we’re putting money into. You can see the list at http://www.b-t.energy/ventures/our-investment-portfolio/. We are looking at all the major drivers of climate change. The companies we chose are run by brilliant people and show a lot of promise for taking innovative clean-energy ideas out of the lab and getting them to market.
Next year I will speak out more about how the U.S. needs to regain its leading role in nuclear power research. (This is unrelated to my work with the foundation.)
Nuclear is ideal for dealing with climate change, because it is the only carbon-free, scalable energy source that’s available 24 hours a day. The problems with today’s reactors, such as the risk of accidents, can be solved through innovation.
The United States is uniquely suited to create these advances with its world-class scientists, entrepreneurs, and investment capital.
Unfortunately, America is no longer the global leader on nuclear energy that it was 50 years ago. To regain this position, it will need to commit new funding, update regulations, and show investors that it’s serious.
There are several promising ideas in advanced nuclear that should be explored if we get over these obstacles. TerraPower, the company I started 10 years ago, uses an approach called a traveling wave reactor that is safe, prevents proliferation, and produces very little waste. We had hoped to build a pilot project in China, but recent policy changes here in the U.S. have made that unlikely. We may be able to build it in the United States if the funding and regulatory changes that I mentioned earlier happen.
The world needs to be working on lots of solutions to stop climate change. Advanced nuclear is one, and I hope to persuade U.S. leaders to get into the game.
The next epidemic
In 1918, the Spanish flu killed 50 million people worldwide. It still ranks as one of the deadliest natural disasters ever.
I had hoped that hitting the 100th anniversary of this epidemic would spark a lot of discussion about whether we’re ready for the next global epidemic. Unfortunately, it didn’t, and we still are not ready.
People rightly worry about dangers like terrorism and climate change (and, more remotely, an asteroid hitting the Earth). But if anything is going to kill tens of millions of people in a short time, it will probably be a global epidemic. And the disease would most likely be a form of the flu, because the flu virus spreads easily through the air. Today a flu as contagious and lethal as the 1918 one would kill nearly 33 million people in just six months.
I have been studying this for several years. To be prepared, we need a plan for national governments to work together. We need to think through how to handle quarantines, make sure supply chains will reach affected areas, decide how to involve the military, and so on. There was not much progress on these questions in 2018.
The good news is that there has been progress toward a vaccine that would protect you from every strain of the flu. This year I visited the U.S. National Institutes of Health in Maryland and got an update from some of the people leading this work.
The challenges of making a universal flu vaccine are fascinating. All strains of the virus have certain structures in common. If you’ve never been exposed to the flu, it’s possible to make a vaccine that teaches your immune system to look for those structures and attack them. But once you’ve had the flu, your body obsesses over the strain that got you sick. That makes it really hard to get your immune system to look for the common structures.
So it is clear how we could make a universal vaccine that would protect anyone (such as the very young) who has never been exposed to the flu before. But for anyone who has already had the virus, it is a lot harder. The problem is a long way from being solved, but new research money is coming in and more scientists are working on it.
To make the most of these scientific efforts (some of which our foundation is funding), the world needs to develop a global system for monitoring and responding to epidemics. That is a political matter that requires international cooperation among government leaders. This issue deserves a lot more focus.
Gene editing
Gene editing made the news in November when a Chinese scientist announced that he had altered the genes of two baby girls when they were embryos. What is unprecedented about his work is that he edited their germline cells, meaning the changes will be passed down to their children. (The other, less controversial type of gene editing involves somatic cells, which aren’t inherited by future generations.)
I agree with those who say this scientist went too far. But something good can come from his work if it encourages more people to learn and talk about gene editing. This might be the most important public debate we haven’t been having widely enough.
The ethical questions are enormous. Gene editing is generating a ton of optimism for treating and curing diseases, including some that our foundation works on (though we fund work on altering crops and insects, not humans). But the technology could make inequity worse, especially if it is available only for wealthy people.
I am surprised that these issues haven’t generated more attention from the general public. Today, artificial intelligence is the subject of vigorous debate. Gene editing deserves at least as much of the spotlight as AI.
I encourage you to read up on it whenever you have a chance. Keep an eye out for articles in your news feed. If you are willing to read a whole book, The Gene by Siddhartha Mukherjee is very well done. This story is one to follow, because big breakthroughs—some good, some worrisome—are coming.
Looking ahead
I am making a resolution for 2019.
Although I have never been one for New Year’s resolutions, I have always been committed to setting clear goals and making plans to achieve them. As I get older, these two things look more and more like the same exercise. So I am making a resolution for 2019. I am committing to learn and think about two key areas where technology has the potential to make an enormous impact on the quality of our lives, but also raises complex ethical and social considerations.
One is the balance between privacy and innovation. How can we use data to gain insights into education (like which schools do the best job of teaching low-income students) or health (like which doctors provide the best care for a reasonable price) while protecting people’s privacy?
The other is the use of technology in education. How much can software improve students’ learning? For years we have been hearing overheated claims about the huge impact that technology would have on education. People have been right to be skeptical. But I think things are finally coming together in a way that will deliver on the promises.
I will be posting updates on these and other issues on the Gates Notes.
In the meantime, Melinda and I are working on our next Annual Letter. The theme is a surprise, though it is safe to say we’ll be sharing some positive trends that make us optimistic about the future. We’ll send the letter out in February.
I hope you have a happy and healthy start to 2019.
A true data farm
Can the Wi-Fi chip in your phone help feed the world?
I recently visited an amazing farm near Seattle that uses data to grow better harvests.
I recently visited a remarkable farm in Carnation, Washington, just 25 miles from downtown Seattle.
At first glance, Dancing Crow Farm looks like any other farm. There are rows of crops and, at least when I was there, the field was dusty. There were farm implements and freshly picked peppers piled up under a lean-to. But if you talk to Sean Stratman—the man responsible for this plot—it quickly becomes clear what makes his farm so special: Sean knows more about his land than almost any other farmer on earth.
Dancing Crow Farm is the pilot site for FarmBeats, an amazing new project that hopes to make farmers more productive by arming them with data. When most people think of groundbreaking digital technology, they don’t picture soil sensors. But a farmer who knows the temperature, pH, and moisture level of his soil can make all sorts of informed decisions that save money and boost yield.
For example, fertilizer works better when it’s applied to moist soil. But how do you know when to fertilize? Soil that feels dry is often still damp below the surface. You’ll end up fertilizing more often than necessary if you go by touch alone. But if you know exactly how much moisture is in your soil at any given moment, you can fertilize only when you need to. You use less and save money.
The problem is that most existing digital platforms that provide this kind of information are expensive. Sensors can cost hundreds of dollars each, and each one only covers 10 meters. The cost is so prohibitive that only the very richest farmers can afford them.
A team of researchers at Microsoft—led by researcher Ranveer Chandra, who I talk to in the video above—wants to change that. In FarmBeats, they’ve developed a series of innovations that might one day put data in the hands of even the poorest farmers.
The main innovation is in how FarmBeats sensors transmit data. Most farms have poor or no access to the Internet. In the United States, 20 percent of people living in rural areas don’t have access to even the slowest broadband speeds. Most farm data systems require expensive transmitters to connect, but FarmBeats relies on a clever workaround: it uses TV white space.
White spaces are unused TV broadcast spectrum. If you’ve ever watched an old TV, you’ve seen white spaces before. They’re the “snow” you’ll sometimes see while flipping through channels. These gaps in spectrum are plentiful in the remote areas where most farms are located, so data can be sent over them the same way that data gets transmitted via broadband.
Here’s how FarmBeats works: The whole system is powered by solar panels. You place a small number of sensors—one every couple hundred meters, instead of 10 meters—in the ground. You then attach your smart phone with the camera facing down to either a drone (if you have money to spare) or a helium balloon (if you don’t).

You walk around the fields with the camera, creating an aerial map of the farm. Data from both the sensors and the phone are transmitted via TV white space to your computer, where an edge device stitches everything together into a data map.
The data generated by FarmBeats has been a game changer for Sean and Dancing Crow Farm. He can use up to 30 percent less water for irrigation and 44 percent less lime to control soil pH. Information on soil temperature and moisture levels has helped him better time the planting of seeds, so he gets a more productive harvest. Because Dancing Crow Farm is located next to a river, flooding is a problem. FarmBeats’ aerial imaging capabilities precisely document flooding patterns, so he’s able to better plan what he plants where. The system even helped Sean identify parts of the farms where inadequate drainage was affecting the quality of beans.
It’ll be at least a year before every component of FarmBeats is available to the public—and even longer before the cost comes down enough for broad adoption (the current version is much cheaper than other farm data systems but still too expensive for poor farmers to afford). But I’m hopeful that one day this technology could be available to every farmer everywhere, including the most remote parts of Africa.
Even as they continue working on the current version, the FarmBeats team is already working on the next generation of their technology. They just released a paper demonstrating for the first time that Wi-Fi signals can be used to collect soil data. Using only their smart phones and super cheap RFID tags buried in the ground, any farmer could get important information about their land—no special, high tech equipment required.
The Wi-Fi technology is still theoretical, but I’m glad brilliant minds are thinking about how we can help the poorest farmers gather data and increase yield. Even small gains in productivity could mean the difference between affording to send your kids to school or not. And for farmers who rely on the food they grow to feed their family—where the size of your harvest is a matter of life or death—FarmBeats could be a literal lifesaver.
More than three-quarters of the world’s poor rely on agriculture to earn a living. If we’re going to win the fight against poverty, we must help farmers—and I believe that FarmBeats could be a powerful tool.
Just the facts, Max
Memorizing these three statistics will help you understand the world
Why we should be optimistic but not complacent.

One of my favorite websites is OurWorldInData.org. Based at the University of Oxford, it uses statistics—on everything from health and population growth to war, the environment, and energy—to give you phenomenal insight into how living conditions are changing around the world. I asked its founder, Oxford economist Max Roser, to share three facts from the site that everyone should know. Here’s what Max had to say. – Bill Gates
In the past few years, it has become easy to find many of the important statistics on global development with a quick online search. And since it is now so easy to find the information you need, many argue that it doesn’t make sense to actually remember these statistics. ‘Just look them up when you need them!’ they say.
I disagree with this. Yes, for some details, it makes sense to just search for them when you need them. But for the large global developments, it is important to know some basic statistics that describe living conditions currently and the direction of change that we have seen over the past few decades. Knowing the facts on global changes gives you the context for the daily news and allows you to make sense of new information that you learn. And it must be the basis for political debate, so that we can discuss what we should and shouldn’t do as a society.
And so I compiled a short list of three facts about global living conditions that I want to remember. Each of them describes the current situation and the direction of change.
Fact #1: Since 1960, child deaths have plummeted from 20 million a year to 6 million a year.
Imagine how awful it must be to see your child die.
Then consider that every minute this happens to about 11 parents. This is the number of children, younger than five years of age, who die—on average—every single minute. Eleven deaths every minute for 24 hours add up to 15,500 deaths per day, or 5.6 million deaths per year.
Do we just have to accept that? Is that just how the world is?
Clearly no. We are very much able to drive positive change. Look at the chart below. The same UN data that shows us that 5.6 million are dying today also shows us that in the 1950s and 60s the world saw around 20 million children dying every year.
One key reason why we struggle to see progress in the world today is that we do not know how very bad the past was.
Both are true at the same time: The world is much better than in the past and it is still awful.
To bring this to mind I need to know both statistics: When someone says we can sit back and relax because the world is in a much better place, I point out that 11 children are still dying every minute. We cannot accept the world as it is today. And when I feel hopeless in the face of this tragedy, I remember that we reduced annual child deaths from 20 million to 5.6 million in the last fifty years.
So I am remembering the current extent of child mortality and the direction of change that we have seen: The number of child deaths is falling; there were 3.5-times as many child deaths 50 years ago. But child deaths are still extremely common; 11 children are dying every minute.
Fact #2: Since 1960, the fertility rate has fallen by half.
The chart below shows the key statistic to understand about world population growth: the global fertility rate—the average number of children per woman in the world. When the fertility rate is close to 2 children per woman, so that every couple is on average replaced by about two children, population growth is slow. But until the late 1960s, each woman had on average more than 5 children, and at such high fertility rates, population growth is fast. At that time the world population increased by 2 percent every year.
The availability of contraceptives allows parents to have only as many children as they want. And that number changes as people’s income goes up. From decades of demographic research, we know that women decide to have fewer children as they get access to better education and better opportunities in the job market. We also know that when child mortality falls, so that families do not need to fear that their children will die, they consequently decide to have fewer children in the first place.
Improvements in conditions for women and the health of children have driven a rapid reduction in fertility rates across the world. In fact, the global fertility rate has halved in the last 50 years, from more than 5 children per woman to fewer than 2.5 children. The world population growth rate has also halved in the last 50 years and is just above 1 percent.
The statistic that I remember on population growth is the one that tells me that rapid population growth is coming to an end in this century. In the last 50 years the global fertility rate has fallen from 5 children per woman to less than 2.5 children per woman. In fifty years the fertility rate has halved.
Fact #3: 137,000 people escaped extreme poverty every day between 1990 and 2015.
Living in poverty means that many of the most essential things in life are out of reach. People in poverty tend to lack decent shelter and basic healthcare, and they often struggle to afford adequate food supplies.
People are considered to live in ‘extreme poverty’ if they have to get by on less than 1.90 international-dollars per day, which is a currency that corrects for price differences between countries and inflation.
In this definition of poverty, the term extreme poverty is clearly appropriate: this is a very low poverty line.
When you ask people whether the world is making progress against extreme poverty, the majority of us believe things are getting worse—that the number of people in extreme poverty in the world is rising.
The opposite is true. Both the number and the share of people in extreme poverty is falling:
In 1990, 1.86 billion people were living on less than 1.90 international-$ per day—more than every third person in the world. Twenty-five years later, the number of people living in extreme poverty has more than halved to 706 million, every tenth person.
This is a very large transformation. It means that, on average, every day for the past 25 years 137,000 fewer people were living in extreme poverty than the day before. On every day in the last 25 years there could have been a newspaper headline reading, “The number of people in extreme poverty fell by 137,000 since yesterday.”
This is the statistic I remember: Today every 10th person is living in extreme poverty—706 million people. An unacceptably large number of people. But we should also know that the trend is moving in the right direction. The number of people in extreme poverty is falling. It is possible to end extreme poverty.
Remembering these facts about the world brings to mind why I think it is important to get engaged in global development. The statistics on the current state of the world make clear that we cannot be complacent about the world as it is today. Especially because progress is uneven, and in sub-Saharan Africa progress has been slower, but is not absent. The statistics on global change over time tell us that it is possible to work for a better world. The number of child deaths is dropping. The challenges of rapid population growth will not continue indefinitely. And the number of people in extreme poverty is falling.
Let’s continue in this direction. Our past successes should encourage us to work for more progress.
Lifesavers
What kangaroos can teach us about saving lives
A simple, low-cost intervention can have a huge impact on newborn health.
I write a lot about new inventions that are improving people’s health and saving lives around the world. But some breakthrough ideas don’t involve any new technology at all. Let me tell you about one of my favorite examples—a solution that is readily available, requires no special equipment, and is so cheap any government can support it.
It’s called kangaroo mother care—continuous skin-to-skin contact between mothers and low-birth weight or premature babies. Combined with exclusive breastfeeding, this practice prevents neonatal deaths by regulating the baby’s temperature, accelerating weight gain, and reducing the risk of infections. What’s more, it encourages mother-infant bonding at a critical time of the child’s development.
Two Colombian pediatricians, Edgar Rey and Hector Martinez, developed kangaroo mother care in the 1970s. The doctors were struggling to care for preterm infants in Bogota, where few incubators were available. Looking for a solution, they drew inspiration from how kangaroos care for their young. Baby kangaroos, born the size of a lima bean, develop inside the pouch on their mother’s belly where they can feed and stay warm.
Years later, study after study has proven the benefits of skin-to-skin contact between mothers and their newborns. For preterm babies, it’s even better than warming them in an incubator. And even as new lifesaving technologies are introduced to facilities to support newborns, kangaroo mother care is an opportunity to keep mothers at the center of their baby’s care.
When kangaroo care has been adopted on a national scale, the impact is truly remarkable. Rwanda, for example, cut its newborn mortality rate by 30 percent between 2008 and 2015, largely due to the spread of kangaroo mother care along with encouraging exclusive breastfeeding and cutting the umbilical cord in a hygienic way.
Surprisingly, despite its clear benefits, kangaroo mother care is not practiced widely. But it should be. Every year, about 2.7 million newborns die during their first month of life. The majority of newborn deaths occur in parts of the world where there are no hospitals or clinics nearby, and no access to skilled birth attendants.
Many of these lives could be saved with simple, affordable health interventions like kangaroo mother care. Our foundation, along with many other organizations, have been working to spread the word about kangaroo mother care with policymakers and health officials so more parents can be trained to use this lifesaving practice.
If you need another reason to be convinced of the power of kangaroo mother care: A recent study found that this practice is a gift that keeps on giving. Kangaroo mother care had “significant, long-lasting social and behavioral protective effects” on children as they entered young adulthood. Parents who practiced kangaroo mother care were more protective and nurturing, and their children were less likely to miss school and less likely to be aggressive or hyperactive. These positive effects were still present in the children 20 years later! Now that’s a smart investment in our children’s future.
Business boost
Giving foreign aid helps America’s economy
Investing in the health of the world’s poor is good for U.S. companies
I’m a big fan of America’s investments in the health and well-being of the world’s poor. Unfortunately, not everyone feels the same way. In fact, some in Washington D.C. have proposed dramatic cuts in foreign assistance.
That would be a terrible mistake. Last month I wrote about how foreign aid helps keep Americans safe. In this post, I want to show how smart health and development programs promote America’s economy, and how cutting back on these investments could backfire on American workers.
(As I said in my previous post, these security and economic arguments aren’t what inspired Melinda and me to get involved in global health. What inspired us was the chance to save children from dying of preventable diseases. But over the years I’ve come to see the connection to America’s security and economy as well.)
I start from the simple premise that everyone is better off when there are more middle-income countries in the world. As a country climbs up the economic ladder, you see concrete improvements in the lives of its people. Richer countries are less likely to go to war and more capable of preventing global epidemics. And they can afford to buy more products from other countries, including the United States.
Here’s one example from my experience with Microsoft. From our earliest days, we intended to expand into markets beyond the United States. In 1986, we chose Tokyo for the site of our first foreign office. That bet paid off phenomenally well. For a time, we sold more software in Japan than anywhere else.
You may be thinking, “Of course an ambitious software company would want a foothold in Japan.” But it wasn’t always so obvious. Just a few decades before we opened our Tokyo office, Japan had been devastated by World War II. Its economy and infrastructure lay in ruins. How did they recover? Among other things, through smart aid programs from the United States and others. By the 1980s Japan’s economy was booming, and the country presented a great opportunity for companies like us. To this day, sales there are a key part of Microsoft’s success and these sales have produced many jobs in Japan and America alike.
Microsoft’s experience in Japan is part of a larger trend that’s still going on today, as more countries join the ranks of the middle class. Countless U.S. companies are doing business in places that used to get American aid but have become self-sufficient, including South Korea, Brazil, Mexico, Vietnam, and Thailand.
Here’s another way that U.S. investments abroad help American businesses: by connecting them directly with new customers and suppliers. America’s chief aid agency, USAID, uses its expertise to encourage private companies to collaborate on projects. For example, they have worked with Cargill and Land O’Lakes to help dairy farmers in East Africa raise their productivity, increasing the value of the companies’ exports to places like Kenya and Uganda. As the companies’ CEOs wrote, “This benefits not only the farmers in Africa, but food producers and their workers in the United States and it promotes goodwill in a part of the world that can be a market for more American goods in the future.” USAID has also worked with Walmart to train thousands of women farmers in sub-Saharan Africa, and with Starbucks, Keurig, and others to help coffee farmers in Latin America improve their crops so they can join the global market.
These and other efforts are part of America’s global economic leadership. Pulling back now would mean retreating from the world stage at a time when other countries are doubling down on their investments. It would deprive American companies of potential new markets and make them less competitive, while also harming the health and productivity of some of the poorest people in the world. It wouldn’t be robbing Peter to pay Paul; it would be robbing Peter and then robbing Paul too.
So it’s good for the American economy when other countries join the middle class. But how much credit does aid deserve for making that happen?
It’s a hard question to answer; growth has many causes. My own conclusion, based on years of looking at the evidence and discussing it with experts, is that although aid may not directly cause growth, there is a strong indirect connection between the two. Moving to the middle class requires a strong education system and good infrastructure, nutrition, and healthcare—and smart, targeted aid can promote those things pretty effectively.
Fighting AIDS, for example, saves lives, and it increases productivity because societies are stronger when they have healthy teachers, police officers, and entrepreneurs. Countries that worked with PEPFAR—America’s phenomenally successful effort to slow the AIDS epidemic—improved three times more on one measure of economic development than their non-PEPFAR counterparts.
Their per-capita income also grew quickly. Between 2005 and 2015, for example, Tanzania’s per-person income went up more than 37 percent. Zambia’s went up 55 percent. Ethiopia’s rose 107 percent. And as these countries grew, so did their appetite for American goods. In the same time frame, U.S. exports to Tanzania rose by more than 77 percent, U.S. exports to Zambia went up 189 percent, and to Ethiopia, 241 percent.
Many other countries are making similar gains. The point is not that aid directly makes poor people richer. It’s that aid helps create a foundation for growth. Along with many other factors, it helps remove some of the barriers that keep people from making the most of their talents. And when people in one place do better, the rest of us do better too.
We can build on this progress if the United States helps maintain the momentum. Investments in aid—which account for less than 1 percent of the federal budget—are an essential part of the solution. We need to keep making them on behalf of Americans and people around the world.
Endgame
Let’s make this the last pandemic
My new book is all about how we eliminate the pandemic as a threat to humanity.
The great epidemiologist Larry Brilliant once said that “outbreaks are inevitable, but pandemics are optional.” I thought about this quote and what it reveals about the COVID-19 pandemic often while I was working on my new book.
On the one hand, it’s disheartening to imagine how much loss and suffering could’ve been avoided if we’d only made better choices. We are now more than two years into the pandemic. The world did not prioritize global health until it was too late, and the result has been catastrophic. Countries failed to prepare for pandemics, rich countries reduced funding for R&D, and most governments failed to strengthen their health systems. Although we’re finally reaching the light at the end of the tunnel, COVID still kills several thousand people every day.
On the other hand, Dr. Brilliant’s quote makes me feel hopeful. No one wants to live through this again—and we don’t have to. Outbreaks are inevitable, but pandemics are optional. The world doesn’t need to live in fear of the next pandemic. If we make key investments that benefit everyone, COVID-19 could be the last pandemic ever.
This idea is what my book, How to Prevent the Next Pandemic , is all about. I’ve been part of the effort to stop COVID since the early days of the outbreak, working together with experts from inside and out of the Gates Foundation who have been fighting infectious diseases for decades. I’m excited to share what I've learned along the way, because our experience with COVID gives us a clear pathway for how to be ready next time.
So, how do we do it? In my book, I explain the steps we need to take to get ready. Together, they add up to a plan for eliminating the pandemic as a threat to humanity. These steps—alongside the remarkable progress we’ve already made over the last two years in creating new tools and understanding infectious diseases—will reduce the chance that anyone has to live through another COVID.
Imagine a scenario like this: A concerning outbreak is rapidly identified by local public health agencies, which function effectively in even the world’s poorest countries. Anything out of the ordinary is shared with scientists for study, and the information is uploaded to a global database monitored by a dedicated team.
If a threat is detected, governments sound the alarm and initiate public recommendations for travel, social distancing, and emergency planning. They start using the blunt tools that are already on hand, such as quarantines, antivirals that protect against almost any strain, and tests that can be performed anywhere.
If this isn’t sufficient, then the world’s innovators immediately get to work developing new tests, treatments, and vaccines. Diagnostics in particular ramp up extremely fast so that large numbers of people can be tested in a short time. New drugs and vaccines are approved quickly, because we’ve agreed ahead of time on how to run trials safely and share the results. Once they’re ready to go into production, manufacturing gears up right away because factories are already in place and approved.
No one gets left behind, because we’ve already worked out how to rapidly make enough vaccines for everyone. Everything gets where it’s supposed to, when it’s supposed to, because we’ve set up systems to get products delivered all the way to the patient. Communications about the situation are clear and avoid panic.
And this all happens quickly. The goal is to contain outbreaks within the first 100 days before they ever have the chance to spread around the world. If we had stopped the COVID pandemic before 100 days, we could’ve saved over 98 percent of the lives lost.
I hope people who read the book come away with a sense that ending the threat of pandemics forever is a realistic, achievable, and essential goal. I believe this is something that everyone—whether you’re an epidemiologist, a policymaker, or just someone who’s exhausted from the last two years–should care about.
The best part is we have an opportunity to not just stop things from getting worse but to make them better. Even when we’re not facing an active outbreak, the steps we can take to prevent the next pandemic will also make people healthier, save lives, and shrink the health gap between the rich and the poor. The tools that stop an outbreak can also help us find and treat more HIV cases. They can protect more children from deadly diseases like malaria, and they can give more people around the world access to high quality care.
Shrinking the health gap was the life’s work of my friend Paul Farmer, who tragically died in his sleep in February. That’s why I’m dedicating my proceeds from this book to his organization Partners in Health, which provides amazing health care to people in some of the poorest countries in the world. I will miss Paul deeply, but I am comforted by the knowledge that his influence will be felt for decades to come.
If there’s one thing the world has learned over the last two years, it’s that we can’t keep living with the threat of another variant—or another pathogen—hanging over our heads. This is a pivotal moment. There is more momentum than ever before to stop pandemics forever. No one who lived through COVID will ever forget it. Just like a war can change the way a generation looks at the world, COVID has changed the way we see the world.
Although it may not always feel like it, we have made tremendous progress over the last two years. New tools will let us respond faster next time, and new capabilities have made us better prepared to fight deadly pathogens. The world wasn’t ready for COVID, but we can choose to be ready next time.
Everyone, everywhere
Vaccinate the world in six months
To prevent pandemics, we need to be able to do it. Here’s how.
The greatest medical breakthrough of this pandemic—and surely one of the most important in decades—is the creation of COVID-19 vaccines. One study found that in their first year, they saved more than 1 million lives and prevented 10 million hospitalizations in the U.S. alone. The number of deaths averted around the world is of course far higher. It’s horrifying to think what COVID-19 would be doing to humanity if it weren’t for vaccines.
The world has a lot to be proud of in the creation and delivery of these vaccines. Scientists have never developed one nearly as quickly as they did in 2020, and the governments of the world have never run immunization campaigns that were as fast and as far-reaching as the ones that took place in 2021.
But there are also serious problems that we need to solve before the next potential pandemic comes along. One is the huge inequity in who has been vaccinated and who has not. It is both unjust and unwise to give a third shot to a healthy 25-year-old in a rich country before a 75-year-old cancer survivor in a poor country gets her first shot.
Another concern is that the speed with which vaccines were created was only partly a matter of skill and diligence. It was also a matter of luck.
Because coronaviruses had already caused two previous outbreaks (SARS and MERS), scientists had learned quite a lot about the structure of the virus. In particular, they had identified its characteristic spike protein—the tips on the crownlike virus you’ve seen a dozen pictures of—as a potential target for vaccines. When it came time to create new vaccines, they had a sense of what part of the virus was most vulnerable to attack.
In the next outbreak, we may not be so lucky. It could be caused by a virus that scientists haven’t studied as closely, or by one they’ve never seen at all.
This is why the world needs to adopt a serious plan for developing, manufacturing, and distributing new vaccines to prevent another pandemic. The manufacturing alone is a huge challenge: To prevent the inequities we’ve seen in COVID-19, the world needs to be ready to produce enough vaccines for everyone on the planet within six months of discovering a new pathogen. That’s 8 billion doses for a single-dose vaccine, and 16 billion for a two-dose version. In a typical year, around 5 billion or 6 billion doses are produced—that’s all vaccines combined.
The plan needs to cover four steps, starting with accelerating the invention of new vaccines.
During the pandemic, the process of creating a new vaccine got a huge boost (no pun intended). Typically, the process involves a lot of trial and error: Scientists spend years identifying weak spots in the virus and trying to identify vaccine candidates that would teach the immune system to attack them.
The creation of the first mRNA vaccines during the COVID-19 pandemic was a big step forward. They work by delivering genetic code to your body that instructs it to make shapes that look like the weak part of the virus. Your immune system notices that those shapes are foreign and sets out to attack them. Once it does, it remembers what the shapes looked like and will attack them the next time they show up. That’s what makes you immune.
One reason mRNA vaccines were so revolutionary is that they’re easily adapted for different pathogens. Once the weak spot of a virus has been identified—a process made much easier by recent advances in mapping viral genomes—it’s simply a matter of changing the genetic code in the vaccine so that it tells your body to make a new shape. This can be done in a matter of days.
As a result, the development of new vaccines will be exponentially faster—as long as researchers have the same deep understanding of future pathogens as they did of coronaviruses. So it is imperative to invest in basic research on a wider array of known viruses and other pathogens, so we understand as much as possible before the next outbreak.
Once a vaccine has been invented, the second step is to test it and get it approved for use in humans. Typically, it takes years to run all the trials necessary to prove that a vaccine is safe and effective—including time spent recruiting tens of thousands of volunteers. Assuming the vaccine proves out, it can take another year to get it authorized by the WHO and the relevant government agencies.
But when an outbreak is threatening to go global, we won’t have years. So we need ways to speed up the process without sacrificing the safety and effectiveness that people have come to expect from vaccines.
The world should build on models like the RECOVERY trial in the U.K. It set up protocols for running drug trials in advance and built infrastructure that made it much easier to get started once COVID hit. In addition, the agencies that regulate vaccines need to agree ahead of time on how volunteers will be enrolled in trials and on the software tools that will enable people around the world to sign up as soon as the disease strikes. And by connecting diagnostic tests to the trial system, we can automatically suggest to doctors that their patients should join a trial if they’re eligible.
The third step, once a vaccine has been approved for use in humans, is to make enough of it fast enough to stop the outbreak. Ending a relatively small outbreak might require hundreds of thousands of doses of a new vaccine, which is not hard to make. (The world already produces more than 5 billion doses of vaccines every year.) But countries need to be prepared for the worst—another big outbreak in which everyone needs to be vaccinated—so we must be ready to produce as many as 8 billion or even 16 billion, roughly triple the amount manufactured in a typical year.
During COVID-19, the closest thing to a breakthrough in manufacturing vaccines was the proliferation of second-source deals. These are agreements in which a company that invented a vaccine agrees to let other companies use their factories to make it. (Picture Honda Accords rolling off the line of a Ford facility.)
It’s hard to overstate the impact of second-source deals during COVID-19. In less than two years, a single manufacturer, AstraZeneca, signed second-source deals involving 25 factories in 15 countries. (AZ also agreed to forgo its profits on the COVID vaccine.) Novavax also signed one with Serum Institute of India—leading to a COVID-19 vaccine now being used in many countries—and Johnson & Johnson signed one with the Indian company Biological E. Limited and the South African firm Aspen Pharmacare. All told, second-source deals led to the production of billions of additional COVID vaccine doses.
In the future, such deals could be done even faster if companies that have them now can maintain their relationships with one another so they can hit the ground running during the next outbreak.
mRNA vaccines could also help speed up manufacturing. Many of the conventional ways to make vaccines are quite complex, so it can take a lot of time to transfer the technology and know-how from one company to another. But because the basic approach to mRNA is pretty much the same—you just swap out your old mRNA for the new one and make sure the lipid is made the right way—it should be easier to transfer between companies. There are also some new modular technologies in the pipeline that, if they prove out, will make it cheaper and easier to build and run factories that can be adapted to make different vaccines.
Finally, the fourth step in the world’s plan should be to make sure that new vaccines reach everyone who needs them—including people who live in low-income countries. In 2021, only 8 percent of people in those countries received at least one dose of a COVID-19 vaccine, while more than half of the world’s population did.
So how can the world make sure that doesn’t happen in future outbreaks?
One key is to take on the problem of vaccine hesitancy. Check out this video about how, by dealing with rumors and myths, one community in India increased its COVID-19 vaccination rate by a factor of five and created a model that other communities are now taking up:
Another key is to make sure it’s possible to manufacture enough vaccines that supply is not a limiting factor, as it was during much of 2021. Another is to make sure that vaccines are affordable for every country. Organizations like COVAX have helped with that during COVID-19. It also helps to work with manufacturers in developing countries to design new vaccines that are much cheaper to produce than existing ones. This is how the price of the pentavalent vaccine, which protects against five debilitating and deadly diseases, dropped from $3.50 per dose to less than $1 a dose—which in turn allowed the number of children who get it every year to increase by more than 16 times since 2005.
There are also a lot of innovations that make it easier to deliver vaccines. For example, auto-disable syringes have a built-in safety mechanism so health workers can’t accidentally poke themselves or use them more than once. New coolers can keep vaccines at the right temperature for longer. Advanced methods for delivering vaccines, such as replacing the needle and syringe with a small patch containing micro-needles—picture something that looks superficially like the nicotine patches that people use to stop smoking—will also help.
With these advances, it will be possible to achieve something amazing beyond preventing pandemics: eradicating entire families of pathogens. The world could rid itself of all coronaviruses, for example, or even all influenza viruses. A future without pandemics—and without the flu—is worth investing in.

Heroic acts
Meet the heroes in Africa fighting back against this pandemic—and working to prevent the next one
As Africa faces many challenges during the pandemic, these heroes are making a difference.
In Africa, the latest statistics on COVID-19 are discouraging. Just 6 percent—about 78 millionof the continent’s 1.3 billion people have been fully vaccinated. Worldwide, by comparison, 43 percent are fully vaccinated, and boosters are now widely available in many countries.
Without enough vaccines available in Africa, COVID-19 marches on infecting millions of people. Even assessing the true scale of the pandemic on the continent is difficult. A recent World Health Organization assessment estimated that only one in seven cases of COVID in Africa are being detected because of a limited amount of testing.
And while many Western and Asian countries are recovering economically from the pandemic and returning to some version of normalcy, most countries in Africa continue to struggle. Disruptions to schooling, health care, and livelihoods have sunk many families deeper into poverty, leaving them without enough food and basic services.
We should all be upset about this inequity. (I’ve written recently about this divide and the steps the world needs to take to get the virus under control.) It’s critical that more be done to get vaccines into the arms of the people at high risk for COVID, including the elderly and immunocompromised, who are living in low-income countries. And the recent detection of the Omicron variant serves as a reminder of how important increasing vaccination rates is to deter new mutations of the virus from emerging.
But even during this difficult time, I think it’s important to highlight the many Africans who are fighting back against this pandemic. They are stepping up to alleviate suffering, to combat misinformation, and to develop the tools needed to prevent future pandemics.
There are thousands of examples of heroic work being done in Africa during this pandemic. Here are three stories of organizations and individuals who are working to save lives and bring hope to their communities.
1. South Africa: The Truck
As COVID-19 swept across South Africa, one of the most pressing needs was access to public health information. People needed to know about the virus and how to stay safe. And as South Africa started rolling out COVID vaccines this year, health officials were also tasked with counteracting the spread of misinformation about the virus and vaccines. This was especially challenging in hard-to-reach communities in South Africa, where people don’t have access to television and other media. But UNICEF, in partnership with the national government, had an answer to this challenge: A truck. Not just any truck but a multi-media messenger on wheels. The truck has LED screens, which allows the truck’s organizer to broadcast videos telling local stories about COVID-19. They also organize presentations in communities to raise awareness of the virus, teach people how to prevent its spread, and promote COVID testing and vaccinations. The truck has logged more than 40,000 miles and delivered messages to hundreds of thousands of people.
2. Lesotho: Mamello Makhele
Mamello Makhele is a nurse-midwife working to improve health care for women in rural Lesotho, where there are high rates of maternal mortality. During the pandemic lockdowns many health facilities closed, leaving women living in these remote communities without access to family planning services. On foot and by donkey, Mamello travels high into the mountain to offer health care, deliver babies, and distribute contraceptives. Mamello has also worked nationwide to empower young women, encouraging them to take control of their health and prevent unwanted pregnancies. Thanks to her incredible work, many women are healthier today in Lesotho.
3. Tanzania: Afyadata
Even as the world seeks to end the current COVID-19 pandemic, we need to also be thinking about how to prevent future pandemics. That’s just what a mobile app called Afyadata is helping health officials do in Tanzania. Designed by the Southern African Center for Infectious Disease Surveillance (SACIDS), Afyadata is a digital surveillance tool that allows health workers and even ordinary people to serve as disease detectives. Users can report unusual health occurrences not only in humans, but also animals. Monitoring animals is critical because most new pathogens start in animals before they spread and sicken humans. With the app, farmers can easily report any suspicious illness among their livestock to health officials, who can then quickly follow up with further investigation, if necessary. While this app is still being piloted in several districts of Tanzania and other parts of Africa, it has already been effective in the detection and identification of several small disease outbreaks. I look forward to learning more about Afyadata’s progress.
Inspiring acts
7 unsung heroes of the pandemic
Incredible people caring for those in need during COVID-19.
When I was a kid, my image of a hero was largely inspired by my dad’s collection of early Superman comics. I read them all. A “hero” was somebody who had supernatural powers like flying, laser vision, or the strength to bend steel.
As humans, of course, we’re all pretty limited in our physical powers. We don’t fly. We can’t see through walls. But what’s unbounded in us is our ability to see injustices and to take them on—often at great risk to ourselves.
My work in global health and development has introduced me to many extraordinary heroes with this kind of superpower. And I’ve had the honor of highlighting many of them on this blog: An epidemiologist who helped eradicate smallpox. A doctor working to end sexual violence in Africa. A researcher working to end hunger with improved crops. Just to name a few.
Why do we need heroes?
Because they represent the best of who we can be. Their efforts to solve the world’s challenges demonstrate our values as a society and they serve as powerful examples of how to make a positive difference in the world. And if enough people hear about their actions, they can inspire others to do something heroic too.
If there’s ever been a time that we need heroes, it’s now. The COVID-19 pandemic has created unprecedented health and economic challenges, especially for the most vulnerable among us. The good news is that many people from all walks of life are doing their part to help them. Health care workers. Scientists. Firefighters. Grocery store workers. Aid workers. Vaccine trial participants. And ordinary citizens caring for their neighbors.
Here are portraits of a few individuals from around the world working to alleviate suffering during this pandemic. I hope their stories inspire you just as much as they have me.
To these heroes and heroes everywhere, thank you for the work you do!

Abundant air
Breathing new hope into Africa’s fight against COVID-19
In Africa’s battle against COVID-19, a Kenyan doctor is making sure every breath counts.
As the COVID-19 pandemic spreads across Africa, hospitals across the continent face shortages of essential medical supplies needed to treat the respiratory disease and keep patients alive.
Not just masks and ventilators, but oxygen.
For people living in wealthy countries, medical oxygen is often taken for granted. In many low-income countries, however, oxygen is often in short supply or not available at all. And globally, a lack of oxygen –needed to treat pneumonia, malaria, and other diseases—leads to hundreds of thousands of deaths each year.
Addressing this often overlooked challenge is the life’s work of Bernard Olayo, a Kenyan doctor who founded Hewatele, an innovative organization working to ensure all patients—even in remote areas of the country—have access to oxygen.
Now, he is playing a critical role in Kenya’s preparations to tackle COVID-19 by scaling up oxygen supplies that will be needed to keep the most critically ill patients alive.
While the number of COVID-19 cases in Africa remains low compared to other parts of the world, the continent is bracing for a surge of infections. According to the World Health Organization, up to 190,000 people could die of COVID-19 in Africa if the disease is not controlled. A widespread outbreak would flood many of Africa’s fragile health systems.
A lot of attention has been focused on the lack of ventilators in Africa. Ventilators are the mechanical devices that help patients breathe, pushing air in and out of their lungs, when they can’t on their own. And the shortage of them is a real problem. But the lack of oxygen itself is equally worrying. The coronavirus attacks the respiratory tract, inflaming the lungs and making it difficult for patients to breathe. Oxygen, delivered through a mask or nasal tube, is an essential and effective first line of treatment that’s less invasive than being on a ventilator. Oxygen is also needed to run a ventilator. If COVID-19 patients have access to oxygen as an initial treatment, however, it may prevent many of them from becoming so critically ill that they would require one of the limited number of ventilators to breathe.
What Bernard is hoping to avoid during this pandemic are the painful choices he faced as a young doctor because of a lack of oxygen. After medical school he was posted to a rural hospital, where many of the patients were children battling pneumonia who needed oxygen for treatment. But Bernard soon learned that there was never enough oxygen available. He and the other hospital staff often had to share a single cylinder of oxygen between patients. When there were too many patients and not enough oxygen, he and other doctors would be forced to decide which children would receive oxygen and live, and which would go without it and sometimes die—a choice that broke his heart, he says.
That experience inspired Bernard to investigate the source of Kenya’s oxygen supply shortages. He discovered that one of the biggest challenges is that oxygen is expensive in Africa. In Kenya, oxygen costs about 13 times more than what it does in the United States. The high cost was driven, in part, by a lack of competition. In many countries, including Kenya, there was just a single oxygen supplier for the entire country. And with many health facilities located hundreds of miles away from the oxygen plants, transportation costs drove up prices even higher. The long distances and poor roads also meant that deliveries were unreliable. Hospitals and clinics would regularly run out of oxygen supplies.
In 2014, Bernard founded a public-private partnership to try a new approach that would make access to medical oxygen more affordable and reliable. He named the organization Hewatele (Swahili for “abundant air”). Given the delivery challenges in Kenya, Bernard decided to build oxygen plants at several of the busiest hospitals in the country, where demand is highest and reliable electricity for production is available. The oxygen is then sent out for delivery using a milkman model, with oxygen cylinders regularly dropped off at remote hospitals and clinics and the empty cylinders returned to be refilled. This system ensures that there is always more than enough oxygen available at each facility. Using this new approach, Hewatele has cut the market price for oxygen in Kenya by 50 percent. Now, Bernard is working to expand the number of oxygen plants in Kenya and bring Hewatele’s business model to other parts of Africa.
While the COVID-19 pandemic has brought much needed attention to the oxygen gap in Africa, more needs to be done to ensure that everyone has access to this simple medical intervention. Thanks to Bernard’s efforts, progress is being made. His work has already helped save the lives of thousands of children and adults and will save many more in the future—one breath at a time.

Catastrophe averted
How to fight malaria during a pandemic
Despite COVID-19 disruptions, Africa’s malaria programs have kept up lifesaving malaria control and treatment efforts.
At the start of the pandemic, many people feared that not only would COVID-19 itself be a disaster, but the lockdowns and other prevention methods would have an awful ripple effect: disrupting the fight against malaria in a catastrophic way.
A modeling analysis from the World Health Organization, which I shared here last year, found that annual malaria deaths in sub-Saharan Africa could double, returning to death rates not seen in over 20 years.
A year later, I’m happy to be able to report that this worst-case scenario, at least for now, has been avoided. This is thanks to the leadership of African countries, which quickly adapted their malaria programs to meet the challenges of the pandemic. Practicing social distancing and other safety measures, malaria workers were able to carry out their duties, delivering long-lasting insecticide-treated bed nets, controlling mosquito populations with indoor spraying, and providing preventive treatment for pregnant women and children. In Nigeria, which still suffers from 60 million cases of malaria each year, health workers managed to even increase their delivery of malaria control, protecting millions of children in one of their largest campaigns to date.
At the same time, malaria resources have served double duty, tackling the mosquito-borne disease and helping to control the spread of COVID-19.
In Zambia, the scientists and equipment in the National Malaria Elimination Program’s genomic surveillance laboratory used to monitor malaria drug resistance quickly pivoted to find COVID-19 variants in the country. In Mozambique, an app created for health workers to provide real-time reporting of malaria cases and fevers has supplied critical data to the national COVID response.
Despite this progress, our work is not over. Malaria still kills more than 400,000 people each year. And pandemic lockdowns and movement restrictions have hampered some critical malaria activities, including access to diagnosis and treatment efforts in Africa.
Still, I’m optimistic that a world without malaria is within reach. And the COVID-19 pandemic reminds us why eradicating malaria is essential. Many of the building blocks we need to fight malaria and prevent the next pandemic are the same: accurate, real-time data; reliable supply chains to bring medicines and resources where they are needed most; and cross-country collaboration.
Investments in malaria programs help build stronger health systems that will not only save lives and bring an end to malaria, but also protect us from the next pandemic. And that creates a healthier, safer world for all.
Birthday Potty
Flush with innovation: 10 years of reinventing the toilet
A decade of innovation has yielded hundreds of new sanitation solutions that will prevent illness and death.
Ten years ago, our foundation challenged the world to reinvent the toilet.
To raise awareness of this challenge, I shared a stage with a jar of human feces.
Took a giant whiff of pit latrine odor.
Drank water made from fecal sludge.
And convinced Jimmy Fallon to drink it too.
All these stunts got some laughs, but my goal was to draw attention to a serious problem: poor sanitation.
About 3.6 billion people—nearly half of the world’s population—lack toilets or use unsafe sanitation.
Living without a toilet is more than an inconvenience. It’s dangerous. Unsafe sanitation means contaminated water, soil, and food. It causes illness and death.
According to the latest estimates, diarrhea and other sanitation-related diseases kill nearly 500,000 children under the age of five every year.
As the world gets more crowded, the human toll of unsafe sanitation will only increase. The United Nations estimates that between now and 2050, the world’s population will grow by two billion people. More than 90 percent of that growth will be concentrated in cities and in developing countries—places that are least likely to have good sanitation.
The COVID pandemic has also served as a powerful reminder of the urgent work households and cities must do to contain and treat deadly pathogens.
But this sanitation crisis can be solved.
In 2011, our foundation’s Reinvent the Toilet Challenge asked researchers if they could develop safe sanitation solutions that work without relying on sewage systems or running water. (Sewers and treatment plants have historically been the best way to safely process waste, but they are extremely expensive to build, maintain, and operate. They also rely on large amounts of water when many countries are suffering from water shortages.)
In the decade since we launched this challenge, the world has responded with the power of innovation. Scientists and engineers from across the globe developed hundreds of exciting ideas for how to design toilets that safely process human waste with little or no need for water or electricity. They created toilets that convert feces into valuable resources, including fertilizer, clean water, and electricity.
Other researchers invented a new system to process fecal sludge from pit latrines, septic tanks and sewers that turns human waste from entire communities into drinkable water and electricity. These machines, called omni-processors, can be used to support a fecal sludge treatment plant or complement a waste-water treatment plant. And they require a fraction of the energy, space and cost that a traditional sewer and wastewater treatment plant require.
In the next phase of the Reinvent the Toilet work, a team of researchers led by Dr. Shannon Yee at Georgia Institute of Technology is taking the best of these ideas to develop a low-cost reinvented toilet. It’s called the Generation 2 Reinvented Toilet. You can read more about the progress Shannon and his team have made here.
To be sure, there are still challenges ahead to bring these innovations to market so that they can transform the lives of the billions of people who need them.
But I’m optimistic about what can be accomplished in the next 10 years and beyond.
75 million toilets
India is winning its war on human waste
In India toilets are saving lives and boosting the economy.
Nearly three years ago, Indian Prime Minister Narendra Modi made one of the boldest comments on public health that I have ever heard from an elected official. It's still having a big impact today.
He made the comment during his first speech to the nation commemorating India's Independence Day. Modi said: “We are living in the 21st century. Has it ever pained us that our mothers and sisters have to defecate in the open?... The poor womenfolk of the village wait for the night; until darkness descends, they can`t go out to defecate. What bodily torture they must be feeling, how many diseases that act might engender. Can`t we make arrangements for toilets for the dignity of our mothers and sisters?”
I can’t think of another time when a national leader has broached such a sensitive topic so frankly and so publicly. Even better, Modi backed up his words with actions. Two months after that speech, he launched a campaign called Clean India (“Swachh Bharat” in Hindi), which now includes ending open defecation nationwide by 2019, installing 75 million toilets throughout the country—75 million!—and making sure that no untreated waste is dumped into the environment.
On my most recent visit to India, I made a video about this amazing undertaking:
If you’re wondering why the Prime Minister would put a spotlight on a subject that most of us would rather not even think about, take a look at the statistics. Of the 1.7 million people worldwide who die from unsafe water, sanitation, and hygiene each year, more than 600,000 are in India. A quarter of young girls there drop out of school because there’s no decent toilet available. When you factor in the deaths, sickness, and lost opportunity, poor sanitation costs India more than $106 billion a year.
In other words, solving this problem will save hundreds of thousands of lives every year, help girls stay in school, and boost the country’s economy. Improving sanitation is a big focus for our foundation, and we’re working closely with the Indian government in support of its goals.
There are two keys to achieving the targets of Clean India. One involves giving everyone access to a well-managed toilet, which means all the waste is treated (either on-site or in a treatment facility) to remove the pathogens that make people sick. It’s crucial to get the entire process right, from containing the waste in a toilet to collecting it, transporting it if necessary, and treating it. If one link in the chain fails, people still get sick.
Unfortunately, in many places, it’s not feasible to lay down sewer pipes or build treatment facilities. That’s why Indian researchers are testing a variety of new tools, including redesigned toilets that don’t require sewer systems and advanced ways to treat human waste.
So far, the progress is impressive. In 2014, when Clean India began, just 42 percent of Indians had access to proper sanitation. Today 63 percent do. And the government has a detailed plan to finish the job by October 2, 2019, the 150th anniversary of Mahatma Gandhi’s birth. Officials know which states are on track and which are lagging behind, thanks to a robust reporting system that includes photographing and geotagging each newly installed toilet.
But giving people access to toilets isn’t enough. You also have to persuade them to use the toilets. That’s the second key to Clean India, and in some ways it is even harder than the first. People can be reluctant to change old habits.
Clean India has ingenious ways of tackling that problem. In some communities, groups of children band together to call out people who are defecating in the open and encourage them to use public toilets instead. In a pilot project that will be expanded next year, the government worked with Google so users in 11 cities could search online for the nearest public toilets, get directions, and read reviews by other users. On streets throughout the country, billboards remind passers-by of the mission. Stars from Bollywood films and cricket teams speak out on TV and radio. Even India’s currency features the Swachh Bharat logo.
The hard work is paying off. Today more than 30 percent of Indian villages have been declared free of open defecation, up from 8 percent in 2015. (You can track the progress on this handy dashboard.)
What I love most about Clean India is that it identified a big problem, got everyone working on it, and is using measurement to show where things need to be done differently. As the old saying goes, What gets measured gets done. If you don’t set ambitious targets and chart your progress, you end up settling for business as usual—and in this case, business as usual would mean poor sanitation keeps killing more than half a million Indians every year.
By aiming high, the people of India are demanding change, and they are taking action to make it happen. It is a great example for other countries and an inspiration for all of us who believe everyone deserves a chance at a healthy, productive life.
War on Pathogens
Update: what ever happened to the machine that turns feces into water?
An update on the machine that turns feces into water.
Earlier this year, I shared a video where I drank water made from feces. (My review: It was delicious.) Today the machine that produced the water, the Janicki Omni Processor—or JOP—is in Dakar, Senegal, as part of a pilot project that could ultimately save lives and reduce disease in poor countries. Here’s an update on where things stand:
You may recall that the JOP takes human waste and turns it into drinking water, electricity, and ash. (It is actually one of several Omni Processors being developed that treat human waste and produce something of value.) It’s tempting to focus on the drinking water, for obvious reasons. But the goal is not to provide water. The goal is to dramatically improve sanitation for all the cities in poor countries.
Today at least 2 billion people use latrines that aren’t properly drained, and diseases caused by poor sanitation kill some 700,000 children every year. Unfortunately, rich-world solutions aren’t feasible in poor countries—they require too much expensive infrastructure. (We put together this slideshow so you can see how the system works in Dakar today and how the JOP fits in.) The idea behind every Omni Processor design is to solve this problem by making sanitation affordable for the poor.
We think we have solved the big engineering challenges, thanks to ingenious design work by our partners Janicki Bioenergy. The technology just keeps getting better: The next version of the machine will burn most types of garbage in addition to human waste, and it will be easier to maintain. We also think we have a good business plan. Janicki is discussing the sale of the first JOP to a Senegalese company, and they’re talking to potential buyers in wealthier countries too.
But business plans and brilliant engineering are not enough. The machine has to be tested—and unlike a computer program, sanitation machines can’t be tested from a desk in Seattle. The real world introduces lots of variables. For example, you have to find the right personnel to run the machine. You have to work with local and national governments and gauge the public’s reaction.
So it is great that we are now on the learning curve with a unit in the field. So far, the results on all fronts have been promising. The JOP is working as predicted. The partners in Dakar, especially the national sanitation utility, have been fantastic—you can see in the video how energetic and optimistic they are. At every step, we’re learning and will incorporate what we find in future designs and operating plans. For example, the team is still looking at ways to make the JOP cheaper and smaller.
Much of the technology involved in the JOP has been around for years. So why hasn’t anyone built one before now? Because the people who understood the technology weren’t getting sick or dying from contaminated water, and they didn’t know anyone who was. Nor was it clear how they could make a profit by working on the problem. It was a classic market failure.
Now we have a business plan, an impassioned team of engineers, great in-country partners, and a pilot project in motion. I think we have a real shot at solving the sanitation problem. This is a great example of what can happen when we get bright people focused on the world’s biggest problems.
Polio
Iron will
I can’t think of a more important moment than right now in the fight against polio.
Most people today probably don’t know what this is.
And that’s a good thing because it shows how much progress the world has made against polio, a terrible and now largely forgotten disease.
This metal tank is an iron lung, a mechanical respirator that saved the lives of thousands of polio victims.
Polio attacks the body’s nervous system, crippling patients. In the worst cases, the disease paralyzes their respiratory muscles and makes it difficult for them to breathe, sometimes resulting in death.
Using changes in air pressure, the iron lung pulls air in and out of a patient’s lungs, allowing them to breathe and stay alive.
During the height of the polio epidemic in the U.S. in the 1940s and 1950s, rows of iron lungs filled hospital wards to treat thousands of polio patients, most of them children.
Polio
Meeting the Musahar
A trip to a remote corner of India taught me a powerful lesson about what it will take to wipe out polio.
Whenever someone asks me why I believe it’s possible to eradicate polio, I tell them about my 2010 trip to India to visit one of the country’s lowest castes—the Musahar.
Today, India is polio free. But less than a decade ago, more than half the world’s cases of polio could be found in India. At the time, many health experts said that India would be the last place on Earth to stop polio because its high birth rate, poor sanitation, and population density allowed the disease to flourish.
So how did they wipe out the disease?
The answer can be found in the remote marshlands of the Kosi River in the Indian state of Bihar. The region is home to one of the poorest, most underserved castes in India, the Musahar. In 2010, vaccinating the Musahar and other people living in remote, high-risk areas was one of the biggest obstacles India faced in its long campaign to end the paralyzing disease. Thousands of children were being missed during the national immunization drives, allowing the disease to continue to spread.
In response, the Indian government launched an all-out effort to reach every child, employing a new communication campaign to mobilize support for polio immunization and better maps to ensure that no family was missed. They deployed more than 2 million vaccinators who covered every speck of the country, including the Musahar village I visited, which was often inaccessible because of flooding from the Kosi River. (One of the most inspiring photographs of that time was an image of polio workers wading waste deep in water to reach remote villages with the polio vaccine.)
By 2014, India achieved its goal of being polio free, proving that the paralyzing disease could be defeated in the most complicated circumstances. With new ties to even the remotest communities, health workers are providing children with much more than the polio vaccine. They continue to work with local communities to improve the delivery of other critical health services, including maternal and newborn care, as well as vaccinations for measles and other preventable diseases.
India’s experience continues to be an inspiration for the world’s final push to wipe out polio in the three countries where it endures: Afghanistan, Pakistan, and Nigeria. Based on the latest figures, in 2017, there were just 21 identified cases of wild poliovirus in the world—the lowest number ever—down from 350,000 cases per year when the global polio eradication effort launched in 1988.
That’s an incredible achievement. But now is no time for complacency. If polio is a threat anywhere in the world, it is a threat to us all. That’s why it’s more important than ever for the world to continue to support the millions of vaccinators who are working tirelessly to finish the job. Their dream, as is mine, is to see the day that polio is defeated.
Exemplars
We’re finally learning why countries excel at saving lives
A new program is spreading the word about the most successful approaches to health.
Ever since I was a teenager, I’ve tackled every big new problem the same way: by starting off with two questions. I used this technique at Microsoft, and I still use it today. I ask these questions literally every week about COVID-19.
Here they are: Who has dealt with this problem well? And what can we learn from them?
They seem like obvious questions, but sometimes it's surprisingly hard to find the answers—especially when it comes to global health. There are low- and middle-income countries that have made huge leaps in, for example, delivering vaccines or ending malnutrition. But anyone who wants to identify those countries, find out how they did it, and apply the lessons in their own country would have their work cut out for them.
In sports, every coach is able to study the most successful teams and figure out what they’re doing well. There’s no reason that things should be any different when the goal is preventing childhood deaths instead of scoring touchdowns.
That’s why I was eager to be part of a global effort to fill the gap. Over the past three years, health experts and organizations from countries at every income level (including the Gates Foundation) have come together to find out who has made the most progress on certain health problems, identify what made them so successful, and help others put these lessons into action.
The result of all this effort—the Exemplars in Global Health program—launched earlier this year. If you want to know which countries have made the most progress with limited resources, Exemplars is a great place to start.
For now, Exemplars focuses on five areas: under-five mortality; vaccine delivery; the role of community health workers; epidemic preparedness and response; and childhood stunting (the reduction in physical and mental development caused by poor nutrition). The team will be adding other areas, including newborn and maternal mortality, family planning, maternal anemia, and primary health care systems.
The Exemplars team has scoured the world for the best performers and worked with experts in those countries to find out what worked so well. For example, they identified seven countries that have excelled at reducing the number of children who die before their fifth birthday: Bangladesh, Cambodia, Ethiopia, Nepal, Peru, Rwanda, and Senegal. The Exemplars website has a profile of each country, detailing insights from its work that other countries could learn from.
Bangladesh—whose childhood mortality rate dropped 56 percent between 2000 and 2015—used data, research, and testing especially well, and empowered women to make decisions about their children’s health. Peru, which achieved roughly the same decline as Bangladesh, conducted local studies to identify interventions that might suit specific communities. All seven countries built up strong community health systems and made specific efforts to close the equity gap by reaching the poorest people.
Of course, not all lessons can be applied in the same way everywhere. What works in one country may not work exactly the same way in another. And it is not always obvious how to implement big changes in national health systems, which are very complex and require a lot of coordination among the government, the private sector, and non-profits.
Recognizing these challenges, the Exemplars program is much more than a website. There is also a community of global and in-country experts ready to help countries make the case for investing in the most effective programs and figure out how to adapt the lessons to their particular needs. We’re not interested in simply getting the information out there—we want to help drive change.
Our hope is to connect with decisionmakers: people who work in the governments of low- and middle-income countries, at development agencies like America’s USAID and the World Bank, and at organizations that implement health programs. Exemplars is all about figuring out how to improve health care based on evidence of what works. It will help governments use time and money more efficiently—and with the COVID-19 pandemic, there has never been a greater need to get the most impact out of every dollar spent.
I’m grateful to all the people in governments, academia, and non-profits who made the Exemplars program possible. We all started out with one goal in mind: to accelerate the progress in improving health, so that the poorest countries don't have 20 times the childhood death rate of the richest ones. I think Exemplars is a great resource that will spread success stories so even countries with very little money can benefit. And that will, ultimately, save lives.
Amazing results
This partnership helped prevent 13 million deaths
Childhood deaths have been cut in half since 1990. Vaccines are a big reason why.
Vaccines have been saving lives for centuries. But from the time Edward Jenner created the first vaccine in the late 1700s, not everyone has had equal access to them. As a result, children in some parts of the world continued to die from diseases that were preventable in other parts.
When Melinda and I learned about this inequity over twenty years ago, we thought it was infuriating—and deeply unfair. So, in 2000, our foundation teamed up with countries whose children were impacted the most, the World Health Organization, the World Bank, UNICEF, vaccine manufactures, and donors to do something about it. Together, we created an organization called Gavi, the Vaccine Alliance.
Gavi works with governments to make sure that every child has access to the lifesaving vaccines they need. The organization makes this happen by negotiating vaccines at prices that are affordable for the poorest countries. Since Gavi guarantees high volumes, manufacturers are able to lower the cost of vaccines quite dramatically. Gavi also helps low-income countries strengthen systems to deliver vaccines to all communities.
Over the last two decades, Gavi has helped vaccinate more than 760 million children and prevented more than 13 million deaths. That’s a truly amazing result.
Governments and partners from around the world are meeting virtually today to raise funds for Gavi’s next five years of work. This investment is more important than ever before, because Gavi is going to play a key role in making sure that, when we have COVID-19 vaccines, they reach the most vulnerable people. Their expertise and experience in distributing vaccines will be invaluable as we work to end this outbreak once and for all.

Scanning for answers to a pandemic
A new surveillance program in Seattle is detecting cases of COVID-19 and helping guide public health responses.
In any fight, it’s important to know your enemy. Unfortunately, in our battle against COVID-19, there’s a lot that we still don’t know.
How many people are infected with the virus, including those without symptoms?
Is it seasonal or weather dependent?
And how will we know when it might be safe to get back to work and send kids back to school?
These are important questions. More testing, of course, will help us answer them. But with tests in short supply in many parts of the world, including the U.S., it is impossible to test everyone—at least for now.
That’s why I’m excited about a new disease surveillance program in the Seattle area to detect cases of COVID-19 and help guide public health responses. Not only will it help improve our understanding of the outbreak in Seattle, it will also provide valuable information about the virus for other communities around the world.
The greater Seattle Coronavirus Assessment Network—or SCAN—is a first-of-its-kind disease surveillance platform for COVID-19 that allows participants to use a self-swab test to collect their own nasal samples and send them to a lab without leaving home. As a surveillance program, SCAN’s goal isn’t to test every person or serve as a replacement for medical care. Instead, SCAN is testing a sample of people in the Seattle region, including those who are healthy as well as those who are feeling sick. The test results and other data (like a person’s age, gender, race, zip code, and any underlying health conditions) are used by researchers, data modelers, and public health officials to paint a clearer picture of how COVID-19 is moving through the community, who is at greatest risk, and whether physical distancing measures are working.
One of the biggest questions puzzling public health officials is exactly how many people are infected with the virus. Think about the pandemic like an iceberg, says Dr. Jay Shendure, scientific director of the Brotman Baty Institute, one of SCAN’s lead partners. With ongoing COVID-19 medical testing, which has been largely focused on people with symptoms, we have been able to see the tip of the iceberg. Just below the surface, however, there is the part of the iceberg we don’t see—the unknown number of people who are infected but experience mild symptoms or no symptoms at all. Dr. Shendure compares SCAN to “a set of sonar pings where we’re skimming over the water and pinging to see what lurks beneath.”
I want to be clear that SCAN does not replace the widespread testing that is still needed in communities. But it has the potential to become an important tool for health officials seeking insights about the spread and behavior of the virus. Early results from SCAN found many cases of COVID-19 in Seattle that might otherwise have gone undetected among individuals who had experienced some symptoms (fever, cough, or shortness of breath) but had not yet sought medical care. As SCAN gathers more test results in the weeks ahead, researchers expect the new data to provide a better sense of the number of infections and serve as one source to help answer other questions, like when physical distancing measures can be relaxed.
SCAN is a partnership between Public Health—Seattle & King County, the Brotman Baty Institute, University of Washington Medicine, Fred Hutchinson Cancer Research Center, and Seattle Children’s Hospital. It relies on data modeling support from the Institute for Disease Modeling (IDM) and receives support from my private office, Gates Ventures, and our foundation.
SCAN is an outgrowth of a research study started before COVID-19. It’s been clear for years that there was a lot the scientific community didn’t understand about respiratory viruses, such as how they spread through a community, and the best ways to stop them. So, in 2018, my office teamed up with the Brotman Baty Institute and other partners to launch a study of respiratory illnesses, including the seasonal flu. That effort, the Seattle Flu Study, aimed to recruit 10,000 volunteers in Seattle who showed cold symptoms to provide a simple nasal swab at kiosks set up in health centers and through at-home tests.
One of the early discoveries of the study was the impact of high-intensity physical distancing measures on reducing the flu. In the winter of 2019, a major snowstorm in Washington state led to week-long school and workplace closures. Analyzing the data from that flu season, researchers found that the snowstorm’s dramatic disruption of social contact led to a drop in the transmission of the flu and other respiratory illnesses.
The Flu Study team hoped that these and other findings would help researchers develop tools to curb and even prevent the spread of the flu—and maybe one day help public health officials prepare for a future pandemic.
That day arrived sooner than anyone ever imagined with COVID-19.
In late January 2020, the first confirmed case of the novel coronavirus appeared in the U.S., just outside Seattle. The patient had visited Wuhan, China, the origin of the outbreak.
Several weeks later, the Seattle Flu Study team started picking up signs of the coronavirus’s genetic signature in their flu study survey samples. In February, they identified the first known case of transmission in the U.S.—a teenager living outside Seattle who had not traveled to China and had no link to anyone with the virus. The Flu Study team sequenced its genome, and quickly realized that the virus had been spreading undetected for weeks.
This finding and the discovery of dozens more coronavirus cases suddenly put the Seattle Flu Study at the center of the area’s response to the coronavirus. We were fortunate to have this existing surveillance platform and an experienced team to quickly shift their focus to the outbreak. In March, we formed the new SCAN partnership with King County’s public health agency to track the spread of COVID-19.
One of the innovations of SCAN is an easy-to-use, at-home, self-swab test kit. The key advantage of this at-home testing approach is that people don’t need to go to a clinic, where they risk exposing themselves or others to infection. People interested in participating in SCAN can enroll online, and, once approved, they get a test delivered directly to their home. After individuals complete the nasal swab test, a courier service picks it up from their home and returns it to SCAN for processing. Anyone who has a positive result gets contacted by a public health worker who provides guidance on how to care for themselves and their families. And all participants can check their results online.
SCAN is currently testing 300 people per day, but actively working to test more. Those test results are then analyzed by disease modelers to map virus transmission chains. By examining the genetic signature of an infection, they can determine whether it represents a new introduction to the region or is part of a local transmission. They can also use the data to estimate disease prevalence and build models to look at how the virus is responding to certain measures—like school closures and physical distancing. You can learn more about their work on Nextstrain and the Institute for Disease Modeling’s research site.
As the SCAN team collects more data, I’m looking forward to learning more about their insights into many of the questions we have about this pandemic and how we can prevent the next one.
The vaccine race, explained
What you need to know about the COVID-19 vaccine
Humankind has never had a more urgent task than creating broad immunity for coronavirus.
One of the questions I get asked the most these days is when the world will be able to go back to the way things were in December before the coronavirus pandemic. My answer is always the same: when we have an almost perfect drug to treat COVID-19, or when almost every person on the planet has been vaccinated against coronavirus.
The former is unlikely to happen anytime soon. We’d need a miracle treatment that was at least 95 percent effective to stop the outbreak. Most of the drug candidates right now are nowhere near that powerful. They could save a lot of lives, but they aren’t enough to get us back to normal.
Which leaves us with a vaccine.
Humankind has never had a more urgent task than creating broad immunity for coronavirus. Realistically, if we’re going to return to normal, we need to develop a safe, effective vaccine. We need to make billions of doses, we need to get them out to every part of the world, and we need all of this to happen as quickly as possible.
That sounds daunting, because it is. Our foundation is the biggest funder of vaccines in the world, and this effort dwarfs anything we’ve ever worked on before. It’s going to require a global cooperative effort like the world has never seen. But I know it’ll get done. There’s simply no alternative.
Here’s what you need to know about the race to create a COVID-19 vaccine.
The world is creating this vaccine on a historically fast timeline.
Dr. Anthony Fauci has said he thinks it’ll take around eighteen months to develop a coronavirus vaccine. I agree with him, though it could be as little as 9 months or as long as two years.
Although eighteen months might sound like a long time, this would be the fastest scientists have created a new vaccine. Development usually takes around five years. Once you pick a disease to target, you have to create the vaccine and test it on animals. Then you begin testing for safety and efficacy in humans.
Safety and efficacy are the two most important goals for every vaccine. Safety is exactly what it sounds like: is the vaccine safe to give to people? Some minor side effects (like a mild fever or injection site pain) can be acceptable, but you don’t want to inoculate people with something that makes them sick.
Efficacy measures how well the vaccine protects you from getting sick. Although you’d ideally want a vaccine to have 100 percent efficacy, many don’t. For example, this year’s flu vaccine is around 45 percent effective.
To test for safety and efficacy, every vaccine goes through three phases of trials:
- Phase one is the safety trial. A small group of healthy volunteers gets the vaccine candidate. You try out different dosages to create the strongest immune response at the lowest effective dose without serious side effects.
- Once you’ve settled on a formula, you move onto phase two, which tells you how well the vaccine works in the people who are intended to get it. This time, hundreds of people get the vaccine. This cohort should include people of different ages and health statuses.
- Then, in phase three, you give it to thousands of people. This is usually the longest phase, because it occurs in what’s called “natural disease conditions.” You introduce it to a large group of people who are likely already at the risk of infection by the target pathogen, and then wait and see if the vaccine reduces how many people get sick.
After the vaccine passes all three trial phases, you start building the factories to manufacture it, and it gets submitted to the WHO and various government agencies for approval.
This process works well for most vaccines, but the normal development timeline isn’t good enough right now. Every day we can cut from this process will make a huge difference to the world in terms of saving lives and reducing trillions of dollars in economic damage.
So, to speed up the process, vaccine developers are compressing the timeline. This graphic shows how:
In the traditional process, the steps are sequential to address key questions and unknowns. This can help mitigate financial risk, since creating a new vaccine is expensive. Many candidates fail, which is why companies wait to invest in the next step until they know the previous step was successful.
For COVID-19, financing development is not an issue. Governments and other organizations (including our foundation and an amazing alliance called the Coalition for Epidemic Preparedness Innovations) have made it clear they will support whatever it takes to find a vaccine. So, scientists are able to save time by doing several of the development steps at once. For example, the private sector, governments, and our foundation are going to start identifying facilities to manufacture different potential vaccines. If some of those facilities end up going unused, that’s okay. It’s a small price to pay for getting ahead on production.
Fortunately, compressing the trial timeline isn’t the only way to take a process that usually takes five years and get it done in 18 months. Another way we’re going to do that is by testing lots of different approaches at the same time.
There are dozens of candidates in the pipeline.
As of April 9, there are 115 different COVID-19 vaccine candidates in the development pipeline. I think that eight to ten of those look particularly promising. (Our foundation is going to keep an eye on all the others to see if we missed any that have some positive characteristics, though.)
The most promising candidates take a variety of approaches to protecting the body against COVID-19. To understand what exactly that means, it’s helpful to remember how the human immune system works.
When a disease pathogen gets into your system, your immune system responds by producing antibodies. These antibodies attach themselves to substances called antigens on the surface of the microbe, which sends a signal to your body to attack. Your immune system keeps a record of every microbe it has ever defeated, so that it can quickly recognize and destroy invaders before they make you ill.
Vaccines circumvent this whole process by teaching your body how to defeat a pathogen without ever getting sick. The two most common types—and the ones you’re probably most familiar with—are inactivated and livevaccines. Inactivated vaccines contain pathogens that have been killed. Live vaccines, on the other hand, are made of living pathogens that have been weakened (or “attenuated”). They’re highly effective but more prone to side effects than their inactivated counterparts.
Inactivated and live vaccines are what we consider “traditional” approaches. There are a number of COVID-19 vaccine candidates of both types, and for good reason: they’re well-established. We know how to test and manufacture them.
The downside is that they’re time-consuming to make. There’s a ton of material in each dose of a vaccine. Most of that material is biological, which means you have to grow it. That takes time, unfortunately.
That’s why I’m particularly excited by two new approaches that some of the candidates are taking: RNA and DNA vaccines. If one of these new approaches pans out, we’ll likely be able to get vaccines out to the whole world much faster. (For the sake of simplicity, I’m only going to explain RNA vaccines. DNA vaccines are similar, just with a different type of genetic material and method of administration.)
Our foundation—both through our own funding and through CEPI—has been supporting the development of an RNA vaccine platform for nearly a decade. We were planning to use it to make vaccines for diseases that affect the poor like malaria, but now it’s looking like one of the most promising options for COVID. The first candidate to start human trials was an RNA vaccine created by a company called Moderna.
Here’s how an RNA vaccine works: rather than injecting a pathogen’s antigen into your body, you instead give the body the genetic code needed to produce that antigen itself. When the antigens appear on the outside of your cells, your immune system attacks them—and learns how to defeat future intruders in the process. You essentially turn your body into its own vaccine manufacturing unit.
Because RNA vaccines let your body do most of the work, they don’t require much material. That makes them much faster to manufacture. There’s a catch, though: we don’t know for sure yet if RNA is a viable platform for vaccines. Since COVID would be the first RNA vaccine out of the gate, we have to prove both that the platform itself works and that it creates immunity. It’s a bit like building your computer system and your first piece of software at the same time.
Even if an RNA vaccine continues to show promise, we still must continue pursuing the other options. We don’t know yet what the COVID-19 vaccine will look like. Until we do, we have to go full steam ahead on as many approaches as possible.
It might not be a perfect vaccine yet—and that’s okay.
The smallpox vaccine is the only vaccine that’s wiped an entire disease off the face of the earth, but it’s also pretty brutal to receive. It left a scar on the arm of anyone who got it. One out of every three people had side effects bad enough to keep them home from school or work. A small—but not insignificant—number developed more serious reactions.
The smallpox vaccine was far from perfect, but it got the job done. The COVID-19 vaccine might be similar.
If we were designing the perfect vaccine, we’d want it to be completely safe and 100 percent effective. It should be a single dose that gives you lifelong protection, and it should be easy to store and transport. I hope the COVID-19 vaccine has all of those qualities, but given the timeline we’re on, it may not.
The two priorities, as I mentioned earlier, are safety and efficacy. Since we might not have time to do multi-year studies, we will have to conduct robust phase 1 safety trials and make sure we have good real-world evidence that the vaccine is completely safe to use.
We have a bit more wiggle room with efficacy. I suspect a vaccine that is at least 70 percent effective will be enough to stop the outbreak. A 60 percent effective vaccine is useable, but we might still see some localized outbreaks. Anything under 60 percent is unlikely to create enough herd immunity to stop the virus.
The big challenge will be making sure the vaccine works well in older people. The older you are, the less effective vaccines are. Your immune system—like the rest of your body—ages and is slower to recognize and attack invaders. That’s a big issue for a COVID-19 vaccine, since older people are the most vulnerable. We need to make sure they’re protected.
The shingles vaccine—which is also targeted to older people—combats this by amping up the strength of the vaccine. It’s possible we do something similar for COVID, although it might come with more side effects. Health authorities could also ask people over a certain age to get an additional dose.
Beyond safety and efficacy, there are a couple other factors to consider:
- How many doses will it be? A vaccine you only get once is easier and quicker to deliver. But we may need a multi-dose vaccine to get enough efficacy.
- How long does it last? Ideally, the vaccine will give you long-lasting protection. But we might end up with one that only stops you from getting sick for a couple months (like the seasonal flu vaccine, which protects you for about six months). If that happens, the short-term vaccine might be used while we work on a more durable one.
- How do you store it? Many common vaccines are kept at 4 degrees C. That’s around the temperature of your average refrigerator, so storage and transportation is easy. But RNA vaccines need to be stored at much colder temperature—as low as -80 degrees C—which will make reaching certain parts of the world more difficult.
My hope is that the vaccine we have 18 months from now is as close to “perfect” as possible. Even if it isn’t, we will continue working to improve it. After that happens, I suspect the COVID-19 vaccine will become part of the routine newborn immunization schedule.
Once we have a vaccine, though, we still have huge problems to solve. That’s because…
We need to manufacture and distribute at least 7 billion doses of the vaccine.
In order to stop the pandemic, we need to make the vaccine available to almost every person on the planet. We’ve never delivered something to every corner of the world before. And, as I mentioned earlier, vaccines are particularly difficult to make and store.
There’s a lot we can’t figure out about manufacturing and distributing the vaccine until we know what exactly we’re working with. For example, will we be able to use existing vaccine factories to make the COVID-19 vaccine?
What we can do now is build different kinds of vaccine factories to prepare. Each vaccine type requires a different kind of factory. We need to be ready with facilities that can make each type, so that we can start manufacturing the final vaccine (or vaccines) as soon as we can. This will cost billions of dollars. Governments need to quickly find a mechanism for making the funding for this available. Our foundation is currently working with CEPI, the WHO, and governments to figure out the financing.
Part of those discussions center on who will get the vaccine when. The reality is that not everyone will be able to get the vaccine at the same time. It’ll take months—or even years—to create 7 billion doses (or possibly 14 billion, if it’s a multi-dose vaccine), and we should start distributing them as soon as the first batch is ready to go.
Most people agree that health workers should get the vaccine first. But who gets it next? Older people? Teachers? Workers in essential jobs?
I think that low-income countries should be some of the first to receive it, because people will be at a much higher risk of dying in those places. COVID-19 will spread much quicker in poor countries because measures like physical distancing are harder to enact. More people have poor underlying health that makes them more vulnerable to complications, and weak health systems will make it harder for them to receive the care they need. Getting the vaccine out in low-income countries could save millions of lives. The good news is we already have an organization with expertise about how to do this in Gavi, the Vaccine Alliance.
With most vaccines, manufacturers sign a deal with the country where their factories are located, so that country gets first crack at the vaccines. It’s unclear if that’s what will happen here. I hope we find a way to get it out on an equitable basis to the whole world. The WHO and national health authorities will need to develop a distribution plan once we have a better understanding of what we’re working with.
Eventually, though, we’re going to scale this thing up so that the vaccine is available to everyone. And then, we’ll be able to get back to normal—and to hopefully make decisions that prevent us from being in this situation ever again.
It might be a bit hard to see right now, but there is a light at the end of the tunnel. We’re doing the right things to get a vaccine as quickly as possible. In the meantime, I urge you to continue following the guidelines set by your local authorities. Our ability to get through this outbreak will depend on everyone doing their part to keep each other safe.
Innovation vs. the coronavirus
The first modern pandemic (short read)
The scientific advances we need to defeat COVID-19.
This post originally appeared as an opinion piece in the Washington Post. It’s adapted from a longer article, which you can read here.
It’s entirely understandable that the national conversation has turned to a single question: “When can we get back to normal?” The shutdown has caused immeasurable pain in jobs lost, people isolated, and worsening inequity. People are ready to get going again.
Unfortunately, although we have the will, we don’t have the way—not yet. Before the United States and other countries can return to business and life as usual, we will need some innovative new tools that help us detect, treat, and prevent COVID-19.
It begins with testing. We can’t defeat an enemy if we don’t know where it is. To reopen the economy, we need to be testing enough people that we can quickly detect emerging hotspots and intervene early. We don’t want to wait until the hospitals start to fill up and more people die.
Innovation can help us get the numbers up. The current coronavirus tests require that health-care workers perform nasal swabs, which means they have to change their protective gear before every test. But our foundation supported research showing that having patients do the swab themselves produces results that are just as accurate. This self-swab approach is faster and safer, since regulators should be able to approve swabbing at home or in other locations rather than having people risk additional contact.
Another diagnostic test under development would work much like an at-home pregnancy test. You would swab your nose, but instead of sending it into a processing center, you’d put it in a liquid and then pour that liquid onto a strip of paper, which would change color if the virus was present. This test may be available in a few months.
We need one other advance in testing, but it’s social, not technical: consistent standards about who can get tested. If the country doesn’t test the right people—essential workers, people who are symptomatic, and those who have been in contact with someone who tested positive—then we’re wasting a precious resource and potentially missing big reserves of the virus. Asymptomatic people who aren’t in one of those three groups should not be tested until there are enough tests for everyone else.
The second area where we need innovation is contact tracing. Once someone tests positive, public-health officials need to know who else that person might have infected.
For now, the United States can follow Germany’s example: interview everyone who tests positive and use a database to make sure someone follows up with all their contacts. This approach is far from perfect, because it relies on the infected person to report their contacts accurately and requires a lot of staff to follow up with everyone in person. But it would be an improvement over the sporadic way that contact tracing is being done across the United States now.
An even better solution would be the broad, voluntary adoption of digital tools. For example, there are apps that will help you remember where you have been; if you ever test positive, you can review the history or choose to share it with whoever comes to interview you about your contacts. And some people have proposed allowing phones to detect other phones that are near them by using Bluetooth and emitting sounds that humans can’t hear. If someone tested positive, their phone would send a message to the other phones, and their owners could get tested. If most people chose to install this kind of application, it would probably help some.
Naturally, anyone who tests positive will immediately want to know about treatment options. Yet, right now, there is no treatment for COVID-19. Hydroxychloroquine, which works by changing the way the human body reacts to a virus, has received a lot of attention. Our foundation is funding a clinical trial that will give an indication whether it works on COVID-19 by the end of May, and it appears the benefits will be modest at best.
But several more-promising candidates are on the horizon. One involves drawing blood from patients who have recovered from COVID-19, making sure it is free of the coronavirus and other infections, and giving the plasma (and the antibodies it contains) to sick people. Several major companies are working together to see whether this succeeds.
Another type of drug candidate involves identifying the antibodies that are most effective against the novel coronavirus, and then manufacturing them in a lab. If this works, it is not yet clear how many doses could be produced; it depends on how much antibody material is needed per dose. In 2021, manufacturers may be able to make as few as 100,000 treatments or many millions.
If, a year from now, people are going to big public events—such as games or concerts in a stadium—it will be because researchers have discovered an extremely effective treatment that makes everyone feel safe to go out again. Unfortunately, based on the evidence I’ve seen, they’ll likely find a good treatment, but not one that virtually guarantees you’ll recover.
That’s why we need to invest in a fourth area of innovation: making a vaccine. Every additional month that it takes to produce a vaccine is a month in which the economy cannot completely return to normal.
The new approach I’m most excited about is known as an RNA vaccine. (The first COVID-19 vaccine to start human trials is an RNA vaccine.) Unlike a flu shot, which contains fragments of the influenza virus so your immune system can learn to attack them, an RNA vaccine gives your body the genetic code needed to produce viral fragments on its own. When the immune system sees these fragments, it learns how to attack them. An RNA vaccine essentially turns your body into its own vaccine manufacturing unit.
There are at least five other efforts that look promising. But because no one knows which approach will work, a number of them need to be funded so they can all advance at full speed simultaneously.
Even before there’s a safe, effective vaccine, governments need to work out how to distribute it. The countries that provide the funding, the countries where the trials are run, and the ones that are hardest-hit will all have a good case that they should receive priority. Ideally, there would be global agreement about who should get the vaccine first, but given how many competing interests there are, this is unlikely to happen. Whoever solves this problem equitably will have made a major breakthrough.
World War II was the defining moment of my parents’ generation. Similarly, the coronavirus pandemic—the first in a century—will define this era. But there is one big difference between a world war and a pandemic: All of humanity can work together to learn about the disease and develop the capacity to fight it. With the right tools in hand, and smart implementation, we will eventually be able to declare an end to this pandemic—and turn our attention to how to prevent and contain the next one.

3 steps
What our leaders can do now
These decisions will affect the course of COVID-19.
There’s no question the United States missed the opportunity to get ahead of the novel coronavirus. But the window for making important decisions hasn’t closed. The choices we and our leaders make now will have an enormous impact on how soon case numbers start to go down, how long the economy remains shut down and how many Americans will have to bury a loved one because of COVID-19.
Our foundation has been working to slow the outbreak for several months. To date, we’ve invested $105 million in efforts to create new therapeutics, expand access to testing, and limit the virus’s impact here in Seattle.
As a result of this work, I’ve spoken with experts and leaders in Washington and across the country. It’s become clear to me that we must take three steps.
First, we need a consistent nationwide approach to shutting down. Despite urging from public health experts, some states and counties haven’t shut down completely. In some states, beaches are still open; in others, restaurants still serve sit-down meals.
This is a recipe for disaster. Because people can travel freely across state lines, so can the virus. The country’s leaders need to be clear: Shutdown anywhere means shutdown everywhere. Until the case numbers start to go down across America—which could take 10 weeks or more—no one can continue business as usual or relax the shutdown. Any confusion about this point will only extend the economic pain, raise the odds that the virus will return, and cause more deaths.
Second, the federal government needs to step up on testing. Far more tests should be made available. We should also aggregate the results so we can quickly identify potential volunteers for clinical trials and know with confidence when it’s time to return to normal. There are good examples to follow: New York state recently expanded its capacity to more than 25,000 tests per day.
There’s also been some progress on more efficient testing methods, such as the self-swab developed by the Seattle Coronavirus Assessment Network, which allows patients to take a sample themselves without possibly exposing a health worker. I hope this and other innovations in testing are scaled up across the country soon.
Even so, demand for tests will probably exceed the supply for some time, and right now, there’s little rhyme or reason to who gets the few that are available. As a result, we don’t have a good handle on how many cases there are or where the virus is likely headed next, and it will be hard to know if it rebounds later. And because of the backlog of samples, it can take seven days for results to arrive when we need them within 24 hours.
This is why the country needs clear priorities for who is tested. First on the list should be people in essential roles such as health-care workers and first responders followed by highly symptomatic people who are most at risk of becoming seriously ill and those who are likely to have been exposed.
The same goes for masks and ventilators. Forcing 50 governors to compete for lifesaving equipment—and hospitals to pay exorbitant prices for it—only makes matters worse.
Finally, we need a data-based approach to developing treatments and a vaccine. Scientists are working full speed on both; in the meantime, leaders can help by not stoking rumors or panic buying. Long before the drug hydroxychloroquine was approved as an emergency treatment for COVID-19, people started hoarding it, making it hard to find for lupus patients who needed it to survive.
We should stick with the process that works: Run rapid trials involving various candidates and inform the public when the results are in. Once we have a safe and effective treatment, we’ll need to ensure that the first doses go to the people who need them most.
To bring the disease to an end, we’ll need a safe and effective vaccine. If we do everything right, we could have one in less than 18 months—the fastest a vaccine has ever been developed. But creating a vaccine is only half the battle. To protect Americans and people around the world, we’ll need to manufacture billions of doses.
Without a vaccine, developing countries are at even greater risk than wealthy ones, because it’s even harder for them to do physical distancing and shutdowns. The further down the income ladder people live, the more important it is that they go to work every day just to feed their family.
If they live in the poorest parts of sub-Saharan Africa or India, staying home simply isn’t an option. Even if they do stay home, they can’t just wall themselves off from their neighbors; in slums, the houses are packed together so closely that there’s no way to keep your distance. All the work that rich countries are doing now to develop vaccines will save lives in those places, too.
We can get a head start on manufacturing all of the doses we’ll need now by building the facilities where these vaccines will be made. Because many of the top candidates are made using unique equipment, we’ll have to build facilities for each of them, knowing that some won’t get used. Private companies can’t take that kind of risk, but the federal government can. It’s a great sign that the administration made deals this week with at least two companies to prepare for vaccine manufacturing. I hope more deals will follow.
In 2015, I urged world leaders in a TED talk to prepare for a pandemic the same way they prepare for war—by running simulations to find the cracks in the system. As we’ve seen this year, we have a long way to go. But I still believe that if we make the right decisions now, informed by science, data, and experience of medical professionals, we can save lives and get the country back to work.
A version of this post originally appeared on the website of the Washington Post.
It’s a small world
What if everyone in the world lived on the same street?
I could spend hours exploring the website Dollar Street.
I’m obsessed with a website called Dollar Street. Created by Factfulness co-author Anna Rosling Rönnlund, Dollar Street imagines a world where everyone lives on the same street and the houses are ordered by income. The poorest live on one end, and the richest live on the other end.
Income can often tell you more about how people live than location can. Whenever I visit a new place, I look for clues about which income level local families live on. Are there power lines? What kind of roofs do the houses have? Are people riding bikes or walking from place to place?
The answers to these questions tell me a lot about the people there. If I see power lines, I know homes probably have electricity in this area—which means that kids have enough light to do their homework after the sun sets. If I see patchwork roofs, families likely sleep less during the rainy season because they’re wet and cold. If I see bikes, that tells me people don’t have to spend hours walking to get water every day.
The significance of income level is brilliantly illustrated by Dollar Street. Anna sent photographers to profile hundreds of homes from countries all over the world. You can sort these homes by income, location, or even household object (so for example you can have it show you just beds, or dish soap, or cooking utensils). Each house is meticulously tagged and includes a biography of the family that lives there. You can explore 135 objects belonging to each family, from their front door to the shoes they wear. The user interference is simple and intuitive to use.
Dollar Street really comes alive when you start comparing objects. I found the photos of toothbrushes to be particularly interesting. The families at the poorest end of the street use their fingers or sticks to clean their teeth. But once you reach a certain income level, everyone starts using a plastic toothbrush with bristles.
The more time you spend on Dollar Street, the clearer it becomes that all of us have the same basic wants and needs. People tend to spend money on the same things once they increase their income whether they live in China or Cameroon. At the end of the day, we all want a solid roof over our head, a more efficient way to get around, and better tools to take care of ourselves. It’s a beautiful reminder that we have more in common with people on the other side of the world than we think.
Anna and her team at Gapminder have managed to capture the most complete picture of humanity I’ve seen yet. I could spend hours exploring Dollar Street, and I hope you check it out.
Good code, big problems
Here’s one great way to use your tech skills
This technologist changed his career to help the poor.
These days I spend a lot of my time thinking about how technology can help the poorest people in the world improve their lives. It’s been a big focus for me since before Melinda and I launched our foundation. But looking back, I think I could have started down this path even sooner than I did.
People with a STEM background have a lot to offer the world of global health and development. That’s one of the reasons why I write about innovation so often here on TGN: I want to encourage software developers, inventors, and scientists to consider how they can use their skills to fight inequity. It’s deeply rewarding. You get the chance to learn from super-capable people—health care workers, farmers, political leaders—and work with them on tools that will empower them.
Last year I heard a talk from a young technologist who came to this realization sooner than I did. His name is William Wu, and he gave a fascinating demonstration at our foundation’s annual Goalkeepers meeting in New York City. Here are some highlights from his presentation:
After hearing William’s talk, I learned more about his story. He grew up in the Bay Area in the ’80s and ’90s. His parents helped him get excited about math and science from an early age. William studied engineering and computer science in college and grad school, ending up with a Ph.D. in electrical engineering from Stanford. While in grad school he met his future wife, Jiehua Chen (she goes by “JC”), who was getting a Ph.D. in statistics with a focus on global development.
After a short time writing code at various startups, William landed a job at NASA’s Jet Propulsion Laboratory, designing a telecommunications system for satellites including the International Space Station. It was fulfilling work—he had been obsessed with space since he was a kid—but eventually he realized he didn’t have to look to the stars for interesting problems to solve.
A turning point came when JC was working on soil analysis in Africa. The field team she was working with needed to convert thousands of data points on a spreadsheet into GPS coordinates, but they couldn’t figure out how to do it quickly. When JC mentioned the problem to William, he knew it could be solved with just a few lines of code. In minutes he had written a small program that did the job.
JC helped William see that someone with skills and interests like his could make a big difference in global development. In 2012, they founded their company, Quantitative Engineering Design, which develops software and hardware to improve farming and health care in developing countries. QED now employs about 20 engineers and scientists and works with national governments around the world as well as organizations like the Centers for Disease Control and Prevention.
The soil project that William describes in the video above is just one example of what QED is doing. They also built the data processing software used in Kenya by the CHAMPS project, an initiative that our foundation is funding to learn why so many young kids still die in some regions.
Another QED project involves digitizing medical forms. Throughout sub-Saharan Africa, health clinics use paper-based, handwritten medical registries. These registries contain a lot of (anonymous) data about how many patients come in and out of the clinic, the staff’s workload, the prevalence of different diseases, and so on. But because this is all done on paper, it’s hard to analyze the data for larger trends. QED is pilot-testing an app that would allow organizations to keep using paper-based books but quickly digitize the results. A health worker would use her mobile phone’s camera to scan the handwritten information, get it transcribed using optical character recognition, store it in the cloud, and export it for analysis, all in 60 seconds.
It’s too early to predict the impact of any of these projects. The point is that people with tech skills can find fascinating problems to work on and terrific partners to work with. It’s great if you decide to make a career of it, but you don’t necessarily have to. Sometimes all it takes to make a difference is the willingness to learn about a problem and use your talents to help solve it.
Our foundation maintains a list of sites that can point you to volunteer opportunities. It’s worth a look.
Meet the X-shredder
Test-tube mosquitoes might help us beat malaria
Genetic editing might help us wipe out the disease.
It’s Mosquito Week again on the Gates Notes. This year I’m exploring some of the science behind malaria and other mosquito-borne diseases. You can read below about how gene editing could play a key role in eradicating malaria. I’ve also written about amazing advances in tracking the disease and how the parasite is a deadly shapeshifter.
Humans have spent thousands of years inventing new ways to kill mosquitoes. The Romans did it by draining swamps. Today you might have a bug zapper in your back yard. In low- and middle-income countries, it’s common to see people spraying insecticides or setting up sticky traps baited with sugar.
But evolution is smart. It is one-upping us by creating mosquitoes that are harder to kill. In sub-Saharan Africa and parts of South America and southeast Asia, we are seeing an alarming number of mosquitoes that can withstand insecticides.
This is especially problematic for the fight against mosquito-borne diseases like malaria. To eradicate these diseases, we need new tools to complement the ones we already have.
Our foundation is backing a lot of different advances. One that I’m especially excited about is a set of techniques for genetically modifying mosquitoes that could dramatically reduce the number of disease-carrying insects in certain areas.
What is cool about these genetic techniques is how precise they can be. Precision matters because out of more than 3,000 species of mosquitoes, only five are responsible for causing most cases of malaria. Of those, only females spread the disease, because they’re the only ones that bite humans. (They do it when they need extra protein for reproduction. Experts call it “taking a blood meal.”) The males just drink nectar.
The promise of gene editing is that, instead of killing a bunch of mosquitoes indiscriminately, we could eliminate only the dangerous ones in a particular area. That would buy us time to cure all the people there of malaria. Then we could let the mosquito population return without the parasite.
One exciting gene-editing technique is called gene drive. The term covers several different approaches, but the basic idea is to use the CRISPR method to rewrite the usual rules of inheritance. Normally, for any given gene, there’s a 50 percent chance that a parent with that gene will pass it on to a child. (It is competing with one from the other parent, and only one of the two can win.) With gene drive, the odds go up to 100 percent. You give a few mosquitoes an edited gene that inserts—or drives—itself into all their offspring. When those mosquitoes mate with wild mosquitoes, all their children will have the edited gene, and over time it will make its way through the entire population.
Imagine if blue-eyed mosquitoes had only blue-eyed children, no matter what color their partners’ eyes were. Eventually, every mosquito in that population would have blue eyes.
This chart shows you how gene drive eventually spreads a gene throughout an entire population:
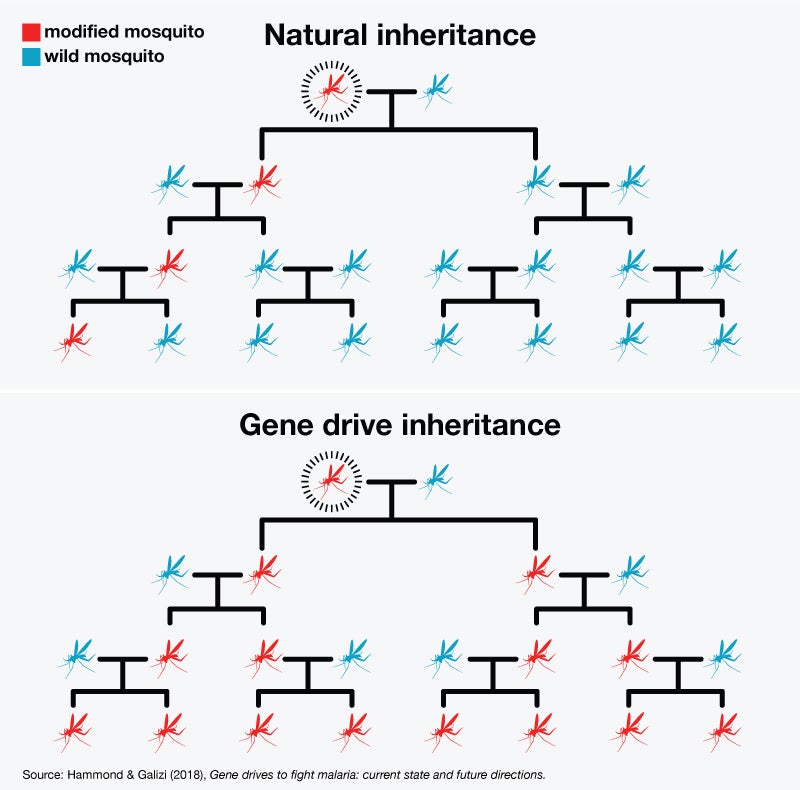
There’s no reason to think gene drive is even feasible in humans, let alone advisable. There are also serious questions surrounding the use of this technology on insects, which I will get to in a moment. But first I want to give you two examples of how it works.
One is the colorfully named X-shredder. As you might remember from biology class, the sex of a mosquito is determined partly by the sex chromosomes it inherits from its parents. Females got one X chromosome from each parent; males got an X from their mother and a Y from their father.
In 2014, scientists at Imperial College London and the Fred Hutchinson center here in Seattle were able to edit a protein in male mosquitoes so that it shreds the X chromosomes in their sperm. As a result, the males pass along mostly Y chromosomes, so most of their offspring will be males. Thanks to gene drive, those offspring will also have the edited protein, so most of their children will be males.
Within a few generations, the male/female ratio gets out of whack, and eventually the species dies off in that area.
Another example involves the doublesex gene, which in mosquitoes works along with the sex chromosome to determine whether an insect turns out male or female. Last year, researchers at Imperial College London found that females with edited doublesex genes develop a mix of male and female organs, including male genitalia and a proboscis that is too flimsy to break human skin. They can’t reproduce, so the population shrinks; and they can’t take a blood meal, so they won’t spread the parasite.
The doublesex edit doesn’t affect males, although thanks to gene drive, they will pass it to their offspring, which is how it keeps spreading through the population.
We know gene-drive technology works in the lab. When the Imperial College researchers put 150 males carrying a copy of the doublesex edit in a small cage with 450 wild-type mosquitoes, the population died off within a few months (about 10 generations). The sex bias edit produced similar results.
The next step is to run tests in larger cages and, eventually, get permission from governments to do them outdoors. We need to understand things like: What’s the impact on the food chain if a certain species of mosquito starts dying off? How many altered insects would we need to introduce? How long do we need the mosquitoes to be gone? Last year, the government of Burkina-Faso agreed to allow the release of sterile, non-gene-drive mosquitoes in the wild so researchers could begin to study some of these questions.
As I mentioned, social and regulatory issues also come into play. For example, because mosquitoes don’t exactly respect national boundaries, neighboring countries will probably need to agree on the rules surrounding the use of gene-editing technology. Policymakers and scientists have been debating these questions in forums like the World Health Organization and the African Union’s development agency, and they are moving toward a consensus.
I think we can have the regulatory approvals in place by 2024 and the first gene-drive mosquitoes ready for use by 2026. Although this technique will never replace the other tools we have for fighting malaria, I’m optimistic that it could become one more important weapon in eradicating the disease.
Captain Kirk vs. malaria
The world’s deadliest shapeshifter
The malaria parasite is good at fooling your immune system. Now scientists are fighting back.
It’s Mosquito Week again on the Gates Notes. In this post I write about how the malaria parasite changes shape to foil your immune system. I’ve also written about ingenious new genetic techniques for fighting mosquitoes and maps that could help us defeat malaria.
I remember an old episode of the original Star Trek where the bad guy is a shapeshifter who turns himself into a second Captain Kirk. There’s a great scene at the end where Spock has to figure out which one is the impostor.
Shapeshifters are not just the stuff of science fiction, though. We have them right here on earth. Some are innocuous, like a caterpillar turning into a butterfly. But there’s another shapeshifter that’s responsible for more than 400,000 deaths every year. I’m talking about the group of microscopic parasites that cause malaria.
Malaria is one of the most fascinating and frustrating diseases our foundation works on, and its ability to change shape is one of the main reasons why. These parasites have figured out ingenious ways to fool your immune system. They have also (mostly) evaded our best efforts to make a malaria vaccine.
To understand how, it helps to know a bit about how your immune system works.
Your system is very good at detecting unusual objects in your body. It looks at the proteins on the surface of an invader and says, “I’ve never seen the funny shape on the outside of this thing. I’m going to attack it.” After the invader is defeated, your body remembers what it looked like and will go after it if it ever shows up again. Vaccines work by taking advantage of this process. When you get a measles shot, it contains a little bit of the virus; it won’t make you sick, but your body learns how to defend itself against future infections.
Unfortunately, malaria is a lot more complex than viruses or bacteria. For one thing, it is caused by parasites. Parasites don’t look as weird to your body as viruses or bacteria do. In fact, they more closely resemble your own cells, so your immune system has a harder time fighting them off.
Another problem is that the malaria parasite goes through three different stages in your body. It looks radically different in each stage, and as the infection goes on, you have all three going on at once.
Stage 1 begins when an infected mosquito bites you and injects a little saliva under your skin. This dose of saliva might contain only 100 parasites (called sporozoites in this stage). They are small and don’t cause any inflammation in your body, so your immune system doesn’t bother to look for them. You’re not feeling any symptoms yet.
Within an hour or two, the sporozoites make their way to your liver for stage 2. Coming out of your liver, they take a new form (called merozoites) and start invading your red blood cells. This invasion causes the symptoms—fever, chills, and so on—that make malaria such a miserable and deadly disease.
Now your body knows it’s sick and your immune system kicks in. But this is where the parasite’s shapeshifting comes into play.
Remember how the measles vaccine helps your immune system learn to identify the virus by looking for certain proteins on its surface? That works because those proteins look the same on each clone of the measles virus in your body. With malaria, each one can present up to 60 different proteins—and thanks to a mechanism that tells the parasite to alter its surface periodically, they shuffle these proteins around in different combinations every few days.
As a result, by the time your immune system has figured out how to attack one shape, the parasite has transformed, and your body’s defenses are useless. Your immune system adjusts, but not before the parasite has shifted again. It’s as if there’s a door on the surface of the parasite, but it keeps changing the locks so your body never has the right key.
Finally, in stage 3, a few of the merozoites develop into male and female cells. These hang out in your bloodstream, waiting for the next mosquito to come bite you. Once they’re in the mosquito’s stomach, they form new sporozoites, which make their way to the bug’s saliva glands and get injected into the next human, where the cycle starts all over again.
So that is the life cycle of malaria. What does all this mean for the effort to control and eventually eradicate this disease?
You might think we could create a vaccine that simply recognizes all the different shapes of the parasite. Unfortunately, that’s not practical. The only vaccine we have ever done that with is for a type of pneumonia. It is very expensive to manufacture and covers only a dozen shapes or so, versus the 60 shapes in one malaria infection and the many hundreds across all malaria parasites worldwide.
The malaria community (including our foundation) has been working for years on a vaccine to protect you in stage 1, before the infection takes hold. This vaccine, called RTS,S, teaches your immune system to hunt for a bit of protein that is always on the surface of the parasite. Unfortunately, the protection provided by RTS,S is not strong enough for long enough to help us make real headway toward eradication. And there are other forms of protection (such as bednets and insecticides) that are more cost-effective for saving lives.
People often ask me if it’s frustrating to fund work that takes so long to come to fruition. My answer is: not at all. Of course, I’m disappointed that we don’t have a long-lasting vaccine yet. But this is hard work. Parasites are such complex organisms that there are no effective vaccines for any of the human diseases that they cause. Besides, the research on RTS,S has given scientists a lot of insight into how malaria works and new clues about how to stop it. In fact, much of what we know about how your body responds (or fails to respond) to this type of parasite came from research on RTS,S.
The malaria community is now building on this knowledge. For example, scientists are working on new approaches that we hope will trigger the immune system to create long-lived, antibody-generating cells. Another promising idea is to create synthetic antibodies rather than trying to get your immune system to make natural ones. These monoclonal antibodies have revolutionized the treatment of cancer and inflammatory disease, and they could do the same for infectious diseases like malaria.
Knowing how complex malaria is helps me appreciate how much progress the world has made in fighting it. Deaths from malaria have dropped 42 percent since 2000, thanks to investments in bednets that prevent it and medicines that cure it. When I see how far we have come and how much we have learned, I am as optimistic as ever that we can beat this clever shapeshifter.

Quality of life
What the plow and lab-grown meat tell us about innovation
I was honored to guest curate MIT Technology Review’s 2019 breakthrough technology issue.
I’m a big fan of the MIT Technology Review’s annual list of ten breakthrough technologies—so when they asked me to choose this year’s list, I jumped at the chance. It’s been a lot of fun working on the issue and picking which innovations to include. I think all ten entries will have a significant impact in the years to come, and I’m excited for you to learn more about them.
Here’s the opening essay I wrote for the issue. You can see the full list of breakthrough technologies here.
I was honored when MIT Technology Review invited me to be the first guest curator of its 10 Breakthrough Technologies. Narrowing down the list was difficult. I wanted to choose things that will not only create headlines in 2019 but captured this moment in technological history—which got me thinking how innovation has evolved over time.
My mind went to—of all things—the plow. The plow is an excellent embodiment of the history of innovation. Humans have been using them since 4000 BCE when Mesopotamian farmers used sharpened sticks to aerate soil. We’ve been slowly tinkering with and improving them ever since, and today’s plows are technological marvels.
But what exactly is the purpose of a plow? It’s a tool that creates more: more seeds planted, more crops harvested, more food to go around. In places where nutrition is hard to come by, it’s no exaggeration to say that a plow gives more years of life to people. The plow—like many technologies, both ancient and modern—is about creating more of something and doing it more efficiently, so that more people can benefit.
Contrast that with lab-grown meat, one of the innovations I picked for this year’s TR10 list. Growing animal protein in a lab isn’t about feeding more people. There’s enough livestock to feed the world already, even as demand for meat goes up. Next-generation protein isn’t about creating more—it’s about making meat better. It lets us provide for a growing and wealthier world without contributing to deforestation or emitting methane. It also allows us to enjoy hamburgers without killing any animals.
Put another way, the plow improves our quantity of life, and lab-grown meat improves our quality of life. For most of human history, we’ve put most of our innovative capacity into the former. And our efforts have paid off: worldwide life expectancy jumped from 34 years in 1913, to 60 in 1973, and has reached 71 today.
Because we’re living longer, our focus is starting to shift toward well-being. This transformation is happening slowly. If you divide scientific breakthroughs into these two categories—things that improve quantity of life versus quality of life—the TR10 list from 2009 looks not so different from this year’s. Like most forms of progress, the change is so gradual that it’s hard to perceive. It’s a matter of decades, not years—and I believe we’re only at the midpoint of the transition.
To be clear, I don’t think humanity will stop trying to extend lifespans anytime soon. We’re still far from a world where everyone everywhere lives to old age in perfect health, and it’s going to take a lot of innovation to get us there. Plus, “quantity of life” and “quality of life” are not mutually exclusive ideas. A malaria vaccine would both save lives and make life better for children who might have otherwise been left with developmental delays from the disease.
We’ve reached a point where we’re tackling both ideas at once, and that’s what makes this moment in history so interesting. If I had to predict what the TR10 will look like a few years from now, I bet technologies that alleviate chronic disease will be a big theme. This won’t just include new drugs (although I would love to see new treatments for diseases like Alzheimer’s on the list). These innovations might look like a mechanical glove that helps a person with arthritis maintain flexibility or an app that connects someone experiencing a major depressive episode with the help they need.
If we could look even further out—let’s say the TR10 list 20 years from now—I would hope to see technologies that center almost entirely on well-being. I think the brilliant minds of the future will focus on more metaphysical questions: How do we make people happier? How do we create meaningful connections? How do we help everyone live a fulfilling life?
I would love to see these questions shape the 2039 list, because it would mean that we’ve successfully fought back disease (and dealt with climate change). I can’t imagine a greater sign of progress than that. For now, though, the innovations driving change are a mix of things that extend life and things that make it better. My picks reflect both. Each one gives me a different reason to be optimistic for the future, and I hope they inspire you, too.
My selections include amazing new tools that will one day save lives, from simple blood tests that diagnose cancer to toilets that destroy deadly pathogens. I’m equally excited by how other technologies on the list will improve our lives. Wearable health monitors like the wrist-based EKG will warn heart patients of impending problems, while others let diabetics not only track glucose levels but manage their disease. Advanced nuclear reactors could provide carbon-free, safe, and secure energy to the world.
One of my choices even offers us a peek at a future where society’s primary goal is personal fulfillment. Among many other applications, AI-driven personal agents might one day make your email inbox more manageable—something that sounds trivial until you consider what possibilities open up when you have more free time.
The thirty minutes you used to spend reading emails could be spent doing other things. I know some people would use that time to get more work done—but I hope most would use it for more fulfilling pursuits, like connecting with a friend over coffee, helping your child with her homework, or even volunteering in your community.
That, I think, is a future worth working toward.
Bug zappers
Mosquito wars
The progress we’ve made to reduce malaria deaths is one of the most remarkable global health stories in recent years.
We’ve come a long way since the days of blaming the stars.
Malaria has terrorized humankind for thousands of years, but for most of that time, we had no idea what caused it. The ancient Greeks thought Sirius the dog star might be responsible. A Chinese medical text from 270 BCE speculated that three demons spread the disease. As recently as the mid-1800s, doctors believed malaria was caused by the stinky fumes that wafted into cities from nearby swamps (the word malaria means “bad air” in Italian).
Today, we know exactly who our enemy is: the mosquito. Doctors no longer subject malaria sufferers to unpleasant (and pointless) treatments like blood-letting and chewing tree bark. Most importantly, we’ve made massive progress in fighting a disease that as recently as 2000 killed nearly 870,000 people in a single year.
This progress is one of the most remarkable global health stories in recent years. Malaria claimed more than 429,000 lives last year, mostly in Africa and Southeast Asia. While that figure is still way too high, it represents a 50 percent reduction overall from the disease’s peak in the early 2000s. I don’t throw the word “miracle” around lightly, but that number is nothing short of miraculous.
How did we get here? I give credit to an unprecedented scale-up in global commitment and cooperation—malaria funding rose by 1,000 percent from 2000 to 2015. This money fueled a number of amazing scientific breakthroughs, enabled us to deliver them at scale, and focused more brainpower on improving both control and treatment efforts.
This October marks a decade since Melinda and I first called for eradicating malaria. It was a controversial move at the time, but the progress made since then has convinced many that this is a realistic goal (although some are still skeptical).
If I had known back in 2007 how much progress we would make in ten years, I would’ve been thrilled by how much we’ve cut the death rate. I’d also be impressed by how many insecticidal bed nets are now in use, how new treatments are helping people with the most severe cases of malaria, and how rapid diagnostic tests have made it easier to find and treat people. But it wouldn’t all be good news.
In 2007, I thought we’d have a long-lasting malaria vaccine by now. The WHO plans to begin pilot demonstration projects of a first-generation malaria vaccine in sub-Saharan Africa next year, although without a booster dose it only protects a child for less than six months. I’m hopeful that researchers will develop a next generation vaccine that offers much longer protection within the next 10 years, but a decade ago I was overly optimistic about where we’d be today.
There are still plenty of reasons to believe we can eradicate malaria, though. In the war against malaria and the mosquitoes who carry it, we’re already fighting on every front. Consider the wide array of innovations in development right now:
- New Insecticide-Treated Bed Nets: The older generation of bed nets needed to be soaked in a special insecticide solution every six months. The long-lasting nets we will distribute in Mozambique through our giveaway protect people from mosquitoes for three years and can even be washed when they get dirty. Unfortunately, some mosquitoes are now developing resistance to the pyrethroid insecticides used in these nets—so researchers are working on next generation bed nets that use combinations of insecticides and appear effective against all mosquitoes, including insecticide-resistant ones.
- Tackling Drug Resistance: In Southeast Asia, we’ve seen some types of the malaria parasite develop resistance to the drug combinations we use to cure and prevent the disease. If this drug resistance spread to Africa, it’d be a disaster. Fortunately, we have partners on the front lines finding ways to fight back. Watch this video about the amazing work one team of researchers is doing to combat drug resistance in Thailand:
- Disease Mapping: We know more today about where malaria is occurring than we have at any other point in history. Public health experts are combining anonymous data from mobile phone records with data on malaria incidence to track the movements of infected mosquitoes. That's super valuable, because it helps countries use their limited resources in places that have the highest disease burden.
- Eave Tubes: Many houses in hot climates have a gap between the roof and the walls to keep the inside cool. By sealing these gaps and inserting special tubes just below the roofline, air still flows into the house but keeps mosquitoes out with a mesh filter. Since the tubes are too high for children to reach them, the mesh can be coated with a high enough dose of insecticide to kill even insecticide-resistant mosquitoes.
- Genome Editing: Our foundation has invested a lot of money into editing the genetic code of mosquitoes. We’re still in the very early stages of development, but scientists are exploring whether this technique could one day render a small number of key mosquito species infertile or unable to carry the malaria parasite.
- Attractive Targeted Sugar Baits: Only female mosquitoes bite people, and they only do it when they’re breeding. The rest of the time, they rely on sugar for energy. These calendar-sized traps hang on the outside of homes and contain a minimum risk toxin that kills more than 95 percent of the mosquitoes that flock to their sweet scent without affecting pollinators. Trials are underway in Mali.
I think we will see an end to malaria in my lifetime. It’s a preventable and curable disease, and the public health community has already demonstrated that it’s possible to shrink the map and save lives. These new tools in the development pipeline will play a huge role in reaching our goal. While we’re still decades away from wiping malaria off the map for good, one thing is clear: the mosquito has met its match.
Loaf actually
The bread lab in my backyard
These Washington state researchers are doing cool things with baked goods.
I’ve been to lots of labs, but until recently I had never seen one that was centered on a full working kitchen. Last month I got my chance when I visited the Bread Lab, located a couple hours north of my hometown Seattle. It brings together local farmers, expert plant breeders, and world-class bakers with the goal of producing wheat for baked goods that are both delicious and good for you.
I could smell the baking bread the minute I walked in the door. Canisters of flour from different types of wheat lined the walls. Bakers were pulling warm rolls out of large commercial ovens. In the corner there was a farinograph, a machine that measures the strength of dough.
It was all very impressive. But deep down, I was a little skeptical: How would the breads actually taste? The Bread Lab emphasizes using whole grains, and not just wheat—lab director Steve Jones loves buckwheat because it’s unusually high in lysine and other nutrients. Although eating whole-grain bread might make me feel virtuous, in my experience it just never seems to taste as good as white bread.
But I got to sample lots of their baked goods, and I’m happy to report that everything I ate was delicious—even the croissants, which are especially hard to get right when you’re using whole grains.
The lab is part of Washington State University, and although most of their work is with rich-world companies including Clif Bar, La Brea Bakery, and Chipotle, they are also applying their expertise to the problem of malnutrition in poorer countries. For example, I met a Pakistani Ph.D. student, Farah Ahmad, who’s looking at ways to make chapatis, cookies, and other foods from her home country using approaches developed by the Bread Lab.
Here’s a video from my visit:
Safety first
Foreign aid keeps Americans safe
The strategic case for fighting disease and poverty abroad.
You may have seen in the news that elected officials in Washington, D.C., are working on next year’s federal budget. One of the ideas that has been floated is to make deep cuts in foreign aid—the investments that America makes to help other countries fight poverty and disease.
That would be a big mistake.
For one thing, these programs amount to less than 1 percent of the federal budget. For anyone worried about the budget deficit, cutting 1 percent will not make a dent.
More importantly, these programs give American taxpayers a phenomenal return on investment, one of the best anywhere in government. They do this in three ways:
- Making Americans safer and the world more stable
- Creating jobs at home and promote trading partners that will buy American goods
- Saving lives and building up health systems so other countries can take better care of their people
Together these three points make what you might call the strategic case for aid—the argument that aid helps the countries that give it as well as those that receive it.
To be honest, the strategic case is not what prompted Melinda and me to get involved in this work more than 17 years ago. We were moved by what you could call the moral case: the idea that it is terribly unjust that people in poor countries—especially children—die of diseases that can be prevented. That is still the main thing that drives us today. But over the years we have come to see the compelling strategic case too. And we have found that people often support aid who aren’t convinced by the moral argument but are by the strategic one.
In this post I want to focus on point #1 above. I’ll come back to #2 and #3 in subsequent posts.
Let’s look at how promoting health and development keeps Americans safe.
Preparing for the next epidemicYou may remember the Ebola epidemic of 2014–16. It killed more than 11,000 people in three West African countries. Each of those deaths was a tragedy, but the epidemic could have been far worse. If it had spread to neighboring Nigeria, home to more than 180 million people and a busy international travel hub with daily flights to the world’s capitals, it would have been very hard to contain. It could have easily jumped the Atlantic and infected Americans, and spread throughout Europe or Asia.
Why didn’t that happen? One key reason is that a number of health workers were stationed in Nigeria as part of the global campaign to stamp out polio. As the Ebola epidemic took hold, they were quickly reassigned from polio to Ebola. They already had a system in place for identifying possible cases, tracking them, and reporting the data to people organizing the response. They helped contain the disease and keep it from spreading farther than it did.
The polio eradication program helped stop Ebola and saved countless people, including Americans. Its biggest public funder? The United States government.
In addition, Ebola may have been only a preview of what is to come. The next epidemic—say, a virulent flu as bad as the Spanish Flu of 1918—could be far worse. Epidemiologists estimate it could kill 30 million people, more than three times the population of New York City.
Funding from the U.S. government helps keep that from happening. It helps other countries strengthen their health systems so they can identify dangerous diseases and contain them before they get out of control.
It is no accident that the Ebola epidemic hit hardest in three countries—Guinea, Sierra Leone, and Liberia—with especially weak health systems. Helping them improve makes it more likely that we can prevent a worldwide epidemic that destabilizes entire regions of the world and kills tens of millions of people.
Stabilizing vulnerable countriesPreventing pandemics is one specific way that U.S. funding makes Americans safer. There is also a broader point here: by fighting poverty and disease, we make the world a more stable place.
For example, both evidence and common sense tell us that when people don’t have reliable food supplies, they will pick up and move someplace else—becoming migrants or refugees—and that leads to more instability. Look at the countries with the least reliable food supplies in the world: Sudan, South Sudan, Eritrea, Burundi. Each of them is either at war or recently emerged from conflict.
Syria is another tragic example. In 2007, the country suffered the worst drought in its history. More than 1 million people fled rural areas for the cities, where they hoped to find food. This migration stoked political tensions and created the foundation for the horrific civil war that continues today. Of course that war has many causes, and not every drought-stricken country will become another Syria. But it is clear that the world is not a safer place when more people are going hungry—and that when we strengthen food and farming systems, we tackle some of the root causes of migration and instability.
Improving health is another way to make countries more secure. One of my favorite all-time examples is PEPFAR, the program America launched in 2003 to stop the spread of AIDS. Today it provides life-saving medicine for more than 11 million people living with HIV in some of the world’s poorest countries. Those 11 million people are teachers, health-care workers, and police officers—people who build strong, self-sufficient societies. So it should not be surprising that in countries where PEPFAR has a presence, political instability fell by 40 percent between 2004 and 2013. In non-PEPFAR countries, it dropped only 3 percent. And the PEPFAR countries grew three times faster.
Shoring up national securityAmerican military leaders understand that fighting poverty and disease is part of a smart national-security strategy. It was true after World War II, when the United States invented modern development assistance to combat instability in Europe and prevent a third World War, and it’s true today. The more stable poor countries are, the lower the odds that America will need to intervene in them.
More than 120 retired generals and admirals recently wrote a letter to Congress arguing that U.S. aid programs “are critical to preventing conflict and reducing the need to put our men and women in uniform in harm’s way.” While he was the head of U.S. Central Command, overseeing American operations in Syria, Pakistan, Afghanistan, and elsewhere, Secretary of Defense James Mattis said: “If you don’t fully fund the State Department”—which houses many aid programs—“then I need to buy more ammunition.”
Aid is an important part of our broad diplomatic and security relationships. Out of 135 countries that receive some health or development aid from the United States, we have bilateral defense agreements with 131 of them.
These are some of the arguments I have been making in Washington on behalf of American aid. In future posts I will explain how aid not only keeps Americans safe, but also creates jobs in the United States and helps other countries become more self-sufficient. All reasons why I believe this money is well-spent and ought to be maintained.
Progress 360
Strong coffee, stronger women
How Ethiopia’s 38,000 health workers have helped save children’s lives and improved the health of their nation.
Of all the charts I’ve seen, this one is the most beautiful:
Why?
First, that descending red line captures one of the most amazing stories of human progress: It shows how the number of deaths of children under 5 per year has been cut in half since 1990.
Second, hidden along that line are millions of stories of the incredible work being done by health officials, governments, donors, and parents around the world to help save all those lives.
Here’s one of those stories. It begins with some remarkable women I met in Ethiopia. They are part of an innovative program that’s improved the health of millions of children in their country.
You can meet them yourself (and join us for a cup of coffee) in this video.
Back in 1990, Ethiopia had one of the highest rates of child mortality in the world. One in five children were dying before their 5th birthdays. With few doctors and most of its population living in rural areas, Ethiopia struggled to provide basic health services to the country. Most women in rural areas gave birth at home.
Then in 2000, the Ethiopian government made a commitment to improve its healthcare system. Ethiopia signed on to the United Nations’ Millennium Development Goals, which focused the world’s attention on fighting disease and ending poverty by using data to measure progress on health and development progress. As part of the goals, Ethiopia pledged to reduce under-five death rates by at least two-thirds by 2015.
To achieve it, Ethiopia needed to find an effective way to deliver healthcare to the remotest corners of the country. But training thousands of new doctors to staff them would take years and would be extremely costly. Instead, Ethiopia created a community health worker program. They selected thousands of people, primarily young women with at least a 10th grade education, and trained them in a set of basic health skills—including how to deliver babies, administer immunizations, and provide family planning support—that are proven to save lives. Most of the health workers were recruited from the communities they served, helping to quickly build public trust in the new effort.
In 2012, I made my first trip to Ethiopia to see the program in action for myself. I was amazed. I visited a remote health post south of Addis Ababa run by two health workers, Yetagesu Alemu and Betula Shemesie. They spent many of their days walking from door to door in their village caring for pregnant women and families with newborns. Their health post didn’t have electricity or any high tech medical equipment. Still, their efforts had made an impact on the health of the families in their community.
What was exciting to see was how this success was being repeated in villages across the country. Despite being one of the poorest countries in the world, Ethiopia managed to dramatically reduce the rate of child mortality. By 2012, Ethiopia had met the target for the Millennium Development Goal on child survival, with under-five death rates dropping by 66 percent since 1990.
One of the key reasons the program has been so effective is that the health workers are dedicated to measuring their progress. Covering nearly every square inch of the walls of the health post I visited were large charts, where the health workers would track births, immunizations, malaria cases, and other indicators. Each indicator helped them understand how well they were performing and which areas demanded more attention.
Today, Ethiopia has more than 15,000 health posts delivering primary health care to the farthest reaches of this rural country of 100 million people. The health posts are staffed by 38,000 health workers like Betula and Yetagesu.
Last summer, I had a chance to visit Ethiopia again. I caught up with Yetagesu and Betula over coffee and to learn more about how the health worker program was going. They told me how women who once delivered their babies at home were now choosing to give birth at health centers. Their communities also had access to ambulances that would pick up any woman who is ready to give birth. Yetagesu and Betula were also proud to report that they had received additional medical training to sharpen their health skills.
To be sure, there’s a lot more work to be done to improve health services in rural Ethiopia. Their communities need more ambulances. Just one vehicle serves 17 health posts, Yetagesu said. They also hoped the country would hire more health workers so they would have the time to provide families with more comprehensive services. And as Melinda and I discussed in this year’s annual letter, one of the biggest challenge in child survival is newborn deaths. In Ethiopia, about 44 percent of all childhood deaths occur within the first 28 days of life. We need to find innovative ways to solve this challenge.
Still, I’m confident that Ethiopia will continue to make progress in child survival. And what’s most exciting is that Ethiopia’s health program has been so successful that it now serves as a model for other countries to follow. Sharing lifesaving innovations like Ethiopia’s ensures that in the years ahead the most beautiful chart in the world will become even more beautiful.
A real bargain
How foreign aid helps Americans
It makes the country more secure, prevents epidemics, and saves lives.
Foreign aid is often in the hot seat, but today the heat is cranked up especially high. The United States government, one of the world’s most influential donors, is considering dramatic cuts to health and development programs around the world. I understand why some Americans watch their tax dollars going overseas and wonder why we’re not spending them at home. Here’s my answer: These projects keep Americans safe. And by promoting health, security, and economic opportunity, they stabilize vulnerable parts of the world.
This is a lesson I’ve learned myself. When I first got involved in health and development more than 15 years ago, the main motivation was to save and improve people’s lives around the world. That’s still true today, but over the years I have come to see the tangible ways in which American aid benefits Americans too.
For one thing, it helps prevent epidemics. The most recent Ebola outbreak in West Africa killed more than 11,000 people, but the death toll would have been much worse if the disease had spread widely in neighboring Nigeria, an international travel hub that’s home to 180 million people. What contained it? Among other things, a group of health workers who were stationed there for an anti-polio campaign. They were quickly reassigned to the Ebola fight, and their efforts helped stop the disease—and keep it from crossing the Atlantic to the United States.
The biggest public funder of anti-polio work has been the U.S. government, and for good reason. It is protecting Americans and helping us get ready for the next epidemic, which could be orders of magnitude deadlier than Ebola. To stop emerging diseases, we need the infrastructure built by consistent funding of well-run health programs.
Another example is America’s global HIV/AIDS effort, known as PEPFAR, which began under President George W. Bush and works with some of the world’s poorest countries. PEPFAR is an undeniable success. There are 11 million people with HIV who are alive today because of the medicines that it provides. Many more never got the virus in the first place because of prevention efforts supported by PEPFAR.
This is not simply a humanitarian accomplishment. For those countries it means more teachers, entrepreneurs, police officers, and health-care workers contributing to strong, stable societies. According to one bipartisan study, political instability and violent activity in African countries with PEPFAR programs dropped 40 percent between 2004 and 2015. Where there was no PEPFAR program, the decline was just 3 percent.
Better health puts nations on the path to self-sufficiency. How? When health improves, people decide to have fewer children, because they’re confident that the children they do have will survive into adulthood. As family size drops, it gets easier for countries to feed, educate, and provide opportunity for their people—and that is one of the best ways to stabilize any vulnerable region.
A more stable world is good for everyone. But there are other ways that aid benefits Americans in particular. It strengthens markets for U.S. goods: of our top 15 trade partners, 11 are former aid recipients. It is also visible proof of America’s global leadership. Popular support for the U.S. is high in Africa, where aid has such a dramatic impact. When you help a mother save her child’s life, she never forgets. Withdrawing now would not only cost lives, it would create a leadership vacuum that others would happily fill.
Syria is a tragic example of what can happen when the key ingredients of stability don’t come together. Beginning in 2007, the country experienced the worst drought in its history, driving more than a million people from rural areas into the cities, stoking political tension, and laying the foundation for the horrific civil war that continues today. Of course there were many causes of that war, and not every country that has a severe drought collapses as badly as Syria did. But the world will not be a safer place if the U.S. stops helping other countries meet their people’s needs.
None of this is lost on our military leaders. More than 120 retired generals and admirals recently wrote a letter to Congress arguing that U.S. programs “are critical to preventing conflict and reducing the need to put our men and women in uniform in harm’s way.” Secretary of Defense James Mattis famously said, back when he was commander of U.S. forces in Afghanistan, Pakistan, and other hotspots: “If you don’t fully fund the State Department”—which runs many of America’s key programs—“then I need to buy more ammunition.”
Protecting Americans, preventing epidemics, strengthening markets, saving lives: aid delivers phenomenal benefits, and for a bargain. It represents less than 1 percent of the federal budget, not even a penny out of every dollar. It is some of the best return on investment anywhere in government. This money is well spent, it has an enormous impact, and it ought to be maintained.
This post originally appeared on time.com.
Future investment
Preparing for the next epidemic: a first step
A new organization will help accelerate the development of vaccines we’ll need to contain future outbreaks.
At a time when world leaders are understandably focused on terrorism and other security threats, another enemy is being largely overlooked—the next epidemic.
We don’t know when the next pathogen will emerge, what it will be, how it will spread, or who will be affected, but we do know that the world is not prepared to deal with it. That was the tough lesson that Ebola (and the Zika outbreak since) taught us. Ebola claimed thousands of lives, caused billions of dollars in economic losses, and showed how vulnerable our society is to epidemics of infectious diseases. As I’ve written about before, the world lacks an effective system to detect, respond to, or prevent the next outbreak.
That’s why I’m excited this week, at the World Economic Forum in Davos, to participate in the launch of a new organization that will help the world get ready for future epidemics. Backed by the governments of Norway, India, Japan, and Germany, along with the Wellcome Trust and our foundation, the Coalition for Epidemic Preparedness Innovations (CEPI) will invest in innovations to accelerate the development of vaccines we’ll need to contain outbreaks.
CEPI’s focus on vaccine development is a critical part of getting prepared for whatever pathogens threaten us next. We know from the world’s defeat of smallpox and its successful fights against polio, measles, and other diseases that vaccines are incredibly effective tools for preventing disease and saving lives. Now, this alliance of governments, philanthropies, vaccine manufacturers, academia, NGOs, and other partners needs to work together to develop new vaccines to make the world safe from future epidemics.
Traditional approaches to making new vaccines are too slow to respond to a sudden disease outbreak. Currently, the development of a new vaccine, including testing and deployment, is a process that can typically take more than 10 years. Fast-moving epidemics don’t allow us to be that patient. In 1918, an extremely infectious and deadly strain of the flu infected about one-fifth of the world’s population and killed at least 30 million people in less than two years. Ebola and Zika were also both frightening viruses, but the way they are transmitted—through bodily fluids and mosquitoes—helped limit their spread globally. A highly-contagious airborne disease would pose a far greater threat. It would thrive in densely populated urban areas and could easily cross national borders and oceans by air travel.
My great hope for CEPI is that it will help enable the world to produce safe, effective vaccines as quickly as a new threat like this emerges. With $460 million in initial funding, CEPI will work to bring together the most advanced vaccine technologies and resources from the private and public sector that can help lead to new breakthroughs in vaccine development. CEPI’s vaccine development strategy includes two areas of focus: “just in time” vaccines for those currently unknown pathogens that will emerge, and “just in case” vaccines for pathogens that we know are at high risk of causing another outbreak, like Ebola and Middle East respiratory syndrome or MERS.
One promising area of vaccine development research is using advances in genomics to map the DNA and RNA of pathogens and make vaccines. The vaccines can be decoded by human cells to make their own vaccines and antibodies inside the body. If successful, this technology could dramatically reduce the development timeline from years to possibly months or weeks.
What’s exciting about these new technologies is that they wouldn’t just protect us from future epidemics. They also would help us to develop vaccines for existing health threats to hundreds of millions of people around the world, including HIV, malaria, and TB.
At the same time, CEPI will work to minimize regulatory hurdles that further delay the deployment of vaccines. CEPI will fund studies to evaluate these newly-developed vaccines and build vaccine stockpiles before epidemics begin, so countries can move swiftly to full vaccine efficacy trials and emergency deployment during an outbreak.
As pleased as I am to see CEPI’s work get underway, it’s important for everyone to understand that this effort is just the first step toward getting us prepared for the next epidemic. It’s an important step, but CEPI alone won’t be enough to protect us. We have a lot more work to do.
We need a global warning and response system for outbreaks. It begins with strengthening local health systems in poor countries, which have gotten hit the hardest during recent epidemics. The thousands of remote health clinics around the world will be the backbone of our global effort to defeat future epidemics. They must have trained health workers who can provide primary health care, deliver vaccines, and monitor the health of their communities.
We must have a better disease surveillance system, which includes a global database so countries can share information on cases. We also need trained medical personnel ready to mount a rapid response to an outbreak.
Last, we need to continue to invest in health research to develop not just vaccines, but also new drugs and diagnostic tests that will strengthen our ability to respond quickly and effectively to the next epidemic.
Still, we’ll never know exactly when a new disease outbreak will emerge. It could arrive tomorrow, next month, next decade, or next century. But that uncertainty shouldn’t be an excuse for inaction. I hope that today’s announcement marks the first of many steps the world will take to get prepared for the next epidemic. All of our futures depend on it.
360⁰ of Connection
South Africa: Virtually There
Travel with me to South Africa to see how the country is hoping to win the fight against AIDS.
If you could shuffle all of the homes in the world like a deck of cards so that people in wealthy countries lived side by side with people from poor countries, it would transform the world’s fight against poverty, hunger, and disease. It would be impossible for people to look away, impossible for them not to help.
I was naïve about the deep poverty in the world until I took my first trip to Africa with Melinda in 1993. Seeing the disparities with our own eyes made all the difference and inspired us to start our foundation.
Since then, I’ve continued to travel regularly to Africa, India, and other parts of the developing world. I always return from my trips humbled and inspired. My one disappointment is that I wish everyone could have seen what I did. I have no doubt it would help more people become aware of the challenges the world’s poorest people face. It would also leave them as optimistic as I am about the incredible progress the world is making in health and development.
During my trip to South Africa in July, I tried something new that I hope will allow people to experience what I have. I had highlights of my visit recorded in virtual reality. It’s still an emerging technology but what excites me about it is that it allows viewers to immerse themselves in another world. You can look up and down. Turn right or left. Listen to sounds all around you. I used to think there was no substitute to being there and seeing things for yourself. But virtual reality is a close second. It fulfills my dream of allowing people to see what I’m seeing and, perhaps, feel what I’m feeling, too.
In this video, you will hear the stories of young women living with HIV. Sit beside me as I drive from the leafy suburbs of Johannesburg to the dusty township of Soweto. Feel what it’s like to be in the center of a stomping gumboot dancing troupe. And be inspired by the power of South Africa’s youth, who will drive the next generation of innovations to create a future free of AIDS.
If you want to know more about my trip to South Africa, you can read about my visit here and here. I also encourage you to learn more about The Global Fund, which has helped provide lifesaving treatment to millions of people living with HIV.
Thanks for watching and look out for more virtual reality videos in the months ahead.
Status Check
We Haven’t Turned the Corner on AIDS
Why we need to invest more in the fight.
Next week I’ll be traveling to Durban, South Africa, to attend the International AIDS Conference. It’s an important opportunity for members of the AIDS community to discuss our ongoing efforts to fight the disease. I’ll be there to listen and learn. But I’ll also be delivering my own message.
The good news is that the fight against AIDS has seen many successes. The infection rate declined for several years and millions of people have been put on treatment, allowing them to live full, productive lives.
But we have not turned the corner. The infection rate has essentially stopped declining. That’s a particular problem in sub-Saharan Africa, which has a growing population of young people, who are most susceptible to the disease. If the infection rate stays the same while the at-risk population rises, then the number of people in sub-Saharan Africa who contract HIV each year could start going up instead of down.
One reason the infection rate has stagnated is that AIDS funding has stagnated. Another reason is that the current prevention tools have not had as much impact as any of us had hoped. Voluntary medical male circumcision is a very effective prevention approach, but the programs offering the procedure have not been scaled up sufficiently to reach all those who would benefit. The newest tool, using AIDS treatment as a way to prevent HIV infection among healthy people, has not been rolled out fast enough, and asking people to take a pill every day for prevention presents its own challenges.
There is the idea of “treatment as prevention”: Treating people who have HIV not only saves their life, it also makes them much less likely to pass the virus along to others. This is a promising approach and certainly we should treat as many people as possible so we can save their lives. But it is not yet clear to me that it is financially feasible to treat enough people to get a large prevention effect. I hope to learn more about this question at the conference next week.
For all these reasons, we need to invest more in both delivering the best prevention tools we have and developing new ones that are even more effective. For example, researchers are working on prevention and treatment tools that last for several months after a single dose, which would make it easier for people to stick to the regimes. I am also optimistic that within a decade we will have an AIDS vaccine that provides an acceptable level of protection.
In this video, I explain what it will take to make the most of these opportunities and ensure that AIDS cases keep going down:
17 Million Saved
Let’s preserve this lifesaver
Why we need to keep supporting the Global Fund.
Let me cut to the chase. There’s a program that has helped save the lives of 17 million people in poor countries since 2002. It’s called the Global Fund to Fight AIDS, TB, and Malaria. It’s poised to do even more good in the years ahead, but to continue its work, it needs donors to make new funding pledges.
I just got back from Europe, which is starting to think through many tough decisions surrounding Brexit. Despite that challenge, the governments of France and Italy became the latest to make commitments to the Global Fund, building on recent pledges from Japan, Canada, the United States, and the European Commission. When I was in London, a senior member of the British government confirmed to Parliament that they remain committed to the Global Fund’s success. Although I’m confident the Global Fund will raise the money it needs—donors have consistently recognized that it’s an effective and low-cost way to save lives—we are not there yet.
Since the Global Fund started, Melinda and I have committed $1.6 billion to it. Here are four reasons why we are such big believers:
- Saving lives. In countries where the Global Fund operates, deaths from HIV, TB, and malaria have dropped by a third since 2002. Certainly the Fund doesn’t deserve sole credit for that phenomenal progress, but it has played an irreplaceable role. And its work is far from finished: Three million people still die every year from these diseases.
- Getting rid of diseases so we never have to fight them again. In my lifetime I expect to see the end of malaria, which kills nearly half a million children every year. When you eradicate a disease, you not only save lives, you free up billions of dollars and many hours of effort. One reason I’m so optimistic about ending malaria is the work of the Global Fund, which has slowed the spread of the disease and saved lives by distributing hundreds of millions of bed nets.
- Helping poor countries become more self-sufficient. If you ever hear people say “poor countries just keep getting foreign aid forever,” tell them about the Global Fund. It helps the countries it works with improve their health systems so they can take better care of their people. They also devote an increasing share of their own budgets to health (they have promised to spend 50 percent more between 2015 and 2017 than they did in the previous three years). That translates into less spending by rich governments.
- Using aid efficiently. The Fund has a done a great job keeping costs low and streamlining its work. Its operating costs are just over 2 percent of all the grants it gives out. That means the vast majority of the money that flows through the Global Fund is reaching the people who need it most.
The Global Fund raises money in three-year batches; the current batch will cover the years 2017-19. They’re asking for $13 billion, which will go toward delivering lifesaving drugs and bed nets as well as developing new tools like better diagnostics and next-generation prevention techniques. To put that number in context, it’s about 3 percent of the total foreign aid that rich countries give over three years. And consider the payoff: By one estimate, the $13 billion raised by the Global Fund will generate about $300 billion in economic benefits.
It is never easy to raise large sums of money like this, and it certainly isn’t easy now, with the refugee crisis in Europe compounding an already difficult global economy. Although I don’t think anyone would argue that fighting disease will directly end wars or stop the flow of refugees, improving health certainly makes countries more stable and more prosperous—and less likely to spread disease and instability to their neighbors.
If you want to save and improve lives, health is one of the most effective investments you can make. And if you want to improve health, the Global Fund is one of the most effective investments you can make. It is one of the kindest things people have ever done for one another, and I am inspired by the countries and leaders who are stepping up to support it.
Innovation Nation
America’s secret weapon
By investing in R&D, the U.S. creates jobs at home and helps people around the world.
This presidential election has the country captivated. As many commentators have pointed out, the primaries are more focused on personalities than policy. While the parties focus on who is going to represent them in the fall, I want to make the case for something that I hope every candidate will agree on in November: America’s unparalleled capacity for innovation. When the United States invests in innovation, it creates companies and jobs at home, makes Americans healthier and safer, and saves lives and fights poverty in the world’s poorest countries. It offers the next president a tremendous opportunity to help people in America and around the world.
Of course, America’s capacity for innovation is nothing new. We have been inventing for more than two centuries: think of Benjamin Franklin, Margaret Knight, Thomas Edison. By the end of World War II, the United States led the world in automobiles, aerospace, electronics, medicine, and other areas. Nor is the formula for success complicated: Government funding for our world-class research institutions produces the new technologies that American entrepreneurs take to market.
What is new is that more countries than ever are competing for global leadership, and they know the value of innovation. Since 2000, South Korea’s R&D spending (measured as a percentage of GDP) has gone up 90 percent. China’s has doubled. The United States’ has essentially flatlined. It’s great that the rest of the world is committing more, but if the U.S. is going to maintain its leading role, it needs to up its game.
I have seen first-hand the impact that this type of research can have. I was lucky enough to be a student when computers came along in the 1960s. At first they were very expensive, so it was hard to get access to them. But the microchip revolution, made possible by U.S. government research, completely changed that. Among other things it enabled Microsoft, the company I co-founded, to write software that made computers an invaluable tool for productivity. Later, the Internet—another product of federal research—changed the game again. It is no accident that today most of the top tech companies are still based in the United States, and their advances will have a massive impact in every area of human activity.
My favorite example is health. America’s investment in this area creates high-paying jobs at universities, biotech companies, and government labs. It leads to new treatments for disease, such as cancer therapies. It helps contain deadly epidemics like Ebola and Zika. And it saves lives in poor countries. Since 1990, the fraction of children who die before age 5 has fallen by more than half. I think that’s the greatest statistic of all time, and the United States deserves a lot of credit for making it happen.
The next few years could bring even more progress. With a little luck we could eradicate polio, a goal that is within reach because of vaccines developed by U.S. scientists. (Polio would be the second disease ever eradicated, after smallpox in 1979—in which the U.S. also played an irreplaceable role.) There is also exciting progress on malaria: The number of deaths dropped more than 40 percent from 2000 to 2012, thanks in part to America’s support for breakthrough tools like drugs and bed nets. But to make the most of these opportunities, we need to invest more in basic health research and specific areas like vaccines.
Energy is another great example. American-funded research defines the state of the art in energy production. Early advances in wind and solar technology were developed with federal money. And this research offers a strong return on investment. Between 1978 and 2000, the Department of Energy spent $17.5 billion (in today’s dollars) on research on efficiency and fossil fuels, yielding $41 billion in economic benefits. Yet until this year, the DOE’s research budget hadn’t seen a real increase since the Reagan administration.
If we step up these investments, we can create new jobs in the energy sector and develop the technologies that will power the world—while also fighting climate change, promoting energy independence, and providing affordable energy for the 1.3 billion poor people who don’t have it today. Some of the more promising areas include making fuel from solar energy, much the way plants do; making nuclear energy safer and more affordable; capturing and storing carbon; and creating new ways to store energy that let us make the most of renewables.
There’s a lot of momentum right now on clean energy research. Last year the leaders of 20 countries, including the United States, committed to double federal investments in this area. Complementing that crucial effort, I helped launch the Breakthrough Energy Coalition, a group of private investors who will back promising clean-energy companies. The next president will have a chance to accelerate this momentum.
Investing in R&D isn’t about the government picking winners and losers. The markets will do that. It’s about doing what we know works: making limited and targeted investments to lay a foundation for America’s entrepreneurs. This approach has been fundamental to U.S. leadership for decades, and it will become only more important in the years ahead.
By the end of this summer, the political parties will have chosen their leaders and will start looking ahead to the November election. The nominees will lay out their vision for America and their agenda for achieving it. These visions will probably have more differences than similarities. But I hope we can all agree that, no matter how you see America’s future, there will always be an essential role for innovation.
This article was originally published by Reuters News Agency.
Lessons From Ebola
We’re not ready for the next epidemic
We’re not ready for it. But we can get there.
I am in Vancouver this week attending the TED conference. I just gave a brief talk on a subject that I’ve been learning a lot about lately—epidemics.
The Ebola outbreak in West Africa is a tragedy—as I write this, more than 10,000 people have died. I’ve been getting regular updates on the case counts through the same system we use to track new cases of polio. Also, last month I was lucky enough to have an in-depth discussion with Tom Frieden and his team at the Centers for Disease Control and Prevention in Atlanta.
What I’ve learned is very sobering. As awful as this epidemic has been, the next one could be much worse. The world is simply not prepared to deal with a disease—an especially virulent flu, for example—that infects large numbers of people very quickly. Of all the things that could kill 10 million people or more, by far the most likely is an epidemic.
But I believe we can prevent such a catastrophe by building a global warning and response system for epidemics. It would apply the kind of planning that goes into national defense—systems for recruiting, training, and equipping health workers; investments in new tools; etc.—to the effort to prevent and contain outbreaks.
This is what my TED talk was about. You can watch it here:
The more I learn about what it takes to respond to an epidemic, the more impressed I am by the health workers who have been risking their lives to care for the sick. Just putting on a protective suit is huge undertaking. Once it’s on, it’s hard to hear what anyone else is saying, and you start to sweat after just a few minutes.
Here’s a short photo essay about one attempt to solve this problem that I was involved with.
At TED we also put together an exhibit where attendees could try on a suit for themselves:
Finally, if you’re interested in learning more, you might want to check out this op-ed I wrote for the New York Times. And if you are willing to read a little more (okay, a lot more), here is a longer paper I wrote for the New England Journal of Medicine.
Melinda and I remain committed to improving the health of the poorest 2 billion. The good news is, many of the steps required to save lives in poor countries—such as strengthening health systems—also improve the world’s ability to deal with epidemics. So I’m optimistic that we can solve this problem. Making the right investments now could save millions of lives.
An Anti-Viral Campaign
Hard questions about the next epidemic
I hit the road to talk about preventing epidemics. Here’s what I heard.
Normally when I post here on TGN, give a speech, or write an op-ed, I’m out to share good news about how the world is getting better. But last month I made an exception. In a TED talk, an op-ed in the New York Times, and a longer paper in the New England Journal of Medicine, I wanted to highlight a sobering fact: The world is not prepared to handle a major epidemic. I shared a few thoughts about what it might take to get ready, based on lessons from the Ebola epidemic in West Africa.
I was curious to hear people’s feedback on my suggestions, so it was great to meet in Berlin with a group of health experts from governments, non-profits, and pharmaceutical companies, and then with U.S. senators in Washington, D.C. In this post, I want to share a few of the things I heard.
There is general agreement that this is a big challenge. Everyone I talked to, politicians and technical experts alike, felt strongly that the world isn’t doing enough to prepare. There is also broad agreement about what to do: we need to create a global alert and response system for epidemics.
As we got into the details, though, we ran into some tough issues.
For example, I argued that in a severe epidemic, the military has to play a role. It’s the only group that can quickly move large numbers of people and equipment in and out of an affected area. But in my conversations in D.C., it became clear that the U.S. military is not chartered for this work and doesn’t prepare for it, which meant that in West Africa they were learning on the fly.
In addition, what happens when there’s an outbreak in a region where people see the army—whether it’s domestic or foreign—as the bad guy? Some NGO leaders and health workers worry that being associated with armed forces could put them in harm’s way by making them a target.
This is one of the toughest issues that came up and it deserves more discussion. At a minimum I think we need a diverse set of military groups from different countries ready to help. And we can take steps to make it clear that troops are on a humanitarian mission, for example by running simulations in different countries so citizens can see what they’re up to.
Another big topic was drug trials. In an epidemic you want to develop and test new treatments very quickly. But how do you make that happen when the usual drug-approval process takes years? Should there be an emergency regulator who decides which drugs to test, how to test them quickly, and whether to deploy one? Should (and can) they indemnify whoever is producing the drug to protect them from lawsuits?
All these conversations raised a larger issue that is fascinating to me: How should the world get ready for rare, potentially cataclysmic events? When an epidemic strikes, we will want the best health and logistics experts ready to spring into action. But which group has the budget to maintain that kind of spare capacity? Even more importantly, how do we get brilliant people to sit around waiting for an event that has a small chance of occurring in any given year?
The closest analogy I can think of is the military, where troops might go years at a time without seeing combat. They use training exercises and war games to stay sharp. I think we should be doing something similar—germ games—for epidemics.
What happens next? Even though the experts mostly agree on the broad strokes of what should be done, I don’t know whether the world will choose to put meaningful resources into this effort. But I am hopeful that it will happen. The group I joined in Berlin is providing input to German Chancellor Angela Merkel and the G7 group of wealthy countries as they think about how they can help solve this problem. Creating a global plan would help more nations see how they can contribute and hopefully draw them in. The United Nations and WHO are also looking at various steps that could improve their ability to respond. And at the Gates Foundation we’re talking about how we might be able to assist.
It is great to see this issue rising up the global agenda. The world isn’t ready yet for a serious epidemic, but I think we have a good chance to make real progress in the next few months.
Well Suited
Arming doctors to fight Ebola
As I learned recently, it’s one thing to find a new tool that will help the people fighting this deadly disease. Getting it to them is another story.
Getting new tools into the hands of the people fighting Ebola is much harder than it needs to be. I have experience with one alarming example.
Health workers in protective suits get so hot that they have a hard time caring for their patients. (For example your goggles fog up and you sweat profusely.) I asked a team of experts who work on technology for keeping vaccines cold to refocus on keeping the medical workers cool.
Within days, the team had found an existing solution: a vest with pockets where you could insert cooling packs.
Doctors who had treated Ebola patients in West Africa helped test and improve these cooling vests. Here you see Dr. Colin Bucks of Stanford University testing a vest and suit at home while under quarantine after working in Liberia. He rode a stationary bike to simulate the heat of West Africa.

Unfortunately, there was no coordinated system for getting the vests to West Africa. The team had to create new distribution channels by working directly with treatment centers in the region. They eventually got the suits to over a thousand health workers.

Although this wasn’t a critical issue, it is just one example of the challenge of preparing for a highly infectious disease. We see similar breakdowns in detecting outbreaks early, training and deploying volunteers, coordinating with the military, and more. But I’m optimistic that if we start now and stay focused, we can get ready for the next epidemic.

Dino-Might
How dinosaurs could help us fight malnutrition
Research on ancient reptiles may help us understand how children grow.
Kids love dinosaurs. When you’re three feet tall and can’t have dinner unless somebody brings you food, the idea of enormous, powerful creatures that have fangs to defend themselves and claws to capture their own meals seems pretty great.
I loved dinosaurs as much as anyone, but eventually I grew tall enough to get my own dinner, and my interest in dinosaurs waned.
My friend Nathan Myhrvold, though, never stopped loving dinosaurs. Actually, there are a lot of things Nathan never stopped loving—he’s published best-selling cookbooks and essays on bioterrorism, among other things—but if you ask him about his longest-running obsession, he’ll tell you it’s dinosaurs. His office is full of dinosaur bones, some of which he dug up himself, along with a model of a dinosaur whose tail moved so fast it broke the sound barrier.

Because he’s so curious, Nathan can take what he knows about these great reptiles and apply it to fields that seem completely unrelated—fields like childhood nutrition, one of the most important and misunderstood areas in all of development.
Here’s a short video in which he explains the connection:
Dinosaur growth rates, it turns out, are hard to study. There may be only thirty fossils of a particular dinosaur species in the world, and none of them may be complete. So how do you know whether a bone is shaped a certain way because that’s how triceratops grew or whether your particular specimen just had a funny-looking head?
In poor countries, children’s physical development is also hard to study, though for different reasons. For one thing, measurements are notoriously inaccurate. If you’re measuring a crying, squirming baby who doesn’t want a cold tape measure pressed up against his body, you might not get the numbers exactly right. There’s also a host of reasons a child could be short. Is this girl short because she’s malnourished? Is she from a short family? Or has she just not hit her growth spurt yet?
What that means is that in both areas, dinosaur growth and childhood growth, you end up with problematic data; with children, it’s messy, and with dinosaurs, it’s sparse. In both cases, though, the problem is the same: looking at the data from the wrong angle gives you the wrong answers.
Nathan thinks he’s figured out a systematic way to look at the growth records from the right angle. Since we started working with him he’s shared some promising ideas about how to measure children’s growth accurately, analyze the trends, and take action on the analysis. For example, some researchers recently looked at the relationship between gross domestic product and childhood stunting and, to everyone’s surprise, they found no correlation—until Nathan pointed out that they were using the wrong statistical methods to analyze the information. The methods he suggested instead—based on his work on dinosaurs—showed that the relationship was actually even stronger than many people in the field had thought. And that could have a big impact on how policymakers and health-care workers approach the problem of childhood nutrition.
This is a great example of a trend I hope we’ll see a lot more of: taking scientific advances from lots of different fields and using them to solve problems in global health.
Ever since dinosaurs were discovered, kids have showered them with love. Thanks to this work, we may have found a way for dinosaurs to pay them back.
Spending Pennies, Saving Lives
The Miracle of Vaccines
Vaccines, one of the best investments you can make for improving health.
Imagine there’s an infectious disease spreading through your community. It leaves some people crippled; others die from it. Then someone comes along and says: “Here’s something that will protect you from this disease for the rest of your life. You and your family can have it, for free.” You would be very relieved, right?
This scenario may seem hypothetical (though perhaps less so given how much the Ebola virus has been in the news). But it is very real for millions of people in the world’s poorest countries. Vaccines that were once out of reach for them are being delivered in greater numbers every year. That means more parents are feeling the relief of knowing their families are protected.
I’ve been looking at some of the data on vaccines and thought I would share what I’m seeing. At a time when so many news headlines are grim, it is inspiring stuff.
I’ll start with polio. Cases are down more than 99 percent since 1988. Earlier this year, we celebrated a fantastic achievement: India was declared polio-free. And in Nigeria, the number of polio cases is at an all-time low, just 6 so far this year versus more than 50 by this time last year. It’s one of only three countries that have never been polio free (the others are Pakistan and Afghanistan).
Wherever we make progress on polio, it’s a testament to the amazing work of many people: political leaders who prioritize stopping the disease, donors who help fund the effort, and—most importantly—the health workers who doggedly go from house to house to deliver vaccines. Thanks to all this work (and with a little luck), 2015 could be the first time Nigeria goes a year without a case of wild poliovirus, and the first time all of Africa is polio-free. If we maintain this commitment, I’m quite optimistic that by 2018 we will get rid of this crippling disease, everywhere, forever.
There’s also fantastic progress in delivering basic immunizations for diseases like measles and pneumonia. The impact is phenomenal: By next year, the public-health group known as Gavi, the Vaccine Alliance will have helped prevent 3.9 million deaths. And expanding vaccine coverage over the next five years can save as many as 6 million lives and unlock more than $100 billion in economic benefit.
Along those lines, we hit a big milestone in September. With the addition of South Sudan, pentavalent vaccine—which protects against five debilitating diseases—has now been introduced in all 73 countries that get financial support from Gavi. Pentavalent replaced a vaccine that protected against only three diseases, which means kids are protected from more diseases without getting any extra shots. This would never have happened without Gavi: By negotiating with manufacturers and bringing in new suppliers, it drove down the cost of pentavalent vaccine from $30 per dose in rich countries to just $1.19 for poor countries.
Another big step has been the rollout of a vaccine for rotavirus, which causes severe diarrhea. Rotavirus is one of the reasons Melinda and I first got involved in global health; in the late 1990s, we were shocked by a newspaper article that said it killed 800,000 children a year—nearly all of them in poor countries—more than almost any other disease. After more research, we decided rotavirus should be a focus of our giving. We’re gratified to see that 65 countries are now rolling out rotavirus vaccines, and more are signing up. Manufacturers in India are working on a new vaccine and talking about exporting it to other countries, which would help save even more children.
We’re also getting closer to solving some big delivery problems, like the fact that many vaccines spoil if they get too warm. Researchers are field-testing a specially designed container that keeps vaccines cold for a month or more, using just a single batch of ice and no electricity. These trials are helping thousands of African children get immunized. I’m very hopeful that containers like this one will eventually help health workers reach far more people.
A Ripple Effect
Vaccines save lives, which is reason enough to make sure they get out there. But that’s not their only benefit. Healthy children spend more time in school, and they learn better while they’re there. When health improves, poor countries can spend more on schools, roads, and other investments that drive growth, which makes them less dependent on aid.
Vaccines deliver all this for, in some cases, just pennies per shot. That’s why I say that if you want to save and improve lives around the world, vaccines are a fantastic investment.
How You Can Help
One way you can help is to ask your political leaders to support Gavi next year, when donor governments need to renew their commitments. In the United States you can do that through Shot@Life, whose website makes it easy to send a message to your representatives.
You can also help by donating to Shot@Life. For $20, you can help protect a child from pneumonia, diarrhea, polio, and measles. And Shot@Life has teamed up with Walgreens for a “Get a shot. Give a shot” program: Get a vaccine at Walgreens and they will provide one for a child in a poor country.
This is flu season in the United States, so you may already be planning to get immunized. Why not help out someone else while you’re at it?
On the Front Lines of an Epidemic
“Your blood tested positive for Ebola. I am sorry.”
A Nigerian doctor’s harrowing account of outlasting the deadly virus.
Once in a while, you read something that’s so compelling, you want to share it with everyone you can. Dr. Ada Igonoh’s story had that effect on me.
Dr. Igonoh is a physician in Lagos, Nigeria, where she helped care for Patrick Sawyer, the patient who introduced Ebola into Nigeria in July. After coming down with the deadly virus herself, she spent two harrowing weeks getting treatment in isolation wards.
When I met her at a conference in New Orleans last week, Dr. Igonoh handed me a written account of her experience. Even knowing she was going to be okay, I couldn’t stop reading—I had to know what happened next. Her optimism was inspiring. Her story also gave me a deeper appreciation for all the health workers who are heroically caring for patients and trying to stop this epidemic. And it is a good reminder of the way uncertainty reigns in the early days of an epidemic. The world’s response since then has been remarkable, and Nigeria has now been certified free of Ebola.
I want to thank Dr. Igonoh for her courage, and for agreeing to let me share her story here. It is well worth your time to read it. — Bill Gates
On the night of Sunday July 20th, 2014, Patrick Sawyer was wheeled into the emergency room of the First Consultants Medical Centre, Obalende, Lagos, with complaints of fever and body weakness. The male doctor on call admitted him as a case of malaria, and took a full history.

Knowing that Mr. Sawyer had recently arrived from Liberia, the doctor asked if he had been in contact with an Ebola patient in the last couple of weeks, and Mr. Sawyer denied any such contact. He also denied attending any funeral ceremony recently. Blood samples were taken for full blood count, malaria parasites, liver function test, and other baseline investigations. He was admitted into a private room and started on antimalarial drugs and analgesics. That night, the blood count result came back as normal and not indicative of infection.
The following day, however, his condition worsened. He barely ate any of his meals. His liver function test result showed his liver enzymes were markedly elevated. We then took samples for HIV and hepatitis screening.
At about 5:00 p.m. he requested to see a doctor. I was the doctor on call that night, so I went in to see him. He was lying in bed with his intravenous (IV) fluid bag removed from its metal stand and placed beside him. He complained that he had stooled about five times that evening and that he wanted to use the bathroom again.
I picked up the IV bag from his bed and hung it back on the stand. I told him I would inform a nurse to come and disconnect the IV so he could conveniently go to the bathroom. I walked out of his room and went straight to the nurses' station where I told the nurse on duty to disconnect his IV. I then informed my consultant, Dr. Ameyo Adadevoh, about the patient's condition, and she asked that he be placed on some medications.
The following day, the results for HIV and hepatitis screening came out negative. As we were preparing for the early morning ward rounds, I was approached by an ECOWAS [Economic Community of West African States] official who informed me that Patrick Sawyer had to catch an 11 o'clock flight to Calabar for a retreat that morning. He wanted to know if it would be possible. I told him it wasn't, as he was acutely ill. Dr. Adadevoh also told him the patient could certainly not leave the hospital in his condition. She then instructed me to write very boldly on his chart that on no account should Patrick Sawyer be allowed out of the hospital premises without the permission of Dr. Ohiaeri, our Chief Medical Consultant. All nurses and doctors were duly informed.
During our early morning ward round with Dr. Adadevoh, we concluded that this was not malaria, and that the patient needed to be screened for Ebola Viral Disease. She immediately started calling laboratories to find out where the test could be carried out. She was eventually referred to Professor Omilabu of the LUTH Virology Reference Lab in Idi-Araba, whom she called immediately.
Prof. Omilabu told her to send blood and urine samples to LUTH straightaway. She tried to reach the Lagos State Commissioner for Health but was unable to contact him at the time. She also put calls across to officials of the Federal Ministry of Health and National Centre for Disease Control.
Dr. Adadevoh at this time was in a pensive mood. Patrick Sawyer was now a suspected case of Ebola, perhaps the first in the country. He was quarantined, and strict barrier nursing was applied with all the precautionary measures we could muster. Dr. Adadevoh went online, downloaded information on Ebola, and printed copies which were distributed to the nurses, doctors and ward maids. Blood and urine samples were sent to LUTH that morning. Protective gear, gloves, shoe covers and facemasks were provided for the staff. A wooden barricade was placed at the entrance of the door to keep visitors and unauthorized personnel away from the patient. Despite the medications prescribed earlier, the vomiting and diarrhea persisted. The fever escalated from 38°C to 40°C.
On the morning of Wednesday, 23rd July, the tests carried out in LUTH showed a signal for Ebola. Samples were then sent to Dakar, Senegal for a confirmatory test. Dr. Adadevoh went for several meetings with the Lagos State Ministry of Health. Thereafter, officials from the Lagos State came to inspect the hospital and the protective measures we had put in place.
The following day, Thursday 24th July, I was again on call. At about 10:00 p.m. Mr. Sawyer requested to see me. I went into the newly created dressing room, donned my protective gear and went in to see him. He had not been cooperating with the nurses and had refused any additional treatment. He sounded confused and said he received a call from Liberia asking for a detailed medical report to be sent to them. He also said he had to travel back to Liberia on a 5:00 a.m. flight the following morning and that he didn't want to miss his flight. I told him that I would inform Dr. Adadevoh. As I was leaving the room, I met Dr. Adadevoh dressed in her protective gear, along with a nurse and another doctor. They went into his room to have a discussion with him, and as I heard later to reset his IV line which he had deliberately removed after my visit to his room.
At 6:30 a.m., Friday 25th July, I got a call from the nurse that Patrick Sawyer was completely unresponsive. Again I put on the protective gear and headed to his room. I found him slumped in the bathroom. I examined him and observed that there was no respiratory movement. I felt for his pulse; it was absent. We had lost him.
It was I who certified Patrick Sawyer dead. I informed Dr. Adadevoh immediately and she instructed that no one was to be allowed to go into his room for any reason at all. Later that day, officials from WHO came and took his body away. The test in Dakar later came out positive for Zaire strain of the Ebola virus. We now had the first official case of Ebola virus disease in Nigeria.
It was a sobering day. We all began to go over all that happened in the last few days, wondering just how much physical contact we had individually made with Patrick Sawyer. Every patient on admission was discharged that day and decontamination began in the hospital. We were now managing a crisis situation.
The next day, Saturday 26th July, all staff of First Consultants attended a meeting with Prof. Nasidi of the National Centre for Disease Control, Prof. Omilabu of LUTH Virology Reference Lab, and some officials of WHO. They congratulated us on the actions we had taken and enlightened us further about the Ebola Virus Disease. They said we were going to be grouped into high risk and low risk categories based on our individual level of exposure to Patrick Sawyer, the "index" case. Each person would receive a temperature chart and a thermometer to record temperatures in the morning and night for the next 21 days. We were all officially under surveillance. We were asked to report to them at the first sign of a fever for further blood tests to be done. We were reassured that we would all be given adequate care. The anxiety in the air was palpable.
The frenetic pace of life in Lagos, coupled with the demanding nature of my job as a doctor, means that I occasionally need a change of environment. As such, one week before Patrick Sawyer died, I had gone to my parents' home for a retreat. I was still staying with them when I received my temperature chart and thermometer on Tuesday, 29th of July. I could not contain my anxiety. People were talking about Ebola everywhere—on television, online, everywhere.

I soon started experiencing joint and muscle aches and a sore throat, which I quickly attributed to stress and anxiety. I decided to take malaria tablets. I also started taking antibiotics for the sore throat. The first couple of temperature readings were normal. Every day I would attempt to recall the period Patrick Sawyer was on admission—just how much direct and indirect contact did I have with him? I reassured myself that the contact with him was quite minimal. I completed the anti-malarials but the aches and pains persisted. I had loss of appetite and felt very tired.
On Friday, 1st of August, my temperature read a high 38.7°C. As I type this, I recall the anxiety I felt that morning. I could not believe what I saw on the thermometer. I ran to my mother's room and told her. I did not go to work that day. I cautiously started using a separate set of utensils and cups from the ones my family member were using.
On Saturday, 2nd of August, the fever worsened. It was now at 39°C and would not be reduced by taking paracetamol. This was now my second day of fever. I couldn't eat. The sore throat was getting worse. That was when I called the helpline and an ambulance was sent with WHO doctors, who came and took a sample of my blood. Later that day, I started stooling and vomiting. I stayed away from my family. I started washing my plates and spoons myself. My parents, meanwhile, were convinced that I could not have Ebola.
The following day, Sunday, 3rd of August, I got a call from one of the doctors who came to take my sample the day before. He told me that the sample which they had taken was not confirmatory, and that they needed another sample. He did not sound very coherent and I became worried. They came with the ambulance that afternoon and told me that I had to go with them to Yaba. I was confused. Couldn't the second sample be taken in the ambulance like the previous one? He said a better-qualified person at the Yaba Centre would take the sample. I asked if they would bring me back. He said "yes." Even with my symptoms, I did not believe I had Ebola. After all, my contact with Sawyer was minimal. I only touched his IV fluid bag just that once without gloves. The only time I actually touched him was when I checked his pulse and confirmed him dead, and I wore double gloves and I felt adequately protected.
I told my parents I had to go with the officials to Yaba and that I would be back that evening. I wore a white top and a pair of jeans, and I put my iPad and phones in my bag.
A man opened the ambulance door for me and moved away from me rather swiftly. Strange behavior, I thought. They were friendly with me the day before, but that day, not so. No pleasantries, no smiles. I looked up and saw my mother watching through her bedroom window.
We soon got to Yaba. I really had no clue where I was. I knew it was a hospital. I was left alone in the back of the ambulance for over four hours. My mind was in a whirl. I didn't know what to think. I was offered food to eat but I could barely eat the rice.
The ambulance door opened and a Caucasian gentleman approached me but kept a little distance. He said to me, "I have to inform you that your blood tested positive for Ebola. I am sorry."
I had no reaction. I think I must have been in shock. He then told me to open my mouth and he looked at my tongue. He said it was typical Ebola tongue. I took out my mirror from my bag and took a look and was shocked at what I saw. My whole tongue had a white coating, looked furry, and had a long, deep ridge right in the middle. I then started to look at my whole body, searching for Ebola rashes and other signs, as we had been recently instructed. I called my mother immediately and said, "Mummy, they said I have Ebola, but don't worry, I will survive it. Please go and lock my room now; don't let anyone inside and don't touch anything." She was silent. I cut the line.
I was taken to the female ward. I was shocked at the environment. It looked like an abandoned building. I suspected it had not been in use for quite a while. As I walked in, I immediately recognized one of the ward maids from our hospital. She always had a smile for me but not this time. She was ill and looked it. She had been stooling a lot, too. I soon settled into the corner and looked around the room. It smelled of feces and vomit. It also had a characteristic Ebola smell to which I became accustomed. Dinner was served—rice and stew. The pepper stung my mouth and tongue. I dropped the spoon. No dinner that night.
Dr. David, the Caucasian man who had met me at the ambulance on my arrival, came in wearing his full protective hazmat suit and goggles. It was fascinating seeing one live. I had only seen them online. He brought bottles of water and ORS, the oral fluid therapy, which he dropped by my bedside. He told me that 90 percent of the treatment depended on me. He said I had to drink at least 4.5 litres of ORS daily to replace fluids lost in stooling and vomiting. I told him I had stooled three times earlier and taken Imodium tablets to stop the stooling. He said it was not advisable, as the virus would replicate the more inside of me. It was better, he said, to let it out. He said good night and left.
My parents called. My uncle called. My husband called crying. He could not believe the news. My parents had informed him, as I didn't even know how to break the news to him.
As I lay on my bed in that isolation ward, strangely, I did not fear for my life. I was confident that I would leave that ward some day. There was an inner sense of calm. I did not for a second think that I would be consumed by the disease.
That evening, the symptoms fully kicked in. I was stooling almost every two hours. The toilets did not flush, so I had to fetch water in a bucket from the bathroom each time I used the toilet. I then placed another bucket beneath my bed for the vomiting. On occasion, I would run to the toilet with a bottle of ORS, so that as I was stooling, I was drinking.
The next day, Monday, 4th of August, I began to notice red rashes on my skin, particularly on my arms. I had developed sores all over my mouth. My head was pounding so badly. The sore throat was so severe I could not eat. I could only drink ORS. I took paracetamol for the pain. The ward maid across from me wasn't doing so well. She had stopped speaking. I couldn't even brush my teeth; the sores in my mouth were so bad. This was a battle for my life but I was determined I would not die.
Every morning, I began the day with reading and meditating on Psalm 91. The sanitary condition in the ward left much to be desired. The whole Ebola thing had caught everyone by surprise. Lagos State Ministry of Health was doing its best to contain the situation but competent hands were few. The sheets were not changed for days. The floor was stained with greenish vomitus and excrement. Dr. David would come in once or twice a day and help clean up the ward after chatting with us. He was the only doctor who attended to us. There was no one else at that time. The matrons would leave our food outside the door. They hardly entered in the initial days. Everyone was being careful. This was all so new. I could understand, was this not how we ourselves had contracted the disease? Mosquitoes were in our room until they brought us mosquito nets.
Later that evening, Dr. David brought another lady into the ward. I recognized her immediately as Justina Ejelonu, a nurse who had started working at First Consultants on the 21st of July, a day after Patrick Sawyer was admitted. She was on duty on the day Patrick reported that he was stooling. While she was attending to him that night, he had yanked off his drip, letting his blood flow almost like a tap onto her hands. Justina was pregnant and was brought into our ward bleeding from a suspected miscarriage. She had been told she was there only on observation. The news that she had contacted Ebola was broken to her the following day after results of her blood test came out positive. Justina was devastated and wept profusely—she had contracted Ebola on her first day at work.
My husband started visiting but was not allowed to come close to me. He could only see me from a window at a distance. He visited so many times. It was he who brought me a change of clothes and toiletries and other things I needed because I had not even packed a bag. I was grateful I was not with him at home when I fell ill or he would most certainly have contracted the disease. My retreat at my parents' home turned out to be the instrumentality God used to shield and save him.
I drank the ORS fluid like my life depended on it. Then I got a call from my pastor. He had been informed about my predicament. He called me every single day, morning and night, and he would pray with me over the phone. He later sent me a CD player, CDs of messages on faith and healing, and Holy Communion packs through my husband. My pastor, who also happens to be a medical doctor, encouraged me to monitor how many times I had stooled and vomited each day and how many bottles of ORS I had consumed. We would then discuss the disease and pray together. He asked me to do my research on Ebola since I had my iPad with me, and told me that he was also doing his study. He wanted us to use all relevant information on Ebola to our advantage. So I researched and found out all I could about the strange disease that had been in existence for 38 years. My research, my faith, and my positive view of life, the extended times of prayer, study and listening to encouraging messages boosted my belief that I would survive the Ebola scourge.
There are five strains of the virus, and the deadliest of them is the Zaire strain, which was what I had. But that did not matter. I believed I would overcome even the deadliest of strains. Infected patients who succumb to the disease usually die between 6 to 16 days after the onset of the disease from multiple organ failure and shock caused by dehydration. I was counting the days and keeping myself well-hydrated. I didn't intend to die in that ward.
My research gave me ammunition. I read that as soon as the virus gets into the body, it begins to replicate really fast. It enters the blood cells, destroys them and uses those same blood cells to aggressively invade other organs where they further multiply. Ideally, the body's immune system should immediately mount up a response by producing antibodies to fight the virus. If the person is strong enough, and that strength is sustained long enough for the immune system to kill off the viruses, the patient is likely to survive. If the virus replicates faster than the antibodies can handle, however, further damage is done to the organs. Ebola can be likened to multi-level, multi-organ attack, but I had no intention of letting the deadly virus destroy my system. I drank more ORS. I remember saying to myself repeatedly, "I am a survivor, I am a survivor."
I also found out that a patient with Ebola cannot be re-infected and they cannot relapse back into the disease as there is some immunity conferred on survivors. My pastor and I would discuss these findings, interpret them as it related to my situation and pray together. I looked forward to his calls. They were times of encouragement and strengthening. I continued to meditate on the Word of God. It was my daily bread.
Shortly after Justina came into the ward, the ward maid, Mrs. Ukoh, passed on. The disease had gotten into her central nervous system. We stared at her lifeless body in shock. It was a whole 12 hours before officials of WHO came and took her body away. The ward had become the house of death. The whole area surrounding her bed was disinfected with bleach. Her mattress was taken and burned.
To contain the frequent diarrhea, I had started wearing adult diapers, as running to the toilet was no longer convenient for me. The indignity was quite overwhelming, but I did not have a choice. My faith was being severely tested. The situation was desperate enough to break anyone psychologically. Dr. Ohiaeri also called us day and night, enquiring about our health and the progress we were making. He sent provisions, extra drugs, vitamins, Lucozade, towels, tissue paper; everything we needed to be more comfortable in that dark hole we found ourselves. Some of my male colleagues also had been admitted to the male ward two rooms away, but there was no interaction with them. We were saddened by the news that Jato, the ECOWAS protocol officer to Patrick Sawyer, who had also tested positive, had passed on days after he was admitted.
Two more females joined us in the ward; a nurse from our hospital and a patient from another hospital. The mood in the ward was solemn. There were times we would be awakened by the sudden, loud cry from one of the women. It was either from fear, pain mixed with the distress, or just the sheer oppression of the isolation.
I kept encouraging myself. This could not be the end for me. Five days after I was admitted, the vomiting stopped. A day after that, the diarrhea ceased. I was overwhelmed with joy. It happened at a time I thought I could no longer stand the ORS. Drinking that fluid had stretched my endurance greatly.
I knew countless numbers of people were praying for me. Prayer meetings were being held on my behalf. My family was praying day and night. Text messages of prayers flooded my phone from family members and friends. I was encouraged to press on. With the encouragement I was receiving, I began to encourage the others in the ward. We decided to speak life and focus on the positive.
I then graduated from drinking only the ORS fluid to eating only bananas, to drinking pap and then bland foods. Just when I thought I had the victory, I suddenly developed a severe fever. The initial fever had subsided four days after I was admitted, and then suddenly it showed up again. I thought it was the Ebola. I enquired from Dr. David, who said fever was sometimes the last thing to go, but he expressed surprise that it had stopped only to come back on again. I was perplexed.
I discussed it with my pastor, who said it could be a separate pathology and possibly a symptom of malaria. He promised he would research if indeed this was Ebola or something else. That night as I stared at the dirty ceiling, I felt a strong impression that the new fever I had developed was not as a result of Ebola but malaria. I was relieved. The following morning, Dr. Ohiaeri sent me an antimalarial medication, which I took for three days. Before the end of the treatment, the fever had disappeared.
I began to think about my mother. She was under surveillance along with my other family members. I was worried. She had touched my sweat. I couldn't get the thought off my mind. I came across a tweet by WHO saying that the sweat of an Ebola patient cannot transmit the virus at the early stage of the infection. The sweat could only transmit it at the late stage.
That settled it for me. It calmed the storms that were raging with me concerning my parents. I knew right away it was divine guidance that caused me to see that tweet. I could cope with having Ebola, but I was not prepared to deal with a member of my family contracting it from me.
Soon, volunteer doctors started coming to help Dr. David take care of us. They had learned how to protect themselves. Among the volunteer doctors was Dr. Badmus, my consultant in LUTH during my housemanship days. It was good to see a familiar face among the care-givers. I soon understood the important role these brave volunteers were playing. As they increased in number, so did the number of shifts increase and subsequently the number of times the patients could access a doctor in one day. That allowed for more frequent patient monitoring and treatment. It also reduced care-giver fatigue. It was clear that Lagos State was working hard to contain the crisis.
Sadly, Justina succumbed to the disease on the 12th of August. It was a great blow and my faith was greatly shaken as a result. I commenced daily Bible study with the other two female patients and we would encourage one another to stay positive in our outlook, though in the natural it was grim and very depressing. My communion sessions with the other women were very special moments for us all.
On the 10th day in the ward, the doctors having noted that I had stopped vomiting and stooling and was no longer running a fever, decided it was time to take my blood sample to test if the virus had cleared from my system. They took the sample and told me that I shouldn't be worried if it comes out positive as the virus takes a while before it is cleared completely. I prayed that I didn't want any more samples collected from me. I wanted that to be the first and last sample to be tested for the absence of the virus in my system. I called my pastor. He encouraged me and we prayed again about the test.
On the evening of the day Justina passed on, we were moved to the new isolation centre. We felt like we were leaving hell and going to heaven. We were conveyed to the new place in an ambulance. It was just behind the old building. Time would not permit me to recount the drama involved with the dynamics of our relocation. It was like a script from a science fiction movie. The new building was cleaner and much better than the old building. Towels and nightwear were provided on each bed. The environment was serene.
The following night, Dr. Adadevoh was moved to our isolation ward from her private room where she had previously been receiving treatment. She had also tested positive for Ebola and was now in a coma. She was receiving IV fluids and oxygen support and was being monitored closely by the WHO doctors. We all hoped and prayed that she would come out of it. It was so difficult seeing her in that state. I could not bear it. She was my consultant and my mentor. She was the imperial lady of First Consultants, full of passion, energy and competence. I imagined she would wake up soon and see that she was surrounded by her First Consultants family but sadly it was not to be.
I continued listening to my healing messages. They gave me life. I literally played them hours on end. Two days later, on Saturday the 16th of August, the WHO doctors came with some papers. I was informed that the result of my blood test was negative for the Ebola virus. If I could somersault, I would have, but my joints were still slightly painful. I was free to go home after being in isolation for exactly 14 days. I was so full of thanks and praise to God. I called my mother to get fresh clothes and slippers and come pick me up. My husband couldn't stop shouting when I called him. He was completely overwhelmed with joy.
I was told however that I could not leave the ward with anything I came in with. I glanced one last time at my CD player, my valuable messages, my research assistant, a.k.a my iPad, my phones and other items. I remember saying to myself, "I have life; I can always replace these items."
I went for a chlorine bath, which was necessary to disinfect my skin from my head to my toes. It felt like I was being baptized into a new life as Dr. Carolina, a WHO doctor from Argentina poured the bucket of chlorinated water all over me. I wore a new set of clothes, following the strict instructions that no part of the clothes must touch the floor and the walls. Dr. Carolina looked on, making sure I did as instructed.
I was led out of the bathroom and straight to the lawn to be united with my family, but first I had to cut the red ribbon that served as a barrier. It was a symbolic expression of my freedom. Everyone cheered and clapped. It was a little but very important ceremony for me. I was free from Ebola! I hugged my family as one who had been liberated after many years of incarceration. I was like someone who had fought death face to face and come back to the land of the living.
We had to pass through several stations of disinfection before we reached the car. Bleach and chlorinated water were sprayed on everyone's legs at each station. As we made our way to the car, we walked past the old isolation building. I could hardly recognize it. I could not believe I slept in that building for 10 days. I was free! Free of Ebola. Free to live again. Free to interact with humanity again. Free from the sentence of death.
My parents and two brothers were under surveillance for 21 days and they completed the surveillance successfully. None of them came down with a fever. The house had been disinfected by Lagos State Ministry of Health soon after I was taken to the isolation centre. I thank God for shielding them from the plague.
My recovery after discharge has been gradual but progressive. I thank God for the support of family and friends. I remember my colleagues who we lost in this battle. Dr. Adadevoh my boss, Nurse Justina Ejelonu, and the ward maid, Mrs. Ukoh were heroines who lost their lives in the cause to protect Nigeria. They will never be forgotten.
I commend the dedication of the WHO doctors, Dr. David from Virginia, USA, who tried several times to convince me to specialize in infectious diseases, Dr. Carolina from Argentina who spoke so calmly and encouragingly, Mr. Mauricio from Italy who always offered me apples and gave us novels to read. I especially thank the volunteer Nigerian doctors, matrons and cleaners who risked their lives to take care of us. I must also commend the Lagos State government, and the state and federal ministries of health for their swift efforts to contain the virus.

To all those who prayed for me, I cannot thank you enough. And to my First Consultants family, I say a heartfelt thank you for your dedication and for your support throughout this very difficult period.
I still believe in miracles. None of us in the isolation ward was given any experimental drugs or so-called immune boosters. I was full of faith, yet pragmatic enough to consume as much ORS as I could, even when I wanted to give up and throw the bottles away. I researched on the disease extensively and read accounts of the survivors. I believed that even if the mortality rate was 99 percent, I would be part of the 1 percent who would survive.
Early detection and reporting to hospital is key to patient survival. Please do not hide yourself if you have been in contact with an Ebola patient and have developed the symptoms. Regardless of any grim stories one may have heard about the treatment of patients in the isolation centre, it is still better to be in the isolation ward with specialist care, than at home where you and others will be at risk.
I read that Dr. Kent Brantly, the American doctor who contracted Ebola in Liberia and was flown out to the United States for treatment was being criticized for attributing his healing to God when he was given the experimental drug, Zmapp. I don't claim to have all the answers to the nagging questions of life. Why do some die and some survive? Why do bad things happen to good people? Where is God in the midst of pain and suffering? Where does science end and God begin? These are issues we may never fully comprehend on this side of eternity. All I know is that I walked through the valley of the shadow of death and came out unscathed.
Breaking a Fever
We can eradicate malaria—within a generation
New tools and a new strategy mean we can eradicate it in a generation.
I’m in New Orleans, where I just had the honor of speaking at the annual meeting of the American Society of Tropical Medicine and Hygiene (ASTMH). As you can imagine, given that this is a gathering of experts on infectious diseases in poor countries, Ebola is on everyone’s mind.
Even though I am confident that the U.S. and other countries with strong public health systems will contain the cases that are popping up within their borders, it’s devastating to see what this virus is doing to entire families in West Africa. At times like this, it’s easy for organizations like ASTMH to make the public case that global health matters to all of us in our increasingly interconnected world. I hope that will help strengthen the public will to do more to help poor countries lift the burden of disease—not just from emerging killers like Ebola but also from pathogens that have held back human potential for thousands of years.
That’s why, in my remarks at the conference, I addressed the Ebola crisis but devoted the bulk of my time to another killer disease: malaria. Based on the progress I’m seeing in the lab and on the ground, I believe we’re now in a position to eradicate malaria—that is, wipe it out completely in every country—within a generation. This is one of the greatest opportunities the global health world has ever had. Melinda and I are so optimistic about it that we recently decided to increase our foundation’s malaria budget by 30 percent.
Melinda and I first called for eradication back in 2007 along with Margaret Chan, who runs the World Health Organization. Melinda was eloquent and passionate in her call to action: “Any goal short of eradicating malaria is accepting malaria; it’s making peace with malaria; it’s rich countries saying: ‘We don’t need to eradicate malaria around the world as long as we’ve eliminated malaria in our own countries.’ That’s just unacceptable.”
Some people said then (and still say today) that we’re overly optimistic to be talking about eradication. After all, malaria is an enormously complex target and has defeated efforts to stamp it out in the past. They’re right that we shouldn’t promise the moon—you don’t get rid of a disease this complex overnight—but I am confident that the future will be different from the past.
Why? Because we’ve seen a huge scale-up in the resources and brainpower focused on this disease. Four countries have eliminated malaria since 2000, and two dozen more could do it in the next decade. Mortality rates worldwide have gone down by a remarkable 42 percent in that time—a good-news story that ought to make critics wary of trumpeting claims that foreign aid doesn’t work. More than 3.3 million people who would have died of malaria are alive today.
And we have tools today we’ve never had before—not everything we will need to achieve eradication, but more than we’ve ever had. Here are two of the recent innovations that fuel my optimism:
- Diagnostics: Malaria is not only treatable but also curable, thanks to a class of drugs derived from a flowering plant called Artemesia annua, or sweet wormwood. But until recently, there was no good way for most people who came down with a fever to find out whether they had malaria. In 2010, we got a great new tool, called the RDT (rapid diagnostic test). Armed with this 50-cent test, community health workers with little training can determine in minutes with 99 percent accuracy whether someone has malaria or not. Last year, we deployed 200 million of them in Africa alone.
- Modeling Systems: The digital revolution has produced fantastic new tools for tracking the disease. Public health experts are combining anonymous data from mobile phone records with data on malaria incidence to identify the key migration hotspots—allowing countries to target their resources in the most cost-effective and strategic ways. In Kenya, for example, these maps helped experts target large-scale tea plantations in the country’s Lake Zone. Comprehensive efforts at the plantations could make it possible to eliminate malaria from large swaths of the country’s highlands without even having to run elimination efforts there.
Just as important as any specific innovation, our team has converged on an eradication strategy that will make the whole greater than the sum of the parts. That strategy has three components: Complete Detection, Complete Cure, and Complete Prevention.
Complete Detection is a departure from current approaches, which focus on finding and treating only those people who have active malaria cases. To achieve eradication, health workers need to find all people who have the parasite in their blood, regardless of whether they’re showing symptoms. (I wrote about this work earlier this year, after Melinda and I saw it in action in Cambodia.) We’re supporting many efforts to develop and bring to market a new generation of diagnostic tools that are even more sensitive than the RDTs now in use and can identify the presence of malaria parasites in all infected individuals.
Complete Cure means using treatments that clear all malaria parasites from the body. Our best anti-malaria treatment today, known as ACT, generally cures the patient clinically but does not eliminate all forms of the parasites that are responsible for continued transmission. So we are trying to supercharge efforts to develop long-lasting, single-dose treatments for malaria that can completely clear malaria parasites from the body and provide a period of protection following the treatment. We believe that our largest partner in this effort, the Medicines for Malaria Venture, could bring these complete-cure drugs to market within five years.
Complete Prevention means reducing opportunities for mosquitoes to pass the parasite on to humans, and preventing the emergence of strains that resist drugs and insecticides. We’ll need next-generation vaccines that block transmission for six months to a year, so that once an area is cleared of the parasite, it stays clear. We’ll also need new insecticides to offset the widespread emergence of mosquito resistance to the chemical compounds we use most frequently today. We may even need cutting-edge approaches, like introducing special fungi into mosquito populations to kill them off or introducing modified genes that can stop mosquitoes from reproducing.
I believe it’s not only possible to eradicate malaria; I believe it’s necessary. Ultimately, the cost of controlling it endlessly is not sustainable. The only way to stop this disease is to end it forever.
If you want to join the fight, please consider donating to our partner Malaria No More.
Beyond the Plow
4 innovations for poor farmers
Four new tools that are helping poor farmers grow more food.
Whenever I visit small farmers in a poor country, I’m struck by how many are laboring with hoes, plows, and other implements that haven’t changed in generations. Yet farmers in wealthier countries have benefited from wave after wave of technological improvements. This gap is one big reason why some farmers produce much more food than others.
Thankfully, some of the brightest minds in Africa, India, and elsewhere are creating new tools to close the gap.
Here are four especially promising innovations…
For many years, so little agriculture research was being done in Africa that we knew less about the soil there than we did about the surface of Mars. Now that’s changing, thanks to an initiative to map the continent’s soil. The Africa Soil Information Service is creating digital maps that help farmers make informed decisions about which seeds to plant, which fertilizers to use, and how to raise their crop yields. They’re available free to anyone with a cell phone or Internet connection.
In Africa, half a billion people depend on cassava as a staple crop. But breeding more-nutritious, disease-resistant varieties of the root takes a long time—a decade or more. Now scientists with the Next Generation Cassava Breeding (NEXTGEN) project have cut that time in half, using computer modeling techniques and a treasure trove of new information on the plant’s genome. They have also improved the breeding cycle, so they can zero in on the most desirable traits earlier in the process.
How do you cheaply spread good information about farming? The Indian nonprofit Digital Green is having success with simple YouTube videos. They’ve shot thousands of videos featuring farmers sharing best practices. (See for yourself.) Farmers, they’ve found, are much more likely to listen to peers who look and sound like them. The idea isn’t limited to farming either: The UK’s development agency is now helping Digital Green use its platform to spread health messages.
Being a dairy farmer has risks. As I learned on a trip to Kenya, milk can spill or spoil on its way from the cow to the chilling station. So I asked the team at Global Good to study the problem. Working with Heifer International, they made a jug that’s easy to clean and won’t spill. Partners in Kenya and Ethiopia will make and sell them for about $5 each, versus up to $30 for other jugs. This modest step could help dairy farmers earn more money—and create new manufacturing and sales jobs too.
Africa’s Table
Why does hunger still exist in Africa?
Not starving, but still hungry in Africa.
When I first started traveling to Africa, I would often meet children in the villages I was visiting and try to guess their ages. I was shocked to find out how often I guessed wrong. Kids I thought were 7 or 8 years old based on how tall they were—would tell me that they were actually 12 or 13 years old.
What I was witnessing was the terrible impact of malnutrition in Africa. These children were suffering from a condition known as stunting. They were not starving, but they were not getting enough to eat, leaving them years behind in their development—and it was hard to see how they could ever catch up.

Stunting not only affects a child’s height. It also has an impact on brain development. Stunted children are more likely to fall behind at school, miss key milestones in reading and math, and go on to live in poverty. When stunted children don’t reach their potential, neither do their countries. Malnutrition saps a country’s strength, lowering productivity and keeping the entire nation trapped in poverty.
Worldwide, one in four children is stunted. Three-quarters of them live in South Asia and sub-Saharan Africa. However, while stunting has declined by more than a third in South Asia since 1990, in sub-Saharan Africa, the number of stunted children is still on the rise, up 12 million since 1990 to 56 million. Forty percent of all children in sub-Saharan Africa are stunted.
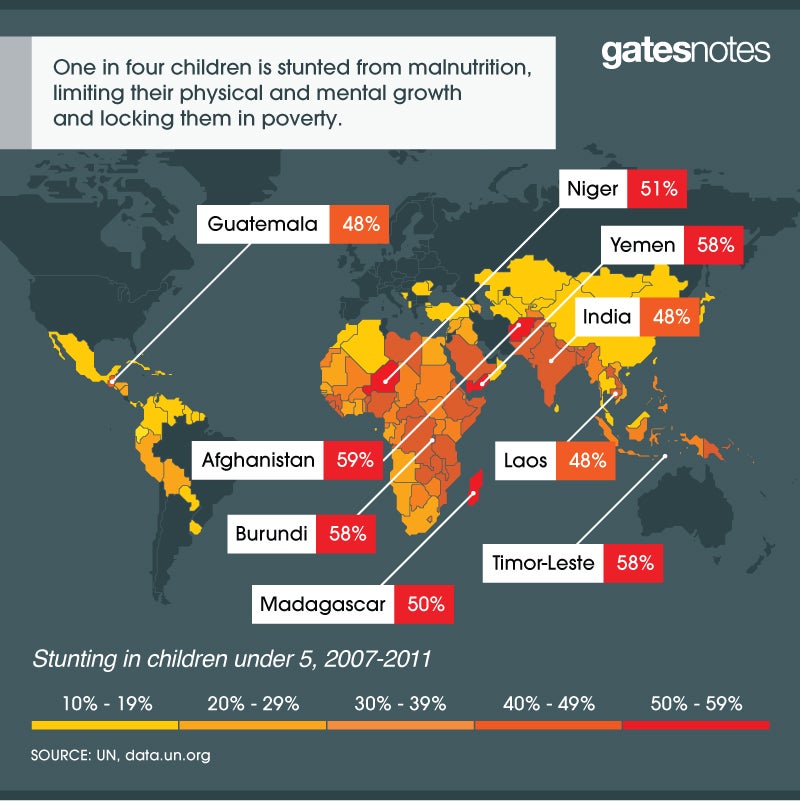
I run into a lot of people from rich countries who still think of Africa as a continent of starvation. The fact is, that’s an outdated picture (to the extent that it was ever accurate at all). Thanks to economic growth and smart policies, the extreme hunger and starvation that once defined the continent are now rare. As I saw when I was back in Africa last month with best-selling author John Green, today the issue isn’t quantity of food as much as it is quality—whether kids are getting enough protein and other nutrients to fully develop.
As Melinda and I have grown aware of the scale of this challenge, we’ve made improving nutrition a bigger priority for our foundation. One thing we’ve quickly come to appreciate is the problem’s complexity. There’s no vaccine to prevent stunting. Proper nutrition involves eating enough food, and the right kinds, every day of your life. While the global health community is still working to understand all of the causes and solutions to malnutrition, we do know a lot about how to ensure children get the nutrition they need for a healthy start to life.
We know that getting children the right nutrition in the first 1000 days—from the start of a woman’s pregnancy until her child’s 2nd birthday – is the best down payment on their future, giving them the opportunity to grow and develop physically and mentally. We also know that exclusive breastfeeding in the first six months of a child’s life is the single most effective intervention to help the brain develop and protect against life-threatening diseases. That’s why we continue to research the best ways to address cultural beliefs and other barriers that have kept almost half of all women from using optimal breastfeeding practices.
We know kids have a hard time getting the nutrients they need when fruits, meats, and vegetables are in short supply—so fortifying staple foods like cooking oil, flour, and salt with essential vitamins and minerals can fill the gap. We’re also beginning to develop new crops that are more-nutritious--including a sweet potato that’s enriched with vitamin A—and also produce a higher yield. Not only does this help smallholder farmers earn more income that can be used to diversify their family’s diet, it also puts more nutritious food directly on their table.
Providing better health care can make a difference too. Children who receive the rotavirus vaccine, for example, have fewer bouts of diarrhea, which can drain kids of vital nutrients and make them more susceptible to infection. Likewise, clean water and sanitation play a role in improving nutrition by reducing illness and disease.
We have many great interventions on our side, but with so many factors at play it can be difficult to measure which interventions have the most impact on improving nutrition and why. If I could have one wish, I would want the world to have a better understanding of malnutrition and how to solve it.
We have much more research to do in this area and we will continue to make progress. But what’s not in doubt is the importance of giving all children the nutrition they need for a healthy start to life. Their future depends on it. So does Africa’s.
Tax-Day Blues?
A reason to smile on April 15
A reason to smile on April 15.
There can’t be many days that are less popular than April 15. But I want to remind you of a fact that might ease the pain: The income taxes you’re paying will save lives in poor countries.
If your family makes the U.S. median household income of roughly $51,000, together you will buy someone in a poor country about seven months’ worth of HIV treatment. Or provide a lifesaving vaccine for 48 children. Or buy eight bednets that will protect people from mosquitoes that cause malaria.
These numbers might make you wonder if a large portion of your income taxes goes to foreign aid. After all, seven months of AIDS treatment can’t be cheap. You wouldn’t be alone in wondering this: Polls show that Americans tend to think nearly a quarter of the budget goes to aid.
It turns out that foreign aid is just 1 percent of the federal budget, or about $30 billion a year. Another way to think about it is that just 1 percent of your income taxes goes to foreign aid.
Compare that to other items in the budget. Defense for example is 17 percent, or more than $1,500 out of the median household’s income tax bill.
I believe that if more people knew what a small share of the budget goes to these programs, and how effective these programs are at saving lives, they’d want to do even more.
April 15 will never be anyone’s idea of a fun day, but I hope it helps to remember how much good American aid is doing around the world.
Meeting Problems with Solutions
Getting better all the time
Halfway through the first day of my India trip, TV personality Prannoy Roy told a story I think really highlights the progress of India’s long journey to better health.
Halfway through the first day of my India trip, TV personality Prannoy Roy told a story I think really highlights the progress of India’s long journey to better health.
We were filming a question-and-answer segment in front of a studio audience for his show on New Delhi Television, one of India’s largest news networks.Prannoy was asking me and Bollywood star Aamir Khan about philanthropy, health, and India’s development when he recounted a discussion he had about 20 years ago. A former prime minister asked him and a group of other people what India could do to be a better country. Prannoy said his answer – provide better toilets for women – was met with nothing but laughter.
Things have really changed. Just before seeing Prannoy, I had spent several hours in meetings with Indian parliamentarians and ministers. Our wide-ranging conversations about health and vaccines almost always returned to how to stop the spread of diseases through better sanitation and, specifically, toilets.
I was glad: the toilet is one of my favorite topics. At each meeting I got to talk about how flush toilets (ones that use water to clear the waste away through plumbing) won’t make it anytime soon to much of the world, including rural India where infrastructure is poor and water is scarce. Instead, we need to invent a better toilet, one that doesn’t use water yet eliminates harmful microbes and gets rid of any smell. Last year our foundation sponsored a “re-invent the toilet” fair where 14 universities submitted innovative answers to that problem. None were perfect but they all were a step in the right direction.
After several meetings it was clear there was strong interest in holding a similar “re-inventing the toilet” event in India early next year. We set some follow-up meetings to start figuring out how to make it happen. We agreed that applying India’s many creative minds to the sanitation problem could speed the path to a breakthrough.
In my post, “Why I’m Going to India,” I wrote that the country is an ideal place for understanding both the problems and the solutions in areas that our foundation focuses on. In my meetings yesterday, the sanitation discussions were just one example of the great optimism I felt from government leaders and health experts for overcoming the problems. I also heard about several new solutions.
A group of polio experts updated me on how India’s focus on ridding itself of that disease is paying dividends to broader health efforts. After a lot of hard work, India has been polio free since January 2011. India will be certified polio-free if there isn’t another case by next January. I’m confident we can get there. Yesterday the experts walked me through how they are using satellite mapping to not only see where they need to provide the polio vaccine but also to expand the country’s system of routine vaccinations (the vaccines children get in their early years). With satellites and cellphones we are getting far more detailed health data on hard-to-reach places. I’m convinced those tools, pioneered with polio, will be a game changer for expanding routine vaccination.
I also sat down with some of India’s top scientists, public health experts and pediatricians. This group was celebrating amazing progress of the phase 3 trial of Rotavac, India’s first home-grown vaccine for rotavirus, the world’s main cause of diarrheal disease—which, after pneumonia, is the second leading killer of children under age five. I touched on rotavirus in yesterday’s post but it’s worth emphasizing again. The work the group did to create the vaccine, and run a very high quality trial is nothing short of phenomenal. Rotavac is a rare global collaboration among the Indian government, vaccine manufacturer Bharat Biotech, and others including PATH, the U.S. Centers for Disease Control and Prevention and the National Institutes of Health. Our foundation provided grants to support the work.The next milestone is to get the vaccine licensed by Indian authorities.
Dr. M.K. “Raj” Bhan, former secretary of India’s Department of Biotechnology and a pediatrician who shepherded the vaccine’s creation, told me that he expects the vaccine to clear India’s regulators by the end of the year, an estimate the country’s minister of health echoed later in the day. That means that India could start introducing the vaccine next year and start saving tens of thousands of kids’ lives a year.
In answering the prime minister two decades ago, Prannoy, our TV interviewer, pointed to a health problem that India still hasn’t fixed. Yet things are absolutely getting better. Since that time, India’s child mortality has dropped 45%, better than 35% for the world as a whole. With every visit to the country I see how India will drop that further as it gradually solves its health issues. An official I met at India’s Planning Commission yesterday described how India is “slow and deliberate” and ultimately successful in working through challenges. “That’s what this country is all about: finding a way,” she told me.
Today I’ll see another example of how India is finding a way when I visit a research center using old and new technologies to help boost agriculture productivity andfight malnutrition.
Closing in on 1%
Turning the Corner on Polio in 2012
The Global Polio Eradication Initiative is making important changes.
Working to support the effort to rid the world of polio has taken me to some exotic places. But earlier this month, it took me to Washington, DC (I suppose you could argue this is also quite an unusual spot) to talk with policy makers about the historic opportunity we have to end polio forever.
My conversations with lawmakers gave me a chance to discuss some of the doubts people have expressed about whether we can really do this. But it also provided the opportunity to bring lawmakers up-to-speed on the results of important changes in the Global Polio Eradication Initiative’s (GPEI) approach—including cool new technology being used and the increased engagement on the part of governments in the countries where polio transmission continues.
In my opinion, the changes and progress in 2012 have made for the most convincing case yet that ending polio is possible—and is one of the most concrete accomplishments possible for global health.
For more than 10 years, we have been 99 percent of the way toward ridding the world of polio. Since then, every few years the global community would vow that year would be the year when polio transmission would stop.
However, 2012 is notably different from the earlier stagnation in progress. And while the global program hasn’t stopped transmission of the wild polio virus everywhere as some had predicted, it did close a big gap in that last one percent when India became polio-free early in the year after a long and hard battle to protect more than 172 million children under the age of five from polio. This was incredible tough terrain in which to run thousands, if not tens of thousands of vaccination campaigns. So, the lessons learned from India’s success are serving as a great guide for what’s needed in the remaining three countries where polio transmission persists—Nigeria, Pakistan and Afghanistan.
There’s no doubt that these countries aren’t easy places to get rid of the disease. There are a number of factors that need to be in place including improved campaign quality, meeting the program’s global funding needs, and anticipating political challenges.
I heard from U.S. lawmakers that the news regularly coming out of Afghanistan and Pakistan has led to reasonable concerns about the role insecurity plays in being able to reach children with vaccines. But in the last 11 months, incredible efforts are being made in these two countries by government officials, religious and community leaders and non-government organizations to negotiate access to children in hard-to-reach places.
And those efforts are paying off.
The polio program has been partnering with a number of NGOs to conduct negotiations to secure access to children, leading to breakthroughs in the past few months. In Afghanistan, the average number of inaccessible children in thirteen of the highest risk districts of the country has been reduced by more than half, from nine percent in June 2012 to 3.4 percent this November. And in the Terah Valley in Pakistan, where children hadn’t received vaccines in three years, approximately 30,000 children were reached with the polio and other critical vaccines during a vaccination campaign earlier this fall.
On the other front, in Nigeria, while cases have actually gone up this year, there is a full-scale effort to revamp the program, with many changes based on what vaccinators in India implemented to great success. Included in these changes are decreases in the size of vaccination teams and the addition of female vaccinators, tracking of nomadic populations, rigorous microplanning and scaling up of additional staff to help with all of these activities.
Another major innovation that is leading to early reports of impressive progress is the work on GIS mapping and GPS tracking to improve polio campaign planning and performance. (It’s a really ingenious use of the technology that you can learn more about here.) GPEI’s focus on using the polio program to increase routine immunization is ensuring that the polio program has an even broader long-term impact on the population.
The Independent Monitoring Board of the GPEI also notes the positive changes in a report released last week and their conclusion that the GPEI “has never been in a stronger position” reflects what I’m seeing too. Their assessment about what comes next for the history books is telling: “The time is momentous for public health history. A final concerted effort could indeed mean writing the story of polio’s last stand.”
I couldn’t agree more.
Photos from My Trip
Snapshots of UN Week
Photos from my week in NY at the UN session on eradicating polio.
While in New York, Sandro Rosell and I recorded a short video together talking about the foundation’s partnership with FC Barcelona to work toward saving children’s lives around the world.

Sandro Rosell (L), the President of FC Barcelona and the FC Barcelona Foundation and Ramon Pont (R), the Vice President and Director of FC Barcelona have been tremendous partners in using their club and its worldwide fan base to raise awareness of polio with their “More than a Goal” campaign.

Dr. Ahmad Mohamed Ali, President of the Islamic Development Bank, and I signed a Memorandum of Understanding between the foundation and the IsDB. Their financial support will make a big difference. But in addition, the support and commitment of so prominent an Islamic institution will be of great help to our efforts in places like Afghanistan and Pakistan.

I enjoyed dinner with senior leadership from the Islamic Development Bank and learned a lot while in New York.

I started Day Two in New York with an early meeting with President Karzai of Afghanistan. His country is one of the last three where polio remains at large. He’s truly on board for doing everything he can to work on polio. Afghanistan presents daunting challenges – but it’s encouraging to see his support and leadership.

The main reason for my trip to New York was to attend a meeting hosted by Ban Ki-moon, the Secretary-General of the United Nations. At the meeting, heads of state from Afghanistan, Nigeria and Pakistan stood alongside donor government officials and new donors from the public and private sector to outline what we need to do to stamp out polio. It was a remarkable display of solidarity, energy and commitment. It was an honor to be there.

Not Flush with Cash
Simple, affordable sanitation innovation in Durban
I met with sanitation experts in Durban who have developed a safer and inexpensive alternative to the pit toilets used by many poorer families around the world.
In 2009, during a foundation trip to South Africa, I met with Neal Macleod, head of Durban Water and Sanitation. Neal is a health expert working to improve sanitation so people no longer have to use pit toilets such as the one in the photo.

The typical developing world toilet is just a pit. You dig a hole in the ground, you put up a shack around it, and in some cases you put some kind of seat in there. There may or may not be water or toilet paper. It’s pretty unattractive, particularly the smell.
Neal showed me an improved toilet model called a Ventilated Improved Pit latrine or V.I.P. The Ventilated Improved Pit latrine is set up so that air flows down through the toilet, down into the pit and up through a pipe which dramatically reduces the smell problem. And by putting the right mesh wiring on the top of the pipe, flies can’t get in.
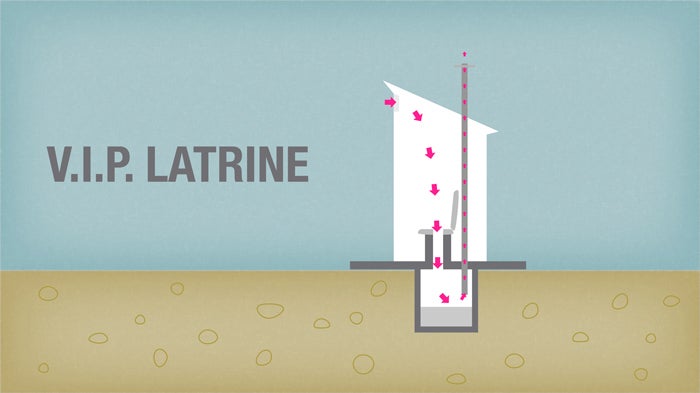
One challenge is that you’ve got to empty the pit. In preparation for emptying a pit latrine, large plastic containers are lined up behind the toilet.

The workers have to wear gloves and protective masks to empty the latrines.

Workers pump out waste from a pit latrine. They would remove the liquid waste by using a hand pump.

Workers empty the waste from a pit latrine into large plastic containers. Each pit would yield 25-60 of these huge buckets full of waste.

Treatment is Working
Why I’m Committed to Turning the Tide on AIDS
A decade ago, almost no one in Africa was receiving drugs to treat HIV. AIDS was a death sentence. Now more than 8 million people in developing countries, the majority of them in Africa, have access to life-saving treatment.
Florence Daka is a healthy mother of four who lives in Lusaka, Zambia. She sees her children off to school every morning and works a full day cleaning offices.
That may not sound extraordinary, but it is. It’s extraordinary because Florence is alive and well and living with HIV, thanks to the effective treatment that she takes. What’s more, the medicines that Florence received during her last pregnancy helped her avoid transmitting HIV to her youngest son, Stephen, who is now a healthy two-year-old.
When I met Florence during a visit to Zambia earlier this year, I was struck by her story and how she and Stephen are living proof of the tremendous progress that we’ve made in the fight against AIDS.
A decade ago, almost no one in Africa was receiving drugs to treat HIV. AIDS was a death sentence. Now more than 8 million people in developing countries, the majority of them in Africa, have access to life-saving treatment. The cost of HIV drugs in Africa has plummeted by more than 99%, and most pregnant African women who are infected with HIV now have access to treatment to prevent mother-to-child transmission of the virus.
It’s important to celebrate this tremendous progress—progress that seemed unimaginable just a decade ago – and to stay committed to the fight against HIV. That’s why I joined government leaders, philanthropists, faith leaders, entrepreneurs and entertainers at the Kennedy Center’s Eisenhower Theatre last night to recognize what the world has achieved in turning the tide on AIDS.
This week, the International AIDS Conference will be held in the United States for the first time in more than 20 years. And last night’s Kennedy Center event – with 1,000 global health advocates in attendance—offered a great stage to share success stories and talk about the importance of sustained HIV funding.
I talked about the strong leadership that the President’s Emergency Plan for AIDS Relief (PEPFAR); the Global Fund to Fight AIDS, Tuberculosis and Malaria; and developing country governments have taken to expand access to treatment and prevention.
I also thanked public and private sector leaders in the U.S. for maintaining America’s long-standing commitment to HIV research and development (R&D). Our country still provides 70 percent of all funding for HIV R&D, including efforts to develop more effective and longer-lasting prevention methods and an HIV vaccine. Americans can be justifiably proud of the tremendous moral leadership that the U.S. has taken in producing breakthrough innovations in the fight against HIV.
But America isn’t in this effort alone. I’ve been honored to meet people around the world who are committed to funding and leading critical R&D activities. And I have told them that the Bill & Melinda Gates Foundation is committed to working with partners everywhere to accelerate the discovery and development of new tools to treat and prevent HIV.
Tomorrow, I will be part of a panel at the International AIDS Conference that will discuss what’s needed to sustain progress against HIV in tough economic times. I look forward to sharing my ideas in a follow-up post.
A Tough Challenge
In Pakistan, Victory Against Polio is in the Hands of Local Officials
Pakistani leaders are working hard to support polio activities.
I met recently with a group of Pakistani national and provincial leaders waging war against polio in a handful of areas where the dreaded disease still exists.
Over the last 25 years, 122 countries where polio was once endemic have eliminated the disease. Just three countries remain: Pakistan, Afghanistan, and Nigeria. Reducing polio infections by more than 99 percent over the last quarter-century could not have been achieved without a sustained commitment from all countries to mount this successful global public health effort. But the hard work of reaching thousands of vulnerable children is largely a challenge that falls to local officials.
In Pakistan, eradicating polio is an especially unique challenge—although I’m optimistic, Pakistan will continue to make progress. A recent report by the Independent Monitoring Board affirms this optimism.
Last year, Pakistan had more polio cases than any other country. But since the beginning of this year, overall, polio cases in Pakistan have dropped by 67%, from 69 cases in 27 districts at this time last year, to 23 cases in 13 districts since the beginning of 2012.
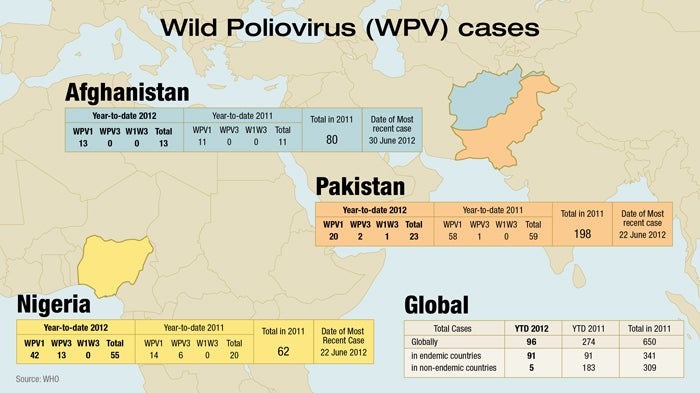
It recently devolved its national health ministry, which means provincial and local officials have to work extra hard to coordinate polio and immunization activities. There are areas such as the semi-autonomous tribal region in northwest Pakistan where conflict and insecurity prevent vaccination activities. Much has recently been written about new challenges that have arisen, including an alleged ban on immunizations by some local leaders in North and South Waziristan, Federally Administered Tribal Areas (FATA). While this further complicates running immunization campaigns in an already-challenging environment, efforts are being undertaken to address the situation. It also is important to note that this affects not even 1% of the country’s target population. However, there are still some areas where the management of local polio campaigns needs to improve. Pakistan is effectively tackling these challenges with new approaches and adopting lessons learned from India.
In the U.S. and other developed countries, we take the administration of vaccines for granted. Young children get immunized when they visit the doctor. But in Pakistan, heroic health workers often have to surmount obstacles, and even risk their lives to reach children who are unprotected. Vaccine teams are enlisting the support of religious leaders to help counter misperceptions about immunizations and suspicions that they are part of a plot. They also are adopting proven methods to reach children in migrant communities where vaccinator teams that speak the local dialect have been recruited to reach local populations and give them more confidence in their efforts. And where it’s encountered political instability and insurgency, the polio program has tried to coordinate with the Pakistani military to get access for vaccinator teams and to try to ensure their safety.
As of last month, there were 16 cases of polio reported in Pakistan.
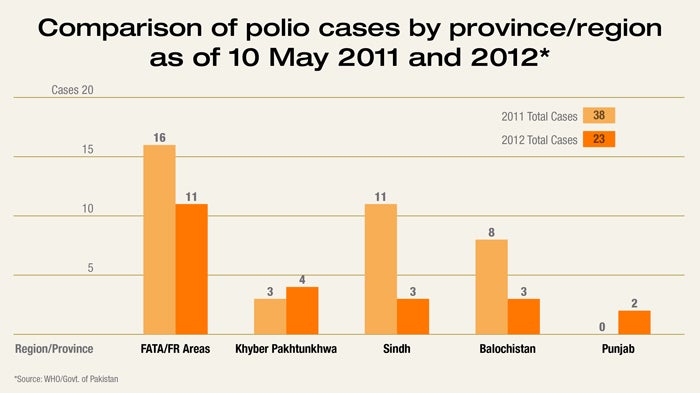
That doesn’t sound like a large number, and the progress that it demonstrates is worth acknowledging.
But polio is a cunning disease. Ninety-nine percent of the people who carry the virus don’t show any visible effects, so it’s hard to know who has it and where it’s traveling until a reported case shows up. In a country with a population of 175 million people, you can imagine how difficult this is.
But India has proven that it can be done in a country with a population of 1.1 billion. Earlier this year, it was removed from the list of polio endemic countries after going a full year without a new case of wild poliovirus. India’s success proves that polio can be defeated in the most challenging circumstances.
It was clear in my meeting with the Pakistani provincial leaders and several national officials who joined them that there’s a strong resolve to finish the job. They were very open about where efforts have fallen short. And the fact that the Pakistanis were willing to travel to India to meet with Indian health officials after their meeting with me really underscored their commitment.
India and Pakistan don’t always see eye-to-eye on things, so seeing the Pakistanis and the Indians sharing what is working and some of their common problems in solving polio was very encouraging. Their meeting was also a chance for India to help their neighbor, and a reminder that they need to stay vigilant in their own country.
Failing to completely eradicate polio would create a very real risk for the rest of the world - a resurgence that could affect tens of thousands of children worldwide getting infected. On the other hand, eradicating polio will result in benefits of up to $50 billion by 2035 in the world’s poorest countries. Our investment in polio eradication is also laying the foundation for delivery of other cost-effective health services—including vaccines for other preventable diseases.
Despite current challenges, my meeting with the Pakistanis and action taken on polio and vaccines by the World Health Assembly reinforce my confidence that we truly are on the verge of ending polio. India has proven that a strong commitment by political and community leaders, well-managed and high-quality vaccination programs tailor-made to local circumstances, and adequate financial resources can get the job done.
When it comes to polio, the Pakistanis and the Indians want the same thing we all do—a world in which no child ever gets this preventable disease again. But the responsibility to end this disease doesn’t just lie with the countries where polio transmission continues, we all have a responsibility to ensure a polio-free world.
Meeting the People
The Urban Health Initiative in India
The Urban Health Initiative helps women in slums get contraception.
I always look forward to visiting India for the opportunity to meet people who are benefiting from projects we’re supporting in key health areas, like family planning, polio eradication, and HIV/AIDS.
On my recent trip, I spoke with several women in one of Lucknow’s urban slums who told me how grateful they are to have a choice of contraceptives. That hasn’t always been the case and there are still many poor women who don’t know about or have access to contraceptives. Efforts like the foundation-supported Urban Health Initiative are designed to change that by educating more women about contraceptive choices and practices like spacing births further apart.
This is a top health priority for the foundation because it directly affects the health (and often the survival) of poor women and their babies. And it offers them something that all mothers desire and deserve—the opportunity to provide their children with a high-quality education and the best chance of success growing up.
Wash Your Hands
Can a simple, safe childbirth checklist save lives in developing countries?
I had the privilege recently of meeting Atul Gawande, a brilliant physician who’s using an amazingly simple concept—checklists for medical practitioners—to save lives and reduce health care costs. With support from our foundation, Gawande is investigating whether a safe childbirth checklist can increase the survival rate of mothers and newborns during childbirth in India and other developing countries.

It’s a well-known fact that hand washing and sterile instruments prevent the transmission of germs during medical procedures. Yet, many doctors and nurses frequently don’t follow these basic protocols.
It’s an especially big problem in developing countries—where many hospitals and clinics lack a basic standard of care.

Dr. Atul Gawande, a high-regarded U.S. surgeon and researcher, may have found the solution: a 1-page checklist that helps health workers avoid the major causes of maternal, newborn, and intrapartum (stillborn) deaths. Although it seems like a simple and obvious approach, no one has ever created a safe childbirth checklist. And until Gawande showed a few years ago that a simple checklist could save lives and avoid complications during surgery, there was no common checklist for that either. His work on developing and implementing checklists has had a dramatic impact on health care in the U.S. and around the world. Could we extend that insight to the developing world for childbirth?
I was a bit skeptical when I first heard about the power of a simple checklist. It sounded almost too good to be true. But Gawande’s research team tested the checklist idea with 8,000 patients undergoing surgery in eight cities around the world. On average, the checklist resulted in a 47% reduction in deaths and a 35% reduction in other complications.

At a time when most things about healthcare are getting more complex and costly, Gawande’s checklist is simplifying healthcare and saving money and lives. And the great thing is that it’s proving to be scalable without adding additional expense—a rare achievement in healthcare. So far, 4,000 hospitals worldwide are using the checklist approach to reduce errors during surgery.
In India, the safe childbirth checklist that Gawande’s research team developed in consultation with the World Health Organization is showing promising results. At the start of a pilot study at one childbirth center, health workers used only about one-third of the practices on the checklist—things like washing their hands before a vaginal exam, using a sterile blade to cut the umbilical cord, and introducing breastfeeding within an hour of birth. After the checklist was introduced—and with the coaching and guidance of the hospital administrator—compliance with best practices checklist shot up to 86%.
Our foundation is now funding a more extensive trial to see if the checklist can be scaled effectively to increase maternal and newborn survival in 120 hospitals in the Indian state of Uttar Pradesh. We focused on Uttar Pradesh because it is one of the poorest states in India. The mortality rate there for women giving birth is more than twice the rate elsewhere in India and over 30 times greater than in the U.S. So the potential impact in terms of saving lives is huge. And if the results are as positive as we hope, the childbirth checklist could be introduced in other developing countries.

One of the things that excites me about the checklist approach is that it focuses on improving health care by empowering the people working in local hospitals and clinics. And it doesn’t cost a lot of money. Getting the checklist right is critical, and not as easy as you might think. But once that’s done, Gawande’s approach is to train a handful of doctors or administrators and encourages them to coach their colleagues. We know that this kind of peer-to-peer coaching works well in other professions, such as teaching.
I first came across Gawande when I read one of his articles in The New Yorker, where he’s a staff writer (in addition to being a practicing surgeon, associate professor at Harvard, researcher, and book author). Gawande writes about his profession—and about his own experiences as a doctor—with an honesty and authenticity that is both refreshing and eye-opening.
I had the opportunity to meet him recently and he’s an impressive guy—one of a handful of people who’s really thinking creatively about how to improve the quality of health care and get costs under control. I’m optimistic there are other simple solutions that can similarly increase the quality of health care and lower costs at the same time. And if we can show their effectiveness in health care, we may discover they can be applied in other fields—such as education—where we also need to improve quality and make the most of limited resources.
Reaching High-Risk Groups
Avahan: Winning Against HIV/AIDS in India
One reason I was very excited to be visiting India recently was to get a chance to check on our foundation’s efforts to support the work of the government of India to halt the spread of HIV/AIDS. India is making good progress and learning lessons that could be helpful in other countries.
In 2003, we worked with Indian partners to launch a project called Avahan, which means “call to action” in Sanskrit, an ancient language of India. The project is a partnership with many Indian NGOs, state and local governments and the national government, which has increased funding for HIV/AIDS and established a national strategic plan that includes community-led HIV prevention.
Avahan’s efforts have been focused on reaching high-risk groups in six states of southern India, where the virus is most prevalent, and elsewhere along the nation’s major trucking routes, long-haul truckers being among those at high risk. Others we’re trying to reach include sex workers, their clients and partners, men who have sex with male partners, and injection drug users.
About 2.7 million people in India are infected with HIV, but that number is far below the dire forecasts that some experts predicted for India a decade ago. Avahan and India’s other efforts have contributed to a 50-percent reduction in HIV/AIDS incidence in the past six years, saving $100 million USD in averted health costs and, more importantly, saving many lives. One estimate puts the number of infections averted in the six states at more than 100,000.
Avahan is engaged in communities and at the street level, helping local groups deploy peer-to-peer counselors, distribute condoms and provide HIV testing, treatment and care. A big part of the effort is aimed at reducing the stigma that often prevents people from seeking HIV prevention and treatment services.
India has taken ownership of its national response to HIV/AIDS and is transitioning the Avahan program to state governments, facilitated by India’s National AIDS Control Programme. During my recent trip to India I was pleased to congratulate in person a number of the leaders who has been involved in transitioning Avahan and sustaining India’s HIV/AIDS prevention efforts.
In Bangalore, I got to spend time at a community center that’s part of Avahan. The center, known as Swathi’s Women's Group, was set up by sex workers to help prevent the spread of AIDS in their community. It’s been quite successful at that, and now it does lots more, like running a micro-finance bank and helping members defend their rights. It’s a great self-help success story.
The India program stands out as one of the best examples of effective national scale up of HIV prevention efforts, but those efforts will need sustained funding and government leadership. We’re hoping that what we learn in India will encourage and guide increased prevention efforts in other parts of the world.
In Bangalore
India: day three
My third day in India started with a visit to a community center that’s doing great work helping reduce HIV and providing support to sex workers. The day concluded with a meeting with a number of business leaders and philanthropists to talk about giving.
I started my last day in India at a Bangalore community center called Swathi’s House—a drop-in center for sex workers that’s part of a foundation-supported HIV prevention project called Avahan. The community members gave me a traditional Indian welcome, called an aarti. It was a day to celebrate, because the program is being handed off to the government for long-term support. But the real driver of success are the members themselves.
The center is run by a remarkable community-based organization called Swathi Mahila Sangha, which has approximately 8,500 members out of a population of about 19,000 sex workers in Bangalore. They provide counseling, medical help, HIV prevention training and a micro-finance bank. All of this is done with a cadre of peer educators and outreach workers. It’s a great model for self-help and empowerment.
I was touched by the community’s honesty and resolve—and their entrepreneurial spirit. Roughly half of the members now have savings accounts and their micro-finance bank has $800,000 USD in assets, with a recovery rate of nearly 100%. (I think most U.S. banks would be envious.) Thanks, in part, to their efforts, rates of HIV and sexually-transmitted diseases are down and the woman I talked with spoke of no longer feeling alone and helpless. They were proud of being able to keep their money, instead of remaining victims to “the thugs and the goons.”
Even though they are still a marginalized group, the sex workers are succeeding in advocating for their own rights and are enthusiastic about getting even more sex workers signed up and involved. There’s also been tremendous progress at the government level tackling the problem of HIV infection head-on, and Avahan and community centers like Swathi House are great examples.
I spent the last part of my trip at a gathering of a number of business leaders and philanthropists. I was the guest of two remarkable individuals. Azim Premji is the founder of Wipro and one of Asia’s biggest philanthropists. Ratan Tata is one of the country’s foremost business leaders and a member of the Tata family well known throughout Indian industry and philanthropy. They were nice enough to invite me to make a few remarks at the beginning, but mostly it was an opportunity to listen and learn about their perspectives on philanthropy in India.
While the circumstances for giving are unique in India, it was amazing just how much their discussion sounded like the conversations I’ve had with wealthy business people and philanthropists in the U.S. and elsewhere. A few common themes emerged. People agreed it was often easier to make the money than to give it away in a thoughtful way. There was a huge feeling of personal satisfaction in their philanthropic work, and a deep sense of societal obligation to give back. With so many problems to address, deciding where to engage and how to do it weighs heavily on their minds.
The group decided they wanted to get together again to learn from one another and talk through issues of common interest. That was fantastic. India is in a new phase of its long history of charitable giving, and I am certain many of these families are going to lead the way by doing remarkable things.
It’s been a very productive and moving three days. I’m grateful I had the chance to meet with so many amazing people in a short time. I’ll post some thoughts on the trip as a whole as well as some video the week of June 11. There’s a lot to reflect on.
Modeling Progress
Ethiopia: exciting innovations in agriculture and health
In Ethiopia, I saw advancements in farming and health services.
Ethiopia is one of the poorest countries in the world and has faced enormous challenges feeding its people and providing critical health services to mothers and their children. Yet, I returned from a recent visit excited about advances the country is making in agriculture and health.
If these innovations—which are a top priority for our foundation—succeed, they can be replicated in other African countries that also face big challenges in health and agriculture.
One factor in Ethiopia’s progress is Prime Minister Meles Zenawi and his leadership team, who have played a key role in reinventing the country’s agricultural and health systems. Making changes to either would be a big challenge in any country, so it’s even more impressive in Ethiopia, which has the second largest population of any country in Africa but a limited economic infrastructure.
Around 85 percent of the country’s population survives by growing crops on small plots of less than five acres. But frequent droughts and soils that have been depleted of nutrients often led to low crop yields and considerable food insecurity. More than half of the country’s population of 83 million is malnourished and more than 5 million households receive food aid each year.
Our foundation has been working with the Ministry of Agriculture, the county’s new Agricultural Transformation Agency, and other partners to help farmers plant higher-yielding, drought-tolerant seeds, improve soil health and fertility, and get higher prices for their crops by selling to global markets.
At the Melkassa Research Station, one of 13 government-run agricultural outposts, Dr. Markus Walsh, Sr. showed me a new, state-of-the-art technology called NIR spectroscopy that’s part of a digital revolution in agriculture. This portable device, which quickly and cheaply analyzes soil conditions, is a fantastic breakthrough that will help farmers everywhere. But it’s especially valuable in countries like Ethiopia, where farmers haven’t been able to afford laboratory tests but need to know how to amend soils to grow better crops. The spectroscopy is part of an even bigger agricultural digital information system that will provide a comprehensive and detailed map of soil properties across the country.
I also met with a number of farmers to talk about new varieties of sorghum (a grain) and beans they are growing. Beans are very important because they provide protein and people need a combination of protein and grain to have a reasonable diet.
Helping small farmers sell their crops in world markets is another important part of the work we’re supporting in Ethiopia. It’s currently a big challenge because poor farmers may not be growing the right crops for world markets and they often lack the roads, trucks, and other infrastructure necessary to enable exports. And getting foreign investors to help build this “value chain” can be difficult. But I visited one agricultural processing facility called ACOS, that is processing and shipping a variety of beans to European markets. It is jointly owned by an Italian company and Ethiopian investors and is a great example of private investment in developing countries.
What Ethiopia is doing in health is really a model system because it reaches everyone in the country. I visited the Germana Gale Health Post, where I talked to several of the more than 30,000 health extension workers who have been trained in recent years to deliver basic health education, prevention, and treatment. Most of the health workers are women, and those I met were energetic and well-trained.
These kinds of primary health services—giving vaccines, educating women about family health, and promoting hygiene and environmental sanitation—is the foundation for building good health systems in poor countries. Ethiopia’s health system also includes district health centers like the Dalocha Health Center I visited. There, they do a little bit of surgery and have more expertise and a wider variety of drugs. There are also primary hospitals that focus on higher level treatment and some emergency surgery, and general hospitals that deal with serious emergencies and high-risk and specialized care.
Ethiopia still faces some big problems. But the people I met and what I saw re-energized me and increased my optimism that the big investments we and other donors are making in health and agriculture will pay off for the people of Ethiopia and can serve as model activities in other African countries. Improving agricultural productivity and the quality of life through better health services is the key to unleashing the potential of Ethiopia and other poor countries and getting them on the road to self-sufficiency.
The People I Met
Photos from my trip to Ethiopia and Zambia
On my recent trip to Ethiopia and Zambia, I met with health workers, families, and farmers, and learned about the progress they are making in meeting healthcare and agricultural challenges.
On my recent trip to Ethiopia and Zambia, I met with health workers, families, and farmers, and learned about the progress they are making in meeting healthcare and agricultural challenges.
I visited the Germana Gale Health Post Site in Silte, Ethiopia, to meet with health extension workers and learn about the critical health issues they see, such as maternal and neonatal health risks, malaria, and pneumonia.
This health post offers several services, and also provides training to residents and community leaders to help spread information and educate the community at large about health issues and available treatments.
The health worker at this post is very active and experienced, providing family health services, and distributing supplies such as bed nets for malaria prevention.
This year, she has seen more than 200 children, most ages 2 weeks and older. On a tour of the delivery room, she explained that she is usually called to homes by family members for births.
She provides family planning services and counseling to new mothers, focusing on the importance of breastfeeding for the babies' health.
A large number of "family folders", individual family medical records, are kept at the health post. There are also many wall charts showing dates and numbers of services.
Each wall chart indicates annual and quarterly targets for each service (immunization, deliveries, preventive treatments).
I asked how closely they were meeting their targets, and learned how they captured the data.
The storage for vaccines includes a broken kerosene refrigerator and a cold box. The refrigerator broke after two years and has not been fixed.
Vaccine is delivered in a small cold box from the health center on the days they provide services.
An immunization clinic was being held on the porch of a side building, where a group of women were receiving tetanus vaccines and children were receiving Penta, polio, measles and PCV.
While most services are given at the health center, the health worker has two outreaches per month, the furthest being a three-hour walk away.
The clinic had a coffee ceremony for me, roasting the beans on the spot.
Coffee was served with popcorn.
I visited a household with a two week-old baby. The home was fairly large, with a fenced-off area for animals. The family has two other children – a 3 year-old and a 6 year-old.
The baby and the older children were all born at home with the help of the health worker, who taught their mother to begin breastfeeding immediately to help boost the baby's immune system with colostrum.
I visited the Melkassa Research Station in Nazaret, Ethiopia, one of 13 stations in the Ethiopian Institute of Agriculture Research that supports technology development for sorghum, maize, common bean and horticulture crops (onion, tomato, fruits).
Farmers are facing challenges in seed production with the current irrigation capacity. To address this, experimental hybrids are being formed under the Drought Tolerant Maize for Africa project.
In the last eight years, the agriculture sector in Ethiopia has been growing at the rate of 10 percent per year. The country also has a comprehensive food security program for drought-prone areas.
Currently, most farmers rely on seed they have saved themselves, which is subject to drought and losses caused by birds. Seed companies can produce hybrid seed, providing the best option increasing production of sorghum.
Workers sort and clean seed at a seed-processing facility.
At the legume seed storage facility, I saw the different market classes of beans (white pea, red kidney, small red, sugar, large kidney beans) as well as chickpea (desi and kabuli), and mungbean.
I visited the cold storage, which plays a critical role in preserving seed viability for legumes. They lose viability faster than cereals because of their high protein content.
Male circumcision can significantly reduce HIV transmission. At the Shang Ring Male Circumcision clinic, they are conducting a trial program where circumcision can be performed at a cost as low as $2 per device.
The Coptic Mission Hospital and Clinic in Lusaka, Zambia, has been a high-quality provider of HIV services.
I met Florence Daka, a cleaner at the hospital, who tested positive for HIV in 2008 and was successfully treated with an antiretroviral (ARV) drug. In 2010, Florence was able to conceive, and safely deliver an HIV-negative child, Stephen.
Some Pictures
Photos from my recent trip to Ethiopia and Zambia
On my recent trip to Africa, I met with many people and heard their interesting, inspiring stories about how aid works. This gallery has stories and photos from the trip.
On my recent trip to Africa, I met with many people and heard their interesting, inspiring stories about how aid works. This gallery is a preview of some of the stories and photos I'll share during a Livestream on April 4th.
In Silte, Ethiopia, we visited one of the nation’s many new “health posts” set up to improve public health, village by village. The staff members here are saving lives with their incredible work.

Bed nets are still one of our best tools against malaria. While in Zambia, we met with local health care officials to talk about their battle against the disease.

Africa is making significant progress toward the Millennium Development Goals of improving maternal and child health.

AIDS/HIV has taken a huge toll in Africa, but more people are getting the life-saving treatments they need, while education and outreach efforts are curbing the rate of new infections.

African farmers of cowpeas (also known as black-eyes peas) are benefitting from an inexpensive solution to weevil infestations that used to ravage their crops after harvest. Scientists from Purdue University developed airtight bags to protect cowpeas.

Now, farmers can store cowpeas for sale when prices are strong. That’s expected to raise farmers’ annual incomes by an average of $150 in West and Central Africa, where most live on about $2 per day.

A Good Effort
A report card on helping the world’s poor
I believe the global community deserves a solid B for progress meeting the UN’s Millennium Development Goals.
People sometimes say that the United Nations doesn’t do enough to solve the big problems of the world. I’ve never really agreed with that point of view, but if anyone is looking for evidence of the UN’s impact, a good place to start is the Millennium Development Goals (MDGs).
The MDGs are an ambitious set of goals for reducing poverty and child mortality rates, and fighting diseases that sap the socioeconomic potential of poor countries. They were agreed to in 2000 by all 193 UN member countries and 23 international organizations. Creating that kind of consensus is—by itself—a significant achievement.
The great thing about the MDGs is that they provide clear targets and indicators of progress in key areas, including ending poverty and hunger, ensuring universal education, gender equality, improving child and maternal health, combatting HIV/AIDS, environmental sustainability, and strengthening global development.
Although a number of countries won’t be able to achieve all of the goals by the target date of 2015, the MDGs have been helpful in getting everyone to really think about their part, the progress they’re making, and what they can learn from others. The goals have focused political attention in developing countries, encouraged UN groups to work together, and inspired wealthy and fast-growing donor countries to coordinate their efforts.
In February, the World Bank announced that the MDG goal of cutting extreme poverty by half had been achieved five years early. A week later, UNICEF and the World Health Organization announced that the goal of halving the number of people without access to safer drinking water was also reached five years early. These are noteworthy achievements though much work remains to be done. Other goals, such as reducing maternal mortality by three-quarters, simply won't be achievable by 2015, although the progress has been really good.
Already, people are talking about what the goals should be for 2030. That’s a great thing because there’s still a lot more work to do, especially in reducing diseases and maternal and childhood deaths. But I believe the global community deserves a solid B for its efforts so far and where there is progress, we should celebrate.
One of the things I’ve learned in my work at Microsoft and the foundation is that setting clear goals and honestly evaluating progress is critical when trying to tackle big challenges. The MDGs provide a report card on the progress the world is making to take care of those most in need.
Goal 1: Eradicate Extreme Poverty and Hunger
Goal 2: Achieve Universal Primary Education
Goal 3: Promote Gender Equality and Empower Women
Goal 4: Reduce Child Mortality
Goal 5: Improve Maternal Health
Goal 6: Combat HIV/AIDS, Malaria and Other Diseases
Goal 7: Ensure Environmental Sustainability
Goal 8: Develop a Global Partnership for Development
Beans
On my way to Africa
On my trip to Africa, I'm thinking about malaria, public health systems, farm productivity, and beans. Yes, beans.
This week I’m in Africa, a place I go a couple of times a year to see our foundation’s work in the field. The reason I go on these trips is to see for myself what’s happening and I come away with success stories, notes on things that we need to get smarter about, and a better understanding overall. This time I’m visiting Ethiopia and Zambia, which should be very interesting.
Eliminating malaria in Zambia
I’ll be looking at malaria intervention in Zambia, because that’s where we supported the first major efforts to distribute bed nets and get people to use them. After we began this work, the U.S. started the President's Malaria Initiative, which essentially expanded what we were doing in Zambia and replicated the program in other countries.
Malaria deaths are way down from their peak in Zambia. Bed nets have been very effective. But we’re still looking for answers to some questions about them. How much do they help long term? How quickly do they wear out? Despite them, do malaria deaths eventually rebound, as we’ve seen somewhat in Zambia (particularly in the north)? Why the increase - is it because people didn’t use the nets, because they’re torn, because mosquitoes adapted, or simply because mosquito numbers vary from year to year?
Nobody ever thought bed nets alone would drive malaria to zero. They’re a really good tool, but you'll need a couple other tools that you use in a deep way to ever get to eliminating malaria in a particular location or community. Everything we’re learning is equipping us to achieve our long-term goal, which is to eliminate malaria locally in a whole lot of communities, building to eventually emptying the malaria map.
New kind of government partnership in Ethiopia
We’ve been working in Ethiopia for more than a decade. In that time we’ve made over 125 grants to partner organizations that are doing health and development projects there. Our engagement deepened a few years ago when Prime Minister Melas Zenawi came to us and said he really wanted to improve agricultural productivity. Agriculture contributes about half of Ethiopia’s GDP and employs roughly 80 percent of the workforce.
But the Prime Minister said he wanted to try something different from the normal way donors come in and support particular projects. He wanted to step back and look at everything involved in farm yields – seed companies, farmer education, fertilizer costs, everything – and then figure out an overall plan. And then ask donors to support things that fit with the plan. So, about a year and a half ago, Ethiopia formed the Agricultural Transformation Agency.
This is exciting, because areas in the Horn of Africa are often on the edge of famine. The situation in Ethiopia is nowhere near as bad as in Somalia, but the eastern part of Ethiopia has had recurring food problems. Improving the amount of food farmers can raise would make a big difference in the lives of those families living there.
Now that ATA has new policies in place, donor money is going to support projects in line with an overall plan. A lot of the focus is on increasing the productivity of small farmers. Part of the plan involves using new types of seeds. I’ll get to see how that’s going.
Community health outreach
I’ll also get to see the results from Ethiopia really bulking up its community health outreach. About 20,000 young women have been trained and placed in newly built health posts, as they’re called. I’ll be interested to see how that’s going and what the challenges are. One surprise is that pregnant women aren’t coming into the health posts to deliver their babies, at least not as much as expected. What would it take to change that, since the health of the mother and the baby are so dramatically improved by delivering in a clinic? I’m also interested in getting a clearer idea of Ethiopia’s vaccination rates. There are conflicting data on that.
Legumes – beans, basically
I'm also visiting an agricultural research station in Ethiopia where they’re doing very interesting work with legumes – beans, basically. The project is developing new varieties and helping farmers learn how to process them for sale to urban markets, which small farmers weren’t getting to before.
Beans are interesting because they’re a staple for really poor people almost everywhere. The most basic or world diets consist of some kind of bean and some kind of grain: beans and rice, beans and wheat, beans and millet. That combination gives you the complete proteins you need to live. So, nearly everywhere, subsistence farmers grow beans. They’re not only a staple, but also a fertilizer for farmers’ other crops, because beans return nitrogen back into the soil, which most every other crop takes out. Coming up with even better varieties could help farmers and improve nutrition in many places.
As always, throughout this trip I’ll be meeting with local representatives of donor groups and leaders of aid projects. We get together and they talk openly about what’s working and what’s not. That’s always very helpful, hearing from people in the field.
When I come back from Africa I plan to share some of the stories and photos of what I’ve seen in the field so that others can have a glimpse of what’s going on in the poorer part of the world. And by providing that glimpse, I hope it draws people in to want to know about and care about these issues.
Innovation on Small Plots
Working together for small farmers
I urged leaders of the international agriculture community that they need to do better for small farmers.
If you care about poor people, you need to care about agriculture.
Most extremely poor people in the developing world get their food and income from farming small plots of land. Many others live in big cities and need access to inexpensive food to be healthy and productive. So helping small farmers grow more food sustainably is the best way to fight hunger and poverty over the long term.
History is on our side. In the past several decades, agricultural yields in many places have doubled, and hunger and poverty have been cut in half. Now it is time to continue and accelerate that progress.
This week, I am speaking to the leaders of the international agriculture community at a meeting at the International Fund for Agricultural Development. The audience will be made up of the key people working in developing countries, aid agencies in developed countries, and international groups like the World Food Program and the Food and Agriculture Organization—and my message is that they need to do better for small farmers.
I am urging them to get together to set a common productivity target and create a system of public scorecards to hold themselves accountable. If they take these steps, I believe it is possible to meet the world’s most aggressive goals for reducing hunger and poverty.
One of the most important priorities is connecting the poorest farmers in the world to breakthroughs in agricultural science and technology. Right now, a digital revolution is changing the way farming is done, but poor small farmers aren’t benefitting from it.
For example, we now have satellites that can identify instantly and precisely how much wheat there is in a field. However, many developing countries are still sending people out with a pad, pencil, and tape measure to estimate yields. As a result, we take more time and expense to get less accurate and incomplete data. Better data, collected in a timely way, means decision makers have better information to make policies that can help farmers. That is one examples of how a digital revolution can make a difference.
Innovation is the concept on which Melinda and I created the foundation. For years, we saw the impact that innovation in the computer industry had on the richest people in the world. But at the same time, the poorest half was hardly benefitting from innovation at all. We hope our foundation can work with partners to help change that.
The stakes could not be higher. The world’s ability to help small farmers be more sustainably productive will determine whether or not they remain in poverty or whether the hard work results in self-sufficiency for hundreds of millions of people.
Swatting Mosquitoes
Using Disease to Fight Disease
A novel approach to controlling mosquito populations
Most people probably wouldn’t want to visit a mosquito research lab on their family vacation, but Melinda and I were in Australia recently and were excited to see some amazing work in molecular biology that could lead to a breakthrough in controlling mosquito-borne diseases such as dengue fever.
Mosquitoes are a plague in much of the developing world, not just because they are a nuisance, but because they are transmission agents for some truly terrible diseases. The scientists we met with in Cairns have discovered a way to infect mosquitoes that are normally capable of carrying diseases like dengue and yellow fever with a bacterium called Wolbachia. Wolbachia is naturally present in many types of insects, but not in these mosquitoes. Although it is harmless to humans and most other animals, when placed in these mosquitoes Wolbachia shortens their lifespan by about 50 percent and inhibits the development of dengue virus and several other pathogens.
If mosquitoes with the Wolbachia strain can be successfully introduced into wild mosquito populations, it could greatly reduce the transmission of infectious diseases to humans because most mosquitoes would die off before the viruses that cause human disease could replicate in their body. Another plus for Wolbachia is that it alters the mosquitoes’ reproductive biology, so that when female mosquitoes that do not carry Wolbachia mate with male mosquitoes that do carry Wolbachia nearly all of their embryos die off. Since Wolbachia is passed through the mother mosquito to her offspring, this means that Wolbachia can spread very rapidly through a mosquito population.
Some of these discoveries were a surprise to scientists. If they can be proven in field trials, Wolbachia could create a cheap, natural, and self-sustaining method of control that dramatically reduces dengue fever and other major infectious diseases such as yellow fever and malaria.
The research, led by Professor Scott O’Neill of Monash University, has been funded since 2005 by the Foundation for the National Institutes of Health (FNIH) under the Grand Challenges in Global Health initiative, which encourages innovation to solve persistent health problems in the developing world. Diseases spread by mosquitoes are definitely at the top of that list.
O’Neill’s work is mainly focused on preventing mosquitoes from transmitting the virus that causes dengue fever, an infectious tropical disease that causes 22,000 deaths—mostly among children—and results in 500,000 cases of severe illness each year. Scientists are optimistic that this approach could also work with other insect-transmitted diseases such as malaria, which kills nearly 1 million people annually, mostly children under 5 years of age.
Historically, the battle against disease-carrying mosquitoes has relied on repellants, insecticides, bed nets and eliminating stagnant water breeding sites. More recently, scientists have been working on vaccines that would prevent people from getting infected with mosquito-borne diseases.
To do his current research, O’Neill has had to convince people in Cairns that releasing mosquitoes in their neighborhoods is a good thing. Melinda and I participated in one release of about 20 jars of mosquitoes—probably 1,000 mosquitoes in all. I was bitten by several dozen, but was safe from getting dengue fever because the mosquitoes being released were lab-reared and not infected with dengue. I have a lot of respect for the volunteers who go into mosquito cages and allow themselves to be bit in the name of science. The average number of bites they get is over 50!
It was fascinating to see the project first-hand. There’s a real possibility that this approach will get deployed broadly and could really help reduce a lot of disease transmission. But as exciting as it was for Melinda and me, our kids said they definitely didn’t mind not going along.
A Bunch of Reasons
Building better bananas
I'm sometimes asked why the foundation has made agricultural development a priority along with global health. Actually, the two are intertwined. One example comes from Australia and Uganda, where researchers are using advanced technology to try to improve the banana.
Our foundation’s work around the world gives me opportunities to meet really smart, visionary people who are doing pioneering work in fields that I might not get a chance to learn much about otherwise. For example, in December Melinda and I went to Cairns, Australia, where James Dale and his team from Queensland University of Technology are doing advanced research on bananas. As odd as that might sound, this research could make a big contribution to public health in a lot of Africa and Asia.
Before our visit, I didn’t know much about bananas. Dale, an agricultural scientist, is one of the world’s leading experts. He has been profiled in The New Yorker, in a fascinating article about the history of bananas as an export crop. As the article explains, a blight has spread among plantations in Asia and Australia in recent years, badly damaging production of the one type of banana that is grown for export, the Cavendish. This disease, a fungus, hasn’t spread to Latin America yet, but if it does, bananas could get a lot scarcer and more expensive in North America and elsewhere. Dale is working to develop new versions of the Cavendish that resist the fungus. He does this by inserting genetic material from other organisms into banana plants.
This work is separate from the research that our foundation supports, although some of the same techniques and scientific principles are involved, including transgenic experiments. Making banana plants less susceptible to diseases is a secondary goal for us. Our primary goal is to help Dale develop new types of banana that are more nutritious—specifically, much richer in Vitamin A and Iron that the body can absorb.
This is important because the diets of millions of people in Africa are deficient in both of these vital nutrients. While rare in the developed world, Vitamin A deficiency in developing countries causes hundreds of thousands of children to go blind each year. It also reduces the body’s ability to fight infection, which raises the fatality rates in poor countries from infectious diseases like measles. Iron deficiency is so serious and widespread that in Uganda, for example, more than 40 percent of young children have stunted growth and 73 percent are anemic.
Meanwhile, bananas are a primary staple of people’s diet in Uganda and many other African nations. (Our foundation also has supported research to enhance the micronutrient content of cassava, rice and sorghum, all staples for millions of the world’s poorest people.) An average Ugandan consumes about five times his or her weight in bananas each year. Fortunately, Ugandans have more varieties of banana to choose from than we usually do in the developed world. Some varieties are eaten raw, while others are cooked as part of a dish with other ingredients. The kind that are cooked are sometimes called plantains, but they’re all bananas. For dessert there’s the sweet Sukali Ndizi, which children especially love.
Unfortunately, the banana varieties grown in Uganda are low in essential micronutrients, particularly Vitamin A and Iron. To increase these levels, Dale and his team in Australia are collaborating closely with Ugandan scientists at that country’s National Agricultural Research Organization. The NARO team, led by Dr. Wilberforce Tushemereirwe, has made important contributions—developing research protocols, conducting field trials, and planning distribution of new, more nutritious banana varieties to Ugandan farmers. The NARO team’s involvement is a great example of young African scientists playing a major role as full partners in using state-of-the-art science for development of new products important to agriculture and health in their own country.
Our foundation has supported this work since 2005, initially as part of our Grand Challenges in Global Health initiative, which fosters early-stage research aimed at breakthroughs on the world’s most pressing health problems. If you had asked me at the time, I would have said the project was one of the more wild things we funded. Some of the original Grand Challenges projects, even some of the ones I thought were the most likely to succeed, have come to an end, but that’s scientific discovery.
Other funders have not been focused on the kind of work that Dale and NARO are doing, so our funding has been important, and the work is progressing well. New banana varieties have been developed that have as much as five times more Vitamin A than before. You have to get the levels just right, though, because too much makes the banana look orange, which consumers might not like. Boosting iron levels seems to be a tougher challenge.
It all takes a long time, though, for a few reasons. Not much was known before about how to work with banana cultures at the molecular level, so a lot of basic science had to be done first. Then, it takes two or three years to take a new banana culture from inception to the point where it produces fruit and you can see if it’s more nutritious. And there have been some unfortunate setbacks. In early 2011, Cyclone Yasi roared through Cairns and destroyed the fruit crop from field trials there. Luckily, the cyclone did not uproot the plants, but the trials were delayed at least nine months until a new crop of bananas could grow.
Once some clearly superior banana varieties are developed and proven, it will take time to do the research to show the health benefits, for regulators to approve them, and for farmers to begin planting them.
It’s great that we started back in 2005.
Fighting Crop Disease
Cassava: can science save a diet staple?
In Tanzania last year, I visited with farmers whose survival – like that of millions of other Africans – depends on the cassava, a diet staple threatened by disease. I also visited with African scientists on the forefront of efforts to protect the cassava and other vitally important crops.
In Tanzania last year, I visited with farmers whose survival—like that of millions of other Africans—depends on the cassava, a diet staple threatened by disease. I also visited with African scientists on the forefront of efforts to protect the cassava and other vitally important crops.
Cassava is a staple crop that provides a basic diet for more than 500 million people worldwide.

Cassava is a starchy root that must be processed before eating because it contains small traces of cyanide. It is often grated, dried, and roasted to make garri, a flour; the leaves are eaten as vegetables in a stew.

When dried to a powder, cassava is known as tapioca.

These cassava plants are infected with mosaic disease, making the cassava root much smaller and less nutritious.

Christina supports her family by farming cassava. In the past two years, Christina’s crop has been invaded by two cassava diseases. Because of these diseases, she is depleting her savings to buy cassava to feed her three children. For Christina and other small farmers getting food is the most pressing daily concern.(Mapinga Village, Tanzania)

When I was in Tanzania last year, I met Dr. Joseph Ndunguru, a plant scientist leading a project to fight the mosaic and brown streak diseases that attack cassava crops. Dr. Ndunguru is part of a new generation of African scientists building up the capacity to do innovative science in Africa.

One Year Polio-Free
India Marks a Milestone for Child Health
This Friday will mark a full year since the last case of wild poliovirus was detected in India. This is a huge milestone in the history of global health. But the fight against polio is not over.
Four years ago, I visited India and saw again what polio does to children. I was in a slum in East Delhi, when I met a 9-month-old girl named Hashmin—paralyzed by polio—cradled in her mother's arms. She will never be able to do many of the normal things kids do because she has polio. Watching her was the strongest of reminders of the imperative of ending this terrible scourge once and for all.
The following year, in 2009, India had more polio cases than any other country in the world. But much has changed since then, and this Friday will mark a full year since the last case of wild poliovirus was detected in India. This is a huge milestone in the history of global health.
With a huge and growing population, hard-to-reach migrant communities, and sanitation and health conditions that limit the effectiveness of polio vaccines, this remarkable achievement in India marks clear progress in the fight against polio.
India really stepped up to the challenge on polio. The government of India funded its own eradication program. Twice a year, 2 million volunteers prepare 800,000 vaccination booths around the country—at schools, hospitals, and community centers. They immunize more than 172 million children one by one. Working with partners like Rotary International, WHO, and UNICEF, they have built an impressive infrastructure for delivering health services to some of the most underprivileged children in the world.
India’s story is proof that major health problems can be solved in the toughest places in the world. But the fight against polio is not over and we are at a critical moment in time.
In 2011, there were still a handful of countries with polio outbreaks. We must sustain funding to ensure a comprehensive immunization effort in India and other countries—until there are no more cases. If we don’t, the virus can spread back into countries where it has been eliminated, as it did last year in Russia and China.
Eradicating polio is a top personal priority and of the greatest importance at the foundation. Last year, I visited India again to see how the country was able to make such phenomenal progress. I also visited Nigeria and Chad to understand the challenges that lie ahead. I’m optimistic that we can vanquish polio forever if other countries choose to learn from India’s success. Together, we can accomplish something amazing.
Keep Giving
A plan to assist the world’s poor
Advances in agriculture, education, health, and sanitation have led to a dramatic decline in child deaths over the last 50 years. But the global economic crisis is putting at risk the development aid so critical to continuing this progress. As Congress considers foreign aid in the coming weeks, I encourage policymakers to consider the remarkable impact of American aid, its benefits to the U.S., and the contributions of a growing number of donor countries.
Fifty years ago, almost 20 million children under the age of 5 died every year. In 2010, the figure was down to 7.6 million. This 60 percent decline in childhood deaths — reflecting advances in agriculture, education, health and sanitation — is compelling evidence of the increasing justice in our world.
But the global economic crisis is putting the long-term trend of progress at risk, as Congress’s debates about the foreign aid budget underscore.
I am giving a report Thursday to the heads of the Group of 20 governments, including President Obama, suggesting creative ways for the world to continue investing in development despite fiscal constraints. I hope three key ideas become part of congressional deliberations over the coming weeks.
First, programs funded by U.S. generosity have been a core component of this 50-year project of raising living standards around the world.
Aid is targeted to fill specific gaps in development. The most important of these gaps is innovation. When the private sector doesn’t have incentive, and poor governments don’t have the money, smart aid pays for breakthrough solutions. The green revolution that fed a billion people in the 1950s and ’60s never would have happened without advanced agricultural science funded by U.S. aid. In just the past 10 years, millions of children have been saved from diseases such as measles and whooping cough by vaccines that Americans paid for through their contribution to an organization called the GAVI Alliance. Immunization is a great example of how aid can be effective. Thirty-six cents worth of measles vaccine protects a child for a lifetime.
Second, development isn’t just good for people in poor countries; it’s good for all of us. It used to be that the world was, roughly speaking, one-third rich and two-thirds poor. Now, the number of dynamic, healthy, highly educated countries is much higher, which is a recipe for prosperity. Imagine the world economy without Brazil, China, India, Indonesia, South Korea, Mexico or Turkey.
If countries that are currently poor can feed, educate and employ their people, then over time they will contribute to the world economy. On the supply side, they’ll increase the production of key commodities such as food, keeping prices lower. On the demand side, as their citizens are more productive, they’ll become important markets for trade.
But if people don’t get access to basic necessities, continued suffering will lead to economic stagnation and instability. It is, for example, not only unconscionable but also a strategic mistake to allow famine to devastate the livelihoods of millions of people in the Horn of Africa.
Third, the United States is not doing development alone. We spend about 1 percent of our total budget on aid, as do dozens of donor countries.
And with only a few exceptions, the amount poor countries spend on their own development is much greater than the amount donors invest. Ethiopia, for example, has in the past five years built 15,000 rural health posts to provide improved services for its citizens.
There is also a group of rapidly growing countries — including Brazil, China and India — that combine recent experience with development and significant technical capacity, giving them the insight and the skill to have special impact. For instance, China is sequencing 10,000 varieties of rice to help small farmers cope with climate change. These efforts can make a big difference. For example, a new submergence-tolerant rice variety being used in flood-prone areas of Bangladesh and India can more than double farmers’ yields. We predict that 20 million farmers will be planting this variety in the next six years.
The private sector hasn’t always invested as much in development as it should because the market incentives haven’t always been clear, but there are ways to encourage involvement. In my report to the G-20, I’ll make half a dozen recommendations for mobilizing tens of billions of dollars annually from private sources. The African diaspora is sitting on $50 billion in savings that could fund development in their home countries if it were captured through diaspora bonds.
If the transaction costs on remittances worldwide were cut from an average of 10 percent to an average of 5 percent, it would unlock $15 billion a year in poor countries. In addition, there are trillions of dollars in sovereign wealth funds, and a portion could be reserved for key infrastructure projects in poor countries.
Sometimes Americans get the impression that we’re shouldering the whole burden of development and that, ultimately, our aid doesn’t make a big difference. I see it very differently. We’re providing strategic investments that link up with many other investments to systematically make a better, more prosperous and safer world. If we do it right, we can keep shrinking the number of countries where aid is needed to zero.
This was originally published on November 1, 2011 in the Washington Post.
Advancing the MDGs
Foreign aid advances millennium development goals
In this photo gallery, meet some of the people who are helping their countries move closer to meeting the U.N. Millennium Development Goals.
From a Kunwasi village in Ghana to a Maksoodpur village in India, development aid is saving children’s lives, improving health conditions, reducing poverty and hunger, and increasing economic growth and stability. In this photo gallery, meet some of the people who are helping their countries move closer to meeting the U.N. Millennium Development Goals.
Ethiopia
Lomitaa, a health extension worker in Ethiopia, makes a home visit in Mojo village. To reduce suffering from preventable and treatable diseases, the government trained more than 32,000 women as health extension workers, to teach rural families about disease prevention and healthy living. It also created “health outposts” to provide basic medical services and preventive care in rural areas. Since the program’s launch in 2006, there has been a 35 percent increase in immunizations for diphtheria, tetanus and pertussis, and a 50 percent reduction in malaria. Health extension workers often walk miles to reach families in the most remote areas.
Nicaragua
Nicaraguan horsemen Julio Mesa Zelodon and his son Santos delicately balance a fragile cargo of rotavirus vaccines, which must be transported in an insulated box to preserve the drug’s effectiveness. Rotavirus is a preventable and treatable diarrheal disease that causes 500,000 deaths each year among infants and young children. Since the vaccine’s introduction in 2006, Nicaragua has seen a 77 percent decrease in severe rotavirus cases. The vaccine is often transported by horse, donkey or boat to reach the country’s most remote areas.
Ethiopia
Since Ethiopia emerged from 16 years of civil war in 1991, the country has made significant progress in poverty reduction, food security, health, nutrition, and education. Education reforms aimed at increasing access, especially for girls and the rural poor, increased student enrollment by 500 percent. School fees were abolished and funding was provided for adult literacy programs, school construction, and to train and hire teachers.
Ghana
Staple crops like cassava and yams as well as cash crops like tomatoes and peppers are on sale at a street side market in Kumasi, Ghana. Through agricultural reforms, farmers are better able to cultivate staples and grow cash crops for additional income, reducing the country’s hunger rate by 75 percent and cutting poverty nearly in half.
Ghana
Andres Yemetey from the Ghana Infant Nutrition Action Network discusses the benefits and proper techniques of breastfeeding with Estherlyne Larkai as she feeds her daughter at the Osu Maternity Home in Accra.
In the past, many women in Ghana supplemented breast-feeding with water, sugar water, or herbal concoctions that caused diarrhea and other problems. As the result of government education efforts, many women now feed their babies only breast milk, and men are encouraged to provide support to make that possible.
Cote d'Ivoire
Kevin Kouassi, 36, who is HIV-positive, works at the NDA Health Center in Dimbokro, Cote d'Ivoire. His job is to encourage testing, counsel those who come to the clinic, and educate them about prevention and treatment. Today free testing for HIV/AIDS is readily available in Cote d'Ivoire and can be done in as little as 15 minutes, ensuring that patients will stay to receive their results. Here, he counsels 24-year-old Aya who is six months pregnant with her second child and has come to the clinic for testing.
Viet Nam
In the last two decades, Viet Nam has become a major exporter of rice and coffee, and its manufacturing sector has boomed. The government has tapped the country’s economic growth to improve health, education, and water and sanitation services. Incomes have risen and the poverty and infant mortality rates have fallen dramatically.
Egypt
Until recently, most births in Egypt were at home and unattended by skilled personnel. Through education and outreach efforts, couples like Saad and Madiha have learned about the value of prenatal visits, medically assisted childbirth, post-partum care, and family planning. Targeted villages have seen dramatic improvements in maternal and child health, including a 27 percent drop in underweight babies.
Bangladesh
A Bangladeshi mother, Shahinoor, gives her child, Santo, oral rehydration solution. Commonly made of ingredients that poor households can afford, such as salt and unrefined brown sugar, oral rehydration therapy has saved the lives of millions of children from death due to diarrhea. Its widespread use, in combination with immunization campaigns for childhood diseases, has significantly reduced child mortality and malnourishment in Bangladesh and worldwide.
India
In 1975, the Indian government started the Anganwadi program, one of the largest child health and development efforts in the world. Here, Anganwadi worker Pushpa Kumari vaccinates a child against polio in a house-to-house campaign in Maksoodpur village. Between 1999 and 2007, India’s under-five mortality rate fell from 117 to 72 per 1,000 children.
Malaria Forum
Charting a course to end malaria
With continuing innovation, we can eradicate malaria.
In the past 10 years, the number of people who die from malaria has declined 20 percent.
For the past three days, the global malaria community has been meeting in Seattle, talking about what it’s going to take to get rid of the other 80 percent. The eradication of malaria is an ambitious goal and a long-term goal—but a goal Melinda and I are 100 percent committed to.
People used to say eradication was impossible, but we remain optimistic because human beings have a spectacular ability to innovate.
The tool that’s most associated with the recent progress against malaria is the long-lasting bed net. Bed nets are a fantastic innovation. But we can do even better. We can invent new ways to control the mosquitoes that carry the malaria parasite.
One of the problems with nets is that they can be uncomfortable to sleep under, so people sometimes chose not to. Researchers are testing spatial repellents that drive mosquitoes away right now. A family could hang a small coil from the ceiling and be protected, without having to accept a terrible night’s sleep.
One innovation the malaria community has been pursuing for decades is a vaccine. We have never had a vaccine for a parasitic disease, and the scientific complexity is dizzying. But at this week’s meetings I was pleased to announce interim results from the final-phase of a trial for a vaccine candidate called RTS,S. Among five to 17-month-old children, the vaccine prevented clinical malaria (which was defined as the presence of fever and parasites in a child who was ill and brought to a health facility for care), in 56 percent of trial participants over a period of one year. We still need to analyze the complete data when it’s available, but this vaccine could be licensed and protecting children by 2015.
We’ll keep on innovating and improving on this vaccine, but these results are a huge milestone in the history of our fight against malaria.
The malaria parasite has been killing children and sapping the strength of whole populations for tens of thousands of years. It is impossible to calculate the harm malaria has done to the world. But we have the ability to make generation after generation of better tools, and we can chart a course to end malaria.
More Work to Do
Why we must outsmart mosquitoes
The decisions we make now will determine what happens to malaria in the future.
On October 18, at the foundation’s second annual Malaria Forum, I spoke about the progress being made in the war against the dreaded parasitic disease. But more needs to be done to control and eradicate it, including a higher level of preventive drug treatment for pregnant women, additional research on chemical repellants, and further investigation of vaccines and drugs to treat those who are infected.
Prepared Remarks by Bill Gates
Thank you, Melinda.
Melinda told you about some of the people we met in Tanzania recently. I was impressed by a man named Prosper Chaki, who runs a larviciding project in Dar es Salaam. He spends his days wading into the standing water where anopheles mosquitoes breed, so he can poison them. It’s not so surprising that he’s gotten malaria 20 times.
“Mosquitoes are smart,” Mr. Chaki said. Then he told us, “We have to be smarter.”
I believe we will be smarter. One reason is that you have come from all over the world to this forum—to challenge each other, to disagree with each other, and to learn from each other. When you leave tomorrow, our team at the foundation will move forward with the benefit of the most rigorous thinking in the world. We are grateful to you for that, and I hope each of you will take inspiration back with you as you continue your personal fight against malaria.
The other reason I believe we will be smarter is that human beings have a spectacular ability to innovate. Innovation is one of the most powerful forces in the world. It can make the impossible, possible.
Melinda talked about the innovations that have changed the course of malaria and saved a million lives in the past 10 years.
But innovations are only as good as our commitment to delivering them. We have to get better at using the innovative tools we have.
Intermittent preventive treatment with drugs during pregnancy and infancy are two proven methods of protecting those most at risk from malaria, but they’re not saving as many lives as they should be. For example, most countries in sub-Saharan Africa provide IPTp in less than 20 percent of pregnancies. That is not good enough.
We have to demonstrate the same level of commitment as new tools come online. I am very optimistic that Seasonal Malaria Chemoprevention will be available starting early next year, when the WHO’s approval process is complete. We must be aggressive in launching pilot studies to understand how this intervention should fit into control strategies, so we save as many lives as possible, as quickly as possible.
We also have to be thinking simultaneously about the next generation of tools. If we think big, bring more partners into the fold, and take smart risks, we will invent novel tools—powerful ways of fighting malaria that don’t exist now. This is the kind of innovation that will enable us to plan for the eventual eradication of malaria.
Eradication is an ambitious goal—and a long-term goal. It is also a goal to which we remain 100 percent committed.
We are committed to it for moral reasons. My children will not die from malaria, thank God. Since that is true, no child should die. It should never be too expensive or too inconvenient to give the poorest a chance to survive when the richest already have it. Equity is not yet a reality, but it is what we believe in and what we are striving for.
We are also committed to eradication for strategic reasons. The only alternative to charting a course to the end of malaria is an eternity of trying to stay just one step ahead of the parasite and the mosquito. If we have to fight in perpetuity, the cost in lives will be enormous. The opportunity cost of never being able to divert our attention to other challenges will be incalculable.
I know some people in the malaria community worry that focusing on the uncertain goal of eradication could distract us from control measures that are working today. I understand the desire to stay focused on saving lives. But I don’t see eradication and control as two separate approaches to the fight against malaria. Instead, they are two compatible parts of a single approach. To achieve elimination and eradication, we need to start with control, drive it up to high levels, and sustain it. But if we don’t target elimination and eradication, control will lapse, and malaria will continue taking lives.
It will take leadership and innovation and money to extend the recent success. It will also take leadership and innovation and money to plan for malaria’s eventual eradication. The conclusion is daunting, but inescapable: We will need enough leadership and innovation and money to do both. We do not have the luxury of choosing one or the other.
I am an optimist. I believe we are capable of setting our sights on an ambitious goal with a generation-long time horizon and multiple, shifting milestones along the way. But eradication will never happen as long as it remains a general aspiration. We must turn it into a specific plan, and our job now is to lead the constant search for new and better tools that will help us execute our plan, step by step.
The best tool we have now is bed nets. Nets are a fantastic innovation, but they’re not perfect and they won’t be sufficient. They are expensive, they are unpleasant to sleep under, and they don’t protect against outdoor- and daytime-biting mosquitoes. There is a clear need for cheaper, easier to use, and more powerful vector control methods.
I am enthusiastic about spatial repellants, chemicals that can keep mosquitoes away from treated areas. Repellants could be a big improvement over nets, because the people benefitting from them wouldn’t have to make the choice to sleep under them every single night. The likelihood of human error or human resistance would shrink by a lot. And spatial repellants would be effective against all types of mosquitoes, no matter when or where they bite.
Recent trials in China showed that mosquito coils containing a chemical repellent decreased people’s odds of contracting malaria by about 80 percent—and coils plus nets were much more effective than coils or nets alone. Right now, additional trials are taking place in Indonesia to confirm the impact of coils on transmission and to measure their impact on the mosquito population. We expect data from this critical proof of principle study in the middle of next year.
Researchers are also busy identifying potential active ingredients for spatial repellants. Larry Zwiebel of Vanderbilt University just isolated a compound that is 1,000 times more powerful than DEET. Other researchers are looking at other formulations, and results from these studies will be available in two or three years.
ACTs are the second tool that has changed the course of malaria control over the past several years. Obviously, they represent a vast improvement over the old drugs that weren’t effective, but, like nets, they are not ideal. Artemisinin is expensive, the course of treatment lasts several days, and resistance is already developing.
The Medicines for Malaria Venture currently has a drug candidate in phase II trials, OZ 439, that has the potential to be a single-dose cure. This could solve many of the problems with ACTs. It should be cheaper, since the total amount of drug needed for treatment will be lower. Adherence will be much higher, since people will have adhered completely as soon as they swallow the pill. This will decrease the risk of treatment failure and slow the development of resistance.
OZ 439 could be licensed as early as 2016, depending on the suitability of the quinolines currently being tested as partner drugs. In addition to finishing the trials, MMV is working to find a partner from the pharmaceutical sector to help it make and market OZ 439 when the time comes.
One of the most important innovations for the future of the fight against malaria will be a tool we don’t yet have: a vaccine. A vaccine is a wonderful thing. It’s the simplest, most cost-effective way to save lives. The smallpox vaccine, plus the innovative approach of ring vaccination, led to the eradication of smallpox. The polio vaccines have pushed the world to the threshold of eradicating polio. Vaccines have slashed the number of deaths caused by diphtheria, measles, tetanus, and a host of other diseases.
But the search for a malaria vaccine has been a long and frustrating process. There has never been a vaccine for a parasitic disease. The scientific complexity is dizzying.
Today, however, we are closer than ever before to tackling that complexity. Four years ago, I announced interim results from phase II trials of the RTS,S vaccine. Today, I am pleased to announce the interim results from the phase III trials. Among five to seventeen month old children, the vaccine prevented clinical malaria in 55.8 percent of trial participants over a period of one year. RTS,S prevented severe malaria in 47.3 percent of trial participants aged five to seventeen months. It prevented severe malaria in 34.8 percent of the entire study population, including infants.
These are only interim results. We need to study the data over a longer period of time to understand whether the effect of the vaccine diminishes. We also need to evaluate the impact of a booster dose. Leaders must have all this information before they can make decisions about how to use the vaccine if and when it’s approved.
Nevertheless, these results signal a huge milestone, and I want to congratulate the many partners that have been working on this project for decades. First, this is proof that it is possible to create a vaccine that is effective against malaria. For a long time, we didn’t know. Now, we know. Second, if RTS,S continues to show effectiveness of around 50 percent—above and beyond bed nets—it has the potential to protect millions of children and save thousands of lives.
And RTS,S is a first-generation vaccine. It is an early outcome of a long process of innovation that will ultimately yield more effective vaccines. Researchers are currently recruiting participants for the phase I trials of a second-generation RTS,S vaccine.
There are many vaccines that work according to completely different mechanisms in various stages of development. I am particularly excited by the potential of transmission blocking vaccines, vaccines that prevent mosquitoes from picking the infection up from human hosts. In the drive toward elimination and eradication, these vaccines will be invaluable.
But the fact is there are still many basic science questions about malaria that we need to answer to make the search for vaccines less challenging. We know there are mechanisms by which people become immune to malaria. We can even produce that immunity artificially, but we don’t understand it. If we get a better sense of what underlies immunity in those cases, we will have a much better chance of filling the vaccine pipeline with good products.
As we develop these new tools, we also have to develop a more sophisticated understanding of how to deploy them. When you have several ways to fight more than one species of parasite, carried by many species of vector, you can’t afford to guess about strategy. What is the smartest way to combine our interventions so they have the maximum effect? We need to be able to answer these questions with evidence.
I believe modeling can help generate that evidence. I want to walk you through some charts from one malaria model to give you a sense of the kinds of answers they can provide.
When our friend and mentor Warren Buffett made his gift to our foundation five years ago, he was clear about the purpose philanthropy should serve. One of his famous quotes about finance is, “I don’t look to jump over 7 foot bars. I look around for 1 foot bars that I can step over.” Philanthropy is the other way around, he tells us. We should be looking around for the 7 foot bars; that’s why we exist.
Malaria eradication is a high bar. To reach it, it will take a constant, concerted effort to innovate. But we can do it. We can drive down the number of cases, lower and lower. We can keep introducing new and better tools, until we interrupt transmission like we’ve done in dozens of countries already. And, eventually, with relentless focus, we can eradicate malaria. We’ve already shrunk the malaria map considerably. We can make it disappear.
It won’t happen in four years, or in eight years. But the decisions we make now will determine what happens to malaria in the future.
The parasite has been killing children and sapping the strength of whole populations for tens of thousands of years. It is impossible to calculate the harm malaria has done to us. Now, we can chart a course to end it.
Thank you.
In Africa
Visiting Tanzania: A Battleground in the Fight Against Malaria
On my most recent trip to Tanzania, Melinda and I spent time looking into how the foundation’s partnerships to reduce malaria are progressing.
On a recent trip to Tanzania with Melinda, we spent time focused on the foundation's efforts to reduce malaria. We were particularly interested in learning about the progress of research into a malaria vaccine.
Bagamoyo District Hospital
These children were waiting to see a doctor at the Bagamoyo District Hospital in Tanzania. They are among several thousand children participating in field trials of the vaccine, known as RTS,S. Just this week, interim results from the clinical trials were reported, and they prove that it’s possible to create a vaccine that’s effective against malaria. It was exciting to visit this clinic because it is so well run, they're offering lots of good health services, and people are coming from far away to participate in the vaccine trial.
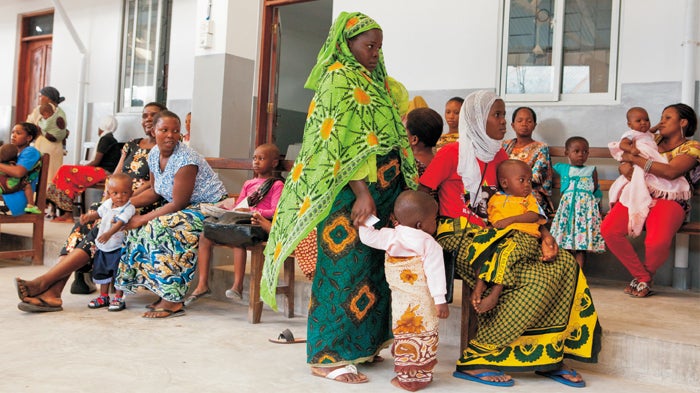
Meeting with Health Officials
We met with health officials from the Bagamoyo District Hospital and the Ifakara Health Institute. There were a lot of visiting scientists from the Swiss Tropical and Public Health Institute, which has a close relationship with the IHI. We saw scientists who are working on ways of repelling mosquitoes so people don’t just have to rely on bed nets, which are only partly successful protection against malaria. It's great that the foundation’s support is helping with the vaccine, and that it is also helping train young scientists and building up a research infrastructure, which will have a lot of long-term benefits.

Ifakara Health Institute
Scientists at the Ifakara Health Institute were great at educating us about their work, including techniques for capturing mosquitos to help prevent malaria, what species of mosquito they were focused on, how they get the vaccine out into the field, and how they saw if the vaccine worked.

Meeting with Hospital Staff
We also met with staff at the local hospital to discuss progress treating and preventing malaria.

Mapinga Village Dispensary
We visited the Mapinga Village Dispensary, which is an example of how healthcare is delivered in Africa. These dispensaries are the first place people go for care in or near their villages. We saw how the dispensaries keep their vaccines, and we talked to people like Neema Malachi Najwale, the nurse in charge of the Mapinga Dispensary, about how they get mothers to come in for the vaccines. We also talked about how they can now use cell phones to send regular status reports on their inventory.

Meeting with Parents
We talked with some of the parents of children participating in the vaccine trials. Although Tanzania is quite poor and hasn't developed a very extensive infrastructure of roads and electricity, in the health area they've done pretty well. They have good vaccine coverage and are on track to meet a lot of the Millennium Development Goals. It’s a great example of the progress taking place in Africa.

Defeating Malaria
At the Mapinga Village Dispensary, we talked with the head nurse about a number of diseases they have to deal with besides malaria. But by far the biggest killer of children and adults in that area of Tanzania is malaria. So the enthusiasm among health officials for the new malaria work there is very high. I’m an optimist when it comes to defeating malaria. There is good progress with the vaccine, drugs to prevent and treat malaria, and other preventive measures. Eradicating malaria won’t happen overnight, but it’s a moral and economic imperative for Africa, and for the entire world.

A Childhood Terror
The history of polio in the U.S.
David Oshinsky remembers growing up in an America terrified by polio—a plague that put every child at risk until a vaccine was finally developed in the mid-1950s.
David Oshinsky, the author of Polio: An American Story reflects on the history of polio and the final push needed for eradication.
First Pledges
GAVI raises $4.3 billion at first pledging conference
Today we get to celebrate a significant milestone for global health equity.
The GAVI Alliance, an organization that helps make sure children in poor countries get the same vaccines that children in rich countries do, just met its fundraising target for the next four years. They did it despite the fact that donors everywhere are coping with budget crises.
This news comes on the heels of an announcement by several multinational and developing country vaccine manufacturers that they will be lowering the prices of some key vaccines. Together, these developments mean that we can save more than 4 million additional lives by 2015.
Vaccines are one of the best long-term investments to prevent disease and give children a healthy start in life. But for a long time, the healthiest children in the least danger were getting vaccines, and the children who needed vaccines the most weren’t getting them. In many cases, it took decades before vaccines made for developed-country markets were available in poor countries. Take the example of rotavirus, the leading causes of diarrheal disease. Only children in poor countries die from rotavirus, yet the vaccines for the disease was made available first in rich countries!
That’s why increasing access to vaccines for the world’s poorest countries is one of the top priorities of the Gates Foundation, and that’s why today we pledged an additional $1 billion to support the lifesaving work of the GAVI Alliance over the next five years. We were joined by many other donors who understand that buying vaccines saves lives, and who know it is an investment worth making, no matter how tight their budgets.
How We Fight Epidemics
Tackling TB Through Innovation
I explored innovation in testing and treating tuberculosis, as I spent World TB Day in India.
Many people think tuberculosis is a disease of the past, but this ancient epidemic remains a huge global problem. Each year there are 9 million new TB cases and 1.7 million deaths.
Yet there is a tremendous opportunity to turn this situation around. Most new TB cases are in major emerging economies like India, China and South Africa, which have a remarkable history of using innovation to address tough health challenges. They are adopting new TB strategies, and are poised to develop the next wave of innovations. This could change the way the world fights the epidemic.
The major problem is outdated tools. TB is preventable and treatable, but the most common TB test is more than 125 years old and misses half the cases. By the time most TB patients are correctly diagnosed and treated, they may have unknowingly infected many others – creating an endless cycle.
At the same time, today’s TB drugs are more than 40 years old and take six months to work. The combination of poor tests and outdated treatments is driving the spread of drug resistance, undercutting global efforts to stop the epidemic.
I witnessed this firsthand in 2009, when I visited the King George V TB hospital in Durban, South Africa. I met a woman with HIV who had been diagnosed with a highly drug-resistant type of TB. She told us about the despair she felt when she learned she had such a dangerous form of the disease.
Fortunately, there is a promising pipeline of new TB diagnostics, drugs and vaccines under development. And we are starting to see results. Just today, I saw how India is using these innovations. I marked World TB Day by visiting the state-of-the-art L.R.S. Institute of Tuberculosis and Respiratory Diseases in New Delhi with Dr. Ashok Kumar, head of India’s TB program. L.R.S. uses a new molecular test, GeneXpert, which can accurately determine whether a patient has TB in about two hours.
Molecular diagnostics could revolutionize TB care, and things will continue to improve as the price comes down and new tests are developed. This is where India could have global impact. India is a leader in developing low-cost health technologies, and the country could produce high-quality, inexpensive molecular TB diagnostics. This would increase access at home and across the globe.
Meanwhile, South Africa is stepping up its own efforts. The country will likely begin widespread use of GeneXpert soon. This could profoundly impact health in a country where thousands of lives are lost each year to TB/HIV co-infection.
India and South Africa’s leadership shows the extraordinary potential for high-burden countries to pioneer TB innovations. Their success could be a model for other countries—and save millions of lives in the process.
Let's Finish the Job
My Annual Letter: End Polio Now
Polio, once a worldwide scourge, threatens to make a comeback unless all countries do their part to eliminate it. Eradication is tantalizingly close but funding to fight the disease still falls short.
Aid for the poorest has already achieved a lot. For example, because of donors’ generosity, we are on the threshold of ending polio once and for all.
Polio is a terrible disease that kills many and paralyzes others. Fifty years ago it was widespread around the world. When you talk to people who remember polio in the United States, they’ll tell you about the fear and panic during an outbreak and describe grim hospital wards full of children in iron lungs that maintained their breathing. At its peak in the United States in 1952, polio paralyzed or killed more than 24,000 people.
As a result of mass mobilizations to administer the polio vaccine, polio was eliminated in the United States and most developed nations decades ago. Most people who live in rich countries assume the disease is long gone and that it doesn’t kill or paralyze children anymore. But it is still a frightening presence in a number of places around the world.
In 1988 the global community adopted the goal of ending polio altogether. At that time more than 350,000 children a year worldwide were killed or paralyzed by the disease. Since then, vaccination coverage has increased significantly and the number of cases has gone down by 99 percent, to fewer than 1,500 last year. There are now just four countries where polio transmission has never been stopped: India, Nigeria, Pakistan, and Afghanistan.
That’s incredible progress, but the last 1 percent remains a true danger. Eradication is not guaranteed. It requires campaigns to give polio vaccine to all children under 5 in poor countries, at a cost of almost $1 billion per year. We have to be aggressive about continuing these campaigns until we succeed in eradicating that last 1 percent.
Therefore, funding is critical to success. Organizations such as Rotary International and the governments of India, the United States, the United Kingdom, and Japan are all major contributors to the polio campaign. Our foundation gives about $200 million each year. But the campaign still faces a 2011-12 funding gap of $720 million. If eradication fails because of a lack of generosity on the part of donor countries it would be tragic. We are so close, but we have to finish the last leg of the journey. We need to bring the cases down to zero, maintain careful surveillance to ensure the virus is truly gone, and keep defenses up with polio vaccines until we’ve confirmed success.
Why is it so important to end polio? Eradication will have three huge benefits.
The first is that getting rid of polio will mean that no child will die or be paralyzed by the disease in the future. One thing most people don’t realize is that if we don’t finish the job on eradication, we will lose a lot of the ground we’ve gained over the past two decades. The disease will not stay at its current low level. If we don’t get rid of it, it will spread back into countries where it’s been eliminated, and it will kill and paralyze children who used to be safe. Only eradication will guarantee that all children are safe.
The second benefit is that the money that will be saved by eradicating polio far exceeds what we are spending on eradication efforts now. The long-term benefits of the last couple of billion dollars spent on eradication will be truly phenomenal. A recent estimate added up the cost of treatment that won’t be necessary and the enhanced economic contribution of adults who won’t get polio. Eradication could save the world up to $50 billion over the next 25 years.
The third benefit is that success will energize the field of global health by showing that investments in health lead to amazing victories. The eradication effort illustrates so well how a major advance in the human condition requires resolve and courageous leadership. To win these big important fights, partnerships, money, science, politics, and delivery in developing countries have to come together on a global scale.
The history of polio and polio eradication is fascinating. (One of the best books I’ve read on the subject is David Oshinsky’s Polio: An American Story.) Polio was the first disease that raised significant money from the broad public. The March of Dimes was created to combat the disease. Although President Roosevelt and lots of Hollywood stars helped the campaign, its huge success came from neighborhood-based fundraising. I remember March of Dimes volunteers ringing our doorbell when I was growing up and asking for a donation. By any measure, the public’s generosity in supporting that charity made it one of the most successful health-related fundraising campaigns ever.
The March of Dimes funded research into the first polio vaccine, which was invented by Dr. Jonas Salk and introduced in 1955. It was such an important priority to get the polio vaccine out widely that the U.S. government sponsored the campaign, which it had never done before. The campaigns of the late-1950s were wildly successful, and by 1961 the number of cases in the United States was down to just 161.
A second polio vaccine—this one in the form of liquid drops that children swallow instead of an injection in the arm—was invented by Dr. Albert Sabin and licensed in 1963. By 1979 there was no more poliovirus in circulation in the United States. Dr. Salk’s and Dr. Sabin’s vaccines are still the key tools used for eradication today.
To this day, the smallpox campaign is the only successful human disease eradication campaign in history. At its peak, smallpox killed over 2 million people every year and also blinded and disabled large numbers. The eradication campaign started in 1967, the last naturally acquired case of smallpox was in 1977, and the world was certified as being free of smallpox in 1979. (Two excellent books on the smallpox eradication are Dr. D.A. Henderson’s Smallpox: The Death of a Disease and the forthcoming House on Fire by another key smallpox warrior, Dr. Bill Foege.)
Smallpox had a number of characteristics that made it easier to eradicate than polio. Almost everyone who got smallpox developed a distinct rash. In contrast most polio infections are not noticed because less than one in 100 people infected are paralyzed, even though all those infected can transmit the virus. This means by the time a paralytic case is found, the poliovirus has probably spread.
Also, the vaccines against polio are not as effective as the smallpox vaccine, which was so powerful that a single vaccination protected almost everyone. In the case of the most common polio vaccine, at least three doses are required to get 85 percent of children fully protected. In many countries of the developing world, even more doses are needed to reach the immunity levels needed to stop transmission of the virus.
But the polio campaign also has some huge advantages that the smallpox campaign did not have. The advanced science we have today lets us sequence the DNA of the polio virus and develop an understanding of the history of transmission, which guides our work. We also have far better communications and modeling tools than were available in the 1970s, and those are being used in smart ways to respond rapidly to every outbreak.
In 2003 I would have said we were just a couple of years away from ending polio, and I would have been wrong. That year there were false rumors in Nigeria that the polio vaccine caused women to become sterile. This allowed the disease to have a resurgence and to spread to many other countries. The experience of 2003 serves as a reminder to be humble as we move forward. But humility does not mean fatalism.
Fortunately those false rumors have been almost completely eliminated through the leadership of key political and religious figures. In 2009 when I visited Northern Nigeria to meet with the most important traditional leader, the Sultan of Sokoto, he committed to the campaign. It was fantastic to see him publicly giving his support. (He also gave me a horse to thank me but I told him I couldn’t take it.)
Last year both India and Nigeria had substantially fewer cases than ever before. In India the number of cases went down from 741 in 2009 to just 41 in 2010. In Nigeria, thanks in large part to the renewed leadership in the northern part of the country, the number went down from 388 to just 18. But alongside the phenomenal progress was another reminder that gains can be lost without sustained action.
The majority of cases in 2010 were in countries that had been polio-free until the virus travelled back across borders and caused outbreaks in areas where people had gotten lax about vaccination. There was a large outbreak in Tajikistan in the first half of 2010 and another in Congo in the second half. In both regions there were a number of immunization campaigns organized as a response. Today the outbreaks appear to be under control.
What those outbreaks in formerly polio-free countries prove is that eradication is a global project requiring every country to do its part. Very few projects demand global participation. In most areas each country can pursue its own approach, and countries can compare outcomes to see which approach is the most successful.
Philosopher and historian Will Durant once observed that the only thing that could get countries to join forces would be an alien invasion. To my mind, terrible diseases are surrogates for an alien invasion. If we are to succeed, the world needs leadership from a global institution and significant, coordinated resources from rich countries to fund activities in the poorest countries.
For polio, the World Health Organization (WHO) has played the central role with Rotary International, the Centers for Disease Control, and UNICEF as key partners. Polio eradication has benefited immensely from having Rotary’s support. Rotary had the vision to get involved in 1985 and has kept polio eradication as its top priority. Everywhere I go to learn about polio, I see Rotary members helping out with the hard work.
I feel sure that with continued support we will be able to show significant progress building on this year’s work. The site www.polioeradication.org tracks the key parts of the campaign including fundraising and the latest cases. I will make a number of trips focused on polio this year, including additional trips to India and Nigeria, and will write a report for the foundation website. For anyone who wants to support the polio campaign, which would be fantastic, visit www.rotary.org/myrotary/en/take-action/end-polio.
Not Letting Up
Going the last mile in India
Eastern India's Bihar state closes in on eradicating polio.
“The last mile is when people get most fatigued,” says Dr. Hemant Shukla, who leads polio eradication efforts in eastern India’s Bihar state. But having made major strides against polio, India now is closing in on it with vaccination programs for nomadic peoples and others who are hardest to reach.
Be Prepared
Annual Letter: A health emergency
I’m willing to be seen as a troublemaker by people who are happy with the status quo on global health.
Malaria: Progress on Multiple Fronts
The fight against malaria is making very good progress. The death toll, overwhelmingly of young children in Africa, went down from 985,000 in 2000 to 781,000 in 2009. Of the 99 countries with malaria, 43 have decreased cases of the disease by more than 50 percent. Turkmenistan and Morocco were recently declared malaria-free. For these communities the reduction in both death and sickness makes a huge difference. And it is possible only because of increased donor spending, which reached $1.5 billion in 2009.
The Roll Back Malaria group, with strong support from the WHO and our foundation, has set an aggressive goal to provide bed nets to almost every household that needs them in the next few years. As coverage goes up from its current level of 42 percent, it will have a dramatic impact. In Senegal, where 80 percent of households own a bed net, the number of malaria cases went down 41 percent in a single year. Many amazing grassroots groups are helping with the delivery of bed nets. The Nothing But Nets campaign, for example, has gotten hundreds of thousands of individual citizens and organizations like the United Methodist Church and the National Basketball Association involved in the fight against malaria.
We are also working on lowering the cost of the anti-malaria drugs containing artemisinin, which are expensive enough that people are still using less effective drugs instead. The approaches range from breeding the plant that provides artemisinin to have a higher yield, to using very advanced synthetic chemistry that can make artemisinin starting with simple sugars.
As is the case with all infectious diseases, the ultimate tool against malaria would be a low cost, highly effective vaccine. The RTS,S vaccine, developed in partnership with the pharmaceutical manufacturer GSK, is in its final phase-3 trial stage. Interim data will be available later this year, and we should have final results by 2015. A number of other vaccine candidates that might be even more effective or might be combined with RTS,S are also making progress, and several will start human trials this year.
Saving the Youngest Children
Of the 8.1 million deaths per year of children under the age of 5, over 40 percent happen in the first 28 days of life, or the neonatal period. The good news is that we are headed in the right direction. In 1995 there were an estimated 5.6 million neonatal deaths. The most recent estimates show the number down to around 3.6 million.
Unlike the deaths that take place after a child is 28 days old, almost all of which can be prevented by inventing and delivering vaccines, reducing these early deaths requires a range of approaches. Some require new tools such as an ointment for the baby’s skin that prevents infection and an antibiotic solution for cleaning the cut umbilical cord. However, many of the key interventions involve social and behavioral change. You can have a huge impact (on both newborn and maternal health) by increasing the number of births done by a skilled provider in a clinic. It’s also important to teach mothers to wash their hands before handling a baby, to have frequent skin-to-skin contact with their babies, and to breastfeed exclusively for the baby’s first six months. (Mother’s milk contains not only key nutrition but also antibodies that block infection until the baby’s immune system is ready to operate on its own.) Where all of these elements come together, neonatal deaths can be reduced by 50 percent or more, so it’s critical that we learn more about how to teach and motivate mothers effectively, especially at a large scale.
Melinda has been a strong leader on maternal and child health issues. She gave an especially powerful speech last year to the Women Deliver conference. The plight of mothers and their babies is something she feels deeply, and it’s something we talk about a lot.
When she came home from a trip to Malawi she shared the experience of seeing two babies in a hospital in the town of Lilongwe, lying side-by-side in the same incubator. They were born within hours of each other. Each had suffered the same condition—they were unable to breathe at birth. Sadly, it was clear that only one would survive. That baby’s mother had made it to the donor-funded hospital in time for her delivery and was able to get the care she needed. Her baby was immediately resuscitated, which saved his life. The other was not so fortunate. He was born on the way to the clinic, on the side of road, and was not resuscitated soon enough. I wish everyone had a chance to experience what Melinda did, so they could see how things are improving but also understand the urgent need to do more.
HIV/AIDS and the Need for Leadership
Progress continues in fighting the AIDS epidemic, but the pace is slow. The rate of HIV infection has been reduced by almost 20 percent over the last 10 years, to fewer than 2.7 million infections per year. The number of people dying from AIDS has gone down by more than 20 percent in the last five years, to fewer than 2 million annually. Given all the lives that are at stake, I am impatient enough about this that I am willing to be viewed as a troublemaker by people who are happy with the status quo.
The war against AIDS is being waged on two fronts—treating those who are already infected and preventing new infections. Treatment continues to be scaled up, with more than 5 million people receiving HIV drugs. This is a great success story. Rich country generosity has been crucial and the execution in poor countries has been strong. However, there will not be enough money to treat everyone who will become infected if we don’t halt the progress of HIV. Because we don’t have a cure for AIDS, treatment has to continue for a patient’s entire life. That means costs continue to increase as you put more and more people on treatment.
Even without including people who will become infected in the future, the cost of treating the 33 million people living with AIDS today would be over $40 billion per year at current costs—over four times as much as is provided in aid today. To minimize the funding gap we need to reduce per patient costs of treatment. Drug costs have already been reduced to less than 20 percent of treatment costs. Most of the future savings will have to come from treatment models that reduce personnel, laboratory, and overhead costs. The difficulty of funding treatment makes it clear how important it is to prevent new cases. The sooner we make progress the better. There needs to be a sense of urgency that doesn’t exist yet.
Prevention breaks down into several different areas. The easiest should be preventing mother-to-child transmission since it simply involves giving a mother drugs to prevent transmission to her child. There is a lot of focus on getting from the current number of over 300,000 infections per year to zero. Another prevention approach is counseling people to change their behavior, including avoiding risky acts and using condoms. Then we have prevention approaches that rely on new tools. We now have three tools that have shown significant impact. The first is male circumcision, which I discussed last year. Amazingly, teenagers in communities with high HIV incidence show a high willingness to be circumcised. Kenya is leading the way with over 200,000 circumcisions performed. However, there are over 10 million men in high-risk settings in Africa who would benefit from male circumcision, and we should be scaling up 10 times faster than we are.
Another new tool is a vaginal microbicide gel that a woman can use to protect herself. A recent trial showed a gel containing tenofovir protected women against infection. Now the question is how long it will take before the gel is rolled out on a large scale. As someone outside the field, I am surprised at the number of steps it takes. First the product has to be licensed, which requires approvals from regulatory groups in both the country where the product will be used and donor countries. Many of these approval steps happen serially rather than in parallel, and it is only when the entire approval process is complete that the product can be rolled out. Even then the process isn’t complete because a whole system for delivering the product needs to be put together, and again a lot of these steps proceed in a slow serial fashion.
Another new prevention tool, PrEP (Pre-Exposure Prophylaxis), involves someone without HIV taking an anti-HIV drug on a regular basis to block infection. A PrEP trial showed a strong prevention benefit for the participants who consistently used the drugs and a weaker impact when all the participants were included. With both microbicides and PrEP I think countries with large epidemics should figure out how to do large community trials as soon as possible. This would shorten the time before all patients have these lifesaving tools by many years.
If the United States had an epidemic where almost half the girls in large neighborhoods contracted a terrible disease, we would find a way to cut through all the complexity. With HIV it is more difficult since there are many countries involved. But we need to work creatively to shorten these delays.
The best tool would be a vaccine for HIV. The scientific progress on this has gone well. The positive results of the trial in Thailand were a turning point for the field, and blood samples from the volunteers are being studied in depth for lessons about why that vaccine worked but only to a limited degree.
There has also been an explosion in the discovery of antibodies that block HIV infection. Scientists don’t yet know how to make a vaccine that will cause patients to generate lots of these antibodies, but there are several approaches that look promising and will be ready to go to trials in the next few years.
In order to get a fully effective HIV vaccine we will almost certainly need several rounds of trials where we learn and improve the candidate vaccines. So to get a vaccine as soon as possible we need to minimize the length of the trials and the time between trials. So far each cycle has taken over five years. The field needs to look into how to shorten this so that progress matches the urgency of the problem.
An Encouraging Visit
Nigeria advances the fight against polio
In a visit to Africa’s most populous nation, I witnessed remarkable progress against polio, with lessons for the fight against infectious diseases worldwide.
With continued hard work and investment the world is on a path toward something pretty incredible, the eradication of polio. In the past two decades, polio cases around the world have been reduced by 99 percent. If we can get rid of the last 1 percent, polio will become the second major infectious disease, after smallpox, that has ever been completely eliminated. There are still gaps in funding for polio eradication, and new outbreaks could reverse some of the progress made so far. But if polio is eliminated, never again will a child be crippled by this terrible virus.
We have a chance to get there because of some great efforts, particularly by the Global Polio Eradication Initiative, which involves the World Health Organization, Rotary International, the US Centers for Disease Control and Prevention (CDC) and the United Nations Children's Fund (UNICEF). The Gates Foundation is very involved in supporting polio immunization campaigns and other efforts to educate parents and communities about the importance of immunization. We’re also supporting work to improve polio surveillance and to develop better vaccines and anti-poliovirus drugs.
Northern India and northern Nigeria are two areas where polio continues to be a problem. I visited northern India in May this year to see the progress there. I was very excited to visit northern Nigeria in June, because the progress there since my last visit in February 2009 has been especially impressive. As of July 14th, only five cases due to wild polio viruses were reported in Nigeria this year, versus hundreds last year.
I spent most of my first day in Kano, one of the northern states most vulnerable to polio. I met with community leaders, visited a local health center and stopped in at an informal school where students study the Koran in Arabic. On the streets and most everywhere else we went, I noticed so many young children around. Nigeria has more people by far than any other African country, and more than 40 percent of them are under the age of 15. That makes polio immunization a big challenge. Kano had just begun a campaign to immunize more than 6 million children under the age of five.
Part of the challenge is overcoming fear and suspicion. In Kano in the past, false rumors linked immunization to sterility and HIV. Community leaders told me that because polio vaccine is free and brought to people in their homes, some people think there must be something wrong with it. Community leaders play a critically important role in helping to overcome mistrust, and a big focus of anti-polio efforts is on informing these leaders and enlisting their support.
Another ironic thing I noticed was that because polio cases have been dramatically reduced, it’s more difficult to know whether local immunization campaigns are reaching everyone they need to reach, particularly sub-populations that may be more at risk. Without many actual cases, you have to rely on other ways of monitoring immunization rates, and the different measures are sometimes quite inconsistent. I think we need to look at how to help get more reliable data to guide our efforts and ensure they’re effective.
Also of concern is the risk that progress against polio in Kano might be undermined by the virus filtering back in from neighboring countries and other parts of northern Nigeria. Increasingly, the problem needs to be approached on a regional basis.
The school we visited was very interesting. It didn’t really look like a school. There were no classrooms, just children sitting on the street, against a wall or under a tree, holding slates with Arabic script written on them. I asked one of the boys to recite the lesson from his slate, and he did.
That night in Abuja, the Nigerian capital, I had dinner with government officials including the Minister of Health, Onyebuchi Chukwu. It was interesting to learn about some of the creative approaches being used to inform Nigerians about the importance of immunization. Pro-immunization messages are being embedded in the plotlines of popular TV entertainment programs, for example. One of Nigeria’s largest mobile phone service providers has agreed to send out about 25 million free text messages on polio and health.
The next day I had a number of meetings including a session with several state governors and one with Nigeria’s new President, Goodluck Jonathan. Commitment from Nigeria’s leaders has been crucial in advancing the nation’s fight against polio.
A recurring theme I picked up from the people I talked to was the importance of using what we’ve learned and accomplished in the drive against polio to fight other illnesses such as infant diarrhea, respiratory ailments and malaria. I do believe that polio eradication helps strengthen routine immunization, which has the potential to save the lives of large numbers of children.
Wherever I go, I always find that saving children’s lives is a universal concern. I was very impressed with Nigeria’s progress against polio. I tried to encourage everyone to not let up.
How to Help
We need productivity and sustainability
Helping poor farmers improve productivity is a critical step in reducing global hunger. But there is an ideological divide over how best to help them. The truth is that both sides have something important to offer.
While the World Summit on Food Security in Rome in November did not achieve all it should, it shined a welcome spotlight on small farmers who make up the vast majority of hungry and poor people in the world. Coming on the heels of a commitment by the G20 to invest $22 billion in developing-country agriculture, the summit provided reason to be optimistic that after decades of neglect, we’ll start investing in the single best strategy to reduce global hunger and poverty.
At the same time, I am worried that as momentum builds behind agricultural development as a long-term alternative to food aid, a growing ideological divide may cause the world to squander a real opportunity to fight hunger and poverty.
The global movement to help small farmers is increasingly divided into two camps. On one side is a technological approach focused on improving productivity. On the other side is an environmental approach that promotes sustainability. Productivity or sustainability – they say you have to choose.
A recent Time Magazine article “Different Shades of Green in Africa,”for example, pits the idea of organic development to help African farmers against the heavy input approach being promoted by the Alliance for a Green Revolution in African (AGRA) and the Bill & Melinda Gates Foundation, calling it “a battle between two very different agricultural philosophies.”
As I said during my speech at the World Food Prize in October, this is a false choice that is dangerous for the field of agricultural development.
At a time of rising population and climate change, we need both organic solutions that promote sustainability and the technological approaches that increase productivity—and there is no reason we can’t have them both.
Many environmental advocates highlight the excesses of the original Green Revolution. They have a point. The Green Revolution increased yields dramatically in many poor countries in the second half of the 20th century, but it also led to over-irrigation and over-fertilization. The next Green Revolution has to be greener than the first.
Some have tried to restrict the spread of biotechnology regardless of its potential to increase productivity. They act as if there is no emergency, even though there are already 1 billion hungry people in the world, and climate change is going to make conditions harsher in the future. The Food and Agriculture Organization estimates that developing countries will have to boost their yields by half to meet the challenge of global hunger. We simply won’t be able to meet that goal without using all the scientific tools at our disposal.
Of course, new technologies must be proven safe for farmers, consumers, and the environment before they’re adopted. That’s why countries should have a strong regulatory infrastructure guided by experts with access to the latest science-based information.
I have seen proof that agricultural science can make people’s lives better. This summer, I attended a roundtable discussion in New Delhi with scientists who developed a new variety of rice called Swarna-sub1. The amazing thing about Swarna-sub1 is that it can survive underwater for more than two weeks, which means it could revolutionize life for millions of farmers in flood-prone areas of India. The researchers used a fascinating technique called marker assisted selection to introduce a single allele, a version of a gene, into an existing rice variety to make it flood tolerant.
I also met with representatives from local NGOs, seed companies, and the government of India to talk about their plans for delivering new seeds to farmers. The government’s goal is to have more than 5 million hectares planted with Swarna-sub1 in just five years.
The tendentious debate pitting productivity against sustainability doesn’t just threaten important scientific advances. It also obscures another crucial lesson from the first Green Revolution: that developing more productive seeds is just one element of an effective strategy. In addition to new seeds, farmers also need training, access to new markets, and organizations to represent their interests. Governments need better data so they can devise sound agricultural policies. By placing so much emphasis on just one link in a very long agricultural value chain, we distract ourselves from a goal we can all agree on: helping small farmers and their families.
Success requires progress on many fronts. African countries must lead the way by spending more on agriculture. Donor countries must do a better job of listening so they can understand what poor countries really need. They should explain more clearly how the money they’re pledging will be spent. I am optimistic that these obstacles can be cleared away and that the world can tap into the opportunity offered by agricultural development. That’s why the Bill & Melinda Gates Foundation has committed more than $1.4 billion to initiatives that support small farmers.
However, if the field doesn’t move past this counterproductive debate, hungry and poor people will suffer. We have a choice: We can let our disagreements get in the way of real progress, or we can agree to help more than a billion people live healthier, happier lives.


